Vasculitis
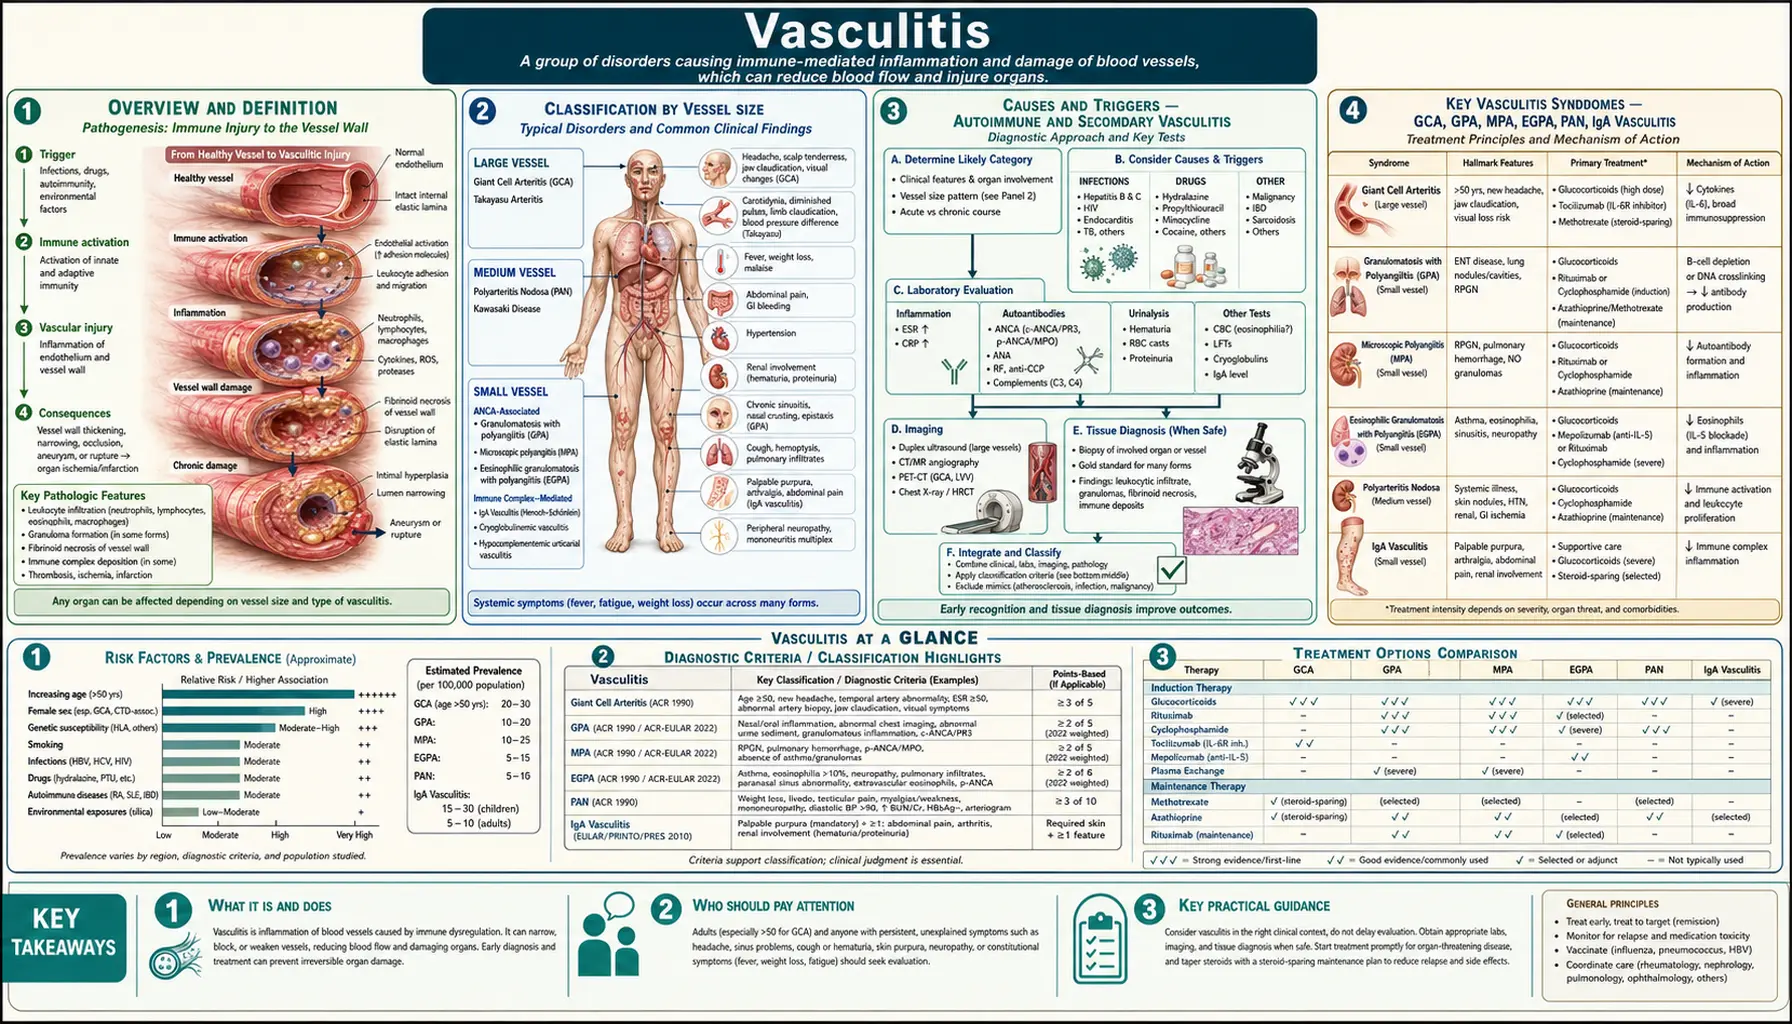
Table of Contents
- Overview and Definition
- Classification by Vessel Size
- Causes and Triggers — Autoimmune and Secondary Vasculitis
- Key Vasculitis Syndromes — GCA, GPA, MPA, EGPA, PAN, IgA Vasculitis
- Symptoms and Organ Involvement
- Diagnosis — Biopsy, ANCA Testing, Imaging
- Treatment — Corticosteroids, Immunosuppressants, Biologics
- Natural and Nutritional Approaches
- Disease Course and Prognosis
- Complications and Organ Damage
- Prevention and Monitoring
- Key Research Papers
- Connections
- Featured Videos
Overview and Definition
Vasculitis is a group of disorders characterized by inflammation of blood vessel walls — arteries, veins, or capillaries. When vessel walls become inflamed, they can thicken, weaken, narrow, or scar, restricting blood flow to tissues and organs. The result ranges from mild skin rashes to life-threatening organ failure, depending on which vessels are involved and how aggressively the disease progresses.
Vasculitis is not a single disease but a family of distinct conditions, named and grouped in the 2012 revised Chapel Hill Consensus Conference nomenclature by the size of vessel affected (Jennette 2013), and further separated by the presence or absence of specific antibodies (particularly ANCA — antineutrophil cytoplasmic antibodies) and the pattern of organ involvement. Some forms are primary (driven by the immune system attacking vessels directly), while others are secondary to infections, medications, malignancy, or other autoimmune diseases such as lupus or rheumatoid arthritis.
How common each form is depends strongly on age, ancestry and region. A 2022 review of global epidemiology describes Giant Cell Arteritis (GCA) as a disease of people aged 50 and over, mainly of northern European ancestry; Takayasu arteritis as occurring mainly in people under 40; Kawasaki disease as occurring mainly in children under 5 and most commonly in children of Asian ancestry; and IgA Vasculitis (Henoch-Schönlein Purpura) as a disease of children and adolescents. The ANCA-associated forms are much less common than GCA and become more frequent with age (Watts 2022). A 2022 meta-analysis of 25 studies estimated a worldwide pooled incidence of ANCA-associated vasculitis of 17.2 per million person-years and a pooled prevalence of 198.0 per million people (GPA 96.8, MPA 39.2 and EGPA 15.6 per million), higher in the northern hemisphere and rising over time (Redondo-Rodriguez 2022).
Speed of diagnosis matters in several forms: GCA can cause permanent vision loss, and the glomerulonephritis of ANCA-associated vasculitis can progress to kidney failure within weeks. Symptom clusters that raise the question of vasculitis include unexplained fever with weight loss, rash, blood in the urine (hematuria), coughing blood (hemoptysis), destructive sinus disease, or new-onset headache in an older adult.
Classification by Vessel Size
The 2012 revised Chapel Hill Consensus Conference (CHCC) Nomenclature provides the internationally accepted framework for naming vasculitis by the predominant vessel size affected (Jennette 2013). The categories below follow that framework.
Large Vessel Vasculitis
Involves the aorta and its major branches. The two primary forms are:
- Giant Cell Arteritis (GCA / Temporal Arteritis): A large-vessel vasculitis of people aged 50 and over (Watts 2022). Involves the cranial branches of the aorta (temporal, ophthalmic, posterior ciliary arteries) and the aorta itself. Hallmark: granulomatous inflammation, often with multinucleated giant cells. In a population-based cohort of 245 patients in Olmsted County, Minnesota, 8.2% had permanent vision loss from GCA, most of it (85%) from arteritic anterior ischemic optic neuropathy (Chen 2016).
- Takayasu Arteritis: A granulomatous vasculitis of the aorta and its major branches, occurring mainly in people under 40 (Watts 2022), predominantly young women and more often reported in Asia. Causes stenosis, occlusion, or aneurysm of the subclavian, carotid, renal, and mesenteric arteries. Presents with limb claudication, absent pulses, and hypertension from renal artery involvement.
Medium Vessel Vasculitis
Involves the main visceral arteries and their branches, including renal, hepatic, coronary, and mesenteric arteries.
- Polyarteritis Nodosa (PAN): Necrotizing arteritis of medium and small arteries without glomerulonephritis or capillaritis. Hepatitis B infection is a recognized cause; in a French series the frequency of hepatitis B-associated PAN fell with improved blood safety and vaccination (Guillevin 2005). Presents with fever, weight loss, livedo reticularis, mononeuritis multiplex, and renal infarction (hypertension but not glomerulonephritis, distinguishing it from ANCA vasculitis).
- Kawasaki Disease: Occurs mainly in children under 5 (Watts 2022). Necrotizing arteritis involving the coronary arteries, with risk of coronary artery aneurysm. Presents with prolonged fever, rash, conjunctivitis, strawberry tongue, and desquamation of the fingertips. Standard treatment is intravenous immunoglobulin (IVIG) and aspirin.
Small Vessel Vasculitis — ANCA-Associated
These three forms are grouped together by their association with antineutrophil cytoplasmic antibodies (ANCA) and their tendency to cause necrotizing inflammation of small vessels, particularly glomerulonephritis and pulmonary capillaritis.
- Granulomatosis with Polyangiitis (GPA, formerly Wegener's Granulomatosis): Granulomatous inflammation of the upper and lower respiratory tracts plus necrotizing glomerulonephritis. Associated mainly with PR3-ANCA (c-ANCA), found in most patients with active generalized disease. Classic triad: destructive sinusitis/ear disease, pulmonary infiltrates or nodules, and renal involvement.
- Microscopic Polyangiitis (MPA): Necrotizing vasculitis without granulomatous inflammation. Associated mainly with MPO-ANCA (p-ANCA): in a French cohort of 85 patients, ANCA were found in 38 of 51 patients tested, with anti-MPO in 31 and anti-PR3 in 4 (Guillevin 1999). Causes rapidly progressive glomerulonephritis and pulmonary hemorrhage (pulmonary-renal syndrome), but lacks the upper respiratory tract destruction seen in GPA.
- Eosinophilic Granulomatosis with Polyangiitis (EGPA, formerly Churg-Strauss Syndrome): Granulomatous inflammation rich in eosinophils, typically in the setting of asthma and blood eosinophilia. In a French cohort of 383 patients, 91.1% had asthma and 31.0% of the 348 tested at diagnosis were ANCA-positive; peripheral neuropathy (51.4%), ear, nose and throat signs (48.0%), skin lesions (39.7%) and cardiomyopathy (16.4%) were among the main manifestations (Comarmond 2013).
Small Vessel Vasculitis — Immune Complex-Mediated
- IgA Vasculitis (Henoch-Schönlein Purpura, HSP): IgA immune complex deposition in small vessel walls. A vasculitis of children and adolescents (Watts 2022) that often follows an upper respiratory infection. Tetrad: palpable purpura (buttocks/legs), arthritis, abdominal pain, and renal involvement (IgA nephropathy pattern).
- Cryoglobulinemic Vasculitis: Caused by immune complexes containing cryoglobulins (immunoglobulins that precipitate in cold). Mixed cryoglobulinemia is strongly associated with hepatitis C infection. Presents with purpura, weakness, arthralgias, and peripheral neuropathy. Treatment of the underlying hepatitis C infection is central to management.
- Hypersensitivity Vasculitis (Leukocytoclastic Vasculitis): Follows exposure to drugs, infections, or food antigens; predominantly skin-limited; often resolves once the trigger is removed.
Causes and Triggers — Autoimmune and Secondary Vasculitis
The causes of vasculitis are incompletely understood but involve a convergence of genetic susceptibility, immune dysregulation, and environmental or infectious triggers that break normal vascular tolerance.
Primary (Idiopathic) Autoimmune Mechanisms
In ANCA-associated vasculitis, the current model holds that primed neutrophils express PR3 or MPO on their surface. ANCA antibodies bind these antigens, activating the neutrophils to release toxic granule contents and reactive oxygen species directly into vessel walls. This neutrophil-endothelial interaction drives the necrotizing inflammation that destroys capillary walls. Why ANCA develop in the first place remains unclear; genetic factors (see below), silica dust exposure (Gómez-Puerta 2013) and chronic nasal carriage of Staphylococcus aureus, which was linked to relapse in a Dutch cohort (Stegeman 1994), are among the factors studied.
In GCA, activated CD4+ T cells infiltrate the arterial wall, differentiating into Th1 and Th17 subsets. Interleukin-6 (IL-6) is a key cytokine driver — the rationale for tocilizumab, an IL-6 receptor blocker that was superior to placebo in the GiACTA trial (Stone 2017). Dendritic cells in the adventitia act as the initial antigen-presenting sentinels, though the triggering antigen has not been identified.
Infectious Triggers
- Hepatitis B: Immune-complex deposition is the proposed mechanism of hepatitis B-associated Polyarteritis Nodosa. In a French series of 115 patients, relapses were rare and did not occur once viral replication had stopped and seroconversion was obtained (Guillevin 2005).
- Hepatitis C: Drives mixed cryoglobulinemia and its associated vasculitis; direct-acting antivirals are used to treat the underlying infection.
- Upper respiratory infections, including streptococcal infections: Often precede IgA Vasculitis (HSP) in children.
- Staphylococcus aureus: In a Dutch cohort of 57 patients with GPA, chronic nasal carriers had a higher relapse risk (adjusted relative risk 7.16); the authors suggested a role for S. aureus in the disease's pathophysiology (Stegeman 1994). The mechanism is not established.
- HIV, CMV, Parvovirus B19: Associated with secondary vasculitis presentations.
Drug-Induced Vasculitis
Several drugs and drug contaminants are associated with ANCA-positive vasculitis, most notably propylthiouracil, hydralazine, minocycline and levamisole-adulterated cocaine. Drug-associated ANCA vasculitis can produce both MPO and PR3 antibodies at once — a pattern rare in primary disease — and often remits after the drug is withdrawn, though immunosuppression is sometimes used for severe organ involvement.
Malignancy-Associated Vasculitis
Lymphomas and solid tumors can provoke paraneoplastic vasculitis. Hairy cell leukemia is classically associated with PAN-like presentations. An underlying malignancy is sometimes looked for in older adults with newly diagnosed vasculitis, especially when constitutional symptoms are prominent.
Genetic and Environmental Risk Factors
A genome-wide association study of 1,233 UK patients with ANCA-associated vasculitis, replicated in 1,454 Northern European patients, found that the strongest genetic associations were with ANCA specificity rather than with the clinical syndrome: anti-PR3 ANCA with HLA-DP and the genes for α1-antitrypsin (SERPINA1) and proteinase 3 (PRTN3), and anti-MPO ANCA with HLA-DQ (Lyons 2012). In a meta-analysis of six case-control studies, ever-exposure to silica was associated with ANCA-associated vasculitis (summary odds ratio 2.56; 3.56 in studies of GPA only and 3.95 in studies of MPA only) (Gómez-Puerta 2013). GCA mainly affects people of northern European ancestry (Watts 2022), which suggests genetic and possibly shared environmental factors.
Key Vasculitis Syndromes — GCA, GPA, MPA, EGPA, PAN, IgA Vasculitis
Giant Cell Arteritis (GCA)
GCA is treated as an ophthalmologic emergency. The typical patient is an older woman of northern European descent presenting with new-onset severe temporal headache, scalp tenderness, jaw claudication (pain with chewing), and systemic symptoms (fever, night sweats, weight loss). Erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP) are usually elevated. Temporal artery biopsy showing granulomatous inflammation confirms the diagnosis, but it is not always positive: in a meta-analysis of 32 studies (3,092 patients), 77.3% of GCA cases were biopsy-positive, with large differences between studies that the authors attribute partly to differences in biopsy sampling, processing or interpretation (Rubenstein 2020). Skip lesions are one reason; a clinical diagnosis is made in some biopsy-negative patients. Large-vessel involvement of the aorta can lead to aortic aneurysm years after the cranial disease settles. In the GiACTA trial of 251 patients, sustained glucocorticoid-free remission at week 52 occurred in 56% of patients given weekly subcutaneous tocilizumab (162 mg) with a 26-week prednisone taper, versus 14% with placebo and a 26-week prednisone taper (Stone 2017).
Granulomatosis with Polyangiitis (GPA)
GPA classically destroys the upper respiratory tract — causing chronic sinusitis that fails antibiotics, bloody nasal discharge, nasal septal perforation, and the characteristic saddle-nose deformity from cartilage collapse. Subglottic stenosis can develop insidiously. Pulmonary involvement causes hemoptysis, cavitating nodules, and diffuse alveolar hemorrhage. Renal involvement (rapidly progressive glomerulonephritis with red cell casts) can progress to dialysis-dependent kidney failure within weeks. Orbital pseudotumor causes proptosis. PR3-ANCA (c-ANCA pattern) is positive in most patients with active generalized GPA; its value as a marker of disease activity is limited (see ANCA Testing under Diagnosis).
Microscopic Polyangiitis (MPA)
MPA lacks the granulomatous tissue destruction of GPA, presenting primarily as a pulmonary-renal syndrome. Rapidly progressive glomerulonephritis often dominates. MPO-ANCA (p-ANCA) is the predominant antibody (see Classification above). Pulmonary capillaritis causing diffuse alveolar hemorrhage is life-threatening; in the PEXIVAS trial, adding plasma exchange to immunosuppression did not reduce death or end-stage kidney disease in severe ANCA-associated vasculitis (Walsh 2020) (see Plasma Exchange under Treatment). In the CYCAZAREM maintenance trial, relapse was less frequent in MPA than in GPA (Jayne 2003). The 2022 EULAR update recommends high-dose glucocorticoids with either rituximab or cyclophosphamide for organ- or life-threatening disease (Hellmich 2024).
Eosinophilic GPA (EGPA / Churg-Strauss)
EGPA unfolds in three phases: a prodromal phase with allergic rhinitis and asthma (which may precede vasculitis by years or decades), an eosinophilic phase (blood eosinophilia, eosinophilic pneumonia, eosinophilic gastroenteritis), and the vasculitic phase. Mononeuritis multiplex — sudden foot drop or wrist drop from ischemic nerve infarction — is a classic presentation. In the French cohort of 383 patients, cardiomyopathy was an independent risk factor for death; the ANCA-positive patients had more ear, nose and throat, peripheral nerve and kidney involvement but less cardiac involvement than the ANCA-negative patients, relapsed more often (35.2% versus 22.5%) and died less often (5.6% versus 12.5%) (Comarmond 2013). Mepolizumab (anti–IL-5) is approved in the US for adults with EGPA (see Treatment).
Polyarteritis Nodosa (PAN)
PAN is distinguished from ANCA-associated vasculitis by: absence of ANCA, absence of glomerulonephritis (though renal artery involvement causes hypertension and infarction), and absence of pulmonary capillaritis. Classic presentation includes fever, weight loss, abdominal pain from mesenteric ischemia, livedo reticularis, testicular pain/tenderness, and mononeuritis multiplex. Angiography (CT or conventional) showing beaded medium-vessel aneurysms is highly suggestive. Hepatitis B testing is part of the work-up, because hepatitis B-associated PAN is treated differently: in the French series, since 1983 treatment combined 2 weeks of glucocorticoids followed by an antiviral drug with plasma exchanges (Guillevin 2005), rather than long-term immunosuppression.
IgA Vasculitis (Henoch-Schönlein Purpura)
A vasculitis mainly of children and adolescents (Watts 2022), which often follows an upper respiratory infection. The cardinal tetrad: (1) palpable purpura on the buttocks and lower extremities (gravity-dependent distribution); (2) arthritis or arthralgias of ankles and knees; (3) colicky abdominal pain, sometimes with intussusception or GI bleeding; (4) renal involvement (hematuria, proteinuria), which may progress to chronic kidney disease in a minority. Most children recover fully; renal involvement is the main determinant of long-term prognosis. Adults with IgA vasculitis have higher rates of severe renal disease. The EULAR/PRINTO/PReS (Ankara 2008) criteria, validated in children, classify IgA vasculitis by purpura or petechiae with lower-limb predominance (mandatory) plus one of four criteria: abdominal pain, histopathology showing IgA deposition, arthritis or arthralgia, or renal involvement (Ozen 2010).
Symptoms and Organ Involvement
Vasculitis can affect virtually any organ. Symptoms vary dramatically by form and vessel size, but constitutional symptoms — unexplained fever, fatigue, weight loss, and night sweats — are common in systemic vasculitis and often the first clue before organ-specific findings emerge. In the French MPA cohort, for example, weight loss was present in 72.9% and fever in 55.3% (Guillevin 1999).
Skin
Palpable purpura (non-blanching, raised red-purple spots representing leaking blood from inflamed capillaries) is the hallmark of small-vessel vasculitis. Livedo reticularis — a mottled, net-like discoloration from interrupted dermal blood flow — suggests medium-vessel disease (such as PAN) or secondary vasculitis. Skin ulcers from digital artery occlusion, urticaria, nodules, and necrotic plaques also occur. Skin biopsy showing leukocytoclasia (neutrophil nuclear fragmentation around inflamed vessels) confirms small-vessel vasculitis histologically.
Kidneys
Glomerulonephritis is a defining feature of ANCA-associated vasculitis. Microscopic hematuria with red cell casts on urinalysis is the key finding. Proteinuria may be nephrotic range. Rising creatinine signals rapidly progressive GN, which is treated as an emergency, usually with urgent kidney biopsy. Renal biopsy showing pauci-immune crescentic GN (few immune deposits, crescentic destruction of glomeruli) is the pathological hallmark of ANCA vasculitis.
Lungs
Pulmonary capillaritis causes diffuse alveolar hemorrhage (DAH) — the most feared acute complication. Patients present with hemoptysis, falling hemoglobin, and bilateral infiltrates on imaging. Bronchoalveolar lavage returning progressively bloodier fluid confirms DAH. Pulmonary nodules in GPA can cavitate and mimic malignancy or fungal infection. Asthma is present in nearly all patients with EGPA (91.1% in the French cohort; Comarmond 2013). Subglottic stenosis in GPA is treated by dilation in some patients.
Nervous System
Mononeuritis multiplex — asymmetric sensorimotor deficits in the distribution of individual named peripheral nerves — results from vasculitis of the vasa nervorum feeding the nerves. Foot drop (peroneal nerve) and wrist drop (radial nerve) are classic. Cranial nerve palsies, optic neuritis, and cerebral vasculitis (headache, stroke-like episodes) occur in PAN, GCA, and CNS vasculitis. GCA-related vision loss is due to ischemia of the optic nerve or retina and rarely recovers once established (Chen 2016).
Eyes
In GCA, visual symptoms — transient monocular vision loss (amaurosis fugax), diplopia from cranial nerve palsy, or sudden permanent vision loss — are treated as a medical emergency, usually with immediate high-dose glucocorticoids, often intravenous methylprednisolone. Scleritis and uveitis occur in GPA, relapsing polychondritis, and Behçet disease. Orbital pseudotumor (proptosis from granulomatous orbital inflammation) is characteristic of GPA.
Joints and Muscles
Arthralgias and myalgias are common across all forms. Polymyalgia rheumatica (PMR) — shoulder and hip girdle aching and stiffness — often coexists with GCA. PMR without vasculitis is treated with lower glucocorticoid doses than GCA. Synovitis resembling rheumatoid arthritis occurs in EGPA and IgA vasculitis.
Gastrointestinal Tract
Abdominal pain from mesenteric vasculitis mimics an acute abdomen. Intestinal infarction and perforation are life-threatening complications of PAN and other medium-vessel forms; gastrointestinal involvement was the major cause of death in the French hepatitis B-associated PAN series (Guillevin 2005). GI bleeding occurs in IgA vasculitis. Intussusception in children with IgA vasculitis is a surgical emergency.
Diagnosis — Biopsy, ANCA Testing, Imaging
No single test diagnoses all forms of vasculitis. Diagnosis requires integration of clinical presentation, laboratory data, imaging, and histopathology. The urgency of pursuing tissue diagnosis is balanced against the need to start empiric treatment in life-threatening presentations (GCA threatening vision, DAH, rapidly progressive GN).
Laboratory Testing
An initial work-up commonly includes: CBC (eosinophilia in EGPA; anemia of inflammation across forms), metabolic panel and urinalysis with microscopy (creatinine, red cell casts), ESR and CRP (nonspecifically elevated; very high ESR typical of GCA), LFTs and hepatitis serology, complement levels (low C3/C4 in cryoglobulinemia, lupus vasculitis), and ANCA testing.
ANCA Testing: Two antigens and two immunofluorescence patterns are clinically important:
- PR3-ANCA (c-ANCA — cytoplasmic pattern): Highly specific for GPA and found in most patients with active generalized disease. Its value as a disease-activity marker is limited: in a prospective study of 156 patients with GPA (Finkielman 2007), changes in PR3-ANCA levels explained less than 10% of the variation in disease activity and increases were not associated with relapse; the authors concluded that ANCA levels cannot be used to guide immunosuppressive therapy.
- MPO-ANCA (p-ANCA — perinuclear pattern): The predominant ANCA in MPA (anti-MPO in 31 of the 38 ANCA-positive patients in a French cohort; Guillevin 1999); ANCA of either type were found in 31.0% of patients with EGPA tested in another French cohort (Comarmond 2013); also seen in drug-induced vasculitis. A positive p-ANCA pattern also occurs in non-vasculitic conditions (IBD, endocarditis), so results are read together with the clinical picture.
Additional antibodies: ANA and anti-dsDNA (lupus), anti-GBM antibodies (Goodpasture's syndrome — distinct from but can mimic or coexist with ANCA vasculitis; McAdoo 2017), cryoglobulins and hepatitis serology (cryoglobulinemic vasculitis), and IgA levels (sometimes raised in IgA vasculitis).
Biopsy
- Temporal artery biopsy: The long-established reference test for GCA; because of skip lesions, a longer segment raises the yield. Glucocorticoids are commonly started before the biopsy when GCA is suspected, because of the risk to vision.
- Renal biopsy: Used to characterize glomerulonephritis (pauci-immune crescentic GN = ANCA vasculitis; IgA deposits = IgA nephropathy/IgA vasculitis; full-house deposits = lupus nephritis).
- Skin biopsy: Direct immunofluorescence showing IgA deposits in vessel walls is diagnostic of IgA vasculitis. Leukocytoclastic vasculitis on H&E confirms small-vessel inflammation.
- Lung/sinus/nerve biopsy: Granulomatous necrotizing inflammation confirms GPA. Nerve biopsy showing axonal loss with necrotizing vasculitis of epineural vessels confirms mononeuritis multiplex.
Imaging
CT Angiography and MR Angiography: Show large-vessel wall thickening (GCA, Takayasu), luminal stenosis, occlusion, or aneurysm (PAN). Aortic PET-CT can detect metabolically active large-vessel inflammation in GCA/Takayasu even when conventional angiography is normal.
High-Resolution Ultrasound: Temporal artery ultrasound can show the "halo sign" (hypoechoic thickening of the vessel wall). The 2023 EULAR imaging update recommends ultrasound as the first-line imaging test in all patients with suspected GCA, with the axillary arteries included in the standard examination; FDG-PET or MRI are alternatives, and MRI is the preferred modality for Takayasu arteritis (Dejaco 2024).
Chest CT: Defines pulmonary nodules, cavities, ground-glass hemorrhage, and subglottic stenosis in GPA/MPA/EGPA.
Birmingham Vasculitis Activity Score (BVAS): A multisystem clinical score of disease activity widely used in therapeutic studies of systemic vasculitis; version 3 reduced the number of items from 66 to 56 and was validated in 313 patients (Mukhtyar 2009).
Classification Criteria
The 2022 ACR/EULAR classification criteria for GPA and MPA are points-based scores applied, after mimics are excluded, to patients already diagnosed with small- or medium-vessel vasculitis. In validation the GPA criteria had 93% sensitivity and 94% specificity (Robson 2022) and the MPA criteria 91% and 94% (Suppiah 2022). They are validated for research classification, not as diagnostic criteria for individual patients.
Treatment — Corticosteroids, Immunosuppressants, Biologics
Treatment goals are to induce remission rapidly, prevent organ damage, maintain remission with the lowest possible drug exposure, and manage treatment toxicity. The approach is stratified by disease severity (localized, generalized, severe/organ-threatening, immediately life-threatening) and by vasculitis type. The doses below are those used in the trials named, not instructions; decisions about treatment belong with a clinician.
Remission Induction
Corticosteroids are the cornerstone of initial treatment across most forms, usually started at high dose; intravenous methylprednisolone pulses are commonly used for immediately life-threatening presentations (DAH, severe rapidly progressive GN, threatened vision in GCA). For ANCA-associated vasculitis, the 2022 EULAR update recommends tapering to a target of 5 mg prednisolone equivalent per day within 4–5 months (Hellmich 2024), and in PEXIVAS a reduced-dose oral glucocorticoid regimen was non-inferior to a standard-dose regimen for death or end-stage kidney disease, with fewer serious infections at 1 year (Walsh 2020).
Cyclophosphamide — either IV pulse or daily oral — was the standard induction partner for corticosteroids in severe ANCA vasculitis for decades. In the CYCLOPS trial of 149 patients with generalized ANCA-associated vasculitis and kidney involvement, pulse cyclophosphamide (15 mg/kg every 2–3 weeks) and daily oral cyclophosphamide (2 mg/kg/day) produced similar remission rates at 9 months (88.1% versus 87.7%), with a lower cumulative dose in the pulse group (de Groot 2009). The 2022 EULAR update recommends high-dose glucocorticoids with either rituximab or cyclophosphamide for organ- or life-threatening disease (Hellmich 2024). Major toxicities: hemorrhagic cystitis, bladder cancer (linked to higher cumulative dose; Talar-Williams 1996), gonadal failure, myelosuppression, and infection. Mesna and hydration are used to reduce bladder toxicity, and regimens aim to keep the cumulative dose low.
Rituximab (anti-CD20, depletes B cells): in the RAVE trial of 197 ANCA-positive patients with GPA or MPA (NEJM 2010, PubMed PMID: 20647199), rituximab (375 mg/m² weekly for 4 weeks) was non-inferior to daily oral cyclophosphamide (2 mg/kg/day): 64% versus 53% reached remission without prednisone at 6 months. In relapsing disease rituximab did better (67% versus 42%), and adverse-event rates did not differ significantly (Stone 2010). The 2021 ACR/Vasculitis Foundation guideline recommends rituximab for remission induction and maintenance in severe GPA and MPA (all its recommendations are conditional) (Chung 2021). Cyclophosphamide's toxicity to the ovaries and testes is one reason rituximab is often discussed for people who may want children.
Plasma Exchange (PLEX/Plasmapheresis): Previously used widely for severe ANCA vasculitis with advanced renal failure. The PEXIVAS trial (NEJM 2020) randomized patients with severe ANCA-associated vasculitis (eGFR below 50 mL/min/1.73 m² or diffuse pulmonary hemorrhage) to plasma exchange (seven exchanges within 14 days) or none, and followed them for up to 7 years: death from any cause or end-stage kidney disease occurred in 100 of 352 patients (28.4%) with plasma exchange and 109 of 352 (31.0%) without it (hazard ratio 0.86, not statistically significant) — plasma exchange did not reduce death or ESKD (Walsh 2020). The 2022 EULAR update states that plasma exchange may be considered in patients with rapidly progressive glomerulonephritis (Hellmich 2024). For patients double-positive for ANCA and anti-GBM antibodies, the authors of a European cohort describe aggressive early treatment of the anti-GBM disease (McAdoo 2017).
Remission Maintenance
After induction (typically 3–6 months), maintenance therapy switches to lower-toxicity regimens:
- Azathioprine — in the CYCAZAREM trial, switching to azathioprine (2 mg/kg/day) after remission did not increase relapse compared with continued cyclophosphamide (15.5% versus 13.7% over 18 months) (Jayne 2003). TPMT enzyme activity is commonly tested before starting, because low activity raises the risk of bone-marrow toxicity.
- Methotrexate — the 2022 EULAR update lists azathioprine and methotrexate as alternatives to biologics for maintenance (Hellmich 2024). Methotrexate is cleared by the kidneys, which limits its use when kidney function is reduced.
- Rituximab maintenance — in the MAINRITSAN trial of 115 patients in complete remission after cyclophosphamide (87 with GPA, 23 with MPA, 5 with renal-limited disease), rituximab 500 mg on days 0 and 14 and at months 6, 12 and 18 was compared with daily azathioprine; major relapse by month 28 occurred in 5% on rituximab versus 29% on azathioprine, with similar rates of severe adverse events (Guillevin 2014). The 2021 ACR and 2022 EULAR guidance both recommend rituximab for maintenance (Chung 2021; Hellmich 2024).
- Mycophenolate mofetil (MMF) — in the IMPROVE trial of 156 patients, relapses were more common with mycophenolate mofetil (42 of 76) than with azathioprine (30 of 80) (hazard ratio 1.69), with similar severe adverse-event rates; the authors concluded it was less effective for maintaining remission (Hiemstra 2010).
- Avacopan (CCX168) — an oral selective complement C5a receptor antagonist approved by the US FDA in October 2021 as an adjunctive treatment for adults with severe active ANCA-associated vasculitis (GPA and MPA), in combination with standard therapy including glucocorticoids. The approval rested mainly on the ADVOCATE trial (Jayne et al., NEJM 2021, PubMed PMID: 33596356), whose published report was retracted by the journal on 29 June 2026 (retraction notice PubMed PMID: 42377355). The European Medicines Agency opened a review in January 2026 over the integrity of the ADVOCATE data and concluded in June 2026 that the trial was conducted in breach of good clinical practice and that the study data provided at the time of assessment were “incorrect and misleading” and could no longer be relied upon to show the medicine’s effectiveness; the EU marketing authorisation was revoked on 4 August 2026 (EMA announcement, 26 June 2026). The EMA’s review also states that avacopan is associated with an increased risk of drug-induced liver injury and vanishing bile duct syndrome, including fatal cases, mostly during the first three months of treatment (EMA referral record). The FDA’s Drugs@FDA record still listed the 2021 US approval as of October 2026; whether the FDA has taken any action since the retraction could not be confirmed. The 2022 EULAR update, published before the retraction, had stated that avacopan may be considered as part of a strategy to reduce glucocorticoid exposure (Hellmich 2024).
Biologics for Giant Cell Arteritis
Tocilizumab (anti-IL-6 receptor) is FDA-approved for GCA based on the GiACTA trial (NEJM 2017, PMID 28745999). Weekly subcutaneous 162 mg achieved sustained glucocorticoid-free remission in 56% of patients at 52 weeks vs. 14% with a 26-week prednisone taper and 18% with a 52-week taper (placebo groups). The cumulative median prednisone dose over 52 weeks was 1,862 mg in each tocilizumab group, compared with 3,296 mg and 3,818 mg in the two placebo groups (Stone 2017). Reported risks include neutropenia, raised liver enzymes and, rarely, bowel perforation. Because tocilizumab blocks IL-6 signalling, ESR and CRP can normalize regardless of disease activity; the 2023 EULAR imaging update states that ultrasound, FDG-PET or MRI may be used to assess suspected relapse, particularly when laboratory markers of inflammation are unreliable (Dejaco 2024).
Mepolizumab (anti-IL-5) is approved in the US for adults with EGPA. In the MIRRA trial of 136 patients with relapsing or refractory EGPA on stable glucocorticoid doses, mepolizumab 300 mg every 4 weeks for 52 weeks produced more accrued weeks of remission than placebo (28% versus 3% had at least 24 weeks of remission) and a lower annualized relapse rate (1.14 versus 2.27; rate ratio 0.50); remission did not occur in 47% of the mepolizumab group versus 81% of the placebo group (Wechsler 2017).
Treatment of Secondary Vasculitis
Hepatitis B-associated PAN: in the French series of 115 patients, the antiviral strategy (2 weeks of glucocorticoids, then an antiviral drug combined with plasma exchanges) was associated with a higher HBe seroconversion rate than conventional treatment (49.3% versus 14.7%), and patients who seroconverted reached complete remission and did not relapse (Guillevin 2005); prolonged immunosuppression can promote viral replication. HCV-associated cryoglobulinemic vasculitis: direct-acting antivirals treat the underlying infection, with rituximab used for severe acute manifestations. Drug-induced vasculitis: withdrawal of the drug, with short-course glucocorticoids in severe cases.
Natural and Nutritional Approaches
Nutritional and lifestyle measures do not replace immunosuppressive therapy for active vasculitis. The research questions are mostly indirect: cardiovascular risk (which is raised in systemic vasculitis), the side effects of long-term glucocorticoids, and general inflammation. Some immune-active supplements could in theory interact with immunosuppressants or affect disease-activity monitoring; decisions about supplements belong with a clinician.
Omega-3 Fatty Acids
Eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA) from oily fish (salmon, sardines, mackerel) shift eicosanoid production away from pro-inflammatory leukotriene B4 (LTB4) and thromboxane A2. No trial of fish oil or omega-3 fatty acids for relapse prevention in GPA or other ANCA-associated vasculitis was found in PubMed; the evidence for a role in vasculitis is indirect, from mechanism and from other inflammatory conditions.
Anti-Inflammatory Diet
A Mediterranean-style diet — rich in vegetables, olive oil, legumes, nuts, whole grains, and oily fish — is studied in the general population for its effects on inflammatory markers (IL-6, TNF-alpha, CRP) and cardiovascular risk. No randomized controlled trial of a dietary intervention in vasculitis exists. Long-term glucocorticoids raise blood sugar and blood lipids and promote weight gain, which is why diet is often discussed for people on prolonged courses.
Vitamin D
In a study of 125 patients with ANCA-associated vasculitis in a North American research cohort, most had sufficient vitamin D levels (mean 37.6 ng/mL; deficiency in 10.4%), deficiency was associated with active disease, and vitamin D levels at a later relapse did not differ from baseline; whether raising vitamin D changes disease activity remains to be determined (Doubelt 2023). In laboratory studies vitamin D has immunomodulatory effects, including on regulatory T cells and Th17 cells. Vitamin D is also part of bone protection during long-term glucocorticoid treatment (see Bone and Muscle Health below).
Smoking
Smoking raises cardiovascular risk, which is already elevated in systemic vasculitis (cardiovascular disease was the leading cause of death after the first year in a European cohort of ANCA-associated vasculitis; Flossmann 2011), and is a recognized risk factor for aortic aneurysm, a late complication of GCA and Takayasu arteritis.
Antioxidant Foods and Supplements
Oxidative stress is part of vascular inflammation. Antioxidant-rich foods — colorful vegetables and fruits (berries, leafy greens, cruciferous vegetables), green tea, and turmeric (curcumin) — have been studied mainly in laboratory and general-population research. Vitamins C and E have been studied in inflammatory vascular conditions with modest effects on endothelial function. Quercetin and resveratrol have anti-inflammatory properties in cell studies; human trial data in vasculitis are lacking.
Bone and Muscle Health on Steroids
Long-term corticosteroid use causes osteoporosis, avascular necrosis, and muscle weakness (steroid myopathy). For adults beginning or continuing more than 3 months of glucocorticoids at 2.5 mg/day or more, the 2022 ACR guideline strongly recommends fracture-risk assessment as soon as possible after starting (clinical fracture assessment, bone mineral density testing with vertebral fracture assessment or spinal X-ray, and the FRAX tool from age 40), and strongly recommends drug treatment (oral or intravenous bisphosphonates, denosumab, or parathyroid hormone analogs) for those at medium, high or very high fracture risk (Humphrey 2023). Calcium, vitamin D and weight-bearing exercise are commonly part of these bone-protection programmes.
Stress Reduction
Psychological stress activates the HPA axis and can promote inflammatory cytokine release. Mindfulness meditation, gentle yoga, and structured relaxation techniques are studied in autoimmune conditions; evidence specific to vasculitis is anecdotal. Corticosteroids disrupt sleep architecture, and poor sleep is linked to inflammatory signaling.
Disease Course and Prognosis
Vasculitis follows highly variable disease courses depending on the form, organ involvement at presentation, rapidity of diagnosis, and response to treatment. Modern immunosuppressive regimens have turned several previously fatal conditions into manageable, though often relapsing, chronic diseases.
ANCA-Associated Vasculitis
Without therapy the prognosis is poor; immunosuppressive treatment has improved survival, though with considerable morbidity from glucocorticoids and other immunosuppressive drugs (Kitching 2020). In a European cohort of 535 patients enrolled in four trials between 1995 and 2002, 25% died over a median follow-up of 5.2 years — a mortality 2.6 times that of an age- and sex-matched general population; infection (48%) and active vasculitis (19%) were the main causes of death in the first year, and cardiovascular disease (26%), cancer (22%) and infection (20%) afterwards (Flossmann 2011). Relapse remains the central challenge. In the NIH series of 158 patients with GPA, 50% of remissions were followed by one or more relapses (Hoffman 1992). A 2021 meta-analysis of patients given cyclophosphamide induction estimated cumulative relapse at about 12% at 1 year, 33% at 3 years and 47% at 5 years, with higher 5-year relapse where more patients had GPA (He 2021). In a French MPA cohort, 34.1% of 85 patients relapsed over a mean follow-up of 69.9 months (Guillevin 1999). Risk factors for relapse in the meta-analysis included PR3-ANCA positivity at diagnosis, a rise in ANCA, extrarenal organ involvement, a lower baseline serum creatinine, intravenous rather than oral cyclophosphamide induction, a shorter maintenance course, and maintenance with mycophenolate mofetil rather than azathioprine (He 2021); chronic nasal carriage of S. aureus was a risk factor in a Dutch GPA cohort (Stegeman 1994). Rituximab maintenance reduced major relapse at 28 months to 5% versus 29% with azathioprine in MAINRITSAN (Guillevin 2014).
Giant Cell Arteritis
In the population-based Minnesota cohort, 8.2% of 245 patients had permanent vision loss from GCA, and presenting and final visual acuities did not differ significantly (Chen 2016); in a Swedish cohort of 840 patients with biopsy-proven GCA, 10% developed at least one visual complication (Saleh 2016). Large-vessel involvement (aortic aneurysm, limb ischemia) is a late-emerging risk; the 2023 EULAR imaging update states that MR angiography, CT angiography or ultrasound may be used for long-term monitoring of structural damage, particularly at sites of earlier vascular inflammation (Dejaco 2024). GCA commonly relapses when glucocorticoids are tapered, and long courses are common (Stone 2017). In GiACTA, the tocilizumab groups received less cumulative prednisone and had fewer serious adverse events (15% and 14%) than the placebo groups (22% and 25%) (Stone 2017).
IgA Vasculitis
Most children recover fully. Long-term kidney disease affects a minority. Adults have higher rates of persistent renal disease and a smaller proportion achieve complete resolution.
PAN and Takayasu Arteritis
PAN, when not associated with hepatitis B, follows a relapsing-remitting course managed with steroids and sometimes cyclophosphamide. In hepatitis B-associated PAN, relapses were rare in the French series and did not occur once viral replication had stopped and seroconversion was obtained (Guillevin 2005). Takayasu arteritis in young women can cause decades of vascular complications including limb ischemia, hypertension, and stroke; management involves steroids, steroid-sparing agents (methotrexate, azathioprine, tocilizumab), and vascular reconstruction procedures for critical stenoses.
Complications and Organ Damage
Vasculitis causes organ damage through two distinct mechanisms: active inflammation destroying vessel walls and occluding blood flow, and treatment toxicity from prolonged immunosuppression. The Vasculitis Damage Index (VDI), developed by the Birmingham Vasculitis Group, is a validated tool that scores cumulative irreversible damage (Exley 1997).
Renal Failure
End-stage kidney disease (ESKD) requiring dialysis or transplantation is a major outcome of ANCA-associated vasculitis; in the French MPA cohort, 10 of 85 patients needed long-term dialysis (Guillevin 1999). Kidney function at presentation (an eGFR below 15 mL/min was associated with worse survival in the European cohort; Flossmann 2011), the extent of fibrous scarring versus active cellular crescents on biopsy, and delay to treatment are tied to kidney outcome. Patients with ANCA vasculitis who reach ESKD can receive kidney transplants after a period in remission; recurrence of vasculitis in the transplant is reported as uncommon.
Pulmonary Damage
Pulmonary fibrosis following repeated episodes of alveolar hemorrhage or eosinophilic pneumonia causes irreversible restrictive lung disease. Subglottic stenosis in GPA is treated with repeated dilation or, in severe cases, tracheostomy. Pulmonary hypertension can develop as a late complication.
Cardiovascular Events
Systemic vasculitis is associated with increased cardiovascular risk — a combination of disease-driven endothelial dysfunction, accelerated atherosclerosis, and steroid-induced dyslipidemia and hypertension; cardiovascular disease was the leading cause of death after the first year in the European ANCA cohort (26%) (Flossmann 2011). Aortic aneurysm — particularly in GCA and Takayasu — can rupture fatally. Blood pressure, lipids and glucose are monitored as part of long-term care.
Peripheral Neuropathy
Mononeuritis multiplex can leave lasting axonal loss and permanent foot drop, wrist drop, or sensory loss. Physical therapy and orthotic devices are used in rehabilitation; recovery of established nerve damage is slow and often incomplete.
Vision Loss
Permanent visual loss in GCA, once established, rarely recovers with steroids; in the Minnesota cohort, presenting and final visual acuities did not differ significantly (Chen 2016). Treatment aims to prevent vision loss in the other eye rather than reverse it.
Treatment Toxicity
Corticosteroids cause: osteoporosis and fractures, cataracts, glaucoma, diabetes, hypertension, adrenal suppression, Cushing's syndrome, and avascular necrosis of the hip. Cyclophosphamide: in 145 NIH patients treated for GPA, half developed non-glomerular hematuria and 5% developed bladder cancer, with an estimated bladder-cancer incidence of 5% at 10 years and 16% at 15 years after first exposure (Talar-Williams 1996); also premature ovarian failure or azoospermia and myelodysplastic syndrome. Methotrexate: hepatotoxicity, pulmonary hypersensitivity. Rituximab: hypogammaglobulinemia with recurrent infections, rare progressive multifocal leukoencephalopathy (PML), and prolonged B-cell depletion requiring immunoglobulin replacement in some patients.
Prevention and Monitoring
Primary prevention of vasculitis is not possible given its largely idiopathic nature; monitoring aims at secondary prevention of organ damage, relapse, and treatment toxicity.
Infection Prophylaxis During Immunosuppression
Trimethoprim-sulfamethoxazole (TMP-SMX) prophylaxis against Pneumocystis jirovecii pneumonia (PCP) is used during cyclophosphamide- or rituximab-based induction and high-dose glucocorticoid treatment. Hepatitis B testing (HBsAg, anti-HBc) is done before rituximab, because rituximab can reactivate occult hepatitis B; antiviral prophylaxis is used in some patients. Inactivated vaccines (influenza, pneumococcal) are usually brought up to date, and live vaccines (MMR, varicella, yellow fever) are not given during significant immunosuppression. Immunoglobulin levels are checked when infections recur on rituximab, and immunoglobulin replacement is used in some patients with low IgG.
Disease Activity Monitoring
Urinalysis with microscopy is a routine part of follow-up in ANCA vasculitis, because returning microscopic hematuria can be an early sign of renal relapse. ANCA levels are often followed: in a meta-analysis a rise in ANCA was one of the risk factors for relapse (He 2021), but in a prospective study of 156 patients with GPA increases in PR3-ANCA levels were not associated with relapse, and the authors concluded that ANCA levels cannot be used to guide immunosuppressive therapy (Finkielman 2007). For GCA patients on tocilizumab, inflammatory markers are suppressed by the drug, and imaging (ultrasound, FDG-PET or MRI) may be used to assess suspected relapse (Dejaco 2024).
Cardiovascular Risk Reduction
Blood pressure, LDL cholesterol and glucose are monitored, with targets taken from general cardiovascular guidelines; low-dose aspirin is used in patients with prior cardiovascular events. Steroid-induced hyperglycemia sometimes needs short-term or long-term antidiabetic treatment during steroid courses.
Bone Protection
For any glucocorticoid course expected to last more than 3 months, the 2022 ACR guideline strongly recommends early fracture-risk assessment, including bone mineral density testing and FRAX from age 40, and drug treatment for those at medium or higher fracture risk (Humphrey 2023) (see Bone and Muscle Health on Steroids above).
Relapse Recognition and Patient Education
Symptoms commonly listed as possible signs of relapse include return of sinusitis or nasal symptoms (GPA), hemoptysis or new cough, new blood in the urine, visual symptoms (GCA), and constitutional symptoms (fever, night sweats, weight loss). Urine dipsticks detect blood between clinic visits but cannot show red cell casts. Patient support organizations offer peer support, self-management resources, and disease-specific education materials.
Key Research Papers
- Jennette JC et al., 2013 — 2012 Revised International Chapel Hill Consensus Conference Nomenclature of Vasculitides. — PubMed PMID: 23045170
- Stone JH et al., 2010 — Rituximab versus cyclophosphamide for ANCA-associated vasculitis (RAVE). N Engl J Med 2010;363(3):221-32. — PubMed PMID: 20647199
- Stone JH et al., 2017 — Trial of Tocilizumab in Giant-Cell Arteritis (GiACTA). N Engl J Med 2017;377(4):317-328. — PubMed PMID: 28745999
- Mukhtyar C et al., 2009 — EULAR recommendations for the management of primary small and medium vessel vasculitis. Ann Rheum Dis 2009;68(3):310-7. — PubMed PMID: 18413444
- Finkielman JD et al., 2007 — Antiproteinase 3 antineutrophil cytoplasmic antibodies and disease activity in Wegener granulomatosis. Ann Intern Med 2007;147(9):611-9. — PubMed PMID: 17975183
- Nordborg C, Nordborg E, Petursdottir V, 2000 — Giant cell arteritis. Epidemiology, etiology and pathogenesis. APMIS 2000;108(11):713-24. — PubMed PMID: 11211963 (replaces an entry, “Hoffman GS et al., 2011 — Giant cell arteritis: epidemiology and pathogenesis”, that could not be found in PubMed; its search link is kept under PubMed Topic Searches)
- Kallenberg CG, 2011 — Pathogenesis of ANCA-associated vasculitides. Ann Rheum Dis 2011;70(Suppl 1):i59-63. — PubMed PMID: 21339221
- Watts RA, Hatemi G, Burns JC, et al., 2022 — Global epidemiology of vasculitis. Nat Rev Rheumatol 2022;18(1):22-34. — PubMed PMID: 34853411 (replaces an entry, “Watts RA et al., 2007 — Epidemiology of systemic vasculitis”, that could not be found in PubMed; its search link is kept under PubMed Topic Searches)
- Zwerina J et al., 2009 — Pathogenesis of Churg-Strauss syndrome: recent insights. Autoimmunity 2009;42(4):376-9. — PubMed PMID: 19811306
- Ozen S et al., 2010 — EULAR/PRINTO/PRES criteria for Henoch-Schönlein purpura, childhood polyarteritis nodosa, childhood Wegener granulomatosis and childhood Takayasu arteritis: Ankara 2008. Part II: Final classification criteria. Ann Rheum Dis 2010;69(5):798-806. — PubMed PMID: 20413568
- Ntatsaki E et al., 2014 — BSR and BHPR guideline for the management of adults with ANCA-associated vasculitis. Rheumatology (Oxford) 2014;53(12):2306-9. — PubMed PMID: 24729399
- Jayne DRW, Merkel PA, Schall TJ, et al., 2021 — Avacopan for the treatment of ANCA-associated vasculitis (ADVOCATE). N Engl J Med 2021;384(7):599-609. — PubMed PMID: 33596356 — Retracted (retraction notice: PubMed PMID: 42377355)
- Walsh M et al., 2020 — Plasma exchange and glucocorticoids in severe ANCA-associated vasculitis (PEXIVAS). N Engl J Med 2020;382(7):622-631. — PubMed PMID: 32053298
- Hellmich B, Sanchez-Alamo B, Schirmer JH, et al., 2024 — EULAR recommendations for the management of ANCA-associated vasculitis: 2022 update. Ann Rheum Dis 2024;83(1):30-47. — PubMed PMID: 36927642
- Chung SA, Langford CA, Maz M, et al., 2021 — 2021 American College of Rheumatology/Vasculitis Foundation guideline for the management of antineutrophil cytoplasmic antibody-associated vasculitis. Arthritis Rheumatol 2021;73(8):1366-1383. — PubMed PMID: 34235894
- Guillevin L et al., 2014 — Rituximab versus azathioprine for maintenance in ANCA-associated vasculitis (MAINRITSAN). N Engl J Med 2014;371(19):1771-80. — PubMed PMID: 25372085
- Jayne D et al., 2003 — A randomized trial of maintenance therapy for vasculitis associated with antineutrophil cytoplasmic autoantibodies (CYCAZAREM). N Engl J Med 2003;349(1):36-44. — PubMed PMID: 12840090
- de Groot K, Harper L, Jayne DR, et al., 2009 — Pulse versus daily oral cyclophosphamide for induction of remission in antineutrophil cytoplasmic antibody-associated vasculitis: a randomized trial (CYCLOPS). Ann Intern Med 2009;150(10):670-80. — PubMed PMID: 19451574
- Hiemstra TF, Walsh M, Mahr A, et al., 2010 — Mycophenolate mofetil vs azathioprine for remission maintenance in antineutrophil cytoplasmic antibody-associated vasculitis: a randomized controlled trial (IMPROVE). JAMA 2010;304(21):2381-8. — PubMed PMID: 21060104
- Hoffman GS et al., 1992 — Wegener granulomatosis: an analysis of 158 patients. Ann Intern Med 1992;116(6):488-98. — PubMed PMID: 1739240
- He P, Hu JP, Tian XJ, et al., 2021 — Prevalence and risk factors of relapse in patients with ANCA-associated vasculitis receiving cyclophosphamide induction: a systematic review and meta-analysis of large observational studies. Rheumatology (Oxford) 2021;60(3):1067-1079. — PubMed PMID: 33677596
- Flossmann O, Berden A, de Groot K, et al., 2011 — Long-term patient survival in ANCA-associated vasculitis. Ann Rheum Dis 2011;70(3):488-94. — PubMed PMID: 21109517
- Kitching AR, Anders HJ, Basu N, et al., 2020 — ANCA-associated vasculitis. Nat Rev Dis Primers 2020;6(1):71. — PubMed PMID: 32855422
- Redondo-Rodriguez R, Mena-Vázquez N, Cabezas-Lucena AM, et al., 2022 — Systematic review and metaanalysis of worldwide incidence and prevalence of antineutrophil cytoplasmic antibody (ANCA) associated vasculitis. J Clin Med 2022;11(9):2573. — PubMed PMID: 35566698
- Guillevin L et al., 1999 — Microscopic polyangiitis: clinical and laboratory findings in eighty-five patients. Arthritis Rheum 1999;42(3):421-30. — PubMed PMID: 10088763
- Comarmond C, Pagnoux C, Khellaf M, et al., 2013 — Eosinophilic granulomatosis with polyangiitis (Churg-Strauss): clinical characteristics and long-term followup of the 383 patients enrolled in the French Vasculitis Study Group cohort. Arthritis Rheum 2013;65(1):270-81. — PubMed PMID: 23044708
- Wechsler ME, Akuthota P, Jayne D, et al., 2017 — Mepolizumab or placebo for eosinophilic granulomatosis with polyangiitis (MIRRA). N Engl J Med 2017;376(20):1921-1932. — PubMed PMID: 28514601
- Lyons PA, Rayner TF, Trivedi S, et al., 2012 — Genetically distinct subsets within ANCA-associated vasculitis. N Engl J Med 2012;367(3):214-23. — PubMed PMID: 22808956
- Stegeman CA, Tervaert JW, Sluiter WJ, et al., 1994 — Association of chronic nasal carriage of Staphylococcus aureus and higher relapse rates in Wegener granulomatosis. Ann Intern Med 1994;120(1):12-7. — PubMed PMID: 8250451
- Gómez-Puerta JA, Gedmintas L, Costenbader KH, 2013 — The association between silica exposure and development of ANCA-associated vasculitis: systematic review and meta-analysis. Autoimmun Rev 2013;12(12):1129-35. — PubMed PMID: 23820041
- Guillevin L, Mahr A, Callard P, et al., 2005 — Hepatitis B virus-associated polyarteritis nodosa: clinical characteristics, outcome, and impact of treatment in 115 patients. Medicine (Baltimore) 2005;84(5):313-322. — PubMed PMID: 16148731
- Rubenstein E, Maldini C, Gonzalez-Chiappe S, et al., 2020 — Sensitivity of temporal artery biopsy in the diagnosis of giant cell arteritis: a systematic literature review and meta-analysis. Rheumatology (Oxford) 2020;59(5):1011-1020. — PubMed PMID: 31529073
- Chen JJ, Leavitt JA, Fang C, et al., 2016 — Evaluating the incidence of arteritic ischemic optic neuropathy and other causes of vision loss from giant cell arteritis. Ophthalmology 2016;123(9):1999-2003. — PubMed PMID: 27297405
- Saleh M, Turesson C, Englund M, et al., 2016 — Visual complications in patients with biopsy-proven giant cell arteritis: a population-based study. J Rheumatol 2016;43(8):1559-65. — PubMed PMID: 27252424
- Dejaco C, Ramiro S, Bond M, et al., 2024 — EULAR recommendations for the use of imaging in large vessel vasculitis in clinical practice: 2023 update. Ann Rheum Dis 2024;83(6):741-751. — PubMed PMID: 37550004
- Mukhtyar C, Lee R, Brown D, et al., 2009 — Modification and validation of the Birmingham Vasculitis Activity Score (version 3). Ann Rheum Dis 2009;68(12):1827-32. — PubMed PMID: 19054820
- Exley AR, Bacon PA, Luqmani RA, et al., 1997 — Development and initial validation of the Vasculitis Damage Index for the standardized clinical assessment of damage in the systemic vasculitides. Arthritis Rheum 1997;40(2):371-80. — PubMed PMID: 9041949
- Robson JC et al., 2022 — 2022 American College of Rheumatology/European Alliance of Associations for Rheumatology classification criteria for granulomatosis with polyangiitis. Arthritis Rheumatol 2022;74(3):393-399. — PubMed PMID: 35106964
- Suppiah R, Robson JC, Grayson PC, et al., 2022 — 2022 American College of Rheumatology/European Alliance of Associations for Rheumatology classification criteria for microscopic polyangiitis. Arthritis Rheumatol 2022;74(3):400-406. — PubMed PMID: 35106973
- McAdoo SP, Tanna A, Hrušková Z, et al., 2017 — Patients double-seropositive for ANCA and anti-GBM antibodies have varied renal survival, frequency of relapse, and outcomes compared to single-seropositive patients. Kidney Int 2017;92(3):693-702. — PubMed PMID: 28506760
- Talar-Williams C, Hijazi YM, Walther MM, et al., 1996 — Cyclophosphamide-induced cystitis and bladder cancer in patients with Wegener granulomatosis. Ann Intern Med 1996;124(5):477-84. — PubMed PMID: 8602705
- Doubelt I, Cuthbertson D, Carette S, et al., 2023 — Vitamin D status in ANCA-associated vasculitis. Rheumatol Adv Pract 2023;7(1):rkad021. — PubMed PMID: 36874269
- Humphrey MB, Russell L, Danila MI, et al., 2023 — 2022 American College of Rheumatology guideline for the prevention and treatment of glucocorticoid-induced osteoporosis. Arthritis Rheumatol 2023;75(12):2088-2102. — PubMed PMID: 37845798 (published simultaneously in Arthritis Care Res, PubMed PMID: 37884467)
PubMed Topic Searches
Connections
- Rheumatology
- Rheumatoid Arthritis
- Arthritis
- Lupus
- Raynaud's Disease
- Sjögren's Syndrome
- Ankylosing Spondylitis
- Gout
- Osteoarthritis
- Ehlers-Danlos Syndrome
- Osteoporosis
- Cardiovascular Disease
- ANCA Test — the antibody test that confirms ANCA-associated vasculitis and separates PR3 from MPO disease.
- Microscopic Polyangiitis (MPA) — ANCA-associated small-vessel vasculitis defined by the absence of granulomas.
- Granulomatosis with Polyangiitis (GPA) — ANCA-associated vasculitis with necrotizing granulomas of the airways and kidneys.
- Glomerulonephritis — the kidney manifestation of ANCA-associated and immune-complex vasculitis.
- Henoch-Schönlein Purpura (IgA Vasculitis) — the most common vasculitis of childhood, covered in full on its own page.
- Granulomatosis with Polyangiitis (Rheumatology) — the rheumatology view of the same ANCA-associated vasculitis, with induction and maintenance regimens.