⚠ Evidence warning: Clinical trials or other evidence do not support the claim that biofeedback and autogenic training are effective in primary Raynaud's. This page keeps it as a report of what people, websites or other media say.
Cold Hands and Feet
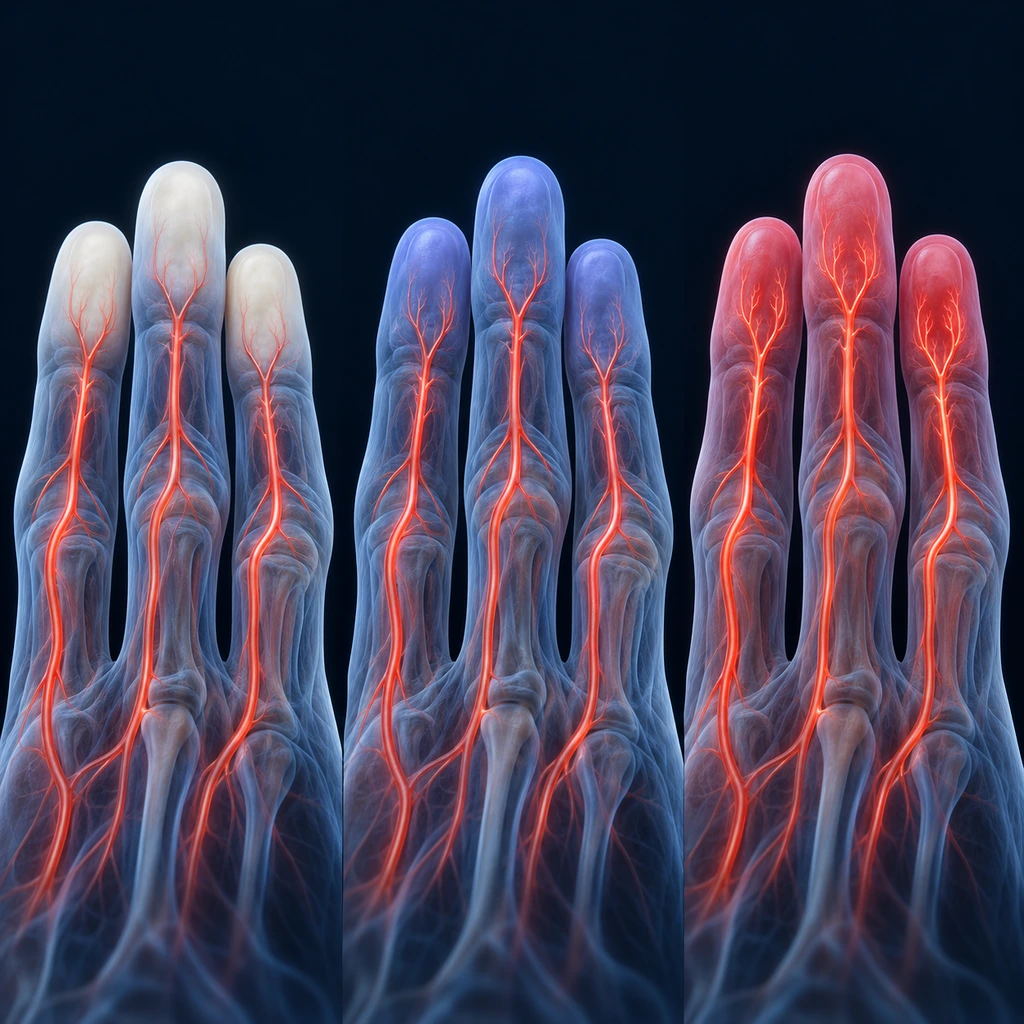
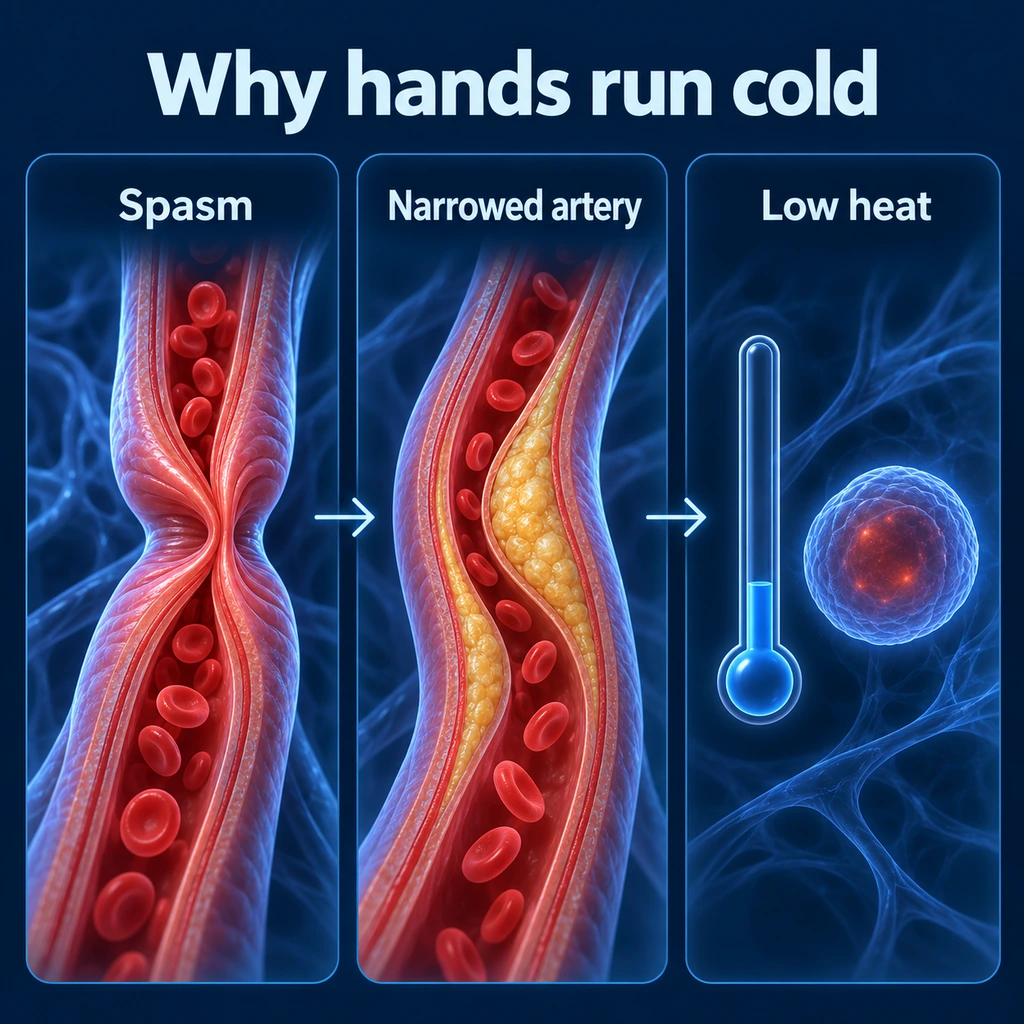
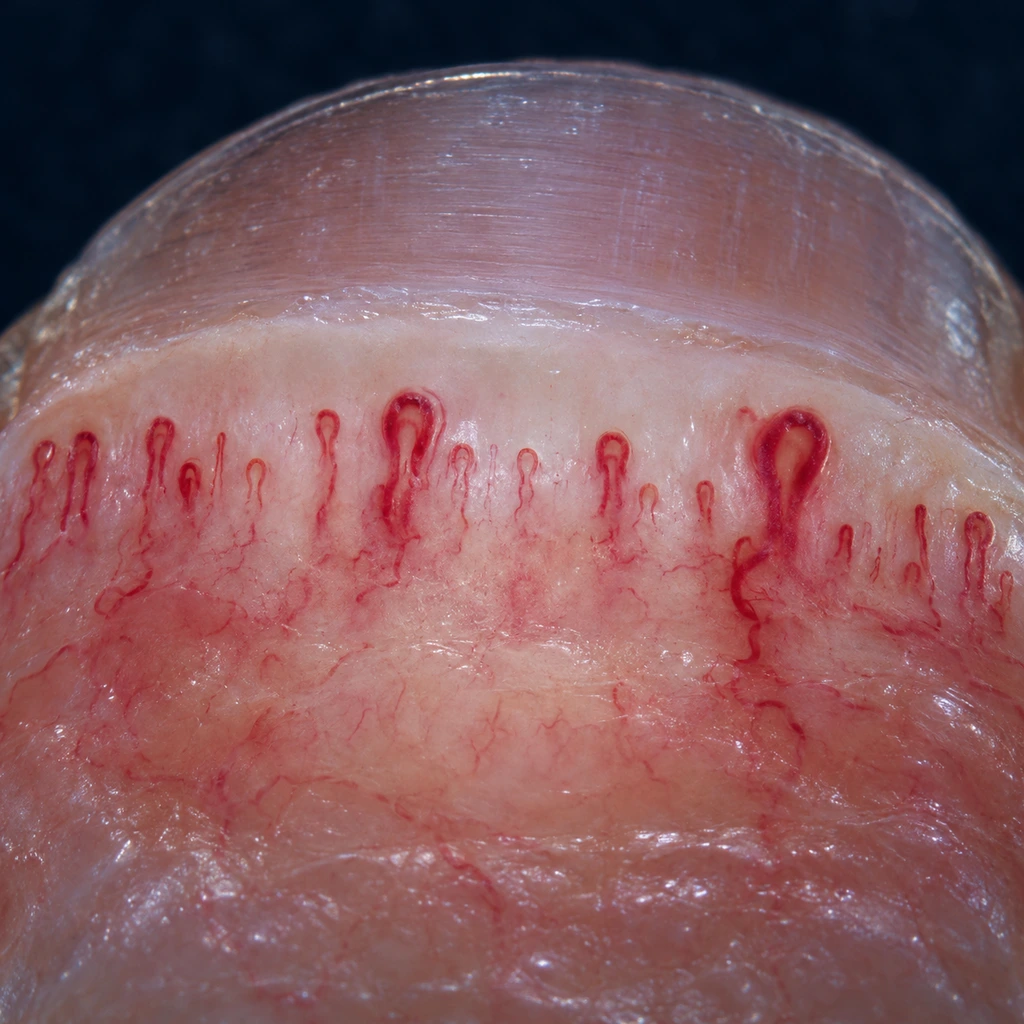
Table of Contents
Overview
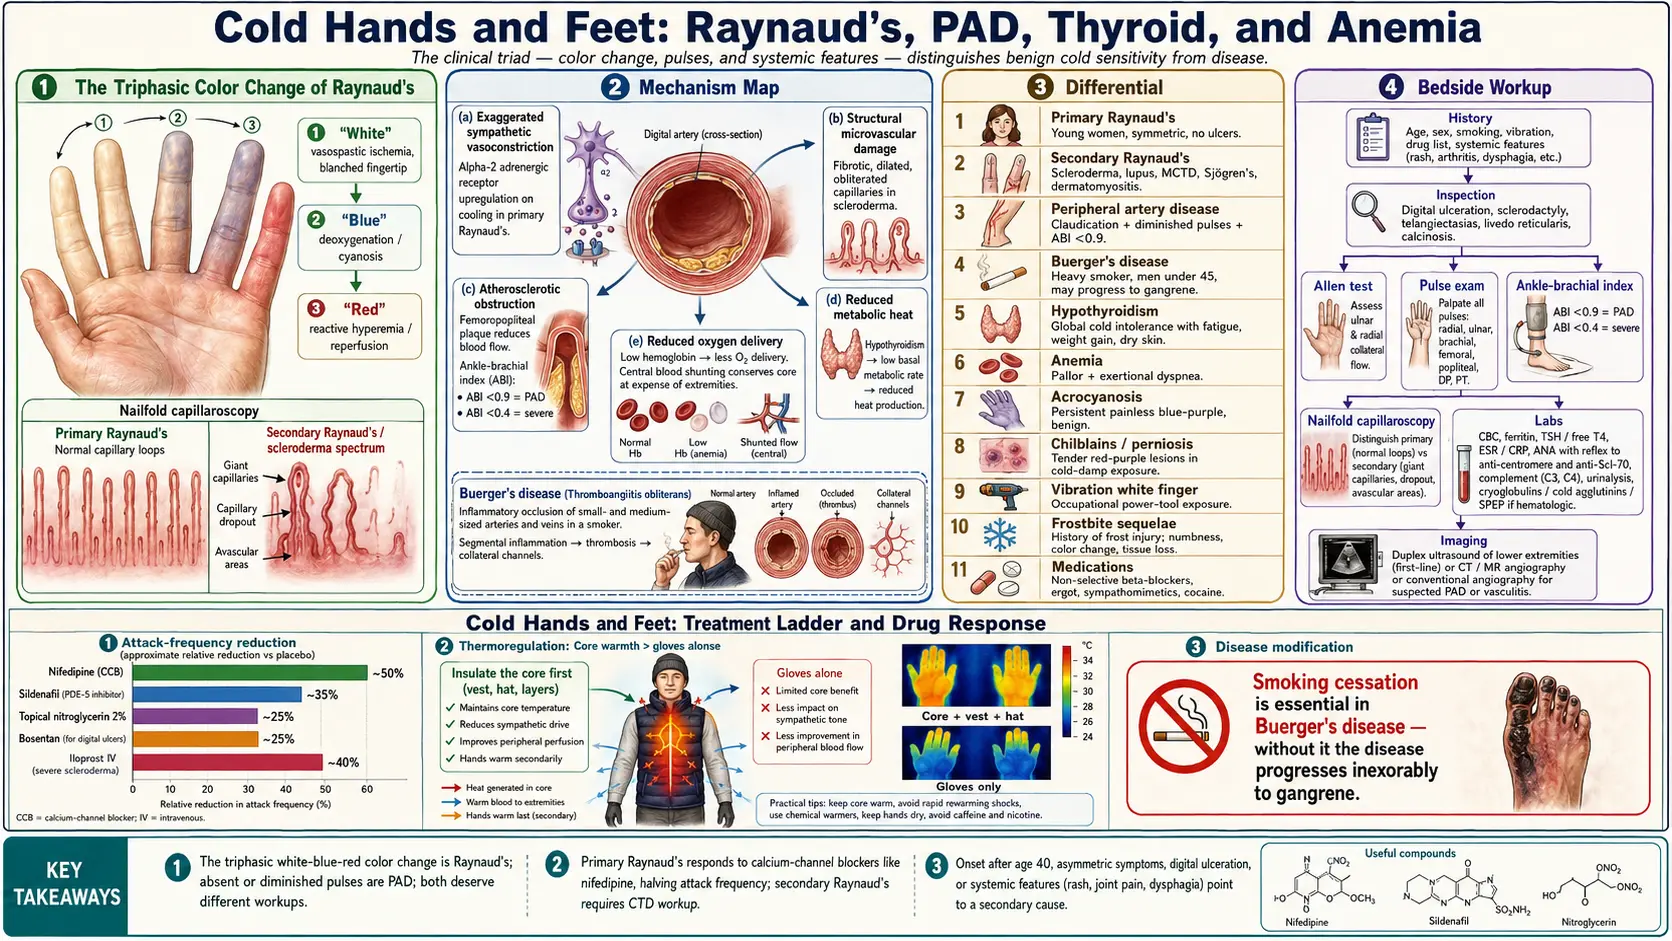
Cold hands and feet span a spectrum from benign vasoconstriction — a chilly room, low body fat, anxiety, or simple physiological cold sensitivity — all the way to vascular disease and connective tissue disease. Most people experience cold extremities occasionally without any underlying pathology, but persistent or asymmetric cold extremities are the pattern clinicians investigate. The clinical triad to assess is straightforward: color change (a white-blue-red triphasic pattern points strongly to Raynaud's phenomenon), pulses (absent or diminished pulses suggest peripheral artery disease), and associated systemic features (cold intolerance with fatigue, weight gain, and dry skin suggests hypothyroidism; cold extremities with pallor and exertional dyspnea suggest anemia). Onset after age 40, asymmetric symptoms, digital ulceration, or systemic features such as joint pain, rash, or dysphagia all raise the probability of a secondary cause that requires specific treatment.
Primary Raynaud's itself is common. A 2015 pooled analysis of 33 observational studies (33,733 people) put it at 4.85% of the general population, with about 0.25% of people developing it each year. Family history had the strongest link (odds ratio 16.6), followed by migraine (4.02), manual work (2.66), female sex (1.65) and smoking (1.27). The definition of primary Raynaud's varied considerably between the studies.
Types
- Primary Raynaud's phenomenon — idiopathic, typically begins in young women, symmetric, no underlying disease, no digital ulceration, normal nailfold capillaries.
- Secondary Raynaud's phenomenon — associated with scleroderma, lupus, mixed connective tissue disease, Sjögren's, dermatomyositis, or hematologic disease. Often asymmetric, may progress to digital ulceration or gangrene, abnormal nailfold capillaroscopy.
- Peripheral artery disease (PAD) — atherosclerotic obstruction of large or medium-sized arteries, producing cold extremities with claudication, diminished pulses, and a low ankle-brachial index.
- Microvascular cold sensitivity — small-vessel disease from diabetes, smoking, or chronic kidney disease. Pulses are typically preserved but capillary blood flow is impaired.
- Metabolic cold intolerance — reduced metabolic heat production from hypothyroidism, anemia, low body weight, or anorexia nervosa. Whole-body cold sensitivity rather than focal extremity findings.
- Acrocyanosis — persistent, painless, symmetric blue-purple discoloration of hands and feet, often with sweating. Benign, usually idiopathic, no triphasic color change.
- Chilblains (perniosis) — tender, itchy, red-purple lesions on toes or fingers triggered by exposure to cold and damp conditions. Self-limited but recurrent. A 2025 review calls it uncommon and inflammatory, with its cause poorly understood; no high-quality randomized trials exist, so treatment recommendations come from case reports and from studies of related conditions such as Raynaud's. In one health system, 169 of 1,478 patients with chilblains (11.43%) had an autoimmune disease, most often lupus (52.6% of those).
Common Causes
- Primary Raynaud's phenomenon — idiopathic vasospasm of the digital arteries, most often in women between ages 15 and 30. Episodes are triggered by cold or emotional stress.
- Secondary Raynaud's — scleroderma, lupus, mixed connective tissue disease, Sjögren's syndrome, dermatomyositis, and rheumatoid arthritis.
- Peripheral artery disease — atherosclerotic obstruction driven by smoking, diabetes, hyperlipidemia, hypertension, and age. Produces cold extremities, claudication, and diminished pulses.
- Buerger's disease (thromboangiitis obliterans) — segmental inflammatory occlusion of small and medium arteries in heavy tobacco smokers, almost always in men under 45. May progress to digital gangrene unless smoking is stopped.
- Hypothyroidism — reduced metabolic rate produces global cold intolerance, fatigue, weight gain, dry skin, constipation, and bradycardia.
- Anemia — reduced oxygen-carrying capacity and compensatory peripheral vasoconstriction produce cold extremities, pallor, and exertional dyspnea.
- Hypothalamic dysfunction — impaired thermoregulation in anorexia nervosa, severe weight loss, panhypopituitarism, or hypothalamic injury.
- Medications — non-selective beta-blockers, ergot alkaloids, sympathomimetics, certain chemotherapy agents (bleomycin, cisplatin), and stimulants can provoke or worsen vasoconstriction. A 2026 analysis of 4,430 World Health Organization drug-safety reports of Raynaud's rated 16 signals as probable, including amphetamine-like drugs, migraine medicines, some cancer drugs and dopamine agonists; signals it names include solriamfetol, tyrosine kinase inhibitors and calcitonin gene-related peptide inhibitors. These are reporting signals meant to generate hypotheses, not proof of cause.
- Cocaine and other vasoconstrictors — intense sympathetic stimulation can produce digital ischemia and Raynaud's-like attacks.
- Vibration injury (vibration white finger) — chronic occupational exposure to hand-held power tools causes structural microvascular damage and cold-induced episodes.
- Frostbite history — previous cold injury permanently lowers the threshold for cold-induced vasoconstriction in the affected fingers and toes.
Mechanisms
Cold extremities reflect either reduced delivery of warm blood to the skin and digits, reduced metabolic heat production, or both. Most patients have one dominant mechanism:
- Exaggerated sympathetic vasoconstriction — in primary Raynaud's, otherwise normal digital arteries respond to cold or stress with intense, prolonged contraction. Alpha-2 adrenergic receptors are upregulated on cooling, amplifying the response.
- Structural microvascular damage — in scleroderma and other connective tissue diseases, the digital and nailfold capillaries become fibrotic, dilated, and obliterated. Capillaroscopy reveals dropout, giant capillaries, and avascular areas. The vasospastic response is layered on top of fixed obstructive disease.
- Atherosclerotic obstruction — in peripheral artery disease, plaque narrows the femoral, popliteal, or tibial arteries and limits flow at rest or during exertion. Collaterals partly compensate but cannot match demand under cold or activity stress.
- Reduced metabolic heat — in hypothyroidism, basal metabolic rate falls, decreasing whole-body heat production. Low body mass and low body fat similarly reduce both heat generation and insulation.
- Reduced oxygen delivery — in anemia, hemoglobin is insufficient to carry adequate oxygen to peripheral tissues. The body responds by shunting blood centrally, leaving the extremities cold and pale.
- Inflammatory occlusion — in Buerger's disease and small-vessel vasculitis, segmental inflammation thromboses small arteries, producing focal ischemia.
Evaluation
Workup is guided by age of onset, symmetry, presence of triphasic color change, and any systemic features. A reasonable starting set includes:
- History — age of onset, sex, smoking history, occupational vibration exposure, drug list (beta-blockers, ergot, stimulants, cocaine), systemic symptoms (rash, joint pain, dry eyes/mouth, dysphagia, dyspnea, weight change).
- Physical exam — looks for color change, digital ulceration, sclerodactyly, telangiectasias, calcinosis, livedo reticularis, rash, and synovitis. Hand temperatures are compared, the Allen test checks radial/ulnar arch patency, and all peripheral pulses are felt.
- Ankle-brachial index (ABI) — bedside ratio of ankle to arm systolic pressure. Values below 0.9 indicate peripheral artery disease; below 0.4 indicates severe disease.
- Nailfold capillaroscopy — magnified inspection of the proximal nailfold. Normal in primary Raynaud's; shows giant capillaries, dropout, and disorganization in scleroderma-spectrum disease.
- Bloodwork — complete blood count (CBC) (anemia), ferritin and iron studies, thyroid-stimulating hormone (TSH) and free T4 (thyroid), comprehensive metabolic panel, erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP) (inflammation), antinuclear antibody (ANA) with reflex to anti-centromere and anti-Scl-70 antibodies (scleroderma spectrum), complement levels, and urinalysis.
- Specialized antibody panel — anti-dsDNA, anti-Ro/La, anti-RNP, anti-Jo-1 if connective tissue disease is suspected on initial screening.
- Cryoglobulins, cold agglutinins, serum protein electrophoresis — if hematologic or paraproteinemic cause is suspected.
- Duplex ultrasound or angiography — for confirmed or suspected peripheral artery disease, to localize and quantify obstruction.
- Cold provocation testing — in selected occupational or research settings; not routinely needed in clinical practice.
Management
- Core warmth — maintaining trunk warmth is often more effective than gloves and socks alone, because peripheral vasoconstriction is partly driven by central thermoregulatory reflexes. Layered clothing, hats, and warm vests reduce attack frequency.
- Known triggers — cold air, cold water, sudden temperature changes, emotional stress, vibration, and tobacco. Insulated gloves worn before entering refrigerated sections of supermarkets are one described measure.
- Smoking cessation — essential in Buerger's disease (without cessation, the disease progresses inexorably) and central in peripheral artery disease treatment.
- Calcium-channel blockers — nifedipine extended-release 30–60 mg daily or amlodipine 5–10 mg daily are first-line drug therapy for Raynaud's. How much they reduce attacks differs by analysis. A meta-analysis in primary Raynaud's called the effect small, 2.8 to 5.0 fewer attacks per week and a 33% reduction in severity. A 2016 Cochrane review in primary Raynaud's called them minimally effective, 1.72 fewer attacks per week. A 2017 Cochrane review of primary and secondary Raynaud's found 6 fewer attacks per week against 13.7 on placebo, or 2.93 fewer after excluding one trial with a very large effect. In the largest single trial (313 people), sustained-release nifedipine gave 66% fewer verified attacks than placebo, and 15% stopped it because of side effects.
- Phosphodiesterase-5 inhibitors — sildenafil or tadalafil for severe digital ischemia, particularly in scleroderma-associated Raynaud's with digital ulcers.
- Topical nitroglycerin — 2 percent ointment applied to affected digits can abort an attack or speed recovery; headache is the limiting side effect.
- Vasodilators in primary Raynaud's — a 2021 Cochrane review (15 studies, 635 people) found no evidence of an effect of topical nitroglycerin on attacks per week (very low certainty), no evidence of a difference with phosphodiesterase inhibitors in frequency, severity or duration of attacks, and a possible small increase in attacks with angiotensin-converting enzyme inhibitors. Its authors call the evidence insufficient to support these drugs in primary Raynaud's.
- Prostacyclin analogs — intravenous iloprost for refractory digital ulcers in scleroderma; produces sustained improvement in healing.
- Endothelin-receptor antagonists — bosentan reduces new digital ulcer formation in scleroderma.
- Treatment of the underlying connective tissue disease — immunosuppression, antifibrotic agents, and disease-specific therapy alter the course of secondary Raynaud's.
- Antiplatelet therapy and statins for peripheral artery disease — aspirin or clopidogrel plus a high-intensity statin reduce cardiovascular events. Cilostazol improves walking distance. Revascularization (angioplasty, stenting, bypass) is reserved for limiting claudication or threatened limbs. The 2024 American College of Cardiology and American Heart Association guideline updates the 2016 recommendations with new evidence and adds new recommendations on comprehensive care.
- Levothyroxine for hypothyroidism — restores metabolic rate; cold intolerance often resolves within weeks of normalizing thyroid-stimulating hormone.
- Iron repletion for anemia — oral or intravenous iron based on severity and tolerance, plus treatment of any underlying cause of iron loss.
- Biofeedback and autogenic training — behavioral therapies that train conscious peripheral vasodilation; effective in primary Raynaud's with sustained practice.
- Sympathectomy — surgical or chemical interruption of the sympathetic nerves to the affected limb; reserved for refractory severe cases with threatened tissue loss.
Signs That Point to a Serious Cause
- Digital ulceration, blackened fingertips, or frank gangrene.
- Sudden, severe cold and pulseless extremity with pain — acute limb ischemia is an emergency requiring immediate evaluation.
- Asymmetric symptoms (one hand or foot affected far more than the other) suggest fixed arterial disease rather than primary Raynaud's.
- Onset after age 40, or onset in a man — both raise the probability of a secondary cause.
- Raynaud's accompanied by systemic features such as rash, joint pain, dry eyes or mouth, dysphagia, shortness of breath, or skin tightening.
- Cold intolerance with progressive fatigue, weight gain, hair loss, or constipation (can point to hypothyroidism).
- Cold extremities with pallor, exertional dyspnea, or palpitations (can point to anemia).
- Calf pain with walking that resolves with rest (intermittent claudication) plus cold extremities suggests peripheral artery disease.
Connections
Key Research Papers
Historical Background
The phenomenon now bearing his name was first described by French medical student Maurice Raynaud in his 1862 doctoral thesis De l'asphyxie locale et de la gangrène symétrique des extrémités, in which he documented twenty-five cases of episodic digital ischemia and proposed an autonomic-nervous-system origin. Edgar Allen described his bedside test of radial and ulnar arch patency in 1929, providing the first reproducible method to assess hand circulation at the bedside. Pharmacologic management began in earnest in the 1980s when nifedipine was shown to reduce attack frequency in primary Raynaud's; in subsequent decades, bosentan and intravenous iloprost transformed the management of digital ulcers in systemic sclerosis. The 2013 ACR/EULAR classification criteria for systemic sclerosis allowed earlier and more reproducible identification of secondary Raynaud's, while nailfold capillaroscopy moved from research tool to routine office procedure.
Key Research Papers
- Wigley FM. Clinical practice. Raynaud's phenomenon. New England Journal of Medicine. 2002;347(13):1001-1008. — doi:10.1056/NEJMcp013013
- van den Hoogen F, Khanna D, Fransen J, et al. 2013 classification criteria for systemic sclerosis: an American College of Rheumatology/European League against Rheumatism collaborative initiative. Annals of the Rheumatic Diseases. 2013;72(11):1747-1755. — doi:10.1136/annrheumdis-2013-204424
- Kowal-Bielecka O, Fransen J, Avouac J, et al. Update of EULAR recommendations for the treatment of systemic sclerosis. Annals of the Rheumatic Diseases. 2017;76(8):1327-1339. — doi:10.1136/annrheumdis-2016-209909
- Korn JH, Mayes M, Matucci Cerinic M, et al. Digital ulcers in systemic sclerosis: prevention by treatment with bosentan, an oral endothelin receptor antagonist. Arthritis & Rheumatism. 2004;50(12):3985-3993. — doi:10.1002/art.20676
- Gerhard-Herman MD, Gornik HL, Barrett C, et al. 2016 AHA/ACC guideline on the management of patients with lower extremity peripheral artery disease. Circulation. 2017;135(12):e726-e779. — doi:10.1161/CIR.0000000000000471
- Aboyans V, Ricco JB, Bartelink MEL, et al. 2017 ESC guidelines on the diagnosis and treatment of peripheral arterial diseases. European Heart Journal. 2018;39(9):763-816. — doi:10.1093/eurheartj/ehx095
- Belch JJ, Ho M. Pharmacotherapy of Raynaud's phenomenon. Drugs. 1996;52(5):682-695. — doi:10.2165/00003495-199652050-00006
- Thompson AE, Pope JE. Calcium channel blockers for primary Raynaud's phenomenon: a meta-analysis. Rheumatology. 2005;44(2):145-150. — doi:10.1093/rheumatology/keh390
- Herrick AL. The pathogenesis, diagnosis and treatment of Raynaud phenomenon. Nature Reviews Rheumatology. 2012;8(8):469-479. — doi:10.1038/nrrheum.2012.96
- Olin JW, Sealove BA. Peripheral artery disease: current insight into the disease and its diagnosis and management. Mayo Clinic Proceedings. 2010;85(7):678-692. — doi:10.4065/mcp.2010.0133
- Ennis H, Hughes M, Anderson ME, et al. Calcium channel blockers for primary Raynaud's phenomenon. Cochrane Database Syst Rev. 2016;2(2):CD002069. — PubMed PMID: 26914257
- Rirash F, Tingey PC, Harding SE, et al. Calcium channel blockers for primary and secondary Raynaud's phenomenon. Cochrane Database Syst Rev. 2017;12(12):CD000467. — PubMed PMID: 29237099
- Comparison of sustained-release nifedipine and temperature biofeedback for treatment of primary Raynaud phenomenon. Results from a randomized clinical trial with 1-year follow-up. Arch Intern Med. 2000;160(8):1101-1108. — PubMed PMID: 10789602
- Garner R, Kumari R, Lanyon P, et al. Prevalence, risk factors and associations of primary Raynaud's phenomenon: systematic review and meta-analysis of observational studies. BMJ Open. 2015;5(3):e006389. — PubMed PMID: 25776043
- Su KY, Sharma M, Kim HJ, et al. Vasodilators for primary Raynaud's phenomenon. Cochrane Database Syst Rev. 2021;5(5):CD006687. — PubMed PMID: 33998674
- Hlavaty A, Dari L, Cracowski JL, et al. Drug-Induced Raynaud's Phenomenon and Underlying Mechanism: A Disproportionality Analysis From the World Health Organization Pharmacovigilance Database. Arthritis Rheumatol. 2026;78(4):985-992. — PubMed PMID: 41261736
- Gornik HL, Aronow HD, Goodney PP, et al. 2024 ACC/AHA/AACVPR/APMA/ABC/SCAI/SVM/SVN/SVS/SIR/VESS Guideline for the Management of Lower Extremity Peripheral Artery Disease. Circulation. 2024;149(24):e1313-e1410. — PubMed PMID: 38743805
- Del Galdo F, Lescoat A, Conaghan PG, et al. EULAR recommendations for the treatment of systemic sclerosis: 2023 update. Ann Rheum Dis. 2025;84(1):29-40. — PubMed PMID: 39874231
- Sharifzadeh A, Smith GP. An Evidence-Based Review of Perniosis (Chilblains): Therapeutic Strategies and Integration With Raynaud's Syndrome Management. Int J Dermatol. 2025;64(10):1781-1787. — PubMed PMID: 40272049
- Argobi Y. Trends and Associations of Chilblains Prevalence with Connective Tissue Diseases, Including COVID-19 Incidence. Clin Cosmet Investig Dermatol. 2025;18:339-344. — PubMed PMID: 39911214
PubMed Topic Searches
Featured Videos