Cluster Headaches
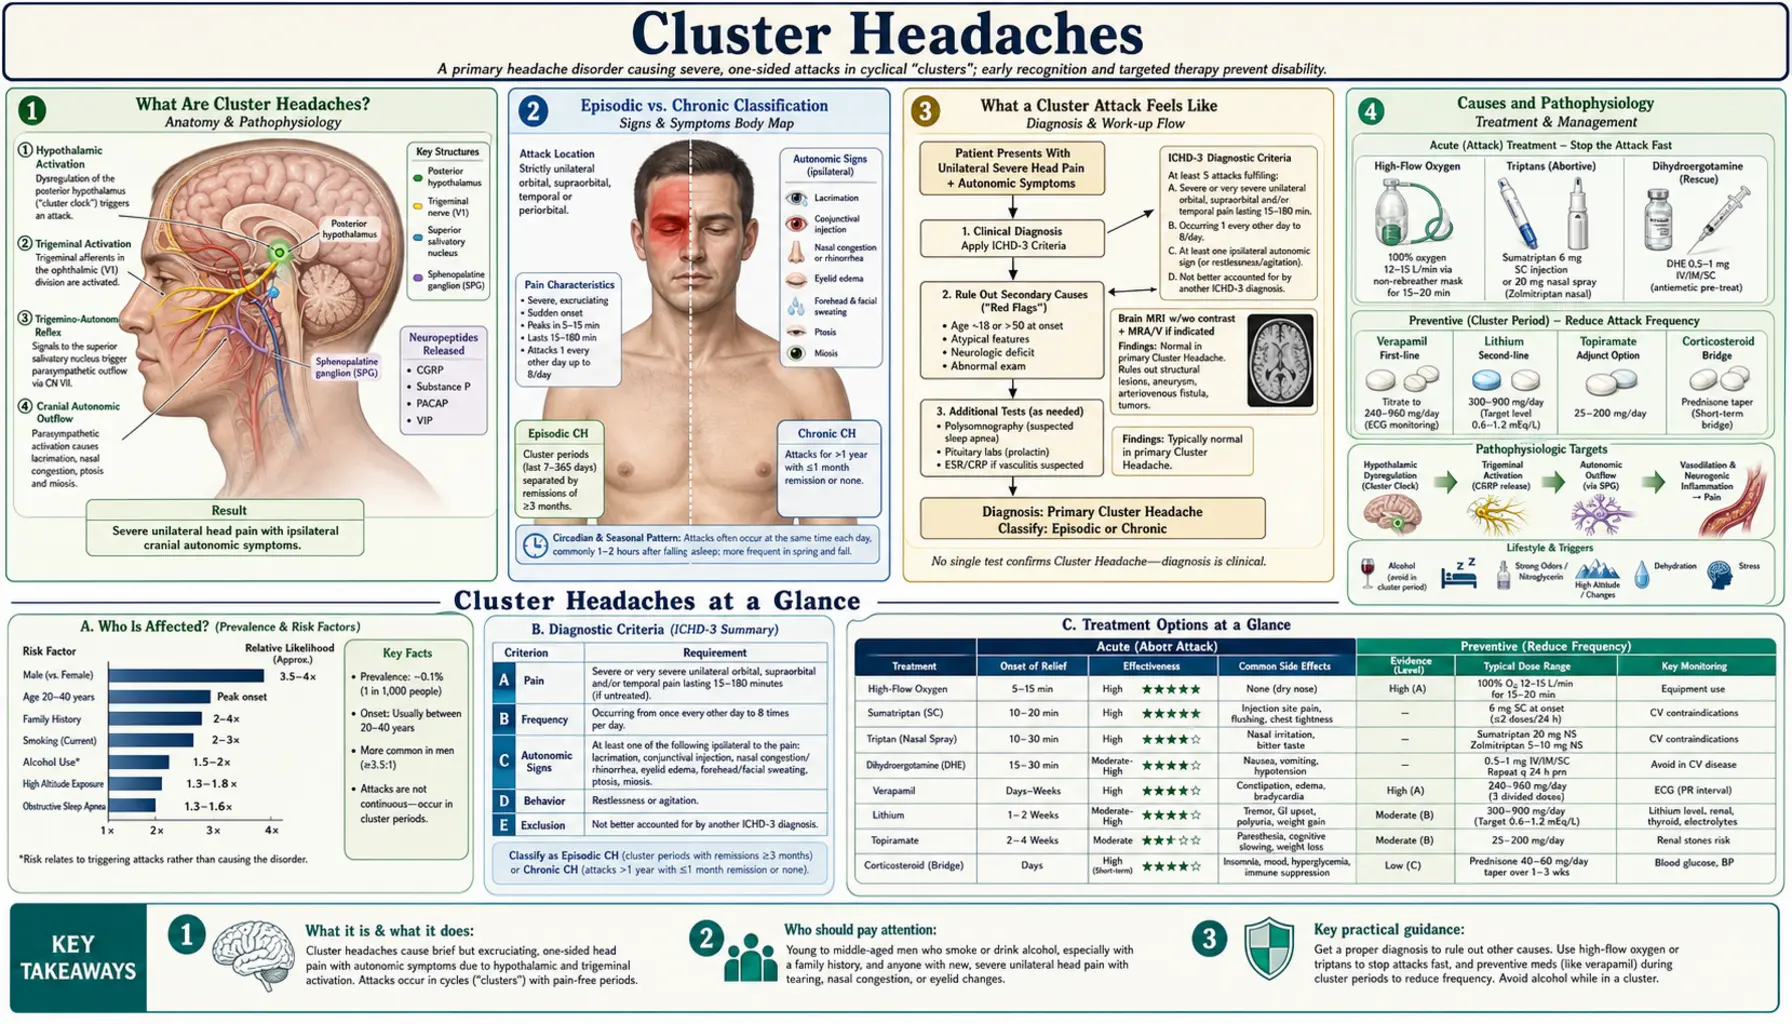
Table of Contents
What Cluster Headaches Are
Cluster headaches are one of the most painful conditions known to medicine — often called "suicide headaches" by patients because of the intensity. They occur in bouts (clusters) lasting weeks to months, separated by remission periods that can last months to years. Each individual attack is brief (15 minutes to 3 hours) but excruciatingly intense, striking one side of the head around or behind one eye.
About 1 in 1,000 people are affected; men are affected 3–5 times more often than women. Despite being classified as a primary headache disorder by the International Headache Society (IHS), cluster headaches are far less researched than migraine. Many patients wait years before receiving an accurate diagnosis, often being told they have migraines, sinus infections, or dental problems.
Episodic vs. Chronic Classification
Cluster headaches fall into two main types based on how remission periods behave:
- Episodic cluster headaches (most common, ~85%): Cluster periods typically last 6–12 weeks, often occurring at the same time of year — spring and autumn are common. Remission periods last at least 3 months between clusters. Many patients develop a reliable seasonal pattern over years.
- Chronic cluster headaches (~15%): Attacks occur for more than 1 year without a remission period of 3 months or longer. The chronic form is harder to treat and associated with greater disability. A small number of episodic patients transition to chronic over time.
The distinction matters for treatment planning. Episodic patients may be managed with short-course prevention during each cluster period. Chronic patients typically require long-term preventive therapy.
What a Cluster Attack Feels Like
The pain of a cluster headache is excruciating, unilateral, and strictly one-sided — centered in or around the eye, temple, or forehead. Patients most commonly describe it as a hot poker or ice pick being driven behind the eye. It builds rapidly to peak intensity within 15 minutes (unlike migraine, which builds over hours) and lasts anywhere from 15 minutes to 3 hours.
Several distinguishing features set cluster attacks apart:
- Restlessness and agitation: Patients pace, rock, or bang their head. This is the opposite of migraine, where lying still in a dark room helps. A person writhing in pain despite the severity is a strong diagnostic clue.
- Autonomic symptoms on the same side as the pain: drooping eyelid (ptosis), small pupil (miosis), tearing and red eye, nasal congestion or runny nose, forehead and facial sweating.
- Circadian pattern: Attacks frequently occur at the same time of day, often 1–2 hours after falling asleep. This "alarm clock" quality is a hallmark of cluster headaches.
- During a cluster period: 1–8 attacks per day are typical. Between attacks, patients feel completely normal — there is no migraine-like prodrome, postdrome, or ongoing sensitivity.
Causes and Pathophysiology
The exact cause of cluster headaches is not fully understood, but research has identified the key players:
- Hypothalamus as pacemaker: The posterior hypothalamus is implicated as the "biological clock" driving cluster headaches, explaining their remarkable circadian and circannual periodicity. Deep brain stimulation of this region reduces attack frequency in medically refractory patients. Neuroimaging during attacks consistently shows hypothalamic activation.
- Trigeminal nerve and autonomic arc: The trigeminal nerve (cranial nerve V) generates the intense pain, while its connection to the pterygopalatine ganglion via the cranial autonomic reflex arc produces the ipsilateral autonomic symptoms — tearing, nasal congestion, ptosis.
- Circadian hormone disruption: Changes in melatonin and cortisol secretion timing correlate with cluster periods. Melatonin levels are blunted during active cluster periods.
- Genetic predisposition: Family history increases risk: first-degree relatives of people with cluster headache had a 14-fold higher risk in a Danish study (1995) and a 39-fold higher risk in an Italian study (2001). The first genome-wide meta-analysis (2023, 4,777 patients) found 8 risk loci (regions of DNA), estimated that common genetic variants account for about 14.5% of the risk (heritability), found three loci shared with migraine, and found genetic evidence that heavier smoking is a cause of cluster headache. Variants in the HCRTR2 gene (orexin receptor 2) have been implicated, linking the disorder to the same hypothalamic wake-sleep signaling system.
Triggers
An important distinction: triggers only precipitate individual attacks during an active cluster period. They do not cause a cluster period to begin, and they do not trigger attacks during remission. This is a key diagnostic clue — a patient who drinks alcohol freely without headache during remission but gets an attack within 30 minutes of one drink during a cluster period almost certainly has cluster headaches.
Common triggers during a cluster period:
- Alcohol — the most reliable trigger; even small amounts can precipitate an attack within 30–60 minutes
- Nitroglycerin — used in research to reliably provoke attacks for study purposes
- Strong smells — perfumes, gasoline, paint fumes
- High altitude — reduced oxygen availability appears to lower the threshold
- Overheating — hot showers, exercise, hot weather
- Disrupted sleep schedule — shift work, jet lag, daytime napping during a cluster period
Diagnostic Criteria (ICHD-3)
The International Classification of Headache Disorders, 3rd edition (ICHD-3) defines cluster headache by the following criteria:
- At least five attacks fulfilling the criteria below
- Severe or very severe unilateral orbital, supraorbital, and/or temporal pain lasting 15–180 minutes (when untreated)
- Either or both of: (1) at least one of the following on the same side as the pain (ipsilateral): conjunctival injection and/or lacrimation (red, watering eye), nasal congestion and/or rhinorrhoea (runny nose), eyelid oedema (swelling), forehead and facial sweating, miosis and/or ptosis (small pupil, drooping eyelid); (2) a sense of restlessness or agitation
- Attacks occurring with a frequency between one every other day and 8 per day (a note adds that during part, but less than half, of the active time-course, attacks may be less frequent, less severe, or shorter or longer)
- Not better accounted for by another ICHD-3 diagnosis
Imaging: magnetic resonance imaging (MRI) of the brain with a pituitary protocol is commonly done at initial diagnosis to exclude secondary causes. Pituitary adenomas can cause pain and autonomic features that closely mimic cluster headaches, which is why this diagnosis is excluded before the headaches are treated as primary.
Acute Treatment
Because cluster attacks build to peak intensity within 15 minutes, oral medications are almost always too slow, so the acute treatments used are fast-acting ones:
- High-flow oxygen (first-line): In a 2009 randomized, placebo-controlled trial of 109 adults, 100% oxygen at 12 L/min by face mask for 15 minutes at the start of an attack made 78% of treated attacks pain-free (or adequately relieved) at 15 minutes, versus 20% with high-flow air, with no important adverse events. Flow rates of 12–15 L/min through a non-rebreather mask for 15–20 minutes are used in practice. It is safe, has no significant side effects, and can be used multiple times per day. It requires a prescription for a home oxygen concentrator or cylinder.
- Sumatriptan 6 mg subcutaneous injection: The fastest pharmaceutical option, effective in 74–80% of attacks within 15 minutes. The auto-injector form is practical during attacks. Sumatriptan nasal spray (20 mg) is slower but still effective.
- Zolmitriptan nasal spray 5 mg: An alternative to sumatriptan nasal spray with good evidence.
- Intranasal lidocaine 4–10%: Applied with the head tilted back and toward the affected side; can abort attacks within minutes by blocking the sphenopalatine ganglion. Underused but effective for patients who cannot tolerate triptans.
- Oral medications: Oral triptans, oral analgesics, and oral nonsteroidal anti-inflammatory drugs (NSAIDs) are too slow to be useful for attacks that peak in 15 minutes. This is a common reason cluster headache patients feel undertreated.
Preventive Treatment
Prevention is the cornerstone of cluster headache management — reducing attack frequency, shortening the cluster period, and in some cases preventing the next cluster period entirely:
- Verapamil (first-line prevention): 240–960 mg/day in divided doses; the most widely used preventive. Requires regular electrocardiogram (ECG) monitoring for cardiac conduction side effects (PR interval prolongation). Takes 2–3 weeks to reach full effect, which is why bridging therapy is often needed.
- Lithium carbonate: Particularly effective for chronic cluster headaches; requires regular monitoring of lithium blood levels, renal function, and thyroid function. Narrow therapeutic window.
- Corticosteroids (bridge/transition treatment): Prednisone 60 mg tapered over 2–3 weeks provides rapid short-term reduction in attacks while verapamil takes effect. Not suitable for long-term use due to side effects, but very useful for episodic patients at the start of a cluster period. The tested regimen comes from a 2021 German randomized, double-blind trial of 116 people with episodic cluster headache: prednisone 100 mg a day for 5 days, then tapered by 20 mg every 3 days, started alongside verapamil, gave a mean of 7.1 attacks in the first week versus 9.5 with placebo (p = 0.002), and side effects were reported by a similar share of each group (71%).
- Melatonin 10–15 mg at night: Evidence-supported and well-tolerated; leverages the hypothalamic circadian mechanism directly. Useful adjunct, especially for nocturnal attacks.
- Galcanezumab 300 mg injection: A monoclonal antibody against calcitonin gene-related peptide (CGRP), approved specifically for episodic cluster headaches — the first genuinely new treatment mechanism in decades. The label dose is 300 mg (three consecutive 100 mg injections under the skin) at the onset of the cluster period, then monthly until the end of the cluster period. In the 8-week trial behind the approval, weekly attacks fell by 8.7 from a baseline of about 17.5, versus 5.2 with placebo (a difference of 3.5 attacks a week, p = 0.036).
- Greater occipital nerve (GON) block: Ipsilateral corticosteroid injection at the base of the skull; rapid onset (within days), effective bridge therapy while oral preventives take effect.
- Deep brain stimulation (DBS): Reserved for medically refractory chronic cluster headache patients. Targets the posterior hypothalamus. Significant improvement in a meaningful proportion of otherwise untreatable patients.
Natural and Lifestyle Approaches
Several non-pharmaceutical strategies have meaningful evidence or strong patient-community support:
- Melatonin 10 mg nightly at bedtime: Nightly melatonin is used during cluster periods to reduce night-time attacks; the proposed mechanism is an effect on the hypothalamic circadian disruption underlying cluster headaches. Well-tolerated with minimal side effects.
- Capsaicin intranasal cream: Daily application to the ipsilateral nostril desensitizes trigeminal nociceptors over time. Small clinical trials show reduction in attack frequency. The initial burning is uncomfortable but subsides with continued use.
- Alcohol during cluster periods: Even small amounts reliably trigger attacks in most patients during an active cluster (ICHD-3 lists alcohol among the provoking factors), which is why patients describe complete avoidance during cluster periods as non-negotiable.
- Maintaining a strict sleep schedule: Stabilizing the sleep-wake cycle helps regulate the hypothalamic circadian disruption. Patients and clinicians describe avoiding daytime naps and keeping consistent bed and wake times during a cluster period.
- Vitamin D: Anti-inflammatory; some cluster headache patients report correlation between low vitamin D levels and more severe or prolonged cluster periods. Supplementation is generally considered low-risk, and patients use it particularly in northern latitudes.
- Omega-3 fatty acids: Anti-inflammatory properties may modestly reduce neuroinflammatory burden. No cluster-specific trials, but general evidence for headache reduction.
- Psilocybin (research context only): Cluster headache patient communities have self-reported benefit for decades, predating mainstream psychedelic research. In a small 2022 randomized, double-blind, placebo-controlled trial, three doses of psilocybin (0.143 mg/kg, about 5 days apart) cut attacks by 3.2 a week versus almost no change with placebo, but the difference was not statistically significant (p = 0.251; 14 participants analysed), and the authors describe the efficacy outcomes as negative, partly because of the small numbers. In a blinded extension phase (2024), 10 participants who repeated the dosing at least 6 months later had about 50% fewer attacks (from 18.4 to 9.8 a week, p = 0.013). Psilocybin was well tolerated in both. The mechanism may involve serotonin 5-HT2A receptor modulation in the hypothalamus. This is not a recommendation to self-treat — psilocybin remains a controlled substance, and use outside formal medical supervision carries significant risks.
Complications
- Suicidal ideation during attacks: The "suicide headache" label is not hyperbole — a significant proportion of cluster headache patients report suicidal thoughts during attacks due to the extreme pain. This is a known, documented phenomenon. This reaction is understood, and effective treatments exist. Emergency support resources are part of the management conversation in headache care.
- Depression and anxiety: Very high comorbidity rates, both as a consequence of recurrent severe pain and potentially sharing neurobiological mechanisms. Screening for them is part of cluster headache care.
- Medication overuse headache: Excessive reliance on acute treatments (particularly triptans) can paradoxically increase attack frequency and complicate the clinical picture.
- Cardiac effects from verapamil: High-dose verapamil (often required for prevention) carries real cardiac risks — bradycardia, heart block — requiring regular electrocardiogram monitoring.
- Occupational and social disability: Cluster periods lasting weeks to months with multiple daily attacks cause significant loss of productivity. The unpredictable, incapacitating nature of attacks makes sustained employment difficult for some patients.
- Social isolation from alcohol avoidance: During cluster periods, patients describe complete alcohol avoidance as necessary. For patients whose social lives involve alcohol, this creates meaningful social friction and isolation.
Key Research Papers
- Headache Classification Committee of the International Headache Society. ICHD-3. Cephalalgia. 2018. — PubMed PMID: 29368949
- Cohen AS, Burns B, Goadsby PJ. High-flow oxygen for treatment of cluster headache: a randomized trial. JAMA. 2009;302(22):2451-7. — PubMed PMID: 19996400
- Leone M, Franzini A, Broggi G, Bussone G. Hypothalamic deep brain stimulation for intractable chronic cluster headache: a 3-year follow-up. Neurol Sci. 2003;24 Suppl 2:S143-5. — PubMed PMID: 12811614
- Kudrow L. Response of cluster headache attacks to oxygen inhalation. Headache. 1981;21(1):1-4. — PubMed PMID: 7007285
- Goadsby PJ, Edvinsson L. Human in vivo evidence for trigeminovascular activation in cluster headache. Neuropeptide changes and effects of acute attacks therapies. Brain. 1994;117(Pt 3):427-34. — PubMed PMID: 7518321
- Sewell RA, Halpern JH, Pope HG Jr. Response of cluster headache to psilocybin and LSD. Neurology. 2006;66(12):1920-2. — PubMed PMID: 16801660
- Schindler EAD, Sewell RA, Gottschalk CH, et al. Exploratory investigation of a patient-informed low-dose psilocybin pulse regimen in the suppression of cluster headache: Results from a randomized, double-blind, placebo-controlled trial. Headache. 2022;62(10):1383-1394. — PubMed PMID: 36416492
- Schindler EAD, Sewell RA, Gottschalk CH, et al. Psilocybin pulse regimen reduces cluster headache attack frequency in the blinded extension phase of a randomized controlled trial. J Neurol Sci. 2024;460:122993. — PubMed PMID: 38581739
- Obermann M, Nägel S, Ose C, et al. Safety and efficacy of prednisone versus placebo in short-term prevention of episodic cluster headache: a multicentre, double-blind, randomised controlled trial. Lancet Neurol. 2021;20(1):29-37. — PubMed PMID: 33245858
- Winsvold BS, Harder AVE, Ran C, et al. Cluster Headache Genomewide Association Study and Meta-Analysis Identifies Eight Loci and Implicates Smoking as Causal Risk Factor. Ann Neurol. 2023;94(4):713-726. — PubMed PMID: 37486023
- Russell MB, Andersson PG, Thomsen LL. Familial occurrence of cluster headache. J Neurol Neurosurg Psychiatry. 1995;58(3):341-3. — PubMed PMID: 7897418
- Leone M, Russell MB, Rigamonti A, et al. Increased familial risk of cluster headache. Neurology. 2001;56(9):1233-6. — PubMed PMID: 11342697
PubMed Topic Searches
- PubMed: Cluster headache treatment
- PubMed: Cluster headache verapamil prevention
- PubMed: Cluster headache oxygen therapy
- PubMed: Trigeminal autonomic cephalalgias
- PubMed: Cluster headache pathophysiology hypothalamus
- PubMed: Galcanezumab cluster headache
- PubMed: The posterior hypothalamus in cluster headache
- PubMed: Symptomatic trigeminal autonomic cephalalgias
- PubMed: Orphanet Journal of Rare Diseases
Connections
- Pain & Allergy
- Migraine
- Chronic Pain
- Neuropathic Pain
- Trigeminal Neuralgia
- Depression
- Anxiety
- Insomnia
- Magnesium
- Vitamin D
- Headache — the symptom overview covering every head-pain type and its red flags.