Blood Urea Nitrogen (BUN): Reference Ranges and Interpretation
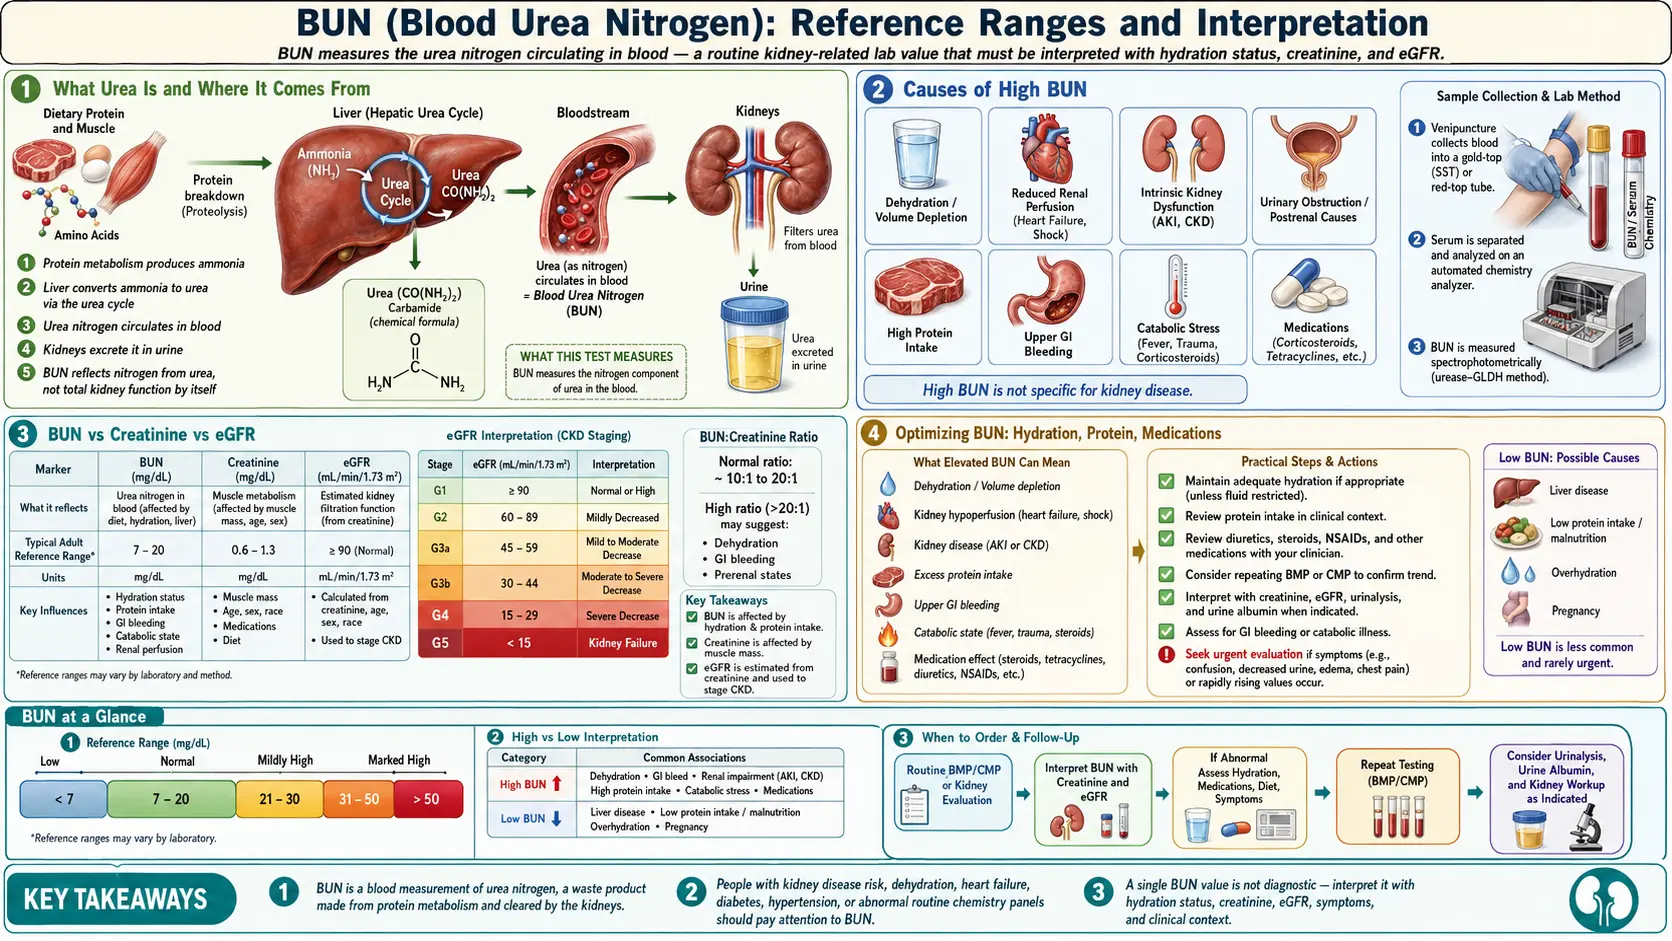
Blood urea nitrogen (BUN) measures the amount of nitrogen carried in blood urea — the principal nitrogen-containing waste product of protein breakdown. It is an inexpensive, routinely ordered kidney test and is often part of the comprehensive metabolic panel (MedlinePlus). Blood urea nitrogen is affected by many things besides kidney function — hydration, dietary protein, bleeding into the gut and tissue breakdown — which makes it less specific than creatinine; it is usually read together with creatinine and estimated glomerular filtration rate (eGFR).
Interactive Visualization Kidney Nephron — watch blood become urine Follow blood into the glomerulus and see filtration and reabsorption turn 180 litres of filtrate into urine — then toggle dehydration or diabetes. Launch →Table of Contents
- What Urea Is and Where It Comes From
- Reference Range
- Why Blood Urea Nitrogen Changes (Beyond Kidney Function)
- Causes of High Blood Urea Nitrogen
- Causes of Low Blood Urea Nitrogen
- Blood Urea Nitrogen-to-Creatinine Ratio
- Blood Urea Nitrogen vs Creatinine vs Estimated Glomerular Filtration Rate
- Preparation and Specimen
- Hydration, Protein and Medications: What the Research Reports
- Key Research Papers
- Connections
- Featured Videos
What Urea Is and Where It Comes From
When the body breaks down dietary or tissue protein, the resulting amino acids are deaminated — their nitrogen is split off as ammonia (NH₃). Ammonia is toxic, particularly to the brain, so the liver runs it through the urea cycle, converting it to urea (CH₄N₂O), which is non-toxic and water-soluble. The kidneys filter urea at the glomerulus; part of the filtered urea is reabsorbed along the tubule, and in the inner medullary collecting duct the urea transporters UT-A1 and UT-A3 respond to vasopressin (antidiuretic hormone) and to hydration status (Klein 2012). The rest is excreted in urine.
Blood urea nitrogen reports only the nitrogen portion of the urea molecule (each urea molecule contains two nitrogen atoms), so a blood urea nitrogen value is a smaller number than the urea concentration of the same sample. Some laboratories report serum urea, usually in mmol/L, instead of blood urea nitrogen — the UK Biobank study described below is one example.
Reference Range
Blood urea nitrogen (mg/dL) — MedlinePlus example range
MedlinePlus (U.S. National Library of Medicine) gives the normal result as generally 6 to 20 mg/dL and notes that normal values vary among laboratories; each lab prints its own range on the report. MedlinePlus also notes that blood urea nitrogen levels can vary by sex and usually increase with age. In pregnancy the glomerular filtration rate rises by about 50%, with a fall in serum creatinine, urea and uric acid (Cheung and Lafayette 2013).
Why Blood Urea Nitrogen Changes (Beyond Kidney Function)
Blood urea nitrogen is influenced by three processes:
- Production — how much nitrogen the liver is converting to urea. Raised by dietary protein, gastrointestinal bleeding, burns and other tissue breakdown, and cortisol excess; lowered by low-protein diets, malnutrition and advanced liver disease (impaired urea synthesis).
- Filtration — how much the glomerulus is removing per minute. Reduced by dehydration, heart failure, shock, kidney disease and urinary tract obstruction.
- Reabsorption — how much filtered urea returns to the bloodstream. Urea transport in the inner medulla is regulated by vasopressin and by hydration status (Klein 2012), one reason dehydration is traditionally described as raising blood urea nitrogen more than creatinine.
This is why blood urea nitrogen is usually read together with creatinine and estimated glomerular filtration rate rather than on its own; MedlinePlus describes it as only one measurement of kidney function.
Causes of High Blood Urea Nitrogen
MedlinePlus lists congestive heart failure, an excessive amount of dietary protein in the gastrointestinal tract, gastrointestinal bleeding, hypovolemia (dehydration), heart attack, kidney disease, kidney failure, shock, urinary tract obstruction, burns, certain medicines and a high-protein diet among the reasons for a higher-than-normal blood urea nitrogen. They fall into four broad groups.
Prerenal (reduced blood flow to the kidneys)
- Dehydration — listed by MedlinePlus as hypovolemia; vasopressin-regulated urea transport responds to hydration status (Klein 2012).
- Heart failure — in 541 patients admitted for decompensated heart failure, the upper quartile of blood urea nitrogen carried an adjusted relative risk of death of 2.3 compared with the lower quartiles, while creatinine and estimated creatinine clearance were not significant predictors after adjustment; the authors wrote that elevated blood urea nitrogen probably reflects renal hypoperfusion (Aronson 2004).
- Hemorrhage, gastrointestinal (GI) bleed — volume loss plus, in the traditional explanation, protein from blood released into the gut.
- Shock and heart attack — both listed by MedlinePlus.
- Nonsteroidal anti-inflammatory drugs (NSAIDs) — KDIGO 2024 describes them as lowering glomerular filtration rate (GFR) by reducing prostaglandin-dependent kidney blood flow.
Renal (kidney itself is damaged)
- Acute kidney injury (any cause) — KDIGO 2012 defines acute kidney injury (AKI) by a rise in serum creatinine or a fall in urine output, not by blood urea nitrogen (Kellum and Lameire 2013)
- Chronic kidney disease (CKD) — classified by KDIGO by cause, glomerular filtration rate category and albuminuria category (Levin 2024; KDIGO 2024)
- Glomerulonephritis, pyelonephritis and acute tubular necrosis (all listed by MedlinePlus)
- Polycystic kidney disease
Postrenal (obstruction)
- Bladder outlet obstruction (benign prostatic hyperplasia (BPH), prostate cancer)
- Ureteral obstruction (stones, retroperitoneal fibrosis, malignancy)
- Neurogenic bladder
Increased urea production (more nitrogen to excrete)
- High protein intake — in a 12-week randomized trial in women aged 40–77 (83 in the complete-case analysis) assigned to 0.8, 1.6 or 2.2 g/kg/day of protein with resistance or concurrent training, urea, blood urea nitrogen and the blood urea nitrogen-to-creatinine ratio increased, and responses differed mainly between 0.8 g/kg/day and the two higher intakes; the authors noted that changes in estimated glomerular filtration rate estimates do not establish organ injury (Bagheri 2026).
- Corticosteroids — traditionally listed through increased protein breakdown. In an observational study of 151 patients with Cushing’s syndrome or subclinical Cushing’s syndrome (cortisol excess) and 78 controls, the blood urea nitrogen-to-creatinine ratio was higher than in controls; the authors called for larger studies (Yarkutay Turkkan 2026).
- Burns and certain medicines — listed by MedlinePlus.
Causes of Low Blood Urea Nitrogen
MedlinePlus lists liver failure, a low-protein diet, malnutrition and over-hydration among the reasons for a lower-than-normal blood urea nitrogen.
- Low protein intake — a low-protein diet and malnutrition. In the UK Biobank, vegans had lower average serum urea than regular meat eaters (adjusted geometric means 4.21 vs 5.36 mmol/L) (Tong 2021).
- Liver disease — MedlinePlus notes that in people with liver disease the blood urea nitrogen level may be low even if the kidneys are normal. In a small tracer study, the urea synthesis rate was lower in 7 patients with end-stage cirrhosis than in 6 healthy controls (Shangraw 1999).
- Pregnancy — the glomerular filtration rate rises by about 50% and serum urea falls (Cheung and Lafayette 2013).
- Over-hydration — listed by MedlinePlus.
MedlinePlus notes that abnormal results don’t always mean a medical condition that needs treatment.
Blood Urea Nitrogen-to-Creatinine Ratio
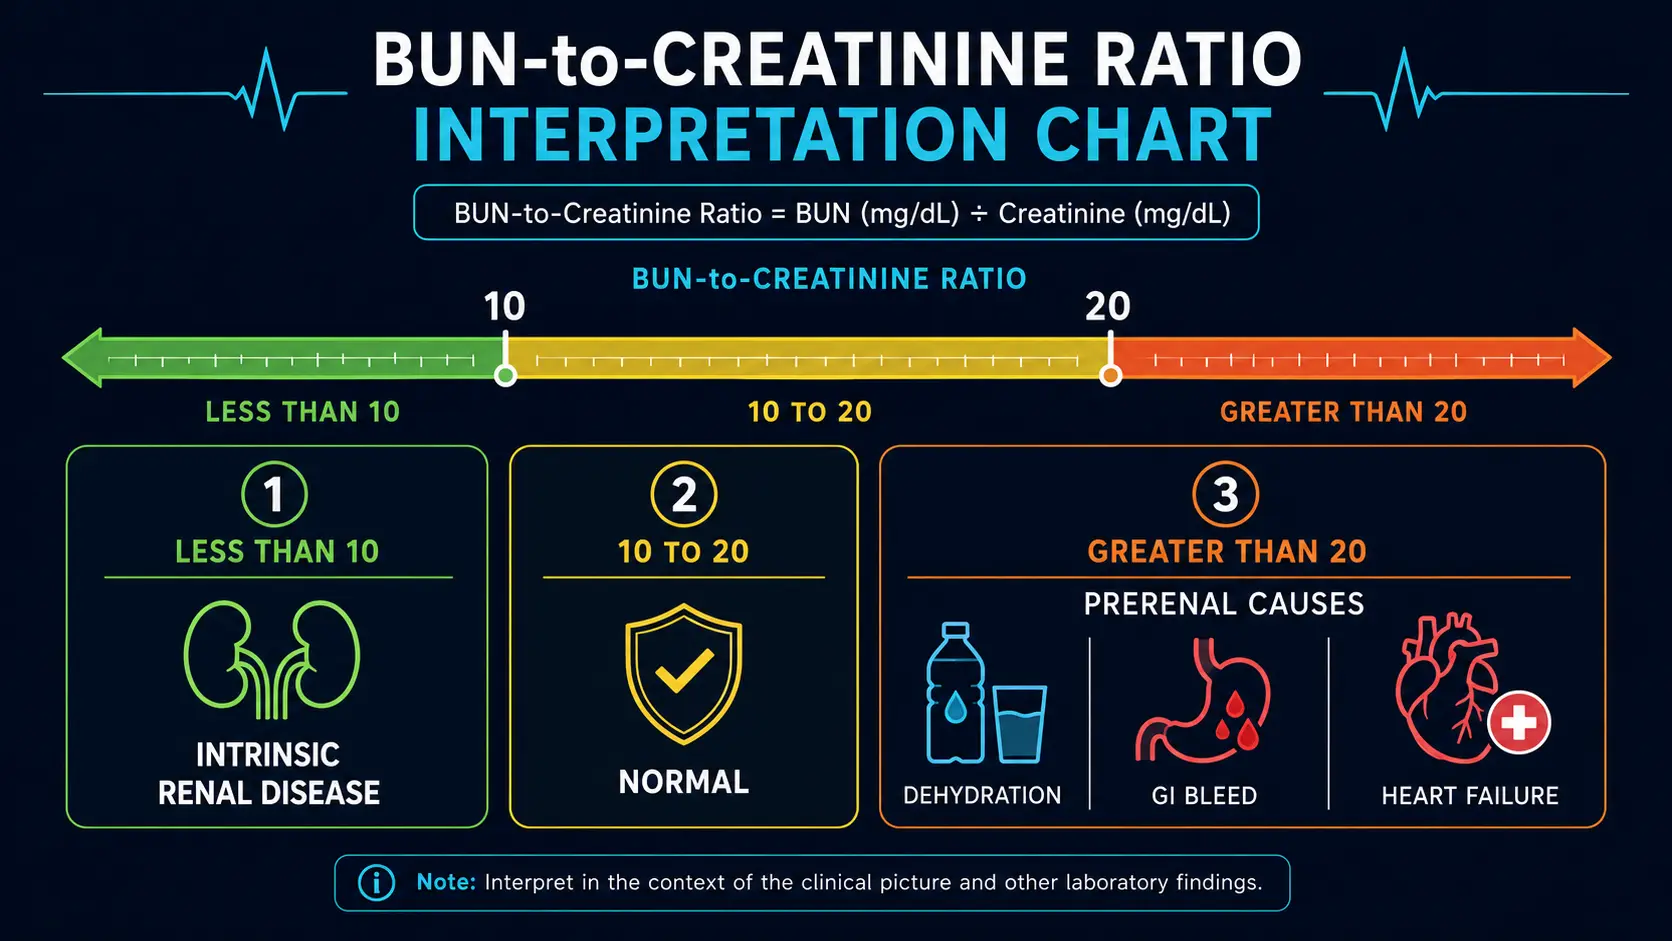
Dividing blood urea nitrogen by creatinine (both in mg/dL) gives a ratio that is traditionally used to sort kidney dysfunction into three broad patterns:
Blood urea nitrogen : Creatinine ratio — traditionally taught cutoffs (mg/dL : mg/dL)
In the traditional interpretation, a high blood urea nitrogen-to-creatinine ratio with normal creatinine points to a prerenal cause — the kidneys themselves are healthy but are working against poor perfusion (dehydration, blood loss, heart failure) or an unusually high nitrogen load (gastrointestinal bleed releasing protein into the gut, very-high-protein diet, corticosteroid-induced catabolism). A low ratio with elevated creatinine is traditionally read as intrinsic renal disease (the kidneys themselves are damaged), severe malnutrition, or advanced liver disease (impaired urea synthesis).
Studies have questioned how well the ratio performs. In a retrospective study of 20,126 hospital patients, about half of those with acute kidney injury had a ratio above 20 — the traditional threshold for prerenal azotemia — and they had higher, not lower, hospital mortality than patients with a lower ratio; the authors concluded that the findings do not support the ratio as a marker of prerenal azotemia (Uchino 2012). In 1,103 emergency-department patients with acute kidney injury, the ratio did not differ between prerenal and intrinsic acute kidney injury and had no capacity to tell them apart (area under the ROC curve 0.5) (Manoeuvrier 2017).
In gastrointestinal bleeding, the ratio has been studied as a clue to where the bleeding comes from. A systematic review found that a serum urea nitrogen-to-creatinine ratio above 30 increased the likelihood of an upper gastrointestinal bleed (summary likelihood ratio 7.5) (Srygley 2012). A 2026 meta-analysis of 17 studies reported, at a threshold above 30, a pooled sensitivity of 38.8% and specificity of 89.3% for upper versus lower gastrointestinal bleeding, and described the ratio’s diagnostic accuracy as moderate (Simadibrata 2026).
Blood Urea Nitrogen vs Creatinine vs Estimated Glomerular Filtration Rate
Each test brings something different:
- Blood urea nitrogen — affected by hydration, protein intake, gastrointestinal bleeding and tissue breakdown as well as by filtration
- Creatinine — the main routine filtration marker. Its relationship with glomerular filtration rate is curved, so in the higher glomerular filtration rate range a large fall in filtration produces only a small rise in creatinine, which can stay inside the reference range (Perrone 1992)
- Estimated glomerular filtration rate — calculated from creatinine, or from creatinine and cystatin C together; KDIGO uses glomerular filtration rate to assign the G1–G5 categories (KDIGO 2024)
- Cystatin C — a second filtration marker that depends far less on muscle mass and diet. The NKF-ASN Task Force and KDIGO 2024 call for wider use of cystatin C to confirm estimated glomerular filtration rate (Delgado 2021; Levin 2024)
The KDIGO 2024 guideline advises testing people at risk for, and with, chronic kidney disease using both a urine albumin measurement and an assessment of GFR (KDIGO 2024).
Preparation and Specimen
- Fasting: MedlinePlus states that usually no special preparation is needed, but fasting for several hours may be required when other tests are ordered on the same blood sample
- Sample: a blood sample taken from a vein in the arm
- Hydration: dehydration is listed among causes of a higher blood urea nitrogen and over-hydration among causes of a lower one (MedlinePlus)
- Protein intake: a high-protein diet is listed among causes of a higher blood urea nitrogen (MedlinePlus)
Hydration, Protein and Medications: What the Research Reports
When blood urea nitrogen is mildly elevated and estimated glomerular filtration rate is normal, the factors described above are the ones usually considered:
- Hydration — dehydration raises blood urea nitrogen and over-hydration lowers it (MedlinePlus).
- Protein intake — blood urea nitrogen rose at higher protein intakes in the 12-week trial described above; its authors noted that the changes in estimated glomerular filtration rate estimates do not establish organ injury or long-term safety (Bagheri 2026).
- Medications — MedlinePlus lists certain medicines among causes of a higher BUN. KDIGO 2024 describes nonsteroidal anti-inflammatory drugs as lowering glomerular filtration rate by reducing prostaglandin-dependent kidney blood flow, and its table of nephrotoxic medicines includes lithium and aminoglycosides.
- Heart failure — in decompensated heart failure, a higher blood urea nitrogen was associated with higher mortality independently of creatinine (Aronson 2004).
When blood urea nitrogen and creatinine are both elevated, the Creatinine and estimated glomerular filtration rate pages describe those tests; KDIGO 2024 pairs urine albumin measurement with glomerular filtration rate assessment in evaluating chronic kidney disease. Decisions about testing and treatment belong with a clinician.
Key Research Papers
- Uchino S, Bellomo R, Goldsmith D (2012). The meaning of the blood urea nitrogen/creatinine ratio in acute kidney injury. Clinical Kidney Journal 5(2):187-191 — PubMed PMID: 29497527
- Manoeuvrier G, Bach-Ngohou K, Batard E, et al. (2017). Diagnostic performance of serum blood urea nitrogen to creatinine ratio for distinguishing prerenal from intrinsic acute kidney injury in the emergency department. BMC Nephrology 18(1):173 — PubMed PMID: 28545421
- Srygley FD, Gerardo CJ, Tran T, et al. (2012). Does this patient have a severe upper gastrointestinal bleed? JAMA 307(10):1072-9 — PubMed PMID: 22416103
- Simadibrata DM, Koo TH, Murlidhar M, et al. (2026). Blood urea nitrogen-to-creatinine ratio to differentiate upper from lower gastrointestinal bleeding: a systematic review and meta-analysis. Journal of Gastroenterology and Hepatology 41(2):477-487 — PubMed PMID: 41555211
- Aronson D, Mittleman MA, Burger AJ (2004). Elevated blood urea nitrogen level as a predictor of mortality in patients admitted for decompensated heart failure. American Journal of Medicine 116(7):466-73 — PubMed PMID: 15047036
- Kellum JA, Lameire N; KDIGO AKI Guideline Work Group (2013). Diagnosis, evaluation, and management of acute kidney injury: a KDIGO summary (Part 1). Critical Care 17(1):204 — PubMed PMID: 23394211
- Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group (2024). KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease. Kidney International 105(4S):S117-S314 — PubMed PMID: 38490803
- Levin A, Ahmed SB, Carrero JJ, et al. (2024). Executive summary of the KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease: known knowns and known unknowns. Kidney International 105(4):684-701 — PubMed PMID: 38519239
- Delgado C, Baweja M, Crews DC, et al. (2021). A unifying approach for GFR estimation: recommendations of the NKF-ASN Task Force on Reassessing the Inclusion of Race in Diagnosing Kidney Disease. Journal of the American Society of Nephrology 32(12):2994-3015 — PubMed PMID: 34556489
- Perrone RD, Madias NE, Levey AS (1992). Serum creatinine as an index of renal function: new insights into old concepts. Clinical Chemistry 38(10):1933-53 — PubMed PMID: 1394976
- Klein JD, Blount MA, Sands JM (2012). Molecular mechanisms of urea transport in health and disease. Pflügers Archiv 464(6):561-72 — PubMed PMID: 23007461
- Cheung KL, Lafayette RA (2013). Renal physiology of pregnancy. Advances in Chronic Kidney Disease 20(3):209-14 — PubMed PMID: 23928384
- Bagheri R, Ghobadi H, Kargarfard M, et al. (2026). Effects of 12 weeks of resistance and concurrent training with graded protein intakes on lipid profile, kidney and liver biomarkers in middle-aged to older women. European Journal of Nutrition 65(7):253 — PubMed PMID: 42742755
- Yarkutay Turkkan C, Canat MM, Erhan Gol H, et al. (2026). Blood urea nitrogen/creatinine ratio in Cushing’s syndrome: associations with disease status and postoperative changes. International Journal of Endocrinology 2026:2517065 — PubMed PMID: 42291844
- Tong TYN, Perez-Cornago A, Bradbury KE, et al. (2021). Biomarker concentrations in white and British Indian vegetarians and nonvegetarians in the UK Biobank. Journal of Nutrition 151(10):3168-3179 — PubMed PMID: 34132352
- Shangraw RE, Jahoor F (1999). Effect of liver disease and transplantation on urea synthesis in humans: relationship to acid-base status. American Journal of Physiology 276(5):G1145-52 — PubMed PMID: 10330005
PubMed Topic Searches
- BUN and kidney function — PubMed search
- BUN-to-creatinine ratio in prerenal azotemia — PubMed search
- Urea cycle and protein metabolism — PubMed search
- BUN as a prognostic marker in heart failure — PubMed search
- High-protein diet and BUN — PubMed search
- Upper GI bleed and BUN/Cr ratio — PubMed search