⚠ Evidence warning: Clinical trials or other evidence do not support the claim that sumatriptan is the most effective drug for stopping a cyclic vomiting episode. This page keeps it as a report of what people, websites or other media say.
Cyclic Vomiting Syndrome
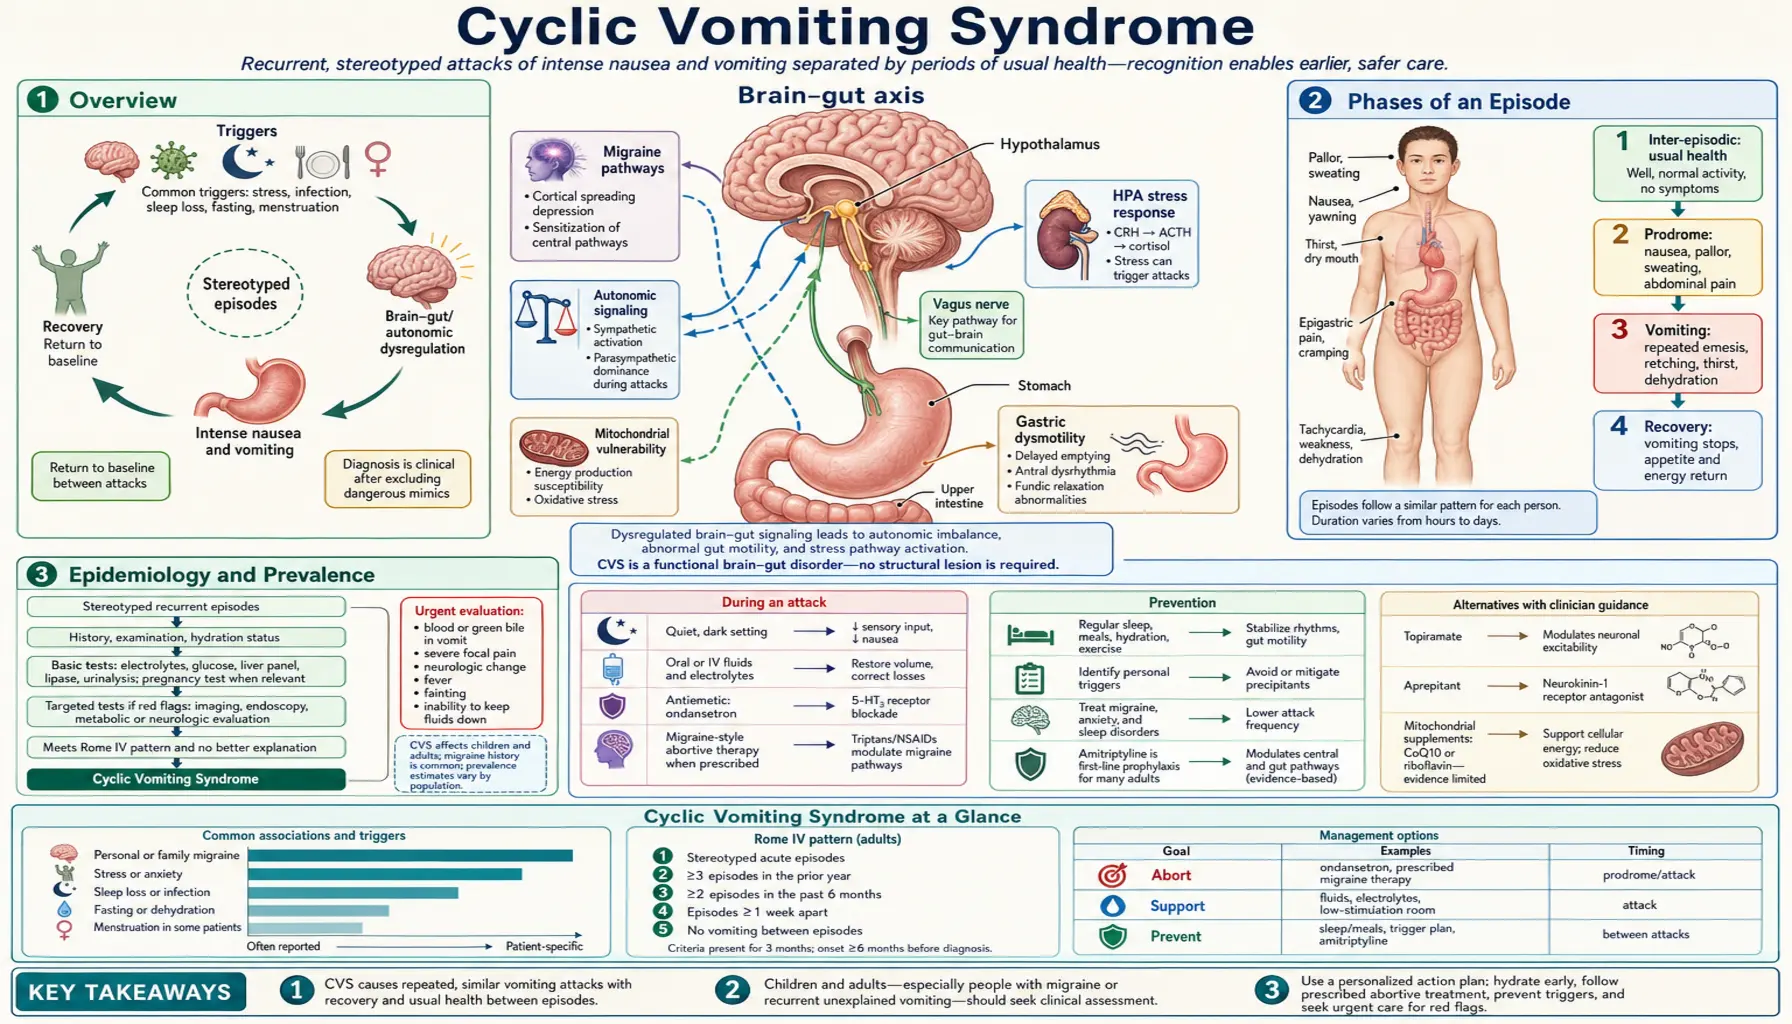
Table of Contents
1. Overview
Cyclic Vomiting Syndrome (CVS) is a functional gut-brain disorder characterized by recurrent, stereotyped episodes of intense nausea and vomiting that are separated by completely symptom-free intervals. Each episode follows a predictable personal pattern — the same warning signs, the same severity, the same duration — and then resolves entirely, leaving the person feeling completely normal between attacks. This stereotypy is both the hallmark diagnostic feature and one of the most puzzling aspects of the condition.
CVS belongs to the family of migrainous disorders. The 2019 adult guideline reports migraine headaches in 13% to 70% of adults with CVS, and a first- or second-degree relative with migraines or migraine variants in 57% of adult CVS patients, and CVS is now understood as a gut-brain axis disorder in which the migraine-generating mechanisms of the central nervous system manifest in the gastrointestinal tract rather than — or in addition to — the head. Many children with CVS go on to develop classic migraine headaches as adults, and the two conditions respond to the same prophylactic medications.
Despite its significant burden — episodes can last days, require emergency hospitalization, and cause chronic dehydration — CVS remains underdiagnosed. The average delay between symptom onset and correct diagnosis exceeds 3 years. Clinicians unfamiliar with the condition often pursue repeated unnecessary endoscopies and imaging studies before recognizing the characteristic episodic pattern.
2. Phases of an Episode
A CVS episode unfolds in three clinically distinct phases. The timing and characteristics of each phase are remarkably consistent for a given individual across different episodes, which is why recognizing the patient's personal pattern is central to both diagnosis and management.
Phase 1: Prodrome (30–60 Minutes)
The prodrome signals that an episode is imminent. It typically lasts 30 to 60 minutes and gives patients and families a narrow window to initiate abortive therapy. Key features include:
- Intense nausea — often described as building waves of sickness rather than constant queasiness
- Pallor — a characteristic blanching of the skin, particularly notable in children
- Profuse sweating (diaphoresis) — cold sweats out of proportion to the degree of physical activity
- Lethargy and social withdrawal — children often become quiet and stop playing; adults retreat to a darkened room
- Abdominal pain — a cramping or burning sensation, often periumbilical, that intensifies through the prodrome
- Photophobia and phonophobia — sensitivity to light and sound, mirroring migraine prodrome features
Recognizing the prodrome is clinically critical because triptans and antiemetics administered during this phase can abort some episodes entirely before the vomiting phase begins.
Phase 2: Vomiting Phase (Hours to Days)
The vomiting phase is the defining and most debilitating part of the episode. Vomiting is intense, forceful, and relentless — occurring up to 6 times per hour at peak intensity, compared to the 1–2 episodes per hour typical of gastroenteritis. The median episode duration is approximately 5 days in adults (range: a few hours to more than 10 days), though pediatric episodes tend to be somewhat shorter.
During this phase, patients typically:
- Are incapacitated and unable to eat, drink, or stand
- Seek a dark, quiet, cool room (heightened sensory sensitivity identical to migraine)
- Experience severe abdominal pain and retching even when nothing remains in the stomach (dry heaving)
- Show signs of progressive dehydration: dry mucous membranes, decreased urine output, orthostatic hypotension
- Often require emergency department visits for intravenous fluid replacement and antiemetic therapy
A characteristic but underappreciated feature of the vomiting phase is its predictable onset time. Many patients find their episodes begin at the same hour of day — frequently in the early morning hours (2–4 AM) — following their personal biological clock. This circadian pattern is consistent across episodes for the same patient and is another diagnostic clue distinguishing CVS from other causes of recurrent vomiting.
Phase 3: Recovery Phase
The recovery phase begins when vomiting ceases and the patient can tolerate oral intake. Recovery is not instantaneous — it typically takes 24–48 hours of gradual rehydration, light foods, and rest before the person feels fully normal. However, the defining feature of recovery from a CVS perspective is its completeness: patients return to their exact baseline state of health with no residual nausea, pain, or functional impairment between episodes. This symptom-free interlude is the feature that most clearly distinguishes CVS from chronic conditions such as gastroparesis or functional dyspepsia, where symptoms persist continuously at varying intensity.
3. Epidemiology and Prevalence
CVS was historically considered a rare childhood disorder, but large-scale population studies have established it as more prevalent than previously recognized. In adults, the Rome Foundation Global Study, an internet survey of 54,127 adults in 26 countries using the Rome IV criteria, found a pooled prevalence of 0.3% (95% confidence interval 0.3% to 0.4%), highest in Brazil at 1%. United States insurance claims for 2019 showed a diagnosis in 16.7 (commercial and Medicare) and 42.9 (Medicaid) people per 100,000. In children, population-based estimates suggest a prevalence of approximately 1.9–2.3%, with a peak incidence in the school-age years (5–12 years old).
Older adult series gave mixed results on sex, but in the worldwide survey women were more often affected (odds ratio 1.52), and United States claims rates were also higher among women and girls. The same survey linked CVS with depression (odds ratio 3.14) and anxiety (odds ratio 1.79). In the United States claims data, only 32% to 35% of newly diagnosed people had a prescription for a preventive drug within 30 days of diagnosis. In children, boys are affected slightly more often than girls. The condition is diagnosed across all ethnic groups, though published series may underrepresent non-White populations due to diagnostic access barriers.
The true prevalence is almost certainly higher than reported figures, because:
- The diagnosis requires recognizing the stereotyped episodic pattern, which can take years of repeated presentations to become apparent
- Episodes are frequently attributed to acute gastroenteritis, food poisoning, or psychosomatic causes
- Many patients normalize their pattern ("I always get these sick spells a few times a year") without seeking specialized evaluation
- CVS in adults was only formally characterized and given diagnostic criteria in the late 2000s, long after pediatric CVS was recognized
Economically, CVS imposes a substantial burden. Emergency department visits average 2–5 per patient per year, each generating hospitalization costs for intravenous (IV) fluids, antiemetics, and diagnostic workup. School absenteeism in children and workplace absenteeism in adults are major impacts; one study found that adults with CVS missed a mean of 22 days of work per year attributable to episodes.
4. Pathophysiology
The pathophysiology of CVS is incompletely understood, but converging evidence points to dysfunction at the intersection of the central nervous system, autonomic nervous system, hypothalamic-pituitary-adrenal (HPA) axis, and mitochondrial energy metabolism — all consistent with its classification as a disorder of the gut-brain axis.
Gut-Brain Axis and Migraine Overlap
CVS shares a mechanistic kinship with migraine at multiple levels. Both conditions feature episodic attacks, stereotyped symptom patterns, similar triggers (stress, hormonal changes, certain foods, sleep disruption), identical autonomic features (pallor, diaphoresis, nausea, photophobia), and response to the same treatments (triptans, amitriptyline, topiramate). The leading hypothesis is that CVS represents a migraine variant in which the brain's migraine-generating cascade activates the vomiting center in the brainstem (area postrema) and dorsal vagal complex rather than — or in addition to — the cortical spreading depression that underlies visual aura and headache.
The trigeminovascular system, central sensitization pathways, and serotonergic neurotransmission that are dysregulated in migraine are similarly implicated in CVS. The high co-occurrence of CVS and migraine (in adults with CVS, migraine headaches in 13% to 70% and an affected close relative in 57%) and the frequent transition from childhood CVS to adult migraine headaches support shared underlying neurobiology.
Corticotropin-Releasing Factor (CRF) and the Hypothalamic-Pituitary-Adrenal Axis
Physical or emotional stress — the most common CVS trigger — activates the hypothalamus to release corticotropin-releasing factor (CRF), which coordinates the stress response via the hypothalamic-pituitary-adrenal axis (stimulating cortisol release) and directly activates CRF receptors in the brainstem vomiting centers and the enteric nervous system. In susceptible individuals with CVS, this CRF-driven stress circuit appears to be dysregulated — with exaggerated or sustained CRF signaling translating acute stressors into the full vomiting cascade. This mechanism explains why episodes cluster during periods of psychological stress, illness, or physiological stress (menstruation, exercise, sleep deprivation).
Mitochondrial Dysfunction
A subset of CVS patients — particularly those with maternal inheritance patterns and additional features suggesting mitochondrial disease (exercise intolerance, developmental delays, myopathy) — carry mitochondrial DNA variants affecting energy metabolism. A 2005 study by Boles et al. took clinical interviews about the family histories of 80 people with CVS and found maternal inheritance suggested in 52% to 54% of the subgroups studied. DNA sequencing came later: in Zaki et al. (2009), the 16519T variant was found in 21 of 30 CVS subjects (70%) against 27% of controls. There is substantial overlap between CVS and mitochondrial disorders.
The mitochondrial hypothesis proposes that cells with high energy demands (neurons, enterocytes, cardiomyocytes) in CVS patients have impaired mitochondrial oxidative phosphorylation. During metabolic stress — illness, fasting, intense exercise, hormonal fluctuations — energy depletion in these cells triggers the vomiting cascade. This hypothesis explains the efficacy of mitochondrial cofactors (coenzyme Q10, riboflavin/B2, L-carnitine) as CVS prophylaxis, as these agents support mitochondrial respiratory chain function.
Autonomic Nervous System Dysregulation
CVS patients demonstrate measurable autonomic dysfunction during both episodes and interictal periods. Tilt-table testing reveals orthostatic intolerance in many patients. Heart rate variability analysis shows reduced parasympathetic tone. Skin conductance studies confirm heightened sympathetic reactivity. The sympathetic surges that accompany emotional or physical stress may directly trigger CRF release and activate the brainstem vomiting centers, representing the neurological bridge between environmental triggers and episodes.
5. Triggers
Identifying and managing personal triggers is a cornerstone of CVS prevention. Triggers vary among patients, but certain categories recur consistently across the literature:
Psychological and Physical Stress
Stress — both emotional (anxiety, excitement, conflict, grief, anticipatory excitement before holidays) and physical (illness, overexertion, travel, sleep deprivation) — is the most commonly reported trigger, identified in 50–80% of patients. Importantly, positive excitement (birthday parties, holidays, school events) triggers episodes as commonly as negative stress, reflecting the shared hypothalamic-pituitary-adrenal axis activation regardless of valence.
Menstrual Cycle
In women of reproductive age, episodes frequently cluster perimenstrually — in the days preceding or during menstruation. This pattern, sometimes called menstrual CVS, reflects the hormonal triggers of estrogen and progesterone fluctuations, which also trigger migraine attacks in many women. Recognition of this pattern can guide contraceptive strategies (hormonal suppression of the menstrual cycle) as an adjunct to standard prophylaxis.
Infections
Viral or bacterial illnesses — particularly upper respiratory infections and gastroenteritis — frequently precipitate CVS episodes. The combination of systemic inflammation, fever, and hypothalamic-pituitary-adrenal axis activation during infection lowers the threshold for episode initiation. This creates a confusing clinical picture, as the vomiting of a CVS episode triggered by viral illness can be indistinguishable from the vomiting of the illness itself during the acute phase.
Dietary Triggers
Specific foods trigger episodes in a subset of patients. The most commonly implicated are:
- Cheese — particularly aged cheeses high in tyramine
- Chocolate — a classical migraine trigger, shared with CVS
- Monosodium glutamate (MSG) — food additive found in processed foods, fast food, and Asian cuisine
- Caffeine — both excess intake and caffeine withdrawal
- Fasting or prolonged intervals between meals — metabolic stress from hypoglycemia is a potent trigger, particularly in children
Sleep Disruption
Insufficient sleep, sleep deprivation, and disrupted circadian rhythms consistently trigger episodes. The mechanism likely involves both hypothalamic-pituitary-adrenal axis dysregulation and melatonin/cortisol rhythm disruption. The characteristic early-morning episode onset in many CVS patients may relate to the nadir of cortisol suppression and the peak of melatonin withdrawal in the pre-dawn hours.
Cannabis
Chronic heavy cannabis use is a specific and increasingly recognized CVS trigger that produces a distinct clinical entity — Cannabis Hyperemesis Syndrome — described in detail in the next section.
Other Triggers
Additional reported triggers include: car travel and motion sickness, intense exercise, hot weather and heat exposure, overheating, strong odors, and allergic reactions. Many patients can identify their personal trigger profile with a symptom diary.
6. Cannabis Hyperemesis Syndrome
Cannabis Hyperemesis Syndrome (CHS) is a distinct clinical entity — a form of cyclic vomiting caused specifically by chronic, heavy cannabis use. The authors of the 2004 series that first described it concluded that cannabis was the cause in all their cases, while a 2019 review says most of the data make it hard to tell whether chronic cannabis use is causal, merely a clinical association with CVS, or unmasks or triggers symptoms in people already predisposed to CVS. As legalization and normalization of cannabis have expanded, CHS has emerged as a significant and frequently missed diagnosis in emergency departments. Understanding the distinction between CHS and classic CVS — and the features linked to CHS — is essential for appropriate management.
How Often It Reaches Emergency Departments
United States doctors gained a dedicated diagnosis code for CHS on October 1, 2025. Visits involving CHS went from 3.35 per 10,000 emergency department visits in September 2025 to 11.26 in October 2025, and the Centers for Disease Control and Prevention report says the jump might partly reflect better recognition and coding rather than a true rise in illness. In Ontario, Canada, monthly emergency visits for CHS rose 13-fold, from 0.26 per 100,000 people in January 2014 to 3.43 in June 2021.
Definition and Mechanism
CHS occurs in a subset of long-term, daily or near-daily cannabis users who develop paradoxical hyperemesis despite cannabis's well-known acute antiemetic properties. The mechanism involves desensitization and downregulation of cannabinoid CB1 receptors in the enteric nervous system and brainstem with chronic heavy exposure. Acutely, cannabis activates CB1 receptors to suppress nausea; chronically, receptor downregulation reverses this effect, and the sympathomimetic and thermoregulatory properties of cannabinoids come to dominate. High-potency tetrahydrocannabinol (THC) products (concentrates, dabs, edibles) accelerate the development of CHS.
The thermoregulatory aspect is central to CHS pathophysiology. Hypothalamic CB1 receptors normally help maintain core body temperature; their dysregulation in CHS leads to impaired thermoregulation, causing patients to feel subjectively overheated during episodes. This drives the compulsive hot showering behavior that is the clinical hallmark of CHS.
The Hot Shower Sign
The most clinically distinctive feature linked to CHS is compulsive bathing in very hot water for prolonged periods during vomiting episodes. Patients report that immersion in scalding-hot showers or baths provides dramatic, near-complete temporary relief of nausea and vomiting, sometimes lasting 20–30 minutes after emerging. They return to the shower repeatedly throughout the episode — sometimes spending hours per day bathing. This behavior is not proof of CHS (not pathognomonic, in the words of the 2019 review): it was noted in 71.5% of 271 patients in published CHS case series, and it is also seen in about 50% of people with CVS who do not use cannabis.
The mechanism appears to be thermal cutaneous stimulation activating transient receptor potential vanilloid (TRPV1) channels in skin afferents, which override the dysregulated hypothalamic thermostat and temporarily restore normal thermoregulatory balance. Topical capsaicin applied to the abdomen is reported to give similar relief and is used as a symptomatic bridge treatment in the emergency department, and it has also been described as a diagnostic test. The 2019 review notes that capsaicin-type treatments have not been tried in people with CVS and no cannabis exposure, so whether the benefit is specific to CHS is uncertain.
CHS vs. Classic CVS: Key Distinctions
- Cannabis use history: CHS requires regular cannabis use (a 2017 systematic review found at least weekly use in 97.4% of published cases, and a 2022 systematic review reported cannabis use lasting from 6 months to 11 years before symptoms); classic CVS does not
- Compulsive hot showering: Linked to CHS but not proof of it; also seen in about 50% of people with CVS who do not use cannabis
- Age of onset: CHS typically presents in young adults (20s–30s) who have been cannabis users since adolescence; classic CVS can present at any age
- Migraine history: In adults with CVS, migraine headaches in 13% to 70% and an affected close relative in 57%; migraine association is less prominent in CHS
- Response to cannabis cessation: Reports describe CHS resolving with sustained cannabis cessation; classic CVS is unaffected by cannabis use history
- Worsening with cannabis: CHS episodes are precipitated by cannabis use; patients with classic CVS may actually use cannabis to self-treat nausea (which is counterproductive in CHS)
Diagnosis and Emergency Management
CHS is diagnosed clinically based on the triad of: (1) chronic heavy cannabis use, (2) recurrent stereotyped vomiting episodes, and (3) relief with hot bathing. In the emergency department, topical capsaicin cream (0.075–0.1%) applied to the abdomen is used for symptomatic relief and has been described as a diagnostic pointer. A 2024 emergency-medicine systematic review of 7 studies (492 patients) found mixed evidence that capsaicin reduces nausea and vomiting, and possible benefit from dopamine-blocking drugs such as haloperidol; its authors call the direct evidence for both limited (more on the separate cannabis hyperemesis syndrome page). A 2021 review says capsaicin cream may ease symptoms, perhaps through the same TRPV1 receptors as hot water. A single-center retrospective study of 201 patients found that 55% of those given capsaicin needed at most one rescue drug, against 21% of those not given it, with a shorter time to discharge after the reference drug (3.72 versus 6.11 hours) but no change in total emergency department stay or number of medication doses; its authors say robust evidence is lacking. Intravenous haloperidol beat ondansetron for CHS in one randomized emergency department trial, HaVOC: among 30 treated patients, weight-based haloperidol (0.05 or 0.1 mg/kg) against ondansetron 8 mg improved pain and nausea by a further 2.3 cm on a 10-cm scale (95% confidence interval 0.6 to 4.0 cm), and emergency department stay was shorter (3.1 versus 5.6 hours). There were 2 return visits for acute dystonia (painful muscle spasms), both at the higher haloperidol dose.
Definitive Treatment: Cannabis Cessation
The only definitive treatment for CHS is complete, sustained cannabis cessation. Follow-up evidence on stopping is thin: in a 2012 Mayo Clinic series of 98 patients, follow-up was available for only 10; of those 10, 7 stopped using cannabis, and 6 of those 7 reported complete resolution of their symptoms. Relapse to cannabis use is reported to bring CHS back: in the 2004 series, seven people who stopped became well, and the three who went back to cannabis became ill again; two of those three abstained again and stayed well. The 2019 review adds that, under stricter criteria, very few patients with purported CHS report symptom reduction lasting more than 3 months, because follow-up in most reports is short or missing. All cannabis products — including cannabidiol (CBD)-dominant products containing trace tetrahydrocannabinol — are described as able to maintain CHS in susceptible individuals. Cessation support, addiction counseling, and motivational interviewing are integral to CHS management.
7. Diagnosis
CVS diagnosis is clinical, based on recognition of the characteristic episodic pattern after exclusion of structural, metabolic, and surgical causes. There is no diagnostic test for CVS — the diagnosis is made by applying validated criteria to a careful history.
Rome IV Criteria
The Rome IV criteria (2016) are the current gold standard for diagnosing adult CVS. All of the following must be present:
- Stereotyped episodes of vomiting regarding onset (acute) and duration (less than 1 week)
- At least three discrete episodes in the prior year and two episodes in the past 6 months, occurring at least 1 week apart
- Absence of vomiting between episodes — though other, milder symptoms (mild nausea, fatigue) may persist
- Symptoms not better explained by another diagnosis
The Rome IV table in the 2019 guideline lists a personal or family history of migraine headaches as its supportive remark. Other features clinicians describe as strengthening the diagnosis include: a predictable stereotyped onset time, the ability to abort episodes with sleep or triptans, and a stereotyped prodrome.
New North American guidelines for children, published in 2025, replace the 2008 consensus statement. The diagnostic guideline recommends screening blood and urine tests and an upper gastrointestinal X-ray series for all children with symptoms suggesting CVS, and finds low yield from other screening tests. The management guideline makes 16 recommendations, with a strong one for anti-migraine drugs to stop attacks in children with a personal or family history of migraine and conditional ones for 5-HT3 and neurokinin-1 receptor blockers.
Differential Diagnosis
The key differential diagnoses that are excluded before accepting a CVS diagnosis include:
- Gastroparesis: Delayed gastric emptying causes chronic nausea and intermittent vomiting, but symptoms are continuous rather than episodic, and symptom-free intervals do not occur. Gastric emptying in CVS differs from gastroparesis: a 2011 review reports it rapid in about 60% of adults with CVS and normal in the rest, and the 2019 guideline reports rapid or normal emptying with only a small subset delayed. That guideline says gastric emptying tests are not typically useful in the CVS workup, though they may help in people with symptoms between episodes.
- Functional nausea and vomiting: Functional dyspepsia and functional nausea present with chronic, persistent symptoms rather than discrete episodic attacks separated by complete normalcy.
- Small bowel obstruction: Intermittent obstruction from adhesions, internal hernias, or malrotation can mimic CVS. CT imaging or small bowel follow-through is indicated, particularly in patients with prior abdominal surgery.
- Pheochromocytoma: Episodic catecholamine release causes paroxysmal hypertension, diaphoresis, and vomiting that can closely mimic CVS. Plasma free metanephrines or 24-hour urine catecholamines are an essential part of the workup.
- Arnold-Chiari malformation: Type I Chiari malformation causes raised intracranial pressure, which can present with episodic vomiting, headache, and autonomic instability. Brain magnetic resonance imaging (MRI) with posterior fossa views is indicated.
- Addison's disease: Primary adrenal insufficiency produces episodic nausea, vomiting, and fatigue triggered by physiological stress — a potentially life-threatening mimic of CVS that requires cortisol and adrenocorticotropic hormone (ACTH) measurement.
- Mitochondrial disorders: MELAS (mitochondrial encephalomyopathy, lactic acidosis, and stroke-like episodes) and other mitochondrial diseases can present with recurrent vomiting. Lactate, pyruvate, and mitochondrial DNA testing are used in patients with suggestive systemic features.
Diagnostic Workup
The recommended workup for a patient presenting with recurrent stereotyped vomiting includes:
- Upper endoscopy (EGD): To exclude structural causes — peptic ulcer disease, outlet obstruction, eosinophilic esophagitis. Also evaluates for Mallory-Weiss tears from forceful vomiting.
- Gastric emptying scintigraphy: To exclude gastroparesis. Performed during the symptom-free interictal period, since emptying is altered during an episode — results in CVS are rapid or normal, with a small subset delayed.
- Brain magnetic resonance imaging with posterior fossa protocol: To exclude Arnold-Chiari malformation and intracranial lesions affecting the vomiting center.
- Abdominal computed tomography (CT) or magnetic resonance imaging: To exclude structural small bowel pathology, superior mesenteric artery (SMA) syndrome, and retroperitoneal masses.
- Metabolic screen: Plasma free metanephrines (pheochromocytoma), morning cortisol/adrenocorticotropic hormone stimulation test (Addison's disease), serum lactate/pyruvate (mitochondrial disease), urine organic acids.
- Cannabis use history: Explicit, non-judgmental inquiry about cannabis use history — frequency, duration, product type, quantity — is essential given the prevalence of CHS.
8. Abortive Treatment
Abortive therapy aims to interrupt an episode during the prodrome or early vomiting phase, shortening its duration and reducing its severity. The prodromal window of 30–60 minutes is the critical treatment opportunity.
Triptans (Sumatriptan)
Sumatriptan, a serotonin 5-HT1B/1D receptor agonist, is the most effective abortive agent for CVS, reflecting the condition's migrainous basis. Its mechanism — constriction of intracranial blood vessels and inhibition of trigeminovascular inflammatory peptides (CGRP, substance P) — directly targets the shared CVS-migraine pathophysiology. Subcutaneous sumatriptan (6 mg) is preferred over oral formulations during CVS episodes, because nausea and the high vomiting frequency make oral absorption unreliable. A nasal spray formulation (20 mg) is a useful intermediate option. The 2019 adult guideline conditionally recommends triptans, recommending them during the prodrome or within 30–45 minutes of the onset of vomiting, and reports that efficacy appears to diminish after the first 60 minutes; it also notes that randomized placebo-controlled studies in CVS attacks are lacking. It is most effective in patients with a clear migrainous history.
Ondansetron
Ondansetron (4–8 mg orally, sublingually, or intravenous) is a 5-HT3 receptor antagonist antiemetic that reduces the intensity of nausea and the frequency of vomiting during established episodes. It does not abort episodes in the same way triptans do, but is an essential component of supportive care — reducing dehydration risk by allowing brief oral rehydration attempts, reducing distress, and reducing the need for intravenous hydration. Oral dissolving tablet (ODT) formulations are practical during episodes when the patient cannot swallow pills reliably.
Lorazepam
Lorazepam (0.5–1 mg orally or intravenous) serves multiple roles in CVS abortive therapy. As a benzodiazepine, it reduces anxiety and activates gamma-aminobutyric acid (GABA) receptors in the brainstem, which modulate the vomiting center. It produces sedation that allows the patient to sleep — and sleep is one of the most effective ways to terminate a CVS episode. It also has independent antiemetic properties and reduces the intense distress accompanying severe vomiting. The combination of lorazepam plus ondansetron is a standard emergency department regimen for acute CVS management.
Haloperidol (Refractory Episodes)
Haloperidol (0.05 mg/kg intravenous, typical dose 1–5 mg) is a typical antipsychotic with potent antiemetic properties mediated through dopamine D2 receptor blockade in the area postrema. It has emerged as a particularly effective agent for CVS and CHS episodes refractory to ondansetron and lorazepam. The randomized evidence is in cannabis hyperemesis rather than classic CVS (the HaVOC trial described above), and the 2019 adult CVS guideline does not mention haloperidol; its use in CVS is described particularly for episodes with extreme vomiting frequency or severe distress. QTc monitoring is described, and akathisia (motor restlessness) can be managed with diphenhydramine pretreatment.
Intravenous Fluid Resuscitation
Dehydration is a universal complication of severe CVS episodes. Intravenous fluid resuscitation with normal saline or lactated Ringer's solution — often including potassium supplementation for hypokalemia — is a mainstay of emergency department management. Many patients require 1–3 liters of intravenous fluid per episode. Dextrose-containing solutions may be preferred for patients with suspected mitochondrial disease, as fasting-induced metabolic stress may be a trigger. A dark, quiet room with minimal stimulation during intravenous infusion reduces sensory triggering of continued vomiting.
9. Prophylactic Treatment
The 2019 adult guideline recommends prophylactic (preventive) therapy for moderate-to-severe CVS, defined by one or more of: frequent episodes (≥4/year), prolonged episodes (>2 days), episodes requiring emergency care or hospitalization, or episodes that significantly interfere with daily activities. The goal is to reduce episode frequency, severity, and duration — not necessarily to eliminate all episodes.
Amitriptyline (First-Line Adults)
Amitriptyline is the first-line prophylactic agent for CVS in adults, endorsed by the 2019 multidisciplinary clinical practice guideline. It is a tricyclic antidepressant that modulates serotonergic and noradrenergic neurotransmission, reduces central sensitization, and has direct antiemetic properties through its anticholinergic and antihistamine effects. Starting doses of 10–25 mg at bedtime are titrated upward over weeks to 50–75 mg (or higher in adults without dose-limiting side effects). The sedating side effects (drowsiness, dry mouth) are often beneficial in CVS — promoting sleep, which is itself therapeutic. Episode frequency reductions of 50–75% in responders are reported. The guideline makes its strong recommendation on very low-quality evidence, from open-label and retrospective studies and two randomized trials in children: across 14 studies and 600 patients, 70% reported complete or partial improvement, and in one open-label study of 46 patients episodes fell from 17 to 3. Because amitriptyline can prolong the QTc interval on a heart tracing and cause arrhythmias, the guideline reports obtaining an electrocardiogram at baseline, once at about 50 mg and again at the target dose, keeping the QTc below 470 ms in women and 450 ms in men. The drug also treats comorbid anxiety and depression, which are prevalent in CVS populations. Cardiac side effect concerns are raised with amitriptyline in children. The 2008 North American consensus statement lists cyproheptadine in children 5 years or younger and amitriptyline for those older than 5. A randomized trial in 64 children aged 3 to 15 found no superiority of either drug (full remission in 65.6% on amitriptyline and 50% on cyproheptadine, P = .206).
Coenzyme Q10 (CoQ10)
Coenzyme Q10 (ubiquinol, 100–600 mg/day) is a mitochondrial cofactor that functions as an electron carrier in the respiratory chain. Its role in CVS prophylaxis is grounded in the mitochondrial dysfunction hypothesis. Observational reports describe reductions in episode frequency with coenzyme Q10 supplementation. In a retrospective internet survey, 68% of 22 people on coenzyme Q10 and 72% of 162 on amitriptyline reported a 50% reduction in at least one episode measure, with no side effects reported on coenzyme Q10; the guideline notes that the same authors recommended 10 mg/kg per day in two divided doses, up to 200 mg twice daily. A chart review of 30 cases treated with combined coenzyme Q10, L-carnitine and, in refractory cases, amitriptyline or cyproheptadine reported episodes resolving in 23. The guideline conditionally recommends coenzyme Q10 on very low-quality evidence, and lists limits including self-selection and an unproven diagnosis in the survey. No randomized trial of it in CVS appeared in the literature searches run for this page. It is used particularly for patients with evidence of mitochondrial involvement (maternal inheritance, exercise intolerance, elevated lactate) and as an adjunct to first-line pharmacological prophylaxis. Coenzyme Q10 has an excellent safety profile and is well tolerated.
Riboflavin (Vitamin B2)
Riboflavin (vitamin B2) at doses of 200–400 mg/day supports mitochondrial complex I and II function and has established efficacy in migraine prophylaxis. Its use in CVS is extrapolated from the shared mitochondrial and migrainous mechanisms. Riboflavin is inexpensive, safe, and well tolerated — side effects are limited to harmless bright-yellow urine discoloration. It is commonly combined with coenzyme Q10 as a mitochondrial support regimen, particularly in patients with a strong migrainous or mitochondrial profile.
L-Carnitine
L-Carnitine (50–100 mg/kg/day, maximum 3 g/day) facilitates the transport of long-chain fatty acids into mitochondria for beta-oxidation and plays a role in buffering the acetyl-CoA pool during metabolic stress. In CVS patients with evidence of carnitine deficiency or mitochondrial dysfunction, L-carnitine supplementation may reduce episode frequency. It is particularly used in pediatric CVS and in adult patients with a mitochondrial phenotype. Plasma carnitine levels can be measured to identify deficiency before initiating supplementation.
Topiramate
Topiramate (25–100 mg/day) is an alternative prophylactic agent, conditionally recommended by the 2019 guideline, for CVS patients who fail or cannot tolerate amitriptyline. It is a sodium channel blocker and gamma-aminobutyric acid agonist with proven efficacy in migraine prophylaxis that translates to CVS through shared mechanisms. Its main limitations are cognitive side effects ("word-finding difficulties," slowed thinking) and weight loss, which can be problematic in patients already prone to nutritional deficits from repeated vomiting episodes. Topiramate is preferred over amitriptyline in patients with obesity or in those for whom the anticholinergic side effects of tricyclics are poorly tolerated. The guideline states that topiramate can interfere with the efficacy of oral contraceptives.
Aprepitant, Zonisamide and Levetiracetam
The 2019 adult guideline also conditionally recommends, on very low-quality evidence, aprepitant (a neurokinin-1 receptor blocker) and zonisamide or levetiracetam (anti-seizure drugs) as alternative preventive drugs. The evidence for aprepitant is one open-label trial in children and adolescents who had not responded to usual treatment, in which 82% of 16 had a complete or partial response at 12 months. In that same trial, aprepitant used to stop attacks shortened episodes from 5 days to 1 day. The evidence for zonisamide and levetiracetam is one retrospective series of 20 adults, in which 75% reported a moderate response and 20% a complete end to episodes, with fatigue, confusion, impaired concentration or headache commonly reported.
Behavioral and Lifestyle Prophylaxis
Non-pharmacological prophylaxis is described as integral to CVS management. The 2019 guideline says techniques like meditation, relaxation and biofeedback may be offered as complementary therapy. Strategies described in the literature include:
- Trigger diary: People keep a personal diary to identify and systematically reduce exposure to individual triggers (dietary, sleep, stress)
- Regular sleep schedule: Maintaining consistent sleep and wake times reduces circadian dysregulation — one of the most modifiable risk factors
- Regular meals: Fasting is a reported trigger; people describe regular meals and carrying snacks to head off hypoglycemia-triggered episodes
- Stress management: Cognitive-behavioral therapy, biofeedback, and mindfulness-based interventions reduce the hypothalamic-pituitary-adrenal axis hyperreactivity that drives stress-triggered episodes
- Cannabis cessation: Described as the only definitive treatment for CHS; also raised for classic CVS patients who use cannabis to self-treat, as this may worsen long-term course
10. Complications
- Dehydration and electrolyte abnormalities: The most immediate and universal complication. Severe vomiting produces hypokalemia (potassium depletion from gastric losses), hyponatremia (from hypotonic fluid replacement), and metabolic alkalosis (from loss of hydrochloric acid). Severe dehydration can cause prerenal azotemia, orthostatic hypotension, and in extreme cases, cardiovascular compromise. Intravenous fluid resuscitation with electrolyte correction is the cornerstone of emergency management.
- Mallory-Weiss tears: Forceful retching during CVS episodes can produce longitudinal mucosal lacerations at the gastroesophageal junction — Mallory-Weiss tears — causing hematemesis (vomiting blood). These tears are typically self-limiting and heal spontaneously, but can cause significant alarming bleeding during an already-distressing episode. Severe or persistent hematemesis warrants urgent endoscopy.
- Boerhaave syndrome (esophageal rupture): Extremely rare but life-threatening complication of explosive vomiting — full-thickness esophageal perforation causing mediastinitis. Presents with severe chest pain, subcutaneous emphysema, and rapidly developing sepsis after a vomiting episode. Requires emergency surgical consultation.
- Dental erosion: Repeated exposure of tooth enamel to gastric acid during frequent vomiting episodes causes progressive erosion of the lingual (tongue-side) surfaces of the upper teeth — the characteristic pattern of acid reflux injury. Dental follow-up is commonly described as part of long-term CVS management; fluoride products are one option offered for enamel, and using them is a matter of informed consent.
- Nutritional deficiencies: Frequent prolonged vomiting episodes — each lasting several days with inability to eat — cumulatively produce caloric, protein, and micronutrient deficits over time. Thiamine (B1) deficiency is a specific risk in patients with frequent and severe episodes, because thiamine stores are limited and depletion can occur within days of reduced intake. Wernicke's encephalopathy (ataxia, ophthalmoplegia, confusion) from thiamine deficiency is a rare but documented complication of severe CVS, and hospitals treat it empirically with intravenous thiamine in a CVS patient presenting with altered mental status.
- School and work absenteeism: CVS episodes, each lasting a mean of 5 days and occurring multiple times per year, produce substantial functional impairment. Children with CVS miss a mean of 24 school days per year — well above the threshold for educational impact. Adults lose a mean of 22 workdays per year. Academic failure, social isolation, and reduced career opportunity are recognized long-term consequences of inadequately treated CVS.
- Psychological impact and psychiatric comorbidity: The chronic unpredictable nature of CVS — with its dramatic, debilitating attacks arising at random and disrupting normal life — produces significant psychological burden. Rates of anxiety disorders (40–50%), depression (25–35%), and health anxiety are substantially elevated in CVS populations. Anticipatory anxiety about the next episode further amplifies sympathetic nervous system activation, potentially increasing episode frequency in a vicious cycle. Psychological support is described as a routine component of comprehensive CVS care.
- Opiate dependence: Prior to the recognition of CVS as a distinct entity and the codification of effective treatments, patients frequently received repeated courses of intravenous opiates during emergency visits. Long-term opiate use for CVS pain management has produced opiate dependence in a significant number of patients, complicating subsequent care. Current guidelines recommend against routine opiate use for CVS and emphasize non-opiate management protocols in emergency settings.
11. Prognosis and Long-term Outcomes
The long-term prognosis of CVS is variable and depends heavily on age of onset, the underlying mechanism, and the adequacy of prophylactic treatment.
Childhood CVS: Transition to Migraine
A defining feature of pediatric CVS is its frequent natural evolution over time. Longitudinal studies show that approximately 50–75% of children with CVS experience resolution or significant reduction of vomiting episodes in adulthood, and many of these children go on to develop classic migraine headaches as adolescents or young adults. In one follow-up of 26 children, 13 (50%) had continuing CVS and/or migraine and the rest were symptom-free; past or present migraine was found in 46%, against 12% of matched controls. The vomiting syndrome transforms into a headache syndrome as the clinical expression of the same underlying neurological predisposition shifts with neurodevelopment. This transition is an important finding to discuss with families at diagnosis — CVS in childhood is not a lifelong vomiting disorder in most patients, but a precursor to migraine that requires the same preventive approach.
A minority of children (approximately 20–30%) continue to experience CVS episodes into adulthood without transitioning to headache-predominant migraine, and a small subset develop concurrent migraine headaches alongside persistent CVS episodes.
Adult CVS: Chronic Course
Adult-onset CVS tends to follow a more persistent course without the natural remission seen in childhood CVS. Adults diagnosed in their 20s and 30s — particularly those with a strong CRF/stress-trigger pattern or mitochondrial features — commonly experience ongoing episodic disease for years to decades. With appropriate prophylactic therapy (amitriptyline first-line), approximately 50–75% of adults achieve a clinically meaningful reduction in episode frequency and severity. Complete remission is achievable but less common in adults than in children.
Prognostic Factors
Features associated with better long-term prognosis include: childhood onset, strong migrainous profile (good response to triptans), compliance with prophylactic therapy, successful trigger identification and avoidance, and absence of psychiatric comorbidity. Features associated with worse prognosis include: adult onset, psychiatric comorbidity (particularly anxiety disorders), cannabis use continuation, opiate dependence, frequent emergency department visits as a pattern of care, and late or missed diagnosis (delaying effective prophylaxis).
For patients with CHS, the published reports link the end of episodes to complete cannabis cessation, but how long people stay well is not well measured: a 2017 German review notes that long-term follow-up of CHS and CVS cases is seldom published, and it found that complete and lasting resolution of all symptoms after stopping cannabis is the only reliable way to tell CHS apart from CVS.
Key Research Papers
- Li BU et al. North American Society for Pediatric Gastroenterology, Hepatology, and Nutrition consensus statement on the diagnosis and management of cyclic vomiting syndrome. J Pediatr Gastroenterol Nutr. 2008;47(3):379-393. — PubMed PMID: 18728540
- Stanghellini V et al. Gastroduodenal Disorders. Gastroenterology. 2016;150(6):1380-1392. — PubMed PMID: 27147122
- Abell TL, Kim CH, Malagelada JR. Idiopathic cyclic nausea and vomiting--a disorder of gastrointestinal motility? Mayo Clin Proc. 1988;63(12):1169-1175. — PubMed PMID: 3199884
- Venkatesan T et al. Guidelines on management of cyclic vomiting syndrome in adults by the American Neurogastroenterology and Motility Society and the Cyclic Vomiting Syndrome Association. Neurogastroenterol Motil. 2019;31(Suppl 2):e13604. — PubMed PMID: 31241819
- Venkatesan T et al. Role of chronic cannabis use: Cyclic vomiting syndrome vs cannabinoid hyperemesis syndrome. Neurogastroenterol Motil. 2019;31(Suppl 2):e13606. — PubMed PMID: 31241817
- Fleisher DR et al. Cyclic Vomiting Syndrome in 41 adults: the illness, the patients, and problems of management. BMC Med. 2005;3:20. — PubMed PMID: 16368014
- Hejazi RA, McCallum RW. Review article: cyclic vomiting syndrome in adults--rediscovering and redefining an old entity. Aliment Pharmacol Ther. 2011;34(3):263-273. — PubMed PMID: 21668458
- Boles RG, Adams K, Li BU. Maternal inheritance in cyclic vomiting syndrome. Am J Med Genet A. 2005;133A(1):71-77. — PubMed PMID: 15643622
- Allen JH et al. Cannabinoid hyperemesis: cyclical hyperemesis in association with chronic cannabis abuse. Gut. 2004;53(11):1566-1570. — PubMed PMID: 15479672
- Dignan F et al. The prognosis of cyclical vomiting syndrome. Arch Dis Child. 2001;84(1):55-57. — PubMed PMID: 11124785
- Zaki EA et al. Two common mitochondrial DNA polymorphisms are highly associated with migraine headache and cyclic vomiting syndrome. Cephalalgia. 2009;29(7):719-728. — PubMed PMID: 19220304
- Boles RG et al. Treatment of cyclic vomiting syndrome with co-enzyme Q10 and amitriptyline, a retrospective study. BMC Neurol. 2010;10:10. — PubMed PMID: 20109231
- Boles RG. High degree of efficacy in the treatment of cyclic vomiting syndrome with combined co-enzyme Q10, L-carnitine and amitriptyline, a case series. BMC Neurol. 2011;11:102. — PubMed PMID: 21846334
- Badihian N et al. Prophylactic Therapy of Cyclic Vomiting Syndrome in Children: Comparison of Amitriptyline and Cyproheptadine: A Randomized Clinical Trial. Am J Gastroenterol. 2018;113(1):135-140. — PubMed PMID: 28719594
- Ruberto AJ et al. Intravenous Haloperidol Versus Ondansetron for Cannabis Hyperemesis Syndrome (HaVOC): A Randomized, Controlled Trial. Ann Emerg Med. 2021;77(6):613-619. — PubMed PMID: 33160719
- Stumpf JL, Williams LD. Management of Cannabinoid Hyperemesis Syndrome: Focus on Capsaicin. J Pharm Pract. 2021;34(5):786-793. — PubMed PMID: 32613883
- Kum V et al. Efficacy of topical capsaicin for cannabinoid hyperemesis syndrome in a pediatric and adult emergency department. Am J Emerg Med. 2021;49:343-351. — PubMed PMID: 34242945
- Myran DT et al. Changes in Emergency Department Visits for Cannabis Hyperemesis Syndrome Following Recreational Cannabis Legalization and Subsequent Commercialization in Ontario, Canada. JAMA Netw Open. 2022;5(9):e2231937. — PubMed PMID: 36112372
- Chen YJ et al. Epidemiology, Comorbidities, and Treatment of Cyclic Vomiting Syndrome in the United States. Am J Gastroenterol. 2024;119(5):965-976. — PubMed PMID: 38088366
- Izagirre A et al. Worldwide Prevalence and Description of Cyclic Vomiting Syndrome According to the Results of the Rome Foundation Global Epidemiology Study. Am J Gastroenterol. 2025;120(5):1108-1115. — PubMed PMID: 39319824
- Karrento K et al. North American Society for Pediatric Gastroenterology, Hepatology, and Nutrition 2025 guidelines for management of cyclic vomiting syndrome in children. J Pediatr Gastroenterol Nutr. 2025;80(6):1028-1061. — PubMed PMID: 40223700
- Karrento K et al. North American Society for Pediatric Gastroenterology, Hepatology, and Nutrition 2025 guidelines on the diagnosis of cyclic vomiting syndrome in children. J Pediatr Gastroenterol Nutr. 2025;81(5):1346-1359. — PubMed PMID: 40836301
- Vivolo-Kantor AM et al. Trends in Emergency Department Visits Involving Cannabis Hyperemesis Syndrome Identified Using a New Diagnosis Code - United States, January 2023-May 2026. MMWR Morb Mortal Wkly Rep. 2026;75(30):391-396. — PubMed PMID: 42560855
- Simonetto DA et al. Cannabinoid hyperemesis: a case series of 98 patients. Mayo Clin Proc. 2012;87(2):114-119. — PubMed PMID: 22305024
- Sorensen CJ et al. Cannabinoid Hyperemesis Syndrome: Diagnosis, Pathophysiology, and Treatment-a Systematic Review. J Med Toxicol. 2017;13(1):71-87. — PubMed PMID: 28000146
- Blumentrath CG, Dohrmann B, Ewald N. Cannabinoid hyperemesis and the cyclic vomiting syndrome in adults: recognition, diagnosis, acute and long-term treatment. Ger Med Sci. 2017;15:Doc06. — PubMed PMID: 28400711
- Senderovich H et al. A Systematic Review on Cannabis Hyperemesis Syndrome and Its Management Options. Med Princ Pract. 2022;31(1):29-38. — PubMed PMID: 34724666
- Sabbineni M et al. SAEM GRACE: Dopamine antagonists and topical capsaicin for cannabis hyperemesis syndrome in the emergency department: A systematic review of direct evidence. Acad Emerg Med. 2024;31(5):493-503. — PubMed PMID: 37391387