Campylobacter Treatment: Azithromycin and Antibiotic Options
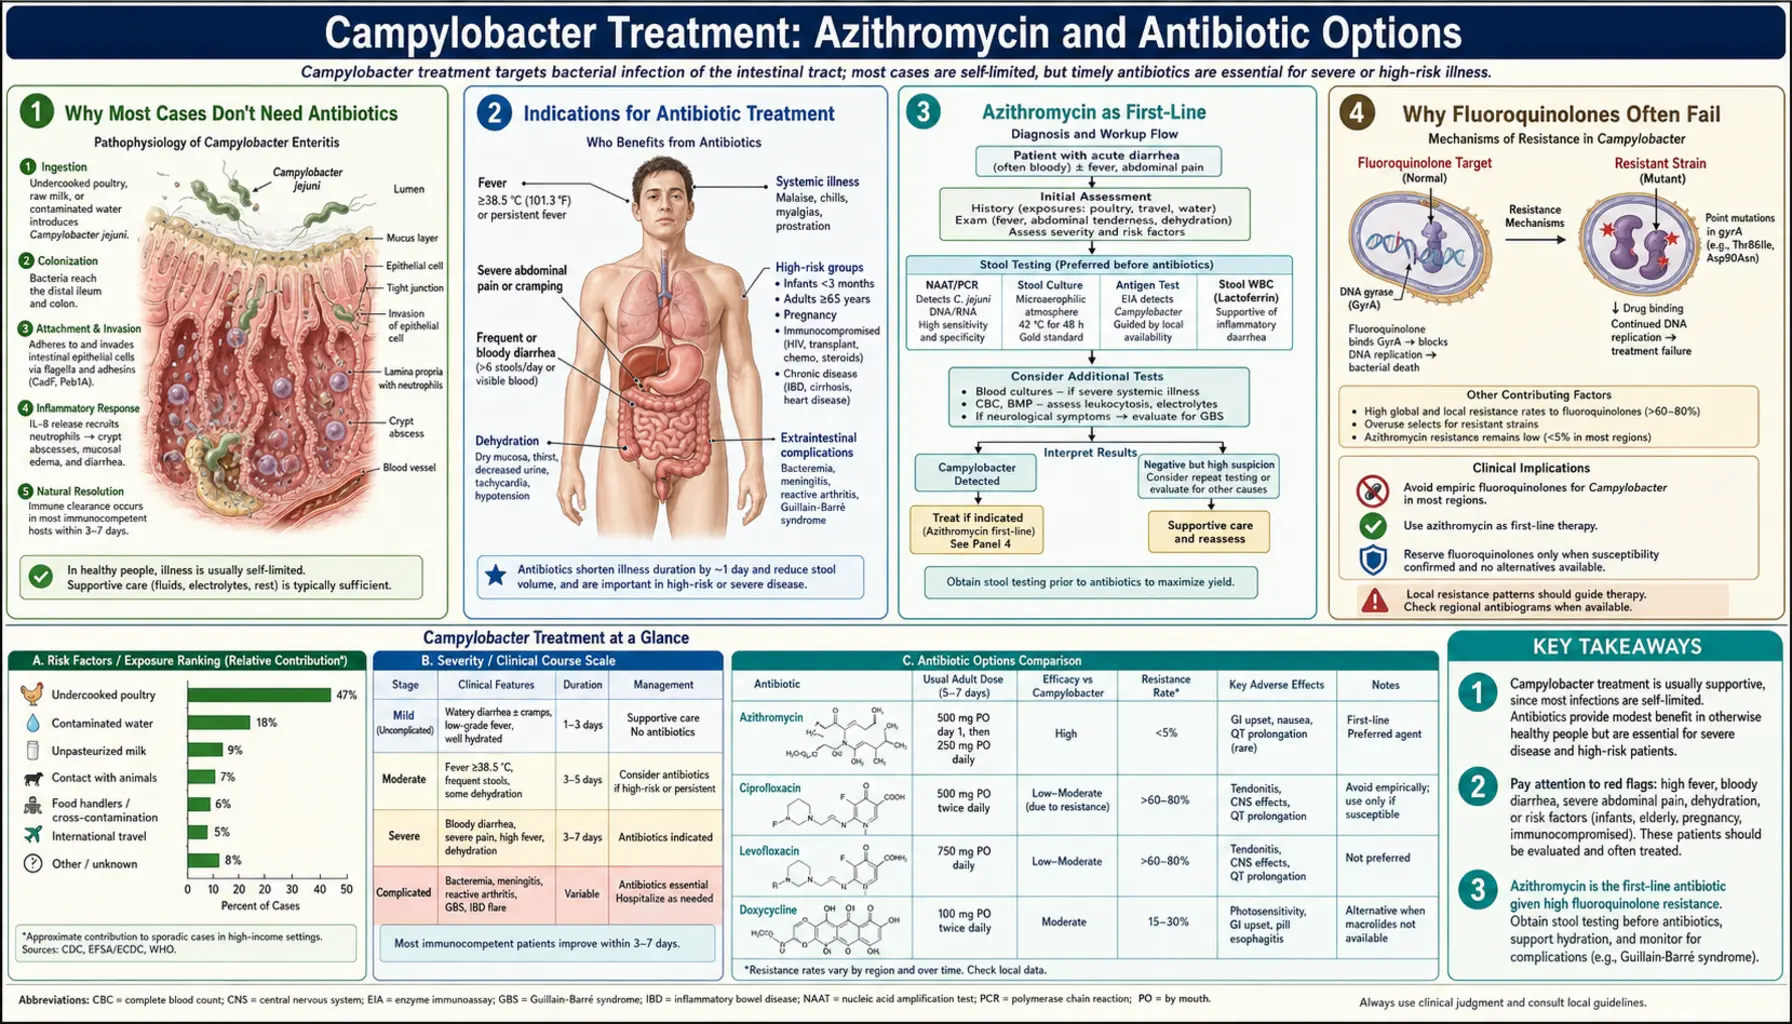
- Why Most Cases Clear Without Antibiotics
- Indications for Antibiotic Treatment
- Azithromycin as First-Line
- Why Fluoroquinolones Often Fail
- Treatment Duration
- Gentamicin and Carbapenem for Invasive Disease
- Oral Rehydration Therapy
- Over-the-Counter Medicines: What the Evidence Shows
- Key Research Papers
- Connections
Why Most Cases Clear Without Antibiotics
Campylobacter jejuni infection is self-limiting in the vast majority of otherwise healthy adults. The immune system clears the infection without any antimicrobial help, typically within 5 to 10 days. A landmark meta-analysis by Ternhag and colleagues (2007) found that antibiotics shorten illness duration by only about 1.3 days on average — a modest gain that has to be weighed against real costs: antibiotic side effects (diarrhea, nausea, rash, Clostridioides difficile risk), out-of-pocket expense, and the population-level harm of accelerating resistance.
There is also a practical timing problem. Stool culture takes 48 to 72 hours to return a positive result, and polymerase chain reaction (PCR) panels take 24 to 48 hours. By the time a confirmed Campylobacter result lands in a doctor's inbox, most patients have already passed the peak of illness and are improving on their own. Starting antibiotics at that point provides little clinical benefit and still carries all the downside risks.
The 2017 clinical practice guideline of the Infectious Diseases Society of America (IDSA) notes that symptoms in the Campylobacter treatment trials were self-limited and that the treatment effect appeared largest when treatment began early in the illness. It describes treating patients with particularly prolonged or severe disease as reasonable, and offering treatment to immunocompromised patients with otherwise uncomplicated Campylobacter gastroenteritis as reasonable. In straightforward cases the focus is supportive care: fluids, rest, and time.
Indications for Antibiotic Treatment
Certain patients do receive antibiotics, and recognizing those situations matters as much as recognizing when antibiotics add little. The following clinical scenarios are the ones commonly cited as reasons for treatment:
- High fever (>39°C / 102.2°F) — suggests a more aggressive or invasive infection
- Bloody diarrhea persisting beyond one week — prolonged mucosal damage or invasive spread
- Signs of dehydration requiring hospital admission — intravenous (IV) antibiotics may be added alongside intravenous fluids
- Bacteremia (positive blood culture) — organism has left the gut; systemic treatment is mandatory
- Immunocompromised host — human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS), solid-organ transplant, hematologic malignancy, high-dose corticosteroids, biologic therapies, or surgical splenectomy all impair the T-cell and macrophage responses needed to clear Campylobacter; these patients face prolonged infection, relapse, and bacteremia
- Very young infants (<3 months) — immature immune defenses and risk of rapid deterioration
- Elderly patients with severe symptoms — age-related immune decline and higher dehydration risk
- Pregnancy — maternal bacteremia can seed the placenta and cause premature labor, neonatal sepsis, or stillbirth
- Healthcare workers and food handlers — shortening the duration of fecal shedding matters when others are at risk; treatment reduces infectious period from a median of 2–4 weeks to several days
For people in these groups with confirmed or strongly suspected Campylobacter infection, the decision on antibiotic treatment, and its timing, belongs with a clinician; the 2017 IDSA guideline notes that the treatment effect in the trials appeared largest when treatment began early in the illness.
Azithromycin as First-Line
When antibiotics are genuinely needed for Campylobacter jejuni, azithromycin is the first choice in most international guidelines. It belongs to the macrolide class — the same family as erythromycin and clarithromycin — and works by binding to the 50S ribosomal subunit, blocking bacterial protein synthesis.
Adult Dosing
- Standard course: 500 mg once daily for 3 days
- Alternative single-dose: 1 g (1000 mg) as a one-time dose (used in some resource-limited settings or when compliance is a concern)
- Severe or immunocompromised: some guidelines extend to 5 days or switch to intravenous erythromycin
Pediatric Dosing
- 10 mg/kg once daily for 3 days (maximum 500 mg/day)
- Well-tolerated in children; azithromycin suspension is available for young children who cannot swallow tablets
Why Azithromycin Works Better Than Alternatives
Azithromycin has two pharmacological advantages for gut infections. First, it concentrates inside tissue and macrophages at levels 10- to 100-fold above serum — important because Campylobacter invades the intestinal mucosa and survives inside host cells. Second, macrolide resistance in C. jejuni remains low in many countries: across the European Union, erythromycin resistance in human C. jejuni isolates was 0.7% in 2020 and 0.9% in 2022 (summary reports of the European Food Safety Authority and the European Centre for Disease Prevention and Control, EFSA/ECDC), though higher in some individual countries, and the 2017 IDSA guideline puts macrolide resistance below 5% among human isolates in the United States. This contrasts sharply with fluoroquinolone resistance, which has blown past 50% in much of the world.
Azithromycin's long half-life (68 hours) means once-daily dosing is sufficient and tissue levels stay therapeutic for days after the last dose. Side effects are generally mild: nausea, loose stools, and abdominal cramping are the most common; rare but serious cardiac effects (QT prolongation) exist but are uncommon at standard doses in otherwise healthy people.
Why Fluoroquinolones Often Fail
Until the late 1990s, ciprofloxacin was the default first-line antibiotic for Campylobacter — and in the test tube it looks excellent: low minimum inhibitory concentrations (MICs), good gastrointestinal (GI) penetration, broad spectrum. In practice, empiric ciprofloxacin treatment for Campylobacter now fails roughly half the time in high-income countries and more than three-quarters of the time in some parts of Asia and the Middle East.
The Resistance Numbers
- European Union ciprofloxacin (fluoroquinolone) resistance in human C. jejuni isolates: 61.2% in 2020 and 69.1% in 2022 (EFSA/ECDC EU summary reports on antimicrobial resistance)
- United States: approximately 25–30% by U.S. Centers for Disease Control and Prevention (CDC) National Antimicrobial Resistance Monitoring System (NARMS) — lower than Europe but rising steadily
- Southeast Asia, China, India: commonly >70–80%
- Even at 25% resistance, empiric ciprofloxacin means 1 in 4 patients gets an antibiotic that won't work
The Mechanism
The dominant resistance mechanism is a single point mutation at codon 86 of the gyrA gene (the quinolone resistance-determining region, QRDR), converting threonine to isoleucine (Thr-86-Ile). This mutation changes the DNA gyrase enzyme so that fluoroquinolones can no longer bind tightly to their target. The mutation arises readily and confers high-level resistance (minimum inhibitory concentration (MIC) jumps from <0.5 mg/L to >32 mg/L in one step). There is no intermediate-susceptibility category — organisms are either fully susceptible or fully resistant.
What This Means in Practice
The 2021–2022 EFSA/ECDC report states that, because of these resistance levels, fluoroquinolones (ciprofloxacin and related drugs such as levofloxacin and moxifloxacin) can no longer be recommended for the treatment of Campylobacter infections in humans, and the 2017 IDSA guideline describes azithromycin as first-line treatment for Campylobacter infection in travelers unless fluoroquinolone susceptibility is confirmed. When susceptibility testing confirms sensitivity, ciprofloxacin remains effective. The resistance crisis is directly linked to fluoroquinolone use in poultry production — a story covered in detail in the Antibiotic Resistance sub-article.
Treatment Duration
The length of antibiotic treatment depends on the clinical scenario:
- Uncomplicated gastroenteritis in a healthy adult: 3 days of azithromycin is the standard. Some guidelines allow a single 1 g dose.
- Severe illness or immunocompromised patients: 5 days of azithromycin; some clinicians extend to 7 days for very immunosuppressed patients.
- Bacteremia: typically 14 days of intravenous or oral therapy, depending on organism, source control, and clinical response. Gentamicin intravenous is used for hospitalized patients who cannot take oral medication.
- Relapsing infection in human immunodeficiency virus: some patients require prolonged suppressive therapy; this is less of an issue with modern antiretroviral therapy but still encountered.
Test of Cure — Not Needed
The 2017 IDSA guideline states that follow-up testing is not recommended in most people once diarrhea has resolved. Campylobacter is commonly shed asymptomatically in stool for 2 to 4 weeks after clinical recovery — even after effective antibiotic treatment. A positive stool culture at day 10 does not mean treatment failed; it just means the organism is still being cleared. Repeat testing is appropriate only if symptoms return, persist unexpectedly, or the patient is a food handler or healthcare worker subject to return-to-work policies.
Gentamicin and Carbapenem for Invasive Disease
Most people with Campylobacter never need intravenous antibiotics, but a subset of patients — particularly the immunocompromised and the very ill — develop bacteremia or focal infections (endovascular infection, cholecystitis, meningitis in neonates) that require parenteral therapy.
Gentamicin
Gentamicin, an aminoglycoside, is the intravenous antibiotic of choice for hospitalized Campylobacter bacteremia when oral therapy is not feasible. It is active against both fluoroquinolone-resistant and fluoroquinolone-susceptible strains, making it valuable precisely because the resistance pattern is often unknown when a patient is critically ill. Standard dosing uses extended-interval (once-daily) dosing to maximize the concentration-dependent killing while minimizing nephrotoxicity. Renal function is monitored closely during treatment.
Carbapenems
Imipenem-cilastatin and meropenem are broad-spectrum beta-lactams used for severe invasive disease or when first-line agents fail. C. jejuni carries beta-lactamases that make it resistant to many penicillins, but carbapenems remain reliably active. These are reserved for life-threatening situations given their cost, side effects, and the importance of preserving carbapenem activity against other organisms.
Campylobacter fetus — A Different Species
C. fetus (distinct from C. jejuni) causes bacteremia in immunocompromised and elderly patients. It is less common in the gut but more likely to seed the bloodstream and cause endovascular infections. Fortunately, C. fetus is typically susceptible to ampicillin, amoxicillin-clavulanate, gentamicin, and imipenem. Treatment is usually 2 weeks minimum for bacteremia, longer for endovascular disease.
Oral Rehydration Therapy
Fluid replacement is the cornerstone of Campylobacter treatment regardless of whether antibiotics are needed. Diarrhea causes rapid losses of water, sodium, potassium, and bicarbonate. For most people, oral rehydration is safe, effective, and far preferable to intravenous fluids — provided the patient can drink and keep fluids down.
The WHO ORS Formula
The World Health Organization's oral rehydration solution (ORS) is the gold standard, designed around the sodium-glucose co-transport mechanism in the intestinal wall. Even in active diarrhea, this co-transport system works well — sipping ORS is absorbed even when plain water is not retained. The World Health Organization (WHO) low-osmolarity formula (2002) contains:
- Sodium: 75 mmol/L
- Potassium: 20 mmol/L
- Chloride: 65 mmol/L
- Citrate: 10 mmol/L (bicarbonate equivalent for acidosis)
- Glucose: 75 mmol/L
- Total osmolarity: 245 mOsm/L
Commercial oral rehydration solutions are sold in pharmacies in many countries, and WHO ORS sachets are distributed in low-income countries. Sports drinks are not equivalent — they are much higher in sugar and lower in sodium and potassium than clinical ORS.
Typical Replacement Volumes
- Adults: 200–400 mL of ORS after each loose stool, plus fluid to thirst
- Children: 10 mL/kg after each loose stool (approximately half a cup for a toddler)
- General principle: fluid intake that keeps pace with, or exceeds, ongoing losses
When Intravenous Fluids Are Needed
Emergency care and intravenous fluids are used when a person cannot keep any fluid down due to vomiting, has signs of severe dehydration (dizziness on standing, very dark urine or none at all, confusion), or has lost more than 10% of body weight from fluid loss. Hospitalization for intravenous normal saline or Ringer's lactate is the usual response in these cases.
Over-the-Counter Medicines: What the Evidence Shows
Several commonly used over-the-counter medications carry known risks or offer little help in Campylobacter infection; the evidence on each is summarized below.
Loperamide — Risks in Bloody Diarrhea
Loperamide slows intestinal motility, which sounds desirable when you have diarrhea. In non-invasive secretory diarrhea (like traveler's diarrhea caused by enterotoxigenic Escherichia coli (ETEC)), it provides real symptom relief. But in invasive bacterial infections like Campylobacter, stopping gut movement traps the bacteria and their toxins in contact with the intestinal wall for longer, worsening mucosal damage. More dangerously, impaired motility may facilitate bacterial spread across the gut wall into the bloodstream. The 2017 IDSA guideline states that loperamide may be given to immunocompetent adults with acute watery diarrhea, “but should be avoided at any age in suspected or proven cases where toxic megacolon may result in inflammatory diarrhea or diarrhea with fever,” and that antimotility drugs such as loperamide “should not be given to children <18 years of age with acute diarrhea.” In its section on traveler's diarrhea, the guideline describes an antimotility agent as an option for nonbloody diarrhea in adults.
Anti-Emetics — Generally Safe
Ondansetron, promethazine, and similar anti-emetics are generally regarded as safe in Campylobacter illness when vomiting prevents keeping fluids down. They do not worsen the infection, and they are typically used short-term.
Nonsteroidal Anti-Inflammatory Drugs — Known Cautions
Ibuprofen and naproxen can reduce fever and relieve the significant abdominal cramping of Campylobacter infection, but they also reduce prostaglandin-mediated gut mucosal protection and can impair renal blood flow in someone already dehydrated. Clinicians typically describe taking them with food and extra fluids, and acetaminophen (paracetamol) is generally regarded as the safer option for fever and pain during active gastrointestinal illness.
Antibiotics Without Clear Indication
Taking antibiotics that aren't needed is not a neutral act. Unnecessary antibiotic exposure kills commensal gut bacteria that normally compete with resistant organisms, leaving you temporarily more vulnerable to C. difficile and resistant-organism colonization. At the population level, unnecessary prescriptions drive the resistance crisis that has already rendered ciprofloxacin unreliable against Campylobacter in much of the world. The 2007 Ternhag meta-analysis concluded that, because of problems with drug resistance, a restrictive attitude towards antibiotics in uncomplicated cases is advised.
Key Research Papers
- Ternhag A, Asikainen T, Giesecke J, Ekdahl K. A meta-analysis on the effects of antibiotic treatment on duration of symptoms caused by infection with Campylobacter species. Clin Infect Dis. 2007;44(5):696–700. — Meta-analysis of 11 placebo-controlled trials finding that antibiotics shortened intestinal symptoms by 1.32 days. — PubMed PMID: 17278062
- Engberg J, Aarestrup FM, Taylor DE, Gerner-Smidt P, Nachamkin I. Quinolone and macrolide resistance in Campylobacter jejuni and C. coli: resistance mechanisms and trends in human isolates. Emerg Infect Dis. 2001;7(1):24–34. — Seminal review of gyrA Thr-86-Ile mutation and macrolide resistance mechanisms. — Search PubMed
- Allos BM. Campylobacter jejuni infections: update on emerging issues and trends. Clin Infect Dis. 2001;32(8):1201–6. — Clinical overview of Campylobacter epidemiology, treatment, and complications including GBS. — Search PubMed
- Wieczorek K, Osek J. Antimicrobial resistance mechanisms among Campylobacter. Biomed Res Int. 2013;2013:340605. — Comprehensive review of resistance genes, mechanisms, and surveillance data across species. — Search PubMed
- Kaakoush NO, Castaño-Rodríguez N, Mitchell HM, Man SM. Global epidemiology of Campylobacter infection. Clin Microbiol Rev. 2015;28(3):687–720. — Global burden, risk factors, and geographic variation in antibiotic resistance rates. — Search PubMed
- Gupta A, Nelson JM, Barrett TJ, et al. Antimicrobial resistance among Campylobacter strains, United States, 1997–2001. Emerg Infect Dis. 2004;10(6):1102–9. — NARMS data showing the trajectory of fluoroquinolone resistance in the US food supply. — Search PubMed
- Smith KE, Besser JM, Hedberg CW, et al.; Investigation Team. Quinolone-resistant Campylobacter jejuni infections in Minnesota, 1992–1998. N Engl J Med. 1999;340(20):1525–32. — Minnesota surveillance study finding the rise in quinolone-resistant infections largely due to foreign travel, with resistant strains from poultry behind the growing number of domestically acquired cases. — PubMed PMID: 10332013
- van Boeckel TP, Gandra S, Ashok A, et al. Global antibiotic consumption 2000 to 2010: an analysis of national pharmaceutical sales data. Lancet Infect Dis. 2014;14(8):742–50. — Context for global antibiotic consumption driving resistance across bacterial pathogens. — Search PubMed
- Luber P. Cross-contamination versus undercooking of poultry meat or eggs — which risks need to be managed first? Int J Food Microbiol. 2009;134(1–2):21–8. — Review of published risk assessments concluding that kitchen cross-contamination matters more than undercooking. — PubMed PMID: 19272666
- Scallan E, Hoekstra RM, Angulo FJ, et al. Foodborne illness acquired in the United States — major pathogens. Emerg Infect Dis. 2011;17(1):7–15. — CDC burden-of-illness estimate placing Campylobacter among the most common US foodborne pathogens. — PubMed PMID: 21192848
- Shane AL, Mody RK, Crump JA, et al. 2017 Infectious Diseases Society of America Clinical Practice Guidelines for the Diagnosis and Management of Infectious Diarrhea. Clin Infect Dis. 2017;65(12):e45–e80. — IDSA guideline; source of the Campylobacter treatment, loperamide and follow-up-testing statements on this page. — PubMed PMID: 29053792
- EFSA, ECDC. The European Union Summary Report on Antimicrobial Resistance in zoonotic and indicator bacteria from humans, animals and food in 2019-2020. EFSA J. 2022;20(3):e07209. — EU ciprofloxacin resistance of 61.2% and erythromycin resistance of 0.7% in human C. jejuni isolates (2020). — PubMed PMID: 35382452
- EFSA, ECDC. The European Union summary report on antimicrobial resistance in zoonotic and indicator bacteria from humans, animals and food in 2021-2022. EFSA J. 2024;22(2):e8583. — EU ciprofloxacin resistance of 69.1% and erythromycin resistance of 0.9% in human C. jejuni isolates (2022). — PubMed PMID: 38419967