Carnosine for Brain Health and Neuroprotection
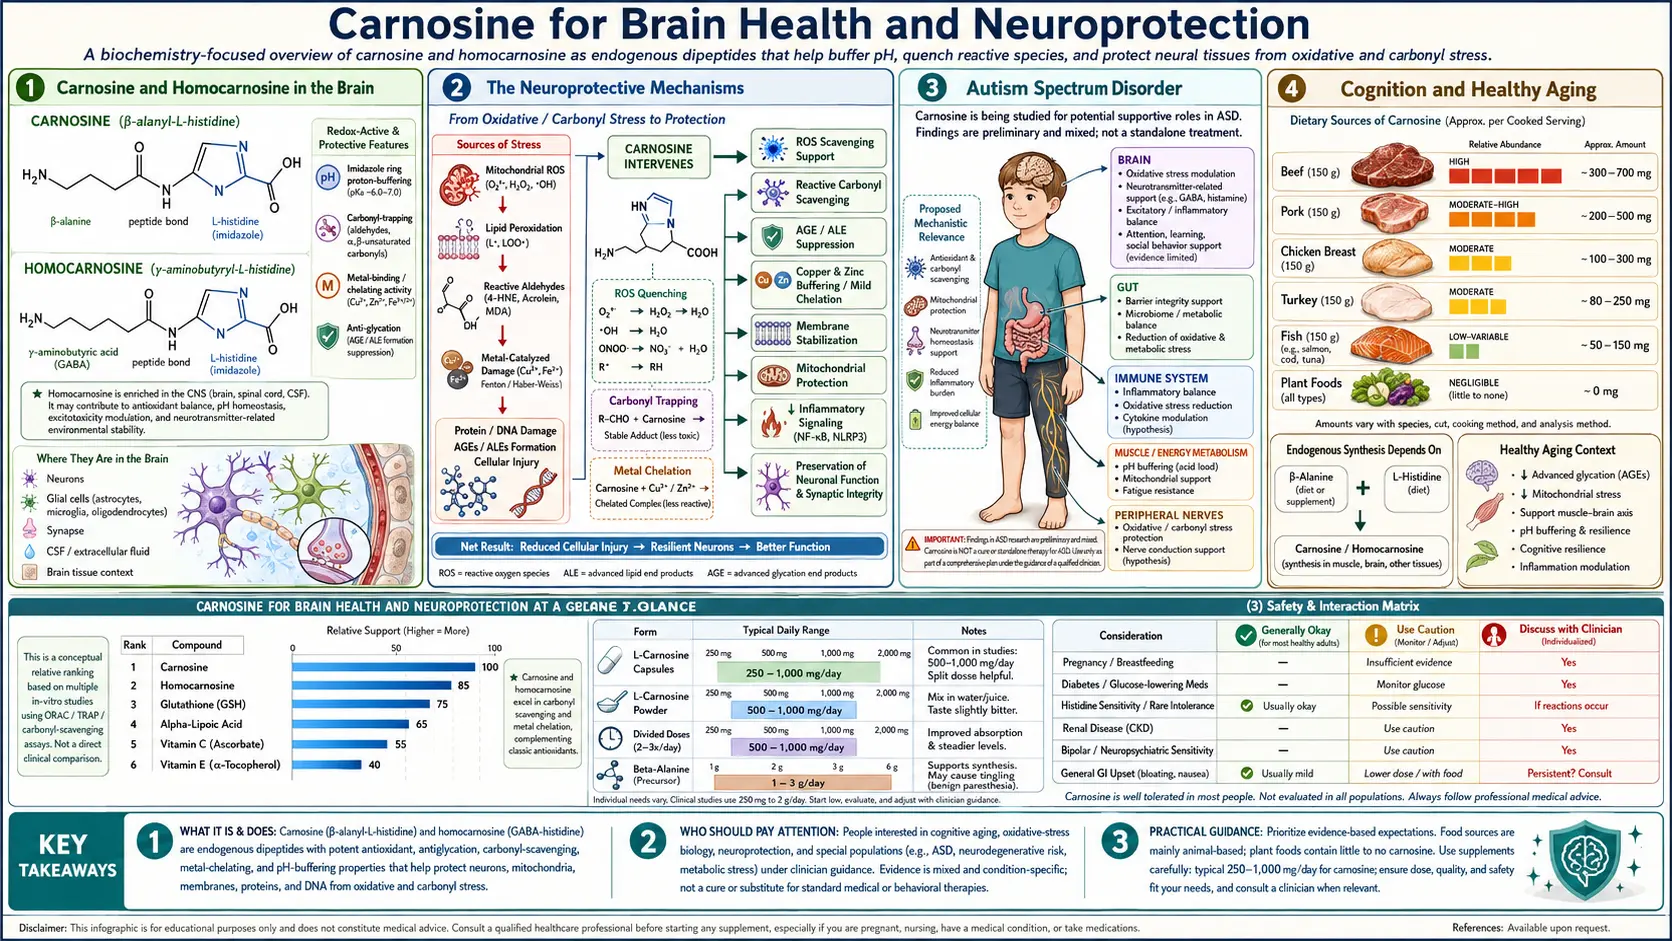
The brain is the second tissue, after muscle, where the body concentrates carnosine — and on paper it looks like an ideal place for a molecule that scavenges free radicals, quenches reactive carbonyls, and buffers the zinc and copper released during nerve signaling. That biochemistry has fueled a large, genuinely interesting research effort into carnosine for autism, age-related cognitive decline, stroke, and neurodegenerative disease. But this is the part of the carnosine story where honesty matters most. The human trials are small, short, sometimes contradictory, and frequently built on top of the same delivery problem that dogs the rest of the field: an enzyme in the blood that takes carnosine apart before it can reach the brain. This page grades the evidence area by area — flagging what is mechanistically plausible, what has weak but real human signals, and what is still only animal data.
Table of Contents
- Carnosine and Homocarnosine in the Brain
- The Neuroprotective Mechanisms
- Autism Spectrum Disorder
- Cognition and Healthy Aging
- Stroke and Cerebral Ischemia
- Neurodegenerative Disease
- The Brain Delivery Problem
- Honest Assessment: Small, Early, Mixed
- Key Points From the Evidence
- Key Research Papers
- Connections
- Featured Videos
Carnosine and Homocarnosine in the Brain
The brain contains carnosine along with a close relative, homocarnosine (gamma-aminobutyryl-histidine), which is actually the dominant imidazole dipeptide in human brain tissue. Carnosine is found especially in the olfactory system, where it is thought to act as a neurotransmitter or neuromodulator, and in glial cells — the support cells that protect and nourish neurons. This tissue-specific concentration is a hint, just as it is in muscle: the body invests in carnosine chemistry precisely in the places under the heaviest oxidative and metabolic load, and the brain, which burns a fifth of the body's energy and is packed with oxidizable fats, is exactly such a place.
Because carnosine is present natively in neural tissue and appears involved in normal signaling, researchers have long suspected it has protective and regulatory roles beyond simple antioxidant defense. Comprehensive reviews of the field (Schon et al., 2019; Berezhnoy et al., 2019) catalog a wide range of proposed brain functions — antioxidant, anti-glycation, metal-buffering, anti-excitotoxic, and pH-regulating — while consistently noting that the clinical evidence lags well behind the mechanistic enthusiasm.
The Neuroprotective Mechanisms
The case for carnosine in the brain rests on several converging, biologically real mechanisms, most demonstrated in cell and animal models:
- Antioxidant defense. Carnosine scavenges reactive oxygen species and, importantly, the reactive carbonyls produced when the brain's abundant polyunsaturated fats are oxidized — the same anti-carbonyl chemistry described on the Anti-Glycation page. Carnosine has been shown to quench acrolein directly in the central nervous system in an animal model of neuroinflammation.
- Zinc and copper buffering. Neurons release zinc and copper during signaling, and excess free zinc or copper is neurotoxic and can seed protein aggregation. Carnosine chelates both metals, and this zinc-buffering role is a central theme in theories of carnosine and neurodegeneration (Kawahara et al., 2018; Trombley et al., 2000).
- Anti-excitotoxicity. Overstimulation by the neurotransmitter glutamate (excitotoxicity) drives damage in stroke and neurodegeneration; carnosine appears to blunt aspects of this cascade in experimental models.
- Anti-aggregation and anti-glycation. By reducing glycation and carbonylation of proteins, carnosine may interfere with the misfolding and aggregation of proteins such as amyloid-beta — the basis for hypotheses about Alzheimer's disease (Hipkiss, 2007; Preston et al., 1998).
These mechanisms are individually well supported in the laboratory. The open question — true throughout this page — is whether they add up to a measurable benefit in a living human brain, given how little intact carnosine survives to get there.
Autism Spectrum Disorder
Autism is the brain condition most associated with carnosine in the public mind, largely because of a single early trial. In 2002, Michael Chez and colleagues ran a small, 8-week, double-blind, placebo-controlled study of oral L-carnosine (800 mg a day) in 31 children with autistic spectrum disorders. After 8 weeks, the children taking L-carnosine showed statistically significant improvements from their starting scores on the Gilliam Autism Rating Scale and a receptive vocabulary test, while the children on placebo showed no statistically significant changes; these results are reported as changes within each group rather than as a direct comparison between the groups (Chez et al., 2002). The proposed rationale involved carnosine's effects on neurological function and possibly on the temporal and frontal lobes.
That trial launched two decades of interest, but later randomized studies have not confirmed a benefit. In a 2020 randomized controlled study by Abraham and colleagues, children aged 3–6 with mild to moderate autism received standard care (occupational and speech therapy) with or without L-carnosine (10–15 mg/kg a day in 2 divided doses) for 2 months; of the 67 children enrolled, 63 completed the study, and no statistically significant difference was found on any of the measured autism, sleep or gut-symptom scores (Abraham et al., 2020). A 2021 systematic review and meta-analysis by the same group (five trials, 215 participants) found no significant difference between L-carnosine and placebo on the Gilliam autism rating scale or the childhood autism rating scale, and concluded that current data do not support the use of L-carnosine in children with autism, because the studies were few and their sample sizes small (Abraham et al., 2021). A broader 2022 network meta-analysis of pharmacological and dietary-supplement treatments for autism, which included 125 randomized trials in children and adolescents, placed carnosine among many interventions with weak or uncertain evidence: it found “some indications of improvement by carnosine” and several other treatments, “yet imprecise and not robust,” with very low or low confidence in these estimates (Siafis et al., 2022).
The honest bottom line: carnosine for autism is an area of legitimate ongoing research with a plausible mechanism and some encouraging small signals, but it is not an established treatment; the 2021 meta-analysis found no significant benefit over placebo. See our Autism page for the broader clinical picture.
Cognition and Healthy Aging
Some of the more encouraging human data come from Japan, where the imidazole dipeptides carnosine and anserine (a methylated carnosine relative abundant in poultry and fish) have been tested for age-related cognitive decline. In a randomized controlled trial, Hisatsune and colleagues (2016) found that anserine/carnosine supplementation preserved verbal episodic memory in elderly participants relative to placebo, with brain-imaging correlates. A later randomized, double-blind, placebo-controlled 12-week trial gave 54 people with mild cognitive impairment either placebo or 750 mg of anserine plus 250 mg of carnosine a day. The active group improved more than placebo on the global Clinical Dementia Rating score (p = 0.023), but showed no benefit on the other tests, including the Mini-Mental State Examination (MMSE), the Wechsler Memory Scale and the Alzheimer's Disease Assessment Scale; when people carrying the APOE4 Alzheimer's-risk gene were analysed separately, they showed benefit on the MMSE (p = 0.025) as well as the global Clinical Dementia Rating (p = 0.026) (Masuoka et al., 2019). A 2021 systematic review with meta-analysis concluded that carnosine/anserine supplementation showed a possible protective effect against cognitive decline, while again emphasizing the small number and modest size of the trials (Caruso et al., 2021). More recently, a post-hoc, secondary analysis of a placebo-controlled randomized trial in healthy adults (the NEAT trial: 299 participants randomized, 2 g of carnosine a day for up to 12 weeks) found statistically significant improvements in overall speed and efficiency on a cognitive test battery in the youngest age group, 23–35 years, while the groups aged 36–50 and 51–65 showed few or no significant improvements (O'Toole et al., 2025). Its clearest results were in young adults, not older ones.
A 2026 systematic review and meta-analysis of 13 studies (12 randomized trials) found that, in five randomized trials, most cognitive function measures did not differ between L-carnosine supplements and placebo. L-carnosine combined with anserine or antioxidant supplements raised the MMSE score by 0.62 points compared with placebo, and the authors rated the strength of the evidence as low (Hsiao et al., 2026).
These are real randomized trials with positive signals, which puts cognition on somewhat firmer footing than most carnosine indications. But the effects are modest, the trials are short, several come from overlapping research groups, and the anserine/carnosine combinations used differ from plain L-carnosine supplements sold elsewhere. It is fair to call cognitive aging the most promising human indication for carnosine chemistry, while stopping well short of calling it proven.
Stroke and Cerebral Ischemia
In animal models of stroke, carnosine looks impressive. Rajanikant and colleagues (2007) showed that carnosine was neuroprotective against permanent focal cerebral ischemia in mice, reducing the size of the brain injury. Multiple subsequent rodent studies have reported that carnosine limits ischemic and reperfusion damage through its combined antioxidant, anti-excitotoxic, anti-inflammatory, and metal-buffering actions, and reviews consistently list stroke among carnosine's most reproducible preclinical successes (Berezhnoy et al., 2019).
The crucial caveat is that this evidence is essentially all preclinical. The history of stroke research is littered with neuroprotective compounds that worked beautifully in rodents and then failed in human trials, because the human brain, the timing of treatment, and the complexity of real strokes differ from tidy animal models. Carnosine for human stroke remains an experimental idea, not a therapy. It is a promising target for properly designed clinical trials, and nothing more than that today.
Neurodegenerative Disease
The neurodegeneration hypothesis ties several carnosine themes together. In Alzheimer's disease, carnosine's ability to inhibit protein glycation, quench carbonyls, and buffer zinc and copper — metals implicated in amyloid aggregation — makes it a theoretically attractive candidate (Hipkiss, 2007; Kawahara et al., 2018). Early cell work showed carnosine and its relatives could protect brain endothelial cells against amyloid-beta toxicity (Preston et al., 1998). In Parkinson's disease, where oxidative stress in the substantia nigra is central, carnosine has shown protective effects in laboratory models, and a 2022 review summarized its antioxidant and neuroprotective actions across neurodegenerative conditions (Solana-Manrique et al., 2022).
A small number of exploratory human studies (for example add-on carnosine in Parkinson's) have reported modest improvements in some measures, but they are pilot-scale and not confirmatory. As with stroke, the mechanism is compelling and the preclinical data are supportive, yet there is no robust human evidence that carnosine prevents or slows Alzheimer's, Parkinson's, or any neurodegenerative disease. See our Alzheimer's Disease and Parkinson's Disease pages for the established clinical picture.
The Brain Delivery Problem
Every brain claim runs into the same wall that limits carnosine elsewhere: serum carnosinase, the blood enzyme that hydrolyzes carnosine within minutes of ingestion, plus the additional barrier of the blood-brain barrier itself. It is genuinely uncertain how much of an oral carnosine dose ever reaches brain tissue intact in humans. Several strategies are being explored to get around this — using anserine (which resists carnosinase somewhat better), designing carnosinase-resistant carnosine analogs and prodrugs, and relying on the brain's own ability to synthesize carnosine from circulating beta-alanine and histidine that cross the barrier.
This delivery uncertainty is a major reason to treat brain trials cautiously. When a study does show benefit, it is not always clear whether the active agent was intact carnosine reaching the brain, the beta-alanine and histidine released from it, or an indirect systemic anti-inflammatory effect. Untangling that is one of the field's central unsolved problems, discussed further on the Sources & Supplements page.
Honest Assessment: Small, Early, Mixed
Pulling the areas together, an evidence-graded summary looks like this:
- Cognitive aging — the strongest human signal, from several small randomized trials of anserine/carnosine, showing modest memory benefit. Promising but unproven.
- Autism — a plausible mechanism and one small early positive report, but a later randomized trial and a 2021 meta-analysis found no significant benefit; not an established treatment.
- Stroke and neurodegeneration — robust and reproducible in animals, essentially untested in rigorous human trials. Experimental only.
- The delivery problem — serum carnosinase and the blood-brain barrier cast doubt on how much oral carnosine reaches the brain, complicating interpretation of every positive study.
Carnosine is a legitimately interesting neuroscience molecule and a reasonable subject for continued clinical research. It is not, on current evidence, a proven brain supplement, and the gap between the elegant mechanisms and the thin human data remains wide.
Key Points From the Evidence
- Carnosine is not a proven brain therapy for autism, dementia, stroke recovery, or Parkinson's. The mechanisms are real; the human proof is not there yet.
- For specific conditions, including autism in children and cognitive concerns in older adults, carnosine remains experimental and has not been tested as a substitute for established care.
- The best-supported brain use — modest memory support in aging — used anserine/carnosine combinations, not necessarily the plain L-carnosine capsules widely sold.
- Dietary intake of carnosine and anserine comes from meat, poultry, and fish; a mixed diet supplies these naturally, as covered on the Sources page.
- Strong marketing claims about carnosine "protecting the brain" or "preventing dementia" run far ahead of the evidence.
Key Research Papers
- Chez MG et al. (2002). Double-blind, placebo-controlled study of L-carnosine supplementation in children with autistic spectrum disorders. J Child Neurol, 17(11):833–837. — PubMed PMID: 12585724
- Schon M et al. (2019). The potential of carnosine in brain-related disorders: a comprehensive review of current evidence. Nutrients, 11(6):1196. — PubMed PMID: 31141890
- Berezhnoy DS et al. (2019). Carnosine as an effective neuroprotector in brain pathology and potential neuromodulator in normal conditions. Amino Acids, 51(1):139–150. — PubMed PMID: 30353356
- Kawahara M, Tanaka KI, Kato-Negishi M (2018). Zinc, carnosine, and neurodegenerative diseases. Nutrients, 10(2):147. — PubMed PMID: 29382141
- Hisatsune T et al. (2016). Effect of anserine/carnosine supplementation on verbal episodic memory in elderly people. J Alzheimers Dis, 50(1):149–159. — PubMed PMID: 26682691
- Masuoka N et al. (2019). Effects of anserine/carnosine supplementation on mild cognitive impairment with APOE4. Nutrients, 11(7):1626. — PubMed PMID: 31319510
- Caruso G et al. (2021). The therapeutic potential of carnosine/anserine supplementation against cognitive decline: a systematic review with meta-analysis. Biomedicines, 9(3):253. — PubMed PMID: 33806459
- O'Toole TE et al. (2025). Carnosine supplementation improves cognitive outcomes in younger participants of the NEAT trial. Neurotherapeutics — PubMed PMID: 39919936
- Rajanikant GK et al. (2007). Carnosine is neuroprotective against permanent focal cerebral ischemia in mice. Stroke, 38(11):3023–3031. — PubMed PMID: 17916766
- Abraham DA et al. (2020). Effect of L-carnosine as adjunctive therapy in the management of children with autism spectrum disorder: a randomized controlled study. Amino Acids, 52(11-12):1521–1528. — PubMed PMID: 33170378
- Abraham DA et al. (2021). Effect of L-carnosine in children with autism spectrum disorders: a systematic review and meta-analysis of randomised controlled trials. Amino Acids, 53(4):575–585. — PubMed PMID: 33704575
- Solana-Manrique C et al. (2022). Antioxidant and neuroprotective effects of carnosine: therapeutic implications in neurodegenerative diseases. Antioxidants (Basel), 11(5):848. — PubMed PMID: 35624713
- Hipkiss AR (2007). Could carnosine or related structures suppress Alzheimer's disease? J Alzheimers Dis, 11(2):229–240. — PubMed PMID: 17522447
- Siafis S et al. (2022). Pharmacological and dietary-supplement treatments for autism spectrum disorder: a systematic review and network meta-analysis. Mol Autism, 13(1):10. — PubMed PMID: 35246237
- Hsiao YF et al. (2026). The effects of carnosine on cognitive function and mental health – a systematic review and meta-analysis. Nutrients, 18(9):1385. — PubMed PMID: 42123986
PubMed Topic Searches
External Authoritative Resources
- PubChem — Carnosine
- PubChem — Anserine (the methylated relative used in cognition trials)
- MedlinePlus — L-Carnosine