⚠ Evidence warning: Clinical trials or other evidence do not support the claim that mice lacking GAD65 have reduced anxiety thresholds and abnormal fear conditioning. This page keeps it as a report of what people, websites or other media say.
Glutamic Acid for Gamma-Aminobutyric Acid (GABA) Production — The Excitatory-to-Inhibitory Switch
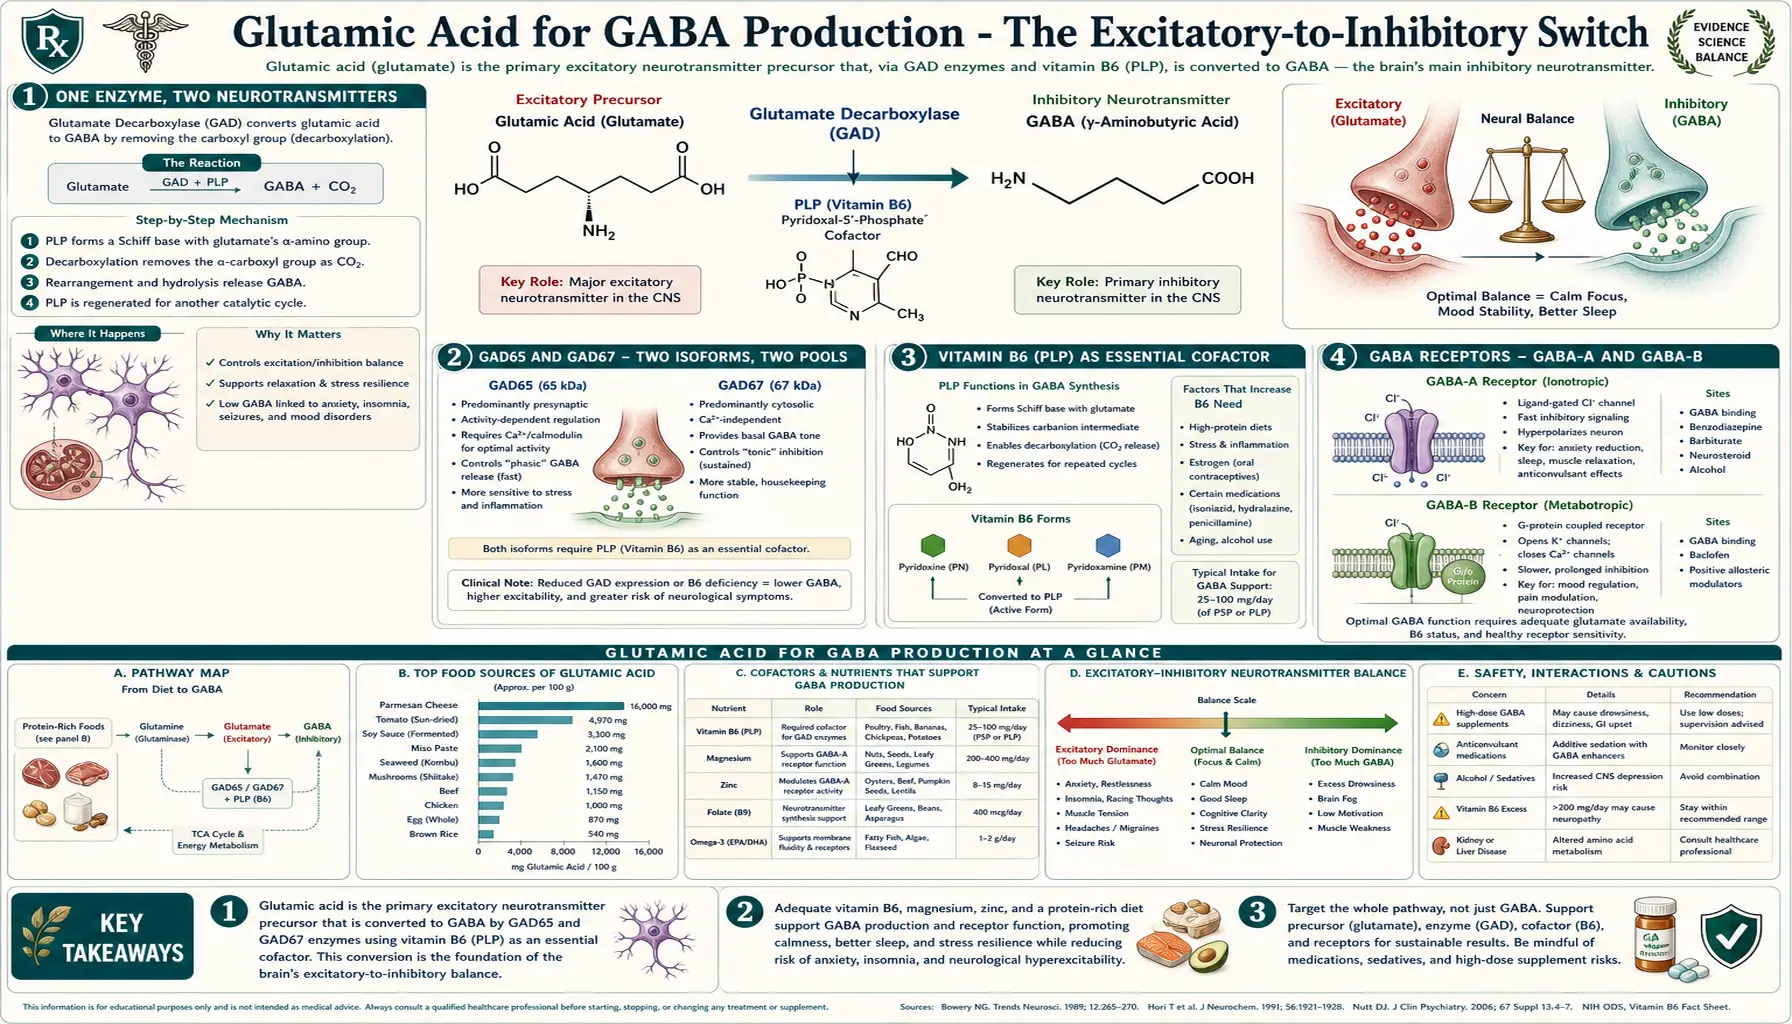
One enzyme — glutamic acid decarboxylase (GAD) — converts the brain's major excitatory neurotransmitter into its major inhibitory neurotransmitter in a single step. By removing a single carboxyl group from glutamate, GAD produces gamma-aminobutyric acid (GABA), which then binds gamma-aminobutyric acid-A and gamma-aminobutyric acid-B receptors throughout the central nervous system to dampen neuronal firing. The reaction is absolutely dependent on pyridoxal 5'-phosphate (PLP), the active form of vitamin B6, as a covalently bound cofactor — making B6 status one of the most direct nutritional determinants of brain excitatory-inhibitory balance. Two GAD isoforms exist: GAD65, concentrated in synaptic terminals and responsible for the rapidly available gamma-aminobutyric acid pool that supports phasic inhibition, and GAD67, distributed throughout the neuronal cytoplasm and responsible for the bulk tonic gamma-aminobutyric acid pool. Both isoforms are targets of autoantibodies in two important autoimmune diseases: stiff-person syndrome (where high-titer anti-GAD65 antibodies are essentially pathognomonic) and a substantial minority of type 1 diabetes (where anti-GAD65 antibodies serve as one of the canonical pre-clinical autoimmune markers, since pancreatic beta cells also express GAD65). This deep dive walks through the chemistry of the GAD reaction, the B6 cofactor mechanism, the regional distribution of GABAergic inhibition, the natural and pharmacological gamma-aminobutyric acid-A modulators (alcohol, benzodiazepines, barbiturates, anesthetics), and the autoimmune disorders that target GAD itself.
Table of Contents
- One Enzyme, Two Neurotransmitters
- GAD65 and GAD67 — Two Isoforms, Two Pools
- Vitamin B6 (PLP) as Essential Cofactor
- Gamma-Aminobutyric Acid Receptors — Gamma-Aminobutyric Acid-A and Gamma-Aminobutyric Acid-B
- Tonic vs Phasic Inhibition
- Gamma-Aminobutyric Acid-A Modulators (Benzos, Barbiturates, Alcohol, Anesthetics)
- Anti-GAD Autoimmunity — Stiff-Person Syndrome and Type 1 Diabetes
- Nutritional Strategies to Support Gamma-Aminobutyric Acid Synthesis
- How Much Oral Gamma-Aminobutyric Acid Reaches the Brain
- Clinical Applications: Anxiety, Insomnia, Seizures
- Key Research Papers
- Connections
- Featured Videos
One Enzyme, Two Neurotransmitters
The economy of the gamma-aminobutyric acid-synthesizing reaction is one of biology's most elegant pieces of design. The same molecule — glutamate — that 90% of the brain's excitatory synapses use as their messenger is converted, in a single enzymatic step, into the principal inhibitory neurotransmitter. The reaction:
glutamic acid → GABA + CO2
Glutamate has two carboxyl groups (alpha and gamma); GAD removes the alpha-carboxyl, releasing CO2 and leaving gamma-aminobutyric acid, which retains the gamma-carboxyl as part of its name (gamma-aminobutyric acid). The same neuron, the same metabolic precursor pool, the same vesicular machinery — the only thing that distinguishes a glutamatergic excitatory neuron from a GABAergic inhibitory neuron is whether the cell expresses GAD or not. Neurons that express GAD load their synaptic vesicles with gamma-aminobutyric acid (using the vesicular gamma-aminobutyric acid transporter, VGAT); neurons that lack GAD load with glutamate (using VGLUT1/2/3).
This binary choice happens during neuronal development. In the cerebral cortex, GABAergic interneurons (about 20% of all cortical neurons) migrate from the medial and caudal ganglionic eminences in the ventral forebrain to populate the dorsal cortex, where they take up residence among the much more numerous glutamatergic pyramidal neurons. The two cell types coexist in a roughly 1:4 ratio in the mature cortex and engage in tightly choreographed back-and-forth signaling that produces the cortex's rich repertoire of oscillations (theta, gamma, beta, alpha rhythms) and the precise spike timing needed for sensory processing and cognition.
Without GAD activity, the entire inhibitory side of the network collapses, and runaway excitation produces seizures. Indeed, the very first inborn error of metabolism shown to cause seizures responsive to vitamin therapy was pyridoxine-dependent epilepsy — a condition where insufficient PLP availability impairs GAD function and produces neonatal seizures that resolve dramatically when high-dose pyridoxine is administered.
GAD65 and GAD67 — Two Isoforms, Two Pools
Mammals express two genes encoding glutamic acid decarboxylase, named for their approximate molecular weights:
- GAD65 (gene: GAD2, chromosome 10p11) is concentrated in nerve terminals, anchored to synaptic vesicle membranes via palmitoylation of its N-terminus. GAD65 binds PLP loosely and reversibly, allowing rapid activation when PLP is available. It is responsible for the synaptic pool of gamma-aminobutyric acid — the rapidly mobilizable, vesicle-loaded gamma-aminobutyric acid that gets released in response to action potentials and mediates fast phasic inhibition.
- GAD67 (gene: GAD1, chromosome 2q31) is distributed throughout the neuronal cytoplasm and binds PLP tightly. It produces the bulk of total brain gamma-aminobutyric acid, supplying the tonic cytoplasmic pool that supports baseline GABAergic tone and is also a metabolic substrate for the gamma-aminobutyric acid shunt (a small-flux side branch of the citric acid cycle).
The two isoforms have markedly different developmental patterns. GAD67 is expressed early and provides the gamma-aminobutyric acid needed for the developing nervous system (where gamma-aminobutyric acid is actually depolarizing and trophic in immature neurons due to a high intracellular chloride concentration that reverses at synaptic maturation). GAD65 expression rises later and reaches adult levels around the time of synapse pruning and circuit refinement, suggesting a role in experience-dependent plasticity. In a 1997 study (Asada and colleagues), mice lacking GAD67 were born in normal numbers but died of severe cleft palate during the first morning after birth; in the cerebral cortex of these newborn mice, GAD activity was 20% and GABA content 7% of normal, yet their brains showed no visible defects. The authors called this the first demonstration of a role for GAD67-made GABA in the development of tissue outside the nervous system. The same group reported that mice lacking GAD65 have unchanged brain GABA content and unchanged behavior, apart from a slight increase in susceptibility to seizures. Mice lacking GAD65 are viable but have reduced anxiety thresholds, increased seizure susceptibility, and abnormal fear conditioning.
Importantly, GAD65 is the dominant target of anti-GAD autoantibodies in stiff-person syndrome and a major target in type 1 diabetes, as discussed below.
Vitamin B6 (PLP) as Essential Cofactor
The chemistry that allows GAD to decarboxylate glutamate is the same chemistry that underpins essentially every amino acid transamination, decarboxylation, racemization, and elimination reaction in biology: the pyridoxal 5'-phosphate (PLP) Schiff-base mechanism. PLP is the active phosphorylated form of vitamin B6 (pyridoxine, pyridoxal, or pyridoxamine in food). Inside the enzyme's active site, the aldehyde of PLP forms a covalent Schiff base (an internal aldimine) with a specific lysine residue. When glutamate enters the active site, its alpha-amino group displaces the lysine, forming an external aldimine between PLP and the substrate. PLP then acts as an electron sink, stabilizing the carbanion intermediate that forms when the alpha-carboxyl departs as CO2. The product gamma-aminobutyric acid is released, and the enzyme regenerates the lysine-PLP internal aldimine to begin the next catalytic cycle.
This dependence on PLP is the molecular reason why vitamin B6 status directly determines gamma-aminobutyric acid synthesis capacity. The relationships are clinical:
- Pyridoxine-dependent epilepsy (PDE) is an autosomal recessive condition caused by mutations in the antiquitin gene (ALDH7A1), which functions in the lysine catabolism pathway. Mutations cause accumulation of alpha-aminoadipic semialdehyde, which spontaneously cyclizes to piperidine-6-carboxylate and irreversibly traps PLP. Affected newborns present with refractory seizures that respond dramatically to high-dose pyridoxine within minutes — one of the most striking responses in all of pediatric neurology.
- The anti-tuberculosis drug isoniazid is a PLP antagonist (it forms a hydrazone with PLP, depleting the free pool) and causes pyridoxine-responsive peripheral neuropathy and, at high doses, seizures. Co-administration of pyridoxine is standard.
- The mushroom Gyromitra esculenta contains gyromitrin, which is hydrolyzed in vivo to monomethylhydrazine — another PLP antagonist that causes seizures responsive to high-dose pyridoxine.
- Chronic alcohol abuse depletes PLP via multiple mechanisms and contributes to alcohol withdrawal seizures, which often respond partially to thiamine and pyridoxine repletion alongside benzodiazepines.
- Marginal B6 deficiency (common in elderly populations, pregnancy, and those on certain medications including isoniazid, cycloserine, hydralazine, and L-DOPA) reduces overall GAD activity and may contribute to subclinical anxiety, sleep disturbance, and reduced seizure threshold.
The clinically meaningful B6 intake range for adults is approximately 1.3-2.0 mg/day from food and supplements combined, with a US upper limit (Institute of Medicine) of 100 mg/day, set because sustained high-dose pyridoxine causes sensory neuropathy. In 2023 the European Food Safety Authority (EFSA) set a much lower adult upper limit of 12 mg/day (including pregnancy and breastfeeding; 2.2–10.7 mg/day for children depending on age), because nerve damage (peripheral neuropathy) has been linked to intakes far below 100 mg; it identified 50 mg/day as its reference point and noted that regular users of high-dose B6 supplements are the group likely to exceed the limit. Naturopathic protocols for gamma-aminobutyric acid support commonly use 25-50 mg/day of pyridoxal-5-phosphate (the activated form) or pyridoxine HCl — two to four times the EFSA limit. See the Vitamin B6 page for more on forms, dosing, and the neuropathy risk at chronic high doses.
Gamma-Aminobutyric Acid Receptors — Gamma-Aminobutyric Acid-A and Gamma-Aminobutyric Acid-B
Gamma-aminobutyric acid signals through two structurally and functionally distinct receptor families, analogous to the ionotropic vs. metabotropic split on the glutamate side:
- Gamma-aminobutyric acid-A receptors are pentameric ligand-gated chloride channels assembled from combinations of alpha (1-6), beta (1-3), gamma (1-3), delta, epsilon, theta, pi, and rho subunits. The dominant central nervous system subtype is alpha1-beta2-gamma2 (in a 2:2:1 stoichiometry). Gamma-aminobutyric acid binding opens the channel, allowing chloride influx that hyperpolarizes the postsynaptic neuron and reduces its excitability. Gamma-aminobutyric acid-A receptors are the targets of essentially all clinical sedative-hypnotic drugs: benzodiazepines, barbiturates, alcohol, propofol, etomidate, and the volatile and intravenous anesthetics all act here, each through distinct binding sites on the receptor.
- Gamma-aminobutyric acid-B receptors are seven-transmembrane G-protein coupled receptors coupled to Gi/Go. They produce slower, longer-lasting inhibition through three mechanisms: (1) opening of G-protein-gated inwardly-rectifying potassium (GIRK) channels postsynaptically, hyperpolarizing the cell; (2) closing of voltage-gated calcium channels presynaptically, reducing neurotransmitter release; and (3) inhibition of adenylate cyclase, reducing intracellular cAMP. The clinical gamma-aminobutyric acid-B agonist baclofen is used for spasticity in multiple sclerosis, spinal cord injury, and cerebral palsy, and is sometimes used off-label for alcohol use disorder.
The relative balance between gamma-aminobutyric acid-A and gamma-aminobutyric acid-B contributions varies by region. Hippocampal pyramidal cells receive substantial gamma-aminobutyric acid-B input that contributes to the slow afterhyperpolarization and the regulation of theta-rhythm oscillations. Cortical layer 1 has dense gamma-aminobutyric acid-B-mediated inhibition that gates ascending thalamic input. Striatal medium spiny neurons receive prominent gamma-aminobutyric acid-B-mediated presynaptic inhibition.
The pharmacological gamma-aminobutyric acid-A site that allows benzodiazepines (diazepam, lorazepam, alprazolam, clonazepam, etc.) to enhance the receptor is at the interface between alpha and gamma subunits and is present only on receptors containing certain alpha subunits (alpha1, alpha2, alpha3, alpha5 are benzodiazepine-sensitive; alpha4 and alpha6 are insensitive). This subunit selectivity explains why some Z-drugs targeting only alpha1 (zolpidem, an approved prescription sleep drug) produce primarily hypnosis without the anxiolytic, anticonvulsant, and myorelaxant effects of broader-spectrum benzodiazepines.
Tonic vs Phasic Inhibition
GABAergic inhibition in the brain operates in two temporally distinct modes:
- Phasic inhibition is mediated by synaptic gamma-aminobutyric acid-A receptors (typically alpha1-beta-gamma2 containing) and produces brief, large-amplitude inhibitory postsynaptic currents in response to vesicular gamma-aminobutyric acid release. Phasic inhibitory postsynaptic currents (IPSCs) decay over milliseconds and provide the rapid moment-to-moment shaping of neuronal firing patterns.
- Tonic inhibition is mediated by extrasynaptic gamma-aminobutyric acid-A receptors (typically containing alpha4, alpha5, alpha6, or delta subunits) that have very high affinity for gamma-aminobutyric acid and are persistently activated by the low ambient concentration of gamma-aminobutyric acid in the extracellular space (estimated at 0.1-1 micromolar). Tonic inhibition produces a small, persistent chloride current that sets the resting input resistance of the cell and the gain of synaptic responses.
The therapeutic implications matter. Benzodiazepines preferentially enhance phasic inhibition (they require the gamma2 subunit, present at synapses). The hypnotic gaboxadol (a selective delta-containing extrasynaptic receptor agonist) enhances tonic inhibition. Neurosteroids like allopregnanolone (an endogenous metabolite of progesterone) and the synthetic neurosteroid brexanolone (U.S. Food and Drug Administration-approved for postpartum depression in 2019) preferentially potentiate delta-containing extrasynaptic gamma-aminobutyric acid-A receptors. Ethanol enhances both synaptic and extrasynaptic gamma-aminobutyric acid-A receptors but with different concentration-response relationships, contributing to its complex behavioral profile.
The mechanism of tonic inhibition explains why the elimination of just one or two key GAD-expressing interneuron populations can dramatically alter the excitability of an entire cortical region — the ambient gamma-aminobutyric acid tone supporting tonic inhibition depends on the small fraction of gamma-aminobutyric acid that escapes from synaptic release and is not immediately reuptaken by GAT-1/GAT-3 transporters.
Gamma-Aminobutyric Acid-A Modulators (Benzos, Barbiturates, Alcohol, Anesthetics)
The gamma-aminobutyric acid-A receptor is one of the most pharmacologically modulated proteins in clinical medicine. The major drug classes acting at this receptor:
- Benzodiazepines (diazepam, lorazepam, alprazolam, clonazepam, midazolam, oxazepam, temazepam, triazolam, etc.) bind the benzodiazepine site at the alpha-gamma interface and increase the frequency of gamma-aminobutyric acid-A channel openings when gamma-aminobutyric acid is bound. Because they require gamma-aminobutyric acid for activity, they have a ceiling effect and are relatively safe in overdose unless combined with other central nervous system (CNS) depressants. Reversal agent: flumazenil.
- Barbiturates (phenobarbital, pentobarbital, thiopental, butalbital) bind a distinct site on gamma-aminobutyric acid-A receptors and increase the duration of channel opening. At higher concentrations they directly open the channel without gamma-aminobutyric acid, removing the ceiling effect — the reason barbiturates are far more dangerous in overdose than benzodiazepines. Largely replaced by safer alternatives but still used for refractory status epilepticus, induction of anesthesia (thiopental, methohexital), and tension headache (butalbital combinations: the US label for butalbital, acetaminophen and caffeine tablets lists the relief of tension, or muscle-contraction, headache, states that evidence on multiple recurrent headaches is unavailable, and warns that butalbital is habit-forming and potentially abusable).
- Z-drugs (zolpidem, zaleplon, eszopiclone) bind the benzodiazepine site but with selectivity for alpha1-containing receptors, producing primarily hypnotic effects with less anxiolytic and myorelaxant action. Tolerance and dependence still occur with chronic use.
- Alcohol (ethanol) potentiates gamma-aminobutyric acid-A receptors at intoxicating concentrations (5-50 mM blood alcohol), particularly the extrasynaptic delta-containing subtypes. This gamma-aminobutyric acid-A potentiation accounts for much of alcohol's sedative and anxiolytic effects; alcohol also has N-methyl-D-aspartate (NMDA) antagonist effects that contribute to its dissociative qualities and the rebound hyperexcitability of withdrawal.
- Volatile and intravenous anesthetics — isoflurane, sevoflurane, desflurane, propofol, etomidate — all potentiate gamma-aminobutyric acid-A receptors as a major (though not sole) mechanism of producing general anesthesia. Each agent has a distinctive binding profile.
- Neurosteroids — allopregnanolone, pregnanolone, tetrahydrodeoxycorticosterone (THDOC) — are endogenous progesterone and deoxycorticosterone metabolites that powerfully potentiate gamma-aminobutyric acid-A receptors at low nanomolar concentrations. The synthetic version brexanolone was U.S. Food and Drug Administration-approved in 2019 for postpartum depression. The oral neurosteroid zuranolone was approved in 2023, also for postpartum depression.
- Gaboxadol (chemical code THIP) is an experimental delta-subunit-selective extrasynaptic gamma-aminobutyric acid-A agonist that was developed for insomnia and explored for fragile X syndrome.
This pharmacological abundance reflects the central role of gamma-aminobutyric acid-A inhibition in setting overall brain state. The Goldilocks principle applies: too little gamma-aminobutyric acid tone produces anxiety, insomnia, and seizures; too much produces sedation, ataxia, and coma. Most of clinical sedative-hypnotic practice is the art of finding the right gamma-aminobutyric acid-A modulator for the right patient at the right dose.
Anti-GAD Autoimmunity — Stiff-Person Syndrome and Type 1 Diabetes
Anti-GAD65 autoantibodies are clinically significant in two very different diseases:
Stiff-person syndrome (SPS) is a rare autoimmune neurological disorder characterized by progressive muscle stiffness, painful spasms, exaggerated startle responses, and a tendency to develop a hyperlordotic posture. The high-titer presence of anti-GAD65 antibodies (often >100-fold the levels seen in type 1 diabetes mellitus, T1DM) is essentially pathognomonic — present in 60-80% of cases. The remaining cases include antibodies against amphiphysin (often paraneoplastic, associated with breast cancer), glycine receptor (the rare PERM variant: progressive encephalomyelitis with rigidity and myoclonus), or other targets. The proposed mechanism is antibody-mediated inhibition of GAD activity and impaired GABAergic inhibition, producing the characteristic stiffness and spasms, but this is not settled: a 2009 review by Dalakas states that anti-GAD antibodies are an excellent diagnostic marker while their role in causing the disease is uncertain. A second antibody target has been found — GABARAP, a protein at GABA synapses — and circulating anti-GABARAP antibodies that reduce GABA-A receptor expression on GABAergic neurons were present in up to 65% of patients. Treatment includes high-dose benzodiazepines (diazepam 60-100 mg/day or higher), baclofen, intravenous immunoglobulin (IVIG), plasmapheresis, and rituximab in refractory cases. The same review notes that most patients respond to GABA-enhancing drugs but the high doses needed cause unacceptable side effects, and that the disease clearly responds to intravenous immunoglobulin but repeated infusions are needed to keep the response. Celine Dion publicly disclosed her SPS diagnosis in 2022, raising awareness of this previously obscure condition.
Type 1 diabetes mellitus is autoimmune destruction of pancreatic beta cells, and anti-GAD65 antibodies are one of the four classic islet autoantibodies used to identify pre-clinical and clinical T1DM (alongside anti-insulin, anti-IA2, and anti-ZnT8 antibodies). The reason beta cells are vulnerable to anti-GAD autoimmunity is that pancreatic beta cells express GAD65 (originally a surprise — gamma-aminobutyric acid was assumed to be a central nervous system-only neurotransmitter). Beta cells produce gamma-aminobutyric acid as part of their islet paracrine signaling, where gamma-aminobutyric acid dampens glucagon secretion from neighboring alpha cells. The shared antigen explains why GAD-targeted immune tolerization (a GAD65-alum antigen-specific immunotherapy) was developed as an attempted T1DM intervention, though clinical results have been modest.
Anti-GAD antibodies (typically at lower titers than in SPS) are also found in some cases of cerebellar ataxia, limbic encephalitis, and pharmacoresistant temporal lobe epilepsy. The mechanistic understanding of how anti-GAD antibodies produce disease is incomplete — some of the antibody effect may be on cell-surface GAD65, but GAD is largely intracellular, so the relationship between autoantibody titer and clinical phenotype is still being worked out.
Nutritional Strategies to Support Gamma-Aminobutyric Acid Synthesis
Naturopathic practitioners describe supporting endogenous gamma-aminobutyric acid synthesis from the glutamate pool by attending to several modifiable factors:
- Vitamin B6 (PLP) — the absolute cofactor. Adequate B6 intake is the single most important nutritional determinant of GAD activity. Naturopathic protocols commonly use 25-50 mg/day of pyridoxal-5-phosphate (P5P) or pyridoxine HCl. The US upper limit is 100 mg/day, and the 2023 EFSA upper limit for adults is 12 mg/day, both set because of pyridoxine-induced sensory neuropathy.
- Magnesium — allosterically potentiates gamma-aminobutyric acid-A receptor function and is the natural N-methyl-D-aspartate channel blocker (see the Neurotransmission page). Practitioners commonly use magnesium glycinate or magnesium L-threonate at 300-600 mg/day elemental magnesium. The US Institute of Medicine upper limit for magnesium from supplements (not food) is 350 mg/day for adolescents and adults, based on diarrhea at 360 mg/day; magnesium from food has no upper limit. Magnesium L-threonate has some evidence for superior brain penetration but is more expensive.
- Zinc — modulates gamma-aminobutyric acid-A receptor function, particularly the gamma2-containing subtypes. Practitioners commonly cite 15-30 mg/day; the US recommended dietary allowance is 8 mg/day for women and 11 mg/day for men, and the adult upper limit is 40 mg/day from food, water and supplements combined, based on reduced copper status.
- L-theanine — an amino acid analog of glutamate found in tea (Camellia sinensis), reaches the brain and modestly enhances gamma-aminobutyric acid, dopamine, and serotonin while producing alpha-wave electroencephalogram (EEG) activity. Commonly used dose 100-400 mg.
- Taurine — a sulfonic amino acid that is itself a weak gamma-aminobutyric acid-A receptor agonist and supports GABAergic tone. Commonly used dose 500-3000 mg/day. See the Taurine page.
- Glycine — an inhibitory neurotransmitter in its own right (spinal cord and brainstem) and a N-methyl-D-aspartate co-agonist (forebrain — making the role complex). Commonly used dose 3-10 g at bedtime for sleep support.
- Botanical GABAergic agents — valerian root, passionflower, lemon balm, skullcap, ashwagandha, kava (with hepatotoxicity caveats), and chamomile all have varying degrees of GABAergic activity. They work through multiple mechanisms including direct gamma-aminobutyric acid-A allosteric modulation and reuptake inhibition.
- Excitatory load — chronic stress, caffeine, alcohol withdrawal, sleep deprivation, and inflammatory states all increase excitatory tone and create disproportionate demand on the gamma-aminobutyric acid system. Lifestyle measures that reduce chronic sympathetic activation (sleep, regular exercise, meditation, breath work) support net inhibitory tone.
In people with anxiety, insomnia, restless legs syndrome, migraine, or seizure disorders, naturopathic practitioners commonly begin with an assessment of B6 and magnesium status. See the Anxiety and Epilepsy pages for condition-specific management.
How Much Oral Gamma-Aminobutyric Acid Reaches the Brain
One of the most persistent questions in supplement marketing is whether oral gamma-aminobutyric acid actually reaches the brain. The answer, despite decades of confident claims by supplement manufacturers, is: poorly, if at all, through the blood-brain barrier directly. Gamma-aminobutyric acid is a small, polar zwitterion. It does not have a dedicated transporter at the blood-brain barrier, and passive diffusion is limited. Multiple studies using radioactive tracers and microdialysis have found that systemically administered gamma-aminobutyric acid produces minimal increases in brain gamma-aminobutyric acid concentrations.
However, the absence of direct blood-brain barrier (BBB) penetration does not necessarily mean oral gamma-aminobutyric acid has no effect. Two indirect mechanisms have been proposed:
- Enteric nervous system effects — gamma-aminobutyric acid receptors are expressed on enteric neurons, vagal afferents, and gut endocrine cells. Oral gamma-aminobutyric acid may signal through these peripheral pathways to influence parasympathetic tone and stress reactivity via the vagus nerve. Electroencephalogram studies have shown that oral gamma-aminobutyric acid (around 100 mg) can produce measurable changes in brain alpha-wave activity within an hour, possibly through these enteric routes. In one such study (Abdou and colleagues, 2006), 13 volunteers had brain-wave recordings after water, GABA or L-theanine; 60 minutes after GABA, alpha waves rose and beta waves fell compared with water or L-theanine. In a second test, 8 people with a fear of heights crossed a suspension bridge: saliva immunoglobulin A (IgA, an immune antibody) fell markedly in the placebo group but stayed significantly higher in the GABA group. Both studies were very small.
- BBB permeability in pathological states — in conditions involving BBB disruption (severe inflammation, sepsis, traumatic brain injury, advanced multiple sclerosis), gamma-aminobutyric acid may penetrate the brain more readily. The clinical relevance for routine supplement use is unclear.
The pragmatic conclusion is that oral gamma-aminobutyric acid at typical supplement doses (100-750 mg) may produce mild anxiolytic effects in some users, but the mechanism is unlikely to be direct brain delivery. Practitioners who emphasize the synthesis precursors (glutamic acid, B6, magnesium) and indirect modulators (L-theanine, taurine, botanicals) regard that approach as more mechanistically sound than oral gamma-aminobutyric acid itself.
Clinical Applications: Anxiety, Insomnia, Seizures
The clinical consequences of inadequate gamma-aminobutyric acid synthesis (or excessive glutamate signaling unmatched by inhibitory counterbalance) span psychiatry and neurology:
- Generalized anxiety disorder — benzodiazepines work, demonstrating that gamma-aminobutyric acid-A potentiation alleviates anxiety. Long-term benzodiazepine use carries dependence, cognitive impairment, and increased dementia risk concerns. Naturopathic practitioners describe addressing B6, magnesium, sleep hygiene, exercise and stress, and using L-theanine, taurine, ashwagandha or valerian; severe cases are usually referred for cognitive behavioral therapy (CBT) and medication.
- Insomnia — gamma-aminobutyric acid-A modulators (benzodiazepines, Z-drugs) dominate prescription sleep aids but have tolerance, rebound, and cognitive concerns. Naturopathic practitioners describe sleep hygiene, light exposure timing, magnesium, glycine 3 g at bedtime, melatonin, valerian and L-theanine. The Fatigue page covers related sleep information.
- Migraine — glutamatergic hyperexcitability is implicated; magnesium 400 mg/day, riboflavin 400 mg/day, and coenzyme Q10 (CoQ10) have some preventive evidence. Anti-calcitonin gene-related peptide (CGRP) monoclonal antibodies have transformed migraine prophylaxis pharmacology, but the gamma-aminobutyric acid/glutamate balance remains relevant.
- Epilepsy — most antiepileptic drugs work at least partly through gamma-aminobutyric acid enhancement (valproate, vigabatrin, benzodiazepines, barbiturates, tiagabine) or glutamate reduction (lamotrigine, topiramate, perampanel). Nutritional ketosis (ketogenic diet) is an effective intervention for refractory pediatric epilepsy and works partly through enhanced gamma-aminobutyric acid synthesis. Pyridoxine repletion is standard in any neonatal seizure work-up.
- Restless legs syndrome / periodic limb movement disorder — iron deficiency is the primary correctable cause. Gabapentin and pregabalin, although built to resemble GABA, are now understood to act mainly by inhibiting voltage-gated calcium channels that contain the alpha2delta-1 subunit, not through GABA targets (Sills 2006). The American Academy of Sleep Medicine (AASM) guideline published in January 2025 sets as good practice regular testing of ferritin and transferrin saturation in every patient with significant restless legs, with iron treatment (by mouth or intravenous) when ferritin is 75 ng/mL or lower or transferrin saturation is below 20%. It strongly recommends gabapentin enacarbil, gabapentin, pregabalin and intravenous ferric carboxymaltose, and it suggests against the standard use of the dopamine-acting drugs levodopa, pramipexole and transdermal rotigotine, because of worsening over long-term use (augmentation).
- Tinnitus — central gain hypotheses implicate reduced GABAergic inhibition in auditory cortex; GABAergic agents have modest clinical effects.
The takeaway: the glutamate-to-GABA conversion is one of the most clinically consequential single biochemical steps in the body. Supporting it through adequate B6 and magnesium status is one of the most underappreciated nutritional interventions in neuropsychiatric care.
Key Research Papers
- Roberts E, Frankel S (1950). Gamma-aminobutyric acid in brain: its formation from glutamic acid. Journal of Biological Chemistry. — PubMed PMID: 14794689
- Erlander MG et al. (1991). Two genes encode distinct glutamate decarboxylases. Neuron. — PubMed PMID: 2069816
- Asada H et al. (1997). Cleft palate and decreased brain gamma-aminobutyric acid in mice lacking the 67-kDa isoform of glutamic acid decarboxylase. PNAS. — PubMed PMID: 9177246
- Solimena M et al. (1988). Autoantibodies to glutamic acid decarboxylase in a patient with stiff-man syndrome, epilepsy, and type I diabetes mellitus. NEJM. — PubMed PMID: 3281011
- Baekkeskov S et al. (1990). Identification of the 64K autoantigen in insulin-dependent diabetes as the GABA-synthesizing enzyme glutamic acid decarboxylase. Nature. — PubMed PMID: 1697648
- Mills PB et al. (2006). Mutations in antiquitin in individuals with pyridoxine-dependent seizures. Nature Medicine. — PubMed PMID: 16491085
- Sigel E, Steinmann ME (2012). Structure, function, and modulation of GABA(A) receptors. Journal of Biological Chemistry. — PubMed PMID: 23038269
- Meldrum BS (1989). GABAergic mechanisms in the pathogenesis and treatment of epilepsy. British Journal of Clinical Pharmacology. — PubMed PMID: 2667605
- Meltzer-Brody S et al. (2018). Brexanolone injection in post-partum depression: two multicentre, double-blind, randomised, placebo-controlled, phase 3 trials. The Lancet. — PubMed PMID: 30177236
- Boonstra E et al. (2015). Neurotransmitters as food supplements: the effects of GABA on brain and behavior. Frontiers in Psychology. — PubMed PMID: 26500584
- Dalakas MC (2009). Stiff person syndrome: advances in pathogenesis and therapeutic interventions. Current Treatment Options in Neurology. — PubMed PMID: 19210912
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA), Turck D, Bohn T, et al. (2023). Scientific opinion on the tolerable upper intake level for vitamin B6. EFSA Journal. — PubMed PMID: 37207271
- Institute of Medicine (1997). Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. National Academies Press. — doi:10.17226/5776
- Institute of Medicine (2001). Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. National Academies Press. — doi:10.17226/10026
- Sills GJ (2006). The mechanisms of action of gabapentin and pregabalin. Current Opinion in Pharmacology. — PubMed PMID: 16376147
- Winkelman JW, Berkowski JA, DelRosso LM, et al. (2025). Treatment of restless legs syndrome and periodic limb movement disorder: an American Academy of Sleep Medicine clinical practice guideline. Journal of Clinical Sleep Medicine. — PubMed PMID: 39324694
- Abdou AM, Higashiguchi S, Horie K, et al. (2006). Relaxation and immunity enhancement effects of gamma-aminobutyric acid (GABA) administration in humans. BioFactors. — PubMed PMID: 16971751
PubMed Topic Searches
Connections
- All Amino Acids
- Glutamic Acid Benefits Hub
- Glutamic Acid Overview
- Neurotransmission & Excitatory Signaling
- Nitrogen Metabolism
- Glutamate & MSG
- Vitamin B6 (PLP Cofactor)
- Magnesium
- Taurine (Gamma-Aminobutyric Acid-A Co-Agonist)
- Glycine
- Glutamine
- Anxiety
- Epilepsy
- Fatigue & Sleep
- Stress Management
- Gut-Brain Axis
- History
- Sources