⚠ Evidence warning: Clinical trials or other evidence do not support the claim that the Marchesini trial reduced recurrence of overt hepatic encephalopathy. This page keeps it as a report of what people, websites or other media say.
Valine for Nitrogen Balance and Wound Healing
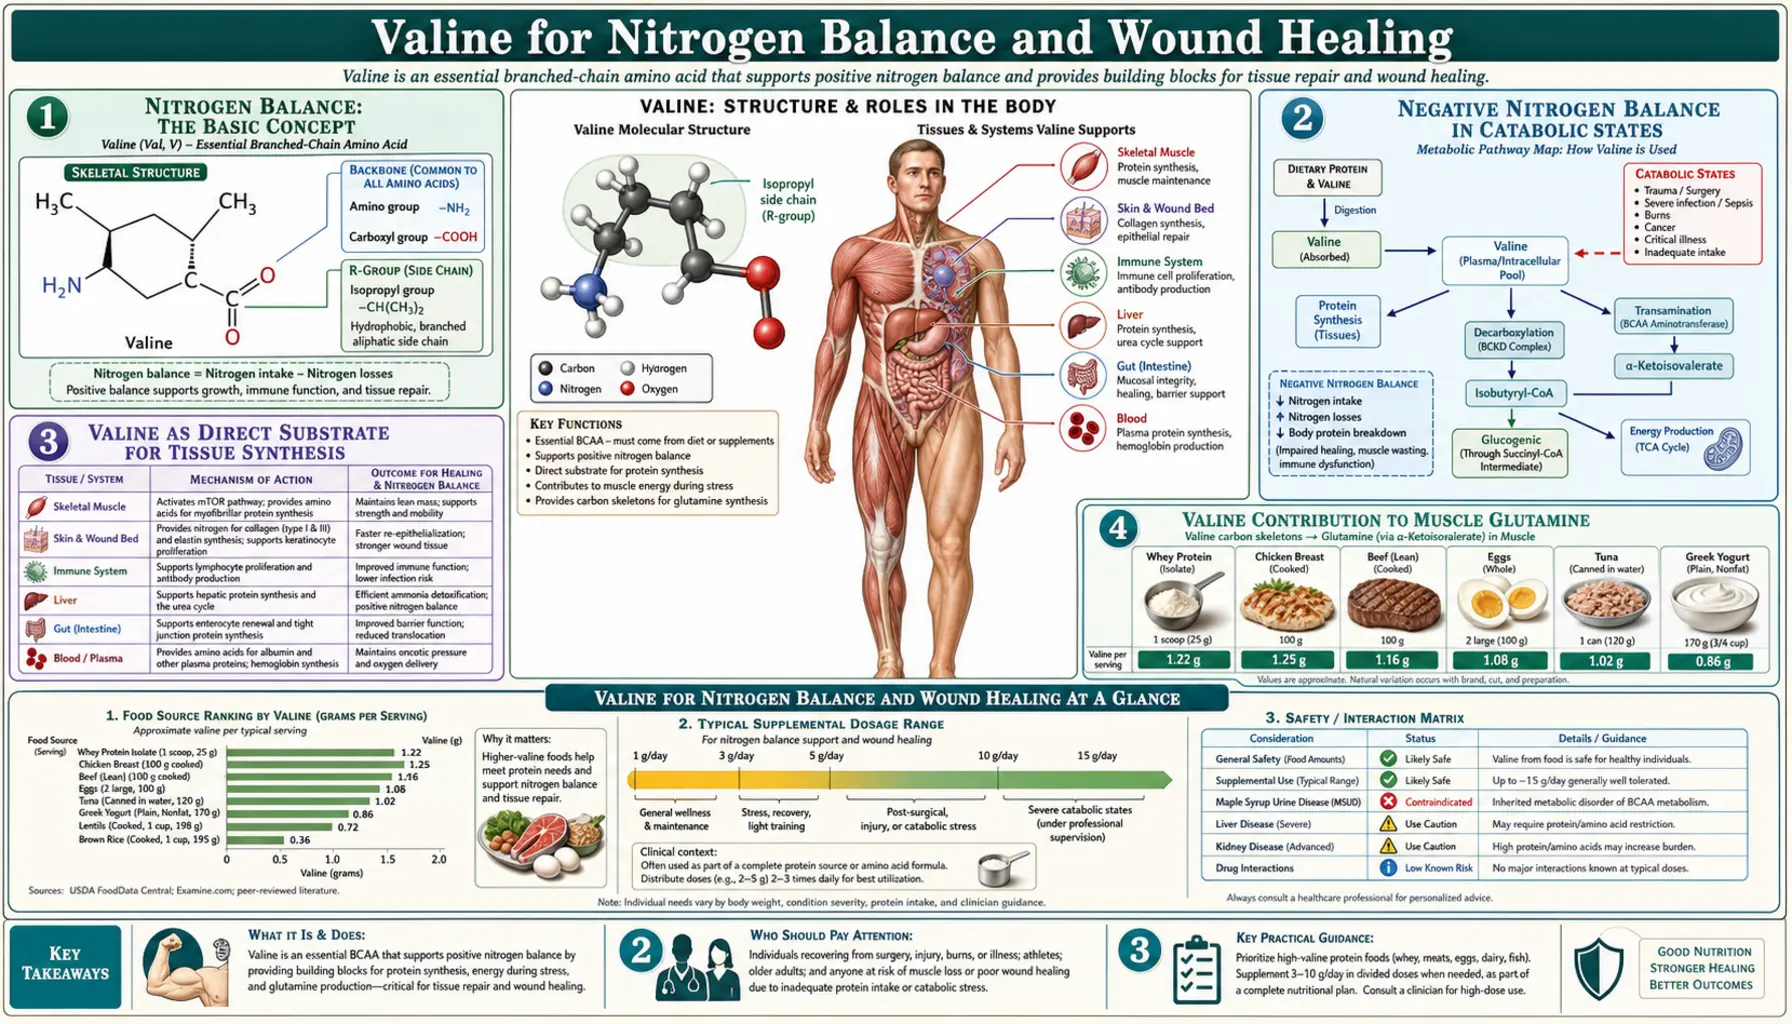
Surgical recovery, traumatic injury, severe burns, and chronic wasting diseases share a common biochemical signature: negative nitrogen balance, in which urinary nitrogen excretion exceeds dietary nitrogen intake. Net protein loss in this state runs at 50-100 g/day in major trauma and up to 200 g/day in extensive burns — equivalent to losing a quarter of total muscle mass per month if uncorrected. Valine's contribution to reversing this loss operates through three connected mechanisms: (1) direct substrate for accelerated tissue synthesis at wounds and surgical sites; (2) nitrogen donor to muscle glutamine pool, the dominant amino acid exported from muscle to gut and immune cells during healing; (3) branched-chain amino acid-mediated suppression of muscle proteolysis through mechanistic target of rapamycin (mTOR) signaling. Branched-chain amino acid (BCAA)-enriched parenteral and oral nutrition has been tested in cirrhosis, trauma, and surgical recovery; older trials reported less negative nitrogen balance with enriched feeding, but the best-known cirrhosis trial (Marchesini 2003) did not measure nitrogen balance, and the 2026 Cochrane review rated the evidence on nitrogen balance as very uncertain. This page covers the biochemistry, the clinical evidence, and the practical applications.
Table of Contents
- Nitrogen Balance: The Basic Concept
- Negative Nitrogen Balance in Catabolic States
- Valine as Direct Substrate for Tissue Synthesis
- Valine Contribution to Muscle Glutamine
- Branched-Chain Amino Acid-Enriched Parenteral Nutrition for Cirrhosis
- The Marchesini Long-Term Oral Branched-Chain Amino Acid Protocol
- Trauma and Burn Applications
- Perioperative Nutrition and Surgical Recovery
- Mechanisms of Branched-Chain Amino Acid Contribution to Wound Healing
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
Nitrogen Balance: The Basic Concept
Nitrogen balance is the simplest quantitative way to assess net protein utilization in the body. Because nitrogen is present at approximately 16% of the mass of all amino acids and is essentially absent from carbohydrates and fats, measuring nitrogen intake and excretion gives a usable measure of net protein anabolism (positive balance, more protein synthesized than degraded) or net protein catabolism (negative balance, more degraded than synthesized).
Nitrogen balance is calculated as:
Nitrogen balance = (dietary protein g/day ÷ 6.25) − (urinary urea nitrogen + fecal N + integumentary N losses)
The factor 6.25 converts dietary protein grams to dietary nitrogen grams (assuming 16% N content). Urinary urea nitrogen (UUN) is the dominant excretory route and the most-measured component, captured by 24-hour urine collection. Fecal nitrogen losses average about 1-2 g/day in healthy adults; integumentary losses (skin, hair, nails) approximately 0.5 g/day. A standard adjustment of 4 g/day total non-urinary loss is often used.
Positive nitrogen balance occurs during growth (children, adolescents), pregnancy, lactation, recovery from illness or injury, and during anabolic training with adequate protein. Negative balance occurs during fasting, severe illness, immobilization, aging (slowly), and frank protein malnutrition. The biological imperative for any patient in catabolic illness is to reverse negative nitrogen balance as quickly as possible, because sustained loss of structural and functional protein from muscle, immune system, and visceral organs compounds morbidity and mortality.
For most healthy adults, nitrogen balance approximates zero at a protein intake of about 0.8 g/kg/day, which is the basis of the Recommended Dietary Allowance (RDA). However, this is the intake required to prevent loss in healthy young adults at rest. For older adults, athletes, and patients in any catabolic state, the requirement is substantially higher (1.0-2.0 g/kg/day depending on context). Insufficient intake leads to sustained negative balance and progressive lean tissue loss.
Negative Nitrogen Balance in Catabolic States
Several clinical states produce sustained negative nitrogen balance even with feeding:
- Major trauma — multi-system trauma (motor vehicle accidents, falls from height, polytrauma) drives nitrogen loss of 15-30 g/day for 7-14 days post-injury. Total protein loss across this acute phase can reach 200-400 grams — equivalent to several pounds of muscle.
- Severe burns — extensive burns (>40% body surface area) produce the most extreme catabolism documented in clinical medicine, with nitrogen losses of 30-50 g/day for weeks or months. Burn patients require 2-3 g/kg/day protein intake just to approach nitrogen balance, and often run negative even at maximal feeding.
- Sepsis with prolonged intensive care unit (ICU) stay — severe sepsis triggers a cytokine-mediated catabolic cascade involving interleukin-6 (IL-6), tumor necrosis factor-alpha, and cortisol, driving nitrogen loss of 15-25 g/day for the duration of acute illness. Long-term intensive care unit survivors often emerge with 20-30% loss of lean body mass (intensive care unit-acquired weakness).
- Cancer cachexia — advanced cancer of certain types (pancreatic, lung, gastric, head/neck) produces a chronic catabolic state with progressive muscle and adipose loss, mediated by both tumor-derived factors (proteolysis-inducing factor) and host inflammatory cytokines. Cachexia accounts for an estimated 20-40% of cancer deaths.
- Cirrhosis — advanced liver disease produces a chronic low-grade catabolic state through altered amino acid metabolism, hyperammonemia, and frequent intercurrent illnesses. Sarcopenia is present in 40-70% of cirrhotic patients awaiting liver transplant and is a strong independent predictor of post-transplant outcomes.
- Major surgery — uncomplicated elective surgery produces transient negative nitrogen balance lasting 3-7 days post-op. Complicated or prolonged surgery extends this period considerably.
- Prolonged immobilization / bed rest — even without illness, simple bed rest produces measurable protein loss within days, accelerating in older adults.
The endocrine signature of these states is consistent: elevated cortisol, glucagon, and catecholamines, often with insulin resistance, driving net muscle proteolysis. The amino acids released — particularly the branched-chain amino acids (BCAAs), glutamine, and alanine — are exported from muscle to support gluconeogenesis, immune cell proliferation, wound healing, and hepatic acute-phase protein synthesis. The total protein lost from muscle far exceeds what is used productively at these other sites; the inefficiency is part of why catabolic illness produces such rapid and substantial wasting.
Valine as Direct Substrate for Tissue Synthesis
The reparative processes triggered by wounding, surgery, or trauma all require new protein synthesis at the affected tissue, plus accelerated protein synthesis at related organs (liver for acute-phase proteins, bone marrow for hematopoiesis, gut for mucosal repair, immune cells for inflammatory response). Each of these synthetic processes requires the full panel of essential amino acids, and valine's 5-6% representation in tissue protein means valine is required in roughly the same proportion.
The specific tissues most rapidly synthesizing during healing include:
- Skin and connective tissue at wound sites — keratinocytes, fibroblasts, and vascular endothelium proliferating to close wounds. Collagen synthesis is the dominant volumetric protein contribution; collagen contains a modest valine fraction (~2-4% depending on type), so collagen-rich tissue synthesis is less valine-demanding than muscle synthesis.
- Skeletal muscle at sites of damage (sarcomeric remodeling after exercise; muscle regeneration after laceration, contusion, or surgical incision) — valine fraction approximately 5-6% as noted above.
- Hepatic acute-phase proteins — C-reactive protein, fibrinogen, haptoglobin, complement proteins, alpha-1 antitrypsin, ceruloplasmin. These rise dramatically in acute inflammation and require substrate amino acids from the dietary or muscle pool.
- Immune cell expansion — activated B and T lymphocytes, neutrophils, macrophages, all undergoing rapid proliferation with concomitant protein synthesis demands.
- Erythropoiesis — in patients with significant blood loss or anemia of chronic disease, bone marrow erythropoiesis requires not only iron but adequate amino acid substrate for globin synthesis. Hemoglobin has a notable valine content (the alpha chain has approximately 5-6% valine residues, the beta chain similar).
The famous glutamate-6-to-valine mutation in beta-globin produces sickle cell disease — a glutamate-to-valine substitution at position 6 of the beta chain alters the protein's polymerization properties and produces the characteristic deoxy-hemoglobin polymer and red cell sickling. This is one of the most-cited examples in introductory biochemistry of how a single amino acid substitution can produce dramatic phenotypic consequences, and the substituted amino acid is valine specifically because of its hydrophobic, branched side chain that fits a complementary pocket on adjacent beta chains and drives polymerization.
The bottom line: any condition that increases the rate of tissue synthesis — healing, recovery, growth, athletic training — increases the absolute demand for valine alongside other amino acids. The 2:1:1 branched-chain amino acid pattern in muscle composition means valine demand parallels leucine and isoleucine demand in synthesis-favoring states.
Valine Contribution to Muscle Glutamine
Glutamine is the most abundant free amino acid in the body and the dominant amino acid exported from skeletal muscle during catabolic illness. Plasma glutamine concentrations are approximately 600-700 µmol/L — far higher than any other amino acid. Glutamine plays multiple critical roles in catabolic states:
- Fuel for rapidly dividing cells — enterocytes (gut lining cells), lymphocytes, macrophages, and tumor cells preferentially consume glutamine as fuel, oxidizing it through glutaminolysis to alpha-ketoglutarate and then the tricarboxylic acid (TCA) cycle, the cell's main energy-producing cycle
- Nitrogen carrier — glutamine transports nitrogen from peripheral tissues to liver and kidney for disposal as urea or ammonia
- Acid-base regulation — renal ammonia generation from glutamine is the major adaptive response to metabolic acidosis
- Nucleotide synthesis substrate — glutamine's amide nitrogen feeds purine and pyrimidine synthesis in proliferating cells
- Glutathione precursor — via glutamate, glutamine indirectly supplies the rate-limiting amino acid for glutathione synthesis
- Gut mucosal integrity — enterocyte glutamine consumption supports the structural integrity of the intestinal lining and is a primary reason for enteral nutrition's superiority over parenteral (intravenous) nutrition in critical illness
Glutamine is conventionally classified as a "conditionally essential" amino acid — the body can synthesize it from glutamate and ammonia in healthy states, but synthesis becomes inadequate during catabolic stress, and plasma glutamine often falls into low-normal or frankly deficient ranges in severe illness. Glutamine supplementation has been tested in numerous intensive care unit and trauma trials with mixed results — some early benefits suggested but later large-scale trials (REDOXS, MetaPlus) showed potential harm in some severely ill populations, leading to current guidelines that recommend against parenteral glutamine in shock/multi-organ failure but permit it selectively in trauma and burn patients.
The valine connection is that branched-chain amino acid transamination in skeletal muscle is a major nitrogen source for muscle glutamine synthesis. The BCAT2 enzyme transfers the amino group from valine (and leucine and isoleucine) to alpha-ketoglutarate, forming glutamate. Glutamate is then amidated by glutamine synthetase (using a second nitrogen from ammonia) to form glutamine. The net effect: valine catabolism provides one of the two nitrogens in every glutamine molecule synthesized by muscle.
This biochemistry means that adequate branched-chain amino acid intake during catabolic illness supports glutamine synthesis at the periphery. Branched-chain amino acid-enriched feeding has been proposed and tested as an indirect way to support glutamine without the safety concerns of pure glutamine infusion. The data are suggestive but not definitive; current clinical practice incorporates this rationale in choosing branched-chain amino acid-enriched enteral formulas for selected high-catabolic patients.
Branched-Chain Amino Acid-Enriched Parenteral Nutrition for Cirrhosis
The first clinical condition where branched-chain amino acid-enriched nutrition was systematically studied was hepatic encephalopathy in cirrhosis. Building on the Fischer-Baldessarini observation of altered amino acid profiles in liver failure, Fischer and colleagues at Harvard developed branched-chain amino acid-enriched parenteral formulas (initially a branched-chain-enriched intravenous amino acid solution, later commercial variants) and tested them in randomized trials starting in the 1970s.
The rationale combined two mechanisms: (1) restoring the ratio of branched-chain amino acids to aromatic amino acids (AAA: phenylalanine, tyrosine and tryptophan) — the Fischer ratio — to normalize neurotransmitter precursor balance and reduce encephalopathic symptoms; (2) providing readily-utilizable nitrogen substrate that bypasses the failing liver, since branched-chain amino acids are primarily metabolized in peripheral muscle rather than liver.
The intravenous branched-chain amino acid-enriched formulations typically contain 35-45% branched-chain amino acids by amino acid content (compared to about 18-20% in standard amino acid solutions), reflecting the 2:1:1 ratio at higher absolute concentrations. In Fischer's own 1976 study, 11 patients (8 with cirrhosis and a sudden worsening, 3 with fulminant hepatitis) received an infusion designed to normalize the plasma amino acid pattern; encephalopathy improved in all 8 with cirrhosis and in 1 of the 3 with fulminant hepatitis, and it improved as the ratio rose from about 1.0 back toward the normal 3.0–3.5. Across trials in acute hepatic encephalopathy, reported findings included:
- Faster resolution of encephalopathy (mental status normalization) in branched-chain amino acid-enriched arm vs standard amino acid arm
- Improved nitrogen balance (less negative or more positive) in branched-chain amino acid-enriched feeding
- Reduced plasma aromatic amino acid concentrations and partial normalization of the Fischer ratio
- No clear mortality benefit in early trials (mortality in advanced cirrhosis is driven by liver failure itself more than by encephalopathy)
European guidelines (the European Society for Clinical Nutrition and Metabolism, ESPEN) recommend branched-chain amino acid-enriched parenteral nutrition as an option in cirrhotic patients with encephalopathy who require intravenous (IV) nutrition support. North American guidelines (the American Society for Parenteral and Enteral Nutrition, ASPEN) take a more permissive but less recommendational stance, considering it appropriate for selected patients but not standard of care.
The Marchesini Long-Term Oral Branched-Chain Amino Acid Protocol
The most influential outpatient application of branched-chain amino acid nutrition for cirrhosis came from Giulio Marchesini and colleagues in Bologna, who designed and tested a long-term oral branched-chain amino acid supplementation regimen for people with advanced cirrhosis. The Marchesini 2003 Gastroenterology trial, a double-blind multicentre study, enrolled 174 patients with advanced cirrhosis and randomized them for one year to:
- Branched-chain amino acid supplement (leucine, isoleucine and valine)
- Lactoalbumin (an isonitrogenous control providing equivalent total amino acid nitrogen)
- Maltodextrin (a calorie-matched non-protein control)
The primary outcomes were a combined end point (death, or worsening to the point of meeting the trial's exclusion criteria), the need for hospital admission, and the length of hospital stay. Key findings from the published abstract:
- Branched-chain amino acid supplementation significantly reduced the combined event rate compared with lactoalbumin (odds ratio 0.43, 95% confidence interval 0.19–0.96; P = 0.039)
- Against maltodextrin the reduction was smaller and not statistically significant (odds ratio 0.51, 95% confidence interval 0.23–1.17; P = 0.108)
- The average hospital admission rate was lower in the branched-chain amino acid arm than with either control (P = 0.006 and P = 0.003)
- In patients who stayed in the study, nutritional measures and liver function tests were on average stable or improved, the Child-Pugh liver score fell (P = 0.013), and loss of appetite (anorexia) and quality of life on the SF-36 questionnaire improved
- Recurrence of overt hepatic encephalopathy was reduced in the branched-chain amino acid group
- Long-term compliance with the supplement was poor, and the authors wrote that new formulas were needed; branched-chain amino acid supplements are widely described as bitter-tasting
- The trial did not report nitrogen balance, so it does not by itself show faster nitrogen-balance recovery
Later trials, oral and intravenous, were pooled in Cochrane reviews:
- 2017 Cochrane review (Gluud and colleagues) — 16 randomized trials, 827 people with hepatic encephalopathy. Branched-chain amino acids had a beneficial effect on hepatic encephalopathy (risk ratio 0.73, 95% confidence interval 0.61–0.88) and no effect on death (risk ratio 0.88, 0.69–1.11), quality of life or nutritional measures. In March 2020 Cochrane added a note that the review had been found, after publication, not to comply with its conflict-of-interest policy, and that the update would have a lead author and a majority of authors free of conflicts.
- 2026 Cochrane update (Aamann and colleagues) — 18 trials, 934 people. Branched-chain amino acids reduced hepatic encephalopathy (risk ratio 0.79, 95% confidence interval 0.64–0.96; low-certainty evidence) but may have little or no effect on death (risk ratio 0.89, 0.71–1.12; very low certainty). Nausea and diarrhoea occurred in 12% of people taking branched-chain amino acids and 3% of those on control diets, and the effect on nitrogen balance was very uncertain (3 studies, 108 people). Trials in children are lacking.
The mechanism connects directly to the nitrogen balance and substrate-availability themes of this page: branched-chain amino acid supplementation provides muscle-utilizable nitrogen substrate that bypasses the failing liver, supports lean tissue preservation in chronically catabolic patients, and improves the ratio of branched-chain to aromatic amino acids, which is proposed to benefit the brain.
A Marchesini-style regimen as it is described in clinical practice for outpatients with cirrhosis:
- 0.25 g/kg/day branched-chain amino acid in 2:1:1 ratio (typically 12-20 g/day total)
- Divided three times daily, taken with meals
- Continued long term as part of medical nutrition therapy (in the 2003 trial, long-term compliance was poor)
- Total daily protein target maintained at 1.0-1.2 g/kg/day (the historical "protein restriction" for hepatic encephalopathy is now considered counterproductive in most patients)
- Late-evening snack with carbohydrate plus a branched-chain amino acid dose, to shorten the overnight fast. A 2012 review (Tsien and colleagues) found that a late evening snack decreased fat burning (lipid oxidation) and improved nitrogen balance whatever its composition, that daytime snacks of the same size did not do the same, that gains in lean or muscle mass were inconsistent, and that no reduction in deaths or need for transplant had been reported
Trauma and Burn Applications
The trauma/burn literature for branched-chain amino acid-enriched nutrition is older and the conclusions more mixed than the cirrhosis literature. Multiple trials in the 1980s and 1990s tested branched-chain amino acid-enriched parenteral nutrition vs standard amino acid parenteral nutrition (PN) in trauma and burn patients, with most showing modest improvements in nitrogen balance but inconsistent effects on harder clinical endpoints (infection rate, ventilator days, intensive care unit length of stay, mortality).
Contemporary critical care nutrition guidelines from ASPEN and the Society of Critical Care Medicine (SCCM) do not strongly recommend branched-chain amino acid-enriched formulas as standard for trauma or burn patients. Instead, the guidelines emphasize:
- Adequate total protein delivery (1.2-2.0 g/kg/day for trauma; up to 2.5-3.0 g/kg/day for severe burns)
- Preference for enteral over parenteral route when feasible
- Early initiation of nutrition (within 24-48 hours)
- Adequate energy delivery (25-30 kcal/kg/day for trauma; higher for burns)
The supplemental contribution of branched-chain amino acid-enrichment to these total-protein goals is now seen as marginal — adequate total protein from any high-biological-value source provides ample branched-chain amino acids in the 2:1:1 ratio naturally, without the need for branched-chain amino acid-enriched formulations. The exception remains hepatic encephalopathy and certain hyperammonemic states, where branched-chain amino acid-enrichment has more specific physiological rationale.
For burn patients specifically, attention moved to glutamine repletion and ample whole-protein delivery. The largest burn nutrition trial, RE-ENERGIZE (2022), randomized 1,209 patients with severe burns (on average 33% of body surface) to enteral glutamine 0.5 g/kg/day or placebo; glutamine did not shorten the time to discharge alive from hospital (median 40 vs 38 days), 6-month deaths were 17.2% vs 16.2%, and serious adverse events did not differ substantially. Branched-chain amino acid-enriched formulas have largely been deprecated in modern burn nutrition.
Perioperative Nutrition and Surgical Recovery
Enhanced Recovery After Surgery (ERAS) protocols have transformed perioperative nutrition over the past two decades. Traditional preoperative fasting from midnight has been replaced by carbohydrate-rich clear fluids up to 2 hours before surgery, and early postoperative oral feeding (within hours) has been adopted in most major procedures. Within this framework, nutritional optimization has shifted to:
- Preoperative protein loading — sarcopenic or undernourished patients identified at the preop assessment benefit from 2-4 weeks of supplemental protein (1.5-2.0 g/kg/day) before elective surgery to optimize lean mass and postoperative recovery
- Immune-enhanced enteral formulas — formulas combining glutamine, arginine, omega-3 fatty acids, and nucleotides have shown benefit in reducing postoperative infections in selected populations (head/neck and gastrointestinal (GI) cancer surgery), though the effect size is modest and not all subgroups benefit
- Early postoperative protein resumption — advancing to full protein intake within 24-48 hours postop, supported by oral or enteral feeding, accelerates return of nitrogen balance
- Branched-chain amino acid supplementation in specific contexts — cirrhotic patients undergoing hepatectomy or liver transplant evaluation; sarcopenic elderly patients undergoing major surgery; some bariatric surgery populations
The specific role of branched-chain amino acid supplementation in surgical recovery has been studied in hepatic surgery extensively. Studies of branched-chain amino acid-enriched oral nutrition for 1-2 weeks postoperatively in patients undergoing hepatectomy for hepatocellular carcinoma have shown improvements in albumin recovery, ascites resolution, and quality-of-life scores. Japanese liver surgery centers have integrated branched-chain amino acid supplementation into standard postoperative care for these patients; Western centers vary in adoption.
For most elective surgery in well-nourished patients, the contribution of branched-chain amino acid-enrichment beyond adequate total protein is small. Where branched-chain amino acid-enrichment matters most is in patients who enter surgery in a sarcopenic, sub-optimally nourished, or otherwise catabolically primed state, and where the postoperative course is expected to be prolonged or complicated.
Mechanisms of Branched-Chain Amino Acid Contribution to Wound Healing
At the wound site, several specific branched-chain amino acid-related mechanisms have been characterized:
- Direct substrate for collagen, elastin, fibrin, and cellular protein synthesis at the wound. Although collagen itself is relatively valine-poor (collagen is rich in glycine, proline, and hydroxyproline), the surrounding cellular machinery synthesizing collagen requires standard amino acid substrate composition.
- Mechanistic target of rapamycin-mediated promotion of fibroblast proliferation at the wound site. Local leucine concentrations at wound exudate are typically elevated due to the rapid proteolysis of damaged tissue, supporting an anabolic local environment.
- Immune cell support — wound macrophages and neutrophils consume substantial amino acid substrate during the acute inflammatory phase. Adequate branched-chain amino acid availability supports this immune response.
- Reduced peripheral proteolysis — oral branched-chain amino acid intake reduces the muscle proteolysis that would otherwise mobilize amino acids for the wound. This is "spared" muscle protein.
- Glutamine support — via the transamination pathway discussed above, branched-chain amino acids contribute nitrogen to glutamine synthesis, and glutamine is preferentially consumed by enterocytes (maintaining gut barrier function during illness) and immune cells (supporting host defense).
- Insulin sensitization in some contexts — branched-chain amino acid + arginine combination has been shown to improve glucose tolerance in some surgical contexts, indirectly supporting wound healing (hyperglycemia impairs wound healing).
- Beta-hydroxy-beta-methylbutyrate (HMB) — the leucine metabolite has been studied specifically for wound healing in chronic pressure ulcers and surgical wounds, with some evidence of benefit. HMB is produced endogenously from approximately 5% of dietary leucine, so adequate leucine intake (and balanced branched-chain amino acid intake) supports HMB availability.
Wound nutrition approaches described in clinical practice, integrating these mechanisms:
- Adequate total protein at 1.2-1.5 g/kg/day for adults with significant wounds, higher (1.5-2.0 g/kg/day) for chronic non-healing wounds or pressure ulcers
- Adequate caloric intake — protein cannot be efficiently used for tissue synthesis if total energy intake is insufficient
- Vitamin C, zinc, and adequate iron status for collagen synthesis and cellular proliferation
- Arginine supplementation in some contexts (oral wound nutrition formulas) for nitric oxide-mediated vasodilation and immune support
- For chronic pressure ulcers, oral HMB-arginine-glutamine combinations (for example, an HMB-arginine-glutamine drink) have randomized controlled trial (RCT) evidence for accelerated healing
Cautions and Contraindications
- Maple syrup urine disease and related branched-chain amino acid metabolism disorders — absolute contraindication. Branched-chain amino acid supplements cannot be given to patients with maple syrup urine disease (MSUD), propionic acidemia, methylmalonic acidemia, or isovaleric acidemia outside of carefully managed metabolic disease centers with specialized formulations.
- Acute hepatic failure with severe hyperammonemia — standard clinical practice limits high-protein loading, including branched-chain amino acid loading, in acute hepatic failure with grade 3-4 encephalopathy. Branched-chain amino acid-enriched parenteral nutrition may be appropriate in this context if total protein delivery is being maintained, but the situation requires hepatology and nutrition team management.
- Chronic kidney disease (advanced stages) — high amino acid intake increases nitrogen load on impaired kidneys. In stage 3 and later chronic kidney disease (CKD), added amino acids increase the nitrogen (urea) load the weakened kidneys must clear; very-low-protein diets with keto-analog supplementation (a specialized approach) include branched-chain amino acid keto-analogs specifically to avoid the Harper imbalance problem.
- Insulin resistance and type 2 diabetes — while moderate dietary branched-chain amino acid from food sources is not harmful, the research raises a concern about chronic high-dose branched-chain amino acid supplementation in obese insulin-resistant people. The Wang/Newgard biomarker work showed elevated plasma branched-chain amino acids associated with insulin resistance; whether this is causal or consequential is debated, but pushing branched-chain amino acids higher in this population may not be optimal.
- Pregnancy and lactation — dietary branched-chain amino acid intake is appropriate and required, but high-dose branched-chain amino acid supplements have not been studied in pregnancy or breastfeeding, where food sources supply the requirement.
- Pediatric use — branched-chain amino acid supplementation in children has been studied only in the clinical management of specific disorders. Children's amino acid requirements are met by normal dietary protein.
Key Research Papers
- Marchesini G et al. (2003). Nutritional supplementation with branched-chain amino acids in advanced cirrhosis: a double-blind, randomized trial. Gastroenterology;124(7):1792-1801. — PubMed PMID: 12806613
- Gluud LL, Dam G, Les I, et al. (2017). Branched-chain amino acids for people with hepatic encephalopathy. Cochrane Database of Systematic Reviews;5(5):CD001939. — PubMed PMID: 28518283
- Aamann L, Deshpande N, Dam G, et al. (2026). Branched-chain amino acids for people with cirrhosis and hepatic encephalopathy. Cochrane Database of Systematic Reviews;1(1):CD001939. — PubMed PMID: 41542879
- Fischer JE et al. (1976). The effect of normalization of plasma amino acids on hepatic encephalopathy in man. Surgery;80(1):77-91. — PubMed PMID: 818729
- Plauth M et al. (2019). ESPEN guideline on clinical nutrition in liver disease. Clinical Nutrition. — PubMed PMID: 30712783
- Williams JZ, Barbul A (2003). Nutrition and wound healing. Surgical Clinics of North America. — PubMed PMID: 12822727
- Wischmeyer PE, Dhaliwal R, McCall M, et al. (2014). Parenteral glutamine supplementation in critical illness: a systematic review. Critical Care;18(2):R76. — PubMed PMID: 24745648
- Heyland D et al. (2013). A randomized trial of glutamine and antioxidants in critically ill patients (REDOXS). New England Journal of Medicine;368(16):1489-1497. — PubMed PMID: 23594003
- Stehle P et al. (2017). Glutamine dipeptide-supplemented parenteral nutrition improves the clinical outcomes of critically ill patients: a systematic evaluation of randomised controlled trials. Clinical Nutrition ESPEN;17:75-85. — PubMed PMID: 28361751
- Posthauer ME et al. (2015). The role of nutrition for pressure ulcer management. Advances in Skin & Wound Care. — PubMed PMID: 25775201
- Singer P et al. (2019). ESPEN guideline on clinical nutrition in the intensive care unit. Clinical Nutrition;38(1):48-79. — PubMed PMID: 30348463
- Tsien CD, McCullough AJ, Dasarathy S (2012). Late evening snack: exploiting a period of anabolic opportunity in cirrhosis. Journal of Gastroenterology and Hepatology;27(3):430-441. — PubMed PMID: 22004479
- Heyland DK, Wibbenmeyer L, Pollack J, et al. (2022). A randomized trial of enteral glutamine for treatment of burn injuries. New England Journal of Medicine;387(11):1001-1010. — PubMed PMID: 36082909
PubMed Topic Searches
Connections
- All Amino Acids
- Valine Overview
- Valine Benefits Hub
- Valine for Muscle Protein Synthesis
- Valine for Energy Metabolism
- Valine for Cognitive Performance
- Leucine (Branched-Chain Amino Acid Partner)
- Isoleucine (Branched-Chain Amino Acid Partner)
- Glutamine
- Arginine
- Alanine
- Liver Disease
- Vitamin C (Collagen Synthesis)
- Zinc (Wound Healing)
- History
- Sources