⚠ Evidence warning: Clinical trials or other evidence do not support the claim that branched-chain amino acids taken during exercise lower perceived exertion by about 5-8%. This page keeps it as a report of what people, websites or other media say.
Valine for Energy Metabolism
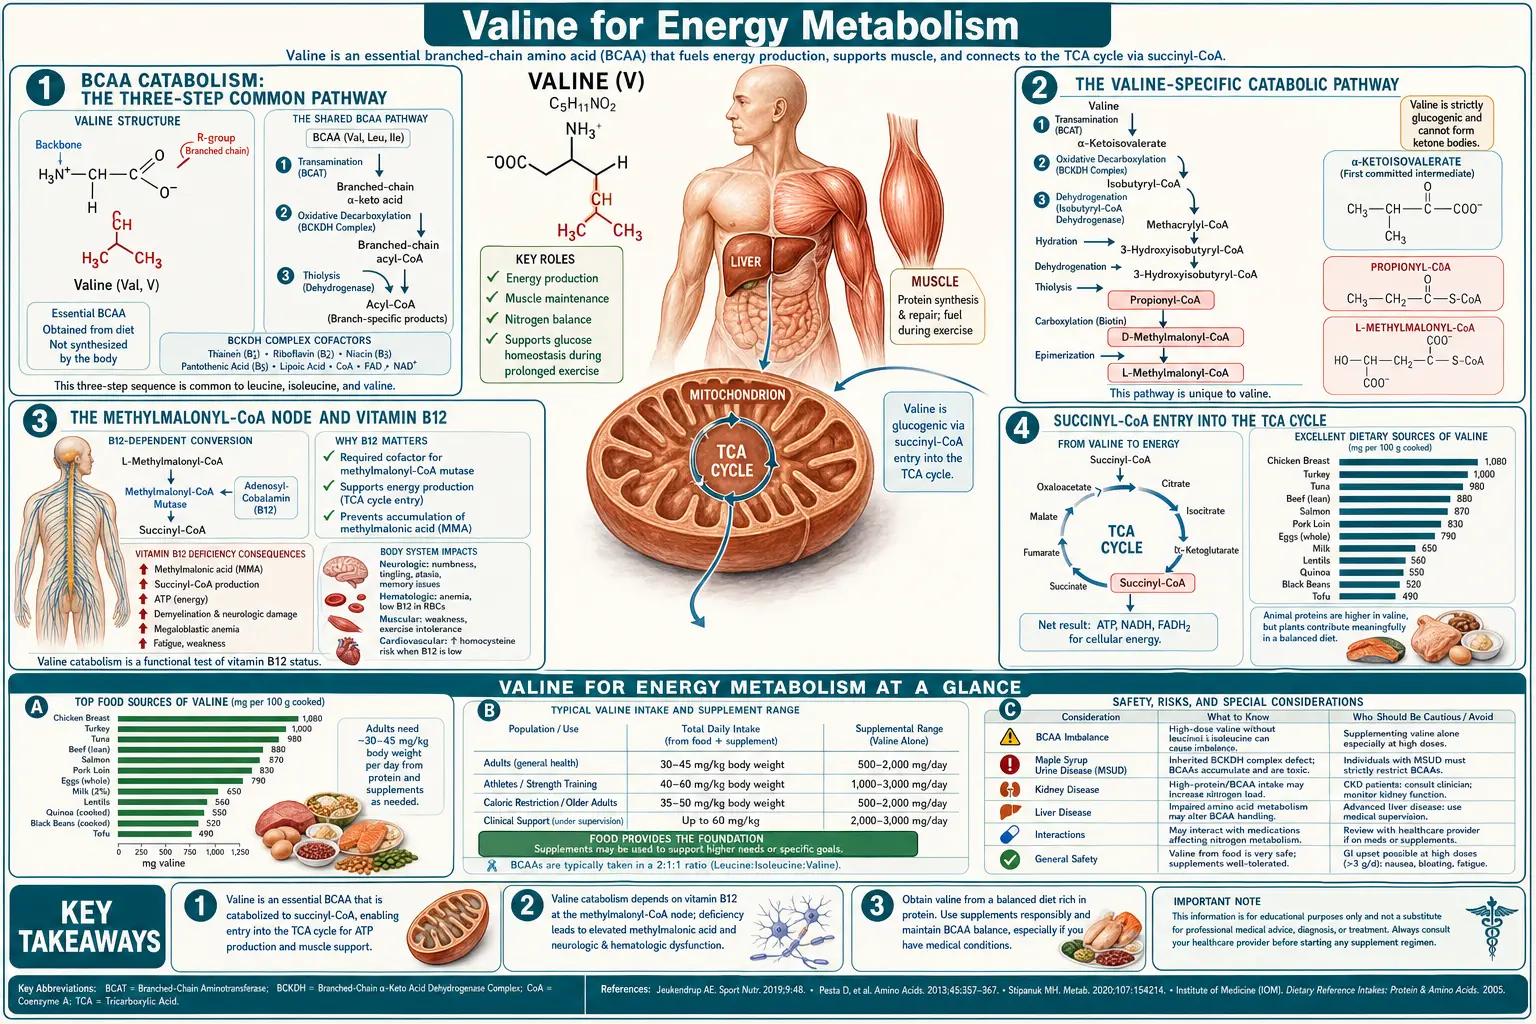
Valine is one of only a handful of amino acids that can feed carbon directly into the TCA (citric acid) cycle as an anaplerotic substrate — replenishing intermediates rather than just being burned for adenosine triphosphate (ATP). Its catabolic pathway runs through propionyl-coenzyme A (propionyl-CoA), methylmalonyl-CoA (the vitamin B12-dependent step), and succinyl-CoA, joining the TCA cycle at the succinate level. An earlier step of the same pathway is the one disrupted in maple syrup urine disease (MSUD) — the classic genetic disorder of branched-chain alpha-ketoacid dehydrogenase (BCKAD) deficiency that elevates plasma branched-chain amino acids (BCAAs) and their toxic ketoacids, producing the maple-syrup-scented urine and neurological crisis that gave the disease its name. A thiamine-responsive MSUD subtype reveals the critical role of vitamin B1 as the BCKAD cofactor. During fasting, valine liberated from muscle proteolysis becomes a gluconeogenic substrate, contributing alongside alanine and glutamine to maintain blood glucose for brain and red blood cells. This page maps that pathway end-to-end and explains its clinical implications.
Table of Contents
- Branched-Chain Amino Acid Catabolism: The Two-Step Common Pathway
- The Valine-Specific Catabolic Pathway
- The Methylmalonyl-CoA Node and Vitamin B12
- Succinyl-CoA Entry into the TCA Cycle
- Valine as an Anaplerotic Substrate
- Maple Syrup Urine Disease (MSUD) and BCKAD Deficiency
- Thiamine-Responsive MSUD and Vitamin B1
- Gluconeogenesis from Muscle Proteolysis During Fasting
- Valine During Prolonged Exercise
- Regulation of BCKAD Activity
- Key Research Papers
- Connections
- Featured Videos
Branched-Chain Amino Acid Catabolism: The Two-Step Common Pathway
All three branched-chain amino acids — leucine, isoleucine, and valine — share the first two steps of their catabolic pathway. Step one is reversible transamination by branched-chain aminotransferase (BCAT), which strips the alpha-amino group and transfers it to alpha-ketoglutarate to form glutamate, leaving behind a branched-chain alpha-ketoacid. For valine, the product is alpha-ketoisovalerate (KIV); for leucine, alpha-ketoisocaproate (KIC); for isoleucine, alpha-keto-beta-methylvalerate (KMV). Two BCAT isoforms exist: BCAT1 in the cytoplasm of many tissues (brain, kidney, ovary) and BCAT2 in mitochondria of essentially all tissues including skeletal muscle, the dominant site of branched-chain amino acid (BCAA) transamination quantitatively.
Step two is the irreversible oxidative decarboxylation by the branched-chain alpha-ketoacid dehydrogenase complex (BCKAD or BCKDH), a mitochondrial multienzyme complex structurally and mechanistically analogous to pyruvate dehydrogenase and alpha-ketoglutarate dehydrogenase. BCKAD removes CO2 from the alpha-ketoacid and attaches the remaining carbon skeleton to coenzyme A as a branched-chain acyl-CoA. The complex requires five cofactors: thiamine pyrophosphate (TPP, from vitamin B1), lipoamide (from lipoic acid), coenzyme A (from pantothenic acid), flavin adenine dinucleotide (FAD, from riboflavin), and nicotinamide adenine dinucleotide (NAD+) (from niacin). Deficiency of any of these B-vitamin cofactors can impair BCKAD activity, although the most clinically dramatic deficiency state is the genetic loss of function that causes maple syrup urine disease.
BCKAD is the rate-limiting enzyme of the entire branched-chain amino acid catabolic pathway. It is heavily regulated by phosphorylation: BCKAD kinase phosphorylates and inactivates the complex; BCKAD phosphatase dephosphorylates and activates it. The kinase is itself inhibited by elevated levels of branched-chain alpha-ketoacids (substrate-level feedback). Net effect, as a 2005 review by Harris and colleagues puts it: the complex is phosphorylated, and so switched off, when there is a need to conserve branched-chain amino acids for protein synthesis, and dephosphorylated, and so switched on, when they are present in excess, at which point they flow into the TCA cycle as fuel.
From here, each branched-chain amino acid diverges into its own product-specific catabolic steps. Leucine yields acetyl-CoA and acetoacetate (purely ketogenic). Isoleucine yields both acetyl-CoA and propionyl-CoA (mixed ketogenic and glucogenic). Valine yields propionyl-CoA only (purely glucogenic). The downstream paths from propionyl-CoA are what make valine unique among the branched-chain amino acids and what tie it to vitamin B12 metabolism.
The Valine-Specific Catabolic Pathway
After BCKAD action on alpha-ketoisovalerate, valine's carbon skeleton continues through the following sequence:
- Isobutyryl-CoA (the immediate BCKAD product from valine)
- Dehydrogenation by isobutyryl-CoA dehydrogenase to methacrylyl-CoA, with electrons passed through reduced flavin adenine dinucleotide (FADH2) to the electron transport chain
- Hydration by enoyl-CoA hydratase to 3-hydroxyisobutyryl-CoA
- Hydrolysis by 3-hydroxyisobutyryl-CoA hydrolase to 3-hydroxyisobutyrate (free acid form, which can leave the mitochondrion and circulate)
- Oxidation by 3-hydroxyisobutyrate dehydrogenase to methylmalonate semialdehyde
- Oxidation and CoA-attachment by methylmalonate semialdehyde dehydrogenase to propionyl-CoA
- Propionyl-CoA (the convergent node shared with isoleucine catabolism, odd-chain fatty acid oxidation, and methionine/threonine catabolism)
- Carboxylation by propionyl-CoA carboxylase (biotin-dependent) to D-methylmalonyl-CoA
- Isomerization by methylmalonyl-CoA racemase to L-methylmalonyl-CoA
- L-methylmalonyl-CoA isomerization by methylmalonyl-CoA mutase (vitamin B12-dependent) to succinyl-CoA
- Succinyl-CoA entry into the TCA cycle
The pathway has ten enzymatic steps from valine to succinyl-CoA, the largest number of any branched-chain amino acid. Genetic defects in any of these enzymes produce specific organic acidemias, the most clinically important being the propionyl-CoA carboxylase defect (propionic acidemia) and the methylmalonyl-CoA mutase defect (methylmalonic acidemia). These are inborn errors of metabolism diagnosed by elevated organic acids in urine and treated by dietary restriction of the precursor amino acids (valine, isoleucine, methionine, and threonine, all of which converge on propionyl-CoA; only the first two are branched-chain). The 2021 revised guideline for these two diseases updates the evidence on precursor-free amino acid mixtures and on transplant outcomes.
One of the steps above has drawn attention in diabetes research. The 3-hydroxyisobutyrate made along this route is released by muscle cells, and in mice it pushed fatty acids across blood vessel walls into muscle, where lipid built up and insulin resistance followed. Levels were higher in muscle from people with diabetes than from people without it. The mouse results do not show the same chain of events in people.
The Methylmalonyl-CoA Node and Vitamin B12
The conversion of L-methylmalonyl-CoA to succinyl-CoA by methylmalonyl-CoA mutase is one of only two reactions in human biochemistry that require vitamin B12 (cobalamin) as cofactor — the other being the homocysteine-to-methionine conversion by methionine synthase. The B12 form required by methylmalonyl-CoA mutase is 5'-deoxyadenosylcobalamin (AdoCbl), an organometallic compound with a covalent cobalt-carbon bond. That bond is not unique to this form: it is also cleaved during catalysis by the methylcobalamin-dependent enzymes.
Functional B12 deficiency — whether from inadequate intake (strict veganism without supplementation), malabsorption (atrophic gastritis, pernicious anemia, ileal disease, metformin use), or genetic disorders of B12 transport and processing — causes a buildup of methylmalonyl-CoA, which hydrolyzes spontaneously to methylmalonic acid (MMA) and accumulates in plasma and urine. Serum or urinary methylmalonic acid is therefore the single most sensitive biochemical marker of functional B12 deficiency, more sensitive than serum B12 itself (which can be in the normal range despite tissue-level deficiency). Methylmalonic acid testing is the standard follow-up for any patient with borderline B12 and suspected neurological or hematological B12 deficiency.
The methylmalonyl-CoA buildup has consequences beyond just its diagnostic utility. Methylmalonyl-CoA is a structural analog of malonyl-CoA, the regulatory and synthetic precursor for fatty acid synthesis. Elevated methylmalonyl-CoA inhibits malonyl-CoA-dependent processes and is thought to contribute to the abnormal lipid composition (odd-chain and branched-chain fatty acids) seen in untreated B12 deficiency and in inborn errors of methylmalonic acidemia. This abnormal lipid synthesis affects myelin composition and is one proposed mechanism for the subacute combined degeneration of the dorsal columns and corticospinal tracts that characterizes severe B12 deficiency neurologically.
The valine connection means that a patient with genetic methylmalonic acidemia has a valine-restricted dietary recommendation as part of management. In genetic methylmalonic acidemia, the valine restriction is strict and lifelong; in B12 deficiency, methylmalonic acid normalizes with B12 repletion and no dietary restriction is needed.
Succinyl-CoA Entry into the TCA Cycle
Succinyl-CoA is one of eight TCA cycle intermediates and one of the most metabolically versatile. Once formed from valine catabolism, succinyl-CoA can be processed through several alternative routes:
- TCA cycle progression: succinyl-CoA synthetase converts succinyl-CoA to succinate, generating one guanosine triphosphate (GTP) by substrate-level phosphorylation. Succinate then proceeds through fumarate, malate, oxaloacetate, and back to citrate — one full turn of the cycle producing 1 GTP, 3 reduced nicotinamide adenine dinucleotide (NADH), and 1 FADH2 (yielding approximately 9-10 adenosine triphosphate per turn through oxidative phosphorylation).
- Heme synthesis: succinyl-CoA condenses with glycine in the mitochondrion (catalyzed by ALA synthase, the rate-limiting and B6-dependent enzyme of heme synthesis) to form delta-aminolevulinate (ALA), the first committed precursor of heme. It has long been assumed that the succinyl-CoA for heme comes from the TCA cycle, which valine feeds, but no measured figure for valine's share was found for this page. In developing red blood cells, a 2018 study found that during the late stages glutamine is the precursor, reaching succinyl-CoA through alpha-ketoglutarate dehydrogenase without passing through the TCA cycle.
- Gluconeogenesis: in the liver, succinate from the TCA cycle can be drawn off as malate, exported from the mitochondrion, converted to oxaloacetate in the cytoplasm, and channeled into gluconeogenesis via phosphoenolpyruvate carboxykinase (PEPCK). This is the route by which valine ultimately contributes to blood glucose during fasting.
- Anaplerotic replenishment: when TCA intermediates are pulled out for biosynthesis (heme, glutamate, aspartate, gluconeogenesis), they must be replenished or the cycle stalls. Succinyl-CoA from valine catabolism is one of several key anaplerotic inputs that keep the cycle topped up.
The succinyl-CoA entry point also explains why valine is mildly insulinogenic. Succinyl-CoA and its downstream TCA intermediates produce adenosine triphosphate, which closes adenosine triphosphate-sensitive potassium channels in pancreatic beta-cells and triggers insulin secretion. This is a small effect compared to glucose or to direct amino-acid-stimulated insulin release (which is most pronounced for leucine), but it contributes to the integrated metabolic response to a protein-containing meal.
Valine as an Anaplerotic Substrate
Anaplerosis — the replenishment of TCA cycle intermediates — is a biochemical concept that often gets short shrift in introductory metabolism teaching, but it is crucial for understanding why some amino acids are particularly valuable in catabolic and high-flux states. The TCA cycle is not a closed loop in the steady state; intermediates are continuously drawn off for biosynthesis (aspartate from oxaloacetate, glutamate from alpha-ketoglutarate, heme from succinyl-CoA), and if they are not replenished, cycle flux drops and aerobic adenosine triphosphate production collapses.
The principal anaplerotic enzyme is pyruvate carboxylase, which converts pyruvate to oxaloacetate (biotin-dependent), and the principal anaplerotic substrates are pyruvate (from glucose), glutamine (from circulating amino acid pool), and the propionyl-CoA-yielding amino acids: valine, isoleucine, methionine, and threonine. Of these, valine and isoleucine quantitatively dominate during fasting, exercise, and any state where dietary protein is being catabolized.
The clinical significance: in conditions where TCA flux is impaired by intermediate depletion — some forms of mitochondrial disease, severe sepsis with mitochondrial dysfunction, certain organic acidemias — valine and other anaplerotic substrates become limiting for energy production. Triheptanoin (a medium-odd-chain triglyceride that yields propionyl-CoA upon oxidation) has been developed as a therapy for long-chain fatty acid oxidation disorders specifically because it can refill the TCA cycle through the same propionyl-CoA-to-succinyl-CoA pathway that valine uses. The biochemistry of valine catabolism is therefore directly applicable to a small but important set of inherited metabolic disorders.
Triheptanoin received FDA approval on 30 June 2020 (application NDA 213687). The figures behind it come from three kinds of study. Roe and Brunengraber reported 52 patients over 15 years, with serious complications falling from about 60% on conventional diet to 10% and mortality from about 65% to 3.8%; this compares against conventional-diet experience, not a randomized control group. In a 32-person double-blind trial against an eight-carbon oil, lasting 4 months with 20% of daily energy from the oil, heart ejection fraction rose 7.4% and heart wall mass fell 20%, with no difference in energy expenditure, body composition or rhabdomyolysis. In a long open-label extension study, 33 patients new to the drug went from a median of 2.00 major clinical events a year to 0.28, a fall of 86%, with no control group; treatment-related side effects occurred in 68.1% of patients in that study, mostly mild or moderate.
Maple Syrup Urine Disease (MSUD) and BCKAD Deficiency
Maple syrup urine disease, first described in 1954 by Menkes, Hurst, and Craig, is the prototypical disorder of branched-chain amino acid catabolism. It is caused by autosomal recessive mutations in any of the four subunits of the BCKAD complex: E1alpha (BCKDHA gene), E1beta (BCKDHB gene), E2 (DBT gene), or E3 (DLD gene; this last subunit is shared with pyruvate dehydrogenase and alpha-ketoglutarate dehydrogenase, so DLD mutations produce a more severe combined phenotype).
With BCKAD nonfunctional, all three branched-chain amino acids and their alpha-ketoacids accumulate to dramatic levels in plasma, urine, and cerebrospinal fluid (CSF). The disease name comes from the distinctive sweet, maple-syrup-like odor of the urine, which a 1999 study of urine from seven patients traced to the compound sotolone, also present in maple syrup and fenugreek and absent from the urine of healthy controls. In the classic neonatal form, infants appear normal at birth but within days of beginning protein feeds develop progressive lethargy, feeding intolerance, alternating hyper- and hypotonia, opisthotonos, and ultimately seizures, coma, and cerebral edema if untreated. Mortality without treatment is essentially 100% in the first month of life.
The mechanism of neurotoxicity is multifactorial:
- Elevated plasma leucine competes with other large neutral amino acids (LNAAs) for transport across the blood-brain barrier via LAT1, depleting brain levels of phenylalanine, tyrosine, tryptophan, methionine, histidine, and threonine
- The neurotransmitter precursors tyrosine and tryptophan become brain-deficient, impairing catecholamine and serotonin synthesis
- Branched-chain alpha-ketoacids are directly neurotoxic, particularly alpha-ketoisocaproate, which inhibits brain alpha-ketoglutarate dehydrogenase and disrupts brain energy metabolism
- Severe accumulation causes cerebral edema, the leading cause of acute mortality in untreated metabolic crisis
Treatment is lifelong dietary restriction of branched-chain amino acids (especially leucine, which is the most neurotoxic), using specialized branched-chain amino acid-free amino acid formulas to provide other essential amino acids, careful protein management, and emergency hospitalization for any catabolic illness or trauma that mobilizes endogenous branched-chain amino acids. Some patients are candidates for liver transplantation, which provides functional BCKAD activity systemically and allows return to a normal diet.
In one series of 35 patients with classical MSUD who received a new liver between 2004 and 2009, patient and graft survival were 100% at about 4.5 years of follow-up. Branched-chain amino acid levels were corrected within hours of surgery, and leucine tolerance rose more than 10-fold. One-third of the patients were mentally impaired before transplant, with no significant change one year later; the authors write that transplant may arrest brain damage but will not reverse it. Six of the patients donated their own livers to recipients without MSUD (domino transplants), and those recipients were alive and well with normal branched-chain amino acid levels.
Thiamine-Responsive MSUD and Vitamin B1
A minority of MSUD patients — approximately 2-5% — have a milder form of the disease that responds dramatically to high-dose pharmacologic vitamin B1 (thiamine) supplementation. These patients carry mutations in the E1alpha or E2 subunits of BCKAD that destabilize the complex's binding of its thiamine pyrophosphate cofactor. Saturating the residual enzyme with high concentrations of TPP partially restores activity, lowering plasma branched-chain amino acid levels and reducing the dietary restriction requirements.
Thiamine-responsive MSUD is treated with 10-200 mg/day of oral thiamine (compared to the 1-2 mg/day Recommended Dietary Allowance (RDA) for healthy adults), typically alongside continued but less restrictive dietary branched-chain amino acid limitation. The dramatic response in these patients — plasma leucine levels can drop by 50-80% within days of starting high-dose thiamine — demonstrates the principle that cofactor availability can rescue residual enzyme function in enzymopathies with partial activity remaining.
The broader implication of thiamine-responsive MSUD extends to wild-type BCKAD activity in the general population. Thiamine deficiency — chronic alcoholism, post-bariatric surgery, prolonged severe malnutrition, hyperemesis gravidarum — impairs BCKAD function and can elevate plasma branched-chain amino acids and their ketoacids, though usually not to MSUD-like levels. This is one of several biochemical mechanisms by which thiamine deficiency produces neurological symptoms (Wernicke encephalopathy, beriberi). The thiamine Recommended Dietary Allowance is built on the assumption of adequate intake; tissues with high TCA flux (brain, heart, skeletal muscle in athletes) may have higher functional requirements.
Thiamine status is most reliably assessed by erythrocyte transketolase activity with and without TPP addition (the "TPP effect" — a percentage increase above 15% suggests deficiency), or by whole-blood thiamine pyrophosphate measurement. Serum thiamine is a poor marker because most thiamine circulates intracellularly. For at-risk populations (chronic alcoholism, post-bariatric, hyperemesis gravidarum), empiric thiamine supplementation at 100 mg/day oral or 100-500 mg intravenous (IV) for acute presentation is standard of care.
Gluconeogenesis from Muscle Proteolysis During Fasting
During an overnight fast, plasma glucose is maintained primarily by hepatic glycogenolysis (the breakdown of stored liver glycogen). As liver glycogen depletes — typically within 12-18 hours of fasting — gluconeogenesis takes over as the dominant glucose source. The substrates for gluconeogenesis are: lactate (from anaerobic glycolysis, especially in red blood cells and exercising muscle), glycerol (from triglyceride lipolysis), and glucogenic amino acids (from net muscle protein breakdown).
Among the amino acids, the principal gluconeogenic substrates released from muscle are alanine and glutamine, accounting for approximately 50-60% of the amino acid nitrogen exported from skeletal muscle during fasting. This is the basis of the glucose-alanine cycle: muscle proteolysis liberates branched-chain amino acids, which donate their amino groups (via BCAT transamination) to pyruvate, forming alanine; alanine is exported to the liver and reconverted to pyruvate (and then to glucose), with the amino group going into the urea cycle. The carbon skeleton of valine (and the other branched-chain amino acids) is largely retained in the muscle, where it enters the TCA cycle as succinyl-CoA and is oxidized for local adenosine triphosphate.
However, a measurable fraction of valine carbon does reach the liver and contribute to gluconeogenesis directly. The succinyl-CoA from valine can be exported as malate, converted in the liver cytoplasm to oxaloacetate and then to phosphoenolpyruvate, and finally to glucose. The quantitative contribution of valine carbon to glucose output during fasting is on the order of 5-10% of total gluconeogenesis — modest but not negligible.
This biochemistry explains why valine (and branched-chain amino acids more broadly) are not classically considered "sparing" of muscle during fasting in the same way that adequate carbohydrate intake is. The amino nitrogen is preserved through transamination to alanine, but the carbon skeleton of valine derived from muscle proteolysis is being oxidized as fuel and lost to the protein pool. Sustained fasting therefore depletes muscle protein even with adequate metabolic adaptation, and prolonged fasting (beyond ~3 weeks) ultimately compromises diaphragm and cardiac muscle function in a way that becomes life-threatening — the historical end point of hunger strikes and famine.
Valine During Prolonged Exercise
During sustained aerobic exercise, fuel selection shifts progressively. The first 30 minutes draw heavily on muscle glycogen and circulating glucose; as glycogen depletes (typically after 60-90 minutes of moderate-to-high-intensity exercise), free fatty acids become the dominant fuel; in very prolonged exercise (4+ hours), amino acid oxidation can account for 5-10% of total energy expenditure. Valine and isoleucine are the principal amino acids oxidized in this context, because of their direct entry into the TCA cycle (and because BCKAD activity in exercising muscle increases approximately 3-5 fold compared to rest).
The practical consequence for endurance athletes is twofold. First, prolonged exercise produces measurable muscle protein breakdown, with elevated urinary 3-methylhistidine (a marker of myofibrillar protein degradation) for 24-48 hours after a very long event. Second, recovery from prolonged exercise requires adequate protein intake to rebuild what was catabolized. Contemporary sports nutrition recommendations for endurance athletes are 1.2-1.6 g/kg/day total protein, with up to 1.8 g/kg/day for ultra-endurance and stage-race contexts.
Intra-workout branched-chain amino acid supplementation has been marketed to endurance athletes on the rationale that providing exogenous branched-chain amino acids reduces the need for endogenous muscle proteolysis. The effects described for it are small: a modest reduction in perceived exertion (~5-8%) and a small reduction in markers of muscle damage, but no clear effect on actual endurance performance or recovery beyond what total protein intake provides. No meta-analysis giving the perceived-exertion figure could be found. A 2017 meta-analysis of eight trials by Rahimi and colleagues, on recovery after muscle-damaging exercise, found creatine kinase (a blood marker of muscle damage) lower than with placebo recovery at under 24 hours and at 24 hours; results for muscle soreness and lactate dehydrogenase were not significant. The proposed mechanism of the perceived-exertion benefit is the central fatigue hypothesis discussed on the cognitive performance page — branched-chain amino acid intake competes with tryptophan for brain entry and reduces serotonin-mediated central fatigue signaling.
Regulation of BCKAD Activity
BCKAD is one of the most heavily regulated metabolic enzymes in the body, reflecting the importance of conserving branched-chain amino acids when they are needed for protein synthesis while permitting rapid catabolism when they are in excess. Key regulatory inputs include:
- Phosphorylation state — BCKAD kinase phosphorylates and inactivates the complex; BCKAD phosphatase reverses this. The kinase is the dominant regulator in vivo; pharmacological inhibition of BCKAD kinase by clofibric acid analogs (currently in research stages) activates the complex and lowers plasma branched-chain amino acids. The drug sodium phenylbutyrate works the same way: laboratory work showed that it blocks the kinase, so the complex stays active, and it lowered these amino acids and their ketoacids in control subjects and in patients with late-onset, intermediate MSUD. The authors describe a benefit in a subset of MSUD patients and call for studies of long-term efficacy.
- Substrate-level feedback — elevated branched-chain alpha-ketoacids (the BCKAD substrates) inhibit the kinase and thereby activate the complex, providing autoregulatory throughput control.
- Hormonal control — in rats, insulin lowered plasma branched-chain amino acids in a dose-dependent way by raising the liver's protein level and activity of BCKAD, with brain insulin signaling a major regulator (Shin and colleagues, 2014); glucagon and glucocorticoids activate BCKAD (mobilize branched-chain amino acid for fuel in fasting and stress).
- Tissue-specific expression — BCKAD activity is highest in liver and kidney, intermediate in heart and skeletal muscle, lower in adipose tissue and brain. The relative tissue distribution shifts the flux of branched-chain amino acid catabolism between organs depending on the metabolic state.
- Inter-organ shuttling — in the fed state, the liver oxidizes a small fraction of dietary branched-chain amino acids and releases most into circulation for uptake by muscle. In the fasted or exercising state, muscle branched-chain amino acid proteolysis releases branched-chain amino acid and branched-chain amino acid-derived alanine to the liver for gluconeogenesis.
Recent research has implicated dysregulated branched-chain amino acid catabolism in metabolic disease. Elevated plasma branched-chain amino acids (and their ketoacids) are among the strongest amino acid biomarkers of insulin resistance and type 2 diabetes risk, observed years before clinical diabetes onset in longitudinal studies. The mechanism is debated — whether elevated branched-chain amino acids cause insulin resistance, or insulin resistance impairs BCKAD activity and elevates branched-chain amino acids secondarily — but the association is robust across populations. This has stimulated interest in BCKAD activators as a potential therapeutic strategy for type 2 diabetes prevention.
A 2022 pooled analysis of 9 studies linked higher blood valine to later type 2 diabetes (odds ratio 2.08, 95% confidence interval 2.04-2.12), holding across follow-up of 0-6, 6-12 and 12 or more years (odds ratios 2.08, 1.86 and 2.14). This shows association, not cause.
A 2022 double-blind crossover trial tested the idea in people with type 2 diabetes. Eighteen were randomized and 16 completed 2 weeks each of sodium phenylbutyrate (4.8 g per square meter of body surface a day) and placebo. Peripheral insulin sensitivity improved by 27% against placebo, and blood branched-chain amino acids and glucose fell, while insulin, triglycerides, free fatty acids and fat in muscle and liver did not change. No adverse events were reported.
Key Research Papers
- Menkes JH, Hurst PL, Craig JM (1954). A new syndrome: progressive familial infantile cerebral dysfunction associated with an unusual urinary substance. Pediatrics. — PubMed PMID: 13214961
- Strauss KA, Puffenberger EG, Morton DH (2020). Maple syrup urine disease. GeneReviews. — PubMed
- Harper AE, Miller RH, Block KP (1984). Branched-chain amino acid metabolism. Annual Review of Nutrition. — PubMed PMID: 6380539
- Chuang DT et al. (2006). Maple syrup urine disease (branched-chain ketoaciduria). In: Scriver's Online Metabolic and Molecular Bases of Inherited Disease. — PubMed
- Wang TJ et al. (2011). Metabolite profiles and the risk of developing diabetes. Nature Medicine. — PubMed PMID: 21423183
- Newgard CB et al. (2009). A branched-chain amino acid-related metabolic signature that differentiates obese and lean humans and contributes to insulin resistance. Cell Metabolism. — PubMed PMID: 19356713
- Lynch CJ, Adams SH (2014). Branched-chain amino acids in metabolic signalling and insulin resistance. Nature Reviews Endocrinology. — PubMed PMID: 25287287
- Brunetti-Pierri N et al. (2011). Phenylbutyrate therapy for maple syrup urine disease. Human Molecular Genetics. — PubMed PMID: 21098507
- Mazariegos GV et al. (2012). Liver transplantation for classical maple syrup urine disease: long-term follow-up in 37 patients and comparative United Network for Organ Sharing experience. Journal of Pediatrics. — PubMed PMID: 21839471
- Roe CR, Brunengraber H (2015). Anaplerotic treatment of long-chain fat oxidation disorders with triheptanoin: Review of 15 years Experience. Molecular Genetics and Metabolism. — PubMed PMID: 26547562
- Banerjee R, Ragsdale SW (2003). The many faces of vitamin B12: catalysis by cobalamin-dependent enzymes. Annual Review of Biochemistry. — PubMed PMID: 14527323
- Stabler SP (2013). Clinical practice. Vitamin B12 deficiency. New England Journal of Medicine. — PubMed PMID: 23301732
- Podebrad F, Heil M, Reichert S, Mosandl A, Sewell AC, Bohles H (1999). 4,5-dimethyl-3-hydroxy-2[5H]-furanone (sotolone)--the odour of maple syrup urine disease. Journal of Inherited Metabolic Disease. — PubMed PMID: 10234605
- Harris RA, Joshi M, Jeoung NH, Obayashi M (2005). Overview of the molecular and biochemical basis of branched-chain amino acid catabolism. Journal of Nutrition. — PubMed PMID: 15930464
- Shin AC et al. (2014). Brain insulin lowers circulating BCAA levels by inducing hepatic BCAA catabolism. Cell Metabolism. (Study in rats and mice, with human liver data.) — PubMed PMID: 25307860
- Forny P et al. (2021). Guidelines for the diagnosis and management of methylmalonic acidaemia and propionic acidaemia: First revision. Journal of Inherited Metabolic Disease. — PubMed PMID: 33595124
- Burch JS et al. (2018). Glutamine via alpha-ketoglutarate dehydrogenase provides succinyl-CoA for heme synthesis during erythropoiesis. Blood. — PubMed PMID: 29991557
- Rahimi MH, Shab-Bidar S, Mollahosseini M, Djafarian K (2017). Branched-chain amino acid supplementation and exercise-induced muscle damage in exercise recovery: A meta-analysis of randomized clinical trials. Nutrition. (A corrigendum was published, PMID 29277517.) — PubMed PMID: 28870476
- Jang C et al. (2016). A branched-chain amino acid metabolite drives vascular fatty acid transport and causes insulin resistance. Nature Medicine. — PubMed PMID: 26950361
- Ramzan I, Ardavani A, Vanweert F, Mellett A, Atherton PJ, Idris I (2022). The Association between Circulating Branched Chain Amino Acids and the Temporal Risk of Developing Type 2 Diabetes Mellitus: A Systematic Review & Meta-Analysis. Nutrients. — PubMed PMID: 36297095
- Vanweert F et al. (2022). A randomized placebo-controlled clinical trial for pharmacological activation of BCAA catabolism in patients with type 2 diabetes. Nature Communications. — PubMed PMID: 35717342
- Gillingham MB et al. (2017). Triheptanoin versus trioctanoin for long-chain fatty acid oxidation disorders: a double blinded, randomized controlled trial. Journal of Inherited Metabolic Disease. — PubMed PMID: 28871440
- Vockley J et al. (2023). Triheptanoin for the treatment of long-chain fatty acid oxidation disorders: Final results of an open-label, long-term extension study. Journal of Inherited Metabolic Disease. — PubMed PMID: 37276053
PubMed Topic Searches
Connections
- All Amino Acids
- Valine Overview
- Valine Benefits Hub
- Valine for Muscle Protein Synthesis
- Valine for Cognitive Performance
- Valine for Nitrogen Balance & Wound Healing
- Leucine (Branched-Chain Amino Acid Partner)
- Isoleucine (Branched-Chain Amino Acid Partner)
- Alanine (Glucose-Alanine Cycle)
- Glutamine
- Vitamin B12 (Methylmalonyl-CoA Mutase Cofactor)
- Vitamin B1 / Thiamine (BCKAD Cofactor)
- Vitamin B2 / Riboflavin
- Insulin Resistance
- Fasting
- History
- Sources