Tryptophan and Cognitive Function
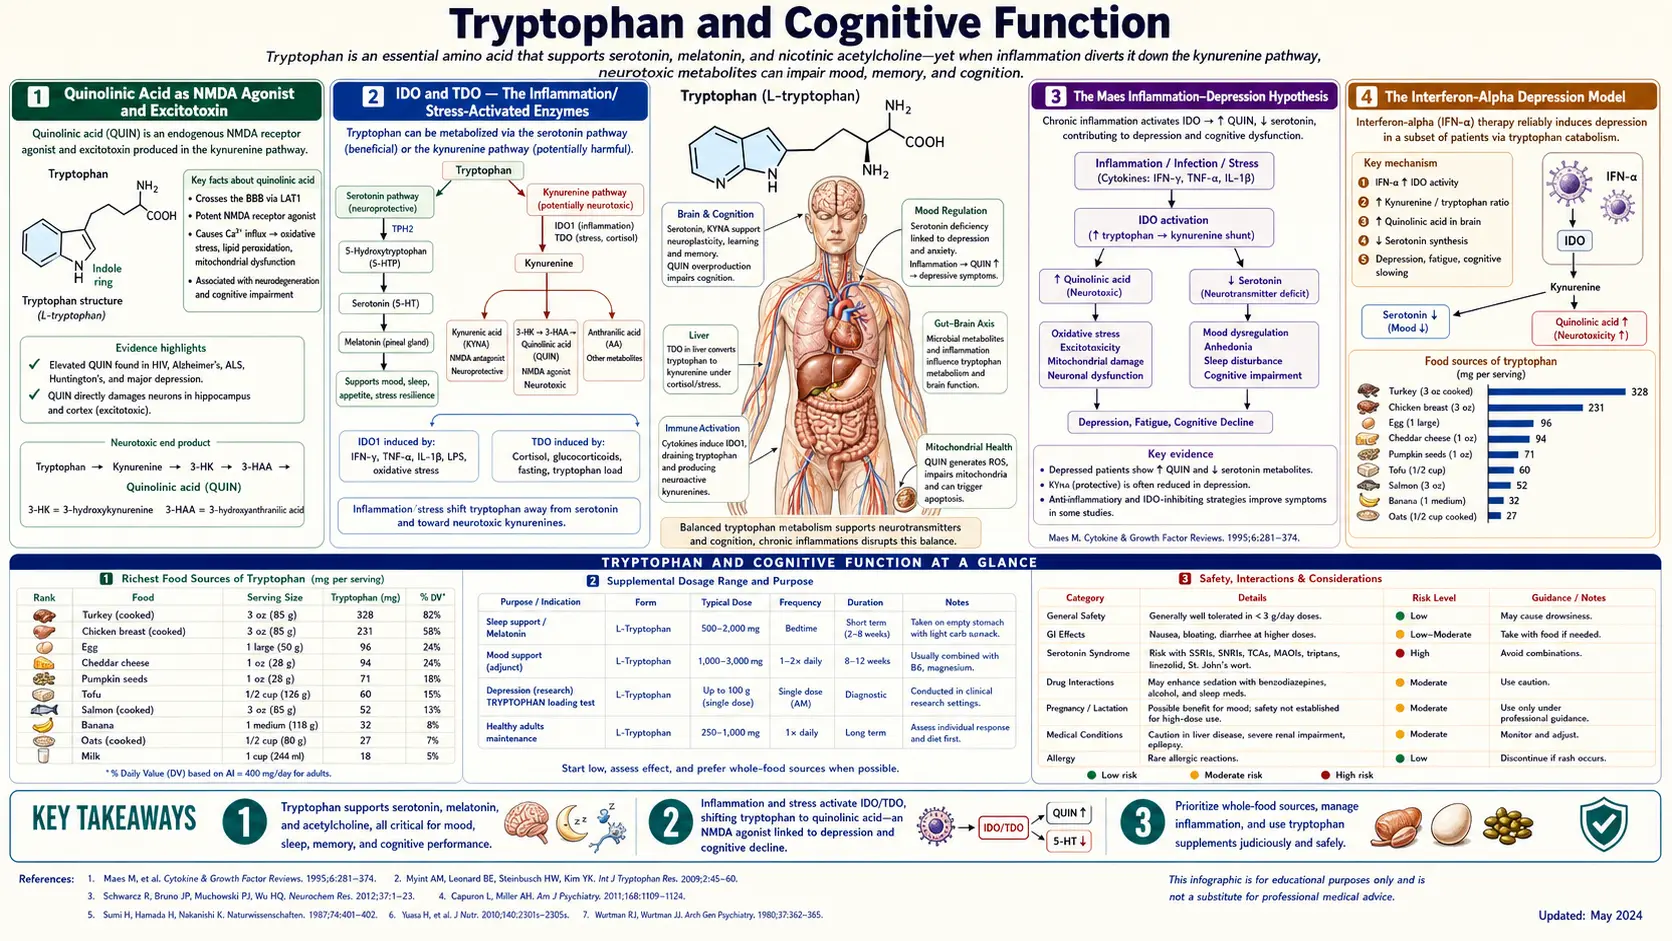
Tryptophan's most consequential effect on cognitive function does not come from serotonin biology, but from the kynurenine pathway and its excitotoxic metabolite quinolinic acid. Quinolinic acid is a N-methyl-D-aspartate (NMDA) glutamate receptor agonist and a generator of reactive nitrogen species; in the inflamed brain it accumulates to neurotoxic concentrations and contributes to neuronal injury in major depression, suicidal ideation, schizophrenia, Alzheimer's disease, Huntington's disease, human immunodeficiency virus-associated neurocognitive disorder, and chronic interferon-alpha therapy. The rate-limiting enzymes IDO (indoleamine 2,3-dioxygenase) and TDO (tryptophan 2,3-dioxygenase) are induced by inflammation (interferon-gamma) and stress (cortisol), respectively — making the kynurenine pathway one of the most important molecular bridges between systemic inflammation, chronic stress, depression, and neurodegeneration. Michael Maes formalized this in the inflammation-depression hypothesis in the 1990s, and the field has since produced an enormous body of clinical evidence linking interferon-induced depression, autoimmune-associated depression, and cerebrospinal fluid (CSF) quinolinic-to-kynurenic ratios as candidate biomarkers. The kynurenic acid branch acts as the neuroprotective counterbalance: kynurenic acid is a N-methyl-D-aspartate antagonist and is broadly neuroprotective. This page walks through quinolinic acid as a N-methyl-D-aspartate agonist and excitotoxin, the IDO/TDO regulatory biology, the Maes inflammation-depression hypothesis, the kynurenic-acid neuroprotection counterweight, and the implications for cognition, mood, and neurodegenerative disease.
Table of Contents
- Quinolinic Acid as N-Methyl-D-Aspartate Agonist and Excitotoxin
- IDO and TDO — The Inflammation/Stress-Activated Enzymes
- The Maes Inflammation-Depression Hypothesis
- The Interferon-Alpha Depression Model
- Quinolinic Acid and Suicidal Ideation
- Quinolinic Acid in Alzheimer's Disease
- Huntington's Disease and the Striatum
- The Schizophrenia Paradox — Elevated Kynurenic Acid
- Kynurenic Acid as Neuroprotective Counterbalance
- KMO Inhibitors as Drug Targets
- Practical Cognitive Implications
- Key Research Papers
- Connections
- Featured Videos
Quinolinic Acid as N-Methyl-D-Aspartate Agonist and Excitotoxin
Quinolinic acid (2,3-pyridinedicarboxylic acid, often abbreviated QUIN) is the penultimate metabolite of the kynurenine pathway before the committing step to nicotinamide adenine dinucleotide (NAD+) biosynthesis. Under normal physiologic conditions, brain quinolinic acid concentrations are low (nanomolar to low-micromolar range). Under chronic inflammation, microglial activation, or persistent interferon signaling, quinolinic acid concentrations can rise to micromolar concentrations that produce two simultaneous neurotoxic effects:
- N-methyl-D-aspartate receptor agonism — quinolinic acid is a selective agonist at the N-methyl-D-aspartate subtype of glutamate ionotropic receptors. N-methyl-D-aspartate receptors are calcium-permeable channels that, when activated chronically or excessively, produce intracellular calcium overload, mitochondrial dysfunction, generation of reactive oxygen and nitrogen species, and ultimately neuronal death via excitotoxicity. The neurons most vulnerable to N-methyl-D-aspartate-mediated excitotoxicity are the medium spiny neurons of the striatum, hippocampal CA1 pyramidal neurons, and pyramidal neurons of the cortex — precisely the regions affected in Huntington's disease and in late Alzheimer's disease.
- Free radical generation — quinolinic acid forms a complex with iron and catalyzes the generation of hydroxyl radicals via Fenton-like chemistry. It also stimulates nitric oxide synthase induction in adjacent astrocytes, generating peroxynitrite (the highly reactive product of nitric oxide combining with superoxide). The combination produces oxidative and nitrosative stress that extends the neurotoxic effect beyond direct N-methyl-D-aspartate-receptor channels.
The clinical-pharmacology evidence for quinolinic acid as a true neurotoxin (rather than a passive biomarker) comes from animal models: direct intrastriatal injection of quinolinic acid in rats produces a precise excitotoxic lesion that is the standard rodent model of Huntington's disease. The lesion preferentially destroys striatal medium spiny neurons while sparing cholinergic interneurons — exactly the pattern seen in Huntington's pathology.
For practical context: in a 2013 Swedish study, healthy adults had a cerebrospinal fluid quinolinic acid concentration of about 18 nM (Erhardt and colleagues). In severe inflammation, sepsis, advanced human immunodeficiency virus-associated neurocognitive disorder, or active interferon-alpha therapy, concentrations can rise several-fold. In human immunodeficiency virus type 1 (HIV-1) infection, Heyes and colleagues (1991) measured spinal-fluid quinolinic acid about twofold above normal in early stages, 3.8-fold in later stages, and over 20-fold in people with overt AIDS dementia complex, aseptic meningitis or opportunistic infections. These elevations correlate with clinical neurocognitive impairment and depressive symptoms.
IDO and TDO — The Inflammation/Stress-Activated Enzymes
The kynurenine pathway has two rate-limiting enzymes that catalyze the same chemical reaction (oxidation of tryptophan's indole ring at the C2-C3 bond) but are regulated by completely different signals:
- Indoleamine 2,3-dioxygenase 1 (IDO1) — expressed in most peripheral tissues including the lung, gut, placenta, dendritic cells, macrophages, and microglia. The principal inducer is interferon-gamma, the master cytokine of T-helper type 1 (Th1) cellular immunity. IFN-gamma can raise IDO1 expression 100-fold within hours. Other inflammatory cytokines (IFN-alpha, tumor necrosis factor-alpha, interleukin-1, interleukin-6) also contribute. IDO1 is also induced in tumor cells as part of immune escape biology — tumors that upregulate IDO1 deplete local tryptophan and starve attacking T cells.
- Indoleamine 2,3-dioxygenase 2 (IDO2) — a related enzyme with more restricted expression. Less well-characterized than IDO1.
- Tryptophan 2,3-dioxygenase (TDO) — expressed predominantly in the liver. Induced by cortisol and by high substrate (tryptophan) availability. TDO is the dominant enzyme handling postprandial tryptophan load and is the principal route for tryptophan disposition in unstressed metabolism.
The regulatory architecture means that any state of systemic inflammation or chronic psychological stress can shunt dietary tryptophan into the kynurenine pathway, with two downstream consequences:
- Less tryptophan available for serotonin/melatonin synthesis — predisposing to depression and insomnia.
- More tryptophan flowing into the kynurenine pathway, with the inflammation-specific bias toward the quinolinic-acid (neurotoxic) rather than the kynurenic-acid (neuroprotective) branch — predisposing to cognitive impairment and neurodegeneration.
This is the molecular pivot that explains why inflammation, chronic stress, depression, and cognitive decline are so consistently clustered in clinical observation.
The Maes Inflammation-Depression Hypothesis
Michael Maes, a Belgian psychiatrist, was one of the earliest and most persistent proponents of the now-mainstream view that major depression is, in many cases, fundamentally an inflammatory disorder. Beginning in the early 1990s, Maes and colleagues published a series of papers documenting that depressed patients had:
- Elevated serum inflammatory cytokines (interleukin-1, interleukin-6, tumor necrosis factor-alpha, soluble interleukin-2 receptor (sIL-2R), acute-phase proteins).
- Elevated indices of oxidative and nitrosative stress (lipid peroxides, oxidized low-density lipoprotein (LDL), reduced glutathione, decreased antioxidant capacity).
- Activated indoleamine 2,3-dioxygenase with reduced plasma tryptophan and shifted tryptophan/competing-amino-acid ratios.
- Elevated kynurenine and quinolinic-acid metabolites in plasma and cerebrospinal fluid.
- Increased intestinal permeability ("leaky gut") with elevated antibodies to bacterial lipopolysaccharide (LPS) components, contributing to chronic low-grade systemic inflammation.
Maes integrated these findings into what he called the IO&NS hypothesis (Inflammation and Oxidative & Nitrosative Stress). In this framework, depression is not simply a serotonin-deficiency disorder but is the brain's response to chronic peripheral inflammation, which acts through kynurenine pathway activation, microglial priming, oxidative stress, and reduced serotonin synthesis to produce the clinical syndrome of major depression.
The implications include:
- Anti-inflammatory interventions should have antidepressant effects (and several do — omega-3 fatty acids, curcumin, and aspirin have all shown modest antidepressant signals in trials).
- Medical conditions associated with chronic inflammation (rheumatoid arthritis, inflammatory bowel disease, chronic hepatitis, cardiovascular disease, type 2 diabetes) should have elevated rates of comorbid depression — and they do.
- Inflammatory biomarkers should predict treatment response — emerging evidence suggests that elevated C-reactive protein (CRP) and interleukin-6 predict poorer response to selective serotonin reuptake inhibitor (SSRI) monotherapy and better response to certain anti-inflammatory adjuncts.
- Treatments targeting the kynurenine pathway (KMO inhibitors, IDO inhibitors) should have antidepressant potential — this is an active drug-development area.
The Maes IO&NS framework has become increasingly mainstream in academic psychiatry over the past fifteen years, particularly with the rise of the broader "inflammation in psychiatry" movement led by figures like Andrew Miller at Emory and Charles Raison.
The Interferon-Alpha Depression Model
The cleanest clinical proof-of-concept for the inflammation-kynurenine-depression hypothesis comes from the iatrogenic depression produced by therapeutic interferon-alpha. From the 1990s through the 2010s, interferon-alpha was widely used to treat chronic hepatitis C, certain hematologic malignancies (chronic myeloid leukemia, hairy cell leukemia), and malignant melanoma. The treatment was famously effective at suppressing viral replication but carried a striking neuropsychiatric side-effect profile: up to 30% of patients receiving sustained IFN-alpha therapy develop a depressive syndrome that meets the Diagnostic and Statistical Manual of Mental Disorders (DSM) criteria for major depressive disorder, often emerging within weeks to months of treatment initiation.
This iatrogenic depression has been one of the most studied human models of cytokine-induced depression. Key findings:
- IFN-alpha activates IDO and drives plasma tryptophan down. In 18 hepatitis C patients given interferon-alpha for 6 months (Bonaccorso and colleagues, 2002), plasma tryptophan and blood serotonin fell, kynurenine and the kynurenine-to-tryptophan ratio rose, and the rise in depression scores (Montgomery-Asberg Depression Rating Scale, MADRS) tracked the rise in kynurenine and the fall in serotonin.
- Cerebrospinal fluid quinolinic acid rises measurably and correlates with depression-rating-scale scores.
- The kynurenine/tryptophan ratio in plasma rises substantially and correlates with severity of depressive symptoms.
- Selective serotonin reuptake inhibitor pretreatment with paroxetine (Musselman, Miller and colleagues, 2001, in 40 melanoma patients on high-dose interferon alfa) cut major depression during the first 12 weeks from 45% on placebo (9 of 20) to 11% (2 of 18), supporting a causal role for serotonin depletion downstream of kynurenine pathway activation. A 2014 meta-analysis of 7 trials in hepatitis C (591 patients) found that selective serotonin reuptake inhibitors as a group lowered the odds of interferon-induced major depression (odds ratio 0.53; about 12 people treated to prevent one case).
- Symptoms resolve over weeks to months after IFN-alpha discontinuation, paralleling the recovery of plasma tryptophan and the resolution of the kynurenine pathway activation.
With the rise of direct-acting antiviral agents for hepatitis C, IFN-alpha is no longer the standard of care, but the model remains scientifically important. It is the strongest available evidence that a controllable, time-limited cytokine stimulus can cause major depression in previously well humans, and that the kynurenine pathway is mechanistically central to the connection.
How common it was: a 2012 meta-analysis of 26 prospective studies of hepatitis C patients starting interferon found that about 1 in 4 developed major depression (25% by 24 weeks of treatment and 28% by 48 weeks). A past episode of depression (odds ratio 3.96), higher interleukin-6 levels before treatment, and female sex were among the factors linked to higher risk.
Quinolinic Acid and Suicidal Ideation
One of the most striking lines of contemporary kynurenine pathway research is the work of Lena Brundin, Sophie Erhardt, and colleagues at the Karolinska Institutet and Lund University in Sweden on quinolinic acid and suicidality. In a series of papers beginning around 2009 and culminating in major publications in 2013 and after, the group demonstrated:
- In the 2013 study, 64 medication-free patients after recent suicide attempts had about twice the cerebrospinal fluid quinolinic acid of 36 healthy controls (41.9 vs 18.2 nM).
- The elevation was largely independent of depression severity scores (it did not correlate with the Montgomery-Asberg Depression Rating Scale) and instead tracked scores on the Suicide Intent Scale and spinal-fluid interleukin-6, so it appeared to be a more specific biomarker of suicidality than of depression itself.
- In the 8 patients who gave a second spinal-fluid sample within 6 months of the attempt, quinolinic acid fell significantly, back to the level of the healthy controls.
- The elevation was accompanied by reduced cerebrospinal fluid kynurenic acid in some studies, magnifying the kynurenic / quinolinic ratio shift toward the neurotoxic side. In the 2013 study kynurenic acid itself did not differ (1.31 vs 1.37 nM), so the shift came from the rise in quinolinic acid.
- Plasma kynurenine metabolite ratios correlated with the cerebrospinal fluid findings, suggesting peripheral biomarkers could be developed.
The hypothesis emerging from this work is that quinolinic acid-driven N-methyl-D-aspartate receptor overactivation in cortical and limbic regions may contribute to the neurobiology of suicidal ideation specifically — over and above the more general inflammation-depression link. This is biologically interesting because it dovetails with the discovery that N-methyl-D-aspartate receptor antagonists like ketamine produce rapid antidepressant and anti-suicidal effects. If suicidality is driven in part by N-methyl-D-aspartate receptor hyperactivity from elevated quinolinic acid, then antagonizing N-methyl-D-aspartate receptors should produce rapid relief — and ketamine does. The kynurenine biology and the ketamine biology may be two sides of the same molecular coin.
Quinolinic Acid in Alzheimer's Disease
The kynurenine pathway is now broadly recognized as one of the inflammatory contributors to Alzheimer's disease pathology. Multiple lines of evidence have accumulated:
- Quinolinic acid concentrations are elevated in the cortex and hippocampus of postmortem Alzheimer's brain tissue, particularly in regions adjacent to amyloid plaques where microglial activation is most intense.
- The kynurenine pathway intermediates are detectable in cerebrospinal fluid and the kynurenine/tryptophan ratio is elevated in Alzheimer's patients compared to age-matched controls.
- Inflammatory cytokines that activate IDO (IFN-gamma, interleukin-1-beta, tumor necrosis factor-alpha) are reliably elevated in Alzheimer's brain and cerebrospinal fluid.
- Microglia surrounding amyloid plaques express high levels of IDO and produce quinolinic acid locally.
The integrative picture is that chronic neuroinflammation — whether triggered by amyloid-beta accumulation, tau pathology, or peripheral inflammatory contributors — activates the microglial kynurenine pathway, generates local quinolinic acid, and contributes to excitotoxic neuronal injury that compounds the primary amyloid/tau pathology. This is not the cause of Alzheimer's disease in the strict sense; it is a contributing mechanism of the neurodegenerative cascade. It is also one of the rationales for ongoing interest in anti-inflammatory and microglial-targeted therapies for Alzheimer's disease.
Pooled human measurements complicate this picture. A meta-analysis of 98 studies published in 2025 (27 of them comparing people with Alzheimer's dementia with healthy people) found that spinal-fluid quinolinic acid was lower, not higher, in Alzheimer's dementia (standardized mean difference −0.38), spinal-fluid kynurenic acid slightly higher, and blood tryptophan and kynurenic acid lower. Links between these metabolites and memory and thinking test scores were inconclusive and mostly not significant. The authors write that the findings challenge the assumption that high neurotoxic quinolinic acid levels are associated with dementia.
Huntington's Disease and the Striatum
Huntington's disease is the textbook example of selective excitotoxicity. The disease is caused by an expanded CAG trinucleotide repeat in the huntingtin gene, producing mutant huntingtin protein that accumulates in neurons. The cellular pathology preferentially affects the medium spiny neurons of the striatum — the projection neurons of the caudate and putamen. The progressive striatal atrophy is the anatomic basis of the motor (chorea) and cognitive (executive dysfunction, dementia) manifestations of the disease.
The striking observation in the kynurenine literature is that direct intrastriatal injection of quinolinic acid in rats produces a precise lesion that recapitulates the cellular pathology of Huntington's disease. Medium spiny neurons die selectively while cholinergic interneurons are spared. This quinolinic-acid lesion model has been the standard rodent model of Huntington's disease for decades. In the 1986 rat study by Beal and colleagues, quinolinic acid lesions depleted the nerve-signal chemicals gamma-aminobutyric acid (GABA) and substance P while sparing the nerve cells that carry somatostatin and neuropeptide Y — the same chemical pattern found in Huntington's brains — whereas other excitotoxins (kainic acid, ibotenic acid, N-methyl-D-aspartate itself) killed all cell types. This is animal evidence, not a human finding.
In human Huntington's disease tissue, kynurenine pathway enzymes are upregulated in microglia, kynurenine pathway metabolites are altered (with kynurenic acid initially elevated and then depleted as the disease progresses), and the kynurenic / quinolinic ratio shifts toward neurotoxicity over time. The relevance of the kynurenine pathway to Huntington's pathogenesis is now well established, and KMO inhibitors that shunt flux toward the kynurenic (protective) branch have shown promise in animal models of the disease.
The Schizophrenia Paradox — Elevated Kynurenic Acid
Schizophrenia presents an interesting paradox in kynurenine biology. While most psychiatric and neurodegenerative conditions show increased quinolinic acid relative to kynurenic acid, several studies have found that schizophrenia patients have elevated kynurenic acid concentrations in cerebrospinal fluid and postmortem brain tissue. This is biologically meaningful because kynurenic acid is a N-methyl-D-aspartate receptor antagonist — and the leading neurobiological hypothesis of schizophrenia is that N-methyl-D-aspartate receptor hypofunction contributes to the disorder's positive, negative, and cognitive symptoms.
The schizophrenia evidence base includes:
- Increased cerebrospinal fluid kynurenic acid in male schizophrenia patients compared to controls (Erhardt et al. 2001: 28 men with schizophrenia, 1.67 nM, vs 17 healthy men, 0.97 nM).
- Increased kynurenic acid in postmortem prefrontal cortex of schizophrenia patients.
- Genetic variants in kynurenine pathway enzymes associated with schizophrenia risk.
- Animal models in which elevated brain kynurenic acid produces deficits in prepulse inhibition, working memory, and social interaction — behaviors that translate to schizophrenia-relevant phenotypes.
This is one of the threads connecting the dissociative anesthetic N-methyl-D-aspartate antagonists (ketamine, phencyclidine (PCP)) to schizophrenia-like states — both pharmacologic N-methyl-D-aspartate antagonism and endogenous elevation of the natural N-methyl-D-aspartate antagonist kynurenic acid can produce overlapping symptomatology. It also raises the interesting possibility that different psychiatric disorders may correspond to different points on the kynurenic-quinolinic continuum: depression and suicidality at the quinolinic (excitotoxic) end, schizophrenia at the kynurenic (N-methyl-D-aspartate-hypofunction) end.
Blood measurements add a qualification. A 2021 meta-analysis of 101 studies (10,912 people) found tryptophan and kynurenine lower in major depression, bipolar disorder and schizophrenia. In the mood disorders the balance tipped toward quinolinic acid (a lower kynurenic-to-quinolinic acid ratio), but blood kynurenic acid was not altered in schizophrenia — the raised kynurenic acid described above comes from spinal fluid and brain tissue, not from blood.
Kynurenic Acid as Neuroprotective Counterbalance
Kynurenic acid is the kynurenine pathway's good news. Produced by the kynurenine aminotransferases (KAT I, KAT II, KAT III, KAT IV), all of which require pyridoxal-5-phosphate as cofactor, kynurenic acid acts at multiple receptors with broadly protective effects:
- N-methyl-D-aspartate receptor antagonism — binds the glycine modulatory site of the N-methyl-D-aspartate receptor and reduces glutamatergic neurotransmission. This is the principal neuroprotective mechanism.
- Alpha-7 nicotinic acetylcholine receptor antagonism — reduces presynaptic glutamate release and modulates cognitive function.
- GPR35 agonism — an orphan G-protein-coupled receptor with anti-inflammatory effects, particularly in the gut and immune cells.
- Free radical scavenging — kynurenic acid is a modest direct antioxidant and reduces oxidative stress in inflamed tissue.
Astrocytes are the principal producers of kynurenic acid in the brain. Astrocytes express KAT II at high levels and continuously produce kynurenic acid as part of their tonic neuromodulation of synaptic glutamate. In acute injury (stroke, traumatic brain injury), astrocyte kynurenic acid production rises as part of the endogenous neuroprotective response.
The therapeutic implication is that boosting kynurenic acid (or its synthetic precursors that cross the blood-brain barrier (BBB) more readily than kynurenic acid itself) might be neuroprotective in stroke, traumatic brain injury, multiple sclerosis, and excitotoxic neurodegenerative disease. Several research programs are pursuing this strategy.
KMO Inhibitors as Drug Targets
Kynurenine 3-monooxygenase (KMO) is the enzyme at the kynurenic-quinolinic branchpoint. It directs kynurenine flux toward the quinolinic-acid (neurotoxic) branch. Inhibiting KMO has the dual effect of:
- Reducing production of quinolinic acid downstream — reducing excitotoxic burden.
- Shunting more kynurenine into the kynurenic-acid (neuroprotective) branch — raising endogenous neuroprotection.
KMO inhibitors are an active drug-discovery area in pharmaceutical research. Several have entered preclinical and early clinical development for Huntington's disease, Alzheimer's disease, major depression, and inflammatory disorders. The class's pharmacological appeal is that it intervenes at a regulatable branchpoint rather than at any single downstream target, potentially producing broad effects with a single pharmacologic action.
Brain-penetrant KMO inhibitors have been the major design challenge — many candidate molecules have good potency in vitro but poor blood-brain barrier penetration, limiting their effect to peripheral kynurenine pathway modulation. The peripheral effect alone produces measurable changes in brain kynurenine pathway metabolites (because circulating kynurenine itself crosses the BBB and shifts brain pathway dynamics), but the peripheral-only constraint has slowed development.
Adjacent drug classes that target the same axis include IDO1 inhibitors (epacadostat and others, mainly in oncology trials), TDO inhibitors (less clinically advanced), and AhR modulators (the aryl hydrocarbon receptor is a kynurenine-activated transcription factor with broad immune and metabolic effects).
The largest test of an IDO1 inhibitor so far was negative. In the phase 3 ECHO-301/KEYNOTE-252 trial, 706 people with advanced melanoma received the immunotherapy drug pembrolizumab plus either epacadostat or placebo; progression-free survival was the same (median 4.7 vs 4.9 months, hazard ratio 1.00) and overall survival did not improve.
Practical Cognitive Implications
Researchers draw several links between kynurenine pathway biology and cognitive function, mood, and long-term brain health:
- Chronic inflammation is bad for brain function in part through the kynurenine pathway. Common ways of lowering chronic inflammatory burden — weight management, regular physical activity, anti-inflammatory dietary patterns (Mediterranean diet, omega-3 fatty acids, polyphenol-rich foods, fiber), adequate sleep, stress management — have a specific molecular rationale in kynurenine biology beyond generic wellness.
- Supplemental tryptophan in active inflammation may not produce the expected serotonin boost because the substrate is being shunted into kynurenine; while the inflammation persists, the diversion continues.
- The pathway depends on vitamin and mineral cofactors. Vitamin B6 (active form pyridoxal-5-phosphate) is required for both kynureninase (kynurenine pathway) and aromatic L-amino acid decarboxylase (AADC, serotonin pathway) and for the kynurenine aminotransferases that produce protective kynurenic acid. Vitamin B2 (riboflavin) is required for KMO. Iron is required for IDO/TDO. Suboptimal status of any of these can distort the pathway in unhelpful directions.
- Researchers describe an inflammatory subtype of depression, often with prominent cognitive features. Elevated C-reactive protein, interleukin-6, or other inflammatory markers may suggest a poorer response to selective serotonin reuptake inhibitor monotherapy and a better response to anti-inflammatory adjuncts (omega-3 fatty acids, curcumin, nonsteroidal anti-inflammatory drugs (NSAIDs) in some studies, or in research settings IDO/KMO inhibitors as they become available).
- Depression and cognitive symptoms are more common in chronic inflammatory disease (rheumatoid arthritis, inflammatory bowel disease (IBD), hepatitis C, type 2 diabetes, cardiovascular disease), an elevated risk that the molecular biology predicts.
- Brain fog in chronic illness has a kynurenine-pathway interpretation. The combination of low serotonin tone (substrate diversion) and elevated quinolinic acid (microglial activation) produces the typical clinical picture of dampened mood, reduced cognitive flexibility, and difficulty concentrating that patients describe. See Brain Fog.
Key Research Papers
- Maes M, Berk M, Goehler L, et al. (2012). Depression and sickness behavior are Janus-faced responses to shared inflammatory pathways. BMC Medicine 10:66. — PubMed PMID: 22747645
- Capuron L, Miller AH (2011). Immune system to brain signaling: neuropsychopharmacological implications. Pharmacology & Therapeutics 130:226–238. — PubMed PMID: 21334376
- Erhardt S, Lim CK, Linderholm KR, et al. (2013). Connecting inflammation with glutamate agonism in suicidality. Neuropsychopharmacology 38:743–752. — PubMed PMID: 23299933
- Schwarcz R, Bruno JP, Muchowski PJ, Wu HQ (2012). Kynurenines in the mammalian brain: when physiology meets pathology. Nature Reviews Neuroscience 13:465–477. — PubMed PMID: 22678511
- Capuron L, Hauser P, Hinze-Selch D, Miller AH, Neveu PJ (2002). Treatment of cytokine-induced depression. Brain, Behavior, and Immunity 16:575–580. — PubMed PMID: 12401471
- Musselman DL, Lawson DH, Gumnick JF, et al. (2001). Paroxetine for the prevention of depression induced by high-dose interferon alfa. New England Journal of Medicine 344:961–966. — PubMed PMID: 11274622
- Udina M, Hidalgo D, Navinés R, et al. (2014). Prophylactic antidepressant treatment of interferon-induced depression in chronic hepatitis C: a systematic review and meta-analysis. Journal of Clinical Psychiatry 75:e1113–e1121. — PubMed PMID: 25373120
- Udina M, Castellví P, Moreno-España J, et al. (2012). Interferon-induced depression in chronic hepatitis C: a systematic review and meta-analysis. Journal of Clinical Psychiatry 73:1128–1138. — PubMed PMID: 22967776
- Wonodi I et al. (2011). Downregulated kynurenine 3-monooxygenase gene expression and enzyme activity in schizophrenia and genetic association with schizophrenia endophenotypes. Archives of General Psychiatry 68:665–674. — PubMed PMID: 21727251
- Beal MF et al. (1986). Replication of the neurochemical characteristics of Huntington's disease by quinolinic acid. Nature 321:168–171. — PubMed PMID: 2422561
- Guillemin GJ, Brew BJ (2002). Implications of the kynurenine pathway and quinolinic acid in Alzheimer's disease. Redox Report 7:199–206. — PubMed PMID: 12396664
- Heyes MP, Brew BJ, Martin A, et al. (1991). Quinolinic acid in cerebrospinal fluid and serum in HIV-1 infection: relationship to clinical and neurological status. Annals of Neurology 29:202–209. — PubMed PMID: 1826418
- Bonaccorso S et al. (2002). Increased depressive ratings in patients with hepatitis C receiving interferon-alpha-based immunotherapy are related to interferon-alpha-induced changes in the serotonergic system. Journal of Clinical Psychopharmacology. — PubMed PMID: 11799348
- Stone TW, Darlington LG (2002). Endogenous kynurenines as targets for drug discovery and development. Nature Reviews Drug Discovery 1:609–620. — PubMed PMID: 12402501
- Erhardt S, Blennow K, Nordin C, et al. (2001). Kynurenic acid levels are elevated in the cerebrospinal fluid of patients with schizophrenia. Neuroscience Letters 313:96–98. — PubMed PMID: 11684348
- Marx W, McGuinness AJ, Rocks T, et al. (2021). The kynurenine pathway in major depressive disorder, bipolar disorder, and schizophrenia: a meta-analysis of 101 studies. Molecular Psychiatry 26:4158–4178. — PubMed PMID: 33230205
- Choe K, Bakker L, van den Hove DLA, et al. (2026). Kynurenine pathway dysregulation in cognitive impairment and dementia: a systematic review and meta-analysis. GeroScience 48:4585–4619. — PubMed PMID: 40338439
- Long GV, Dummer R, Hamid O, et al. (2019). Epacadostat plus pembrolizumab versus placebo plus pembrolizumab in patients with unresectable or metastatic melanoma (ECHO-301/KEYNOTE-252): a phase 3, randomised, double-blind study. Lancet Oncology 20:1083–1097. — PubMed PMID: 31221619
PubMed Topic Searches
Connections
- All Amino Acids
- Tryptophan Overview
- Tryptophan Benefits Hub
- Tryptophan for Sleep
- Tryptophan for Mood
- Tryptophan and Niacin
- Depression
- Anxiety
- Brain Fog
- Vitamin B6 (Multiple Pathway Enzymes)
- Vitamin B3 (Niacin / Nicotinamide Adenine Dinucleotide)
- Omega-3 Fatty Acids (Anti-Inflammatory)
- Gut-Brain Axis
- Inflammatory Bowel Disease
- Iron (IDO/TDO Cofactor)
- Schizophrenia — the kynurenine paradox: elevated kynurenic acid and N-methyl-D-aspartate receptor hypofunction.
- History
- Sources