Vitamin B6 Deficiency: Depression and Confusion
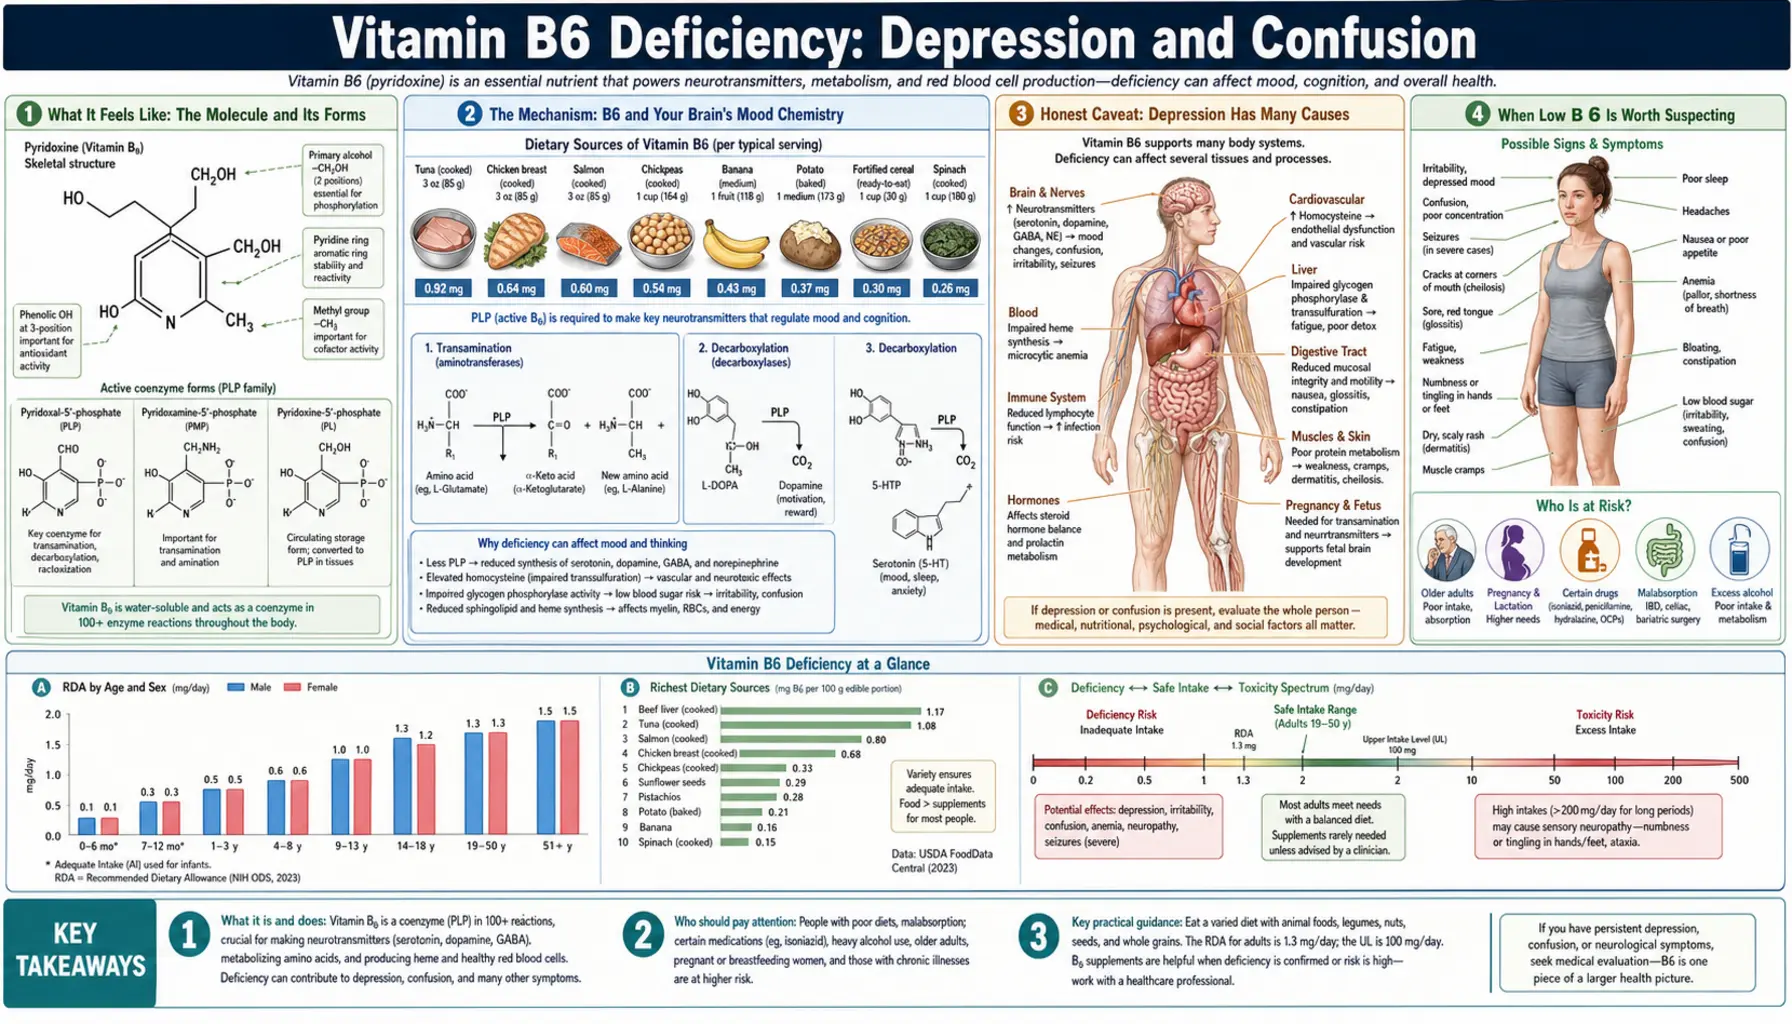
Vitamin B6 sits at the center of how your brain makes its mood chemicals. In its active form, pyridoxal-5′-phosphate, it is the spark that converts amino acids into serotonin, dopamine, and gamma-aminobutyric acid (GABA) — the messengers that steady your mood, drive motivation, and quiet the nervous system. When B6 runs genuinely low, that chemistry can falter, and some people feel it as low mood, irritability, mental fog, or confusion. But here is the honest part you deserve up front: most depression is not caused by low B6, and taking B6 will not lift the mood of someone whose levels are already normal. This page is about the specific situation of a real deficiency — what it can feel like, why the brain is involved, how to tell whether B6 is actually part of your picture, and how it is corrected.
Table of Contents
- What It Feels Like
- The Mechanism: B6 and Your Brain's Mood Chemistry
- Honest Caveat: Depression Has Many Causes
- When Low B6 Is Worth Suspecting
- What Drives B6 Low Enough to Affect Mood
- Getting Tested
- Correcting Low B6 Safely
- When to Seek Care / Red Flags
- Key Research Papers
- Connections
- Featured Videos
What It Feels Like
The mood and thinking changes tied to low vitamin B6 are usually subtle and slow-building rather than sudden. They rarely announce themselves as “a vitamin problem.” Instead, people tend to describe a gradual dimming — a sense that the color has drained out of things, that the usual rewards of life feel flat, and that the mind doesn't run as clearly as it used to. Common descriptions include:
- Low or depressed mood — a persistent heaviness, sadness, or emptiness that doesn't lift with rest or good news, and a loss of interest or pleasure in things that normally feel good.
- Irritability and a short fuse — feeling on edge, snapping at small things, or being unusually impatient. This is one of the more frequently reported features when B-vitamin status is poor.
- Mental fog and slowed thinking — trouble concentrating, losing your train of thought, reading the same paragraph twice, or feeling like your mind is moving through molasses.
- Confusion — in more pronounced or prolonged deficiency, genuine disorientation: difficulty keeping track of the day, the conversation, or where things are. This is more typical of older adults, heavy alcohol use, or deficiency layered on top of other illness.
- Low energy and poor sleep — fatigue and disrupted sleep often travel alongside the mood changes, because the same neurotransmitter pathways shape both.
Two things are worth understanding about this symptom picture. First, it is non-specific — every one of these complaints has dozens of possible causes, and none of them, alone, points to vitamin B6. Second, when low B6 is contributing, it almost never travels alone: it tends to show up alongside other clues of poor B6 status, such as the cracked lips and skin rash described on the Skin Rashes and Cracked Lips page, or the tingling and numbness covered under Nerve Symptoms. A mood change plus those physical signs, in someone with a reason to be deficient, is a far stronger hint than mood change by itself.
The Mechanism: B6 and Your Brain's Mood Chemistry
To understand why a vitamin would touch your mood at all, it helps to know what vitamin B6 actually does in the brain. B6 from food (pyridoxine, pyridoxal, pyridoxamine) is converted in the body into one master active form: pyridoxal-5′-phosphate, usually abbreviated PLP. PLP is what scientists call a coenzyme — a helper molecule that more than 140 different enzymes borrow in order to do their jobs. A large share of those enzymes work on amino acids, and several of them are the exact enzymes that build your brain's neurotransmitters (Parra 2018; Kennedy 2016).
Three of those neurotransmitter-building steps matter most for mood and clear thinking:
- Serotonin — the “steadiness” chemical involved in mood, calm, and sleep. The amino acid tryptophan is converted toward serotonin by an enzyme (aromatic L-amino acid decarboxylase) that requires PLP to fire. No PLP, no efficient final step to serotonin.
- Dopamine — the “motivation and reward” chemical. The same PLP-dependent decarboxylase enzyme performs the final step that produces dopamine from its precursor. Low dopamine signaling is linked to the flat, joyless, unmotivated feeling that people in low mood often describe.
- Gamma-aminobutyric acid — the brain's main calming, inhibitory messenger, the brake pedal of the nervous system. Gamma-aminobutyric acid is made from the amino acid glutamate by an enzyme called glutamic acid decarboxylase, which again cannot work without PLP (see Glutamic Acid and gamma-aminobutyric acid Production). When PLP falls far enough, gamma-aminobutyric acid production drops, the brake weakens, and the nervous system becomes over-excitable — which is part of why severe B6 deficiency can, at its extreme, trigger seizures (covered on the Anemia and Seizures page).
An analogy. Think of PLP as the single specialized tool that three different workers on an assembly line all need to finish their product — one worker boxes up serotonin, one boxes up dopamine, one boxes up gamma-aminobutyric acid. When the toolbox is full, all three lines run smoothly. When B6 gets scarce, there aren't enough tools to go around: every line slows at once, and the brain's supply of its mood-and-calm chemicals tightens together. That is why a single vitamin shortage can ripple out into mood, motivation, and a jittery, foggy feeling all at the same time — the deficiency isn't hitting one chemical, it's throttling the shared step that makes several of them.
This shared role is also why B6 is part of the broader story of the brain's chemistry that Vitamin B6 for Neurotransmitter Synthesis and Pyridoxine and Brain Health explore in more depth. It is the biological reason a genuine deficiency can affect mood — not proof that mood problems are usually caused by it, which brings us to the honest caveat.
One study in people fits the gamma-aminobutyric acid part of this picture. In a 2022 double-blind study in young adults, one month of high-dose vitamin B6 reduced self-reported anxiety (measured in 265 people) and showed only a trend toward reduced depression (measured in 146 people) compared with placebo; the authors linked the result to B6's known role in making gamma-aminobutyric acid (Field 2022).
Honest Caveat: Depression Has Many Causes
Put plainly: Depression is common, serious, and almost always has nothing to do with vitamin B6. The plausible biology above does not mean that low mood is usually a vitamin problem, and it does not mean that swallowing B6 will fix it. Two separate facts both need to be true at once, and confusing them causes real harm.
Fact one: low B6 status and depression are statistically linked in some studies. Researchers have repeatedly found that people with lower blood levels of B6 (low plasma PLP) report more depressive symptoms. The Danish study by Hvas and colleagues found that a lower B6 level was associated with more symptoms of depression (Hvas 2004). Among 618 older Caribbean Hispanic adults and a comparison group of 251 older non-Hispanic white adults in Massachusetts, Merete and colleagues found that low B6 status was associated with more depressive symptoms: a plasma PLP below 20 nmol/L “approximately doubled the likelihood of depressive caseness” (Merete 2008), and a follow-up of older Latino adults found the same relationship held over time (Arévalo 2019). A 2022 meta-analysis that pooled 18 observational studies found that people in the highest category of dietary vitamin B6 intake had a lower risk of depression than those in the lowest (pooled relative risk 0.81); the link was significant in women (0.71) but not in men (0.92) (Wu 2022). These are associations, not proof of cause — but the association is real.
Fact two: association is not the same as cause, and supplementing B6 in people who are not deficient does not treat depression. A low B6 level in someone who is depressed could mean the depression (poor appetite, poor diet, inflammation, less time outdoors and cooking) lowered the B6 — the arrow may point the other way. When this has been put to the test in randomized trials — the gold standard — giving B vitamins to people who are not deficient has generally not prevented or relieved depression. In a two-year placebo-controlled trial, 299 men aged 75 and older who were free of clinically significant depression took either 400 micrograms of vitamin B12, 2 mg of folic acid and 25 mg of vitamin B6 a day, or a placebo. The vitamins did not reduce the onset or severity of depressive symptoms compared with placebo: at the end, 84.3% of the men on vitamins and 79.1% of those on placebo remained free of clinically significant depressive symptoms, a difference that was not statistically significant (Ford 2008). Major reviews of B vitamins and the brain reach a similar bottom line: supplementation helps when there is a genuine shortfall, and does little for mood when status is already adequate (Kennedy 2016).
The everyday causes of depression and confusion are many, and most are far more likely than a B6 deficiency:
- Clinical depression itself — a real medical condition driven by genetics, brain chemistry, and circumstance, treatable with therapy and/or medication. It does not require a vitamin to explain it.
- Stress, grief, burnout, and life events — loss, overwork, isolation, and chronic stress are among the most common triggers of low mood.
- Thyroid disease — an underactive thyroid is a classic, very common, and very treatable mimic of depression and mental sluggishness.
- Poor or disrupted sleep, and sleep apnea — chronic sleep loss alone can produce low mood, irritability, and foggy thinking.
- Other nutrient gaps — low vitamin B12, low folate (vitamin B9), low iron, and low vitamin D are each associated with mood and cognitive symptoms, and they often travel together with low B6 in the same at-risk person.
- Medications, alcohol, and other medical illness — many drugs, heavy alcohol use, and conditions such as anemia, infection, or kidney and liver disease can all cause low mood or confusion.
- In older adults, sudden confusion is a red flag — abrupt confusion (delirium) is more often caused by infection, dehydration, medications, or another acute illness than by any vitamin, and it needs prompt medical evaluation (see red flags).
The honest takeaway: B6 belongs on the list of contributors worth checking in the right person, but it is near the bottom of the list of likely causes for most people with depression. High-dose pills taken for presumed “low B6” in place of proper care fall short on two counts — in people who are not deficient, B vitamins have not relieved depression in trials, and, paradoxically, too much B6 from supplements can itself cause nerve problems (see the B6 toxicity discussion).
When Low B6 Is Worth Suspecting
Given how common depression is and how rarely B6 is the culprit, when does it make sense to actually think about vitamin B6? The signal is strongest when mood or cognitive changes appear in the right context and alongside other signs of deficiency rather than in isolation. Reasonable clues include:
- The mood change comes with physical signs of B6 deficiency — a greasy, scaly rash around the nose, mouth, or eyes; cracked, sore lips and corners of the mouth (covered under Skin Rashes and Cracked Lips); or new tingling, burning, or numbness in the hands and feet (see Nerve Symptoms). Mood plus these is a much stronger pointer than mood alone.
- There's a concrete reason to be deficient — heavy alcohol use, a medication known to deplete B6 (such as the tuberculosis drug isoniazid or the Parkinson's drug levodopa), kidney disease or dialysis, a malabsorption condition, or a markedly poor diet. These are detailed in the next section.
- Other B-vitamin or nutrient deficiencies are present — B6 rarely drops in isolation. If B12, folate, or iron are also low, the whole nutritional picture is worth correcting, and mood may be one of several things that improve.
- An unexplained anemia accompanies the mood change — because PLP is also needed to build hemoglobin, a particular type of anemia can travel with B6 deficiency (see Anemia and Seizures).
Conversely, low B6 is an unlikely explanation when someone eats a varied diet, takes a multivitamin, has no malabsorption or relevant medication, and has no physical signs of deficiency. In that very common situation, the mood symptoms deserve a proper depression evaluation — not a bottle of B6.
What Drives B6 Low Enough to Affect Mood
Vitamin B6 is widespread in the food supply — in fish, poultry, organ meats, potatoes and other starchy vegetables, chickpeas, and bananas — so deficiency severe enough to affect the brain is uncommon in well-fed people eating a varied diet. When it does occur, a specific reason is usually behind it:
- Heavy alcohol use — this is one of the most important causes. Alcohol interferes with B6 in two ways: it worsens diet, and its breakdown product, acetaldehyde, speeds the breakdown of PLP, so less PLP builds up (Lumeng & Li 1974). In that study, 35 of 66 alcoholic patients with normal liver tests had plasma PLP below the lowest level seen in 94 controls, yet the enzymes that make PLP in their red blood cells were not reduced; the acetaldehyde effect itself was shown in human red blood cells in the laboratory, where it worked through an enzyme (a phosphatase) that breaks down the active, phosphate-carrying forms of B6. Mood changes, confusion, and B6 deficiency commonly cluster in people drinking heavily.
- Medications that deplete B6 — the tuberculosis drug isoniazid is the classic example: it binds pyridoxine and inactivates PLP, which is why neuropsychiatric and neurological effects (including, in overdose, seizures) can occur, and why isoniazid is routinely co-prescribed with pyridoxine (Sankar 2024). That 2024 review explains that the drug's reactive –NH2 group “tends to react with vital endogenous molecules such as pyridoxine, leading to their deficiency, a major cause of peripheral neuropathy”; nerve damage (peripheral neuropathy) occurs in 2%–6.5% of people taking isoniazid. Other B6-lowering drugs include the Parkinson's medication levodopa, the chelating drug penicillamine, certain anti-seizure medicines, and, to a lesser degree, some older oral contraceptives.
- Kidney disease and dialysis — impaired kidney function and the dialysis process both lower B6 status, which is why supplementation is often part of dialysis care.
- Malabsorption — celiac disease, inflammatory bowel disease, and other conditions that impair absorption can lower B6 along with other nutrients.
- Poor diet and the elderly — older adults are more likely to have marginal B6 status because of smaller appetites, less varied diets, more medications, and changes in how the body handles the vitamin — and they are also the group in whom confusion and depression most need careful evaluation.
- Pregnancy — B6 requirements rise in pregnancy, and intake can fall short, though severe deficiency remains uncommon.
A key point: most of these are situations where multiple things are going wrong nutritionally at once. That is why correcting B6 in isolation, without addressing the alcohol, the medication, the kidney disease, or the overall diet, rarely solves the whole problem.
Getting Tested
Vitamin B6 status is measured with a blood test for plasma pyridoxal-5′-phosphate (PLP), the active form of the vitamin. A plasma PLP below about 20 nmol/L is generally considered inadequate (it is the cut-off below which the Merete study above found the likelihood of depression approximately doubled), and it is the most commonly used marker of B6 status. The test is not part of a routine checkup and usually has to be specifically requested, often when there's a concrete reason to suspect deficiency (the clues above) rather than for ordinary low mood.
Because B6 deficiency so rarely travels alone, the more useful approach when mood or confusion is the concern is to evaluate the whole picture, not just B6 in isolation:
- A Complete Blood Count can reveal an accompanying anemia and hint at which nutrient is involved.
- Levels of vitamin B12, folate, iron, and vitamin D are usually checked alongside B6, since these are the nutrient gaps most associated with mood and cognitive symptoms, and they frequently coexist.
- A thyroid panel is one of the highest-yield tests for anyone with new depression or mental sluggishness, because an underactive thyroid is such a common and treatable mimic.
- Because PLP is the cofactor that helps clear homocysteine, a homocysteine level may be elevated when B6 (or B12 or folate) is low, and is sometimes used as a supporting clue — the connection to thinking and memory is discussed under cognitive decline in the research below (Tucker 2005).
Just as important as the blood tests is a proper clinical assessment of the mood symptoms themselves — a depression screen, a review of medications and alcohol, and, in an older adult with new confusion, a search for infection or other acute illness. The lab tests find a contributing deficiency; the clinical assessment finds what is actually driving the symptoms.
Correcting Low B6 Safely
If testing confirms a genuine B6 deficiency, the good news is that it is straightforward to correct, and any mood or cognitive symptoms that were truly driven by the shortfall tend to improve as levels normalize. The approach follows a clear order.
- Food first. For mild or marginal deficiency in someone who is otherwise well, B6-rich whole foods are the foundation and the safest source. Good options include salmon, tuna, poultry, beef liver, potatoes and other starchy vegetables, chickpeas, and bananas. The B6 food sources page lists more. The adult Recommended Dietary Allowance is roughly 1.3–1.7 mg per day, an amount easily met by a varied diet.
- Supplements when needed. When diet alone isn't enough, or when an ongoing cause (a medication, dialysis) keeps draining B6, a clinician may recommend a supplement — often as part of a B-complex or multivitamin, since other B vitamins are commonly low too. Doses used to correct a deficiency are modest.
- The underlying cause matters. Replacing B6 without addressing why it dropped — reducing alcohol, adding pyridoxine to isoniazid therapy, managing kidney disease, treating malabsorption, improving the overall diet — only buys time.
- Depression is treated on its own merits. This is essential: if someone has clinical depression, correcting a B6 deficiency is a helpful piece of overall health, but it is not a substitute for proper treatment of the depression with therapy, medication, or both. Time spent “waiting for the vitamins to work” is time without effective treatment of the depression.
A crucial safety warning that cuts the other way. More B6 is not better, and high-dose supplements are not a harmless mood booster. Taking large amounts of B6 over time — typically from high-dose pills, not food — can cause a sensory nerve disorder (peripheral neuropathy): numbness, tingling, burning, and unsteadiness, often in the hands and feet. This is exactly the kind of harm that comes from self-treating presumed “low B6” for low mood at high doses, and it is detailed on the B6 toxicity and sensory neuropathy page.
The 2023 European safe upper limit. In 2023 the European Food Safety Authority (EFSA) called the link between too much vitamin B6 and nerve damage (peripheral neuropathy) “well established” and set the tolerable upper intake level (the most that is considered safe to take every day) at 12 mg a day for adults, including during pregnancy and breastfeeding. EFSA found that people in the European Union are unlikely to go above this limit, except regular users of food supplements containing high doses of vitamin B6 (EFSA 2023).
When to Seek Care / Red Flags
Mood and cognitive symptoms deserve attention regardless of cause, and a few patterns are ones that call for prompt medical evaluation — and some are treated as emergencies that need care right away:
- Thoughts of suicide or self-harm, or thoughts of harming someone else. This is an emergency. In the United States, immediate help is available by calling or texting 988 (the Suicide and Crisis Lifeline) or at the nearest emergency department.
- Sudden or rapidly worsening confusion — new disorientation, not knowing the date or place, seeing or hearing things that aren't there, or a marked change in alertness. Abrupt confusion (delirium), especially in an older adult, is a medical emergency and is far more often caused by infection, dehydration, medications, low blood sugar, or stroke than by any vitamin.
- Depression that is severe, persistent, or worsening — low mood that lasts more than two weeks, interferes with daily life, work, or relationships, or keeps getting worse is the pattern clinicians evaluate as possible clinical depression. In the Ford trial above, B vitamins given to older men without depression did no better than placebo at preventing depressive symptoms.
- A seizure, fainting, or severe new neurological symptoms. Severe B6 deficiency can, at its extreme, contribute to seizures (see Anemia and Seizures), but a first seizure from any cause is treated as an emergency.
- New numbness, tingling, burning, or unsteadiness — these can come from a deficiency or from too much supplemental B6; the EFSA upper limit above is based on this nerve damage (see Nerve Symptoms).
The reassuring reality is that depression and confusion are highly treatable when the real cause is found. A vitamin level is one quick, inexpensive piece of that workup — but the workup, and the care for the mood itself, are what matter most.
Key Research Papers
- Parra M, Stahl S, Hellmann H (2018). Vitamin B6 and Its Role in Cell Metabolism and Physiology. Cells;7(7):84. — DOI: 10.3390/cells7070084. — doi:10.3390/cells7070084
- Kennedy DO (2016). B Vitamins and the Brain: Mechanisms, Dose and Efficacy — A Review. Nutrients;8(2):68. — DOI: 10.3390/nu8020068. — doi:10.3390/nu8020068
- Hvas AM, Juul S, Bech P, Nexø E (2004). Vitamin B6 Level Is Associated with Symptoms of Depression. Psychotherapy and Psychosomatics;73(6):340-343. — DOI: 10.1159/000080386. — doi:10.1159/000080386
- Merete C, Falcon LM, Tucker KL (2008). Vitamin B6 Is Associated with Depressive Symptomatology in Massachusetts Elders. Journal of the American College of Nutrition;27(3):421-427. — DOI: 10.1080/07315724.2008.10719720. — doi:10.1080/07315724.2008.10719720
- Arévalo SP, Scott TM, Falcón LM, Tucker KL (2019). Vitamin B-6 and depressive symptomatology, over time, in older Latino adults. Nutritional Neuroscience;22(9):625-636. — DOI: 10.1080/1028415X.2017.1422904. — doi:10.1080/1028415X.2017.1422904
- Tucker KL, Qiao N, Scott T, Rosenberg I, Spiro A (2005). High homocysteine and low B vitamins predict cognitive decline in aging men: the Veterans Affairs Normative Aging Study. The American Journal of Clinical Nutrition;82(3):627-635. — DOI: 10.1093/ajcn/82.3.627. — doi:10.1093/ajcn/82.3.627
- Ford AH, Flicker L, Thomas J, Norman P, Jamrozik K, Almeida OP (2008). Vitamins B12, B6, and Folic Acid for Onset of Depressive Symptoms in Older Men: Results From a 2-Year Placebo-Controlled Randomized Trial. The Journal of Clinical Psychiatry;69(8):1203-1209. — DOI: 10.4088/JCP.v69n0801. — doi:10.4088/JCP.v69n0801
- Sankar J, Chauhan A, Singh R, Mahajan D (2024). Isoniazid — historical development, metabolism associated toxicity and a perspective on its pharmacological improvement. Frontiers in Pharmacology;15:1441147. — DOI: 10.3389/fphar.2024.1441147. — doi:10.3389/fphar.2024.1441147
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA), Turck D, Bohn T, Castenmiller J, et al. (2023). Scientific opinion on the tolerable upper intake level for vitamin B6. EFSA Journal;21(5):e08006. — DOI: 10.2903/j.efsa.2023.8006. — doi:10.2903/j.efsa.2023.8006
- Wu Y, Zhang L, Li S, Zhang D (2022). Associations of dietary vitamin B1, vitamin B2, vitamin B6, and vitamin B12 with the risk of depression: a systematic review and meta-analysis. Nutrition Reviews;80(3):351-366. — DOI: 10.1093/nutrit/nuab014. — doi:10.1093/nutrit/nuab014
- Field DT, Cracknell RO, Eastwood JR, Scarfe P, Williams CM, Zheng Y, Tavassoli T (2022). High-dose Vitamin B6 supplementation reduces anxiety and strengthens visual surround suppression. Human Psychopharmacology;37(6):e2852. — DOI: 10.1002/hup.2852. — doi:10.1002/hup.2852
- Lumeng L, Li TK (1974). Vitamin B6 Metabolism in Chronic Alcohol Abuse: Pyridoxal Phosphate Levels in Plasma and the Effects of Acetaldehyde on Pyridoxal Phosphate Synthesis and Degradation in Human Erythrocytes. Journal of Clinical Investigation;53(3):693-704. — DOI: 10.1172/JCI107607. — doi:10.1172/JCI107607
- Mastrangelo M, Gasparri V, Bernardi K, Foglietta S, Ramantani G, Pisani F (2023). Epilepsy Phenotypes of Vitamin B6-Dependent Diseases: An Updated Systematic Review. Children;10(3):553. — DOI: 10.3390/children10030553. — doi:10.3390/children10030553
PubMed Topic Searches
- PubMed: Vitamin B6 (pyridoxal phosphate) and depression
- PubMed: PLP and neurotransmitter synthesis (serotonin, GABA)
- PubMed: B-vitamin supplementation and depression (randomized trials)
- PubMed: B vitamins, homocysteine, and cognitive decline
- PubMed: Isoniazid, pyridoxine deficiency, and neuropsychiatric effects
Connections
- All Vitamins
- Vitamin B6 Deficiency Hub
- B6 Deficiency: Skin Rashes & Cracked Lips
- B6 Deficiency: Nerve Symptoms
- B6 Deficiency: Anemia & Seizures
- Vitamin B6 Overview
- B6 for Neurotransmitter Synthesis
- B6 Toxicity & Sensory Neuropathy
- Pyridoxine and Brain Health
- Vitamin B6 Food Sources
- Tryptophan (Serotonin Precursor)
- Glutamic Acid and Gamma-Aminobutyric Acid Production
- Vitamin B12
- Depression
- Anxiety
- Homocysteine Test
- Complete Blood Count