⚠ Evidence warning: Clinical trials or other evidence do not support the claim that pantothenic acid and pantethine are non-toxic even at gram-level doses. This page keeps it as a report of what people, websites or other media say.
Pantothenic Acid and Adrenal Function
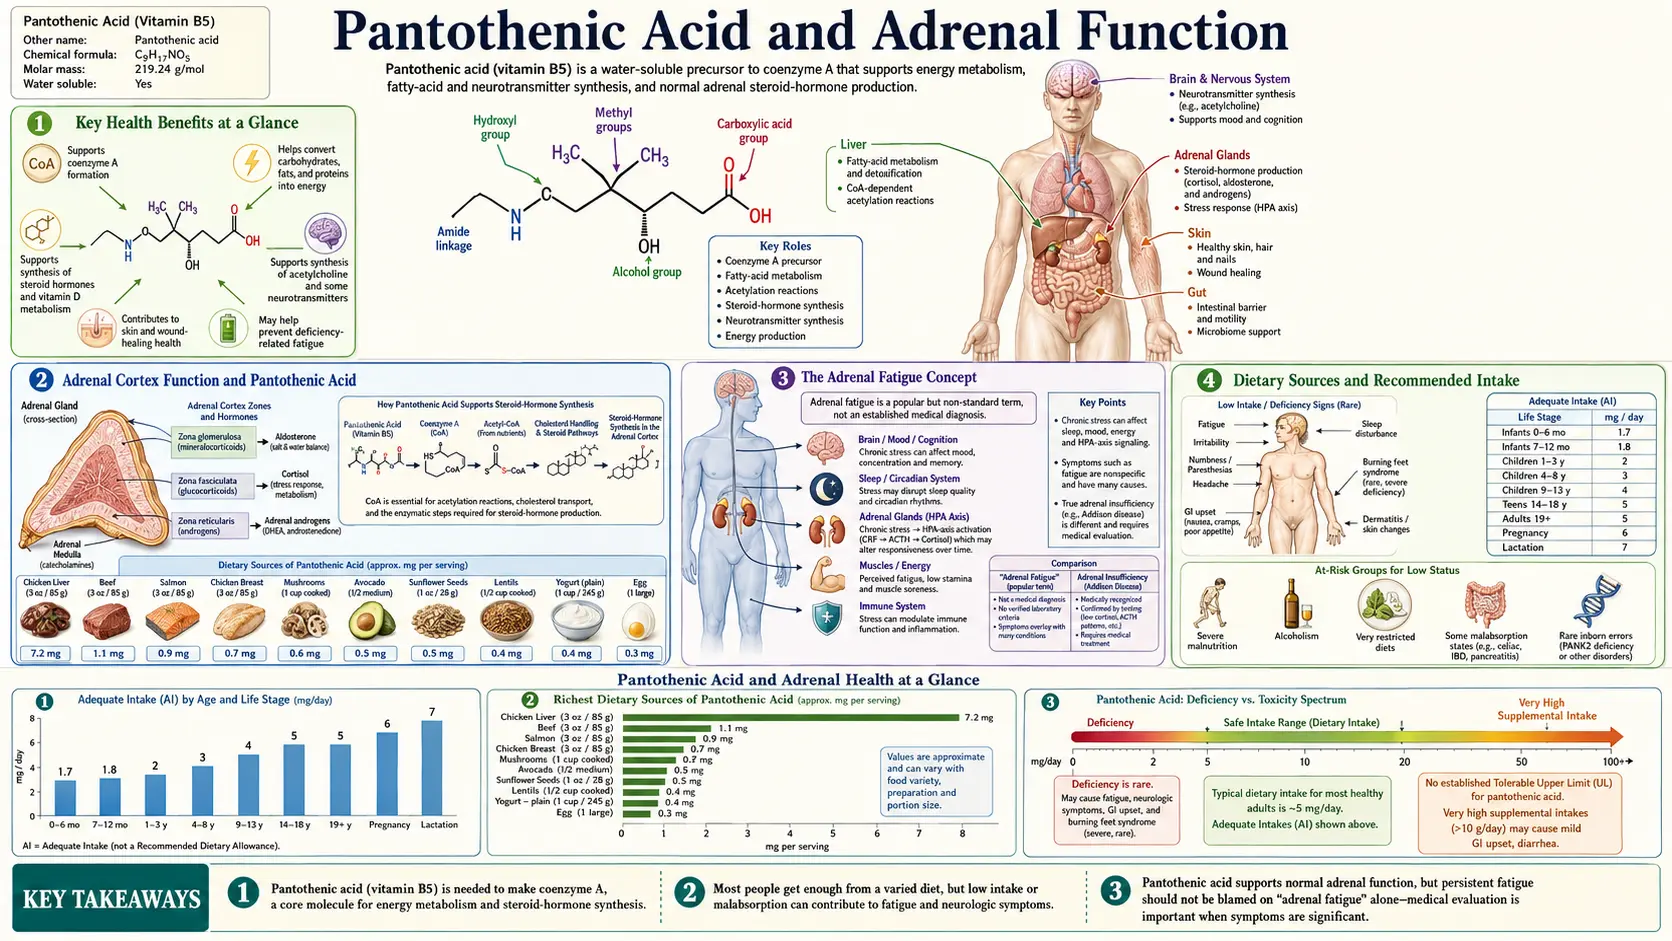
Pantothenic acid (vitamin B5) is an essential water-soluble vitamin whose name derives from the Greek word "pantos," meaning "everywhere," reflecting its widespread presence in virtually all foods. Despite its ubiquity in the diet, pantothenic acid plays a disproportionately critical role in adrenal gland function, steroid hormone synthesis, and the body's capacity to mount an appropriate stress response. The adrenal glands contain among the highest concentrations of pantothenic acid of any organ in the body, underscoring the intimate relationship between this vitamin and adrenal physiology.
Table of Contents
- Key Health Benefits at a Glance
- Coenzyme A Synthesis Pathway
- Cortisol and Steroid Hormone Production
- Adrenal Cortex Function and Pantothenic Acid
- The Stress Response and the Hypothalamic-Pituitary-Adrenal Axis
- Pantothenic Acid Depletion During Chronic Stress
- The Adrenal Fatigue Concept
- Pantethine Supplementation
- Clinical Evidence for Stress Management
- Dietary Sources and Recommended Intake
- Key Research Papers
- Connections
- Featured Videos
Key Health Benefits at a Glance
The following summarizes the evidence-backed roles of adequate pantothenic acid (vitamin B5) status, with particular emphasis on adrenal physiology and the stress response. Each bullet is expanded in the sections below and supported by research in the Key Research Papers section.
- Coenzyme A (CoA) synthesis – Pantothenic acid is the obligate precursor to CoA, a cofactor for over 100 metabolic reactions spanning the citric acid cycle, fatty acid metabolism, and steroid hormone synthesis.
- Adrenal steroidogenesis – CoA-derived acetyl groups drive the conversion of cholesterol to pregnenolone and the downstream synthesis of cortisol, aldosterone, and DHEA.
- Among the highest tissue concentrations – The adrenal cortex maintains some of the highest CoA levels in the body, reflecting the extraordinary throughput of steroidogenic reactions.
- Hypothalamic-pituitary-adrenal-axis support – CoA-dependent energy metabolism underpins CRH release, adrenocorticotropic hormone (ACTH) processing, and adrenal cortisol output.
- Stress-induced depletion – Chronic psychological or physiological stress increases CoA demand and accelerates pantothenic acid turnover.
- Lipid-modifying effects of pantethine – 600–1,200 mg/day of pantethine reduces total cholesterol and triglycerides, an effect attributed to enhanced hepatic CoA availability.
- Glutathione synthesis support – Adequate CoA is required for the antioxidant defense pathways that protect adrenal tissue from oxidative damage during cortisol output.
- Outstanding safety profile – No tolerable upper intake level (UL) has been established; pantothenic acid and pantethine are non-toxic even at gram-level doses.
- Safety profile – No tolerable upper intake level (UL) has been established. The Linus Pauling Institute lists diarrhea at very high intakes of 10 to 20 grams a day of calcium D-pantothenate as the only adverse effect noted, plus one case report of a life-threatening reaction in a woman taking vitamin B5 with biotin (see Dietary Sources and Recommended Intake).
Coenzyme A Synthesis Pathway
The primary biochemical role of pantothenic acid is as a precursor to coenzyme A (CoA), one of the most important cofactors in all of metabolism. The biosynthesis of CoA from pantothenic acid proceeds through five enzymatic steps:
- Step 1: Phosphorylation — pantothenate kinase (PanK) phosphorylates pantothenic acid to 4'-phosphopantothenate. This is the rate-limiting step in CoA synthesis and is regulated by feedback inhibition from CoA and its thioesters.
- Step 2: Cysteine conjugation — phosphopantothenoylcysteine synthetase adds a cysteine residue to form 4'-phosphopantothenoylcysteine, incorporating the sulfhydryl group that will become the business end of CoA.
- Step 3: Decarboxylation — phosphopantothenoylcysteine decarboxylase removes the carboxyl group to yield 4'-phosphopantetheine.
- Step 4: Adenylylation — phosphopantetheine adenylyltransferase adds an AMP moiety to produce dephospho-CoA.
- Step 5: Final phosphorylation — dephospho-CoA kinase adds the final phosphate group to produce coenzyme A.
CoA participates in over 100 metabolic reactions, including the citric acid cycle (via acetyl-CoA), fatty acid synthesis and oxidation, amino acid metabolism, and critically for adrenal function, the synthesis of all steroid hormones from cholesterol.
Cortisol and Steroid Hormone Production
The adrenal cortex synthesizes steroid hormones from cholesterol through a series of enzymatic reactions that are fundamentally dependent on CoA:
- Cholesterol mobilization — the initial and rate-limiting step in steroidogenesis involves the transport of cholesterol from the outer to the inner mitochondrial membrane by the steroidogenic acute regulatory protein (StAR). The cholesterol itself is delivered to the adrenal cortex via low-density lipoprotein (LDL) receptor-mediated uptake and stored as cholesteryl esters, which are formed through CoA-dependent acyltransferase reactions.
- Pregnenolone synthesis — cholesterol is converted to pregnenolone by the cytochrome P450 side-chain cleavage enzyme (CYP11A1), the common precursor to all steroid hormones.
- Cortisol production — pregnenolone is converted to cortisol through a series of hydroxylation reactions in the zona fasciculata. Each step requires adequate cofactor availability, and the acetyl groups donated by acetyl-CoA are essential for the acetylation reactions that regulate enzyme activity and protein function throughout this cascade.
- Aldosterone synthesis — the zona glomerulosa produces aldosterone, the primary mineralocorticoid, through a parallel pathway from pregnenolone.
- DHEA and androgen production — the zona reticularis produces dehydroepiandrosterone (DHEA) and androstenedione, adrenal androgens that serve as precursors for peripheral sex hormone synthesis.
Adrenal Cortex Function and Pantothenic Acid
The adrenal glands have a uniquely high demand for pantothenic acid, reflected in several observations:
- Tissue concentration — the adrenal glands maintain CoA concentrations that are among the highest in the body, second only to the liver. This high concentration reflects the enormous throughput of acetyl-CoA required for steroid hormone synthesis.
- Animal studies — classic experiments in pantothenic acid deficiency in rats demonstrated adrenal cortical atrophy, hemorrhagic necrosis of the adrenal glands, and impaired corticosterone production. These animals showed reduced ability to mount a stress response and had shortened survival under experimental stress conditions.
- Adrenal ascorbic acid depletion — pantothenic acid-deficient animals show impaired release of ascorbic acid from the adrenal glands in response to adrenocorticotropic hormone stimulation, indicating disrupted adrenal signaling cascades.
- Human implications — while frank pantothenic acid deficiency is rare in humans due to its widespread dietary availability, subclinical insufficiency during periods of high demand may compromise optimal adrenal function.
The Stress Response and the Hypothalamic-Pituitary-Adrenal Axis
The hypothalamic-pituitary-adrenal (HPA) axis is the body's central stress response system, and pantothenic acid is integral to its function at every level:
- Hypothalamic activation — stress triggers the release of corticotropin-releasing hormone (CRH) from the paraventricular nucleus of the hypothalamus. CRH synthesis and release require adequate cellular energy metabolism, which depends on CoA-mediated pathways.
- Pituitary response — CRH stimulates the anterior pituitary to release adrenocorticotropic hormone (ACTH), which is derived from the precursor molecule proopiomelanocortin (POMC). The post-translational processing of POMC involves acetylation steps that are CoA-dependent.
- Adrenal cortisol output — adrenocorticotropic hormone stimulates the adrenal cortex to synthesize and release cortisol. As described above, this entire steroidogenic cascade requires adequate CoA availability derived from pantothenic acid.
- Negative feedback — cortisol feeds back to suppress CRH and adrenocorticotropic hormone release, completing the regulatory loop. Impaired cortisol production due to CoA insufficiency could theoretically result in loss of this negative feedback, leading to chronic hypothalamic-pituitary-adrenal axis activation.
Pantothenic Acid Depletion During Chronic Stress
Chronic psychological, physical, or physiological stress places sustained demands on the adrenal glands that may deplete pantothenic acid reserves:
- Increased cortisol demand — chronic stress elevates cortisol production, increasing the throughput of CoA-dependent steroidogenic reactions and consuming pantothenic acid-derived CoA at an accelerated rate.
- Elevated energy expenditure — the heightened metabolic rate during stress increases demand for acetyl-CoA in the citric acid cycle and oxidative phosphorylation, competing with steroidogenic pathways for the available CoA pool.
- Nutrient depletion patterns — stressed individuals often adopt poor dietary habits, including increased consumption of refined foods that are low in B vitamins, creating a mismatch between increased demand and reduced intake.
- Inflammatory cytokine effects — chronic stress-induced inflammation may alter pantothenic acid metabolism and increase its catabolism, further reducing available stores.
- Clinical observations — accounts of early human deficiency experiments describe increased fatigue, irritability, and reduced tolerance to stress, symptoms reported to resolve with supplementation. The Linus Pauling Institute summary of those experiments lists headache, fatigue, insomnia, intestinal disturbances, and numbness and tingling.
The Adrenal Fatigue Concept
The term "adrenal fatigue" has been popularized in integrative and functional medicine to describe a constellation of symptoms attributed to suboptimal adrenal function under chronic stress:
- Proposed mechanism — proponents suggest that prolonged stress exhausts the adrenal glands' capacity to produce adequate cortisol, leading to persistent fatigue, brain fog, sleep disturbance, salt and sugar cravings, and poor stress tolerance.
- Conventional medical perspective — major endocrine societies do not recognize "adrenal fatigue" as a medical diagnosis. The Endocrine Society has stated that there is no scientific evidence supporting the concept that chronic stress leads to "fatigued" adrenal glands with reduced cortisol output. True adrenal insufficiency (Addison's disease) is a well-defined medical condition with distinct diagnostic criteria.
- Pantothenic acid connection — practitioners who use the adrenal fatigue framework frequently recommend pantothenic acid supplementation as part of adrenal support protocols, based on the rationale that enhanced CoA availability supports optimal steroidogenesis. While the biochemistry is plausible, rigorous clinical evidence demonstrating that pantothenic acid supplementation improves adrenal function in otherwise healthy stressed individuals is limited.
- Balanced interpretation — regardless of whether "adrenal fatigue" exists as a distinct entity, the underlying premise that chronic stress increases demand for nutrients involved in cortisol synthesis, including pantothenic acid, is biochemically sound.
- Systematic review — a 2016 systematic review titled “Adrenal fatigue does not exist” (Cadegiani and Kater) searched PubMed, MEDLINE and Cochrane up to April 2016 and found 58 studies that met its criteria. It notes that no endocrinology society recognises the condition, found mostly conflicting results, and concluded there is no substantiation that “adrenal fatigue” is an actual medical condition.
Pantethine Supplementation
Pantethine is the disulfide form of pantetheine, a CoA breakdown-and-recycling product and a direct precursor to CoA. It has attracted clinical interest for several reasons:
- Shorter route to CoA — pantethine is split into two pantetheine molecules, which pantothenate kinase phosphorylates directly to 4'-phosphopantetheine, skipping the two middle steps of CoA synthesis. It does not bypass the rate-limiting pantothenate kinase step itself, which stays under feedback control by CoA, so whether it raises cellular CoA more efficiently than pantothenic acid is unproven.
- Lipid-lowering effects — older clinical trials, mostly in high-risk patients studied in Italy and Japan and reviewed by McRae in 2005, reported that pantethine supplementation (600 to 1,200 mg daily) can reduce total cholesterol by 8 to 15 percent, low-density lipoprotein cholesterol by 10 to 20 percent, and triglycerides by 14 to 33 percent, while modestly increasing high-density lipoprotein (HDL) cholesterol. These effects are attributed to enhanced CoA availability for hepatic fatty acid oxidation and reduced cholesterol synthesis. Newer placebo-controlled trials in North America found smaller effects (below).
- Newer North American trials — the largest gave 120 people at low-to-moderate heart risk pantethine (600 mg a day for 8 weeks, then 900 mg a day) or a dummy pill for 16 weeks, on top of a cholesterol-lowering diet. Compared with the dummy pill, pantethine lowered total cholesterol by about 3%, LDL cholesterol by about 4% and apolipoprotein B by about 5%; the authors called the absolute size of these effects small (Rumberger 2011). A smaller trial of 32 people on the same doses found an 11% fall in LDL cholesterol from baseline with pantethine and a 3% rise with the dummy pill at 16 weeks (Evans 2014).
- Adrenal support — if its shorter route does raise CoA availability, pantethine may provide superior support for steroidogenesis compared to pantothenic acid alone, though direct comparative studies in adrenal function are lacking.
- Safety profile — pantethine is generally well-tolerated, with gastrointestinal discomfort being the most commonly reported side effect. It does not share the flushing side effects associated with niacin supplementation.
Clinical Evidence for Stress Management
The evidence supporting pantothenic acid's role in stress management comes from several lines of investigation:
- Human deficiency studies — Hodges and colleagues induced pantothenic acid deficiency in volunteers in the late 1950s (1958 and 1959), in one experiment by combining a deficient diet with omega-methyl pantothenic acid, a blocker of the vitamin. The Linus Pauling Institute summary lists the participants’ complaints as headache, fatigue, insomnia, intestinal disturbances, and numbness and tingling of the hands and feet; malaise, impaired antibody production and increased sensitivity to insulin are also reported from these experiments. These symptoms closely overlap with those attributed to chronic stress.
- Supplementation studies — some small clinical trials have reported that B5 supplementation (up to 1,000 mg daily) improved subjective measures of stress tolerance and reduced self-reported fatigue in high-stress populations, though these studies were generally limited by small sample sizes and lack of blinding.
- Combination formulas — pantothenic acid is a common component of B-complex and adrenal support supplements. Studies of multi-nutrient formulas containing pantothenic acid alongside vitamin C, B6, and adaptogenic herbs have shown modest improvements in stress-related outcomes, though isolating the specific contribution of pantothenic acid is difficult.
- Animal evidence — rodent studies consistently demonstrate that pantothenic acid deficiency impairs adrenal function and stress tolerance, and that repletion restores these functions. However, animal studies using deficiency models may not directly translate to supplementation above adequate levels in humans.
- Intake in practice — high-dose pantothenic acid supplementation for "adrenal support" lacks strong clinical trial evidence. The Adequate Intake (AI) for adults is 5 mg daily, and many practitioners recommend 100 to 500 mg daily during periods of stress.
Dietary Sources and Recommended Intake
- Rich dietary sources — liver and organ meats, egg yolks, sunflower seeds, mushrooms (especially shiitake), avocados, sweet potatoes, lentils, chicken breast, and yogurt.
- Adequate Intake (AI) — the Adequate Intake for adults is 5 mg per day, 6 mg per day in pregnancy and 7 mg per day when breastfeeding (Institute of Medicine figures, as listed by the Linus Pauling Institute). No tolerable upper intake level (UL) has been established. The Linus Pauling Institute describes pantothenic acid as not known to be toxic in humans; the only adverse effect it lists is diarrhea at very high intakes of 10 to 20 grams a day of calcium D-pantothenate.
- Case report — one case report describes a 76-year-old woman who had taken vitamins B5 and H (biotin) for two months and developed fluid around the heart and lungs with very high counts of eosinophils (a type of white blood cell). It was life-threatening, and she recovered after the vitamins were stopped (Debourdeau 2001). The Linus Pauling Institute gives her doses as 300 mg a day of pantothenic acid with 10 mg a day of biotin.
- Processing losses — according to the Linus Pauling Institute, processing and refining grains causes significant losses, up to 55% for wheat and up to 88% for maize, and freezing and canning foods cause similar losses. Diets high in processed foods may provide less pantothenic acid than expected.
- Historical deficiency — naturally occurring deficiency is very rare and has been seen only in severe malnutrition. World War II prisoners in the Philippines, Burma and Japan had numbness and painful burning and tingling in their feet, which pantothenic acid supplementation relieved (Linus Pauling Institute).
This content is provided for informational purposes only and does not constitute medical advice. The safety facts in brief: the Adequate Intake is 5 mg a day for adults, 6 mg in pregnancy and 7 mg when breastfeeding; very high intakes of 10 to 20 grams a day have caused diarrhea; and one case report links vitamin B5 taken with biotin to a life-threatening build-up of fluid around the heart and lungs that cleared when the vitamins were stopped.
Key Research Papers
The following are landmark and frequently cited research papers underpinning the claims on this page. Links resolve to the publisher DOI, PubMed record, or PubMed topic search.
Pantothenic Acid Biochemistry and CoA Synthesis
- Leonardi R, Zhang YM, Rock CO, Jackowski S. Coenzyme A: back in action. Progress in Lipid Research. 2005;44(2-3):125-153. PubMed PMID: 15893380
- Jackowski S, Rock CO. Regulation of coenzyme A biosynthesis. Journal of Bacteriology. 1981;148(3):926-932. (A study in the bacterium Escherichia coli, not in human tissue.) PubMed PMID: 6796563
Adrenal Steroidogenesis and CoA
- Miller WL, Auchus RJ. The molecular biology, biochemistry, and physiology of human steroidogenesis and its disorders. Endocrine Reviews. 2011;32(1):81-151. PubMed PMID: 21051590
- Pantothenic acid deficiency and adrenal cortical function — classical rodent studies. (PubMed topic search)
Pantethine and Lipid Metabolism
- Evans M, Rumberger JA, Azumano I, Napolitano JJ, Citrolo D, Kamiya T. Pantethine, a derivative of vitamin B5, favorably alters total, LDL and non-HDL cholesterol in low to moderate cardiovascular risk subjects eligible for statin therapy: a triple-blinded placebo and diet-controlled investigation. Vascular Health and Risk Management. 2014;10:89-100. PubMed PMID: 24600231
- McRae MP. Treatment of hyperlipoproteinemia with pantethine: a review and analysis of efficacy and tolerability. Nutrition Research. 2005;25(4):319-333. doi:10.1016/j.nutres.2004.12.009
- Rumberger JA, Napolitano J, Azumano I, Kamiya T, Evans M. Pantethine, a derivative of vitamin B(5) used as a nutritional supplement, favorably alters low-density lipoprotein cholesterol metabolism in low- to moderate-cardiovascular risk North American subjects: a triple-blinded placebo and diet-controlled investigation. Nutrition Research. 2011;31(8):608-615. PubMed PMID: 21925346
Human Deficiency and Stress
- Hodges RE, Ohlson MA, Bean WB. Pantothenic acid deficiency in man. Journal of Clinical Investigation. 1958;37(11):1642-1657. PubMed PMID: 13587673
- Hodges RE, Bean WB, Ohlson MA, Bleiler R. Human pantothenic acid deficiency produced by omega-methyl pantothenic acid. Journal of Clinical Investigation. 1959;38(8):1421-1425. PubMed PMID: 13673099
- Fry PC, Fox HM, Tao HG. Metabolic response to a pantothenic acid deficient diet in humans. Journal of Nutritional Science and Vitaminology. 1976;22(4):339-346. (A 63-day diet study that measured pantothenic acid in urine and blood and nitrogen balance; its abstract reports no symptoms.) PubMed PMID: 1011047
- Cadegiani FA, Kater CE. Adrenal fatigue does not exist: a systematic review. BMC Endocrine Disorders. 2016;16(1):48. PubMed PMID: 27557747
- Debourdeau PM, Djezzar S, Estival JL, Zammit CM, Richard RC, Castot AC. Life-threatening eosinophilic pleuropericardial effusion related to vitamins B5 and H. Annals of Pharmacotherapy. 2001;35(4):424-426. PubMed PMID: 11302404
External Authoritative Resources
- NIH Office of Dietary Supplements — Pantothenic Acid Fact Sheet for Health Professionals
- Linus Pauling Institute Micronutrient Information Center — Pantothenic Acid
- Harvard T.H. Chan School of Public Health — The Nutrition Source: Vitamin B5 (Pantothenic Acid)
- PubMed — Pantothenic acid and adrenal stress research