Pantethine for Cholesterol and Lipid Management
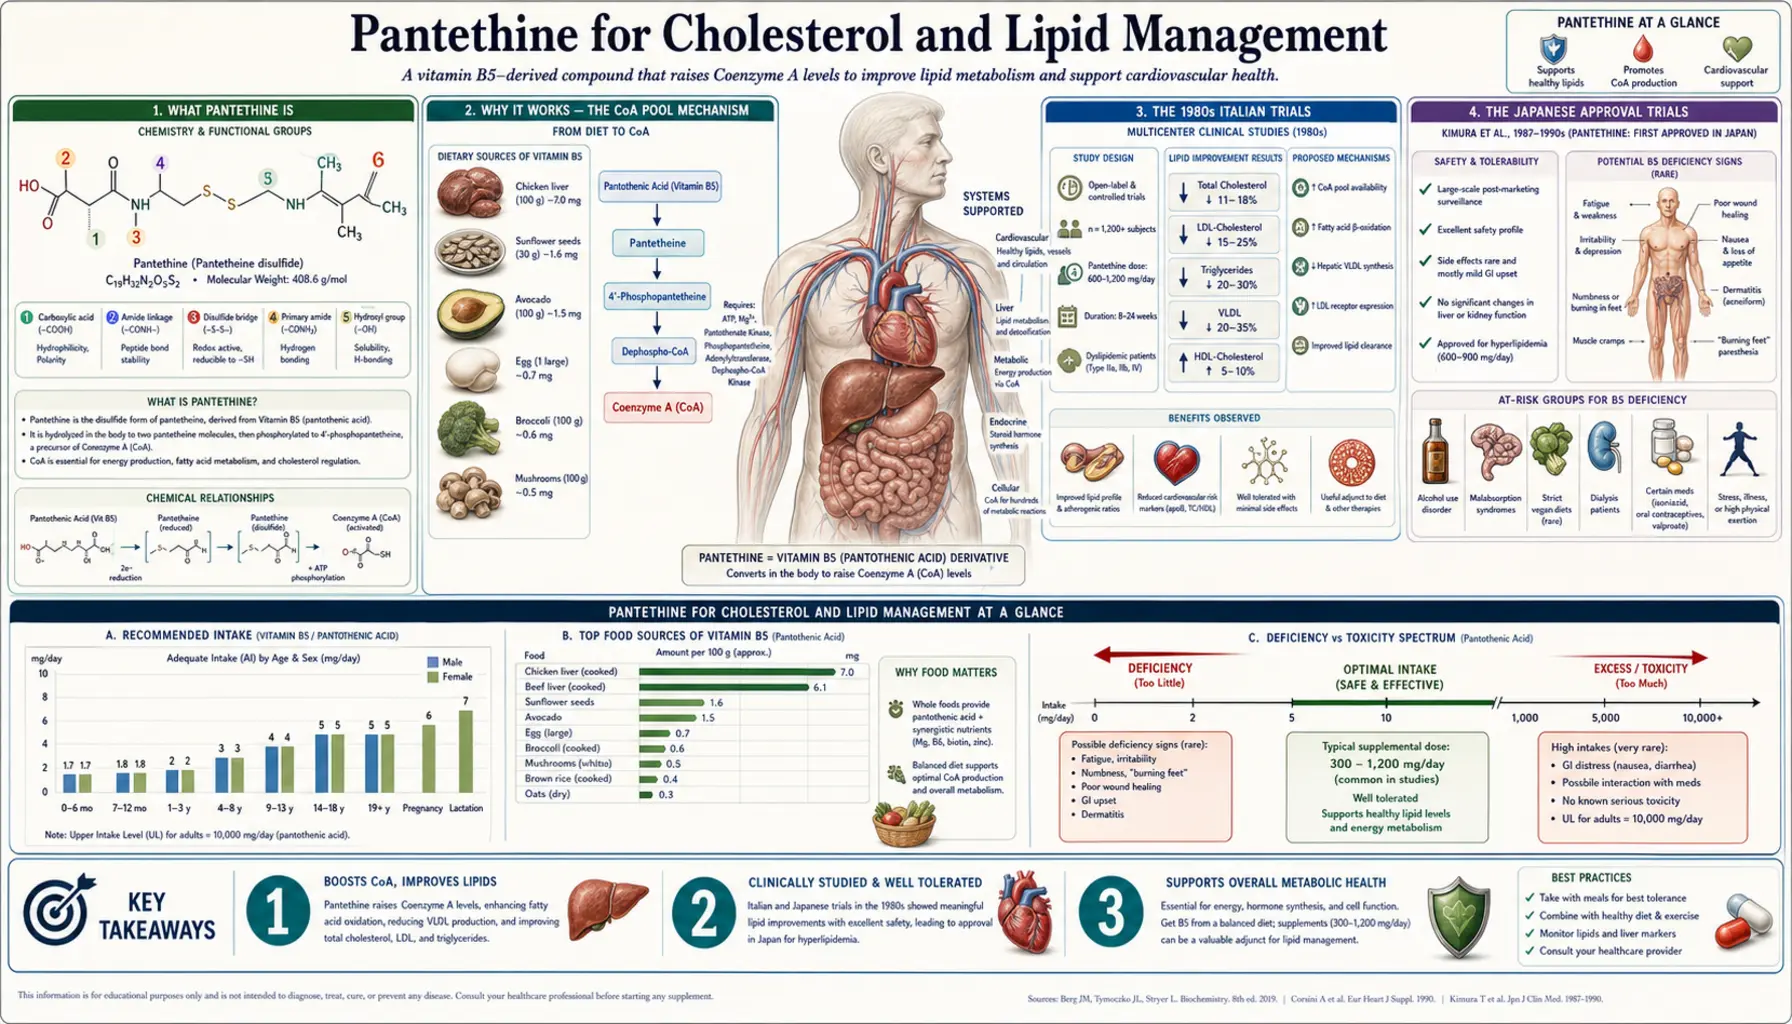
Pantethine is the disulfide dimer of pantetheine, a CoA recycling product that still enters through PANK (the rate-limiting enzyme of CoA biosynthesis) on its way to Coenzyme A: PANK phosphorylates it straight to 4'-phosphopantetheine. It does not bypass that bottleneck — it skips the two middle steps (PPCS and PPCDC) that pantothenate must also climb. Italian and Japanese clinical trials from the 1980s reported that 900-1,200 mg/day of pantethine in divided doses lowered total cholesterol and low-density lipoprotein (LDL) — by 13.5% in the type IIB patients of a 1984 Italian double-blind trial, where high-density lipoprotein (HDL) also rose about 10% — and lowered triglycerides. The later American trial of 120 people at low-to-moderate risk (Rumberger 2011) found smaller reductions against placebo: 3% for total cholesterol, 4% for LDL and 5% for apolipoprotein B. The effect is smaller than statins (which typically achieve 30-55% low-density lipoprotein reduction at standard doses) but the safety profile is exceptional — no myopathy, no hepatotoxicity signal, no glycemic disturbance. Pantethine sits in modern lipidology as an adjunct or a niche alternative for statin-intolerant patients and patients with mild lipid abnormalities, not as a first-line therapy. This page walks through the trial data, the mechanism, the practical protocols, the head-to-head comparison with statins, and where pantethine reasonably fits in contemporary cardiovascular risk management.
Table of Contents
- What Pantethine Is
- Why It Works — The CoA Pool Mechanism
- The 1980s Italian Trials
- The Japanese Approval Trials
- Rumberger 2011 — The Modern US RCT
- Pooled Effect Sizes Summary
- Pantethine vs Statins
- Doses and Combinations Used
- Who Practitioners Describe Benefiting Most
- Where Pantethine Fits in Modern Lipidology
- Patient FAQ
- Cautions
- Key Research Papers
- Connections
- Featured Videos
What Pantethine Is
Pantethine is a stable, orally absorbable form of pantetheine — specifically, two molecules of pantetheine joined by a disulfide bond between their cysteamine-derived thiol groups. The molecule is two biosynthetic steps closer to Coenzyme A than pantothenic acid itself — not because it skips PANK, but because PANK turns it directly into 4'-phosphopantetheine. The chemistry, schematically:
- Pantothenate (Vitamin B5) →
[PANK phosphorylates] → 4'-phosphopantothenate →
[PPCS attaches cysteine] → 4'-phosphopantothenoylcysteine →
[PPCDC decarboxylates] → 4'-phosphopantetheine →
[COASY adenylylates] → dephospho-CoA →
[COASY phosphorylates] → Coenzyme A
Pantetheine is not itself a step of the main pathway — it is the dephosphorylated form of 4'-phosphopantetheine (the product of the PPCDC step), formed when CoA is degraded and the phosphate is removed before the molecule is recycled back to pantothenate or to CoA again. In supplement form, two pantetheines are joined as a disulfide for chemical stability (pantetheine alone is unstable in air because the free thiol oxidizes; the disulfide is stable). The disulfide is rapidly reduced to two pantetheine molecules in the body, where pantothenate kinase (PANK) phosphorylates each one directly to 4'-phosphopantetheine, which COASY then completes to CoA — skipping the PPCS and PPCDC steps, but not PANK itself.
Key point: pantethine does not bypass the PANK rate-limiting step — PANK binds and phosphorylates pantetheine as it does pantothenate, and the feedback inhibition of PANK by CoA and acetyl-CoA still applies. What it skips are the two middle steps, PPCS and PPCDC. (The compound that genuinely bypasses PANK is 4'-phosphopantetheine itself, which cells can finish into CoA with COASY alone.) Pantethine still produces clinical effects (most notably on lipid metabolism) that pantothenate itself does not produce at comparable doses, but the shorter route is not by itself a proven explanation. The same total nutritional contribution to CoA biosynthesis, entering two steps later through the same regulated gate, has different functional consequences.
Why It Works — The CoA Pool Mechanism
The accepted mechanistic hypothesis for pantethine's lipid-modifying effect: pantethine expands the cellular pool of free CoA (and especially of mitochondrial CoA), which produces two downstream consequences on lipid metabolism:
1. HMG-CoA Reductase Regulation
HMG-CoA reductase is the rate-limiting enzyme of cholesterol biosynthesis — the same enzyme statin drugs inhibit. The enzyme is allosterically regulated by the CoA pool: free CoA inhibits, while elevated upstream substrate (HMG-CoA) activates. By expanding the free CoA pool, pantethine produces a modest reduction in HMG-CoA reductase activity, lowering hepatic cholesterol synthesis. The magnitude of the inhibition is far smaller than statin-mediated inhibition (statins are potent direct inhibitors at the catalytic site; pantethine produces gentle allosteric modulation), which is offered as the reason pantethine's reported low-density lipoprotein-lowering effect (13.5% in the 1984 Italian trial's type IIB patients, 4% against placebo in the 2011 American trial) is far smaller than statins' 30-50%.
2. Enhanced Fatty Acid β-Oxidation
Fatty acid β-oxidation in mitochondria depends on a steady supply of free CoA at the start of each round of chain shortening. When the mitochondrial CoA pool is expanded by pantethine supplementation, the rate-limiting step of long-chain fatty acid oxidation is relieved, and the cell oxidizes fatty acids more efficiently. The clinical consequence is a reduction in triglyceride synthesis (less substrate available for storage) and an elevation in high-density lipoprotein (the lipoprotein that carries cholesterol from peripheral tissues back to liver, partly driven by improved fatty acid handling).
The combination of reduced cholesterol synthesis + enhanced fatty acid oxidation produces the characteristic pantethine lipid profile change: low-density lipoprotein down, total cholesterol down, triglycerides down significantly, high-density lipoprotein up modestly. This is roughly the same pattern as fibrates produce (gemfibrozil, fenofibrate) but driven by different molecular targets.
Other Proposed Effects
- Reduced lipid peroxidation. Pantethine's thiol chemistry (free or as the disulfide) provides modest antioxidant activity that may reduce oxidative modification of low-density lipoprotein particles, the proximate event in atherogenesis.
- Reduced platelet aggregation. Some early studies reported reduced platelet aggregation on pantethine, which would be cardiovascular-protective independent of the lipid effect.
- Reduced fatty liver. Multiple animal studies and some human studies show pantethine reduces hepatic steatosis — consistent with the enhanced fatty acid oxidation mechanism.
The 1980s Italian Trials
Pantethine's lipid-lowering effect was first established in a series of Italian clinical trials in the 1980s, primarily at the University of Bologna and various centers across northern Italy. The Italian government approved pantethine as a prescription lipid-modifying agent in 1979, which is why so much of the early literature comes from Italian-language journals.
Gaddi et al. (1984)
One of the foundational trials: a double-blind, 8-week comparison of pantethine (300 mg three times a day, 900 mg/day) with placebo in 29 patients — 11 with type IIB hyperlipoproteinemia, 15 with type IV and 3 with only a low high-density lipoprotein level. In the type IIB patients, total and low-density lipoprotein cholesterol both fell 13.5% and high-density lipoprotein rose about 10%. Triglycerides fell around 30% in type IIB and type IV patients when pantethine was given first (17.8% and 13.0% when placebo came first). Cholesterol returned quickly to its starting level when patients switched from pantethine to placebo.
Bertolini et al. (1986)
Pantethine 900-1,200 mg daily for 3 to 6 months in 7 children and 65 adults with high cholesterol, alone or with high triglycerides (types IIa and IIb). Total cholesterol, low-density lipoprotein cholesterol, triglycerides and apolipoprotein B fell significantly, and high-density lipoprotein (especially the HDL2 fraction) and apolipoprotein A-I rose.
Arsenio et al. (1986)
A one-year trial in 24 patients with type IIA, IIB and IV dyslipidemia, some of them also with diabetes. Blood lipids measured at 1, 3, 6, 9 and 12 months showed significant reductions in total cholesterol, low-density lipoprotein cholesterol and apolipoprotein B, with rises in high-density lipoprotein and apolipoprotein A. Results were equally good in patients with and without diabetes, and no side effects were detected.
Tonutti et al. (1991)
A 6-month comparison in 27 people with diabetes and dyslipidemia — relevant given that diabetic dyslipidemia (high triglycerides, low high-density lipoprotein, small dense low-density lipoprotein particles) is the lipid pattern most associated with cardiovascular risk in the post-statin era. The three groups received pantethine 600 mg/day, acipimox 500 mg/day or bezafibrate 600 mg/day. Pantethine lowered triglycerides by 37.7%; bezafibrate produced the broadest lipid changes.
The Italian trial body, taken collectively, established 600-1,200 mg/day pantethine as a clinically meaningful lipid-modifying intervention. The trials were generally small (typically 20-60 patients each), open-label or single-blind, often industry-sponsored, and predated modern reporting standards — but they were consistent in direction and effect size, and they were the basis on which European regulators approved pantethine as a prescription cardiovascular agent.
The Japanese Approval Trials
Pantethine has a longer and stronger clinical history in Japan than in Western countries. The original development was actually done by Japanese pharmaceutical research in the 1950s-60s — pantethine reached the Japanese market as a prescription drug for dyslipidemia, hepatic steatosis, and related metabolic conditions decades before its Italian re-emergence.
Key Japanese trials and observations:
- Multiple multi-center trials in the 1960s-70s established pantethine's safety and efficacy for hyperlipidemia in Japanese populations
- Studies in alcoholic fatty liver showed pantethine reduced hepatic triglyceride content
- Use in diabetic dyslipidemia was particularly well-studied
- Pantethine remains an approved pharmaceutical in Japan with a long-established safety record — one of the few "natural" molecules that achieved formal Japanese drug approval rather than supplement status
The cross-cultural validation matters: the Italian and Japanese trials independently confirmed similar effect sizes (10-15% low-density lipoprotein reduction, 15-25% TG reduction, ~10% high-density lipoprotein elevation) in different populations and different research traditions. This raises the confidence that the effect is real and reproducible, even though individual trials are small by modern statin-trial standards.
Rumberger 2011 — The Modern US RCT
The most methodologically rigorous modern trial of pantethine in a Western population was Rumberger et al., published in Nutrition Research in 2011; a separate, smaller trial by the same group followed in 2014 (Evans et al.).
Study design:
- 120 North American subjects at low-to-moderate cardiovascular risk (60 per group)
- Randomized, triple-blinded, placebo-controlled
- Pantethine 600 mg/day for weeks 1-8, then 900 mg/day for weeks 9-16, vs placebo
- 16-week treatment period
- Participants started a TLC (Therapeutic Lifestyle Changes) diet 4 weeks before randomization and kept to it throughout
Results:
- Total cholesterol reduced by 3% (6 mg/dL) vs placebo
- Low-density lipoprotein cholesterol reduced by 4% (4 mg/dL) vs placebo
- Apolipoprotein B reduced by 5% (4 mg/dL) vs placebo; the authors described the absolute size of these effects as small
- High-density lipoprotein changes were modest and not significantly different from placebo
- Triglyceride changes were modest in this low-baseline-TG population (the effect is larger when baseline TG is elevated)
- Safety profile was excellent — no significant adverse events, no myopathy signal, no liver function changes
The separate 2014 trial (Evans, Rumberger and colleagues) randomized 32 people at low-to-moderate risk who were eligible for statin therapy, with the same triple-blinded design and dose schedule. Low-density lipoprotein fell 11% from baseline on pantethine at weeks 4, 8, 12 and 16, while the placebo group showed a 3% increase at week 16; total cholesterol and non-HDL cholesterol were also significantly lower than placebo by week 16. Several of its authors were staff of pantethine ingredient manufacturers.
Rumberger 2011 tested whether the older Italian and Japanese results would hold in a low-to-moderate-risk American population using contemporary research standards. The direction was the same, but the reductions against placebo (3-4%) were much smaller than the Italian trials reported, in people who were already on a diet. This was the trial that brought pantethine into modern American integrative-cardiology practice.
Pooled Effect Sizes Summary
| Lipid Parameter | Expected Change (600-900 mg/day pantethine, 4-6 months) |
|---|---|
| Total cholesterol | −10 to −15% |
| Low-density lipoprotein cholesterol | −10 to −15% |
| High-density lipoprotein cholesterol | +5 to +10% |
| Triglycerides | −15 to −25% (larger effect at higher baseline) |
| Apolipoprotein B | −8 to −12% |
| Time to maximal effect | 4-6 months |
| Effect persists with continued use | Yes (no tachyphylaxis) |
| Effect reverses on discontinuation | Yes — typically within 2-4 weeks |
Pantethine vs Statins
| Aspect | Pantethine | Atorvastatin / Rosuvastatin |
|---|---|---|
| Low-density lipoprotein reduction | 10-15% | 30-55% |
| Triglyceride reduction | 15-25% (better at higher baseline) | 10-25% |
| High-density lipoprotein change | +5 to +10% | +5 to +10% |
| CV outcome data | None — no hard endpoint trials | Extensive — mortality, myocardial infarction (MI), stroke reductions in large randomized controlled trials (RCTs) |
| Myopathy risk | None documented | ~5% mild, ~0.1% severe (rhabdomyolysis very rare) |
| Hepatotoxicity | None documented | Rare LFT elevations |
| Glycemic effect | Neutral or modestly favorable | Small increase in diabetes incidence (well-documented but small effect) |
| Coenzyme Q10 (CoQ10) depletion | No — pantethine actually supports mitochondrial function | Yes — statins reduce endogenous coenzyme Q10 (clinical significance debated) |
| Cost (US, monthly) | $25-50 | $5-15 (generic) |
| Insurance coverage (US) | Not covered — over-the-counter (OTC) supplement | Generally covered |
The clinical bottom line: pantethine's low-density lipoprotein-lowering effect is about one-third the magnitude of moderate-intensity statin therapy. For patients at high cardiovascular risk who need substantial low-density lipoprotein reduction (post-MI, diabetic with established coronary heart disease (CHD), familial hypercholesterolemia), pantethine alone falls short of that reduction, and statins carry an established mortality benefit in those populations. For patients at low-to-moderate risk who want modest low-density lipoprotein reduction without statins, who are statin-intolerant, or who are in primary prevention with a borderline risk profile, pantethine is one of the options used.
The biggest functional difference between pantethine and statins is not the effect size on low-density lipoprotein — it's the absence of hard cardiovascular outcome trials for pantethine. Statins have repeatedly demonstrated reductions in myocardial infarction (MI), stroke, and mortality across multiple populations. Pantethine has only shown lipid-level changes; no trial has been powered to detect a cardiovascular event reduction. Whether the lipid changes pantethine produces translate proportionally into clinical outcomes is a reasonable hypothesis but not proven.
Doses and Combinations Used
The pantethine doses below are the ones the trials used; the combinations with other supplements are those described in practice.
Standard protocol (mild-moderate dyslipidemia)
- Pantethine 300 mg three times daily (900 mg/day total) — the dose in the 1984 Italian trial (Gaddi)
- OR Pantethine 600 mg/day for 8 weeks, then 900 mg/day for weeks 9-16 — the schedule in the two US trials (Rumberger 2011, Evans 2014)
- Commonly taken with meals
- In the US trials, a TLC diet throughout (reduced saturated fat, increased fiber, weight management)
- The US trials repeated the lipid panel during treatment (weeks 4, 8, 12 and 16 in Evans 2014); the summary table above puts the full effect at 4-6 months
Triglyceride-focused protocol
- Pantethine 600-900 mg/day in divided doses
- Combined in practice with omega-3 (eicosapentaenoic acid (EPA)+docosahexaenoic acid (DHA)) 2-3 g/day — described as the strongest natural triglyceride-lowering combination
- Berberine 500 mg twice daily is described as further reducing TG and low-density lipoprotein through a complementary mechanism
- Strong carbohydrate reduction, which practitioners describe as the most effective intervention for elevated TG
Statin-intolerant patient protocol
- Pantethine 600 mg/day
- Plant sterols (1.5-2 g/day) — additive low-density lipoprotein-lowering through reduced cholesterol absorption
- Red yeast rice (1.2-2.4 g/day standardized to monacolin K) — a natural source of monacolin K (chemically identical to lovastatin); described for mild cases only, since it carries some of the same myopathy risk as pharmaceutical statins
- Berberine 500 mg twice daily
- Bergamot extract (500-1000 mg/day standardized to flavonoids) — another complementary lipid-lowering compound
Combination with statin (lower statin dose)
- Practitioners describe some patients on a statin lowering the statin dose after adding pantethine 600 mg/day, with similar lipid control, less statin exposure and lower myopathy risk
- This is an off-label combination used in practice; no interactions between pantethine and statins are documented (see Cautions).
Forms: the US trials used a standardized pantethine ingredient. Supplements sell pantethine in 300 mg or 450 mg capsules. Pantethine is a different compound from pantothenic acid (plain vitamin B5), and labels state which of the two a product contains.
Who Practitioners Describe Benefiting Most
Practitioners describe the most clinically meaningful benefit in:
- Mild-to-moderate hypercholesterolemia (low-density lipoprotein 130-190 mg/dL) where a 10-15% reduction is enough to bring low-density lipoprotein to target without statin therapy
- Mixed dyslipidemia with high triglycerides — the TG-lowering effect is largest when baseline TG is >150 mg/dL. Patients with TG 200-500 mg/dL often see meaningful reductions.
- Metabolic syndrome lipid phenotype (high TG, low high-density lipoprotein, small dense low-density lipoprotein) — pantethine addresses all three abnormalities
- Diabetic dyslipidemia — pantethine improves lipids without adversely affecting glucose control, and may modestly improve fatty liver
- Statin-intolerant patients who have stopped a statin because of muscle symptoms or other side effects but still need lipid management
- Patients in primary prevention with borderline risk who want to avoid pharmaceutical therapy if possible
- Patients with non-alcoholic fatty liver disease (NAFLD) — the mitochondrial fatty acid oxidation effect addresses the underlying pathology
The reductions reported for pantethine fall short of what is needed in:
- Patients with established cardiovascular disease (post-MI, post-stroke, established coronary heart disease) who need maximal low-density lipoprotein reduction
- Familial hypercholesterolemia (heterozygous or homozygous), which requires substantial low-density lipoprotein reduction beyond what pantethine achieves
- Patients with very high baseline low-density lipoprotein (>190 mg/dL) without other intervention
- Acute lipid management post-cardiac event — the clinical benefit of statins in this setting is too well-established and too large to forgo for a smaller alternative
Where Pantethine Fits in Modern Lipidology
Pantethine occupies a specific and reasonable niche in contemporary cardiovascular risk management:
- Adjunct to lifestyle in primary prevention. The first-line intervention for elevated lipids in primary prevention remains diet, exercise, weight management, and addressing metabolic factors. Pantethine sits as a low-risk pharmacologic adjunct for patients who have done the lifestyle work but still have lipid abnormalities that would benefit from further reduction.
- Alternative for statin-intolerant patients. The roughly 5-10% of patients who cannot tolerate any statin (true statin myopathy, severe statin-associated muscle symptoms) need alternative lipid management. Ezetimibe, PCSK9 inhibitors, and bempedoic acid are pharmacologic options; pantethine is used as an adjunct or alternative in mild cases.
- Combination therapy. Some patients are well-controlled on a low-dose statin + pantethine combination who would otherwise need higher statin doses. This reduces statin exposure and may reduce side effects.
- Triglyceride-dominant phenotype. The TG-lowering effect is one of pantethine's strongest, particularly relevant in metabolic-syndrome populations where the lipid abnormality is dominated by TG and small dense low-density lipoprotein rather than absolute low-density lipoprotein elevation.
- Non-alcoholic fatty liver disease adjunct. The mitochondrial fatty acid oxidation effect that drives the lipid changes also addresses hepatic steatosis. Pantethine has a long Japanese clinical history specifically for fatty liver disease.
What pantethine is not: a replacement for statins in established cardiovascular disease, a "natural alternative" that has equivalent outcomes data to statins, or a sufficient intervention for severe dyslipidemia. In established cardiovascular disease, statins carry outcome evidence that pantethine does not have.
Patient FAQ
Pantethine in place of a statin
This depends on cardiovascular risk. In established coronary artery disease, or after a heart attack (MI) or stroke, a statin does more than lower low-density lipoprotein — it reduces the risk of another event, with strong outcome trial evidence, while pantethine has no outcome trials at all. In primary prevention with mild lipid elevation and no established disease, practitioners describe trying pantethine with lifestyle changes and re-checking in 4-6 months.
How long results take
In the 2014 US trial, low-density lipoprotein was already 11% below baseline at week 4 and stayed there through week 16. The summary table above puts the full effect at 4-6 months. Practitioners describe re-checking labs at about 12 weeks, and describe a response that shows no movement by then as likely to stay limited.
Pantethine and statin-type "muscle aches"
No. Pantethine has no documented myopathy or muscle-symptom signal across all the trials. The mechanism is completely different from statins.
The 600 mg and 900 mg doses
The trials used different doses: 900 mg/day (300 mg three times a day) in Gaddi 1984, 900-1,200 mg/day in Bertolini 1986, 600 mg/day in Tonutti 1991, and 600 mg/day for 8 weeks then 900 mg/day in the two US trials. None of these trials compared two doses head to head. In practice the daily amount is split into 300 mg twice daily or 200 mg three times daily.
Pantethine together with a statin
No significant interactions are documented. The combination is sometimes used to reach target lipid levels with a lower statin dose.
Red yeast rice and other natural alternatives
Red yeast rice contains monacolin K, which is chemically identical to lovastatin — effectively a "natural statin." It has the same potential for myopathy, hepatotoxicity, and drug interactions as pharmaceutical statins, just at typically lower doses. Red yeast rice taken with a prescription statin amounts to a double statin dose. Pantethine is mechanistically different and combines safely with all the statin-pathway interventions.
Pantethine and blood sugar
No adverse effect; possibly mildly favorable in diabetic populations. Pantethine does not have the small diabetes-incidence increase seen with statins.
Cautions
- Statins in established cardiovascular disease. After a myocardial infarction (heart attack) or stroke, or with established coronary artery disease (CAD), a statin prevents another event with strong evidence. Pantethine has no outcome trial data and has not been tested as a replacement for statin therapy in this setting.
- Gastrointestinal (GI) side effects. Mild loose stools or stomach upset can occur, particularly when starting. Taking it with food and splitting the dose across the day are the usual ways people describe easing this.
- Mild thiol odor. Some patients notice a faint sulfurous odor in breath or urine on pantethine — this is the disulfide chemistry and is harmless.
- Pregnancy and lactation. Limited safety data at pharmacologic doses; safety in pregnancy and breastfeeding has not been established.
- Drug interactions. No significant interactions documented, including with statins, ezetimibe, fibrates, PCSK9 inhibitors, bempedoic acid, niacin, omega-3, plant sterols.
- Response varies. Not everyone responds; a lipid panel at about 12 weeks is how practitioners describe telling whether it is working.
- Lifestyle remains the base. Pantethine is described as working best as part of a comprehensive lifestyle approach (diet, exercise, weight management, sleep); both US trials tested it on top of a diet.
- Biotin competition. Like pantothenate, pantethine shares the SMVT transporter with biotin. Long-term high-dose use may modestly reduce biotin absorption; practitioners describe adding 300-500 µg biotin daily for use beyond 6 months.
Key Research Papers
- Gaddi A, Descovich GC, Noseda G et al. (1984). Controlled evaluation of pantethine, a natural hypolipidemic compound, in patients with different forms of hyperlipoproteinemia. Atherosclerosis. — PubMed PMID: 6365107
- Bertolini S, Donati C, Elicio N et al. (1986). Lipoprotein changes induced by pantethine in hyperlipoproteinemic patients: adults and children. International Journal of Clinical Pharmacology, Therapy, and Toxicology. — PubMed PMID: 3098691
- Arsenio L, Bodria P, Magnati G, Strata A, Trovato R (1986). Effectiveness of long-term treatment with pantethine in patients with dyslipidemia. Clinical Therapeutics. — PubMed PMID: 3094958
- Rumberger JA, Napolitano J, Azumano I, Kamiya T, Evans M (2011). Pantethine, a derivative of vitamin B(5) used as a nutritional supplement, favorably alters low-density lipoprotein cholesterol metabolism in low- to moderate-cardiovascular risk North American subjects: a triple-blinded placebo and diet-controlled investigation. Nutrition Research. — PubMed PMID: 21925346
- Evans M, Rumberger JA, Azumano I, Napolitano JJ, Citrolo D, Kamiya T (2014). Pantethine, a derivative of vitamin B5, favorably alters total, LDL and non-HDL cholesterol in low to moderate cardiovascular risk subjects eligible for statin therapy: a triple-blinded placebo and diet-controlled investigation. Vascular Health and Risk Management. — PubMed PMID: 24600231
- Coronel F, Tornero F, Torrente J et al. (1991). Treatment of hyperlipemia in diabetic patients on dialysis with a physiological substance. American Journal of Nephrology. — PubMed PMID: 2048576
- Carrara P, Matturri L, Galbussera M, Lovati MR, Franceschini G, Sirtori CR (1984). Pantethine reduces plasma cholesterol and the severity of arterial lesions in experimental hypercholesterolemic rabbits. Atherosclerosis. — PubMed PMID: 6442152
- Tonutti L, Taboga C, Noacco C (1991). Comparison of the efficacy of pantethine, acipimox, and bezafibrate on plasma lipids and index of cardiovascular risk in diabetics with dyslipidemia [article in Italian]. Minerva Medica. — PubMed PMID: 1745376
- Pins JJ, Keenan JM (2006). Dietary and nutraceutical options for managing the hypertriglyceridemic patient. Progress in Cardiovascular Nursing. — PubMed PMID: 16760691
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B5 Overview
- B5 Benefits Hub
- CoA Biosynthesis
- Adrenal Support
- Acne & Skin
- Cholesterol
- Cardiology
- Metabolic Syndrome
- Diabetes
- Non-Alcoholic Fatty Liver Disease (Fatty Liver)
- Lipid Panel
- Apolipoprotein B
- Low-Density Lipoprotein Particle Number
- Berberine
- Coenzyme Q10
- Deficiency
- Toxicity
- History
- Sources