⚠ Evidence warning: Clinical trials or other evidence do not support the claim that niacin is a medication that helps, so that a harmless flush need not scare anyone off it. This page keeps it as a report of what people, websites or other media say.
Niacin (Vitamin B3) Toxicity: Skin Flushing
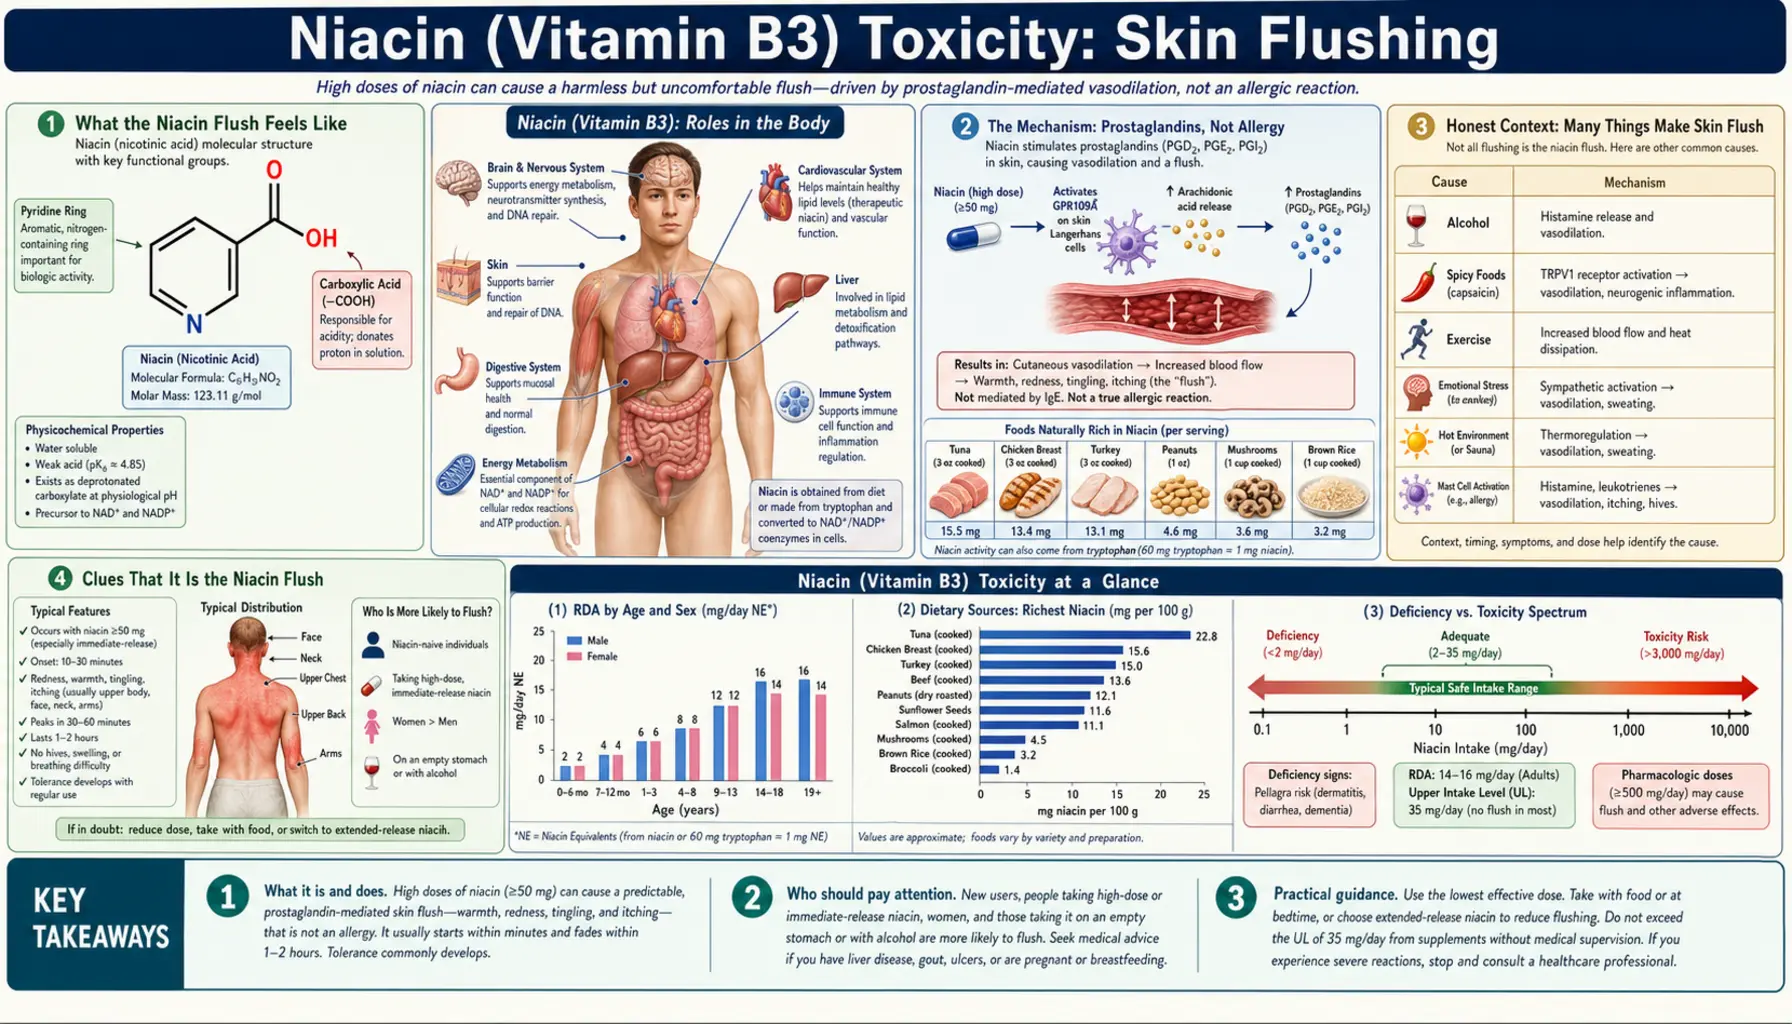
Within minutes of swallowing a dose of nicotinic acid — the form of vitamin B3 used to treat cholesterol — the skin of the face, neck, and chest can suddenly turn hot and red, prickle and tingle, and itch. This is the famous niacin flush, and it can be startling enough to feel like an allergic reaction or even a heart problem. Here is the reassuring truth: in almost every case the flush is harmless and self-limiting, fading on its own within an hour as the body clears the dose. It is not an allergy, not a sign of overdose damage, and not dangerous in itself — just genuinely uncomfortable, and the single most common reason people quit niacin. The good news is that it is also one of the most manageable side effects in all of medicine: aspirin beforehand, taking the dose with food, starting low and building up slowly, and choosing the right form of B3 can shrink the flush dramatically. This page explains exactly what causes it, why it happens so fast, what reduces it, and the rare circumstances in which redness of the skin means something else.
Table of Contents
- What the Niacin Flush Feels Like
- The Mechanism: Prostaglandins, Not Allergy
- Honest Context: Many Things Make Skin Flush
- Clues That It Is the Niacin Flush
- Which Form and Dose Causes It
- What Reduces the Flush
- Getting Checked
- If a Flush Is Happening Now
- Red Flags: Signs Hospitals Treat as Urgent
- Key Research Papers
- Connections
- Featured Videos
What the Niacin Flush Feels Like
The niacin flush has such a consistent shape that, once you have felt it, it is hard to mistake. It usually begins 15 to 30 minutes after a dose of immediate-release nicotinic acid — sometimes sooner — and unfolds in a recognizable order:
- It starts at the top and spreads down. The warmth and redness typically appear first on the face and ears, then move down the neck and onto the upper chest. The hands and the rest of the body are usually spared, though a strong flush can reach the arms and trunk.
- Heat and visible redness. The skin feels hot, looks pink to deep red, and may feel as if it is “burning” or sunburned. People often describe a sudden, all-over warm rush.
- Tingling and itching. Alongside the warmth comes a prickling, tingling sensation and, very commonly, an itch — the itch is often the most bothersome part, and it can be intense.
- It builds, peaks, and fades. The sensation tends to peak within roughly 30 to 45 minutes and then subsides on its own. A typical flush is over within about an hour to ninety minutes; it does not require treatment to stop.
Some people also notice a few minutes of lightheadedness, a faster heartbeat, or mild sweating during a strong flush — the same blood vessels widening in the skin can cause a small, temporary dip in blood pressure. None of this is the flush being “dangerous”; it is the expected consequence of many small skin blood vessels opening at once.
What the flush is not is just as important. It is not hives (raised, migrating welts), it is not swelling of the lips or tongue, and it does not cause wheezing or trouble breathing. Those would point to a true allergic reaction, which is an entirely different and far rarer event — covered in the red-flags section below.
The Mechanism: Prostaglandins, Not Allergy
The most useful thing to understand about the niacin flush is that it is not an allergic reaction at all. It is a predictable, dose-related chemical event that follows a clear chain — and knowing the chain explains exactly why the standard remedies work.
When nicotinic acid is absorbed, it activates a specific receptor on the surface of certain skin cells called GPR109A (also known by its older names HM74A and PUMA-G). This is the same receptor through which niacin affects fat tissue, but in the skin it is found on immune cells in the upper layers — particularly the Langerhans cells. Activating GPR109A on these cells triggers them to manufacture and release a signaling lipid called prostaglandin D2 (PGD2), with a contribution from prostaglandin E2 (PGE2) as well.
Prostaglandin D2 is a potent vasodilator: it makes the small blood vessels of the skin widen and fill with blood. That sudden surge of blood flow to the skin is the flush — the heat, the visible redness, and the prickling, itching nerves that the inflammatory mediators irritate. The whole sequence runs in minutes, which is why the flush comes on so quickly after a dose, and it fades as the prostaglandins are cleared and the body adapts.
Two pieces of evidence nail down this mechanism, and both have direct practical payoffs:
- Aspirin blocks the trigger. Prostaglandins are made by the enzyme cyclooxygenase (COX). Aspirin and other non-steroidal anti-inflammatory drugs block COX — so aspirin taken before or with niacin cuts the prostaglandin surge at its source and reduces the flush. This is not folk wisdom; it is the mechanism worked backward.
- The receptor is the on-switch. Laboratory studies showed that animals lacking the GPR109A receptor do not flush in response to nicotinic acid at all, and human studies traced the released prostaglandin directly to skin immune cells. Drugs designed to block the PGD2 receptor (such as laropiprant) were specifically built to suppress the flush. In the HPS2-THRIVE trial of 25,673 adults with vascular disease, extended-release niacin combined with laropiprant did not reduce major vascular events (13.2% versus 13.7% on placebo over a median 3.9 years) and increased serious side effects, including disturbances in diabetes control, infections, and bleeding.
An analogy. Think of GPR109A as a doorbell on the skin's immune cells. Nicotinic acid presses the bell; the cells answer by releasing prostaglandin D2, which throws open all the windows of the skin's blood vessels at once — warmth, color, and an itchy draft rush in. Aspirin is like quietly disconnecting the bell's wiring beforehand: the door never opens, so the windows stay shut. And because the household gets used to the bell, ringing it the same way every day (a steady dose) leads the cells to respond less and less — which is why the flush fades over the first one to two weeks of consistent use, a phenomenon called tachyphylaxis.
One more consequence falls straight out of the biology. The two other common forms of vitamin B3 do not act strongly on this skin pathway: nicotinamide (niacinamide) barely activates GPR109A and so essentially does not flush, and inositol hexanicotinate (“no-flush niacin”) releases its nicotinic acid so slowly that little flush occurs — a tradeoff discussed in the next sections.
Honest Context: Many Things Make Skin Flush
It would be misleading to suggest that flushing of the face and chest is somehow unique to niacin, or that flushing always points to vitamin B3. Flushing is one of the body's most common and least specific reactions — the skin reddens for dozens of ordinary reasons, and vitamin excess is only one entry on a long list. Being honest about this helps you tell a harmless niacin flush apart from a flush that deserves a closer look.
Common, everyday causes of facial and chest flushing include:
- Alcohol — one of the most frequent causes; some people (often those of East Asian descent) flush intensely after even small amounts. Notably, alcohol can amplify a niacin flush if the two are taken together.
- Spicy food, hot drinks, and heat — capsaicin and warmth dilate skin vessels directly.
- Emotion and exertion — blushing with embarrassment, stress, or exercise.
- Hormonal shifts — the hot flushes of menopause are a classic, recurring cause.
- Rosacea — a chronic skin condition in which the face flushes and stays persistently red.
- Medications — many drugs cause flushing, including calcium-channel blockers, some blood-pressure medicines, and others.
- Fever and infection — a flushed face is common when running a temperature.
There are also a few uncommon but medically important causes of flushing that are unrelated to niacin and that doctors keep in mind when flushing is persistent, unexplained, or comes with other symptoms: carcinoid syndrome (a hormone-secreting tumor), mast cell disorders, pheochromocytoma, and certain other endocrine conditions. These are rare, but they are the reason that flushing which does not have an obvious trigger — and especially flushing accompanied by diarrhea, wheezing, palpitations, or weight loss — is evaluated by doctors rather than dismissed.
The bottom line: a flush that arrives reliably 15–30 minutes after a known dose of nicotinic acid, follows the top-down face-to-chest pattern, and clears within an hour is almost certainly the niacin flush. A flush with no clear trigger, or one tied to other persistent symptoms, is a different question, with the other causes above in play.
Clues That It Is the Niacin Flush
You can usually identify the niacin flush from its fingerprint. The features that point firmly toward it — rather than to alcohol, menopause, rosacea, or something rarer — are:
- Tight timing. It begins about 15–30 minutes after a dose of immediate-release nicotinic acid and is gone within an hour or two. A reliable clock-like relationship to the dose is the strongest single clue.
- The form matters. It happens with nicotinic acid (plain niacin or prescription extended-release niacin) and essentially not with nicotinamide. If you flush on one B3 product but not another, the difference in form is usually the explanation.
- The classic pattern. Top-down: face and ears first, then neck and upper chest, with prickling and itch rather than welts.
- It eases with continued use. A flush that was strong in the first few days and then steadily milder over a week or two fits niacin's tachyphylaxis — the body adapting to a steady dose. Few other causes behave this way.
- It responds to aspirin and food. If pre-dosing with aspirin, or taking the niacin with a meal, clearly reduces it, that points strongly to the prostaglandin-driven niacin flush.
If your flushing does not fit this fingerprint — no relationship to a niacin dose, no improvement with the standard measures, persistent redness, or accompanying symptoms like diarrhea or palpitations — then the other causes above become more likely. Vitamin B3 is a common scapegoat for flushing it did not cause.
Which Form and Dose Causes It
Whether you flush, and how badly, depends almost entirely on which form of vitamin B3 you take and how the dose enters the bloodstream. The flush is driven by a rapid rise in nicotinic acid hitting the skin receptor, so anything that delivers the dose quickly makes it worse, and anything that softens the peak makes it milder.
- Immediate-release (IR) nicotinic acid — plain niacin tablets, including most inexpensive over-the-counter “niacin” and the high doses once used for cholesterol. This form floods the system fastest and causes the most flushing. Doses in the hundreds of milligrams to gram range routinely flush.
- Prescription extended-release (ER) niacin — engineered to release nicotinic acid more slowly, which lowers the peak and produces less flushing than IR niacin, though flushing is still its most common side effect and the leading reason people stop. Prescription ER niacin is a different product from unregulated “sustained-release” products, some of which release too slowly and have been linked to liver injury.
- Nicotinamide (niacinamide) — a different molecule that does the vitamin's job in the body but does not meaningfully activate the skin's GPR109A receptor. It essentially does not flush. It also, however, does not have niacin's cholesterol-lowering effect, so the two forms are not interchangeable for that purpose. In a 2025 records study of 13,108 U.S. patients (Vanderbilt University Medical Center and the Million Veteran Program), people who used nicotinamide did not have a higher rate of major adverse cardiovascular events (heart attacks, strokes, and related events), and a 2025 overview of 14 reviews found side effects less common with oral nicotinamide than with niacin, and more common at higher doses.
- Inositol hexanicotinate (“no-flush niacin”) — an over-the-counter product that releases nicotinic acid very slowly, so it flushes little. The catch is that, because so little free nicotinic acid is released, studies have generally found it does not lower cholesterol effectively. In a 6-week trial of 1,500 mg a day (about 40 people per group), inositol hexanicotinate improved no blood fat more than placebo, and a small blood-level substudy showed no evidence that it was absorbed (bioavailability), while wax-matrix extended-release niacin at the same dose lowered LDL cholesterol by 18%. “No-flush” in this case often means “little active effect” for lipids.
Other things that make a given dose flush more: taking it on an empty stomach, taking it with hot drinks or alcohol, and a jump in dose after a break (the adaptation resets if you stop for even a couple of days, so restarting at the old high dose can bring back a strong flush). The next section describes what studies and the drug label report about reducing it.
It is worth restating the context: this flushing arises almost entirely from supplemental and pharmacologic doses of nicotinic acid — hundreds of milligrams and up. The small amounts of niacin in food, and the modest amounts in an ordinary multivitamin, do not cause it.
What Reduces the Flush
Because the flush is a well-understood prostaglandin reaction, the measures that reduce it are specific. The U.S. prescribing label for extended-release niacin and the trials cited below describe them.
- Aspirin before or with the dose. In a trial of 148 healthy men given a single 2,000 mg dose of extended-release niacin, 650 mg of aspirin taken 30 minutes before or together with the niacin cut the share who flushed from 77% to 53–61%, lowered flush intensity and duration by 30–40%, and shortened the median flush from about 1 hour to 37–48 minutes; before and together worked about the same. The extended-release niacin label describes pretreatment with aspirin (up to 325 mg) 30 minutes before the dose. Other nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen can help similarly. Aspirin carries its own bleeding and stomach-ulcer risks, which add to those of blood thinners.
- With food. The extended-release niacin label says to take it at bedtime after a low-fat snack, and that taking it on an empty stomach is not recommended; food slows absorption and softens the peak. (A very high-fat meal can raise blood levels of certain ER formulations.)
- A low starting dose, raised slowly. The label starts extended-release niacin at 500 mg at bedtime and raises the daily dose by no more than 500 mg in any 4-week period, and states that flushing, itching, and stomach upset are greatly reduced by slowly increasing the dose. This gives the skin time to adapt (tachyphylaxis), so by the time the target dose is reached the flush has largely faded.
- Steady daily use. Adaptation resets quickly. Missing even a day or two can bring the flush back at the next dose, while steady daily use keeps it suppressed. The label says that after any interruption in dosing, the dose is built up again from a low level (re-titration).
- Bedtime dosing, and triggers around the dose. Taken at night, much of any flush from ER niacin can pass during sleep. The label lists alcohol, hot drinks, and spicy foods around the time of the dose as things that may increase flushing and itching; alcohol and heat widen skin vessels.
- The form. Nicotinamide avoids the flush entirely but does not lower cholesterol. The forms that lower cholesterol are IR and prescription ER nicotinic acid; the “no-flush” inositol form did not lower blood fats in the trial described above.
A mild, brief flush during the first week or two is common; the label states that tolerance to flushing develops rapidly over several weeks. It is the body adjusting, and it usually settles. Knowing in advance that the flush will come, peak, and pass — and that it is harmless — is itself one of the best tools for tolerating it.
Getting Checked
For a textbook niacin flush — the right timing, the right pattern, after a known dose of nicotinic acid, clearing within an hour — no testing is needed at all. The history is the diagnosis. The reason to involve a clinician is not to confirm the flush but to manage the niacin therapy safely and to be sure the redness is not something else.
A clinician will typically:
- Review the form, dose, and timing. Sorting out IR versus ER nicotinic acid versus nicotinamide, and how and when it is taken, usually explains the flush immediately and points to the fixes above.
- Distinguish flush from allergy. A true drug allergy — hives, swelling, wheezing, low blood pressure — looks and behaves differently from a prostaglandin flush, and the distinction matters because an allergy means stopping the drug, whereas a flush usually does not.
- Monitor the things that genuinely need watching on high-dose niacin. When niacin is used to treat cholesterol, periodic blood tests check the liver (niacin can raise liver enzymes — see Niacin and Liver Damage) and blood sugar and uric acid (niacin can raise both — see Niacin, Blood Sugar & Gout). A lipid panel tracks whether the niacin is achieving its purpose, and a comprehensive metabolic panel covers liver enzymes and glucose. These tests address niacin's real risks — the flush itself is not among them.
- Consider other causes when the picture does not fit. If flushing is unexplained, persistent, or comes with diarrhea, wheezing, palpitations, or weight loss, a clinician will look beyond niacin toward the less common causes named earlier rather than assuming it is the vitamin.
If a Flush Is Happening Now
A niacin flush in progress needs no emergency treatment — it will pass on its own, usually within an hour. The goal in the moment is simply comfort and a calmer next dose:
- It passes on its own. The flush peaks and fades without treatment. A cool room, cool (not hot) water, and one less layer of clothing make the heat and itch more bearable while it resolves.
- What makes it worse. Alcohol and hot drinks widen skin vessels and prolong the flush.
- The next dose. The measures described above — aspirin before or with the dose, taking it after a snack, and a slower dose increase or a different form — are the ones studied for the next dose.
- What it is. A warm, red, itchy face and chest, on schedule after a niacin dose, with no swelling and no trouble breathing, is the expected reaction — not an overdose and not an emergency.
If a flush is unusually severe and accompanied by a feeling of faintness, lying down with the legs raised until it passes eases the temporary dip in blood pressure. Any feature of a true allergic reaction — the red flags below — takes priority over the flush.
Red Flags: Signs Hospitals Treat as Urgent
The flush itself is benign, so the red flags here are mainly about the few situations where redness of the skin is not a simple niacin flush, or where high-dose niacin is harming something the flush does not announce. Hospitals treat these signs as reasons for prompt assessment — the first group as an emergency:
- Signs of a true allergic reaction — raised hives or welts that come and go, swelling of the lips, tongue, or throat, wheezing or shortness of breath, or feeling faint with a fast pulse. This is different from a flush and can be an emergency; call emergency services for breathing trouble or throat swelling.
- Flushing with diarrhea, wheezing, palpitations, or unexplained weight loss — especially flushing that is not clearly tied to a niacin dose. This combination warrants evaluation for the uncommon causes (such as carcinoid syndrome or a mast-cell disorder) rather than being attributed to the vitamin.
- Signs that high-dose niacin is harming the liver — nausea, vomiting, abdominal pain, unusual fatigue, dark urine, or yellowing of the skin or eyes. These are signs of liver injury that hospitals treat as urgent; see Niacin and Liver Damage.
- New or worsening high blood sugar or a gout attack — excessive thirst and urination, or a hot, swollen, painful joint, in someone on high-dose niacin; see Niacin, Blood Sugar & Gout.
- Persistent facial redness with no clear trigger — redness that stays for hours or days and does not follow a niacin dose may be rosacea or another skin condition rather than niacin.
The ordinary niacin flush — warm, red, itchy, on time after a dose, gone within the hour, with no swelling or breathing trouble — is not an emergency. Knowing which is which is the whole point: a harmless flush need not scare anyone off a medication that helps, and a flush can also be telling you something else. Whether niacin protects the heart is a separate question from the flush. In the AIM-HIGH trial (3,414 patients with heart and blood-vessel disease already on a statin), adding extended-release niacin did not reduce heart and stroke events (16.4% versus 16.2% on placebo), and the trial was stopped after about 3 years for lack of benefit. In HPS2-THRIVE (25,673 adults), extended-release niacin with laropiprant did not reduce major vascular events (13.2% versus 13.7%) and increased serious side effects. The U.S. label for extended-release niacin states that it did not reduce cardiovascular illness or death in patients on simvastatin in a large randomized trial.
Key Research Papers
- Tunaru S, Kero J, Schaub A, et al. (2003). PUMA-G and HM74 are receptors for nicotinic acid and mediate its anti-lipolytic effect. Nature Medicine;9(3):352-355. — DOI: 10.1038/nm824. — doi:10.1038/nm824
- Benyö Z, Gille A, Kero J, et al. (2005). GPR109A (PUMA-G/HM74A) mediates nicotinic acid–induced flushing. Journal of Clinical Investigation;115(12):3634-3640. — DOI: 10.1172/JCI23626. — doi:10.1172/JCI23626
- Maciejewski-Lenoir D, Richman JG, Hakak Y, et al. (2006). Langerhans Cells Release Prostaglandin D2 in Response to Nicotinic Acid. Journal of Investigative Dermatology;126(12):2637-2646. — DOI: 10.1038/sj.jid.5700586. — doi:10.1038/sj.jid.5700586
- Kamanna VS, Kashyap ML (2008). Mechanism of Action of Niacin. The American Journal of Cardiology;101(8A):20B-26B. — DOI: 10.1016/j.amjcard.2008.02.029. — doi:10.1016/j.amjcard.2008.02.029
- Gille A, Bodor ET, Ahmed K, Offermanns S (2008). Nicotinic Acid: Pharmacological Effects and Mechanisms of Action. Annual Review of Pharmacology and Toxicology;48:79-106. — DOI: 10.1146/annurev.pharmtox.48.113006.094746. — doi:10.1146/annurev.pharmtox.48.113006.094746
- Cefali EA, Simmons PD, Stanek EJ, et al. (2007). Aspirin reduces cutaneous flushing after administration of an optimized extended-release niacin formulation. International Journal of Clinical Pharmacology and Therapeutics;45(2):78-88. — DOI: 10.5414/CPP45078. — doi:10.5414/CPP45078
- Guyton JR, Bays HE (2007). Safety Considerations with Niacin Therapy. The American Journal of Cardiology;99(6A):22C-31C. — DOI: 10.1016/j.amjcard.2006.11.018. — doi:10.1016/j.amjcard.2006.11.018
- Capuzzi DM, Guyton JR, Morgan JM, et al. (1998). Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. The American Journal of Cardiology;82(12A):74U-81U. — DOI: 10.1016/S0002-9149(98)00731-0. — doi:10.1016/S0002-9149(98)00731-0
- AIM-HIGH Investigators; Boden WE, Probstfield JL, et al. (2011). Niacin in Patients with Low HDL Cholesterol Levels Receiving Intensive Statin Therapy. New England Journal of Medicine;365(24):2255-2267. — DOI: 10.1056/NEJMoa1107579. — doi:10.1056/NEJMoa1107579
- HPS2-THRIVE Collaborative Group; Landray MJ, Haynes R, et al. (2014). Effects of Extended-Release Niacin with Laropiprant in High-Risk Patients. New England Journal of Medicine;371(3):203-212. — DOI: 10.1056/NEJMoa1300955. — doi:10.1056/NEJMoa1300955
- Keenan JM (2013). Wax-matrix extended-release niacin vs inositol hexanicotinate: a comparison of wax-matrix, extended-release niacin to inositol hexanicotinate “no-flush” niacin in persons with mild to moderate dyslipidemia. Journal of Clinical Lipidology;7(1):14-23. — PubMed PMID: 23351578
- Wheless L, Guennoun R, Michalski-McNeely B, et al. (2025). Risk of Major Adverse Cardiovascular Events Following Nicotinamide Exposure. JAMA Dermatology;161(5):515-522. — PubMed PMID: 40009360
- Young SL, Gazzard G (2025). The adverse effects of oral niacin/nicotinamide — an overview of reviews. Eye;39(16):2852-2859. — PubMed PMID: 40999226
- U.S. National Library of Medicine, DailyMed. Niacin extended-release tablets: prescribing information (Dosage and Administration; Limitations of Use). — DailyMed label