Vitamin B12 for Cognition and Methylation
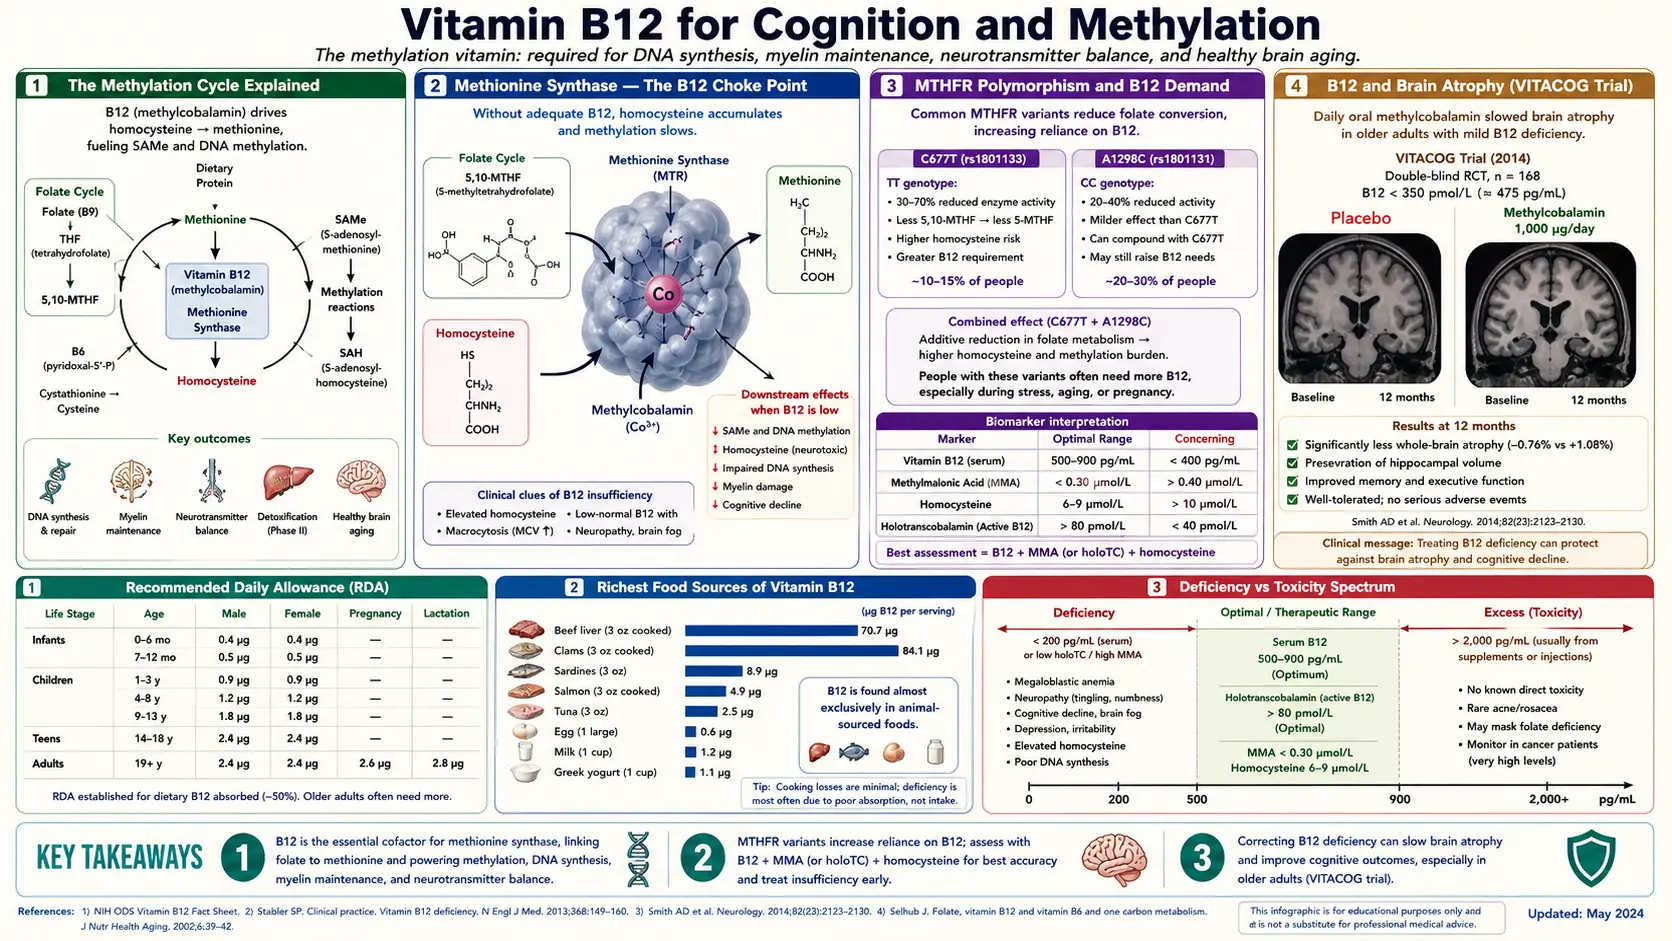
The methylation cycle is the most consequential biochemical reaction sequence in the human body that most people have never heard of. Methyl groups are added to and removed from DNA, RNA, proteins, phospholipids, and small molecules thousands of times per second in every cell, controlling gene expression, neurotransmitter synthesis, myelin maintenance, hormone metabolism, and homocysteine clearance. The whole system pivots on a single B12-dependent enzyme: methionine synthase. Low B12 collapses methylation, drives homocysteine upward, and accelerates brain atrophy. This deep-dive walks through the methylation cycle in clinical detail, the methylenetetrahydrofolate reductase (MTHFR) polymorphism that increases B12 demand, the 10-20% prevalence of low B12 in elderly cognitive decline, the S-adenosylmethionine (SAMe) and monoamine-synthesis mechanism behind B12's antidepressant effect, and the VITACOG trial, in which B-vitamin supplementation slowed brain atrophy by about 30% overall and by 53% in people whose homocysteine was above 13 micromol/L.
Interactive Visualization Vitamin B12’s Impossible Journey Five stages, two carrier proteins, a working stomach and one specific stretch of gut. Break any link — a proton pump inhibitor (PPI), metformin, pernicious anaemia — and absorption collapses. Launch →
Table of Contents
- The Methylation Cycle Explained
- Methionine Synthase — The B12 Choke Point
- Methylenetetrahydrofolate Reductase Polymorphism and B12 Demand
- B12 and Brain Atrophy (VITACOG Trial)
- B12 and Dementia — The Elderly Connection
- Depression and S-Adenosylmethionine Mechanism
- Monoamine Synthesis Dependency
- B-Complex Protocols for Memory and Mood
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Methylation Cycle Explained
The methylation cycle is the set of reactions that produces and recycles the cellular methyl-group currency that drives more than 200 distinct biochemical reactions. The center of the cycle is the conversion of methionine to S-adenosylmethionine (SAMe) — the universal methyl donor. When S-adenosylmethionine gives up its methyl group (to DNA, to a neurotransmitter precursor, to a phospholipid, etc.), it becomes S-adenosylhomocysteine (SAH), which is then hydrolyzed to homocysteine.
Homocysteine has three possible fates:
- Remethylation to methionine via methionine synthase (requires B12 as cofactor and 5-MTHF as methyl donor) — the dominant pathway in most tissues
- Remethylation to methionine via betaine-homocysteine methyltransferase (BHMT) (requires betaine/TMG as methyl donor) — a secondary pathway predominantly in liver and kidney
- Transsulfuration to cysteine via cystathionine beta-synthase (CBS) (requires B6 as cofactor) — the irreversible disposal pathway that feeds glutathione synthesis
The relative flux through these pathways depends on the body's current needs. When S-adenosylmethionine is abundant, it allosterically activates CBS and inhibits BHMT, pushing homocysteine into the transsulfuration pathway for disposal. When S-adenosylmethionine is depleted, the brakes come off remethylation and homocysteine cycles back to methionine and S-adenosylmethionine to restore the pool.
Methylation downstream of S-adenosylmethionine touches:
- DNA methylation — the epigenetic marking of gene promoter regions that controls which genes are turned on or off. Affects every cell, every day. Aberrant DNA methylation is implicated in cancer, aging, neurodegeneration, and developmental disorders.
- Histone methylation — chemical modifications of the proteins that package DNA into chromatin, controlling gene accessibility.
- Neurotransmitter synthesis — methylation steps in the production and degradation of dopamine, norepinephrine, epinephrine, serotonin, and melatonin. Catechol-O-methyltransferase (COMT) and phenylethanolamine N-methyltransferase (PNMT) are S-adenosylmethionine-dependent.
- Phospholipid synthesis — conversion of phosphatidylethanolamine to phosphatidylcholine via phosphatidylethanolamine N-methyltransferase (PEMT). Phosphatidylcholine is the major lipid component of cell membranes and a critical building block of myelin.
- Creatine synthesis — guanidinoacetate methyltransferase (GAMT) uses S-adenosylmethionine to make creatine. Creatine biosynthesis consumes ~75% of the body's daily S-adenosylmethionine production.
- Hormone metabolism — estrogen, thyroid hormone, and other steroid hormones undergo methylation reactions in their metabolism and detoxification.
- Carnitine, melatonin, and many other small molecules — S-adenosylmethionine-dependent synthesis steps.
When methylation collapses (most commonly because of B12 deficiency, less commonly because of folate deficiency, methylenetetrahydrofolate reductase polymorphism, B2/B6 deficiency, or BHMT/CBS variants), the downstream effects radiate across every cell type. The brain is particularly vulnerable because of its high methylation demand: neurotransmitter synthesis, myelin maintenance, and gene regulation in neurons are all methylation-dependent.
Methionine Synthase — The B12 Choke Point
Methionine synthase is the only enzyme in human biology that uses methylcobalamin as its cofactor. The reaction it catalyzes is conceptually simple but biologically critical: it transfers a methyl group from 5-methyltetrahydrofolate (5-MTHF) onto homocysteine, producing methionine and regenerating tetrahydrofolate (THF).
Two failure modes simultaneously emerge from methionine synthase inactivity:
- Homocysteine accumulates — because the major pathway for its disposal is blocked. Elevated homocysteine is an independent risk factor for cardiovascular disease, stroke, cognitive decline, dementia, neural tube defects, and recurrent miscarriage.
- Folate gets stuck — the so-called "methyl trap." 5-MTHF is normally an intermediate that quickly donates its methyl group and recycles. When methionine synthase is inactive, 5-MTHF builds up because there is nowhere for it to go (the methyl-group transfer is the only enzymatic exit from 5-MTHF). Meanwhile, THF (the form needed for thymidine synthesis and purine synthesis) is not regenerated. The cell becomes functionally folate-deficient even when total folate is adequate.
The methyl trap is the molecular explanation for why B12 deficiency produces an anemia that looks exactly like folate deficiency — the underlying defect is the same (insufficient active folate for DNA synthesis), it's just reached via different upstream causes.
Methionine synthase activity also depends on the cell's redox state. The cobalt at the heart of B12 must be maintained in the reduced (Co+1) state to accept and transfer the methyl group. Oxidative stress periodically oxidizes the cobalt to Co+2, inactivating the enzyme. The cell uses an auxiliary enzyme called methionine synthase reductase (encoded by MTRR) to reactivate it. MTRR polymorphisms are increasingly recognized as a factor in functional B12 deficiency — some people with adequate B12 still have low methionine synthase activity because their MTRR is less efficient.
Methylenetetrahydrofolate Reductase Polymorphism and B12 Demand
methylenetetrahydrofolate reductase (MTHFR) is the enzyme that produces 5-MTHF — the folate form that methionine synthase needs. Two common polymorphisms reduce methylenetetrahydrofolate reductase activity:
- C677T (rs1801133) — the more clinically important variant. Heterozygotes (C/T genotype, one copy of each allele) have ~35% reduced enzyme activity; homozygotes (TT) have ~70% reduced activity. Approximately 10-15% of people of European descent are TT homozygous; rates are higher in some Hispanic and lower in some African populations.
- A1298C (rs1801131) — less impact on enzyme activity but can compound C677T effects when both variants coexist (compound heterozygosity).
The clinical consequences of reduced methylenetetrahydrofolate reductase activity include:
- Higher homocysteine levels at any given folate and B12 intake
- Reduced 5-MTHF generation, which can functionally starve methionine synthase even when B12 is adequate
- Increased risk for neural tube defects in offspring of TT mothers
- Association with cardiovascular disease in some populations
- Association with depression, particularly treatment-resistant depression
- Possible association with some cancers (the literature is mixed)
The clinical implication for B12: patients with methylenetetrahydrofolate reductase variants need more of the upstream cofactors (B12, B2, B6) and benefit from supplementation with the already-methylated folate form (L-5-methyltetrahydrofolate, often abbreviated as L-methylfolate, LMTHF, or just "methylfolate") rather than folic acid. L-methylfolate bypasses the methylenetetrahydrofolate reductase step entirely — the body doesn't need to reduce it before use. This approach (combined methylcobalamin + L-methylfolate, plus B6 as P5P and B2 as R5P) is the standard "methylated B-complex" protocol used in integrative psychiatry for treatment-resistant depression with methylenetetrahydrofolate reductase variants.
Cautions:
- Methylenetetrahydrofolate reductase variants are common (one-third of the population has at least one C677T allele); their presence does not mean a person needs lifelong special supplementation unless they have clinical or biochemical evidence of dysfunction (elevated homocysteine, low folate or B12, depression, etc.) The variant alone is not a disease.
- Methylfolate at very high doses (15+ mg/day) can occasionally cause overstimulation, anxiety, or insomnia — especially in patients with COMT variants or histamine-sensitivity profiles. Integrative practitioners describe starting at 400-800 mcg and raising the dose gradually.
B12 and Brain Atrophy (VITACOG Trial)
The VITACOG trial (Smith et al., 2010, PLoS ONE) is the landmark study demonstrating that B vitamins can slow brain atrophy in mild cognitive impairment. The trial randomized 271 elderly patients with mild cognitive impairment (MCI — the prodromal state preceding Alzheimer's disease) to one of two arms for 2 years:
- Active arm: folic acid 0.8 mg + cyanocobalamin 0.5 mg + vitamin B6 (pyridoxine) 20 mg daily
- Placebo arm: identical-appearing placebo tablets
The primary outcome was the change in whole-brain volume measured by magnetic resonance imaging (MRI) at baseline and at 2 years. Brain atrophy in healthy elderly people occurs at a rate of approximately 0.5% per year; in MCI patients it accelerates to 1-1.5% per year; in Alzheimer's disease it approaches 2.5% per year.
Results:
- Mean rate of brain atrophy in the B-vitamin arm: 0.76%/year
- Mean rate of brain atrophy in the placebo arm: 1.08%/year
- Relative reduction in atrophy: 29.6% overall
- In participants with baseline homocysteine above 13 micromol/L, the atrophy rate was 53% lower in the B-vitamin arm
- The effect was driven entirely by patients with elevated homocysteine — in those with low baseline homocysteine, B vitamins produced no benefit
A follow-up VITACOG cognitive analysis (de Jager et al., 2012) showed that the B-vitamin arm preserved cognitive function on standardized testing better than placebo, again primarily in the elevated-homocysteine subgroup. A subsequent magnetic resonance imaging sub-study (Douaud et al., 2013) demonstrated that the B-vitamin arm specifically preserved the brain regions most vulnerable to Alzheimer's disease — the medial temporal lobes, including the hippocampus.
The VITACOG findings established three critical principles:
- B-vitamin supplementation can slow brain atrophy in at-risk elderly patients
- The benefit is driven by homocysteine reduction — not by some other mechanism
- The intervention works only in patients with elevated baseline homocysteine; patients with already-low homocysteine get no incremental benefit
How practitioners apply this: integrative and some memory-clinic practitioners measure homocysteine in people with MCI, a family history of dementia, or risk factors for cognitive decline. When homocysteine is above 10-11 micromol/L (common in elderly people), they describe a B12 + folate + B6 course, aiming for homocysteine below 9 micromol/L.
B12 and Dementia — The Elderly Connection
Low B12 is found in approximately 10-20% of elderly patients presenting with cognitive decline. The mechanisms are multiple:
- Atrophic gastritis — affects roughly 30% of adults over 60, reducing gastric acid output and impairing protein-bound B12 extraction from food. Stomach acid is needed to free B12 from food protein; without it, B12 passes through undigested. The condition is often asymptomatic and unrecognized.
- Reduced intrinsic factor production — some elderly patients have insufficient intrinsic factor without overt pernicious anemia. Borderline IF deficiency progresses gradually and may not be picked up by anti-IF antibody testing.
- Polypharmacy — proton pump inhibitors (omeprazole, esomeprazole, pantoprazole), H2 blockers (famotidine, ranitidine historically), and metformin all reduce B12 absorption. Many elderly patients are on at least one and often several of these medications for years.
- Decreased dietary intake — elderly patients often eat less meat, less variety, and may shift toward lower-cost soft foods with lower B12 content.
- Slower hepatic stores depletion — means deficiency can develop over many years without obvious clinical onset, presenting eventually as gradual cognitive decline that is easy to attribute to "normal aging."
The pseudodementia presentation: a subset of elderly patients with B12 deficiency present with cognitive symptoms severe enough to look like dementia — memory loss, confusion, executive dysfunction, sometimes psychotic features. These patients are frequently misdiagnosed with Alzheimer's disease. Aggressive B12 repletion (IM hydroxocobalamin 1000 mcg daily for 1-2 weeks, then weekly for 4-8 weeks, then monthly indefinitely) can produce dramatic cognitive recovery in pseudodementia patients — sometimes complete reversal of symptoms within 3-6 months.
The American Academy of Neurology, the Alzheimer's Association, and most dementia consensus guidelines recommend B12 (with methylmalonic acid (MMA) if borderline) as part of every dementia workup. The cost is trivial; the cost of missing reversible cognitive impairment is high. Even in patients who turn out to have primary Alzheimer's disease, optimizing B12 status reduces the additive contribution of B12 deficiency to their cognitive trajectory.
For patients with established Alzheimer's disease and low or borderline B12, B12 repletion does not reverse the AD pathology but may slow disease progression and provide modest cognitive benefit. The intervention is low-risk and inexpensive.
Depression and S-Adenosylmethionine Mechanism
The link between B12 deficiency and depression is biologically grounded in the methylation cycle. Three mechanisms operate in parallel:
- S-adenosylmethionine deficiency — S-adenosylmethionine is itself an antidepressant. Multiple randomized controlled trials have shown that exogenous S-adenosylmethionine (typically 800-1600 mg/day) has antidepressant efficacy comparable to first-line selective serotonin reuptake inhibitors (SSRIs) in major depressive disorder. When B12 deficiency reduces endogenous S-adenosylmethionine production, this antidepressant background is lost.
- Monoamine synthesis impairment — serotonin synthesis from tryptophan, dopamine synthesis from tyrosine, and norepinephrine synthesis all depend on tetrahydrobiopterin (BH4) as a cofactor. BH4 production and regeneration are linked to the methylation cycle; B12 deficiency indirectly reduces BH4 availability.
- Homocysteine neurotoxicity — elevated homocysteine is itself neurotoxic, activating N-methyl-D-aspartate (NMDA) receptors, generating oxidative stress in brain tissue, and promoting cerebrovascular damage. The depression of B12 deficiency may be partly a homocysteine-induced phenomenon.
The clinical evidence:
- Low B12 is significantly more common in depressed patients than in matched controls
- Low B12 is significantly more common in treatment-resistant depression than in treatment-responsive depression
- B12 supplementation augments antidepressant response in patients with low or borderline B12
- Folic acid (and especially L-methylfolate) augments antidepressant response in patients with low folate or methylenetetrahydrofolate reductase variants — in two 2012 trials by Papakostas and colleagues, L-methylfolate added to an SSRI at 7.5 mg/day did not differ from placebo, while 15 mg/day was more effective than continued SSRI treatment alone
- The combination of B12 + L-methylfolate + S-adenosylmethionine is used clinically as a "methylation-support" protocol for treatment-resistant depression
Cautions:
- B12 alone does not treat primary depression in patients with adequate baseline B12. The intervention is targeted at the subgroup with deficiency or borderline status.
- B12 optimization is used as an add-on to, not a replacement for, evidence-based depression treatment; severe depression carries a suicide risk that B vitamins do not address.
- The methyl-donor protocols (high-dose methylfolate, methylcobalamin, S-adenosylmethionine) can rarely trigger overstimulation, anxiety, or insomnia in sensitive individuals; practitioners describe starting low and raising the dose gradually.
Monoamine Synthesis Dependency
The synthesis of dopamine, norepinephrine, epinephrine, serotonin, and melatonin all depend on a small handful of cofactors. Methylation supports several steps:
- BH4 regeneration — tetrahydrobiopterin, the cofactor for tyrosine hydroxylase (TH, the rate-limiting enzyme in dopamine synthesis) and tryptophan hydroxylase (TPH, the rate-limiting enzyme in serotonin synthesis), depends on functional methylation cycles for proper regeneration.
- COMT and PNMT — S-adenosylmethionine-dependent enzymes in catecholamine metabolism. COMT degrades dopamine, norepinephrine, and epinephrine; PNMT converts norepinephrine to epinephrine.
- Melatonin synthesis — serotonin is converted to N-acetylserotonin by N-acetyltransferase, then N-acetylserotonin is converted to melatonin by hydroxyindole O-methyltransferase (HIOMT), a S-adenosylmethionine-dependent enzyme.
- Phosphatidylcholine — required for membrane integrity in synaptic terminals; produced by S-adenosylmethionine-dependent methylation of phosphatidylethanolamine.
When methylation collapses from B12 deficiency, all of these pathways become less efficient. The cumulative effect on mood, cognition, sleep, and motivation is what we recognize clinically as the psychiatric syndrome of B12 deficiency — depression, anhedonia, slowed thinking, poor concentration, sleep disturbance, and in severe cases frank psychiatric illness ("megaloblastic madness").
This is why B12 repletion in deficient patients often produces such striking improvements in mental energy, mood, and clarity within weeks: the methylation cycle resumes, neurotransmitter synthesis catches up, membrane phospholipids are repaired, and the entire central nervous system functions better.
B-Complex Protocols for Memory and Mood
The synergy among B vitamins means that single-nutrient supplementation often underperforms a coordinated B-complex approach. The standard protocols in integrative practice:
Cognitive Decline / MCI Prevention (Modeled on VITACOG)
- Methylcobalamin 1000 mcg daily (or hydroxocobalamin 1000 mcg IM monthly)
- L-methylfolate 400-1000 mcg daily (or folic acid 800 mcg if no methylenetetrahydrofolate reductase variants)
- Vitamin B6 (P5P) 25-50 mg daily
- Vitamin B2 (riboflavin or R5P) 25-50 mg daily — supports methylenetetrahydrofolate reductase enzyme function
- Target homocysteine below 9 micromol/L
Treatment-Resistant Depression Augmentation
- Methylcobalamin 1000-5000 mcg daily
- L-methylfolate 15 mg daily (the dose that was effective in the 2012 Papakostas trials; 7.5 mg was not)
- Vitamin B6 (P5P) 25-100 mg daily
- Vitamin B2 (R5P) 25 mg daily
- S-adenosylmethionine 800-1600 mg/day in divided doses (sometimes added)
- Omega-3 eicosapentaenoic acid (EPA) > 1000 mg daily (sometimes added)
- Vitamin D optimization, target 50-80 ng/mL (sometimes added)
- The prescribed antidepressant is continued alongside
Cognitive Performance Enhancement (No Deficiency)
- Methylcobalamin 500-1000 mcg daily
- L-methylfolate 400-800 mcg daily
- Vitamin B6 (P5P) 10-25 mg daily
- Vitamin B2 (R5P) 10-25 mg daily
- Plus other cognitive supports per individual (e.g., omega-3, magnesium L-threonate, exercise, sleep optimization)
The protocols are well-tolerated and inexpensive. Daily methylcobalamin 1000 mcg costs roughly $5-10 per month; methylfolate is similar; B6 and B2 are cheaper still. The combined methylated B-complex monthly cost is typically under $30.
Cautions
- Methylation overstimulation — in some patients, particularly those with COMT slow variants or histamine sensitivity, high-dose methylated B-complex protocols can trigger anxiety, insomnia, irritability, or headache. Practitioners describe starting at the low end (methylfolate 400 mcg, methylcobalamin 1000 mcg) and raising the dose slowly.
- Folic acid masking B12 deficiency — if folate is given without B12, the anemia corrects but the neurological problem progresses, which is why B12 status is checked before high-dose folate is given.
- Methylenetetrahydrofolate reductase variant testing — useful in patients with elevated homocysteine, treatment-resistant depression, or recurrent miscarriage. Not necessary for everyone — the polymorphism is common (one-third of the population has at least one C677T allele) and most carriers are clinically asymptomatic.
- Drug interactions — methotrexate (used in rheumatology and oncology) works by blocking folate, so high-dose methylfolate can in theory blunt its effect. S-adenosylmethionine has been reported to precipitate mania in people with bipolar disorder.
- Bipolar disorder caution — aggressive methylation support, especially S-adenosylmethionine, can trigger manic or hypomanic episodes in bipolar patients; signs are reduced need for sleep, racing thoughts, and unusually high energy or irritability.
- Add-ons, not substitutes — the B-complex protocols are used as adjuncts to evidence-based psychiatric care, not substitutes for it; stopping an antidepressant abruptly can cause withdrawal symptoms and relapse.
Key Research Papers
- Smith AD et al. (2010). Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment: a randomized controlled trial. PLoS One. 5(9):e12244. — PubMed PMID: 20838622
- de Jager CA et al. (2012). Cognitive and clinical outcomes of homocysteine-lowering B-vitamin treatment in mild cognitive impairment: a randomized controlled trial. Int J Geriatr Psychiatry. — PubMed PMID: 21780182
- Douaud G et al. (2013). Preventing Alzheimer's disease-related gray matter atrophy by B-vitamin treatment. PNAS. — PubMed PMID: 23690582
- Clarke R et al. (1998). Folate, vitamin B12, and serum total homocysteine levels in confirmed Alzheimer disease. Arch Neurol. — PubMed PMID: 9823829
- Seshadri S et al. (2002). Plasma homocysteine as a risk factor for dementia and Alzheimer's disease. NEJM. — PubMed PMID: 11844848
- Papakostas GI, Shelton RC, Zajecka JM, et al. (2012). L-methylfolate as adjunctive therapy for SSRI-resistant major depression: results of two randomized, double-blind, parallel-sequential trials. Am J Psychiatry. 169(12):1267-74. — PubMed PMID: 23212058
- Coppen A, Bailey J (2000). Enhancement of the antidepressant action of fluoxetine by folic acid. J Affect Disord. — PubMed PMID: 10967371
- Papakostas GI et al. (2010). S-adenosyl methionine (SAMe) augmentation of serotonin reuptake inhibitors for antidepressant nonresponders. Am J Psychiatry. — PubMed PMID: 20595412
- Bottiglieri T (2002). S-Adenosyl-L-methionine (SAMe): from the bench to the bedside — molecular basis of a pleiotrophic molecule. Am J Clin Nutr. — PubMed PMID: 12418493
- Refsum H et al. (2006). The Hordaland Homocysteine Study: a community-based study of homocysteine, its determinants, and associations with disease. J Nutr. — PubMed PMID: 16702348
- Frosst P et al. (1995). A candidate genetic risk factor for vascular disease: a common mutation in MTHFR. Nature Genetics. — PubMed
- Selhub J, Jacques PF, Wilson PW, Rush D, Rosenberg IH (1993). Vitamin status and intake as primary determinants of homocysteinemia in an elderly population. JAMA. 270(22):2693-8. — PubMed PMID: 8133587
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B12’s Impossible Journey — interactive animation
- Vitamin B12 Overview
- B12 Benefits Hub
- B12 for Nerve Health
- B12 for Anemia
- B12 for Vegans & Absorption
- B12 and the Nervous System
- Vitamin B9 (Folate / Methylfolate)
- Vitamin B6
- Vitamin B2 (Riboflavin)
- Homocysteine
- Vitamin B12 Test
- Depression
- Dementia
- Alzheimer's Disease
- Methionine
- Brain Fog
- Fatigue
- Deficiency
- Toxicity
- History
- Sources