⚠ Evidence warning: Clinical trials or other evidence do not support the claims that high-dose oral B12 is equivalent to injections for maintenance in pernicious anemia, that the vast majority of those patients can be managed on oral therapy alone, that the described oral protocol is clinically valid, and that subcutaneous injection gives equivalent absorption. This page keeps it as a report of what people, websites or other media say.
Vitamin B12 for Anemia and Hematology
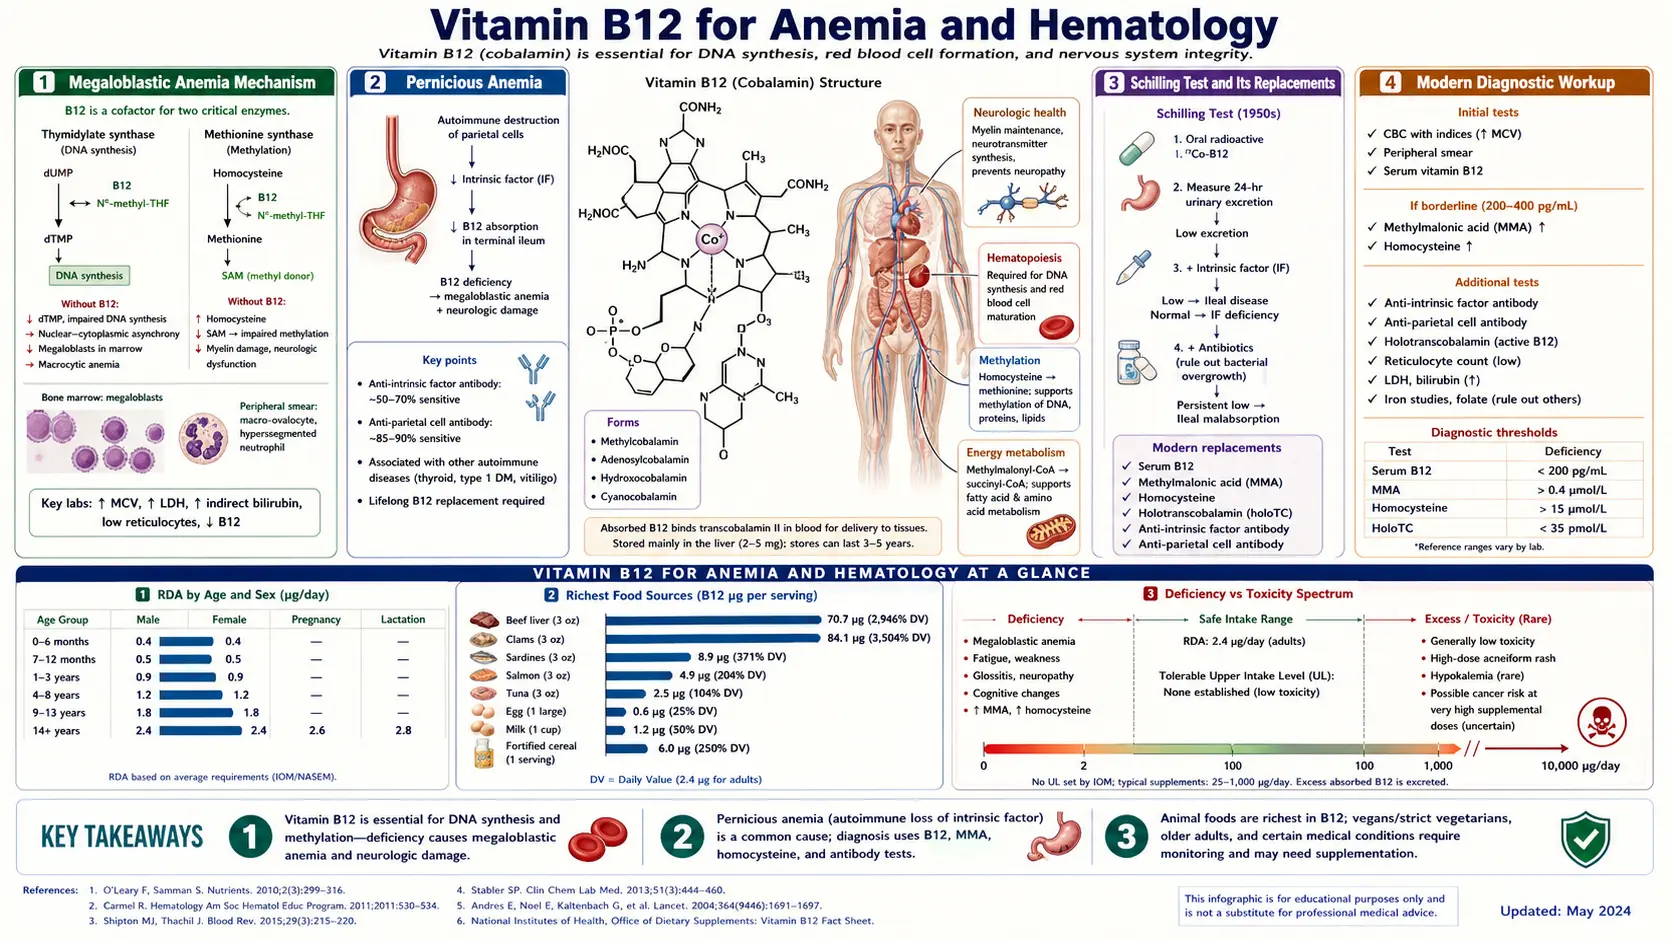
Pernicious anemia was the disease behind the 1934 Nobel Prize in Physiology or Medicine, awarded to George Whipple, George Minot and William Murphy "for their discoveries concerning liver therapy in cases of anaemia"; vitamin B12 was later identified as the active factor in liver. Before B12 was characterized, pernicious anemia was uniformly fatal: a relentless progression of fatigue, neurological deterioration, and death over 1-3 years. Today it remains the most well-known clinical context for B12 therapy, but the picture is wider than autoimmune intrinsic factor deficiency alone: megaloblastic anemia from any cause (vegan diet, malabsorption, drug-induced) responds to B12. This deep-dive walks through the molecular mechanism of the megaloblastic defect, the autoimmune pathophysiology of pernicious anemia, the historical Schilling test and its modern replacements, the intramuscular (IM) injection schedules, and the trials showing that high-dose oral B12 can raise blood B12 even when absorption is impaired.
Interactive Visualization Vitamin B12’s Impossible Journey Five stages, two carrier proteins, a working stomach and one specific stretch of gut. Break any link — a proton pump inhibitor (PPI), metformin, pernicious anaemia — and absorption collapses. Launch →
Table of Contents
Megaloblastic Anemia Mechanism
Megaloblastic anemia is defined by abnormally large, immature red blood cell precursors in the bone marrow (megaloblasts) and abnormally large mature red blood cells in the peripheral blood (macrocytes, or more specifically macro-ovalocytes). The mean corpuscular volume (MCV) is elevated, typically above 100 fL and often above 110 fL in severe cases.
The underlying defect is impaired DNA synthesis in rapidly dividing cells. Erythroblasts in the bone marrow are among the fastest-dividing cells in the body — producing roughly 200 billion new red blood cells every day in a healthy adult. This proliferative burst requires intact synthesis of thymidine, one of the four nucleotide building blocks of DNA. Thymidine is made by the methylation of deoxyuridine monophosphate (dUMP) to deoxythymidine monophosphate (dTMP) by the enzyme thymidylate synthase, which uses 5,10-methylenetetrahydrofolate as its methyl donor.
Here is where B12 enters the picture. The body's largest pool of folate is in the form of 5-methyltetrahydrofolate (5-MTHF). To enter the thymidine synthesis pathway, 5-MTHF must first donate its methyl group to homocysteine via the methionine synthase reaction, regenerating tetrahydrofolate (THF), which can then be reconverted to 5,10-methylenetetrahydrofolate for thymidine synthesis. Methionine synthase requires B12. When B12 is deficient, 5-MTHF cannot donate its methyl group, folate becomes trapped in the methylated form (the "methyl trap"), and the active folate pool needed for thymidine synthesis collapses.
The consequence: erythroblasts cannot synthesize enough thymidine to replicate their DNA. They continue to grow and accumulate cytoplasmic contents (including hemoglobin), but their nuclei lag behind. The result is a giant cell with abundant cytoplasm and an immature, oversized nucleus — the megaloblast. Many of these cells die in the bone marrow (ineffective erythropoiesis); those that mature into circulating red blood cells are oversized, oval-shaped, and short-lived. The patient becomes profoundly anemic despite a hyperactive bone marrow.
Because the defect is upstream of all three blood-cell lineages, severe B12 deficiency can also produce leukopenia (low white blood cells), thrombocytopenia (low platelets), and ultimately pancytopenia (low everything). White blood cells show the same nuclear immaturity defect — hypersegmented neutrophils (5 or more nuclear lobes) are an early and sensitive sign of the megaloblastic process, often present before MCV elevation becomes obvious.
Folate deficiency produces an identical hematological picture through a different mechanism (depletion of folate substrate). This is why supplementing folate alone can correct the anemia of B12 deficiency — folate bypasses the methyl trap by providing fresh folate substrate downstream. The danger: folate supplementation corrects the blood picture but does not fix the methylation defect, so neurological damage continues to progress silently while the patient and clinician think the problem is resolved. This is one of the most important principles in B12 medicine: folic acid can correct the anemia while nerve damage from B12 deficiency goes on, which is why B12 and folate are both measured in macrocytic anemia before folate is started.
Pernicious Anemia
Pernicious anemia (PA) is the classic and most studied cause of B12 deficiency. It is an autoimmune disease in which the immune system attacks the gastric parietal cells (the cells of the stomach that produce intrinsic factor and stomach acid) or intrinsic factor itself. Two antibody types are characteristic:
- Anti-parietal cell antibodies (APCA) — present in ~85% of PA patients but also present in 5-10% of the healthy elderly population without disease. Sensitive but not specific.
- Anti-intrinsic factor antibodies (AIFA) — present in 50-70% of PA patients and highly specific for the disease. Very rarely found outside PA. Less sensitive but more specific.
Two clinical sub-types of anti-IF antibody exist: type I (blocks B12 binding to IF) and type II (blocks the IF-B12 complex from binding to its ileal receptor). Either pattern produces the same clinical result: B12 cannot be absorbed through the normal physiological pathway, and over years to decades the patient's hepatic B12 stores deplete, leading to the classic triad of macrocytic anemia + neurological symptoms + glossitis.
PA is strongly associated with other autoimmune conditions, particularly:
- Hashimoto's thyroiditis (most common association)
- Graves' disease
- Vitiligo
- Type 1 diabetes mellitus
- Addison's disease
- Premature ovarian failure
- Primary biliary cholangitis
These conditions cluster as part of the autoimmune polyendocrine syndrome. A 2009 review (Lahner and Annibale) reports autoimmune thyroid disease in about 40% of people with pernicious anemia and diabetes in about 10%.
PA also carries an elevated risk of gastric cancer, related to the chronic atrophic gastritis that develops from autoimmune parietal cell destruction. A 2013 systematic review of 27 studies (Vannella and colleagues) put the gastric cancer rate in pernicious anemia at 0.27% per person per year, an estimated nearly sevenfold relative risk (relative risk 6.8). Only 7 of the 27 studies were rated high quality, and the reviewers called for better studies to confirm the higher risk. Endoscopic surveillance every 3-5 years is recommended in established PA, particularly if the diagnosis was made before age 50.
Treatment is lifelong B12 supplementation — the underlying autoimmune disease does not remit, and the intrinsic factor deficiency does not reverse. Without sustained B12 replacement, the anemia and neurological complications return inexorably.
Schilling Test and Its Replacements
The Schilling test was the gold standard for diagnosing B12 absorption defects from the 1950s through the early 2000s. It involved giving the patient an oral dose of radioactive cyanocobalamin (cobalt-57 or cobalt-58 labeled), followed by a large parenteral "flushing" dose of unlabeled B12. The radioactive B12 absorbed from the gut would be excreted in the urine over 24 hours; the amount of urinary radioactivity reflected the patient's intrinsic absorptive capacity.
If urinary excretion was low, suggesting absorption defect, the test was repeated with intrinsic factor added to the oral dose. Normalization indicated pernicious anemia (intrinsic factor deficiency); persistent low excretion indicated ileal disease or bacterial overgrowth.
The Schilling test was retired in most clinical settings in the early 2000s because:
- The radioactive material became difficult to source
- Better and safer alternatives became available
- Treatment decisions can usually be made without precisely localizing the absorption defect
The modern replacements:
- Anti-intrinsic factor antibodies (AIFA) — highly specific for pernicious anemia. A positive AIFA in a patient with B12 deficiency essentially confirms PA without needing further testing.
- Anti-parietal cell antibodies (APCA) — sensitive but less specific; suggests autoimmune gastritis and supports PA diagnosis when combined with other findings.
- Serum gastrin — markedly elevated in PA (typically >500 pg/mL) because parietal cell destruction removes the negative feedback that normally suppresses G-cell gastrin secretion.
- Pepsinogen I and the pepsinogen I/II ratio — pepsinogen I is low in PA reflecting parietal cell loss; the ratio is suppressed.
- Holotranscobalamin (holoTC) — measures the bioavailable B12 fraction; low in any B12 deficiency.
- Upper endoscopy with biopsy — demonstrates the body-predominant atrophic gastritis characteristic of PA; rules out gastric cancer.
Without a Schilling test, intrinsic factor deficiency cannot be proven directly. A 2009 review (Lahner and Annibale) reports that intrinsic factor antibodies and parietal cell antibodies used together as markers pick up 73% of pernicious anemia cases (sensitivity) with 100% specificity. The same review notes that pernicious anemia is mainly thought of as a disease of the elderly, but younger patients make up about 15% of cases.
For most patients, the combination of clinical picture (macrocytic anemia, neurological symptoms, autoimmune background), elevated methylmalonic acid (MMA), and positive anti-IF antibody is sufficient to confirm pernicious anemia without invasive testing.
Modern Diagnostic Workup
The recommended workup for suspected B12 deficiency anemia:
- Complete blood count (CBC) with differential and peripheral blood smear — assess hemoglobin, MCV, MCH, white cell count, platelet count, and morphology. Look for macrocytosis, oval macrocytes, hypersegmented neutrophils.
- Serum B12 — the starting point. <200 pg/mL is clearly deficient; 200-400 pg/mL is borderline; 400-900 pg/mL is normal; >900 pg/mL is supraphysiological (usually supplementation).
- Serum folate and red cell folate — rule out concurrent folate deficiency (which is also a cause of macrocytic anemia). Always check before starting folate supplementation.
- Methylmalonic acid (MMA) — the most specific functional marker of B12 deficiency. Elevated methylmalonic acid in the presence of borderline or low B12 confirms functional deficiency.
- Homocysteine — elevated in B12 deficiency, but also elevated in folate deficiency, B6 deficiency, and renal insufficiency. Sensitive but not specific.
- Reticulocyte count — usually inappropriately low in megaloblastic anemia (because erythropoiesis is ineffective).
- Lactate dehydrogenase (LDH) and indirect bilirubin — elevated due to intramedullary hemolysis (red cell precursors dying in the bone marrow).
- Iron studies — rule out concurrent iron deficiency, which can mask the macrocytosis of B12 deficiency.
- Thyroid-stimulating hormone (TSH) — rule out hypothyroidism, which is commonly associated with PA and also causes macrocytosis.
- If B12 deficiency confirmed: anti-intrinsic factor antibodies, anti-parietal cell antibodies, and serum gastrin to evaluate for pernicious anemia.
The pattern that confirms B12 deficiency anemia: low or borderline B12, elevated methylmalonic acid, elevated homocysteine, macrocytic anemia with hypersegmented neutrophils. Pernicious anemia is confirmed by positive anti-IF antibody and/or elevated gastrin with hypopepsinogenemia.
Intramuscular (IM) Injection Schedules
Intramuscular B12 injection has been the standard treatment for pernicious anemia and severe B12 deficiency for over 70 years. Suggested schedules differ considerably between countries. A 2023 BMJ review (Wolffenbuttel and colleagues) gives two examples:
- British National Formulary, neurological involvement: hydroxocobalamin 1 mg by intramuscular injection on alternate days until there is no further improvement, then 1 mg every 2 months.
- Dutch pharmacotherapeutic guidelines, same symptoms: 1000 mcg once or twice weekly for up to two years.
The same review notes that little robust evidence supports any of the current dosing schedules, that people differ widely in how much they need, and that some people with neurological symptoms need injections anywhere from twice weekly to every 2-4 weeks to become and stay free of symptoms. The 2014 British Society for Haematology guideline (Devalia and colleagues) says treatment follows the British National Formulary and that oral therapy may be suitable when appropriate doses are taken and doses are not missed. The 2024 NICE guideline on vitamin B12 deficiency (NG239) recommends lifelong intramuscular replacement when autoimmune gastritis (the stomach disease behind pernicious anemia) is the cause or suspected cause.
Other schedules in common use: cyanocobalamin 1000 mcg IM daily for 1-2 weeks (cheaper, equally effective hematologically, possibly less optimal for neurological involvement), continuing with the next phase based on response; and for maintenance, hydroxocobalamin 1000 mcg IM every 2-3 months for life (UK NHS standard: every 3 months; US standard: every 1-3 months depending on individual response and severity of disease).
The injection schedules used in the two randomized oral-versus-injection trials described below were:
- Kuzminski 1998: cyanocobalamin 1 mg intramuscularly on days 1, 3, 7, 10, 14, 21, 30, 60 and 90.
- Bolaman 2003: cobalamin 1000 mcg intramuscularly once daily for 10 days, then once a week for 4 weeks, then once a month for life.
Hydroxocobalamin is used for maintenance in much of Europe because its longer tissue retention allows less frequent dosing than cyanocobalamin. Hydroxocobalamin is now widely available in the US as well.
Injection technique: deep intramuscular injection into the deltoid or vastus lateralis. Most patients can be trained to self-inject after the induction phase, dramatically reducing the burden of treatment. Subcutaneous injection (less painful, easier to self-administer) has been shown to produce equivalent absorption in several recent studies and is now used in some practices. Subcutaneous injection (under the skin) is sometimes used when intramuscular injection is unsuitable, for instance in people taking anticoagulants; a 2023 BMJ review notes that studies comparing the two routes are lacking.
High-Dose Oral B12
The single most important development in B12 medicine over the past 30 years is the demonstration that high-dose oral B12 (1000-2000 mcg/day) works even in pernicious anemia.
In 1968 the Swedish physicians H. Berlin, R. Berlin and G. Brante reported treating pernicious anemia with high oral doses of vitamin B12 without intrinsic factor. The randomized trials comparing oral and injected B12 came later:
- Kuzminski 1998 (Blood): 38 newly diagnosed people with cobalamin deficiency were randomly assigned to 2 mg oral cyanocobalamin daily for 120 days or the injection schedule above; 33 could be evaluated. Blood and nerve abnormalities corrected promptly and equally in both groups. After 4 months, mean serum B12 was 1,005 pg/mL on oral versus 325 pg/mL on injections, and methylmalonic acid 169 versus 265 nmol/L. The authors concluded that 2 mg a day by mouth was as effective as 1 mg injected monthly and may be superior.
- Bolaman 2003 (Clin Ther): 60 people with megaloblastic anemia from cobalamin deficiency completed a 90-day open-label trial of 1000 mcg oral versus 1000 mcg injected on the same schedule. Blood counts recovered in a similar way in both groups. Nerve symptoms improved in 7 of 9 people on oral B12 (77.8%) and 9 of 12 on injections (75.0%) by day 30. Oral treatment was better tolerated and cost less; the authors noted the small size and short length of the study.
- Cochrane review 2018 (Wang and colleagues): 3 randomized trials, 153 people, 3-4 months of treatment. Low-quality evidence showed oral and intramuscular B12 having similar effects in bringing serum B12 back to normal, with oral treatment costing less. One trial using 2000 mcg a day found serum B12 680 pg/mL higher on oral. No trial reported on symptoms or quality of life.
The biological basis: although most dietary B12 absorption needs intrinsic factor and the ileal cubilin-amnionless receptor, a small fraction of a large oral dose crosses the gut wall by passive diffusion. A 2023 BMJ review (Wolffenbuttel and colleagues) states that a 2000 mcg oral dose may let up to 10-12 mcg be absorbed daily, but that passive absorption may be well below 1% in many patients. The same review reports that some people can switch to 2000 mcg daily by mouth instead of injections, but that it is impossible to predict in whom this can be done safely, and that symptoms can worsen, sometimes permanently, when injections are reduced too quickly.
Oral cyanocobalamin or methylcobalamin 1000-2000 mcg/day is equivalent to IM 1000 mcg monthly for maintenance in pernicious anemia. The vast majority of pernicious anemia patients can be successfully managed with oral therapy alone after an initial IM induction.
A practical oral protocol:
- Induction: IM during this phase to ensure rapid tissue saturation, particularly if neurological symptoms are present.
- Transition to oral: After hematological response is established and patient is clinically stable, a switch to oral methylcobalamin 2000 mcg daily.
- Maintenance: Oral methylcobalamin or cyanocobalamin 1000-2000 mcg daily indefinitely.
- Patient choice: patients who prefer monthly IM injections can continue them indefinitely — both approaches are clinically valid.
Adherence is the key issue with oral therapy — daily lifelong supplementation is harder to remember than an injection every few months; the British Society for Haematology guideline ties the suitability of oral therapy to doses being taken reliably. For patients with reliable adherence, oral is more convenient, cheaper, and equally effective.
Response Monitoring
The hematological response to B12 repletion follows a predictable timeline:
- Days 1-3: Subjective improvement in energy and well-being begins. Methylmalonyl-CoA levels begin to fall.
- Days 3-7: Reticulocyte count rises (reticulocytosis) as the bone marrow is suddenly able to produce competent red cells from the accumulated mature precursors. Peak reticulocyte response is typically at day 5-10 and confirms that the diagnosis was correct.
- Weeks 2-4: Hemoglobin begins to rise; MCV begins to fall toward normal; hypersegmented neutrophils disappear; lactate dehydrogenase and indirect bilirubin normalize as ineffective erythropoiesis resolves.
- Weeks 4-8: Hemoglobin reaches the normal range; MCV normalizes; full hematological recovery achieved.
- Months 2-6: If neurological symptoms were present, gradual neurological recovery proceeds as discussed in the Nerve Health page.
If reticulocytosis does not occur within 10 days of starting parenteral B12, the diagnosis is in doubt. Failure to respond suggests:
- Concurrent iron deficiency (most common cause of failed reticulocyte response, found on iron studies)
- Concurrent folate deficiency (check serum folate)
- Concurrent thyroid disease
- Bone marrow disease (myelodysplastic syndrome can present with macrocytosis and pancytopenia and does not respond to B12)
- Wrong diagnosis
Monitoring during maintenance, as commonly described: serum B12, methylmalonic acid, and complete blood count at 3 months, 6 months, then annually if stable; for people on oral maintenance, at least one repeat methylmalonic acid at 6-12 months after switching to confirm continued adequacy.
Combined Iron + B12 + Folate Deficiency
One of the most clinically important presentations is combined deficiency: simultaneous iron, B12, and/or folate deficiency. This is particularly common in:
- Elderly patients with atrophic gastritis (low iron absorption and low B12 absorption simultaneously)
- Patients with celiac disease, Crohn's disease, or post-bariatric surgery
- Patients with chronic alcohol use disorder
- Pregnant women with poor nutritional baseline
- Patients with chronic blood loss from any cause
The hematological picture in combined deficiency can be confusing — iron deficiency causes microcytic anemia (low MCV), while B12/folate deficiency causes macrocytic anemia (high MCV). The two opposing effects can produce a normal-appearing MCV (the so-called "dimorphic" picture) that masks both deficiencies. Examination of the peripheral blood smear is critical: a dimorphic population of small hypochromic cells alongside large oval macrocytes is the giveaway.
Treatment requires addressing each deficiency separately:
- Iron repletion (oral ferrous sulfate 325 mg or other iron form, vitamin C improves its absorption, and coffee, tea and dairy reduce it)
- B12 repletion (as above)
- Folate repletion (folic acid 1-5 mg/day, or methylfolate 1-7.5 mg/day in patients with methylenetetrahydrofolate reductase (MTHFR) variants)
- If concurrent thyroid disease is present, address it as well
Iron deficiency frequently coexists with B12 deficiency because both require gastric acid for proper absorption, and both rise in the same at-risk populations (elderly, post-gastrectomy, atrophic gastritis, vegan/vegetarian). A 2009 review (Lahner and Annibale) describes monitoring for the onset of iron deficiency as part of the care of pernicious anemia.
Cautions
- Hypokalemia during induction — severe pernicious anemia patients can develop dangerously low potassium during rapid hematological response. Newly formed red cells take potassium into the intracellular compartment, dropping serum levels. Low potassium can develop during the first weeks of treatment; a 2023 BMJ review describes this transient drop in people with severe anemia as usually mild and without clinical consequences.
- Hypophosphatemia — similar mechanism; rapid cell proliferation depletes serum phosphate. Less common than hypokalemia but documented.
- Iron deficiency unmasked — B12 repletion drives a burst of erythropoiesis that consumes iron rapidly. Latent iron deficiency may become symptomatic. A 2023 BMJ review notes that coexisting iron deficiency may be present and need iron supplementation.
- Folate masking — folic acid supplementation can correct the anemia of B12 deficiency without addressing the neurological problem. Nerve damage can progress while the blood count looks normal.
- Gastric cancer surveillance — a 2013 systematic review put the gastric cancer rate in pernicious anemia at 0.27% per person per year, nearly seven times the usual risk (relative risk 6.8); the review called for better studies to confirm it.
- Thyroid screening — autoimmune thyroid disease is found in about 40% of people with pernicious anemia (Lahner and Annibale 2009); Hashimoto's thyroiditis and PA cluster together, and the thyroid-stimulating hormone (TSH) blood test detects an underactive thyroid.
- Family screening — a 2009 review (Lahner and Annibale) reports that human leucocyte antigen-DR genotypes suggest a role for genetic susceptibility in pernicious anemia.
Key Research Papers
- Whipple GH, Minot GR, Murphy WP (1934). Nobel Prize in Physiology or Medicine "for their discoveries concerning liver therapy in cases of anaemia". — PubMed; nobelprize.org
- Kuzminski AM, Del Giacco EJ, Allen RH, Stabler SP, Lindenbaum J (1998). Effective treatment of cobalamin deficiency with oral cobalamin. Blood 92(4):1191-8. — the randomized trial showing oral B12 works in cobalamin deficiency, including absorption defects. — PubMed PMID: 9694707
- Bolaman Z et al. (2003). Oral vs intramuscular cobalamin in megaloblastic anemia: a single-center, prospective, randomized trial. Clin Ther. — PubMed PMID: 14749150
- Vidal-Alaball J et al. (2005). Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency. Cochrane Database Syst Rev. (Superseded by the 2018 update below.) — PubMed PMID: 16034940
- Wang H, Li L, Qin LL, Song Y, Vidal-Alaball J, Liu TH (2018). Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency. Cochrane Database Syst Rev 3:CD004655. — PubMed PMID: 29543316
- Berlin H, Berlin R, Brante G (1968). Oral treatment of pernicious anemia with high doses of vitamin B12 without intrinsic factor. Acta Med Scand 184(4):247-58. — PubMed PMID: 5751528
- Toh BH et al. (1997). Pernicious anemia. NEJM. — PubMed PMID: 9358143
- Lahner E, Annibale B (2009). Pernicious anemia: new insights from a gastroenterological point of view. World J Gastroenterol. — PubMed PMID: 19891010
- Devalia V, Hamilton MS, Molloy AM; British Committee for Standards in Haematology (2014). Guidelines for the diagnosis and treatment of cobalamin and folate disorders. Br J Haematol 166(4):496-513. — PubMed PMID: 24942828
- Annibale B, Marignani M, Azzoni C, et al. (1997). Atrophic body gastritis: distinct features associated with Helicobacter pylori infection. Helicobacter 2(2):57-64. — PubMed PMID: 9432330
- Carmel R (2008). How I treat cobalamin (vitamin B12) deficiency. Blood. — PubMed
- Hvas AM, Nexo E (2006). Diagnosis and treatment of vitamin B12 deficiency — an update. Haematologica. — PubMed PMID: 17043022
- Stabler SP (2013). Clinical practice. Vitamin B12 deficiency. N Engl J Med 368(2):149-60. — PubMed PMID: 23301732
- Vannella L, Lahner E, Osborn J, Annibale B (2013). Systematic review: gastric cancer incidence in pernicious anaemia. Aliment Pharmacol Ther 37(4):375-82. — PubMed PMID: 23216458
- Wolffenbuttel BHR, Owen PJ, Ward M, Green R (2023). Vitamin B12. BMJ 383:e071725. — PubMed PMID: 37984968
- National Institute for Health and Care Excellence (2024). Vitamin B12 deficiency in over 16s: diagnosis and management (NG239). — NICE NG239
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B12’s Impossible Journey — interactive animation
- Vitamin B12 Overview
- B12 Benefits Hub
- B12 for Nerve Health & Neuropathy
- B12 for Cognition & Methylation
- B12 for Vegans & Absorption
- B12 Deficiency Diagnosis
- Anemia
- Complete Blood Count
- Vitamin B12 Test
- Homocysteine
- Iron
- Vitamin B9 (Folate)
- Hashimoto's Thyroiditis
- Celiac Disease
- Crohn's Disease
- Small Intestinal Bacterial Overgrowth
- Fatigue
- Pernicious Anemia — the autoimmune loss of intrinsic factor behind the classic B12-deficiency anemia.
- Deficiency
- Toxicity
- History
- Sources