Choline for Liver Health & Non-Alcoholic Fatty Liver Disease (NAFLD) — The Essential Nutrient Story
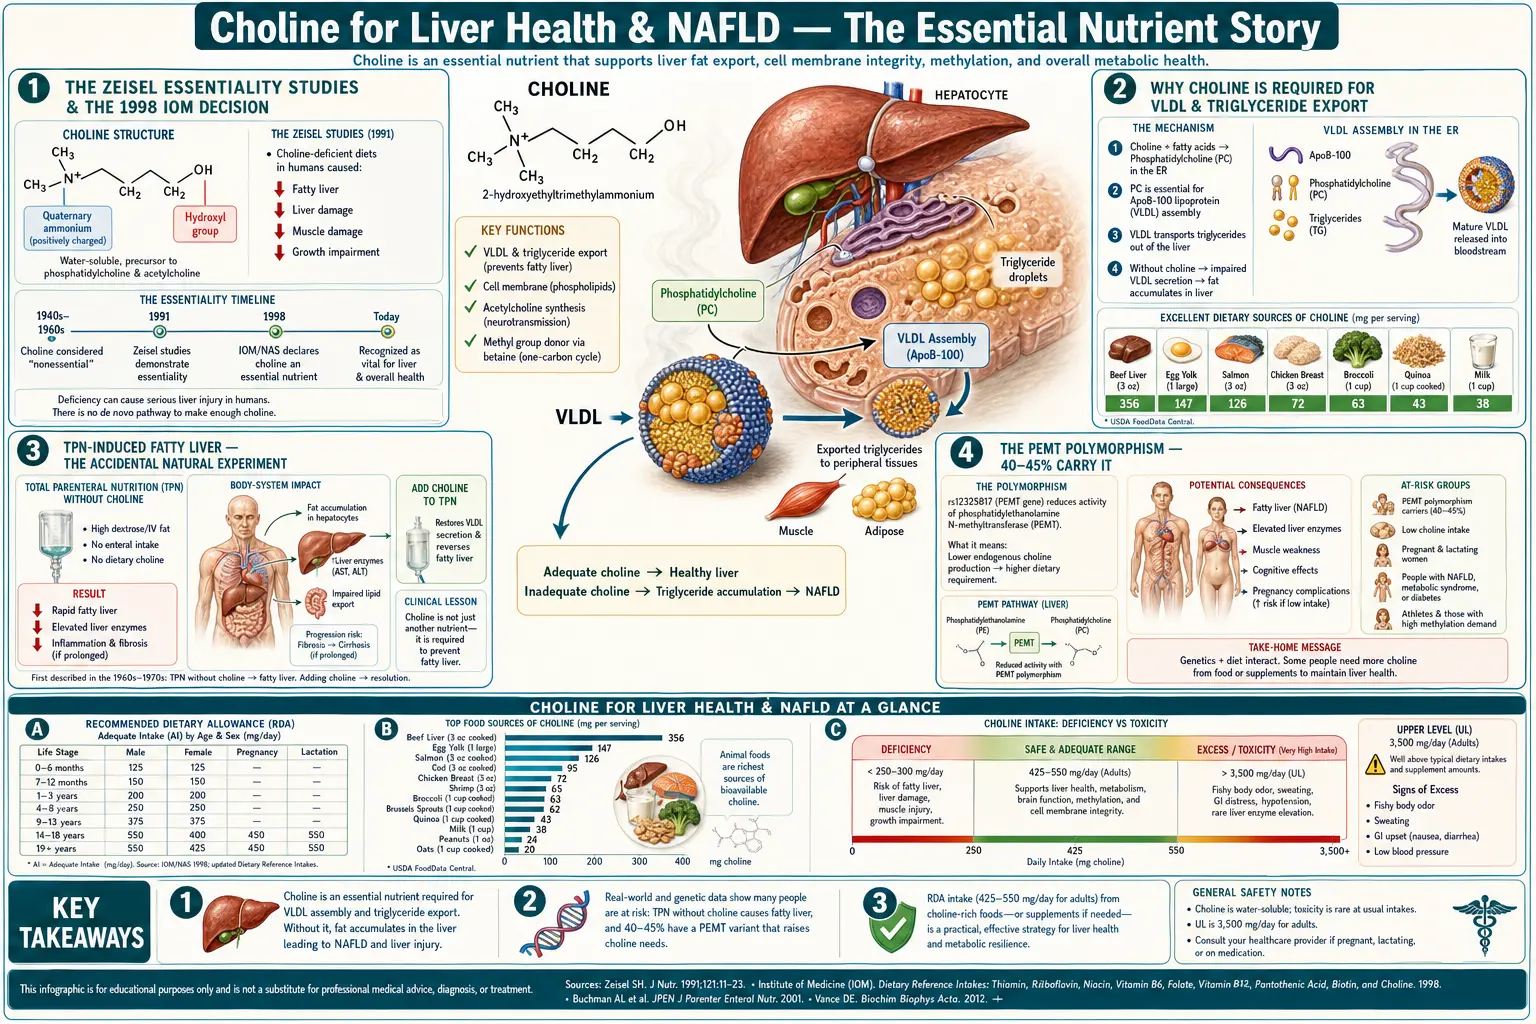
Choline is the only B-vitamin-adjacent nutrient whose essentiality in humans was definitively established by inducing — and then reversing — liver damage in controlled feeding studies. Steven Zeisel's 1991 study at UNC showed that healthy men fed a choline-deficient diet for 3 weeks developed a rise in the liver enzyme alanine aminotransferase (ALT), and a larger 2007 feeding study from the same group found fatty liver or muscle damage in most men and postmenopausal women deprived of choline, with normal organ function restored when choline was added back. This led directly to the 1998 Institute of Medicine recognition of choline as an essential nutrient with an adequate intake of 425 mg/day (women) and 550 mg/day (men). The mechanism is elegant: without choline, the liver cannot package very-low-density-lipoprotein (VLDL) and triglycerides accumulate within hepatocytes — non-alcoholic fatty liver disease (NAFLD) by induction. This deep-dive walks through the science, the PEMT gene variant that raises some people's choline needs, and where phosphatidylcholine fits alongside milk thistle, N-acetylcysteine (NAC), and TUDCA in the integrative liver-support stack.
Table of Contents
- The Zeisel Essentiality Studies & The 1998 IOM Decision
- Why Choline Is Required for Very-Low-Density Lipoprotein & Triglyceride Export
- TPN-Induced Fatty Liver — The Accidental Natural Experiment
- PEMT Gene Variants and Choline Needs
- Postmenopausal Loss of Estrogen-Mediated Synthesis
- Choline Intake & Non-Alcoholic Fatty Liver Disease Risk in Epidemiological Data
- Phosphatidylcholine Supplementation Trials
- Where Choline Fits in the Liver-Support Stack
- Amounts Described in Practice
- Cautions Specific to Liver Use
- Key Research Papers
- Connections
- Featured Videos
The Zeisel Essentiality Studies & The 1998 IOM Decision
Until the late 1980s, choline was considered "semi-essential" — useful, dietary, but not a true essential nutrient because the liver can synthesize choline de novo via the phosphatidylethanolamine N-methyltransferase (PEMT) pathway. This view shifted because of a series of controlled feeding studies conducted by Steven Zeisel and colleagues at the University of North Carolina in the early 1990s.
Zeisel's 1991 experiment: healthy male volunteers were hospitalized and fed a semisynthetic diet with no choline, plus 500 mg/day of choline, for one week. They were then randomly split into a group that kept receiving choline and a group that received none for three more weeks; in the fifth week all received choline again. A later study from the same group (Fischer et al., 2007) fed 57 adults less than 50 mg/day of choline — well below the eventual 550 mg/day adequate intake — for up to 42 days and tracked liver fat by magnetic resonance imaging (MRI).
What they found:
- Zeisel 1991: in the choline-deficient group, serum alanine aminotransferase (ALT) rose steadily from a mean of 0.42 to 0.62 µkat/L over the 3 weeks, with no such change in the control group; other tests of liver and kidney function were unchanged
- Zeisel 1991: plasma choline and phosphatidylcholine fell about 30%, and serum cholesterol fell about 15%, in the deficient group
- Fischer 2007: 77% of men and 80% of postmenopausal women developed fatty liver or muscle damage, versus 44% of premenopausal women
- Fischer 2007: organ function returned to normal when choline was added back to the diet; 6 men developed these signs even at 550 mg/day, the adequate intake
This was the clean demonstration that humans, like the long-studied rodent models, develop liver disease on choline-deficient diets — meaning endogenous PEMT synthesis is insufficient to meet requirements. In 1998, the Institute of Medicine's Food and Nutrition Board reviewed Zeisel's work alongside the rodent and primate literature and formally classified choline as an essential nutrient with the following adequate intake values:
- Adult men: 550 mg/day
- Adult women: 425 mg/day
- Pregnancy: 450 mg/day
- Lactation: 550 mg/day
- Tolerable upper limit: 3,500 mg/day
The IOM also explicitly noted that the Adequate Intake (AI) values were conservative — based on the minimum needed to prevent liver dysfunction in healthy young adults — and that optimal intake for other indications (pregnancy, postmenopausal women) was likely substantially higher. Despite this 1998 recognition, choline has remained largely off the public-health radar; the U.S. Department of Agriculture (USDA) Dietary Guidelines do not emphasize it, prenatal vitamins underdose it, and only about 8% of US adults meet the Adequate Intake (Wallace & Fulgoni 2017).
Why Choline Is Required for Very-Low-Density Lipoprotein & Triglyceride Export
The mechanism by which choline deficiency causes fatty liver is both elegant and unforgiving. To understand it, you have to follow a triglyceride molecule from its synthesis in the hepatocyte to its export.
- Glucose (from carbohydrate intake) and fatty acids (from diet, lipolysis, or de novo lipogenesis) enter the hepatocyte and are esterified into triacylglycerols (triglycerides) on the smooth endoplasmic reticulum.
- For the liver to export those triglycerides to peripheral tissues (adipose for storage, muscle for oxidation), it must package them into very-low-density-lipoprotein (VLDL) particles.
- Very-low-density lipoprotein is a spherical lipoprotein with a hydrophobic triglyceride core and a hydrophilic surface coat consisting of phosphatidylcholine, free cholesterol, and apolipoprotein B-100.
- Phosphatidylcholine is the dominant phospholipid in the very-low-density lipoprotein surface coat — roughly 70-75% of total surface phospholipid mass. The surface coat is the structural prerequisite for the particle to be secreted from the hepatocyte into the bloodstream.
- Without sufficient choline (and therefore insufficient phosphatidylcholine), very-low-density lipoprotein assembly stalls. Triglycerides accumulate intracellularly because they cannot be exported. The hepatocyte fills with fat droplets — the histological signature of steatosis.
This is the unifying mechanism behind every category of choline-deficiency-induced fatty liver: TPN-induced (no oral intake, no dietary choline), alcohol-induced (alcohol depletes hepatic S-adenosylmethionine (SAMe) and choline pools), genetic (PEMT polymorphisms reducing endogenous synthesis), and now — in the modern epidemiology — ordinary dietary inadequacy in a population that doesn't eat eggs or organ meats.
The pharmacological inverse is also true: in animal models of methionine-choline-deficient (MCD) diets, repletion with phosphatidylcholine restores very-low-density lipoprotein assembly and reverses steatosis. This is the mechanistic basis for using polyenylphosphatidylcholine (PPC) as a hepatoprotective intervention in clinical hepatology (the original Lieber work on alcoholic liver disease used PPC for this reason).
TPN-Induced Fatty Liver — The Accidental Natural Experiment
One of the cleanest demonstrations of choline's essentiality came from an accidental experiment in the hospital setting: total parenteral nutrition (TPN). In the 1970s and 1980s, when TPN became standard for patients who could not eat (post-bowel surgery, severe Crohn's, short bowel syndrome, intensive care unit (ICU) on long-term ventilation), an unexpected complication emerged: many of these patients developed progressive hepatic steatosis, elevated liver enzymes, and in some cases overt liver failure within weeks of starting TPN.
The TPN formulations of that era contained adequate calories, protein, glucose, lipid, vitamins, and minerals — but they did NOT contain choline, because choline was not yet recognized as essential. Investigators (notably Alan Buchman at UCLA in the early 1990s) noted that the TPN-induced steatosis pattern was indistinguishable from the rodent choline-deficiency model. The natural experiment: add choline back to the TPN solution and see what happens.
Buchman's 1995 study of four patients who had been on TPN for about 10 years found that:
- The patients had low plasma free choline and hepatic steatosis on computed tomography (CT)
- Adding 1 to 4 grams of choline chloride daily to the TPN solution for 6 weeks brought plasma free choline into the normal range within 1 week
- The steatosis resolved completely on CT, with liver density significantly improved by week 2
- Steatosis returned in one patient after 10 weeks back on choline-free TPN
The clinical implication was twofold: TPN formulations need choline — yet a 2024 review states that current TPN solutions still interrupt choline supply and calls for choline formulations suitable to be added to them (Bernhard et al., 2024); and choline is genuinely essential in the operational sense that humans cannot synthesize enough endogenously to compensate for zero dietary intake.
The TPN natural experiment also illuminated something important about the homeostatic model: people who eat normally have considerable dietary buffering, and the consequences of marginal deficiency may take years to manifest. People who eat nothing reveal the bottom-line essentiality within weeks.
PEMT Gene Variants and Choline Needs
The liver synthesizes some choline endogenously via the phosphatidylethanolamine N-methyltransferase (PEMT) enzyme. PEMT methylates phosphatidylethanolamine to phosphatidylcholine, consuming three molecules of S-adenosylmethionine (SAMe) per molecule of phosphatidylcholine produced. This is the largest single consumer of methyl groups in the human body — more than DNA methylation, more than creatine synthesis, more than neurotransmitter methylation.
da Costa et al. (2006) fed 57 adults a low-choline diet until they developed organ dysfunction or for up to 42 days, and tested common single-nucleotide polymorphisms (SNPs) in choline-metabolism genes. The variant that mattered was in the promoter region of the PEMT gene, -744 G>C (rs12325817): 18 of 23 carriers of the C allele (78%) developed organ dysfunction on the low-choline diet (odds ratio 25). A variant in the PEMT coding region, rs7946, was not associated with susceptibility to choline deficiency. Two variants in the choline dehydrogenase (CHDH) gene also mattered: rs9001 was protective and rs12676 raised susceptibility.
Carriers of the rs12325817 C allele therefore appear to need more dietary choline than non-carriers.
Consumer genetic tests, read through third-party interpretation services, report PEMT genotypes, including rs12325817. In a carrier who has elevated liver enzymes or fatty liver on imaging, low choline intake is one of the possible causes.
Postmenopausal Loss of Estrogen-Mediated Synthesis
The PEMT enzyme is regulated by estrogen — specifically, the PEMT gene promoter contains an estrogen response element, and estradiol upregulates PEMT transcription. This means that premenopausal women have higher endogenous choline synthesis capacity than men or postmenopausal women, which partly explains why the IOM AI is lower for women (425 mg) than men (550 mg).
The implication for postmenopausal women: estrogen levels drop by 80-90%; PEMT activity drops correspondingly; endogenous choline synthesis is no longer adequate; and dietary choline requirements rise to the male range (550 mg/day) or higher if a PEMT polymorphism is present. This is exactly the population that:
- Has the highest incidence of non-alcoholic fatty liver disease progression to non-alcoholic steatohepatitis (NASH)
- Is most likely to develop "cryptogenic" elevated liver enzymes without an obvious cause
- Often follows a calorie-restricted diet that further reduces choline intake
- Is rarely screened for dietary choline adequacy
Resseguie et al. (2007) showed in human and mouse liver cells that estrogen (17-beta-estradiol) increases PEMT gene expression, protein and enzyme activity, and the Fischer et al. (2007) feeding study found organ dysfunction in 80% of postmenopausal women but only 44% of premenopausal women on a choline-deficient diet. On this basis, practitioners describe hormone replacement therapy (HRT, estrogen) as possibly restoring part of PEMT activity after menopause.
Practitioners who focus on choline describe checking dietary choline in postmenopausal women with fatty liver on imaging, elevated liver enzymes, or unexplained fatigue. The amounts they describe are 500-1000 mg/day of supplemental choline, or 2 eggs a day plus a phosphatidylcholine supplement — well under the 3,500 mg/day upper limit.
Choline Intake & Non-Alcoholic Fatty Liver Disease Risk in Epidemiological Data
Beyond the controlled feeding studies, the epidemiological evidence linking low dietary choline to non-alcoholic fatty liver disease has accumulated steadily:
- Yu et al. (2014) — a cross-sectional analysis of 56,195 Chinese adults (fatty liver by self-reported physician diagnosis) found that people in the highest fifth of choline intake had lower odds of fatty liver than those in the lowest fifth (odds ratio 0.68 in women, 0.75 in men). After further adjustment for metabolic disease and body-mass index (BMI), the association was no longer significant (0.88 and 0.85); it remained only in normal-weight women (odds ratio 0.72).
- Guerrerio et al. (2012) — a cross-sectional study of 664 people with biopsy-proven non-alcoholic fatty liver disease in the NASH Clinical Research Network found that postmenopausal women with deficient choline intake (below 50% of the Adequate Intake) had worse liver scarring (fibrosis). Choline intake was not identified as a contributor to disease severity in children, men, or premenopausal women.
- Fischer et al. (2007) — healthy adults placed on choline-deficient diets developed fatty liver or muscle damage (77% of men, 80% of postmenopausal women, 44% of premenopausal women). The authors link the premenopausal protection to estrogen, which up-regulates PEMT synthesis.
- Wallace & Fulgoni (2017) — NHANES 2009-2014 data show that only about 8% of US adults meet the Adequate Intake for choline; adults who eat eggs were far more likely to meet it than those who do not (57% vs 2%).
The epidemiology has limits — choline intake correlates with overall diet quality, with egg consumption (which carries other associations), and with socioeconomic factors. But the mechanistic story is strong enough, and the controlled feeding data direct enough, that the epidemiological signal is best read as confirming the laboratory science rather than as standalone evidence.
Choline status, PEMT genotype and choline supplementation are not part of the routine non-alcoholic fatty liver disease workup in most hepatology practice. Researchers in this field argue that they belong there, especially for postmenopausal women, people on long-term TPN, and carriers of PEMT risk variants documented by consumer genetic testing.
Phosphatidylcholine Supplementation Trials
The most directly liver-targeted form of choline is phosphatidylcholine (commonly sold as "PC" or lecithin). Polyenylphosphatidylcholine (PPC) — phosphatidylcholine enriched in polyunsaturated fatty acids, sold as a polyenylphosphatidylcholine preparation — has been studied in liver disease for decades, primarily in Eastern European and Russian hepatology.
Charles Lieber's group at the Bronx Veterans Affairs Medical Center and Mount Sinai School of Medicine published the main human trial in alcoholic liver disease (Lieber et al., 2003): a 2-year trial at 20 Veterans Affairs centers in 789 heavy drinkers (averaging 16 drinks a day) with liver fibrosis on biopsy. PPC did not differ from placebo in its effect on fibrosis progression. Alcohol intake unexpectedly fell in both groups to about 2.5 drinks a day, and even so about one patient in five advanced at least one fibrosis stage. A trend favoring PPC was seen for liver enzymes (transaminases) and bilirubin at some time points in subgroups (hepatitis C-positive drinkers or heavy drinkers).
In non-alcoholic fatty liver disease/non-alcoholic steatohepatitis specifically:
- Several open-label studies have shown that phosphatidylcholine 1.8-3.0 g/day for 12-24 weeks reduces alanine aminotransferase, aspartate aminotransferase, and gamma-GT
- Magnetic resonance imaging/ultrasound measures of hepatic fat content decrease with treatment
- The effect size is modest but consistent across studies
- PPC is well-tolerated even at high doses
PPC is not approved by the U.S. Food and Drug Administration (FDA) for non-alcoholic fatty liver disease. Integrative practitioners include it in liver-support combinations, particularly for people with documented choline deficiency or a PEMT risk variant. Sunflower-derived phosphatidylcholine is the common soy-free source.
Where Choline Fits in the Liver-Support Stack
Integrative liver support typically combines several hepatoprotective compounds with non-overlapping mechanisms. Choline / phosphatidylcholine fits alongside:
- Milk Thistle (silymarin) — flavonolignan complex that stabilizes hepatocyte membranes, supports glutathione, and has anti-fibrotic effects. The canonical European herbal liver remedy.
- N-Acetylcysteine — glutathione precursor; the gold-standard antidote for acetaminophen overdose; broader hepatoprotective effects in non-alcoholic fatty liver disease and chronic liver disease.
- Phosphatidylcholine (PPC / lecithin) — this article's topic; the very-low-density lipoprotein substrate and membrane substrate.
- TUDCA (tauroursodeoxycholic acid) — bile acid; reduces ER stress and apoptosis in hepatocytes; particularly useful in cholestatic patterns.
- Alpha Lipoic Acid — mitochondrial cofactor; heavy metal chelator; broad antioxidant. Particularly useful when non-alcoholic fatty liver disease coexists with metabolic syndrome.
- Vitamin E — in the PIVENS trial (Sanyal 2010), 800 international units (IU)/day for 96 weeks improved biopsy-proven non-alcoholic steatohepatitis in 43% of adults without diabetes versus 19% on placebo, with less liver fat and inflammation but no improvement in fibrosis scores.
- Vitamin D — low 25-OH-vitamin D correlates with non-alcoholic fatty liver disease severity; repletion is uncontroversial.
The mechanistic logic for combining: silymarin stabilizes membranes, N-acetylcysteine supports glutathione (defends against oxidative damage), phosphatidylcholine supplies the substrate for very-low-density lipoprotein and membrane repair, TUDCA reduces ER stress, ALA addresses mitochondrial dysfunction, and vitamin E sequesters lipid peroxides. None of these in isolation is curative, but the combination addresses multiple parallel mechanisms.
Weight loss, fewer refined carbohydrates and exercise are the foundation of non-alcoholic fatty liver disease care. Two drugs now have FDA approval, used along with diet and exercise, for non-alcoholic steatohepatitis (now also called metabolic dysfunction-associated steatohepatitis, MASH) with moderate to advanced liver scarring: resmetirom on 14 March 2024, the first such treatment (FDA announcement), and semaglutide under accelerated approval on 15 August 2025 (FDA announcement). Integrative combinations described by practitioners typically include milk thistle, N-acetylcysteine, phosphatidylcholine, and Vitamin E with vitamin D repletion if deficient.
Amounts Described in Practice
Fatty liver (documented or suspected Non-Alcoholic Fatty Liver Disease)
- Phosphatidylcholine (sunflower lecithin) 1200-2400 mg/day, taken in divided doses with meals
- or choline bitartrate 500-1000 mg/day (cheaper, modestly less liver-targeted)
- or 2 whole eggs daily (~300 mg choline plus phosphatidylcholine)
- Practitioners often combine it with milk thistle 200-400 mg standardized to 80% silymarin twice daily
- and with N-acetylcysteine 600-1200 mg/day for glutathione support
- Liver enzymes are commonly rechecked at 3 months
Carriers of the PEMT rs12325817 risk variant
- Practitioners describe 700-900 mg/day total choline intake (vs the 550 mg male Adequate Intake)
- Eggs are the food source most often described (1 egg = ~147 mg choline)
- For people who do not eat eggs, phosphatidylcholine or bitartrate supplements supply it
- Methylation co-factors (methylated B12, methylfolate) are sometimes added, because PEMT-driven synthesis uses a lot of S-adenosylmethionine
Postmenopausal women
- The intake practitioners describe is 550 mg/day, the Adequate Intake for adult men
- Liver enzymes are part of routine annual blood work
- If non-alcoholic fatty liver disease develops, the same amounts as above are described
- Hormone replacement therapy raises estrogen, which increases PEMT expression in liver cells (Resseguie 2007); this liver effect is one of several effects of HRT
People on long-term TPN or with severe malabsorption
- Current TPN solutions lack choline, according to a 2024 review that calls for choline formulations suitable to be added to them
- Enteral phosphatidylcholine is an option when any gastrointestinal (GI) absorption is possible
- Liver function tests are commonly monitored at least monthly
Cautions Specific to Liver Use
- Trimethylaminuria (fish odor syndrome / TMAU) — rare genetic condition where high choline intake produces strong fish-like body odor due to inability to oxidize TMA to trimethylamine N-oxide (TMAO). In TMAU, high-dose choline supplements make the odor worse, and limiting dietary choline is part of its usual management.
- Active liver failure — in fulminant hepatitis or end-stage cirrhosis, choline metabolism itself may be impaired.
- Trimethylamine N-oxide concerns — lecithin and bitartrate that reach the colon feed TMA-producing bacteria. Phosphatidylcholine is absorbed more in the upper gut than bitartrate, so less of it reaches these bacteria. See the trimethylamine N-oxide deep dive.
- Soy lecithin sensitivity — some lecithin supplements are soy-derived. Sunflower lecithin is the modern alternative; both work biochemically.
- Drug interactions — bile-acid sequestrants (cholestyramine, colesevelam) can reduce phosphatidylcholine absorption when taken concurrently; a 4-hour gap is the spacing usually described.
- Gastrointestinal side effects — nausea, bloating, fishy breath odor at high doses (>3 g/day). Lower doses split into 3-4 daily doses are described as easing them.
- Methylation co-factor depletion — high-dose choline supplementation drives the methionine cycle hard. Folate and B12 are the co-factors involved; practitioners sometimes order methylation panel tests in people with symptoms.
Key Research Papers
- Zeisel SH et al. (1991). Choline, an essential nutrient for humans. FASEB Journal. — PubMed PMID: 2010061
- da Costa KA et al. (2006). Choline deficiency increases lymphocyte apoptosis and DNA damage in humans. American Journal of Clinical Nutrition. — PubMed PMID: 16825685
- Buchman AL et al. (1995). Choline deficiency: a cause of hepatic steatosis during parenteral nutrition that can be reversed with intravenous choline supplementation. Hepatology. — PubMed PMID: 7590654
- Fischer LM et al. (2007). Sex and menopausal status influence human dietary requirements for the nutrient choline. American Journal of Clinical Nutrition. — PubMed PMID: 17490963
- Yu D et al. (2014). Higher dietary choline intake is associated with lower risk of nonalcoholic fatty liver in normal-weight Chinese women. Journal of Nutrition. — PubMed PMID: 25320186
- Guerrerio AL et al. (2012). Choline intake in a large cohort of patients with nonalcoholic fatty liver disease. American Journal of Clinical Nutrition. — PubMed PMID: 22338037
- Resseguie M, Song J, Niculescu MD, da Costa KA, Randall TA, Zeisel SH. (2007). Phosphatidylethanolamine N-methyltransferase (PEMT) gene expression is induced by estrogen in human and mouse primary hepatocytes. FASEB Journal. — PubMed PMID: 17456783
- da Costa KA, Kozyreva OG, Song J, Galanko JA, Fischer LM, Zeisel SH. (2006). Common genetic polymorphisms affect the human requirement for the nutrient choline. FASEB Journal. — PubMed PMID: 16816108
- Lieber CS, Weiss DG, Groszmann R, Paronetto F, Schenker S. (2003). II. Veterans Affairs Cooperative Study of polyenylphosphatidylcholine in alcoholic liver disease. Alcoholism: Clinical and Experimental Research. — PubMed PMID: 14634492
- Wallace TC & Fulgoni VL. (2017). Usual choline intakes are associated with egg and protein food consumption in the United States. Nutrients. — PubMed PMID: 28783055
- Bernhard W, Böckmann KA, Minarski M, et al. (2024). Evidence and perspectives for choline supplementation during parenteral nutrition — a narrative review. Nutrients. — PubMed PMID: 38931230
- Sanyal AJ et al. (2010). PIVENS Trial: Pioglitazone, vitamin E, or placebo for nonalcoholic steatohepatitis. NEJM. — PubMed PMID: 20427778
- Vance DE. (2014). Phospholipid methylation in mammals: from biochemistry to physiological function. Biochimica et Biophysica Acta. — PubMed PMID: 24184426
- Zeisel SH & da Costa KA. (2009). Choline: an essential nutrient for public health. Nutrition Reviews. — PubMed PMID: 19906248
PubMed Topic Searches
Connections
- All Vitamins
- Choline Overview
- Choline Benefits Hub
- Beef Liver for Choline
- Choline for Cognition
- Choline for Pregnancy
- Choline & Trimethylamine N-Oxide
- Phosphatidylcholine
- Non-Alcoholic Fatty Liver Disease
- Milk Thistle
- N-Acetylcysteine
- Alpha Lipoic Acid
- Glutathione
- Liver Cleansing
- Vitamin E
- Vitamin D
- Folate (B9)
- Vitamin B12
- Liver Function Tests
- Eggs
- Organ Meats
- Deficiency
- Toxicity
- History
- Sources