⚠ Evidence warning: Clinical trials or other evidence do not support the claims that low choline intake raises homocysteine regardless of folate and vitamin B12 status, and that higher choline intake goes with fewer cardiovascular events or lower all-cause mortality. This page keeps it as a report of what people, websites or other media say.
Choline, Cardiovascular Health & the Trimethylamine N-Oxide (TMAO) Controversy
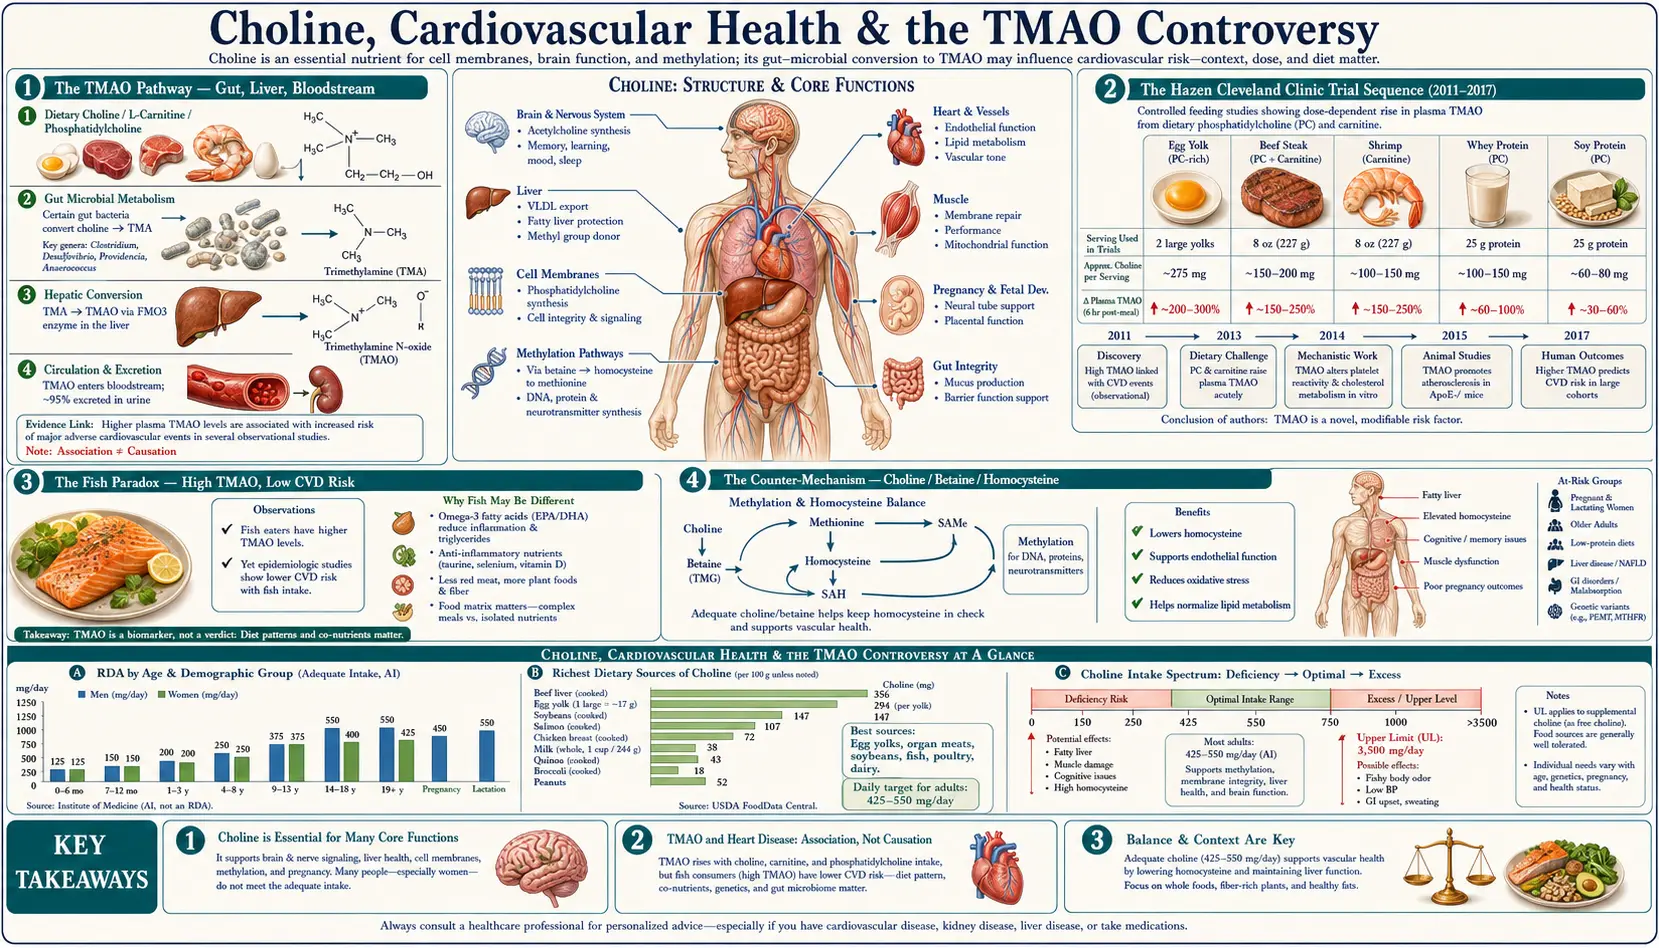
The trimethylamine N-oxide (TMAO) controversy is the most contentious topic in choline nutrition. Stanley Hazen's Cleveland Clinic team proposed in 2011 (Nature) and 2013 (New England Journal of Medicine, NEJM) that gut bacteria convert dietary choline to trimethylamine (TMA), which the liver then oxidizes to trimethylamine N-oxide (TMAO), and that elevated plasma trimethylamine N-oxide accelerates atherosclerosis. The mechanistic story is plausible, and the observational data show trimethylamine N-oxide-CVD associations. But the epidemiology is conflicting: fish — especially deep-sea fish — produces the highest plasma trimethylamine N-oxide elevations of any food, yet fish consumption is associated with REDUCED cardiovascular risk. Choline-rich populations who get their choline from eggs and meat (and who have healthy gut microbiomes) don't obviously have higher cardiovascular disease (CVD) than choline-deficient populations. This deep-dive walks through both sides of the debate, the methylation-and-homocysteine axis that probably outweighs the trimethylamine N-oxide signal in choline-replete individuals, and what the research shows for people with heart or kidney disease.
Table of Contents
- The Trimethylamine N-Oxide Pathway — Gut, Liver, Bloodstream
- The Hazen Cleveland Clinic Trial Sequence (2011-2017)
- The Fish Paradox — High Trimethylamine N-Oxide, Low Cardiovascular Disease Risk
- The Counter-Mechanism — Choline / Betaine / Homocysteine
- What the Choline / Cardiovascular Disease Meta-Analyses Actually Show
- The Gut Microbiome Matters More Than Choline Intake
- Choline Deficiency Worsens Dyslipidemia (the Forgotten Mechanism)
- Why Trimethylamine N-Oxide Is Probably a Marker, Not a Cause
- What the Research Shows for People With Heart or Kidney Disease
- Cautions Specific to Cardiovascular Use
- Key Research Papers
- Connections
- Featured Videos
The Trimethylamine N-Oxide Pathway — Gut, Liver, Bloodstream
Trimethylamine N-oxide (TMAO) is produced via a two-organism, two-organ pathway:
- Dietary precursor — choline (in eggs, liver, meat, fish), phosphatidylcholine (in lecithin supplements and food), L-carnitine (in red meat), and betaine (in beets, spinach, wheat germ) all contain or generate trimethylamine moieties.
- Gut bacterial conversion — specific bacterial taxa in the colon (most notably members of the Firmicutes phylum, including Anaerococcus hydrogenalis, Clostridium asparagiforme, Edwardsiella tarda, Streptococcus sanguinis, and others) express the choline TMA-lyase (CutC/CutD) and L-carnitine TMA-lyase (CntA/CntB) enzymes that cleave the trimethylamine moiety from dietary precursors. The free trimethylamine (TMA) is absorbed across the colonic mucosa into the portal circulation.
- Hepatic oxidation — the liver enzyme flavin-containing monooxygenase 3 (FMO3) oxidizes TMA to trimethylamine N-oxide. FMO3 expression varies between individuals; women have higher FMO3 expression than men (regulated by estrogen). The rare genetic loss-of-function of FMO3 causes the inability to oxidize TMA, leading to trimethylaminuria ("fish odor syndrome").
- Circulation — trimethylamine N-oxide enters systemic circulation, where it can be measured in plasma. Normal fasting plasma trimethylamine N-oxide is typically 1-5 µM; postprandial levels rise into the 10-50 µM range after a high-precursor meal; some individuals run chronically elevated above 10 µM.
- Renal excretion — trimethylamine N-oxide is freely filtered and excreted in urine. Chronic kidney disease patients have dramatically elevated trimethylamine N-oxide levels due to impaired excretion (and this is one of the cleanest contexts in which the trimethylamine N-oxide-cardiovascular association may matter clinically).
The key insight: dietary choline does NOT automatically equal trimethylamine N-oxide. The conversion depends on the gut microbiome composition. Two people eating identical choline intakes can have 5-10x different plasma trimethylamine N-oxide levels depending on which bacterial species dominate their colon. This is why the choline-CVD epidemiology is so messy: the dietary exposure is poorly correlated with the proposed mechanistic biomarker.
The Hazen Cleveland Clinic Trial Sequence (2011-2017)
Stanley Hazen and the Cleveland Clinic Lerner Research Institute group have been the principal investigators on the trimethylamine N-oxide-cardiovascular hypothesis. Their work proceeded in steps:
Wang et al. (2011) Nature
The foundational paper. Used metabolomics to identify trimethylamine N-oxide as a circulating metabolite predictive of cardiovascular events in a prospective cohort. Studies in germ-free mice (mice with no gut bacteria) confirmed that dietary choline and gut bacteria are both needed to make trimethylamine N-oxide and to drive cholesterol build-up in immune cells (macrophage foam cells). In mice bred to develop atherosclerosis, suppressing the gut bacteria blocked the extra atherosclerosis caused by dietary choline. Established the gut-bacteria-as-mediator hypothesis.
Tang et al. (2013) NEJM
4,007 patients undergoing elective coronary angiography. Higher trimethylamine N-oxide levels were associated with major adverse cardiac events (death, myocardial infarction (MI), stroke) over 3-year follow-up, even after adjustment for traditional risk factors. Patients in the highest trimethylamine N-oxide quartile had a hazard ratio of 2.54 (95% confidence interval 1.96 to 3.28) for a major adverse cardiovascular event compared with the lowest quartile.
Koeth et al. (2013) Nature Medicine
Demonstrated that L-carnitine (abundant in red meat) is also a TMA-producing dietary substrate. Showed that long-term meat-eaters had higher TMA-producing bacterial capacity than vegetarians, and that omnivores produced more trimethylamine N-oxide than vegans or vegetarians after swallowing L-carnitine, through a gut-bacteria-dependent mechanism.
Zhu et al. (2016) Cell
Showed that trimethylamine N-oxide directly enhances platelet hyperreactivity and thrombosis risk in animal models. This was an important mechanistic step from "trimethylamine N-oxide is a marker" toward "trimethylamine N-oxide is a cause."
Senthong et al. (2016) Journal of the American Heart Association
Confirmed trimethylamine N-oxide as a prognostic marker in patients with peripheral artery disease. In 935 such patients, those in the highest trimethylamine N-oxide quartile had about twice the risk of death from any cause over 5 years compared with the lowest quartile (adjusted hazard ratio 2.06, 95% confidence interval 1.36 to 3.11).
Through this sequence, Hazen's group built a coherent case for trimethylamine N-oxide as both a marker and a contributor to cardiovascular risk. The mechanistic studies have been replicated; the observational associations have been replicated; the platelet-hyperactivity work has been replicated. The case is strong on its own terms.
What the Hazen work has NOT done is run a randomized intervention trial reducing dietary trimethylamine N-oxide precursors (or blocking TMA-lyase pharmacologically) and showing that cardiovascular events drop. That would be the clean causal test, and it has not been performed at adequate scale or duration to settle the debate.
The Fish Paradox — High Trimethylamine N-Oxide, Low Cardiovascular Disease Risk
The single biggest dietary disruption to the trimethylamine N-oxide-causes-CVD story is fish. Deep-sea fish — especially codfish, halibut, and other gadiform species — contain large amounts of pre-formed trimethylamine N-oxide (it is an osmolyte that helps deep-sea fish survive high pressure). In a crossover feeding trial in 40 healthy young men (Cho 2017), a fish meal raised blood and urine trimethylamine N-oxide 46-62 times more than eggs, beef or a fruit control did. Blood levels rose within 15 minutes of eating the fish, which the authors say suggests that trimethylamine N-oxide in food can be absorbed without any processing by gut bacteria.
And yet:
- Fish consumption is consistently associated with REDUCED cardiovascular mortality in epidemiological studies (Mozaffarian, Hu, Iso, Bouzan)
- The American Heart Association (AHA) recommends 2+ servings of fish per week specifically for cardiovascular protection
- The Mediterranean and Japanese-style traditional diets — both high in fish, both high in trimethylamine N-oxide — have among the lowest cardiovascular mortality in the world
- Fish-eating populations don't show the elevated cardiovascular event rates that the trimethylamine N-oxide hypothesis would predict
The standard explanation is that fish provides multiple compounds (eicosapentaenoic acid (EPA), docosahexaenoic acid (DHA), taurine, vitamin D, selenium) that powerfully protect against cardiovascular disease, and that these effects outweigh whatever trimethylamine N-oxide is doing. That is plausible. But it raises a question: if fish-induced trimethylamine N-oxide is being "overwhelmed" by fish's other benefits, it is unclear why a smaller, less dramatic trimethylamine N-oxide elevation from eggs or red meat would matter more.
A second possibility: trimethylamine N-oxide from fish is biologically different from trimethylamine N-oxide from gut-bacterial conversion. Same molecule, but different kinetics, different tissue distribution, different downstream effects. This has not been definitively proved or disproved.
A third possibility: trimethylamine N-oxide is correlated with cardiovascular events but is not causally driving them. The trimethylamine N-oxide-CVD association may reflect underlying renal dysfunction (chronic kidney disease (CKD) patients have very high trimethylamine N-oxide; chronic kidney disease itself is a powerful cardiovascular disease risk factor), or underlying gut dysbiosis (which has many cardiovascular disease-relevant consequences beyond trimethylamine N-oxide), or underlying dietary patterns that we haven't adequately controlled for.
The fish paradox is, in the considered view of many researchers, a strong argument that the trimethylamine N-oxide-CVD relationship is more nuanced than "trimethylamine N-oxide is bad, lower it."
The Counter-Mechanism — Choline / Betaine / Homocysteine
Even if we accept some trimethylamine N-oxide-mediated cardiovascular risk from dietary choline, there is a powerful competing mechanism running in the OPPOSITE direction: choline supports homocysteine disposal through the betaine-homocysteine methyltransferase (BHMT) pathway. Elevated homocysteine is itself a substantial cardiovascular risk factor (endothelial dysfunction, accelerated atherosclerosis, increased thrombotic risk).
The pathway:
- Choline is oxidized in the liver and kidneys to betaine (trimethylglycine)
- Betaine serves as a methyl donor for the BHMT enzyme, which converts homocysteine back to methionine
- This pathway operates in parallel with the folate-dependent methionine synthase pathway
- When folate or B12 intake is marginal, the choline-betaine pathway becomes the primary route of homocysteine disposal
The clinical implication: choline DEFICIENCY raises homocysteine; choline REPLETION lowers homocysteine. The cardiovascular benefit of normalizing homocysteine likely outweighs any trimethylamine N-oxide cost from the same dietary choline in most individuals.
Olthof et al. (2005) tested this directly: in a crossover trial, 26 healthy men with mildly raised homocysteine took about 2.6 g of choline a day as phosphatidylcholine for 2 weeks, and their fasting plasma homocysteine fell 18% compared with placebo. This is a meaningful cardiovascular biomarker movement. An earlier trial by the same group (Olthof 2003) gave betaine itself: 1.5, 3 and 6 g a day for 6 weeks lowered fasting homocysteine by 12%, 15% and 20% compared with placebo.
Low choline intake correlates with elevated homocysteine independent of folate / B12 status.
The competing mechanisms are not symmetrical. The trimethylamine N-oxide mechanism applies disproportionately to people with TMA-producing bacteria, with intact FMO3, and presumably with some underlying vascular pathology that makes them sensitive to trimethylamine N-oxide's thrombotic effects. The choline-betaine-homocysteine mechanism applies to everyone whose methylation cycle depends on adequate substrate — which is the entire population, but particularly those with methylenetetrahydrofolate reductase (MTHFR) polymorphisms (~40-45% of population).
What the Choline / Cardiovascular Disease Meta-Analyses Actually Show
If trimethylamine N-oxide drives cardiovascular risk in proportion to dietary choline intake, you would expect epidemiological studies to consistently show: higher choline intake = higher cardiovascular event rates. What the meta-analyses actually show is more equivocal:
- Meyer & Shea (2017) systematic review and meta-analysis of dietary choline / betaine and cardiovascular disease: no consistent association between higher choline intake and increased cardiovascular disease events. It pooled 6 prospective studies with 184,010 participants and 18,076 new cardiovascular events. New cardiovascular disease was not linked to choline intake (relative risk 1.00, 95% confidence interval 0.98 to 1.02) or betaine intake (relative risk 0.99), and the result was the same for coronary heart disease, stroke and total cardiovascular disease. Only two studies had data on cardiovascular death: together they showed no link (relative risk 1.09, 0.89 to 1.35), but one of the two found a higher risk and the two disagreed strongly, so the authors call for more research on choline and cardiovascular death.
- Nagata et al. (2015) Japanese cohort of 13,355 men and 15,724 women in Takayama, followed for 16 years: no significant association between choline intake and cardiovascular disease death in men or women. Higher betaine intake went with fewer coronary heart disease (CHD) deaths in men only, with no clear trend across intake levels.
- Bidulescu et al. (2007) Atherosclerosis Risk in Communities (ARIC) cohort of 14,430 middle-aged adults, followed about 14 years (1,072 coronary heart disease events): no significant association between choline intake and coronary heart disease. The highest choline quartile had a slightly, non-significantly higher risk (hazard ratio 1.22, 0.91 to 1.64), and the authors concluded that higher choline and betaine intakes "were not protective".
- Dalmeijer et al. (2008) Dutch cohort of 16,165 women aged 49-70, followed a median of 97 months (717 cardiovascular cases): neither choline intake (hazard ratio 1.04, 0.71 to 1.53, highest versus lowest quartile) nor betaine intake (0.90, 0.69 to 1.17) was associated with cardiovascular disease.
Some studies showed inverse associations (more choline = lower events), some showed null associations, a few showed weak positive associations. The highest tertile of choline intake has been reported to have lower all-cause mortality.
The pattern: at the epidemiological level, dietary choline does NOT show the consistent positive association with cardiovascular events that the trimethylamine N-oxide hypothesis would predict. In these studies the signal is null. If anything, the signal is null or weakly inverse.
The most defensible interpretation: trimethylamine N-oxide may be a real cardiovascular risk factor in some contexts (chronic kidney disease patients, individuals with specific microbiome compositions, individuals with underlying vascular pathology), but at the population level, dietary choline within reasonable intake ranges does NOT translate to detectable cardiovascular harm. The competing benefits (homocysteine lowering, hepatic protection, cell membrane integrity, cholinergic neurotransmission) likely outweigh whatever trimethylamine N-oxide cost there is.
The Gut Microbiome Matters More Than Choline Intake
If trimethylamine N-oxide is the relevant intermediate, then the variable that matters is gut microbiome composition — specifically, whether your colon harbors TMA-producing bacteria in significant abundance. This is partly modifiable:
- Vegetarians and vegans have lower abundance of TMA-producing bacteria (because long-term low choline / carnitine intake selects against them). In the Koeth 2013 study, vegans and vegetarians given L-carnitine (the trimethylamine source in red meat) produced less trimethylamine N-oxide from it than omnivores did.
- High dietary fiber shifts microbiome composition toward Bacteroidetes and away from TMA-producing Firmicutes
- Mediterranean diet (high fiber, polyphenols, fermented foods, olive oil) is associated with lower trimethylamine N-oxide production capacity
- Probiotics and fermented foods may displace TMA-producing taxa, though the evidence is preliminary
- Antibiotics transiently lower trimethylamine N-oxide production capacity (and have been used as a research tool to demonstrate the gut-bacterial mediation)
- The bacteria mix differs between people — in the Cho 2017 feeding trial, the men whose urine trimethylamine N-oxide rose 20% or more after eggs and beef had more Firmicutes than Bacteroidetes and less gut-bacteria diversity, which the authors read as trimethylamine N-oxide production depending on each person's gut microbiome
Eggs tested directly. A 2025 meta-analysis of six randomized trials of egg eating (Aryaeian and colleagues; five of the trials measured trimethylamine N-oxide) found no significant effect of eggs on blood trimethylamine N-oxide (mean difference −0.08, 95% confidence interval −0.47 to 0.32), and rated the certainty of that evidence as moderate.
What follows from this: if trimethylamine N-oxide from dietary choline matters, gut microbiome composition (shaped by diet, fiber and fermented foods) probably matters more than choline intake itself. Choline restriction has many downsides (cognitive, hepatic, methylation, prenatal); gut microbiome optimization has many upsides beyond just trimethylamine N-oxide.
Some clinicians use plasma trimethylamine N-oxide testing (offered by commercial laboratories) to identify patients who are high trimethylamine N-oxide producers. For those patients, some practitioners describe more gut microbiome work and a switch to choline forms said to be absorbed mostly in the upper gut (alpha-glycerylphosphorylcholine (alpha-GPC) and cytidine diphosphate-choline (CDP-choline, citicoline)) rather than forms that reach the colon (bitartrate, lecithin). Alpha-GPC has its own stroke finding in a very large Korean cohort, described in the section on heart and kidney disease below.
Choline Deficiency Worsens Dyslipidemia (the Forgotten Mechanism)
An under-appreciated cardiovascular dimension: choline DEFICIENCY directly worsens dyslipidemia through the very-low-density lipoprotein (VLDL) mechanism described in the Liver & non-alcoholic fatty liver disease (NAFLD) deep dive. Without adequate choline / phosphatidylcholine, the liver cannot properly export triglycerides as very-low-density lipoprotein, leading to:
- Hepatic triglyceride accumulation (non-alcoholic fatty liver disease)
- Disturbed plasma lipid profile (elevated triglycerides, sometimes elevated apolipoprotein B (apoB))
- The atherogenic lipid pattern associated with metabolic syndrome
- Non-alcoholic fatty liver disease itself is now recognized as an independent cardiovascular risk factor
So the choline-cardiovascular relationship is not unidirectional. Adequate choline:
- Lowers homocysteine (cardioprotective)
- Supports very-low-density lipoprotein assembly and prevents non-alcoholic fatty liver disease-driven dyslipidemia (cardioprotective)
- Provides phosphatidylcholine for membrane integrity in vascular endothelium (cardioprotective)
- BUT — in susceptible individuals with TMA-producing microbiomes — raises trimethylamine N-oxide (possibly cardiotoxic)
The net effect for any individual depends on their methylation status, their lipid profile, their microbiome composition, their renal function, and their underlying vascular health. For most healthy individuals eating a varied diet, the net effect of adequate choline intake is almost certainly cardioprotective.
Why Trimethylamine N-Oxide Is Probably a Marker, Not a Cause
Several lines of evidence suggest that trimethylamine N-oxide is more likely a marker of cardiovascular risk than a direct cause:
- Renal function confounding — trimethylamine N-oxide is renally excreted; chronic kidney disease patients have very high trimethylamine N-oxide; chronic kidney disease itself is a powerful cardiovascular disease risk factor. Much of the trimethylamine N-oxide-CVD association may simply reflect impaired renal clearance in patients who already have cardiovascular disease.
- The fish paradox — fish raises trimethylamine N-oxide most dramatically but is cardioprotective.
- The null choline-intake-CVD epidemiology — dietary choline intake doesn't consistently predict cardiovascular disease events, even though it should if trimethylamine N-oxide is the mediator.
- The intervention gap — no large randomized controlled trial (RCT) has shown that lowering trimethylamine N-oxide (by any means) reduces cardiovascular events. The mechanistic story is plausible; the clinical proof is absent.
- Confounding by underlying gut dysbiosis — trimethylamine N-oxide-producing microbiomes are correlated with other adverse microbiome features (inflammation, increased intestinal permeability, metabolic endotoxemia) that have their own cardiovascular disease implications. Trimethylamine N-oxide may simply be one measurable marker of an unhealthy gut ecosystem.
A 2025 review of the reviews. An umbrella review by Obeid and colleagues examined 27 published systematic reviews and meta-analyses on blood trimethylamine N-oxide and stroke, cardiovascular disease, death and related kidney outcomes. Most of them found higher trimethylamine N-oxide in people who had these conditions. But the underlying studies were done in people who already had several risk factors and did not adequately account for confounders; prospective studies that measured trimethylamine N-oxide in healthy people and then followed them for disease were "entirely absent"; and no clinical trial has shown whether lowering trimethylamine N-oxide reduces these diseases. The authors found serious flaws in the methods of most of the reviews, giving "critically low confidence in the results".
The minority view (held by Hazen and collaborators) is that trimethylamine N-oxide is causal and that interventions should target the gut bacterial CutC/CutD enzyme or the FMO3 hepatic conversion step. Several small-molecule TMA-lyase inhibitors are in early development. Clinical proof remains pending.
The mainstream view, particularly in cardiology and integrative medicine, is more measured: trimethylamine N-oxide is an interesting biomarker that may help stratify cardiovascular risk in some patients, but it does not justify avoidance of choline-rich foods or restriction of choline supplementation in patients who would otherwise benefit (non-alcoholic fatty liver disease patients, pregnant women, cognitively impaired patients).
What the Research Shows for People With Heart or Kidney Disease
People with established cardiovascular disease or major cardiovascular risk factors
- The Adequate Intake (AI) for choline set by the Institute of Medicine is 550 mg a day for men and 425 mg a day for women; food supplies most people's choline
- Fish-based choline sources (salmon, sardines) come with the eicosapentaenoic acid / docosahexaenoic acid / vitamin D / selenium package, and fish eating is linked with lower cardiovascular death even though fish raises trimethylamine N-oxide more than any other food (see the fish paradox above)
- A high-fiber diet, fermented foods and the Mediterranean pattern are the dietary patterns linked above with lower trimethylamine N-oxide production capacity
- Choline forms: practitioners focused on trimethylamine N-oxide often describe alpha-GPC and CDP-choline as absorbed in the upper gut, and bitartrate and lecithin as reaching the colon, where TMA-producing bacteria live. Alpha-GPC has its own finding: in a South Korean national cohort of 12,008,977 adults aged 50 or older (Lee 2021), people prescribed alpha-GPC had a higher 10-year risk of stroke than matched non-users (adjusted hazard ratio 1.43 for any stroke, 1.34 for ischemic stroke and 1.37 for hemorrhagic stroke), and the risk rose with longer use. The authors note that choline has been linked to heart disease through trimethylamine N-oxide, and say the mechanism behind the stroke link still needs study. It is an observational study, so it shows a link, not proof of cause
- Folate, B12, and B6 keep the folate-dependent methylation pathway working alongside the choline-betaine pathway
- Homocysteine is measured with a blood test; raised homocysteine is itself a cardiovascular risk factor, and the counter-mechanism section above explains why some researchers weigh it above trimethylamine N-oxide
People with chronic kidney disease
- Chronic kidney disease elevates trimethylamine N-oxide independently, and it is the clearest context for trimethylamine N-oxide-cardiovascular concern. In 521 people with chronic kidney disease (Tang 2015), median trimethylamine N-oxide was 7.9 µmol/L, markedly higher than in 3,166 people without kidney disease. Those in the highest quartile had a 2.8-fold higher risk of death over 5 years, and high trimethylamine N-oxide still predicted death after adjustment for other risk factors and kidney function (hazard ratio 1.93)
- In the same paper's animal experiments, high dietary choline or trimethylamine N-oxide directly led to progressive scarring (fibrosis) and loss of function in the kidneys
- High-dose lecithin and carnitine supplements are concentrated sources of trimethylamine precursors; fish and eggs in moderate amounts supply choline at food levels
People with raised trimethylamine N-oxide on a lab test
- Practitioners who use the test describe working on the gut microbiome first (fiber, Mediterranean diet, fermented foods), looking for any underlying kidney problem, and retesting trimethylamine N-oxide 3-6 months later
- No clinical trial has yet shown that lowering trimethylamine N-oxide reduces heart disease or stroke (Obeid 2025 umbrella review)
Otherwise-healthy people taking choline for memory or liver reasons
- In the cohort studies above, dietary choline was not linked to more cardiovascular disease (Meyer & Shea 2017: relative risk 1.00 across 184,010 people)
- The Cognition and Liver deep dives cover the research on choline for those uses
- In the 2025 meta-analysis of randomized trials, eating eggs did not change blood trimethylamine N-oxide; fish raises it, yet fish eating is linked with lower cardiovascular risk. The evidence reviewed on this page does not support cutting out eggs or fish on trimethylamine N-oxide grounds
Cautions Specific to Cardiovascular Use
- Trimethylamine N-oxide in perspective — the evidence for dietary choline restriction as a cardiovascular intervention is weak. The evidence for benefit of adequate choline intake is strong (homocysteine, hepatic, cognitive). Net likely benefit in most patients.
- Chronic kidney disease changes the calculus — impaired renal clearance plus elevated trimethylamine N-oxide plus already-high cardiovascular disease risk shifts the risk-benefit. Trimethylamine N-oxide builds up when kidney function falls, and in people with chronic kidney disease higher levels went with a higher 5-year risk of death (Tang 2015).
- Carnitine in the same conversation — L-carnitine (and acetyl-L-carnitine) are also TMA precursors and have been part of the same controversy. The same microbiome / form-selection questions apply to heavy meat-eaters who take carnitine supplements; in the Koeth 2013 study, omnivores made more trimethylamine N-oxide from L-carnitine than vegans or vegetarians did.
- Anticoagulation — the proposed trimethylamine N-oxide mechanism includes platelet activation: in Zhu 2016, trimethylamine N-oxide enhanced platelet hyperreactivity and thrombosis risk in animal models. This bears most on people taking anticoagulants or with active clotting (thrombotic) disease.
- Trimethylaminuria (TMAU) — rare; FMO3 deficiency prevents oxidation of TMA to trimethylamine N-oxide, leaving TMA itself to circulate and produce the fish-odor phenotype. Choline restriction is part of TMAU management.
- FMO3 gene variants — common partial-loss-of-function variants affect trimethylamine N-oxide levels. Consumer genetic testing may reveal these.
- Sex differences — women have higher FMO3 expression than men (estrogen-driven), so women tend to oxidize TMA to trimethylamine N-oxide more efficiently. The clinical implication is unclear.
Key Research Papers
- Wang Z et al. (2011). Gut flora metabolism of phosphatidylcholine promotes cardiovascular disease. Nature — PubMed PMID: 21475195
- Tang WHW et al. (2013). Intestinal microbial metabolism of phosphatidylcholine and cardiovascular risk. NEJM — PubMed PMID: 23614584
- Koeth RA et al. (2013). Intestinal microbiota metabolism of L-carnitine, a nutrient in red meat, promotes atherosclerosis. Nature Medicine. — PubMed PMID: 23563705
- Zhu W et al. (2016). Gut microbial metabolite TMAO enhances platelet hyperreactivity and thrombosis risk. Cell. — PubMed PMID: 26972052
- Meyer KA, Shea JW (2017). Dietary Choline and Betaine and Risk of CVD: A Systematic Review and Meta-Analysis of Prospective Studies. Nutrients;9(7):711. — PubMed PMID: 28686188
- Nagata C et al. (2015). Choline and betaine intakes are not associated with cardiovascular disease mortality risk in Japanese men and women. Journal of Nutrition. — PubMed PMID: 26063062
- Olthof MR et al. (2003). Low dose betaine supplementation leads to immediate and long-term lowering of plasma homocysteine in healthy men and women. Journal of Nutrition. — PubMed PMID: 14652361
- Olthof MR, Brink EJ, Katan MB, Verhoef P (2005). Choline supplemented as phosphatidylcholine decreases fasting and postmethionine-loading plasma homocysteine concentrations in healthy men. American Journal of Clinical Nutrition;82(1):111-117. — PubMed PMID: 16002808
- Dalmeijer GW, Olthof MR, Verhoef P, Bots ML, van der Schouw YT (2008). Prospective study on dietary intakes of folate, betaine, and choline and cardiovascular disease risk in women. European Journal of Clinical Nutrition;62(3):386-394. — PubMed PMID: 17375117
- Bidulescu A et al. (2007). Usual choline and betaine dietary intake and incident coronary heart disease: the Atherosclerosis Risk in Communities (ARIC) study. BMC Cardiovascular Disorders. — PubMed PMID: 17629908
- Landfald B et al. (2017). Microbial trimethylamine-N-oxide as a disease marker: something fishy? Microbial Ecology in Health and Disease. — PubMed PMID: 28588431
- Cho CE & Caudill MA (2017). Trimethylamine-N-oxide: friend, foe, or simply caught in the cross-fire? Trends in Endocrinology and Metabolism. — PubMed PMID: 27825547
- Senthong V, Wang Z, Fan Y, Wu Y, Hazen SL, Tang WH (2016). Trimethylamine N-Oxide and Mortality Risk in Patients With Peripheral Artery Disease. Journal of the American Heart Association;5(10):e004237. — PubMed PMID: 27792653
- Cho CE, Taesuwan S, Malysheva OV, Bender E, Tulchinsky NF, Yan J, Sutter JL, Caudill MA (2017). Trimethylamine-N-oxide (TMAO) response to animal source foods varies among healthy young men and is influenced by their gut microbiota composition: A randomized controlled trial. Molecular Nutrition & Food Research;61(1). — PubMed PMID: 27377678
- Tang WH, Wang Z, Kennedy DJ, Wu Y, Buffa JA, Agatisa-Boyle B, Li XS, Levison BS, Hazen SL (2015). Gut microbiota-dependent trimethylamine N-oxide (TMAO) pathway contributes to both development of renal insufficiency and mortality risk in chronic kidney disease. Circulation Research;116(3):448-455. — PubMed PMID: 25599331
- Lee G, Choi S, Chang J, Choi D, Son JS, Kim K, Kim SM, Jeong S, Park SM (2021). Association of L-α Glycerylphosphorylcholine With Subsequent Stroke Risk After 10 Years. JAMA Network Open;4(11):e2136008. — PubMed PMID: 34817582
- Obeid R, Mohr L, White BA, Heine GH, Emrich I, Geisel J, Carter RC (2025). Circulating trimethylamine N-oxide and cardiovascular, cerebral, and renal diseases including mortality: Umbrella review of published systematic reviews and meta-analyses. Nutrition, Metabolism and Cardiovascular Diseases;35(8):103908. — PubMed PMID: 40118729
- Aryaeian N, Heydarian A, Tahvilian N, Hosseini H, Ahmadi AR, Davarpanah SH (2025). Effect of egg consumption on circulating choline, betaine, and trimethylamine n-oxide in adults: a systematic review and meta-analysis of randomized controlled trials. Nutrition Journal;24(1):165. — PubMed PMID: 41146117
PubMed Topic Searches
Connections
- All Vitamins
- Choline Overview
- Choline Benefits Hub
- Choline for Cognition
- Choline for Liver & Non-Alcoholic Fatty Liver Disease
- Choline for Pregnancy
- Cardiovascular Disease
- Homocysteine
- Folate (B9)
- Vitamin B12
- Vitamin B6
- Methionine
- L-Carnitine
- Probiotics
- Fermented Foods
- Nephrology / Chronic Kidney Disease
- Non-Alcoholic Fatty Liver Disease
- Salmon
- Eggs
- Deficiency
- Toxicity
- History
- Sources