Beef Liver, Choline & the Liver-Brain Connection
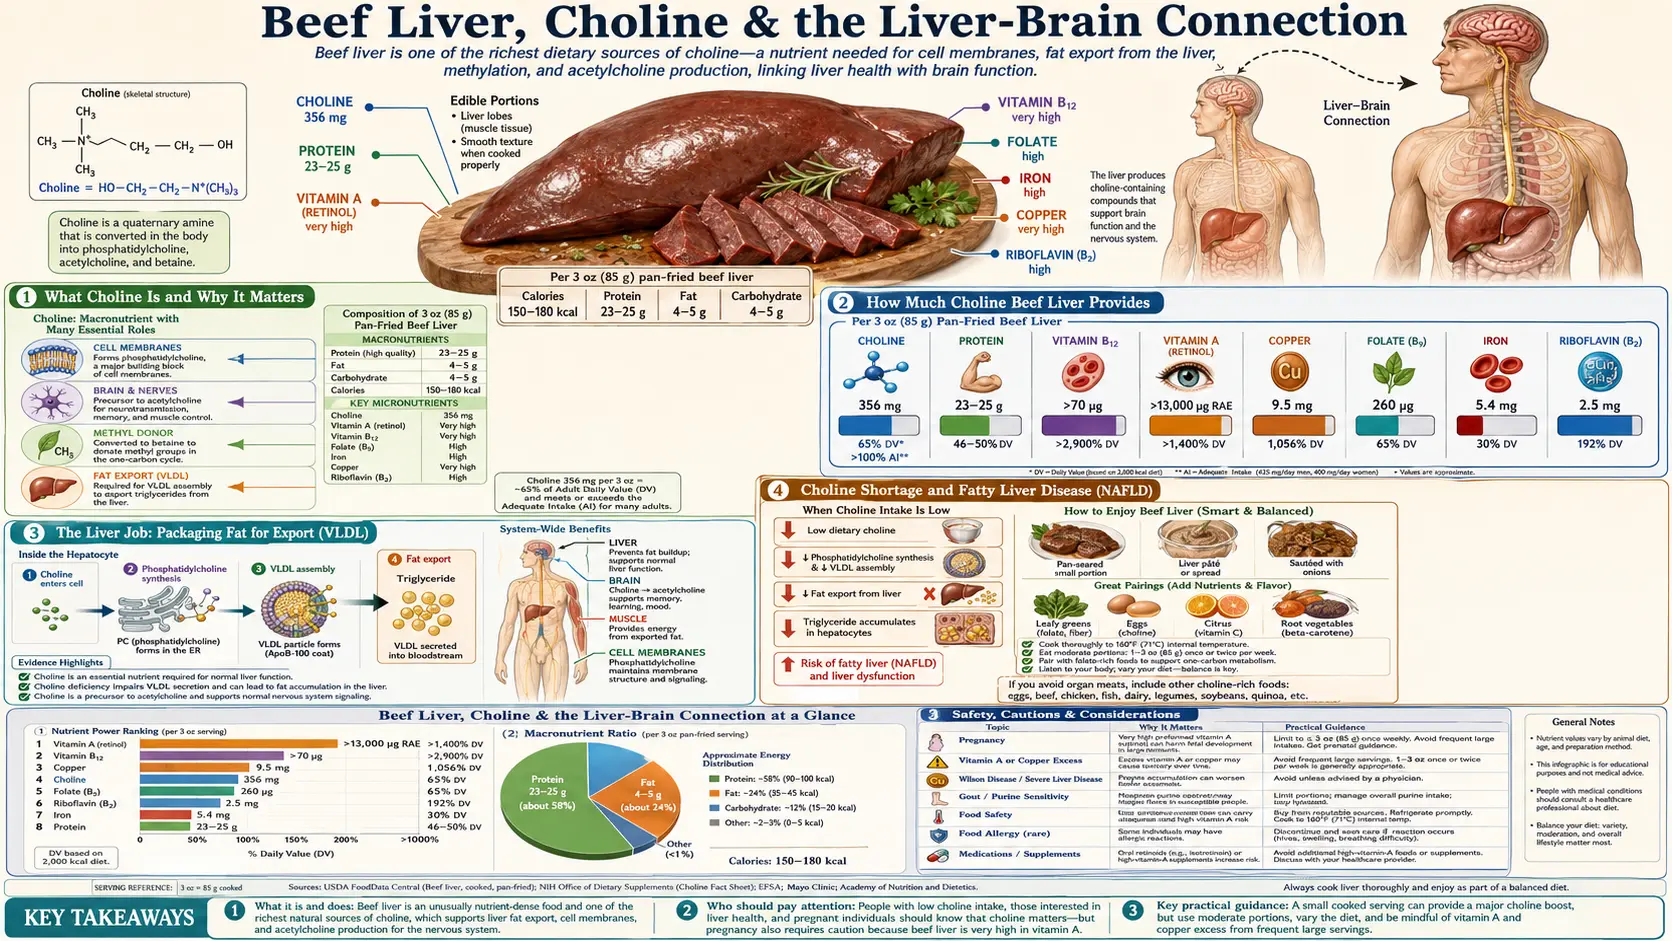
Choline is an essential nutrient that most people have never heard of, yet it sits at the crossroads of two of the body's most important jobs: keeping the liver from clogging with fat, and building the brain. Beef liver is one of the single richest whole-food sources of choline on the planet — a 100-gram serving of cooked beef liver supplies more than 400 milligrams, rivaling or beating eggs. This page explains what choline actually does, why a shortage drives fat to back up in the liver (the same fatty-liver problem now affecting about 30% of adults worldwide), how choline becomes the memory chemical acetylcholine and the scaffolding of every brain cell membrane, and who — especially pregnant and breastfeeding women — almost certainly needs more than they are getting.
Table of Contents
- What Choline Is and Why It Matters
- How Much Choline Beef Liver Provides
- The Liver Job: Packaging Fat for Export (Very-Low-Density Lipoprotein)
- Choline Shortage and Fatty Liver Disease (Non-Alcoholic Fatty Liver Disease)
- The Brain Job: Acetylcholine and Memory
- Choline as the Brain's Building Material
- Pregnancy, the Baby's Brain & the Hippocampus
- Methylation: Choline, Betaine and Homocysteine
- Who Needs More — and How Much
- Food Sources, Moderation & Supplement Alternatives
- Key Research Papers
- Connections
- Featured Videos
What Choline Is and Why It Matters
Choline is a small, water-soluble molecule that chemists group loosely with the B-vitamins, though it is not technically a vitamin. For decades it was assumed the body could make all it needed on its own. That assumption was overturned in the 1990s: when researchers fed healthy adults a diet stripped of choline, many of them developed liver and muscle damage within a few weeks, and the damage reversed once choline was added back. In 1998 the U.S. Institute of Medicine formally classified choline as an essential nutrient — meaning the body cannot make enough on its own and the rest has to come from food.
The reason a shortage shows up so fast in the liver and brain is that choline is not a luxury molecule used here and there. It is a structural raw material. Your body pulls choline down three main pathways, and each one is load-bearing:
- Into phosphatidylcholine — the most abundant building block of the membrane that wraps every single cell, and the molecule the liver uses to package fat for shipping. This pathway alone consumes most of your daily choline.
- Into acetylcholine — the neurotransmitter your brain uses for memory and learning, and the signal every nerve uses to fire a muscle.
- Into betaine — a "methyl donor" that helps recycle the amino acid homocysteine and supports the body's methylation chemistry, overlapping with folate and vitamin B12.
Because choline feeds membranes, brain chemistry, and methylation all at once, running short does not produce one neat deficiency disease. It produces a quieter, multi-system strain — and the two organs that feel it first are the liver and the brain. That is the story this page tells. For the fuller chemistry, see the dedicated Choline overview.
How Much Choline Beef Liver Provides
Beef liver is, gram for gram, one of the densest sources of choline in the entire food supply. According to the U.S. Department of Agriculture's FoodData Central database, the numbers are:
- Beef liver, cooked (pan-fried): about 418 mg of choline per 100 grams.
- Beef liver, raw: about 333 mg per 100 grams (cooking concentrates it as water cooks off).
- For comparison — one whole large egg supplies roughly 147 mg (whole egg is about 294 mg per 100 grams), and the prized egg yolk runs about 820 mg per 100 grams.
- Chicken liver, cooked: about 327 mg per 100 grams — also excellent, slightly lower than beef.
To put that in plain terms: a single modest 100-gram serving of cooked beef liver — about the size of a deck of cards — delivers roughly three-quarters of an entire day's recommended choline intake for an adult man, and nearly all of the 425 mg daily target for women. Eggs are usually called the poster-child choline food, but liver actually matches or beats whole egg on a per-100-gram basis. This is one of the few nutrients where the two richest everyday sources are both organ-and-egg foods, which is exactly why people who avoid both tend to fall short (more on that below).
One practical caveat: those choline numbers come from the U.S. Department of Agriculture (USDA)'s long-standing reference (SR Legacy) values, and the choline content of any liver will vary somewhat with the animal's diet and the exact cut. But across every dataset, liver consistently lands at the very top of the choline rankings.
The Liver Job: Packaging Fat for Export (Very-Low-Density Lipoprotein)
Here is the single most important thing to understand about choline and the liver. The liver is constantly handling fat — fat you eat, and fat it manufactures from excess sugar and carbohydrate. It cannot just let that fat sit there. To get fat out of the liver and into the bloodstream where the rest of the body can use it, the liver has to package it into tiny shipping containers called very-low-density lipoprotein (VLDL) particles.
Building a very-low-density lipoprotein particle requires a specific outer wrapper, and that wrapper is made largely of phosphatidylcholine — which the liver builds from choline. Think of it this way: triglyceride fat is the cargo, and phosphatidylcholine is the shrink-wrap and shipping label. Without enough shrink-wrap, the cargo cannot leave the warehouse.
When choline runs low, the liver simply cannot assemble enough phosphatidylcholine to export its fat. The fat has nowhere to go, so it accumulates inside liver cells as droplets. This is not a vague theory; it is one of the oldest and most reproducible findings in nutritional science, demonstrated in animals since the 1930s and confirmed in humans. The liver makes the cargo faster than it can build the packaging, and the warehouse fills up. That backed-up fat is the beginning of fatty liver disease — the subject of the next section.
It is worth noting that the liver has a second, backup route to make phosphatidylcholine (an enzyme called PEMT that builds it from a different starting material). But that backup route is limited, it competes for the same methyl-group chemistry described later, and in many people — particularly premenopausal women with certain common gene variants — it cannot keep up. Dietary choline is the dependable supply line.
Choline Shortage and Fatty Liver Disease (Non-Alcoholic Fatty Liver Disease)
Non-alcoholic fatty liver disease (NAFLD) — since 2023 officially renamed metabolic dysfunction-associated steatotic liver disease (MASLD) — is the most common liver condition in the world, affecting about 30% of adults worldwide. It is defined by exactly the problem described above: too much fat stored inside the liver, in someone who does not drink heavily. The new name comes from a 2023 consensus of 236 liver experts and patient advocates from 56 countries, which also changed the definition: liver fat plus at least 1 of 5 cardiometabolic risk factors. A 2023 review of 92 population studies covering more than 9.3 million people put the global figure at 30%, rising from 25.3% in 1990–2006 to 38.0% in 2016–2019. In its worst forms it can progress to inflammation, scarring, and even cirrhosis. Our dedicated page covers the full clinical picture: Non-Alcoholic Fatty Liver Disease.
The most direct human proof that choline shortage causes liver fat came from an unusual source: hospital patients fed entirely through a vein (total parenteral nutrition). In the early days, those intravenous nutrition formulas contained no choline. A landmark 1995 study showed these patients developed hepatic steatosis — fatty liver — and that giving them choline reversed it. The deficiency caused the fat; the repletion cleared it. That is about as clean a cause-and-effect demonstration as nutrition science ever produces in living humans.
Controlled feeding studies then sharpened the picture. When researchers placed healthy volunteers on a choline-depleted diet, a sizeable fraction developed measurable liver dysfunction. In one such study (Fischer 2007, 57 adults), a folic acid supplement did not change who developed it; sex and menopausal status made the difference, with premenopausal women — whose estrogen boosts the body's own phosphatidylcholine production — affected far less often. Later work using metabolomic "fingerprinting" of the blood could even predict which individuals would develop liver dysfunction when choline was removed, underscoring that susceptibility varies from person to person. Importantly, postmenopausal women and people with certain common gene variants (in the PEMT and MTHFD1 genes) are notably more vulnerable, because their backup phosphatidylcholine route is weaker.
The takeaway is not that choline deficiency is the sole cause of every fatty liver — sugar, alcohol, insulin resistance, and obesity are major drivers. But adequate choline is a genuine, evidence-backed piece of liver protection, and beef liver is one of the most concentrated ways to supply it from food. A choline-rich diet gives the liver the packaging material it needs to keep exporting fat instead of storing it.
The Brain Job: Acetylcholine and Memory
Switch organs now, from liver to brain. One of choline's starring roles is serving as the direct raw material for acetylcholine, one of the most important neurotransmitters in the body. Acetylcholine does two big jobs:
- Memory and learning. Acetylcholine is the principal signaling molecule of the brain circuits involved in attention, learning, and forming new memories. The cells that make it are among the first to degenerate in Alzheimer's disease, which is why several Alzheimer's drugs work by slowing acetylcholine's breakdown to keep more of it around.
- Muscle activation. Every time your brain tells a muscle to contract — to lift your arm, blink, or breathe — the nerve releases acetylcholine at the junction with the muscle. No acetylcholine, no movement.
Your body builds acetylcholine by attaching an acetyl group onto a molecule of choline. That means the supply of available choline can directly influence how much acetylcholine the brain is able to make, particularly when demand is high. The brain guards its choline supply carefully — choline crosses from the blood into the brain through a dedicated transporter — but the building block still has to come from the diet, and ultimately from foods like liver and eggs.
It is worth being honest here: eating more choline does not turn an average adult into a memory savant. The clearest cognitive payoffs from choline are seen at the two ends of life — during fetal and infant brain construction (covered below), and in the context of protecting an aging brain's acetylcholine system. For a healthy adult in between, the main point is simply not to run short.
Choline as the Brain's Building Material
Beyond the acetylcholine signal, choline is literally part of the brain's physical structure. Every neuron is wrapped in a membrane, and the brain is one of the fattiest organs in the body — much of that fat is phosphatidylcholine (and a related molecule, sphingomyelin, that also depends on choline-derived building blocks). These molecules form the insulating sheaths around nerve fibers and the flexible membranes that let brain cells grow connections and communicate.
When a brain is being built — in the womb, in infancy, and during the explosive growth of early childhood — the demand for membrane-building phosphatidylcholine is enormous. The raw material is choline. The same molecule that the liver uses to wrap fat for export is the molecule the developing brain uses to wrap its billions of new cells. This dual role — signaling chemical and structural material — is what makes choline uniquely important for the brain, and it is why the next section focuses on pregnancy.
Pregnancy, the Baby's Brain & the Hippocampus
If there is one life stage where choline truly shines, it is pregnancy and breastfeeding. A developing fetus draws heavily on the mother's choline to build its brain and the rest of its body. The placenta actively pumps choline from mother to baby, keeping fetal levels far higher than the mother's own — a sign of just how essential the supply is. A great deal of the research interest centers on the hippocampus, the brain's memory-and-learning center, which appears to be especially sensitive to choline availability during its construction.
The most striking human evidence comes from a carefully controlled feeding study in which pregnant women in their third trimester were assigned to either a moderate or a high choline intake. The infants of mothers in the higher-choline group showed faster information-processing speed — an early marker of cognitive function — measured in the baby's first year. Because the women's entire diet was supplied and controlled, this is unusually strong evidence that maternal choline intake shapes infant brain development, not just an association that could be explained by other lifestyle factors.
The same feeding trial was followed up when the children reached age 7. Children whose mothers had eaten 930 mg of choline a day in the third trimester, against 480 mg a day (about the Adequate Intake for pregnancy), kept their attention better through a 12-minute computer task (primary attention score, p = 0.02). Only 20 children were tested, so the study is small. The authors noted that pregnant women eat, on average, about 70% of the Adequate Intake.
This is why choline is now discussed alongside folate as a pregnancy-critical nutrient. Folate gets nearly all the attention (rightly — it prevents neural-tube defects), but choline overlaps with folate in the body's methylation chemistry and carries its own distinct role in building the fetal brain. The problem is that prenatal vitamins historically contained little or no choline, and surveys show most pregnant women fall well below the recommended intake. A few servings of beef liver or eggs per week is one of the most reliable dietary ways to close that gap — with the important moderation caveat for liver discussed in the final section.
Methylation: Choline, Betaine and Homocysteine
The third major use of choline connects it to a quieter but important piece of body chemistry called methylation — the constant transfer of tiny "methyl groups" (a carbon with three hydrogens) that the body uses to switch genes on and off, build neurotransmitters, and recycle key molecules. Methylation usually gets framed as a folate-and-vitamin-B12 story, but choline is a full partner in it.
Here is the link. The body converts some choline into a molecule called betaine. Betaine then donates a methyl group to convert homocysteine — an amino acid that, at high levels, is associated with cardiovascular and other health concerns — back into the useful amino acid methionine. In other words, choline (via betaine) is an alternate route for clearing homocysteine, working in parallel with the better-known folate/B12 route. This is genuinely useful: a controlled human study found that supplementing choline as phosphatidylcholine lowered blood homocysteine, especially after a methionine challenge.
The two routes back each other up. When folate or B12 is in short supply, the body leans harder on choline and betaine to keep homocysteine in check — which can drain choline reserves and is one reason choline-and-folate status are intertwined. This is exactly why the sibling page on beef liver's B12 & Folate content matters here too: beef liver happens to be loaded with B12, folate, and choline simultaneously, supplying all three players in the methylation system in a single food. Few foods do that.
Who Needs More — and How Much
Because choline was only recognized as essential relatively recently, official intake targets are set as an Adequate Intake (AI) rather than a precise daily requirement. The U.S. Adequate Intake values are:
- Adult men: 550 mg per day.
- Adult women: 425 mg per day.
- Pregnancy: 450 mg per day.
- Breastfeeding (lactation): 550 mg per day — the highest target, because the mother is exporting large amounts of choline into breast milk.
The uncomfortable reality is that most people do not hit these numbers. National survey data consistently show that the large majority of adults — and, critically, the large majority of pregnant women — consume below the recommended amount. Choline is simply not abundant in the foods many people eat most of (it is concentrated in eggs, liver, other organ meats, and to a lesser degree other meats and some legumes and cruciferous vegetables). People who avoid eggs and organ meats, or who follow strictly plant-based diets, are at the highest risk of falling short.
Certain groups have an even greater need or vulnerability:
- Pregnant and breastfeeding women — highest demand, and most are under-consuming; the developing brain is at stake.
- Postmenopausal women and people with certain common gene variants (in PEMT and folate-pathway genes) — their internal backup production of phosphatidylcholine is weaker, so they depend more on dietary choline and develop signs of deficiency faster when intake is low.
- People with low folate intake — with the folate methyl-donor route under strain, the body burns through more choline.
The numbers behind this list come from a 2007 controlled feeding study of 57 adults (26 men, 16 premenopausal women, 15 postmenopausal women) who were switched to a diet with almost no choline (under 50 mg a day) for up to 42 days. 77% of the men and 80% of the postmenopausal women developed fatty liver or muscle damage, against 44% of the premenopausal women; normal organ function returned when choline was added back. Six men developed these signs even while eating 550 mg a day (per 70 kg of body weight), the Adequate Intake, and the authors concluded that the current Adequate Intake was not enough to prevent organ damage in 19 of the volunteers. A folic acid supplement did not change the results.
For context: a single 100-gram serving of cooked beef liver (about 418 mg) covers nearly all of a woman's daily Adequate Intake and most of a man's — from one food, once.
Food Sources, Moderation & Supplement Alternatives
Beef liver is a top-tier choline food, but it comes with one specific vitamin A caution — and there are other choline foods for people who do not eat liver.
The vitamin A caution. The very thing that makes liver a superfood — its extraordinary nutrient density — also means it is extremely concentrated in preformed vitamin A (retinol). Too much preformed vitamin A is harmful, and is specifically dangerous in early pregnancy, where excess can cause birth defects. The numbers: according to USDA FoodData Central, 100 grams of pan-fried beef liver carries 7,740 micrograms of vitamin A activity (retinol activity equivalents; 26,100 IU), almost all of it preformed retinol (7,730 micrograms). In a 1995 study of 22,748 pregnant women, those who took more than 10,000 IU of preformed vitamin A a day from supplements had 4.8 times the rate of birth defects in tissues that develop from the cranial neural crest compared with women taking 5,000 IU or less, and the extra defects were concentrated in babies whose mothers had taken high amounts before the seventh week of pregnancy. This is covered in detail on the sibling page Vitamin A for Vision, Immunity and Skin. The good news: even one small weekly serving makes a meaningful contribution to your weekly choline supply.
Other excellent choline foods. If you want choline without leaning entirely on liver, the standouts are:
- Whole eggs — the most practical everyday source; the choline is in the yolk, not the white. Two eggs supply roughly 300 mg. See Eggs.
- Other organ meats and meats — chicken liver is nearly as rich as beef liver; muscle meats, poultry, and fish supply moderate amounts.
- Legumes (such as kidney beans), cruciferous vegetables (broccoli, Brussels sprouts), and wheat germ — the best plant sources, though lower per serving than eggs or liver.
Supplements. For people who cannot or will not eat eggs and organ meats — or pregnant women trying to meet the target without over-doing liver's vitamin A — choline supplements exist. The most common forms are lecithin and purified phosphatidylcholine, along with choline bitartrate and choline-supplemented prenatal vitamins. These are reasonable alternatives, though whole foods deliver choline alongside its natural co-nutrients. The deeper dive on choline and liver protection lives at Choline for Liver & non-alcoholic fatty liver disease.
One honest counterpoint — trimethylamine N-oxide (TMAO). A fair page mentions the other side. Gut bacteria can convert some dietary choline and phosphatidylcholine into a compound called trimethylamine N-oxide (TMAO), and high blood trimethylamine N-oxide has been linked in some studies to cardiovascular risk. This finding has been debated, and it does not overturn choline's essential status — the body genuinely needs choline, and the doses in normal food are not the concern that megadose research probes. But it is one more reason the sensible approach is adequate choline from whole foods in moderation, rather than chasing the absolute highest intake possible.
Key Research Papers
- Zeisel SH, da Costa KA. Choline: an essential nutrient for public health. Nutrition Reviews. 2009;67(11):615-623. — doi:10.1111/j.1753-4887.2009.00246.x
- Zeisel SH, Da Costa KA, Franklin PD, et al. Choline, an essential nutrient for humans. The FASEB Journal. 1991;5(7):2093-2098. — doi:10.1096/fasebj.5.7.2010061
- Zeisel SH. Choline: critical role during fetal development and dietary requirements in adults. Annual Review of Nutrition. 2006;26:229-250. — doi:10.1146/annurev.nutr.26.061505.111156
- Corbin KD, Zeisel SH. Choline metabolism provides novel insights into nonalcoholic fatty liver disease and its progression. Current Opinion in Gastroenterology. 2012;28(2):159-165. — doi:10.1097/MOG.0b013e32834e7b4b
- Buchman AL, Dubin M, Moukarzel A, et al. Choline deficiency: a cause of hepatic steatosis during parenteral nutrition that can be reversed with intravenous choline supplementation. Hepatology. 1995;22(5):1399-1403. — doi:10.1002/hep.1840220510
- Sha W, da Costa KA, Fischer LM, et al. Metabolomic profiling can predict which humans will develop liver dysfunction when deprived of dietary choline. The FASEB Journal. 2010;24(8):2962-2975. — doi:10.1096/fj.09-154054
- Fischer LM, da Costa KA, Kwock L, et al. Sex and menopausal status influence human dietary requirements for the nutrient choline. The American Journal of Clinical Nutrition. 2007;85(5):1275-1285. — doi:10.1093/ajcn/85.5.1275
- Wiedeman AM, Barr SI, Green TJ, et al. Dietary choline intake: current state of knowledge across the life cycle. Nutrients. 2018;10(10):1513. — doi:10.3390/nu10101513
- Caudill MA, Strupp BJ, Muscalu L, et al. Maternal choline supplementation during the third trimester of pregnancy improves infant information processing speed: a randomized, double-blind, controlled feeding study. The FASEB Journal. 2018;32(4):2172-2180. — doi:10.1096/fj.201700692RR
- Olthof MR, Brink EJ, Katan MB, et al. Choline supplemented as phosphatidylcholine decreases fasting and postmethionine-loading plasma homocysteine concentrations in healthy men. The American Journal of Clinical Nutrition. 2005;82(1):111-117. — doi:10.1093/ajcn/82.1.111
- Craig SA. Betaine in human nutrition. The American Journal of Clinical Nutrition. 2004;80(3):539-549. — doi:10.1093/ajcn/80.3.539
- Tang WHW, Wang Z, Levison BS, et al. Intestinal microbial metabolism of phosphatidylcholine and cardiovascular risk. New England Journal of Medicine. 2013;368(17):1575-1584. — doi:10.1056/NEJMoa1109400
- Bahnfleth CL, Strupp BJ, Caudill MA, Canfield RL. Prenatal choline supplementation improves child sustained attention: A 7-year follow-up of a randomized controlled feeding trial. The FASEB Journal. 2022;36(1):e22054. — doi:10.1096/fj.202101217R
- Rinella ME, Lazarus JV, Ratziu V, et al. A multisociety Delphi consensus statement on new fatty liver disease nomenclature. Hepatology. 2023;78(6):1966-1986. — doi:10.1097/HEP.0000000000000520
- Younossi ZM, Golabi P, Paik JM, et al. The global epidemiology of nonalcoholic fatty liver disease (NAFLD) and nonalcoholic steatohepatitis (NASH): a systematic review. Hepatology. 2023;77(4):1335-1347. — doi:10.1097/HEP.0000000000000004
- Rothman KJ, Moore LL, Singer MR, et al. Teratogenicity of high vitamin A intake. New England Journal of Medicine. 1995;333(21):1369-1373. — doi:10.1056/NEJM199511233332101