Vitamin A for Skin & Cellular Differentiation
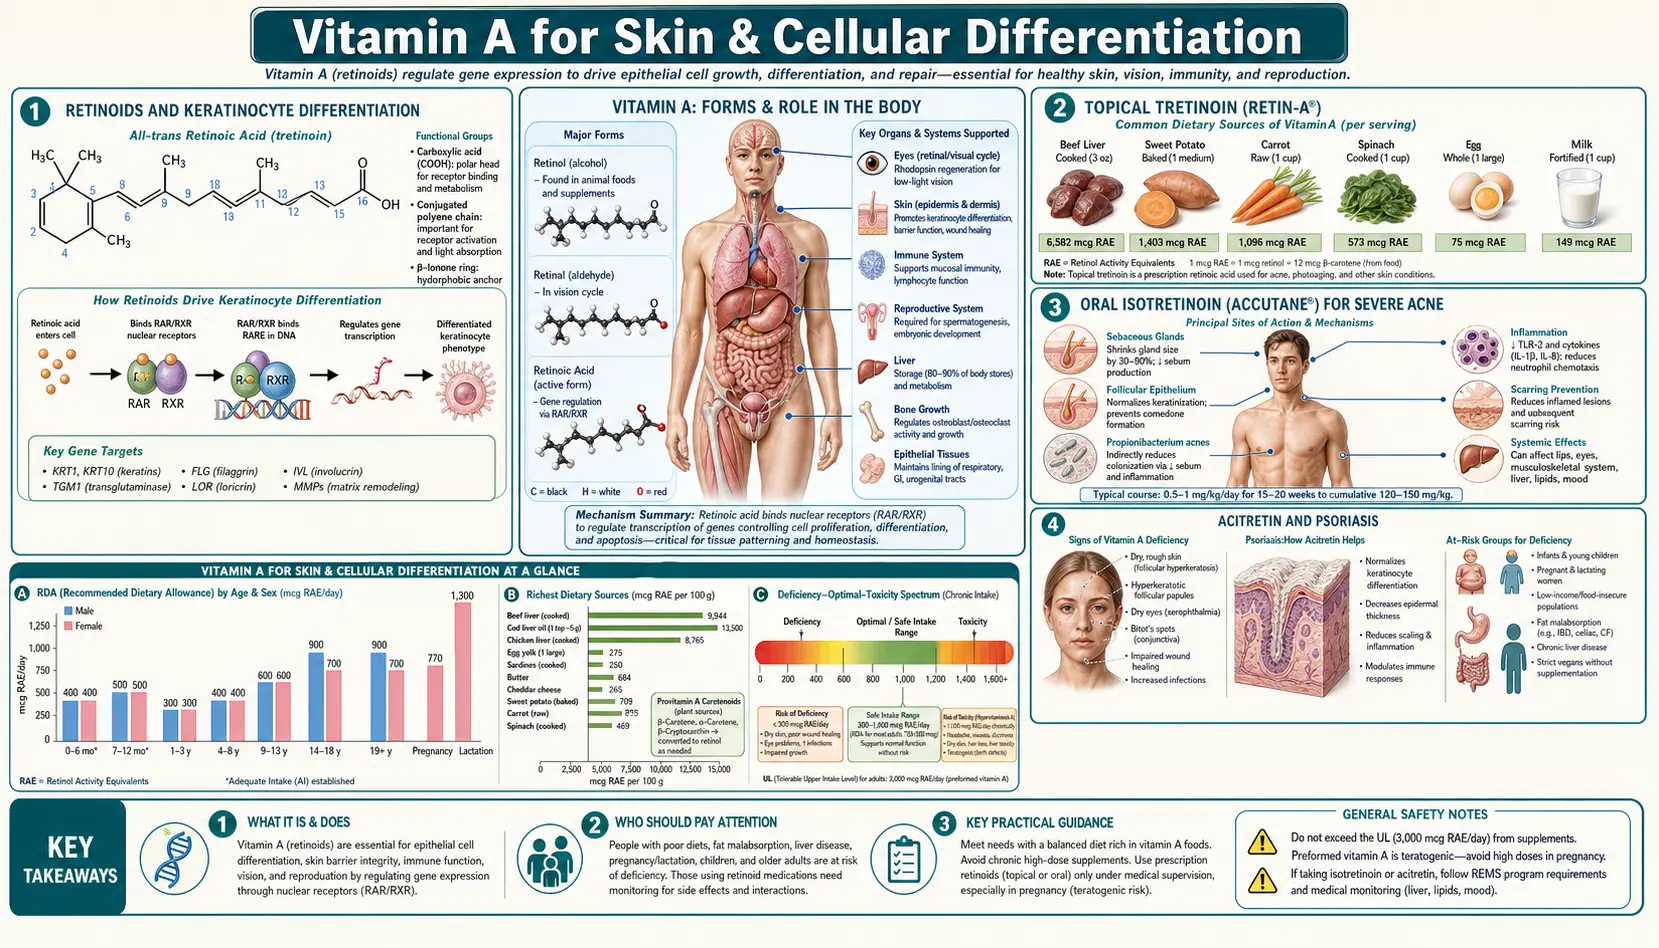
Topical and oral Vitamin A derivatives — collectively called retinoids — constitute the single most therapeutically important drug class in dermatology. Tretinoin for acne and photoaging, isotretinoin for severe nodulocystic acne, acitretin for psoriasis, adapalene for over-the-counter acne, retinaldehyde for sensitive skin, and the retinyl esters of mass-market cosmetics all work through the same RAR/RXR nuclear receptor mechanism that drives normal keratinocyte differentiation. The same mechanism that makes retinoids so effective also makes them the most reliably teratogenic drug class known to dermatology — oral retinoids are absolutely contraindicated in pregnancy and require monthly pregnancy testing under the iPLEDGE program in the United States. This deep-dive walks through each retinoid drug, its mechanism, its place in clinical practice, and the warnings that matter most.
Table of Contents
- Retinoids and Keratinocyte Differentiation
- Topical Tretinoin
- Oral Isotretinoin for Severe Acne
- Acitretin and Psoriasis
- Photoaging Reversal Trials
- Retinaldehyde — The Gentler Alternative
- Retinyl Esters in Over-the-Counter Cosmetics
- Adapalene — Over-the-Counter Synthetic Retinoid
- Pregnancy Contraindication and iPLEDGE
- How Retinoids Are Used in Practice
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Retinoids and Keratinocyte Differentiation
The epidermis is a stratified squamous epithelium with a continuous lineage from basal keratinocytes to terminally differentiated, anucleate corneocytes that shed from the skin surface. The journey from stem-cell-like basal layer to fully cornified flake takes approximately 28 days in healthy adult skin. Retinoic acid is a master regulator of this differentiation program.
Retinoic acid binds to RAR (retinoic acid receptor) and RXR (retinoid X receptor) nuclear receptors, which heterodimerize and bind retinoic acid response elements (RAREs) in promoter regions of dozens of keratin and cornified-envelope genes. The effects on keratinocyte biology are:
- Acceleration of basal keratinocyte proliferation (the layer thickens)
- Normalization of the differentiation gradient (cells progress at the correct rate through the differentiation layers)
- Prevention of pathological hyperkeratosis (the abnormal thickening of cornified layer seen in psoriasis, ichthyosis, and acne plugs)
- Reduction of sebaceous gland output (the basis for the dramatic isotretinoin effect on acne)
- Increased dermal collagen synthesis through fibroblast effects (the basis for photoaging reversal)
- Reduction of melanocyte hyperactivity and reduction of post-inflammatory hyperpigmentation
- Suppression of matrix metalloproteinases (MMP-1, MMP-3, MMP-9) that drive collagen breakdown in photoaged skin
The same mechanism that produces these therapeutic effects also produces the characteristic irritation profile of topical retinoid use — erythema, scaling, dryness, and sting — especially during the first 4-8 weeks while the keratinocyte turnover rate normalizes. This is called "retinization" and is expected, not a sign of allergy or wrong product choice.
Topical Tretinoin
Tretinoin is all-trans-retinoic acid — the same molecule produced endogenously when retinaldehyde is oxidized in the skin and other tissues. As a topical drug, tretinoin acts directly on the RAR receptors of basal keratinocytes without requiring any further metabolic conversion, which makes it the most potent (and most irritating) of the topical retinoids.
U.S. Food and Drug Administration-approved indications are acne vulgaris and photoaging. Available concentrations range from 0.01% through 0.025%, 0.05%, and 0.1% in cream, gel, and microsphere-encapsulated formulations. Today generic versions are widely available.
How it is commonly used in dermatology practice:
- Treatment usually starts low (0.025% cream) and is increased over weeks to months as tolerated
- A pea-sized amount is spread over the entire face, not just affected spots
- It is applied at bedtime — tretinoin is photolabile and is degraded by daylight
- It is put on dry skin 20-30 minutes after washing the face, which reduces irritation
- For the first 2-3 weeks it is often used only every other night while tolerance develops
- Daily SPF 30+ sunscreen is the standard companion — retinized skin is more sensitive to sunlight
- A basic moisturizer (ceramide-based products are a common choice) eases retinization dryness
- Peak clinical improvement typically takes 8-12 weeks
The microsphere-encapsulated formulation (tretinoin 0.025% or 0.04% microsphere gel) releases the active drug more slowly, reducing peak skin concentration and substantially reducing irritation. For people with sensitive skin who cannot tolerate plain tretinoin, it is a commonly prescribed option.
For more on the disease context, see our Acne page.
Oral Isotretinoin for Severe Acne
Isotretinoin is 13-cis-retinoic acid — a stereoisomer of tretinoin that can be metabolized in tissue to all-trans-retinoic acid (the active RAR ligand) and to 4-oxo-isotretinoin metabolites. As an oral drug, isotretinoin produces sustained tissue exposure to retinoids and is the only treatment that can produce permanent remission of severe nodulocystic acne in a substantial fraction of patients.
Mechanism of action against acne (the four pillars of acne pathogenesis it addresses):
- Sebum reduction — isotretinoin causes apoptosis and atrophy of sebaceous glands, reducing sebum output by 80-90%. This is the central effect — without sebum, the entire downstream acne cascade is suppressed.
- Comedolysis — normalizes follicular keratinization, dissolving existing comedones and preventing new ones
- Anti-inflammatory — reduces neutrophil chemotaxis and proinflammatory cytokine production in the pilosebaceous unit
- Reduction of Cutibacterium acnes — secondary to sebum reduction; with no sebum the anaerobic bacterium loses its growth substrate
Standard course: 0.5-1.0 mg/kg/day for 16-24 weeks, targeting a cumulative dose of approximately 120-150 mg/kg total. Clinical improvement begins around week 4-6, typically with an "initial flare" period during the first month as deep nodules are mobilized. Peak benefit at week 16-20. After completing the course, approximately 50-60% of patients have permanent remission, 30% have lasting improvement but require some topical maintenance, and 10-15% relapse and may benefit from a second course.
Side effect profile is significant and predictable:
- Universal: dry lips (cheilitis), dry skin, dry eyes, dry nasal mucosa with epistaxis
- Common: elevated triglycerides and low-density lipoprotein (LDL) cholesterol, mildly elevated liver transaminases, joint and muscle aches
- Less common: increased intracranial pressure (pseudotumor cerebri, especially with concurrent tetracycline class antibiotics — combination is contraindicated), corneal opacities, decreased night vision
- Controversial: mood changes and depression — the U.S. Food and Drug Administration (FDA) label warns of this association, but controlled studies have not consistently demonstrated causation distinct from the impact of severe acne itself on mood (see the 2024 meta-analysis below)
- Absolute: teratogenicity — see iPLEDGE section below
Mood and suicide research. A 2024 meta-analysis (Tan and colleagues, JAMA Dermatology) pooled 25 studies with 1,625,891 participants. Across the population, isotretinoin users did not have a higher risk of psychiatric disorders overall (risk ratio 1.08, 95% confidence interval 0.99-1.19, not significant). In the first year of use, the pooled risk of completed suicide, suicide attempt, suicidal thoughts and self-harm was each under 0.5%, and the risk of depression was 3.83%. Users were less likely than non-users to attempt suicide 2, 3 and 4 years after treatment (risk ratios 0.92, 0.86 and 0.85). The authors call the findings reassuring and still describe monitoring patients for signs of mental distress during treatment.
Low-dose isotretinoin. Isotretinoin is also used off-label at low daily doses for mild-to-moderate acne that has not responded to other treatment. A 2022 systematic review and meta-analysis (Al Muqarrab and Almohssen) found that the conventional dose (0.5-1.0 mg/kg a day to a total of 120-150 mg/kg) gave a better response and a better chance of long remission in adults with mild-to-moderate acne than low daily doses, and that low daily doses did better than pulsed (intermittent) dosing; the authors rated the overall quality of the evidence as low.
Acitretin and Psoriasis
Acitretin is an oral retinoid specifically developed for hyperkeratotic disorders, particularly chronic plaque psoriasis and pustular variants. It is the active metabolite of etretinate (which is no longer marketed because of its extraordinarily long half-life of 120 days).
The clinical mechanism in psoriasis is normalization of the dramatically accelerated keratinocyte turnover that defines the disease. In psoriasis, the normal 28-day epidermal turnover compresses to 3-7 days, producing the characteristic thickened plaques with silvery scale. Acitretin slows this turnover by RAR-mediated suppression of basal keratinocyte proliferation and acceleration of terminal differentiation, allowing the abnormal stratum corneum to shed and the epidermis to normalize.
Typical dosing: 25-50 mg/day orally, often combined with phototherapy (PUVA or narrow-band ultraviolet B, UVB) for synergistic effect. Clinical response begins at 4-6 weeks and peaks at 12-16 weeks. Acitretin works particularly well for pustular psoriasis, erythrodermic psoriasis, and palmoplantar variants that respond poorly to other treatments.
Side effect profile is similar to isotretinoin: dry lips, skin, and eyes; elevated triglycerides; teratogenicity. The teratogenicity warning is particularly stringent for acitretin because it can be re-esterified to long-half-life etretinate in vivo, and the FDA advises a contraceptive period of at least three years after stopping it. For this reason, acitretin is largely restricted to male patients and post-menopausal women.
How long etretinate stays in the body. Etretinate, the acitretin metabolite, is stored in body fat for a long time. A 2022 Korean study (Jeong and colleagues) measured blood levels in 14 people who had taken acitretin and 58 controls. Blood acitretin tended to fall with time since stopping, but etretinate did not follow that pattern; alcohol intake did not change blood etretinate levels in this group (an earlier report had suggested alcohol speeds the conversion of acitretin to etretinate); and people differed widely in how long etretinate stayed in their blood. The authors call the data preliminary and say more research is needed before one contraception rule is applied to everyone.
For more on the disease context, see our Psoriasis page.
Photoaging Reversal Trials
The classic photoaging trials by Albert Kligman, Jonathan Weiss, and James Leyden in the late 1980s and early 1990s established topical tretinoin as the first scientifically demonstrated reversal of photoaging changes — not just prevention of further damage but actual partial reversal of accumulated damage.
Key findings from the Kligman / Weiss tretinoin photoaging trials:
- Daily 0.1% tretinoin cream applied for 6-12 months produces measurable improvements in fine wrinkles, mottled hyperpigmentation, skin roughness, and sallow color
- Improvements were objectively documented by silicone replica analysis, photography, and histology — not just subjective patient-reported outcomes
- Histologic findings showed increased basal keratinocyte proliferation, normalization of cellular atypia, increased dermal collagen synthesis, reduced solar elastosis, and increased dermal-epidermal anchoring
- Improvements continued progressively for 12+ months of treatment, then plateaued
- Discontinuation of treatment led to gradual loss of benefit over 6-12 months — tretinoin is a long-term commitment for photoaging maintenance, similar to its use for acne
The two founding studies. Kligman, Grove, Hirose and Leyden (Journal of the American Academy of Dermatology, 1986) compared daily 0.05% tretinoin cream with the same cream without the drug on the face and forearms. Under the light and electron microscope, treated skin showed a thicker outer layer replacing the thinned one, loss of abnormal (dysplastic and atypical) cells, clearing of microscopic actinic keratoses, more even pigment, new collagen and new small blood vessels in the upper dermis; the authors concluded tretinoin can at least partly reverse sun damage. Weiss and colleagues (JAMA, 1988) ran a 16-week randomized, double-blind trial in which each person put tretinoin on one forearm and plain cream on the other, and half also used tretinoin on the face. All 30 people who finished improved on the tretinoin forearm but not the plain-cream forearm; 14 of the 15 who used tretinoin on the face improved, against none of the faces given plain cream. The only side effect was irritation of treated skin.
For long-term anti-aging use, the pattern commonly described is:
- Treatment starts with 0.025% tretinoin cream nightly and is increased to 0.05% or 0.1% as tolerated
- Broad-spectrum SPF 30+ sunscreen is used daily alongside it
- Moisturizing skincare eases retinization
- Visible improvement typically takes 3-6 months; full benefit 12+ months
- Results are maintained only while use continues
Lower-concentration prescription options exist for sensitive-skin patients: tazarotene 0.05% and trifarotene 0.005% (a fourth-generation retinoid). For over-the-counter (OTC) alternatives without prescription requirements, see the retinaldehyde and retinyl ester sections below.
Retinaldehyde — The Gentler Alternative
Retinaldehyde (also called retinal) is the aldehyde intermediate in the conversion of retinol to retinoic acid. Topically applied retinaldehyde is metabolized by skin enzymes (aldehyde dehydrogenases) to retinoic acid at the cellular site of action, providing the same RAR signaling as tretinoin but at a lower peak concentration — and therefore with substantially less irritation.
Comparative pharmacology:
- Tretinoin (retinoic acid): potency 100%, irritation 100% (reference)
- Retinaldehyde (retinal): potency approximately 25-50%, irritation approximately 10-25% the favorable efficacy-to-tolerability ratio
- Retinol: potency approximately 5-10%, irritation approximately 5-10%
- Retinyl esters (retinyl palmitate, retinyl acetate): potency approximately 1-5%, irritation minimal
Retinaldehyde is available over-the-counter in concentrations up to 0.1% in serums and creams from a number of skincare makers. The trade-off compared to prescription tretinoin is slightly slower onset (perhaps 3-4 months to peak effect instead of 8-12 weeks) and slightly lower peak benefit, in exchange for dramatically better tolerability and no prescription required.
Retinaldehyde is commonly chosen by:
- First-time retinoid users who want to ease in
- Sensitive-skin patients who cannot tolerate tretinoin even at the lowest concentration
- Maintenance users who have completed an isotretinoin course and want a topical for long-term skin maintenance
- Patients who want anti-aging benefits without dealing with prescription logistics
Retinyl Esters in Over-the-Counter Cosmetics
Retinyl palmitate and retinyl acetate are the storage forms of Vitamin A in the body (the liver stores Vitamin A primarily as retinyl palmitate in hepatic stellate cells). When applied topically, retinyl esters must be hydrolyzed to retinol, then oxidized to retinaldehyde, then oxidized again to retinoic acid before they can engage RAR receptors. Each step is enzyme-limited, so peak skin retinoic acid concentration from a retinyl ester is dramatically lower than from applied tretinoin.
The practical consequence is that retinyl ester products in mass-market cosmetics provide gentle, slow-acting anti-aging effects with minimal irritation, but require longer treatment timelines (6-12 months) to produce visible benefit comparable to a few months of prescription tretinoin. They are used as entry-level retinoids and as maintenance products for very sensitive skin, but they do not match prescription strength.
One specific cosmetic-safety concern: the U.S. Food and Drug Administration has reviewed but not enacted concerns about retinyl palmitate possibly increasing ultraviolet-driven skin damage when applied just before sun exposure. The mechanism is debated; some researchers have suggested retinyl palmitate may catalyze free-radical formation under ultraviolet (UV) light. Common practice is to apply retinyl palmitate at bedtime (as with all retinoids) and to use daily sunscreen — both of which are standard retinoid practice anyway.
Adapalene — Over-the-Counter Synthetic Retinoid
Adapalene is a third-generation synthetic retinoid that selectively binds RAR-beta and RAR-gamma receptors. It was approved for prescription acne use in the 1990s and was switched to over-the-counter status in the United States in 2016 — making it the only true retinoid (RAR-binding compound) available without a prescription.
Compared to tretinoin:
- Better photostability (does not degrade in daylight, so can be applied at any time)
- Better tolerability profile (less retinization in the first weeks)
- Similar efficacy for inflammatory acne
- Slightly less efficacy for comedonal acne
- Less photoaging data — the U.S. Food and Drug Administration approval is for acne only, not photoaging. In a 2018 Brazilian investigator-blinded trial (Bagatin and colleagues), once-daily adapalene 0.3% gel was non-inferior to tretinoin 0.05% cream for photoaged skin over 24 weeks: the two did not differ on overall photoaging, wrinkles around the eyes and on the forehead, freckles and dark spots, or actinic keratoses, and safety was similar
- Available as 0.1% or 0.3% gel
For people wanting predictable RAR signaling without a prescription, adapalene 0.1% gel is often the first retinoid tried. It is commonly applied the same way as tretinoin: a pea-sized amount on dry skin, every other night at first and then nightly, with moisturizer and sunscreen.
Pregnancy Contraindication and iPLEDGE
Oral retinoids are the most reliably teratogenic drug class in dermatology. The teratogenic effect was first documented in case series in the early 1980s. The Lammer 1985 NEJM paper documented a characteristic pattern of fetal malformations from isotretinoin exposure: central nervous system (CNS) abnormalities (hydrocephalus, microcephaly, cortical malformations), craniofacial defects (microtia/anotia, cleft palate, micrognathia), cardiac outflow tract defects (transposition of great vessels, tetralogy of Fallot), and thymic hypoplasia.
The paper studied 154 pregnancies exposed to isotretinoin. Their outcomes were 95 elective abortions, 26 babies without major malformations, 12 miscarriages and 21 malformed babies. In the 36 of those pregnancies that were followed from early on (prospectively), there were 8 miscarriages, 23 normal babies and 5 malformed babies. Exposure was linked to a 25.6 times higher risk of a group of selected major malformations (95% confidence interval 11.4 to 57.5). Among the 21 malformed babies, the defects counted were small or missing ears (microtia/anotia, 15 babies), a small jaw (micrognathia, 6), cleft palate (3), heart outflow and aortic-arch defects (8), thymus defects (7), retina or optic-nerve defects (4) and brain and nervous-system malformations (18).
The U.S. response evolved over decades from voluntary patient warnings (1982) through the isotretinoin pregnancy-prevention programme known as SMART (2002) to the current iPLEDGE program (2006-present), a mandatory risk evaluation and mitigation strategy (REMS) administered by the U.S. Food and Drug Administration:
- Both prescribers and patients must register
- Female patients of reproductive potential must commit to two simultaneous forms of contraception
- Monthly pregnancy testing required before each prescription refill
- Prescriptions are limited to 30-day supplies, must be filled within 7 days of pregnancy test
- Patient must answer monthly comprehension questions about teratogenicity
- Prescriber must verify all elements through the iPLEDGE web portal
- Pharmacy must verify all elements before dispensing
The system is logistically burdensome but has reduced isotretinoin-exposed pregnancies. The teratogenic risk persists for approximately one month after discontinuing isotretinoin (the elimination half-life of the parent drug and its metabolites). For acitretin, the FDA advises a contraceptive period of at least three years after stopping because of potential re-esterification to long-half-life etretinate.
For topical tretinoin, some older generic cream and gel labels still carry the former U.S. Food and Drug Administration pregnancy category C. Labels written in the FDA's newer format, which drops the letter categories, state that published observational studies of topical tretinoin in pregnant women have not established a drug-associated risk of major birth defects, miscarriage or other harm to mother or baby, that these studies have limitations such as small size, and that case reports describe babies exposed in the first trimester with major birth defects similar to those seen after oral retinoids. The over-the-counter adapalene gel label says “Pregnancy/Breastfeeding, ask a doctor before use.” Absorption through intact skin is typically very low, and most dermatologists advise pausing topical retinoids in pregnancy.
How Retinoids Are Used in Practice
The regimens below describe how retinoids are commonly used in dermatology practice and in the drug programmes above. They are a description, not a treatment plan.
For acne (mild-to-moderate)
- Common starting point: over-the-counter adapalene 0.1% gel or prescription tretinoin 0.025% cream
- Frequency: usually every other night for the first 2 weeks, then nightly
- Usually used with: a gentle non-comedogenic cleanser, a ceramide-based moisturizer and daily SPF 30+ sunscreen
- Typical timeline: visible improvement at 8-12 weeks, peak benefit at 4-6 months
- When the response is not enough after 4 months, common next steps are a stronger tretinoin (0.05% or 0.1%), benzoyl peroxide in the morning, or a course of antibiotics
For severe nodulocystic acne
- Isotretinoin is prescribed through dermatology
- Before treatment: pregnancy test (women), blood fats (lipid panel), liver function tests, complete blood count
- iPLEDGE enrollment for women who could become pregnant
- Standard course: 0.5-1.0 mg/kg/day for 16-24 weeks, target cumulative dose 120-150 mg/kg
- Monthly monitoring: pregnancy test, lipids, LFTs, symptom check
For photoaging / anti-aging
- Common starting point: over-the-counter retinaldehyde 0.05% serum or prescription tretinoin 0.025%
- Frequency: usually every other night for 2 weeks, then nightly
- Often combined with: a vitamin C serum in the morning, daily SPF 30+ sunscreen, a weekly hydrating mask
- Typical timeline: visible improvement at 3-6 months, continued improvement through year 1, plateau thereafter
- Benefit lasts only while use continues
For psoriasis (moderate-to-severe)
- Acitretin is prescribed through dermatology
- Acitretin 25-50 mg/day, often combined with phototherapy (PUVA or narrow-band UVB)
- Monitoring: blood fats and liver function tests every 1-3 months, bone density at the start
- For women who could become pregnant, the FDA advises contraception for at least three years after stopping
Cautions
- Teratogenicity in pregnancy — absolute for oral retinoids (isotretinoin, acitretin, bexarotene, alitretinoin). Two forms of contraception, monthly pregnancy testing, iPLEDGE program enrollment required for isotretinoin in the United States. For acitretin, the FDA advises contraception for at least three years after stopping. Topical retinoids in pregnancy are typically avoided despite limited evidence of harm.
- Concurrent tetracycline antibiotics with isotretinoin — absolute contraindication; combination increases risk of pseudotumor cerebri (idiopathic intracranial hypertension) with potential vision loss. Doxycycline, minocycline and tetracycline are therefore stopped before isotretinoin is started.
- Liver disease — isotretinoin and acitretin can elevate transaminases. Pre-existing liver disease is a relative contraindication, and liver tests are monitored during treatment.
- Hypertriglyceridemia — isotretinoin and acitretin can substantially elevate triglycerides. Pre-existing severe hypertriglyceridemia is a relative contraindication, and blood fats are monitored.
- Depression / mood symptoms with isotretinoin — U.S. Food and Drug Administration label warns of association; controlled studies are inconsistent. A 2024 meta-analysis of 25 studies found no higher population-level risk of psychiatric disorders or suicide among users, and its authors still describe monitoring patients for signs of mental distress during treatment.
- Bone effects with chronic retinoid use — long-term acitretin can produce diffuse interstitial skeletal hyperostosis (DISH) and bone loss. Periodic bone density checks are described for multi-year users.
- Sun sensitivity with all topical retinoids — retinized skin is more vulnerable to ultraviolet damage, which is why daily broad-spectrum SPF 30+ sunscreen is standard retinoid practice.
- Irritation in first weeks (retinization) — expected, not allergic. It is usually managed with reduced frequency (every 2-3 nights at first), a low-strength formulation, a ceramide moisturizer and a gentle cleanser; the usual approach is to use the retinoid less often rather than stop it, until tolerance develops.
Key Research Papers
- Lammer EJ et al. (1985). Retinoic acid embryopathy. NEJM. — PubMed PMID: 3162101
- Kligman AM, Grove GL, Hirose R, Leyden JJ (1986). Topical tretinoin for photoaged skin. J Am Acad Dermatol;15(4 Pt 2):836-59. — PubMed PMID: 3771853
- Weiss JS et al. (1988). Topical tretinoin improves photoaged skin. A double-blind vehicle-controlled study. JAMA. — PubMed PMID: 3336176
- Plewig G, Nikolowski J, Wolff HH (1982). Action of isotretinoin in acne rosacea and gram-negative folliculitis. J Am Acad Dermatol;6(4 Pt 2 Suppl):766-85. — PubMed PMID: 6461680
- Goldfarb MT, Ellis CN, Voorhees JJ (1990). Topical tretinoin: its use in daily practice to reverse photoageing. British Journal of Dermatology;122 Suppl 35:87-91. — PubMed PMID: 2186791
- Fisher GJ, Wang ZQ, Datta SC, Varani J, Kang S, Voorhees JJ (1997). Pathophysiology of premature skin aging induced by ultraviolet light. NEJM;337(20):1419-28. — PubMed PMID: 9358139
- Saurat JH et al. (1994). Topical retinaldehyde on human skin: biologic effects and tolerance. JID. — PubMed PMID: 7798613
- Pile HD, Patel P (2025). Isotretinoin. StatPearls. Treasure Island (FL): StatPearls Publishing. — PubMed PMID: 30247824
- Mukherjee S et al. (2006). Retinoids in the treatment of skin aging: an overview of clinical efficacy and safety. Clinical Interventions in Aging. — PubMed PMID: 18046911
- Bagatin E, Gonçalves HS, Sato M, Almeida LMC, Miot HA (2018). Comparable efficacy of adapalene 0.3% gel and tretinoin 0.05% cream as treatment for cutaneous photoaging. European Journal of Dermatology;28(3):343-350. — PubMed PMID: 30105991
- Huang CK, Miller TA (2007). The truth about over-the-counter topical anti-aging products: a comprehensive review. Aesthetic Surgery Journal. — PubMed PMID: 19341668
- Tan NKW, Tang A, MacAlevey NCYL, Tan BKJ, Oon HH (2024). Risk of Suicide and Psychiatric Disorders Among Isotretinoin Users: A Meta-Analysis. JAMA Dermatology;160(1):54-62. — PubMed PMID: 38019562
- Al Muqarrab F, Almohssen A (2022). Low-dose oral isotretinoin for the treatment of adult patients with mild-to-moderate acne vulgaris: Systematic review and meta-analysis. Dermatologic Therapy;35(4):e15311. — PubMed PMID: 35000295
- Jeong JH, Hyun GH, Park YJ, Kwon SW, Lee AY (2022). Clinical Factors Affecting the Serum Retention of a Teratogenic Etretinate after the Acitretin Administration. Biomolecules & Therapeutics;30(6):562-569. — PubMed PMID: 35871607
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin A Overview
- Vitamin A Benefits Hub
- Beef Liver for Vitamin A
- Vitamin A for Vision
- Vitamin A for Immune Function
- Beta-Carotene vs Preformed
- Acne
- Psoriasis
- Eczema
- Zinc (Acne, RBP Synthesis)
- Vitamin D3
- Vitamin E
- Vitamin C (Photoaging Synergy)
- Collagen
- Organ Meats
- Deficiency
- Toxicity
- History
- Sources