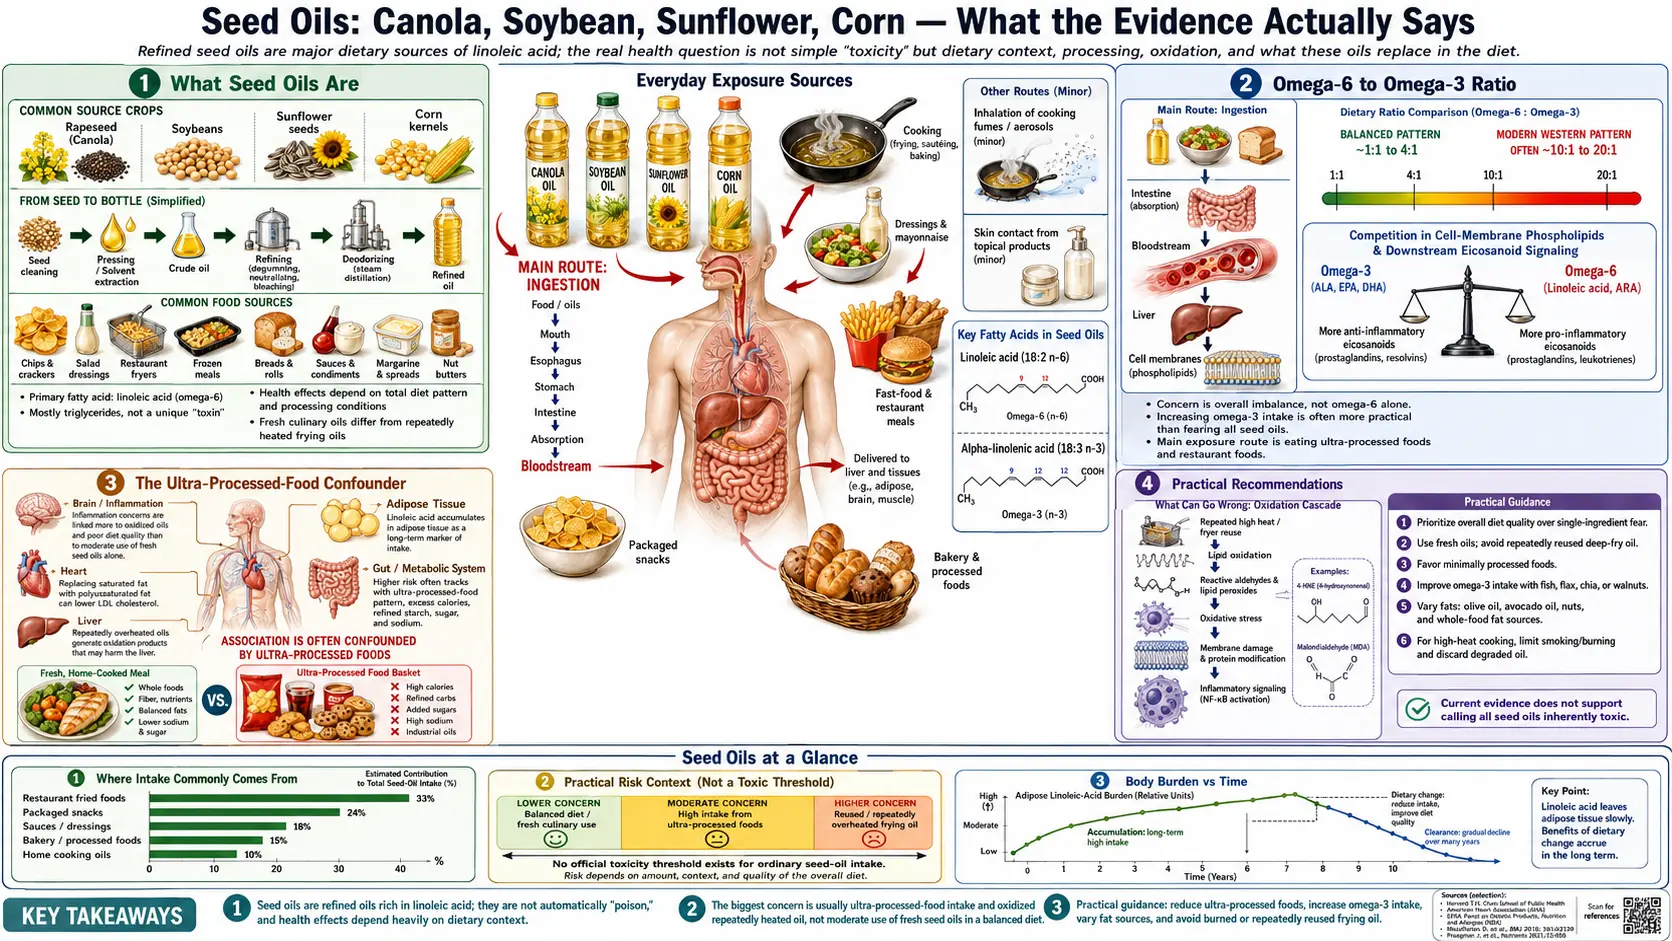
Seed Oils: Canola, Soybean, Sunflower, Corn — What the Evidence Actually Says

Few topics in modern nutrition have generated as much public debate as seed oils — industrial vegetable oils extracted from seeds and grains including soybean, canola (rapeseed), corn, sunflower, safflower, cottonseed, grapeseed, and rice bran. Critics argue that their high linoleic-acid (omega-6) content, solvent extraction with hexane, oxidation during high-heat cooking, and their pervasive presence in ultra-processed foods make them a major driver of chronic inflammation and metabolic disease. Defenders cite randomized trials in which linoleic-acid-rich oils lowered cholesterol, cohort studies that link higher linoleic acid to lower cardiovascular risk, and expert reviews that read the trials as showing benefit. The evidence is considerably more mixed than either camp usually acknowledges.
This article sets out which parts of the case are well established, which are contested, and which have not been tested.
Table of Contents
- What Seed Oils Are
- The Claims, Laid Out
- The Linoleic Acid Debate
- Omega-6 to Omega-3 Ratio
- Heating, Oxidation, and Aldehydes
- Industrial Processing
- The Ultra-Processed-Food Confounder
- The Randomized-Trial Evidence
- What the Cohort Studies Show
- Where the Evidence Actually Leaves Us
- Findings Most Relevant to Everyday Eating
- How Common Cooking Fats Behave Under Heat
- Key Research Papers
- Connections
- Featured Videos
What Seed Oils Are
“Seed oils” is a popular rather than a scientific category. It generally means the industrially extracted oils pressed or solvent-extracted from seeds and grains: soybean, corn, canola (rapeseed), sunflower, safflower, cottonseed, grapeseed, rice bran and peanut. What they have in common is a high proportion of linoleic acid, an omega-6 polyunsaturated fatty acid, and a manufacturing process that involves heat and usually a solvent.
Their share of the diet has changed more than almost any other food component in the last century. Working from United States food-availability data, Blasbalg and colleagues (American Journal of Clinical Nutrition, 2011) estimated that per-capita soybean oil consumption rose more than 1000-fold between 1909 and 1999, and that the availability of linoleic acid rose from 2.79% to 7.21% of energy. That is a genuinely unprecedented dietary shift. The argument is not about whether the change happened; it is about whether it caused harm.
One clarification: olive oil and avocado oil are fruit oils, not seed oils — pressed from the flesh of the fruit rather than from a seed, and mostly monounsaturated. They are not usually grouped with seed oils in this debate, although refined grades of both exist.
The Claims, Laid Out
The case against seed oils, stated at its strongest, is a chain of four claims. Each link is examined separately in the sections below, because they are of very different evidential strength — and the chain is only as strong as its weakest link.
- Linoleic acid is inherently inflammatory, because it is a precursor to arachidonic acid and thence to pro-inflammatory eicosanoids.
- The omega-6 to omega-3 ratio has shifted dramatically — in one widely cited estimate, from an ancestral ratio of about 1:1 to between 15:1 and 16.7:1 in Western diets.
- Polyunsaturated fats oxidise readily when heated, producing toxic aldehydes that are consumed with fried food.
- The industrial process itself — hexane extraction, bleaching, deodorising — produces a degraded product.
The Linoleic Acid Debate
The mechanistic story is real: linoleic acid can be elongated and desaturated to arachidonic acid, which is the substrate for prostaglandins, thromboxanes and leukotrienes, several of which are pro-inflammatory. From a biochemistry diagram, the inference that eating more linoleic acid means more inflammation looks obvious.
Two systematic reviews of human trials tested that inference directly.
- Changing dietary linoleic acid did not change blood arachidonic acid. Rett and Whelan (Nutrition & Metabolism, 2011) reviewed adult trials on Western-type diets. Raising dietary linoleic acid up to six-fold, or cutting it by up to 90%, was not significantly correlated with changes in arachidonic acid in plasma or serum phospholipids, and the authors concluded that modifying current linoleic acid intake does not change arachidonic acid levels in plasma, serum or red blood cells in adults eating Western-type diets.
- Adding linoleic acid did not raise inflammatory markers. Johnson and Fritsche (Journal of the Academy of Nutrition and Dietetics, 2012) reviewed 15 randomised controlled trials in healthy people. None reported significant changes in a wide range of inflammatory markers, including C-reactive protein, fibrinogen, cytokines, soluble adhesion molecules and TNF-α; the authors concluded that virtually no evidence from such trials shows that adding linoleic acid to the diet raises inflammatory markers.
These trials measured blood markers in healthy adults over weeks to months; they do not address whether decades of high intake affect disease. Within those limits, the first link in the chain — the one doing most of the rhetorical work — is the one that has been tested most directly, and the tests did not support it.
Omega-6 to Omega-3 Ratio
The ratio argument holds that omega-6 and omega-3 fats compete for the same desaturase and elongase enzymes, so an excess of omega-6 crowds out the conversion of alpha-linolenic acid to EPA and DHA. The competition is real at the enzyme level.
The ratio itself is an estimate attached to a hypothesis. Simopoulos (Biomedicine & Pharmacotherapy, 2002) wrote that several sources of information suggest humans evolved on an omega-6 to omega-3 ratio of about 1:1, against 15:1 to 16.7:1 in Western diets, and argued that a high ratio promotes cardiovascular, inflammatory and autoimmune disease. The United States food-availability analysis by Blasbalg and colleagues put the linoleic to alpha-linolenic acid ratio at 6.4 in 1909 and 10.0 in 1999, and modelled that the rise in linoleic acid has likely lowered tissue EPA and DHA — a prediction from a model rather than a measurement.
How much the ratio matters depends partly on how much EPA and DHA the body makes from plant omega-3. Brenna (2002) summarised that studies generally agree whole-body conversion of alpha-linolenic acid to DHA is below 5% in humans, and that it depends on the omega-6 content of the diet. Burdge and Calder (2005) described conversion to EPA as limited in men and further conversion to DHA as very low, with higher conversion in women. A 2009 review by Brenna and colleagues found that supplemental alpha-linolenic acid raises blood EPA but has little effect on blood DHA, and concluded that, with no other change in diet, blood DHA status improves with preformed DHA but not with alpha-linolenic acid or other precursors.
The two readings therefore coexist. Ratio proponents see omega-6 crowding an already limited pathway; on the trial data, blood DHA tracks the intake of preformed DHA — from oily fish such as salmon, sardines, mackerel and herring, or from supplements — more closely than any change in plant omega-3.
Heating, Oxidation, and Aldehydes
This is the strongest part of the case against, and it deserves to be stated at full strength.
Polyunsaturated fats have multiple double bonds, and every double bond is a site where oxygen can attack. Heat, light, oxygen and time all accelerate this. Oils held at frying temperatures produce lipid oxidation products, including aldehydes such as 4-hydroxynonenal (4-HNE), malondialdehyde and various alkenals. A 2021 review by Grootveld (Frontiers in Nutrition) sets out the case that polyunsaturate-rich oils are unsuitable for high-temperature frying, covering how these aldehydes form, their fate in the body, and their mutagenicity and genotoxicity — evidence drawn largely from laboratory and animal work.
What the evidence supports:
- Aldehydes accumulate the longer oil is heated. In laboratory frying at 180 °C, aldehyde levels rose with heating time, and continuous heating changed the oils more than interrupted heating (Ampem and colleagues, 2023; Gibson and colleagues, 2023). Ampem and colleagues single out reused oil as the setting where suppressing these compounds most needs study.
- More polyunsaturated fat means more oxidation. In simulated shallow frying at 180 °C, production of α,β-unsaturated aldehydes ran chia > rapeseed ≈ soybean > olive oil, in line with each oil’s polyunsaturated and monounsaturated content (Gibson and colleagues, 2023). In the 2023 frying study, polyunsaturate-rich oils were the most susceptible, while coconut oil, very high in saturated fat, was highly resistant (Ampem and colleagues).
- Fried-food consumption is associated with more cardiovascular disease. A 2021 meta-analysis of observational studies (Qin and colleagues, Heart) found the highest versus lowest fried-food intake associated with more major cardiovascular events (relative risk 1.28), coronary heart disease (1.22) and heart failure (1.37), but not with cardiovascular mortality (1.02) or all-cause mortality (1.03); the authors noted high heterogeneity and possible recall bias.
What it does not establish:
- How much of these aldehydes people actually eat, and what that amount does. Grootveld’s review notes that estimates of human dietary aldehyde intake are limited mostly to acrolein and smaller aldehydes, and calls for tolerable daily intakes for a much wider range of these compounds and for epidemiological studies linking their intake to chronic disease.
- That the fried-food association is caused by the aldehydes specifically, rather than by the calories, the salt, the refined starch, or the dietary pattern that goes with frequent fried food.
On this evidence, the best-documented hazard is oil held at frying temperature for long periods or used again and again, where aldehyde levels are highest, rather than the mere presence of a seed oil in a kitchen — with the qualification that, under the same heating, polyunsaturated oils generate more of these compounds than monounsaturated or saturated fats.
Industrial Processing
Most refined seed oils are extracted with hexane, then refined, bleached and deodorised (the “RBD” process). This is genuinely industrial and quite unlike the mechanical pressing used for extra-virgin olive oil.
- Hexane residue in finished oil is regulated; the European Union sets a maximum residue limit. In a 2021 analysis of four edible oils sold in Malaysia, residue exceeded the EU limit only in the sunflower oil (Samsuri and colleagues). Studies linking dietary hexane residue to health outcomes in people are lacking.
- Deodorising, a high-temperature step, generates small amounts of trans fat along with other processing contaminants (3-MCPD esters and glycidyl esters). In a laboratory study of sunflower oil, trans fat rose from 0.062% to 0.698% as deodorising temperature and time increased (An and colleagues, 2022). Five refined soybean oils sold in Brazil contained 5.8 to 30.2 mg/g of trans polyunsaturated fatty acids, with the variation attributed to differences in deodorisation between producers (Martin and colleagues, 2006). Unrefined, cold-pressed oils do not go through this step.
- Refining removes part of the oil’s vitamin E. In the same sunflower-oil study, deodorising lowered total tocopherols from 535.94 to 240.26 mg/kg across the conditions tested, with retention falling from 96.29% to 44.83%; phytosterols fell too. A comparison of traditional and newer vegetable oils found that refinement lowers tocopherol and tocotrienol content, although the grade on the label did not predict the content of a given oil (Wen and colleagues, 2020). Refining also removes most of the polyphenols from olive oil, as the Olive Oil page describes, and PREDIMED tested extra-virgin olive oil only.
So the processing objection is partly valid: refining adds small amounts of trans fat and other contaminants and removes part of the oil’s own antioxidants, while the evidence on solvent residue is regulatory and analytical rather than clinical.
The Ultra-Processed-Food Confounder
This is the single biggest interpretive problem in the whole debate, and it cuts both ways.
Seed oils are ubiquitous in ultra-processed food: crisps, biscuits, fast food, ready meals, commercial baked goods, salad dressings. People who eat a lot of seed oil often eat a lot of ultra-processed food — along with the refined starch, added sugar, salt, emulsifiers and calorie density that come with it. Observational studies of “seed oil intake” are therefore studying a whole dietary pattern.
That ultra-processed pattern has independent, randomised evidence of harm. Hall and colleagues (Cell Metabolism, 2019) admitted 20 adults to the NIH Clinical Center and gave them ultra-processed or unprocessed diets for two weeks each, with meals matched for presented calories, energy density, macronutrients, sugar, sodium and fibre, eaten freely. On the ultra-processed diet participants ate 508 kcal more per day and gained 0.9 kg; on the unprocessed diet they lost 0.9 kg. Processing changed how much people ate even when the nutrients on offer were matched.
The implication is uncomfortable for both camps. The observational signal blamed on seed oils may belong partly to the food they arrive in — and because seed oils are concentrated in ultra-processed food, a diet lower in ultra-processed food is also lower in seed oil as a side effect. Studies of either exposure are hard to separate from the other.
The Randomized-Trial Evidence
Two recovered-data analyses led by Christopher Ramsden are the most-cited trial evidence against linoleic acid, and they are genuinely important. In both, replacing saturated fat with linoleic-acid-rich oil lowered cholesterol without lowering deaths. Here is what each found.
- Sydney Diet Heart Study (Ramsden et al., BMJ 2013). 458 men aged 30–59 with a recent coronary event were randomised in 1966–73 to replace saturated fat with safflower oil and safflower-oil polyunsaturated margarine, or to no specific dietary instruction. Serum cholesterol fell more in the intervention group (−13.3% v −5.5% at 12 months), yet that group had higher all-cause mortality (17.6% v 11.8%; hazard ratio 1.62), cardiovascular mortality (17.2% v 11.0%) and coronary mortality (16.3% v 10.1%). Trans fat is a disputed caveat: the trial did not record it. Ramsden’s team noted that cutting common margarines and shortenings would be expected to lower trans-fat intake in the intervention group, possibly offset by small amounts in the safflower margarine, whose exact composition was not specified. The team also proposed that oxidised linoleic acid metabolites might help explain the excess deaths — a hypothesis, not a finding of the trial.
- Minnesota Coronary Experiment (Ramsden et al., BMJ 2016). A double-blind trial run in 1968–73 in one nursing home and six state mental hospitals, with 9,423 women and men aged 20–97. The intervention replaced saturated fat with corn oil and corn-oil polyunsaturated margarine; the control diet was high in saturated fat from animal fats, common margarines and shortenings — which, the authors note, were rich in trans fat. The intervention lowered serum cholesterol (−13.8% v −1.0%) and showed no mortality benefit in the full cohort or in any prespecified subgroup. Each 30 mg/dL fall in serum cholesterol was associated with a 22% higher risk of death (hazard ratio 1.22), and a 1981 thesis by one of the original investigators noted that the excess mortality in the diet group “seems to have been confined primarily to patients 65 or older.” Caveats: only 2,403 of those randomised stayed on the study diets for a year or more, and their mean follow-up was 2.9 years. In the same paper, a meta-analysis of five such trials (10,808 participants) found no benefit on coronary mortality (hazard ratio 1.13) or all-cause mortality (1.07).
Set against these, what pooled trial evidence shows depends heavily on which trials are pooled.
The Cochrane review of omega-6 fats (Hooper and colleagues, 2018) pooled 19 randomised trials in 6,461 participants followed for one to eight years. It found low-quality evidence that increasing omega-6 fats may make little or no difference to all-cause mortality (risk ratio 1.00) or cardiovascular events (0.97), was uncertain about cardiovascular mortality (very low-quality evidence), and found that more omega-6 may reduce myocardial infarction (risk ratio 0.88, 95% CI 0.76 to 1.02) and lowers total cholesterol a little.
The 2020 Cochrane review of cutting saturated fat (Hooper and colleagues; 15 trials, 56,675 participants) found that reducing saturated fat for at least two years lowered combined cardiovascular events by 17% (risk ratio 0.83), with little or no effect on all-cause mortality (0.96) or cardiovascular mortality (0.95). Replacing the saturated fat with polyunsaturated fat or with carbohydrate did not differ significantly in its subgroup analysis.
Hamley (Nutrition Journal, 2017) sorted the trials of replacing saturated fat with mostly omega-6 polyunsaturated fat by whether the groups also differed in other ways. Pooling only the trials judged adequately controlled showed no effect on major coronary events (risk ratio 1.06) or total mortality (1.07); pooling all trials suggested fewer total coronary events (0.80).
The American Heart Association’s 2017 presidential advisory (Sacks et al., Circulation) reached a different conclusion: randomised trials that lowered saturated fat and replaced it with polyunsaturated vegetable oil reduced cardiovascular disease by about 30%, “similar to the reduction achieved by statin treatment,” and the panel concluded “strongly” that replacing saturated fat with unsaturated fats, especially polyunsaturated fats, will lower the incidence of cardiovascular disease. That disagreement over which trials belong in the pool is where much of the dispute genuinely lives, and readers deserve to see it rather than one side’s trial list.
What the Cohort Studies Show
The largest biomarker evidence points the other way from the seed-oil hypothesis, and the picture is incomplete without it.
Marklund and colleagues (Circulation, 2019) pooled individual-level data from 30 prospective cohorts in 13 countries (68,659 participants, 15,198 cardiovascular events), measuring linoleic acid in blood and fat tissue rather than relying on food questionnaires. Higher linoleic acid levels were associated with lower risk of total cardiovascular disease (hazard ratio 0.93 per interquintile range), cardiovascular mortality (0.78) and ischaemic stroke (0.88). Arachidonic acid levels were not associated with higher risk. Two of the authors reported research support from a food manufacturer for this work.
Farvid and colleagues (Circulation, 2014) pooled 13 cohort studies with 310,602 people: the highest versus lowest linoleic acid intake was associated with 15% fewer coronary events (relative risk 0.85) and 21% fewer coronary deaths (0.79), and replacing 5% of energy from saturated fat with linoleic acid with 9% fewer coronary events and 13% fewer coronary deaths.
Wang and colleagues (JAMA Internal Medicine, 2016), following 126,233 people for up to 32 years, found the highest versus lowest polyunsaturated fat intake associated with lower total mortality (hazard ratio 0.81), and estimated that replacing 5% of energy from saturated fat with polyunsaturated fat was associated with 27% lower total mortality.
These are observational and carry the usual confounding caveats — people with higher linoleic acid levels differ in other ways. But biomarker-based studies avoid the recall error that plagues dietary questionnaires, and the consistency across 30 cohorts is not easily dismissed. Accounts of the seed-oil case that leave this evidence out omit its strongest counter-argument.
Where the Evidence Actually Leaves Us
Setting aside the rhetoric on both sides, this is a fair summary by strength of evidence:
- Well supported: oil held at frying temperature accumulates aldehydes over time, and polyunsaturated oils generate more than monounsaturated or saturated fats; frequent fried-food consumption is associated with more cardiovascular disease in observational studies. Ultra-processed food caused excess calorie intake and weight gain in a controlled trial.
- Supported by systematic reviews of trials: in adults on Western-type diets, changing dietary linoleic acid does not change blood arachidonic acid, and adding it does not raise inflammatory markers in healthy people.
- Genuinely contested: whether replacing saturated fat with linoleic acid reduces cardiovascular events and deaths. The two recovered trials found lower cholesterol without fewer deaths; pooled analyses range from no effect to about 30% less cardiovascular disease depending on which trials they include; expert bodies reading the same literature reach different conclusions.
- Points away from harm: large cohorts, including biomarker-based ones, associate higher linoleic acid with lower cardiovascular risk and lower cardiovascular mortality.
- Not established: that seed oils are the primary driver of modern chronic disease, or that hexane residue at the levels found in oil causes harm.
- Unknown: whether the sheer magnitude of the historical increase in linoleic acid intake has long-term effects that no trial has been long enough to detect. This is the most defensible version of the concern, and current data cannot answer it.
Several findings hold under either reading of the dispute: the aldehyde load is highest in oil heated for long periods or reused, ultra-processed food raised calorie intake in a controlled trial, and blood DHA rises with preformed DHA rather than with plant omega-3.
Findings Most Relevant to Everyday Eating
- Deep-fried takeaway and restaurant food. Oil held at frying temperature for long periods, or reused, is where the frying studies above find the highest aldehyde levels, and fried-food intake is associated with more cardiovascular events.
- Extra-virgin olive oil. In PREDIMED (Estruch and colleagues; the 2013 report was retracted and republished in 2018 after protocol deviations in randomisation at some sites), 7,447 adults at high cardiovascular risk were assigned to a Mediterranean diet supplemented with extra-virgin olive oil, a Mediterranean diet supplemented with mixed nuts, or a control diet (advice to reduce dietary fat). Major cardiovascular events were lower in both Mediterranean arms (hazard ratio 0.69 with olive oil, 0.72 with nuts), so the result reflects the diet as a whole rather than the oil alone. In two large US cohorts, olive oil intake above half a tablespoon a day was associated with 14% lower cardiovascular disease and 18% lower coronary heart disease than no olive oil, but showed no significant association when compared with other plant oils combined (Guasch-Ferré and colleagues, 2020).
- Oily fish and omega-3. Blood DHA rises with preformed DHA from oily fish — salmon, sardines, mackerel, herring — or supplements, not with plant omega-3 (Brenna and colleagues, 2009).
- Ultra-processed food. It has controlled-trial evidence of excess calorie intake and weight gain, and it is one of the main ways seed oils enter the diet.
- Cold-pressed seed oils skip the high-temperature deodorising step that forms trans fat and the other processing contaminants described above. Light, heat and oxygen oxidise every oil in storage.
- Whole-food diets. Meals built from vegetables, fruit, olive oil, fish, eggs, meat, nuts, legumes, and whole grains such as brown rice, oats and barley contain little seed oil beyond what is used in cooking.
- Scale. The trials and cohorts above concern sustained intake over years, not occasional small amounts such as a restaurant salad dressed with canola oil.
How Common Cooking Fats Behave Under Heat
Smoke point is the temperature at which an oil starts to give off visible smoke. It is a rough guide but not the whole story — degree of unsaturation and antioxidant content also shape how an oil behaves under heat, as the frying studies above show.
- Unheated uses — extra-virgin olive oil, cold-pressed rapeseed, walnut and flaxseed oils are commonly used in dressings and for finishing. Walnut and flaxseed oils are highly polyunsaturated, the class that forms the most aldehydes when heated.
- Sautéing and roasting — in simulated shallow frying at 180 °C, olive oil formed fewer α,β-unsaturated aldehydes than rapeseed, soybean or chia oil (Gibson and colleagues, 2023), in line with its mostly monounsaturated profile; the Olive Oil page covers its heat stability in more detail. Butter and ghee are also used for cooking; ghee has had the milk solids removed and is commonly used at higher heat than butter.
- High-heat cooking — refined oils, including refined avocado oil and refined olive oil, and ghee are commonly used. Refining raises the smoke point but, as described above, removes part of the oil’s own antioxidants.
- Deep frying — the setting where the frying studies find the most oxidation, especially when oil is heated continuously for long periods or reused.
- Storage — oxidation begins before the oil ever meets a pan; light, heat and oxygen all accelerate it.
- Cost — extra-virgin olive oil generally costs more than refined seed oils, a real constraint for many households.
Key Research Papers
Each citation below was checked against its PubMed record; the linked DOI resolves to the paper named. Papers supporting and opposing the seed-oil hypothesis are both included at full strength, because the dispute is real and readers are entitled to see both sides of it.
- Ramsden CE, Zamora D, Leelarthaepin B, et al. Use of dietary linoleic acid for secondary prevention of coronary heart disease and death: evaluation of recovered data from the Sydney Diet Heart Study and updated meta-analysis. BMJ. 2013;346:e8707. — doi:10.1136/bmj.e8707 · PubMed PMID: 23386268 — higher mortality in the linoleic acid arm; trans-fat intake was not recorded.
- Ramsden CE, Zamora D, Majchrzak-Hong S, et al. Re-evaluation of the traditional diet-heart hypothesis: analysis of recovered data from Minnesota Coronary Experiment (1968–73). BMJ. 2016;353:i1246. — doi:10.1136/bmj.i1246 · PubMed PMID: 27071971 — cholesterol fell, mortality did not improve; the control diet’s margarines and shortenings were rich in trans fat.
- Hooper L, Al-Khudairy L, Abdelhamid AS, et al. Omega-6 fats for the primary and secondary prevention of cardiovascular disease. Cochrane Database Syst Rev. 2018;11(11):CD011094. — doi:10.1002/14651858.CD011094.pub4 · PubMed PMID: 30488422 — may make little or no difference to mortality or cardiovascular events (low-quality evidence).
- Sacks FM, Lichtenstein AH, Wu JHY, et al. Dietary fats and cardiovascular disease: a presidential advisory from the American Heart Association. Circulation. 2017;136(3):e1–e23. — doi:10.1161/CIR.0000000000000510 · PubMed PMID: 28620111 — the opposing expert reading of the same literature.
- Marklund M, Wu JHY, Imamura F, et al. Biomarkers of dietary omega-6 fatty acids and incident cardiovascular disease and mortality. Circulation. 2019;139(21):2422–2436. — doi:10.1161/CIRCULATIONAHA.118.038908 · PubMed PMID: 30971107 — 30 cohorts; higher linoleic acid associated with lower risk.
- Johnson GH, Fritsche K. Effect of dietary linoleic acid on markers of inflammation in healthy persons: a systematic review of randomized controlled trials. J Acad Nutr Diet. 2012;112(7):1029–1041. — doi:10.1016/j.jand.2012.03.029 · PubMed PMID: 22889633 — no effect on inflammatory markers.
- Rett BS, Whelan J. Increasing dietary linoleic acid does not increase tissue arachidonic acid content in adults consuming Western-type diets: a systematic review. Nutr Metab (Lond). 2011;8:36. — doi:10.1186/1743-7075-8-36 ( PubMed PMID: 21663641)
- Wang DD, Li Y, Chiuve SE, et al. Association of specific dietary fats with total and cause-specific mortality. JAMA Intern Med. 2016;176(8):1134–1145. — doi:10.1001/jamainternmed.2016.2417 ( PubMed PMID: 27379574)
- Hall KD, Ayuketah A, Brychta R, et al. Ultra-processed diets cause excess calorie intake and weight gain: an inpatient randomized controlled trial of ad libitum food intake. Cell Metab. 2019;30(1):67–77.e3. — doi:10.1016/j.cmet.2019.05.008 · PubMed PMID: 31105044 — the confounder, tested directly.
- Guasch-Ferré M, Liu G, Li Y, et al. Olive oil consumption and cardiovascular risk in U.S. adults. J Am Coll Cardiol. 2020;75(15):1729–1739. — doi:10.1016/j.jacc.2020.02.036 ( PubMed PMID: 32147453)
- Estruch R, Ros E, Salas-Salvadó J, et al.; PREDIMED Study Investigators. Primary prevention of cardiovascular disease with a Mediterranean diet supplemented with extra-virgin olive oil or nuts. N Engl J Med. 2018;378(25):e34. — doi:10.1056/NEJMoa1800389 · PubMed PMID: 29897866 — corrected and republished PREDIMED report; the 2013 report was retracted after protocol deviations in randomisation.
- Farvid MS, Ding M, Pan A, et al. Dietary linoleic acid and risk of coronary heart disease: a systematic review and meta-analysis of prospective cohort studies. Circulation. 2014;130(18):1568–1578. — doi:10.1161/CIRCULATIONAHA.114.010236 · PubMed PMID: 25161045 — 13 cohorts; higher linoleic acid intake associated with fewer coronary events.
- Hooper L, Martin N, Jimoh OF, et al. Reduction in saturated fat intake for cardiovascular disease. Cochrane Database Syst Rev. 2020;8(8):CD011737. — doi:10.1002/14651858.CD011737.pub3 · PubMed PMID: 32827219 — fewer combined cardiovascular events, little or no effect on mortality.
- Hamley S. The effect of replacing saturated fat with mostly n-6 polyunsaturated fat on coronary heart disease: a meta-analysis of randomised controlled trials. Nutr J. 2017;16(1):30. — doi:10.1186/s12937-017-0254-5 · PubMed PMID: 28526025 — no effect when only adequately controlled trials are pooled.
- Blasbalg TL, Hibbeln JR, Ramsden CE, et al. Changes in consumption of omega-3 and omega-6 fatty acids in the United States during the 20th century. Am J Clin Nutr. 2011;93(5):950–962. — doi:10.3945/ajcn.110.006643 · PubMed PMID: 21367944 — food-availability estimates, 1909–1999.
- Simopoulos AP. The importance of the ratio of omega-6/omega-3 essential fatty acids. Biomed Pharmacother. 2002;56(8):365–379. — doi:10.1016/s0753-3322(02)00253-6 · PubMed PMID: 12442909 — review setting out the ratio hypothesis.
- Brenna JT. Efficiency of conversion of alpha-linolenic acid to long chain n-3 fatty acids in man. Curr Opin Clin Nutr Metab Care. 2002;5(2):127–132. — doi:10.1097/00075197-200203000-00002 · PubMed PMID: 11844977
- Burdge GC, Calder PC. Conversion of alpha-linolenic acid to longer-chain polyunsaturated fatty acids in human adults. Reprod Nutr Dev. 2005;45(5):581–597. — doi:10.1051/rnd:2005047 · PubMed PMID: 16188209
- Brenna JT, Salem N Jr, Sinclair AJ, Cunnane SC; ISSFAL. alpha-Linolenic acid supplementation and conversion to n-3 long-chain polyunsaturated fatty acids in humans. Prostaglandins Leukot Essent Fatty Acids. 2009;80(2–3):85–91. — doi:10.1016/j.plefa.2009.01.004 · PubMed PMID: 19269799 — blood DHA rises with preformed DHA, not with ALA.
- Grootveld M. Evidence-based challenges to the continued recommendation and use of peroxidatively-susceptible polyunsaturated fatty acid-rich culinary oils for high-temperature frying practises: experimental revelations focused on toxic aldehydic lipid oxidation products. Front Nutr. 2021;8:711640. — doi:10.3389/fnut.2021.711640 · PubMed PMID: 35071288 — the case against frying with polyunsaturated oils.
- Gibson M, Percival BC, Edgar M, Grootveld M. Low-field benchtop NMR spectroscopy for quantification of aldehydic lipid oxidation products in culinary oils during shallow frying episodes. Foods. 2023;12(6):1254. — doi:10.3390/foods12061254 · PubMed PMID: 36981180 — aldehydes: chia > rapeseed ≈ soybean > olive oil.
- Ampem G, Le Gresley A, Grootveld M, Naughton DP. High-resolution 1H NMR analysis of continuous and discontinuous thermo-oxidative susceptibility of culinary oils during frying at 180 °C. J Food Drug Anal. 2023;31(1):95–115. — doi:10.38212/2224-6614.3439 · PubMed PMID: 37224552
- Qin P, Zhang M, Han M, et al. Fried-food consumption and risk of cardiovascular disease and all-cause mortality: a meta-analysis of observational studies. Heart. 2021;107(19):1567–1575. — doi:10.1136/heartjnl-2020-317883 · PubMed PMID: 33468573
- Samsuri AH, Ang MY, Ng SY. Optimization of residual hexane in edible oils analysis using static headspace gas chromatography. Int J Anal Chem. 2021;2021:1941336. — doi:10.1155/2021/1941336 · PubMed PMID: 34745265
- An H, Ma Y, Wang X, Zheng Y. Effects of deodorization on the formation of processing contaminants and chemical quality of sunflower oil. J Oleo Sci. 2022;71(7):975–984. — doi:10.5650/jos.ess22050 · PubMed PMID: 35691841
- Martin CA, Visentainer JV, de Oliveira CC, et al. Trans polyunsaturated fatty acid contents in Brazilian refined soybean oil. Anal Sci. 2006;22(4):631–633. — doi:10.2116/analsci.22.631 · PubMed PMID: 16760612
- Wen Y, Xu L, Xue C, et al. Assessing the impact of oil types and grades on tocopherol and tocotrienol contents in vegetable oils with chemometric methods. Molecules. 2020;25(21):5076. — doi:10.3390/molecules25215076 · PubMed PMID: 33139648
PubMed Topic Searches
These queries surface current peer-reviewed work as it is indexed.
- PubMed: Search: linoleic acid cardiovascular disease
- PubMed: Search: omega-6 to omega-3 ratio and inflammation
- PubMed: Search: 4-hydroxynonenal and frying oil
- PubMed: Search: repeatedly heated cooking oil and health
- PubMed: Search: ultra-processed food and cardiometabolic risk
- PubMed: Search: vegetable oil refining and trans fat formation
- PubMed: Search: extra-virgin olive oil polyphenols and heat stability
- PubMed: Search: ALA conversion to EPA and DHA
- PubMed: Search: replacing saturated with polyunsaturated fat, randomized
- PubMed: Search: fried food consumption and cardiovascular outcomes
Connections
- Fake Olive Oil — How seed-oil dilution of olive oil is detected — and why grade fraud is the bigger problem
- All Toxins
- Ultra Processed Foods
- Olive Oil
- Avocado
- Anti-Inflammatory Diet
- Processed Oils
- Cardiovascular Disease
- Inflammatory Markers
- Omega-3 Fatty Acids
- Lipid Panel
- Insulin Resistance
- Obesity
- Food Additives
- Trans Fats
- Fake Avocado Oil — The oils found blended into nine in ten “avocado oil” processed foods
Featured Videos