Cold and Sauna Exposure for Stress Management
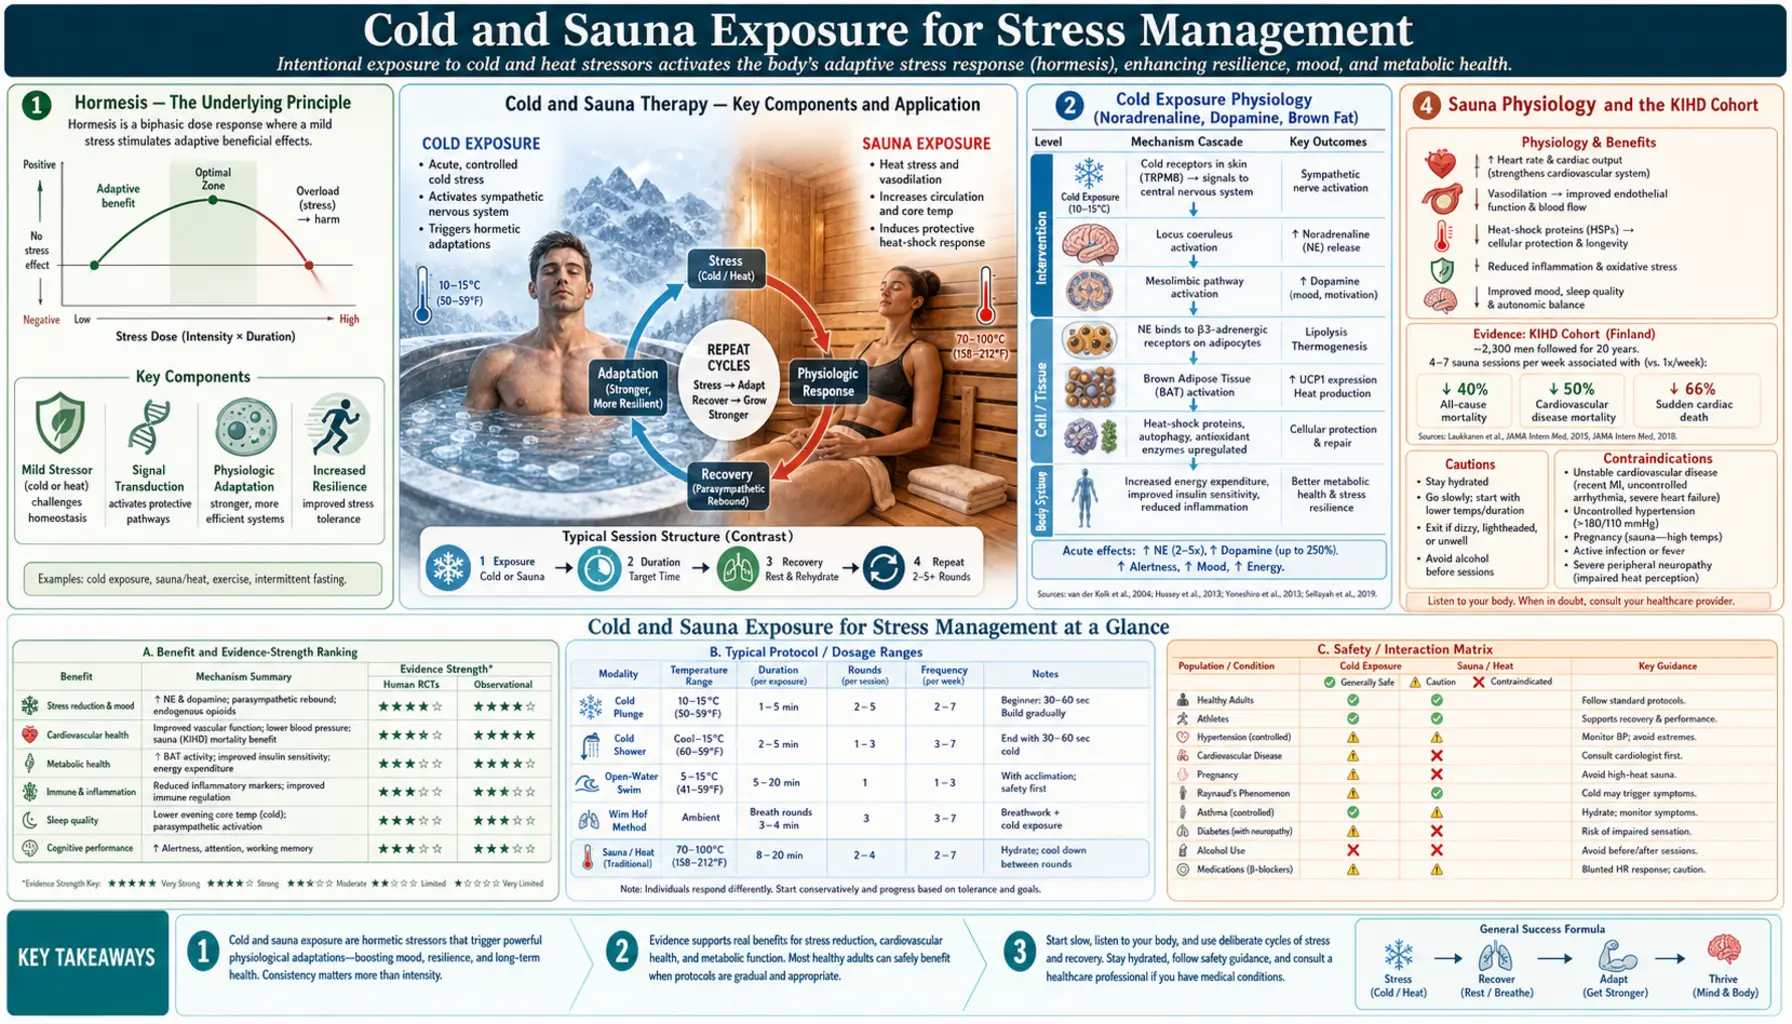
Cold-water immersion and dry-sauna heat are the two most-studied hormetic stressors in the modern stress-management literature. In a 1-hour immersion in 14°C (57°F) water, plasma noradrenaline rose 530% and dopamine 250%, producing a sustained mood elevation that has been compared to a controlled pharmacological intervention. Dry-sauna heat — especially the Finnish-style 80-100°C sauna — has been linked in the Kuopio Ischaemic Heart Disease (KIHD) cohort, followed for a median of 20.7 years, to a 63% lower risk of sudden cardiac death and about 40% lower all-cause mortality at 4-7 sessions per week compared with once a week. The unifying mechanism is hormesis: a brief, intense, predictable stressor produces adaptive upregulation of the body's stress-defense systems (heat-shock proteins, antioxidant enzymes, baseline vagal tone), with the net effect that subsequent chronic stress produces less downstream damage. This deep dive walks through the physiology of cold and heat exposure, the principal protocols (cold plunge, cold shower, breathing-and-cold methods, Finnish sauna, infrared sauna, contrast therapy), the documented clinical outcomes, and the contraindications — particularly the genuine arrhythmia and cold-shock risks that make this category not for everyone.
Table of Contents
- Hormesis — The Underlying Principle
- Cold Exposure Physiology (Noradrenaline, Dopamine, Brown Fat)
- Cold Protocols (Plunge, Shower, Open-Water, Breathing Methods)
- Sauna Physiology and the KIHD Cohort
- Sauna Protocols (Finnish, Infrared, Contrast)
- The Søberg / Soberg Cold-and-Sauna Protocol
- Mental Health Effects (Depression, Anxiety, Mood)
- Cardiovascular and All-Cause Mortality Evidence
- Contraindications and Risk Management
- Key Research Papers
- Connections
- Featured Videos
Hormesis — The Underlying Principle
Hormesis is a biological dose-response phenomenon in which a low or moderate dose of a stressor produces a beneficial adaptive response, whereas a high dose of the same stressor causes harm. The classic example is exercise: muscular and cardiovascular stress within a tolerable range drives adaptation that makes the body stronger and more resilient; the same stress beyond the tolerable range causes injury and rhabdomyolysis. Cold and heat exposure are pure thermal-stress applications of the same principle.
The molecular machinery of hormesis is well-mapped. Mild stress triggers transcription factors including HSF1 (heat shock factor 1), Nrf2 (nuclear factor erythroid 2-related factor 2), FOXO, and SIRT1, which in turn upregulate a coordinated suite of cytoprotective proteins: heat-shock proteins (HSP70, HSP90), antioxidant enzymes (superoxide dismutase, catalase, glutathione peroxidase), mitochondrial biogenesis factors, and proteostasis machinery. The cell becomes more resistant to subsequent stress of all kinds — what the cardiology literature calls "preconditioning."
The translation to deliberate thermal exposure is direct. A 3-minute cold plunge at 50°F or a 20-minute Finnish sauna at 85°C delivers a brief but intense thermal stress that is well below the tissue-damage threshold but well above the threshold for hormetic transcription-factor activation. Regular practice over weeks-to-months produces measurable upregulation of HSP70, improved antioxidant capacity, and improved tolerance to subsequent stress of any kind — thermal, psychological, infectious, or surgical.
Cold Exposure Physiology (Noradrenaline, Dopamine, Brown Fat)
Sudden cold exposure triggers a coordinated sympathetic activation called the cold-pressor response. The principal acute effects, as measured by Šrámek and colleagues in young men during 1-hour head-out immersions at 32, 20 and 14°C (90, 68 and 57°F):
- Plasma noradrenaline rose 530% during the 1-hour immersion at 14°C in the Šrámek 2000 paper (Eur J Appl Physiol).
- Plasma dopamine rose 250% in the same 14°C immersion. This is an unusual feature — few pharmacological or behavioral interventions produce a dopamine elevation of this magnitude without rapid tolerance.
- Plasma cortisol did not rise — in the Šrámek study cortisol tended to decrease at 14°C, and immersion at none of the three temperatures increased blood cortisol.
- Brown adipose tissue (BAT) activation — cold exposure is the principal physiological activator of brown fat thermogenesis. Brown fat burns glucose and fatty acids for heat via uncoupling protein 1 (UCP1). Regular cold exposure expands BAT mass and BAT activity over weeks; the Søberg 2021 Cell Reports Medicine paper found no brown-fat activity at rest in winter swimmers, and on cooling a rise in brown-fat glucose uptake similar to that of controls, with a greater rise in cold-induced heat production.
- Improved insulin sensitivity — the BAT activation and the noradrenergic activation jointly improve glucose disposal. Regular cold exposure has documented effects on insulin sensitivity comparable to moderate exercise.
- Reduced inflammation — the Kox 2014 PNAS paper documented that subjects trained in a breathing and cold-exposure method (the Wim Hof method) were able to voluntarily attenuate the inflammatory response to endotoxin (lipopolysaccharide, LPS) administration, with reduced tumor necrosis factor-α, interleukin-6 (IL-6), and IL-8 production.
The sustained mood elevation following cold exposure — widely reported anecdotally and now documented in multiple psychophysiology studies — is almost certainly driven by the dopamine elevation. Unlike pharmacological dopamine agonists, the cold-induced rise produces no acute hedonic spike (the experience during immersion is uncomfortable, not pleasurable), and there is no documented tolerance with regular practice.
Cold Protocols (Plunge, Shower, Open-Water, Breathing Methods)
The principal cold-exposure protocols differ in intensity, duration, and accessibility:
- Cold shower — the most accessible protocol: a normal warm shower that ends with 30 seconds to 3 minutes of the coldest setting (typically 50-65°F in residential plumbing). Buijze and colleagues (PLoS One 2016) randomized 3,018 adults to daily cold showers (30, 60, or 90 seconds) for 30 days; the active group had a 29% reduction in self-reported sick-days from work, with no difference between dose groups.
- Cold plunge / ice bath — immersion to the neck in 38-55°F water for 2-5 minutes. Commercial cold-plunge tubs commonly target ~50°F as a typical setting. A protocol popularised online calls for total weekly cold exposure of ~11 minutes (e.g., 3 minutes × 4 sessions/week at 50°F).
- Open-water swimming — winter swimming in lakes, rivers, or oceans at 40-50°F. The Finnish, Scandinavian, and Russian traditions have centuries of practice. A 2018 BMJ Case Reports paper described a sustained reduction in depression symptoms, and stopping of medication, in a single patient following adoption of weekly cold-water swimming — an anecdote that triggered a wave of clinical research.
- Breathing-and-cold methods — structured programs combining cold exposure with a specific breathing technique (3-4 rounds of 30-40 power breaths followed by breath-holding) and progressive cold tolerance training. The 2014 Kox PNAS paper, which studied the Wim Hof method, found that subjects trained in it could voluntarily attenuate the lipopolysaccharide inflammatory response — the first documented evidence of voluntary modulation of the innate immune system.
- Cryotherapy chamber — brief (2-3 minute) exposure to extremely cold air (-110 to -140°C) in a commercial whole-body cryotherapy chamber. The very short exposure means much less actual tissue cooling than a 50°F water immersion despite the more dramatic stated temperature. Clinical evidence for cryotherapy chambers is mixed and substantially weaker than for water immersion.
Beginner programs described by practitioners start with 30-second cold showers and work up to 1-3 minutes over 4-8 weeks before moving to a cold plunge. Practitioners hold that frequency matters more than duration — that 4×3-minute sessions per week work better than 1×12-minute session per week.
Sauna Physiology and the KIHD Cohort
The Finnish sauna tradition, going back over two thousand years, exposes the body to dry heat at 80-100°C (176-212°F) for 5-30 minutes at a time. Core body temperature rises by 0.5-1.0°C, heart rate roughly doubles (from a typical resting 60-70 bpm to 100-150 bpm), cardiac output increases 60-70%, and significant sweating produces fluid loss of 0.5-1.5 liters per session.
The cardiovascular load is comparable to moderate exercise. Heart rate, stroke volume, and cardiac output increase. Peripheral vasodilation lowers systemic vascular resistance and blood pressure transiently falls during the session, then rebounds in the cooling phase. Repeated sessions appear to drive cardiovascular adaptation similar to exercise: improved endothelial function, lower resting blood pressure, improved arterial compliance, and reduced left ventricular hypertrophy.
The single most influential body of evidence is the Kuopio Ischaemic Heart Disease (KIHD) prospective cohort study of 2,315 middle-aged Finnish men followed from baseline (1984-1989) for over 20 years. The headline findings, published by Tanjaniina Laukkanen and colleagues in JAMA Internal Medicine 2015:
- Compared to men using the sauna 1 time/week, men using the sauna 2-3 times/week had a 22% lower sudden cardiac death (SCD) risk; men using the sauna 4-7 times/week had a 63% lower SCD risk.
- All-cause mortality showed a similar dose-response: 24% lower at 2-3 sessions/week, 40% lower at 4-7 sessions/week.
- Time-per-session also mattered: sessions of >19 minutes were associated with 52% lower SCD risk vs sessions of <11 minutes.
- Subsequent KIHD analyses extended the findings to dementia (66% lower risk at 4-7 sessions/week), Alzheimer's disease, stroke, and hypertension.
The KIHD findings are observational and the population is genetically and culturally distinct, so causal inference and external generalizability require caution. But the consistency of the dose-response across multiple endpoints, the biological plausibility of the cardiovascular and HSP-related mechanisms, and the supporting evidence from short-term randomized trials together make the sauna intervention one of the best-supported lifestyle interventions for cardiovascular and all-cause mortality currently known.
Sauna Protocols (Finnish, Infrared, Contrast)
The three principal sauna modalities differ in heat source and air temperature:
- Finnish (traditional) sauna — wood- or electric-heated stones radiating dry heat at 80-100°C (176-212°F), with occasional water pours (löyly) producing brief humidity spikes. This is the modality of the KIHD evidence. Typical session: 10-20 minutes, 1-2 rounds, with cooling intervals between. Twice-weekly is the minimum dose with documented mortality benefit; 4-7 times/week is associated with the largest effect.
- Infrared sauna — far-infrared (FIR) emitters heating the body directly without significantly heating the surrounding air. Cabin temperatures are much lower (50-65°C) but skin and tissue heating is comparable due to the radiant transfer. Infrared sauna is the closest readily available analog to the Finnish sauna for residential use. Direct mortality evidence is limited (no KIHD-scale infrared cohort exists) but short-term cardiovascular and inflammatory markers respond similarly.
- Steam room (Turkish hammam / Russian banya) — much lower temperature (40-50°C) with very high humidity. The cardiovascular load is lower than a dry Finnish sauna. Documented benefits exist but are smaller in magnitude.
- Contrast therapy — alternating heat (sauna) and cold (plunge or cold shower) in rotating cycles. The Scandinavian tradition (sauna → jump in lake → back to sauna) is the canonical pattern. Contrast amplifies both the sympathetic activation of the cold component and the vasodilatory effect of the heat component; subjects typically report a more dramatic mood elevation than either modality alone.
The Hussain and Cohen 2018 systematic review (Evid Based Complement Alternat Med) catalogs the documented clinical effects across all modalities: reduced blood pressure, improved endothelial function, reduced symptoms of rheumatoid arthritis and ankylosing spondylitis, modest weight reduction (mostly fluid loss with rebound), improved chronic pain, and reduced depression scores.
The Søberg / Soberg Cold-and-Sauna Protocol
Susanna Søberg, a Danish physiologist and the author of the 2022 book "Winter Swimming," has been one of the principal researchers translating Scandinavian cold-and-heat traditions into clinical protocols. Her 2021 Cell Reports Medicine paper compared young men who practised Scandinavian winter swimming — brief cold dips combined with hot sauna sessions, 2-3 times a week — with non-swimming controls. At rest the swimmers had a lower core temperature and no brown-fat activity; on cooling, their cold-induced heat production (thermogenesis) rose more than the controls', while brown-fat glucose uptake rose similarly in both groups.
The "Søberg principle" articulated in interviews and subsequent writing is summarised in these figures:
- For cold adaptation: 11 minutes per week total — spread across 2-4 sessions, typically 2-3 minutes per session at 50-55°F. This was the average weekly cold-water time of the winter swimmers in her 2021 study.
- For sauna benefit: 57 minutes per week total — spread across 3-7 sessions of 15-20 minutes each. This was the average weekly sauna time of the same winter swimmers.
- Ending on cold, not on heat, is described for metabolic adaptation — ending on cold preserves the brown-fat activation signal. Ending on heat closes the session with vasodilation and gentle relaxation but blunts the BAT signaling.
- Ending on heat, not on cold, is described for sleep and relaxation — the post-sauna cooling phase, especially in a cooler bedroom, mimics the natural pre-sleep core-temperature drop and facilitates sleep onset.
This is a useful framework but the underlying evidence is more modest than the precision of the numbers suggests; the "11 minutes" and "57 minutes" describe the weekly habits of the winter swimmers in one small study, not doses tested in a clinical trial.
Mental Health Effects (Depression, Anxiety, Mood)
The mental-health literature on cold and sauna exposure is smaller than the cardiovascular literature but has been accelerating since 2018:
- Depression — the 2018 van Tulleken open-water swimming case report in BMJ Case Reports described a 24-year-old woman, treated for depression since age 17 and not helped by two antidepressants, whose symptoms fell steadily after she took up weekly cold-water swimming; she stopped her medication and was still medication-free a year later. Open-water swimmers commonly report improvements in mood and depression symptoms. The 2016 Janssen Hyperthermia trial (JAMA Psychiatry) found a single whole-body hyperthermia session produced significant reduction in depression scores at 6 weeks compared to sham.
- Anxiety — both cold and sauna produce acute sympathetic activation, which counterintuitively can lower chronic anxiety through habituation. Open-water swimming communities report reduced trait anxiety; mechanism is plausibly stress inoculation.
- Mood and well-being — the sustained dopamine elevation following cold exposure produces a 2-3 hour mood elevation that subjects compare to (but find more sustainable than) pharmacological stimulants. The post-sauna parasympathetic rebound produces a complementary calm-and-relaxed state.
- Cognitive function — people describe feeling more alert and focused immediately after cold exposure, which practitioners attribute to the noradrenergic surge.
- Sleep — evening sauna with subsequent cooling facilitates sleep onset; morning cold exposure advances the circadian phase and supports morning alertness.
Cardiovascular and All-Cause Mortality Evidence
The cardiovascular evidence for sauna is among the strongest for any lifestyle intervention. The principal datasets:
- KIHD (Kuopio Ischaemic Heart Disease) — 2,315 Finnish men, 20+ year follow-up, sauna 4-7×/week associated with 63% reduction in sudden cardiac death and 40% reduction in all-cause mortality vs 1×/week.
- Kunutsor 2018 (Annals of Medicine) — in 2,277 KIHD men followed for a median of 26.1 years, men with both high cardiorespiratory fitness and frequent sauna (3-7 sessions a week) had lower cardiovascular mortality (hazard ratio 0.42) and all-cause mortality (hazard ratio 0.60) than men with low fitness and infrequent sauna — a stronger association than high fitness or frequent sauna alone.
- Patrick & Johnson 2021 (Exp Gerontol) — comprehensive review of sauna as a lifestyle practice for healthspan extension, summarizing the KIHD and supporting short-term mechanistic evidence.
- Cold-water exposure — the mortality evidence is limited because no KIHD-equivalent cold cohort exists. The Esperland 2022 review in the International Journal of Circumpolar Health (104 studies) found most studies small, reported that cold-water immersion seems to reduce or transform body fat and reduce insulin resistance, and concluded that without further conclusive studies the topic will remain a subject of debate.
The combined cold-and-sauna evidence supports a reasonable inference that the protective effect is driven by repeated mild sympathetic stress with full subsequent parasympathetic recovery — the same fundamental mechanism that makes exercise cardioprotective. The thermal protocols are best understood as a partial substitute for or supplement to exercise in patients who cannot or will not exercise at sufficient volume, not as a replacement for it.
Contraindications and Risk Management
Both modalities carry genuine risks that exclude meaningful subsets of the population:
- Uncontrolled cardiovascular disease — cold and sauna both significantly load the cardiovascular system. Patients with unstable angina, recent myocardial infarction, severe aortic stenosis, uncontrolled hypertension (>180/110), or recently decompensated heart failure, both heat and cold put a heavy load on a weak heart.
- Arrhythmia — the acute sympathetic surge of cold immersion can precipitate atrial fibrillation, ventricular ectopy, and (rarely) ventricular tachycardia in susceptible individuals, most of all in people with a history of arrhythmia.
- Cold shock response — sudden whole-body immersion in <60°F water triggers a gasp reflex, hyperventilation, and a vagally mediated heart-rate spike that can be life-threatening, particularly in the first 30 seconds. The leading cause of cold-water swimming deaths is cold-shock-induced cardiac arrest, not hypothermia. Sudden head-first entry brings on the strongest gasp reflex, and a person swimming alone has no one to help if it strikes.
- Pregnancy — sauna use in the first trimester has been associated with neural tube defects in some studies; most obstetric guidelines recommend avoiding sauna during pregnancy. Cold exposure is also generally not recommended.
- Dehydration and electrolyte loss — sauna sessions produce 0.5-1.5 L of fluid loss. Water and electrolytes replace these losses; over many sessions, sodium and magnesium losses add up.
- Alcohol — the combination of alcohol and sauna is the principal cause of sauna-related deaths in Finland. Alcohol impairs thermoregulation, masks warning symptoms, and increases arrhythmia risk.
- Hyperventilation before breath-holding (breathing-and-cold methods) — hyperventilation lowers blood CO₂ without significantly raising O₂, delaying the urge to breathe. Hyperventilation followed by breath-holding underwater has caused multiple drownings, in water and close to it.
- Raynaud's phenomenon — severe Raynaud's patients can develop digital ischemia and frank tissue injury with cold exposure; relative contraindication.
- Children and elderly — thermoregulation is less robust at the extremes of age. Shorter durations and closer supervision.
Key Research Papers
- Laukkanen T et al., Association between sauna bathing and fatal cardiovascular and all-cause mortality events (JAMA Intern Med 2015) — PubMed PMID: 25705824
- Laukkanen JA, Laukkanen T, Kunutsor SK, Cardiovascular and other health benefits of sauna bathing: a review of the evidence (Mayo Clin Proc 2018) — PubMed PMID: 30077204
- Hussain J, Cohen M, Clinical effects of regular dry sauna bathing: a systematic review (Evid Based Complement Alternat Med 2018) — PubMed PMID: 29849692
- Søberg S et al., Altered brown fat thermoregulation and enhanced cold-induced thermogenesis in young, healthy, winter-swimming men (Cell Rep Med 2021) — PubMed PMID: 34755128
- Kox M et al., Voluntary activation of the sympathetic nervous system and attenuation of the innate immune response in humans (PNAS 2014) — PubMed PMID: 24799686
- Šrámek P et al., Human physiological responses to immersion into water of different temperatures (Eur J Appl Physiol 2000) — PubMed PMID: 10751106
- Buijze GA et al., The effect of cold showering on health and work: a randomized controlled trial (PLoS One 2016) — PubMed PMID: 27631616
- Janssen CW et al., Whole-body hyperthermia for the treatment of major depressive disorder: a randomized clinical trial (JAMA Psychiatry 2016) — PubMed PMID: 27172277
- van Tulleken C et al., Open water swimming as a treatment for major depressive disorder (BMJ Case Rep 2018) — PubMed PMID: 30131418
- Tipton MJ et al., Cold water immersion: kill or cure? — PubMed PMID: 28833689 (Exp Physiol 2017)
- Patrick RP, Johnson TL, Sauna use as a lifestyle practice to extend healthspan (Exp Gerontol 2021) — PubMed PMID: 34363927
- Kunutsor SK, Khan H, Laukkanen T, Laukkanen JA, Joint associations of sauna bathing and cardiorespiratory fitness on cardiovascular and all-cause mortality risk: a long-term prospective cohort study (Ann Med 2018) — PubMed PMID: 28972808
- Esperland D et al., Health effects of voluntary exposure to cold water — a continuing subject of debate (Int J Circumpolar Health 2022) — PubMed PMID: 36137565