⚠ Evidence warning: Clinical trials or other evidence do not support the claim that a 12-week multi-step diet, supplement and breathing protocol restores a dysregulated gut-brain axis. This page keeps it as a report of what people, websites or other media say.
Gut-Brain Axis Restoration Protocols
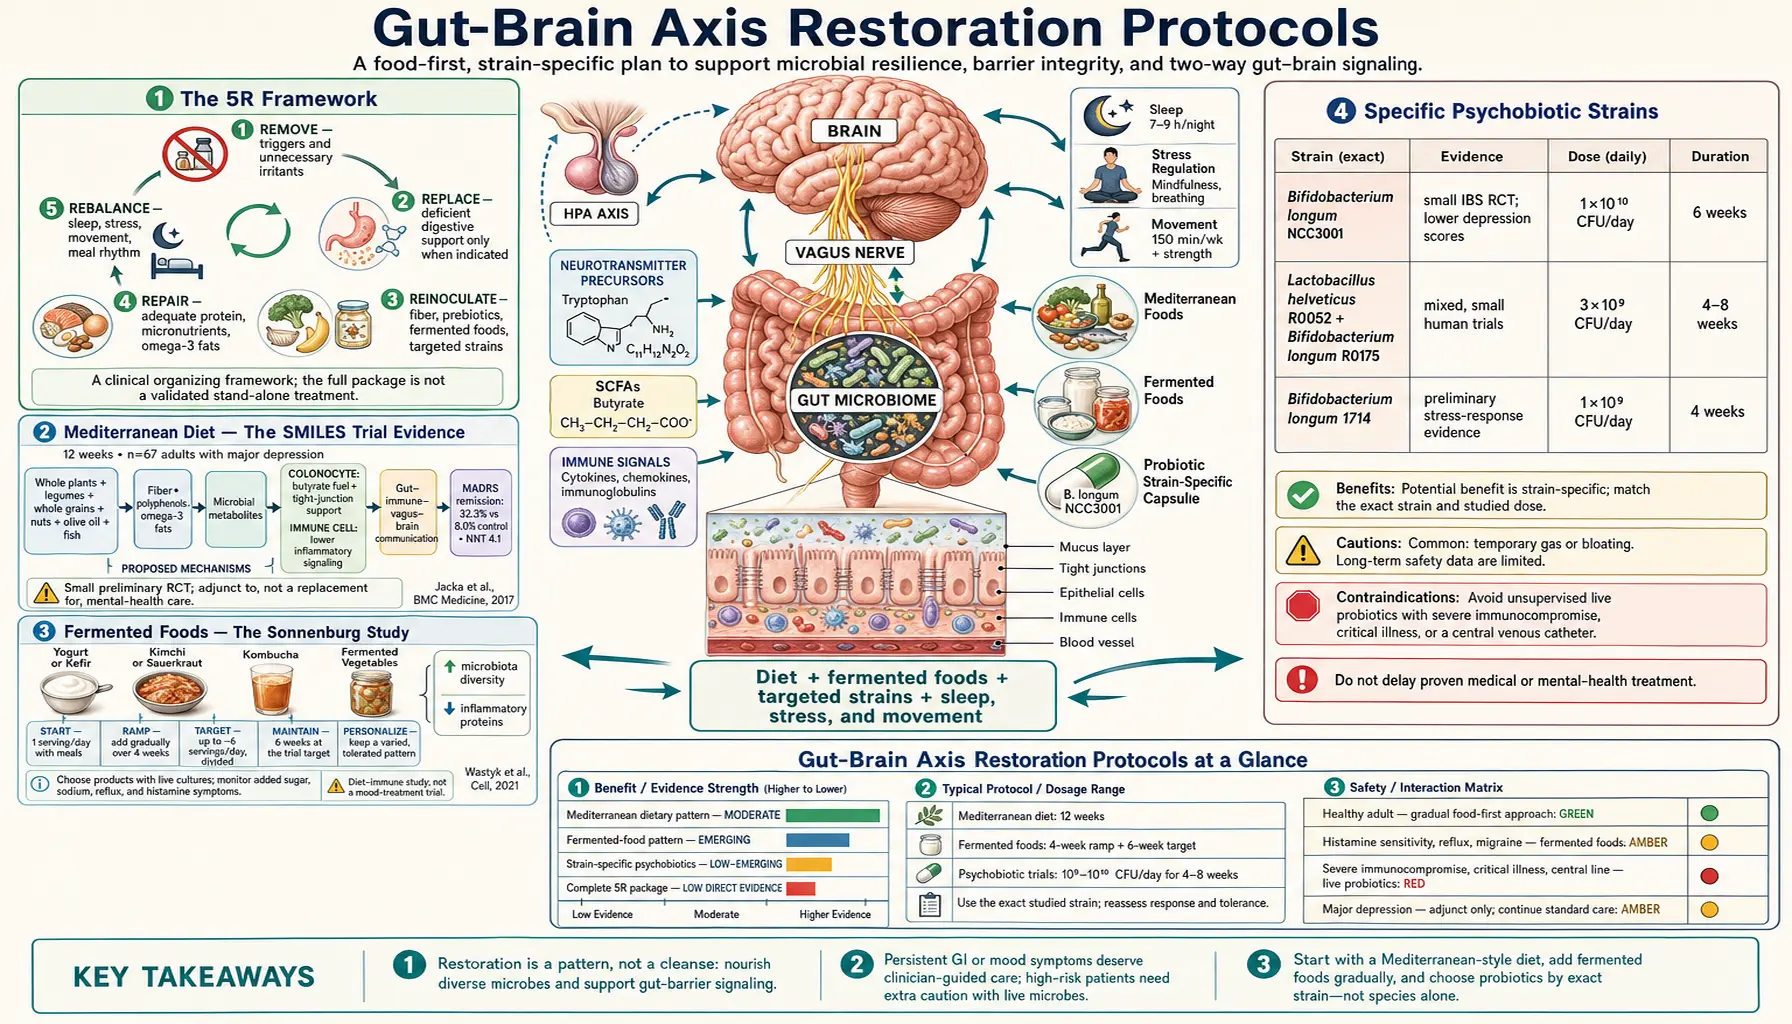
Restoring a dysregulated gut-brain axis requires multi-modal intervention that addresses all four communication pathways simultaneously — vagal tone, microbial composition, intestinal barrier integrity, and stress reactivity. No single intervention reliably reverses the stress-permeability-inflammation feedback loop once it has become entrenched. The Functional Medicine 5R framework (Remove, Replace, Reinoculate, Repair, Rebalance) provides a useful structure, but the highest-impact specific interventions are now well-characterized: the Mediterranean diet, fermented foods (specifically 6 servings/day per the Sonnenburg 2021 Cell study), strain-specific psychobiotic supplementation (Bifidobacterium longum 1714 and L. helveticus R0052 + B. longum R0175), daily slow-paced breathing for vagal tone, L-glutamine and zinc carnosine for barrier repair, and root-cause stress reduction. This page gathers what the research reports on each of these, where it is thin, and how practitioners sequence them for people with established gut-brain dysregulation.
Table of Contents
- The 5R Framework
- Mediterranean Diet — The SMILES Trial Evidence
- Fermented Foods — The Sonnenburg Study
- Specific Psychobiotic Strains
- Prebiotic Fiber and Butyrate Production
- How the Low-FODMAP Diet Works
- Barrier Repair Nutrients (L-Glutamine, Zinc Carnosine, DGL)
- Vagal Tone Training Protocol
- Root-Cause Stress Reduction
- How a 12-Week Protocol Is Sequenced
- Key Research Papers
- Connections
- Featured Videos
The 5R Framework
The 5R framework, developed in the Functional Medicine community in the 1990s and 2000s, provides a useful organizing structure for gut-brain restoration:
- Remove — identify and eliminate the inputs driving dysregulation: food intolerances and sensitivities (gluten, dairy, lectins, FODMAPs in susceptible patients), unnecessary medications (proton pump inhibitors (PPIs), nonsteroidal anti-inflammatory drugs (NSAIDs), antibiotics), environmental toxins, occult infections (parasites, small intestinal bacterial overgrowth (SIBO), candida, H. pylori).
- Replace — restore inputs that may be deficient or insufficient: digestive enzymes (bromelain, pancreatic enzymes), hydrochloric acid (betaine HCl when gastric acid is low), bile salts (ox bile when gallbladder is removed or sluggish).
- Reinoculate — restore beneficial microbiome composition: psychobiotic probiotic strains (see below), fermented foods, prebiotic fiber to feed butyrate-producers.
- Repair — provide nutrients and conditions for mucosal regeneration: L-glutamine, zinc carnosine, deglycyrrhizinated licorice (DGL), N-acetyl-glucosamine, slippery elm, marshmallow root, sufficient protein, omega-3 fatty acids.
- Rebalance — address the broader life context that drives recurrence: stress reduction, sleep optimization, vagal tone training, regular movement, social connection, sense of meaning and purpose.
The 5Rs are sequential in concept but often parallel in practice. Practitioners describe most patients benefiting from beginning Repair and Rebalance steps in parallel with Remove and Reinoculate, particularly stress reduction and L-glutamine supplementation. The mental shorthand is: stop the offending inputs, add back the missing inputs, fix the substrate, support the long-term context.
It is worth noting that the 5R framework is a Functional Medicine clinical heuristic, not a U.S. Food and Drug Administration-recognized treatment protocol. The individual components have varying degrees of evidence support — some excellent (Mediterranean diet for depression, fermented foods for microbiome diversity), some emerging (specific probiotic strains), some thin (extensive food-sensitivity panels with elimination of large food groups). Practitioners adjust the components to the individual.
Mediterranean Diet — The SMILES Trial Evidence
A leading randomized controlled trial of dietary intervention for major depression is the SMILES (Supporting the Modification of lifestyle In Lowered Emotional States) trial conducted by Felice Jacka and colleagues at Deakin University, published in BMC Medicine in 2017. The design:
- Population: 67 adults with moderate-to-severe major depressive disorder, mostly already on antidepressants and/or in psychotherapy; 56 had complete data at 12 weeks (31 in the dietary arm, 25 in the control arm)
- Intervention arm (33 patients): 7 sessions of dietary counseling over 12 weeks toward a Mediterranean-style diet (whole grains, vegetables, fruits, legumes, low-fat unsweetened dairy, raw unsalted nuts, fish, lean red meats, chicken, eggs, olive oil)
- Control arm (34 patients): 7 sessions of social support (befriending), matched for time and attention
- Primary endpoint: Montgomery-Asberg Depression Rating Scale (MADRS) at 12 weeks
Results:
- MADRS score: from 26.1 to 14.8 in the dietary arm vs. from 24.7 to 20.5 in the control arm, an estimated between-group difference of 7.1 points (large effect size, Cohen's d -1.16, with a wide 95% confidence interval of -1.73 to -0.59)
- Remission (MADRS <10): 32.3% (10 people) in dietary arm vs. 8.0% (2 people) in control arm
- The authors report that the effects appeared independent of changes in body mass index (BMI), self-efficacy, smoking rates and physical activity; social support was the comparison arm
- Greater dietary adherence correlated with greater clinical improvement
The authors call these results "preliminary RCT evidence" and stress "the preliminary nature of this study and the imperative for replication in studies with larger sample sizes." The effect size in SMILES is larger than most pharmaceutical antidepressant trials. Replication by the same group and others has been described as generally supportive, though with effect sizes more modest in some trials. Later tests include the AMMEND randomized trial of a Mediterranean diet in young men with depression, and HELFIMED, an Australian trial of 152 adults with self-reported depression, who received food hampers, cooking workshops and fish oil. In HELFIMED depression fell more than with social groups at 3 months, and the gains in diet and mental health held at 6 months; the fish oil makes it a combined test rather than a test of diet alone. The combined evidence supports Mediterranean dietary counseling as an evidence-based intervention for major depression.
The SMILES dietary advice itself listed whole grains (5-8 servings/day), vegetables (6/day), fruit (3/day), legumes (3-4/week), low-fat and unsweetened dairy foods (2-3/day), raw unsalted nuts (1/day), fish (at least 2/week), lean red meats (3-4/week), chicken (2-3/week), eggs (up to 6/week) and olive oil (3 tablespoons/day), with sweets, refined cereals, fried food, fast food, processed meats and sugary drinks held to no more than 3/week.
Practical descriptions of the Mediterranean pattern, whose targets differ from the trial's, emphasize:
- Vegetables: 5+ servings/day, especially leafy greens and cruciferous
- Fruits: 2-3 servings/day, especially berries
- Whole grains: 3-5 servings/day (oats, quinoa, brown rice, whole wheat)
- Legumes: 3-5 servings/week
- Nuts: 1 handful/day, especially walnuts
- Fish: 2-3 servings/week, especially oily fish (salmon, sardines, mackerel)
- Extra virgin olive oil: 3+ tablespoons/day
- Limited red meat: <1 serving/week
- Limited processed foods, sugar, and refined grains
The DASH and MIND diets (variations with overlapping principles) have similar evidence support. For more on the Mediterranean diet, see our Mediterranean Diet page.
Fermented Foods — The Sonnenburg Study
The landmark Sonnenburg and Wastyk 2021 Cell study (Stanford) provided the first rigorous comparison of high-fiber vs. high-fermented-foods diets on the human microbiome and immune system. The design:
- Two arms over 10 weeks: high-fiber arm gradually increased fiber from baseline to 45 grams/day; fermented foods arm gradually increased fermented food intake from baseline to 6 servings/day (yogurt, kefir, fermented cottage cheese, kimchi, sauerkraut, fermented vegetables, vegetable brine drinks, kombucha)
- Participants: generally healthy adults, 18 per arm
- Primary outcome: cytokine response score, which did not change significantly from baseline to the end of the intervention in either arm
- Secondary and exploratory outcomes: 16S rRNA microbiome sequencing, a panel of 93 inflammatory serum proteins, multidimensional immune cell phenotyping
Key findings:
- Fermented foods arm: Significant increase in microbiome diversity (alpha diversity), decrease in 19 of the 93 inflammatory markers measured, including interleukin-6 (IL-6), IL-10 and IL-12b, and lower activation in 14 of 60 immune signaling responses. The size of these changes did not differ significantly between higher and lower fermented-food consumers. An increase in regulatory T cells and larger effects in people starting with lower diversity are also claimed for fermented foods; neither appears in this paper.
- High-fiber arm: Variable response. Fiber-degrading enzymes encoded by the microbiome increased while community diversity stayed stable, and the authors did not observe an increase in butyrate. Participants fell into three immune-response groups, two with lower and one with higher steady-state immune activation ("high-inflammation"); that last group had lower starting diversity than one of the other two (p = 0.037). The related claim, that people with more fiber-degrading capacity at the start gain short-chain fatty acids (SCFA) while others see minimal change, is not what this paper reports: a subset of SCFAs fell in this arm. An inference the study did not test is that high-fiber interventions may need to be preceded or accompanied by microbiome restoration in people with significantly depleted microbiomes.
An inference drawn from this study of healthy adults: for people with depleted microbiome diversity (typical after antibiotics, in chronic gastrointestinal (GI) disease, or in association with chronic stress), fermented foods may be more reliably beneficial than fiber as a first-line intervention. Fermented foods provide both live microorganisms (transient passengers that influence the resident community) and bacterial metabolites (lactic acid, acetic acid, conjugated linoleic acid, exopolysaccharides) that have direct biological effects.
Practitioners describe 4-6 servings of fermented foods per day; the study's fermented-food arm averaged 6.3 by the end of its maintenance phase. A serving is roughly 1/2 cup yogurt or kefir, 1/4 cup sauerkraut or kimchi, or 4-8 ounces of kombucha. Important: many commercial yogurts are pasteurized after fermentation and contain no live cultures; the label phrase "live and active cultures" marks those that do. For more on fermented foods, see Fermented Foods.
Specific Psychobiotic Strains
Probiotic effects are strain-specific. Buying a generic "Lactobacillus" capsule does not provide the benefits documented for specific researched strains. The strains with the best human evidence for mood, anxiety, and gut-brain effects:
| Strain | Indication | Product Category |
|---|---|---|
| Bifidobacterium longum 1714 | Stress and anxiety in healthy adults; emerging depression evidence | Single-strain probiotic product |
| L. helveticus R0052 + B. longum R0175 | Anxiety, depression, stress | Two-strain probiotic blend |
| Bifidobacterium infantis 35624 | Irritable bowel syndrome (IBS) with mood comorbidity | Single-strain probiotic product |
| L. plantarum 299v | Irritable bowel syndrome bloating, depression cognitive symptoms | Single-strain probiotic product |
| 8-strain probiotic blend | Ulcerative colitis, pouchitis, mood in inflammatory bowel disease (IBD) | Multistrain blend sold as a medical food |
| L. rhamnosus GG (LGG) | Antibiotic-associated diarrhea, pediatric anxiety | Single-strain probiotic product |
| Saccharomyces boulardii | Antibiotic and traveler's diarrhea, prevention of Clostridioides difficile infection | Probiotic yeast product |
Important practical points:
- Duration: At least 4-8 weeks of daily use to see meaningful clinical effect. Some effects (e.g., hypothalamic-pituitary-adrenal (HPA) axis dampening) take longer (12 weeks).
- Dose: Manufacturer-specified dose; more is not necessarily better, and the doses used in the underlying studies are the ones with data behind them.
- Quality: Probiotics are subject to viability degradation. Refrigerated products generally have better viability than shelf-stable, but some shelf-stable strains (especially spore-forming Bacillus species) are intentionally robust.
- Contraindications: Probiotics are generally contraindicated in patients with central venous catheters, severely immunocompromised states, severe acute pancreatitis (one trial showed harm), and short bowel syndrome (small intestinal bacterial overgrowth concerns).
- Tracking: Published clinical guides to probiotic products map strains to indications.
Across 34 controlled trials, Liu and colleagues found small effects of probiotics on depression (d = -.24) and anxiety (d = -.10), with a larger effect in a preliminary analysis of psychiatric samples (d = -.73). Prebiotics did not differ from placebo for depression or anxiety. A 2023 pilot trial added a multistrain probiotic or placebo to antidepressants for 8 weeks in 49 adults with an incomplete response. Depression scores improved more on the probiotic (Hamilton scale at week 4, standardized effect 0.70), with no serious adverse reactions; it was built to size a larger trial, not to settle the question.
For more general probiotic information, see Probiotics.
Prebiotic Fiber and Butyrate Production
Prebiotics are non-digestible food components that selectively feed beneficial gut bacteria. The most well-studied prebiotics:
- Inulin and fructo-oligosaccharides (FOS) — found in chicory root, Jerusalem artichoke, garlic, onions, leeks, asparagus, bananas. Selectively feeds Bifidobacterium. Can cause bloating and gas at high doses, especially in small intestinal bacterial overgrowth patients.
- Galacto-oligosaccharides (GOS) — found in human milk and certain dairy products; also available as supplements. Tend to be better tolerated than inulin/FOS. B. longum 1714 has been shown to ferment GOS effectively.
- Resistant starch — found in cooked-and-cooled potatoes, cooked-and-cooled rice, green bananas, raw oats. Selectively fermented by butyrate-producing bacteria like Faecalibacterium prausnitzii and Roseburia.
- Beta-glucan — found in oats, barley, mushrooms. Modulates immune function and supports butyrate production.
- Psyllium husk — not strictly a prebiotic, but a soluble fiber that supports microbial diversity and is well-tolerated.
- Pectin — found in apples, citrus, berries. Modified citrus pectin is a supplemental form.
The clinical rationale for prebiotic supplementation is to support butyrate-producing bacteria. Butyrate is the primary energy source for colonocytes, a histone deacetylase (HDAC) inhibitor with epigenetic effects, an activator of vagal afferent signaling, and a modulator of microglial function. Diets producing inadequate butyrate (the typical Western diet) produce a measurable colonocyte energy deficit that contributes to barrier dysfunction.
Practitioners commonly describe 25-35 grams of total fiber per day from food sources, with deliberate inclusion of prebiotic-rich foods, and from a low baseline a gradual increase over 2-4 weeks to allow microbiome adaptation and reduce bloating. Direct butyrate supplementation (calcium-magnesium butyrate or tributyrin) is available but generally not necessary if fiber intake is adequate.
How the Low-FODMAP Diet Works
FODMAPs (fermentable oligosaccharides, disaccharides, monosaccharides, and polyols) are short-chain carbohydrates that are poorly absorbed in the small intestine and rapidly fermented in the colon. In susceptible patients (typically those with irritable bowel syndrome, small intestinal bacterial overgrowth, or visceral hypersensitivity), FODMAP-rich foods produce excessive gas production, distension, and pain.
The low-FODMAP diet developed at Monash University is a well-validated intervention for irritable bowel syndrome, with approximately 70% of irritable bowel syndrome patients reporting symptom improvement in randomized trials. A network meta-analysis of 13 randomized trials and 944 patients gave a relative risk of symptoms not improving of 0.67 (95% confidence interval 0.48 to 0.91) against habitual diet; most of those trials did not study reintroduction and personalization. The protocol has three phases:
- Elimination phase (2-6 weeks) — strict avoidance of high-FODMAP foods to establish symptom baseline. This includes wheat (high in fructans), onions and garlic (high in fructans), beans and legumes (high in galacto-oligosaccharides), apples and pears (high in fructose and sorbitol), milk and yogurt with lactose, stone fruits (high in polyols), and many others.
- Reintroduction phase (8-12 weeks) — systematic reintroduction of each FODMAP subgroup one at a time to identify specific triggers. This is the critical phase that many patients skip, leading to unnecessarily restrictive long-term diets.
- Personalization phase (long-term) — ongoing diet that avoids only the specifically identified triggers, allowing maximal dietary variety and microbiome diversity.
Important cautions:
- Low-FODMAP is a diagnostic tool more than a long-term lifestyle. Sustained strict low-FODMAP eating reduces microbiome diversity over time (because it eliminates the very fibers that feed beneficial bacteria) and can paradoxically worsen long-term gut health.
- The reintroduction phase is usually carried out with a registered dietitian or a FODMAP food-guide app.
- Low-FODMAP is used for irritable bowel syndrome, small intestinal bacterial overgrowth, and visceral hypersensitivity patterns. It was not designed as a general "gut health" diet for people without symptoms.
- When irritable bowel syndrome does not respond to low-FODMAP within 6 weeks, practitioners look at alternative diagnoses (small intestinal bacterial overgrowth, inflammatory bowel disease, food intolerance, bile acid malabsorption).
For more on FODMAPs and irritable bowel syndrome, see irritable bowel syndrome and small intestinal bacterial overgrowth.
Barrier Repair Nutrients (L-Glutamine, Zinc Carnosine, DGL)
Several specific nutrients have evidence support for intestinal barrier repair:
- L-Glutamine — the primary fuel for enterocytes (intestinal cells preferentially use glutamine even over glucose). Supplementation at 5-15 grams per day has been shown to reduce intestinal permeability in burn patients, athletes with exercise-induced leaky gut, and patients with inflammatory bowel disease. Mechanism: provides energy substrate for enterocyte regeneration, supports tight junction protein synthesis, reduces oxidative stress. Practitioners describe taking it on an empty stomach in divided doses. Generally well-tolerated. Contraindicated in advanced cirrhosis (ammonia metabolism concerns). In a randomized, placebo-controlled 8-week trial of adults with diarrhea-type irritable bowel syndrome and a leaky gut after a gut infection, glutamine 5 g three times a day met the main goal (a 50-point drop on a symptom score) in 79.6% against 5.8% on placebo, and gut permeability returned to normal. Adverse events were low and similar in both groups, and the authors call for larger trials. See Glutamine page.
- Zinc Carnosine — the combination compound (polaprezinc) used clinically in Japan for peptic ulcer disease for decades. Multiple human studies show acceleration of gastric and intestinal mucosal healing, reduction of nonsteroidal anti-inflammatory drug (NSAID)-induced leaky gut, and reduction of permeability in athletes. Commonly used dose: 75 mg twice daily (containing 16 mg zinc and 59 mg L-carnosine). The randomized crossover trial cited below used half that, 37.5 mg twice daily, in 10 healthy volunteers: the painkiller indomethacin caused a threefold rise in gut permeability on placebo and no significant rise with zinc carnosine. Generally well-tolerated.
- Deglycyrrhizinated Licorice (DGL) — licorice root with glycyrrhizin removed (glycyrrhizin can raise blood pressure). DGL has been used for decades for peptic ulcer disease and chronic gastritis. Acts through stimulation of mucin production and prostaglandin synthesis, supporting the mucus barrier layer. Commonly used dose: 380-760 mg chewed before meals.
- N-Acetyl-Glucosamine (NAG) — substrate for the mucin glycoprotein synthesis. Used in inflammatory bowel disease and chronic gastritis. Commonly used dose: 500-1500 mg/day.
- Slippery Elm and Marshmallow Root — demulcent herbs that coat the gut lining. Traditional use; mechanism involves mucilage providing a protective film. Helpful for acute symptomatic relief in esophageal and gastric inflammation. Commonly used dose: 400-500 mg powder mixed with water, 3 times daily.
- Quercetin — flavonoid with mast cell stabilizing effects, reducing histamine release and tight junction disruption. Commonly used dose: 500-1000 mg twice daily, often combined with bromelain for absorption.
- Omega-3 fatty acids (eicosapentaenoic acid (EPA)/docosahexaenoic acid (DHA)) — anti-inflammatory effects, reduce intestinal inflammation. Commonly used dose: 2-4 grams eicosapentaenoic acid+docosahexaenoic acid per day from fish oil or algae oil. See Omega-3 page.
- Vitamin D3 — supports tight junction integrity and mucosal immunity. Deficiency (serum 25-hydroxyvitamin D, 25-OH-D, below 30 ng/mL) is associated with increased intestinal permeability and inflammatory bowel disease risk. Repletion typically requires 2000-5000 international units (IU)/day, with monitoring. The Institute of Medicine's 2011 tolerable upper intake level is 4,000 IU/day for ages 9 and older, so the top of that range runs past it.
- Zinc (separate from carnosine form) — zinc deficiency directly impairs barrier function. Commonly used supplemental dose: 15-30 mg/day; balance with copper (zinc supplementation depletes copper at higher chronic doses).
A barrier-repair combination practitioners describe for people with documented leaky gut symptoms: L-glutamine 5 g twice daily, zinc carnosine 75 mg twice daily, omega-3 fish oil 2 g eicosapentaenoic acid+docosahexaenoic acid daily, vitamin D3 to maintain serum 25-OH-D at 40-60 ng/mL, plus the dietary interventions above, run for 8-12 weeks and then reassessed.
Vagal Tone Training Protocol
Daily vagal tone training is one of the highest-leverage interventions available because it directly targets the dominant gut-to-brain communication channel. The protocol as practitioners describe it:
- Daily slow-paced breathing — 10 minutes at 5-6 breaths per minute (5 seconds in, 5 seconds out). Practitioners favor first thing in the morning, before phone or email. Breathing apps provide the pacing.
- Heart rate variability (HRV) monitoring — a chest strap or compatible wrist device gives objective feedback. Practitioners track morning RMSSD (root mean square of successive differences, a standard HRV measure) and its 7-day rolling average, looking for a stable or rising trend.
- Cold exposure — cold water face immersion for 30-60 seconds 1-2 times per day, or cold shower for 30-90 seconds at the end of regular shower, or weekly cold plunge if available.
- Aerobic exercise — 150+ minutes per week of moderate-intensity aerobic activity. Zone 2 cardio (heart rate that allows nasal breathing) is particularly effective for vagal tone.
- Sleep optimization — 7-9 hours per night, consistent bedtime and wake time, dark cool room, no screens 1 hour before bed.
- Mindfulness or meditation — 10-20 minutes per day. Loving-kindness meditation has particularly strong HRV evidence.
- Optional: gargling, humming, singing — 2-3 minutes per day. Activates pharyngeal and laryngeal vagal branches.
- Optional: transcutaneous vagus nerve stimulation (tVNS) device — U.S. Food and Drug Administration-cleared nerve stimulators include a supraorbital device for migraine, which acts on the trigeminal nerve rather than the vagus nerve, and a non-invasive vagus nerve stimulator for cluster headache. Consumer-grade devices have weaker evidence.
See the Vagal Nerve Signaling page for the underlying mechanisms.
Root-Cause Stress Reduction
None of the gut-targeted interventions will produce lasting effect if the underlying chronic stress driver remains in place. Identifying and addressing the root cause of chronic stress is often the most important and most difficult component of restoration. Common categories:
- Work-life conflict — unsustainable workload, toxic workplace, misalignment between values and work. May require boundary-setting, role change, or career change.
- Relationship strain — marital conflict, family conflict, social isolation. May benefit from couples therapy, family therapy, or social network rebuilding.
- Financial stress — chronic financial precarity activates the hypothalamic-pituitary-adrenal axis as effectively as acute trauma. Addressing through financial planning, lifestyle restructuring, or income increase.
- Unresolved trauma — childhood trauma, sexual trauma, combat trauma, medical trauma. Evidence-based therapies: eye movement desensitization and reprocessing (EMDR), somatic experiencing, internal family systems, prolonged exposure, cognitive processing therapy.
- Health anxiety — chronic worry about health itself can perpetuate the loop. Cognitive behavioral therapy (CBT) for health anxiety is effective.
- Grief and loss — unresolved or complicated grief can produce persistent hypothalamic-pituitary-adrenal dysregulation.
- Caregiving burden — chronic caregiver stress is a documented driver of inflammatory disease.
Evidence-based therapies that reduce chronic stress and inflammation:
- Cognitive-behavioral therapy (CBT)
- Mindfulness-based stress reduction (MBSR; the Kabat-Zinn 8-week program)
- Mindfulness-based cognitive therapy (MBCT)
- Acceptance and commitment therapy (ACT)
- EMDR for trauma
- Somatic experiencing
- Internal family systems (IFS)
A review of 47 randomized trials with active comparison groups (3,515 people) found that mindfulness programs improved anxiety (effect size 0.38), depression (0.30) and pain (0.33) at about 8 weeks, with moderate evidence, and found "no evidence that meditation programs were better than any active treatment" such as drugs, exercise and other behavioral therapies.
For some patients, pharmaceutical management of the mood/anxiety component is used alongside lifestyle interventions — selective serotonin reuptake inhibitors (SSRIs), serotonin-norepinephrine reuptake inhibitors (SNRIs), low-dose tricyclic antidepressants, buspirone, or atypical agents like bupropion or mirtazapine, prescribed by a primary care physician or psychiatrist. The interventions on this page are not replacements for evidence-based pharmacologic treatment of moderate-to-severe depression or anxiety.
How a 12-Week Protocol Is Sequenced
A starting protocol as practitioners describe it for gut-brain dysregulation (chronic gastrointestinal symptoms plus mood/anxiety symptoms, no red-flag findings):
Weeks 1-2: Foundation
- Mediterranean-style eating, gradually displacing ultraprocessed foods
- Daily 10-minute slow breathing practice (5-6 breaths per minute)
- A consistent sleep schedule (target 8 hours)
- L-glutamine 5 g morning, 5 g evening (empty stomach)
- Fish oil 2 g eicosapentaenoic acid+docosahexaenoic acid daily
- A vitamin D level check, with supplementing if <40 ng/mL
- Identifying and beginning to remove primary stressors
Weeks 3-6: Microbiome restoration
- All of the above continues
- Fermented foods: 1 serving/day week 3, 2 servings/day week 4, working up to 4-6 servings/day by week 6
- A psychobiotic supplement: B. longum 1714 OR L. helveticus R0052 + B. longum R0175, at the dose on the product label
- Gradually increasing dietary fiber (especially prebiotic-rich foods)
- Starting or increasing aerobic exercise (150 min/week target)
Weeks 7-12: Repair, refine, and rebalance
- All of the above continues
- Zinc carnosine 75 mg twice daily added if gastrointestinal symptoms persist
- DGL 380 mg before meals for upper gastrointestinal symptoms (heartburn, gastritis)
- A mindfulness practice (MBSR, app-based meditation, or therapist-guided)
- An elimination-and-reintroduction trial if specific food triggers are suspected
- Reassessment at week 12: symptom diary, stress level, sleep quality, exercise consistency, dietary adherence
Reassessment markers at week 12:
- Substantial improvement (>50% symptom reduction): Maintenance continues; specific supplements may be reduced while diet and lifestyle stay.
- Modest improvement (20-50%): The protocol continues with additional targeted interventions (specific elimination diet trial, additional psychobiotic strain, formal psychotherapy).
- Minimal improvement (<20%): The diagnosis comes back into question. Possibilities: undiagnosed small intestinal bacterial overgrowth, food intolerance, parasite infection, untreated mental health condition requiring pharmacotherapy, autoimmune condition requiring specialist evaluation, mast cell disorder.
Most patients with mild-to-moderate gut-brain dysregulation experience meaningful improvement on this protocol within 8-12 weeks. Patients with severe or complex presentations (chronic inflammatory bowel disease, established autoimmune disease, treatment-resistant depression, severe mast cell activation syndrome (MCAS)) typically need specialist care alongside these foundational interventions.
Key Research Papers
- Jacka FN, O'Neil A, Opie R, Itsiopoulos C, Cotton S, Mohebbi M, Castle D, Dash S, Mihalopoulos C, Chatterton ML, Brazionis L, Dean OM, Hodge AM, Berk M (2017). A randomised controlled trial of dietary improvement for adults with major depression (the 'SMILES' trial). BMC Medicine 15(1):23. — PubMed PMID: 28137247
- Wastyk HC, Fragiadakis GK, Perelman D, Dahan D, Merrill BD, Yu FB, Topf M, Gonzalez CG, Van Treuren W, Han S, Robinson JL, Elias JE, Sonnenburg ED, Gardner CD, Sonnenburg JL (2021). Gut-microbiota-targeted diets modulate human immune status. Cell 184(16):4137-4153. — PubMed PMID: 34256014
- Allen AP, Hutch W, Borre YE, et al. (2016). Bifidobacterium longum 1714 as a translational psychobiotic: modulation of stress, electrophysiology and neurocognition in healthy volunteers. Translational Psychiatry 6(11):e939. — PubMed PMID: 27801892
- Messaoudi M, Lalonde R, Violle N, et al. (2011). Assessment of psychotropic-like properties of a probiotic formulation (Lactobacillus helveticus R0052 and Bifidobacterium longum R0175) in rats and human subjects. British Journal of Nutrition 105(5):755-764. — PubMed PMID: 20974015
- Rao R, Samak G (2012). Role of glutamine in protection of intestinal epithelial tight junctions. Journal of Epithelial Biology and Pharmacology 5(Suppl 1-M7):47-54. — PubMed PMID: 25810794
- Mahmood A, FitzGerald AJ, Marchbank T, et al. (2007). Zinc carnosine, a health food supplement that stabilises small bowel integrity and stimulates gut repair processes. Gut 56(2):168-175. — PubMed PMID: 16777920
- Whelan K, Martin LD, Staudacher HM, Lomer MCE (2018). The low FODMAP diet in the management of irritable bowel syndrome: an evidence-based review of FODMAP restriction, reintroduction and personalisation in clinical practice. Journal of Human Nutrition and Dietetics 31(2):239-255. — Low FODMAP IBS. — PubMed PMID: 29336079
- Lehrer PM, Gevirtz R (2014). Heart rate variability biofeedback: how and why does it work? Frontiers in Psychology 5:756. — HRV biofeedback. — PubMed PMID: 25101026
- Goyal M, Singh S, Sibinga EM, et al. (2014). Meditation programs for psychological stress and well-being: a systematic review and meta-analysis. JAMA Internal Medicine 174(3):357-368. — PubMed PMID: 24395196
- Liu RT, Walsh RFL, Sheehan AE (2019). Prebiotics and probiotics for depression and anxiety: a systematic review and meta-analysis of controlled clinical trials. Neuroscience & Biobehavioral Reviews 102:13-23. — PubMed PMID: 31004628
- Mosaffa-Jahromi M, Lankarani KB, Pasalar M, et al. (2016). Efficacy and safety of enteric coated capsules of anise oil to treat irritable bowel syndrome. Journal of Ethnopharmacology 194:937-946. — PubMed PMID: 27815079
- Berk M, Williams LJ, Jacka FN, et al. (2013). So depression is an inflammatory disease, but where does the inflammation come from? BMC Medicine 11:200. — PubMed PMID: 24228900
- Parletta N, Zarnowiecki D, Cho J, et al. (2019). A Mediterranean-style dietary intervention supplemented with fish oil improves diet quality and mental health in people with depression: A randomized controlled trial (HELFIMED). Nutritional Neuroscience 22(7):474-487. — PubMed PMID: 29215971
- Bayes J, Schloss J, Sibbritt D (2022). The effect of a Mediterranean diet on the symptoms of depression in young males (the "AMMEND: A Mediterranean Diet in MEN with Depression" study): a randomized controlled trial. The American Journal of Clinical Nutrition 116(2):572-580. — doi:10.1093/ajcn/nqac106
- Zhou Q, Verne ML, Fields JZ, et al. (2019). Randomised placebo-controlled trial of dietary glutamine supplements for postinfectious irritable bowel syndrome. Gut 68(6):996-1002. — PubMed PMID: 30108163
- Nikolova VL, Cleare AJ, Young AH, Stone JM (2023). Acceptability, Tolerability, and Estimates of Putative Treatment Effects of Probiotics as Adjunctive Treatment in Patients With Depression: A Randomized Clinical Trial. JAMA Psychiatry 80(8):842-847. — PubMed PMID: 37314797
- Black CJ, Staudacher HM, Ford AC (2022). Efficacy of a low FODMAP diet in irritable bowel syndrome: systematic review and network meta-analysis. Gut 71(6):1117-1126. — PubMed PMID: 34376515
- Schoenen J, Vandersmissen B, Jeangette S, et al. (2013). Migraine prevention with a supraorbital transcutaneous stimulator: a randomized controlled trial. Neurology 80(8):697-704. — PubMed PMID: 23390177
- Ross AC, Manson JE, Abrams SA, et al. (2011). The 2011 report on dietary reference intakes for calcium and vitamin D from the Institute of Medicine: what clinicians need to know. The Journal of Clinical Endocrinology and Metabolism 96(1):53-58. — PubMed PMID: 21118827
PubMed Topic Searches
Connections
- All Remedies
- Gut-Brain Axis Hub
- Gut-Brain Benefits Deep-Dive
- Vagal Nerve Signaling
- Serotonin and Mood
- Stress and Permeability
- Gut Healing
- Stress Management
- Mediterranean Diet
- Elimination Diet
- Natural Anxiety Relief
- Fermented Foods
- Probiotics
- Glutamine
- Omega-3 Fatty Acids
- Irritable Bowel Syndrome
- Covered in depth on its own page: Fermented Foods