⚠ Evidence warning: Clinical trials or other evidence do not support the claims that the refeed preserves or destroys a fast's benefits, that glutamine and probiotics speed gut recovery, and that three meals beat frequent small meals at equal calories. This page keeps it as a report of what people, websites or other media say.
Refeeding Strategy — How to Break a Fast Without Losing the Benefits
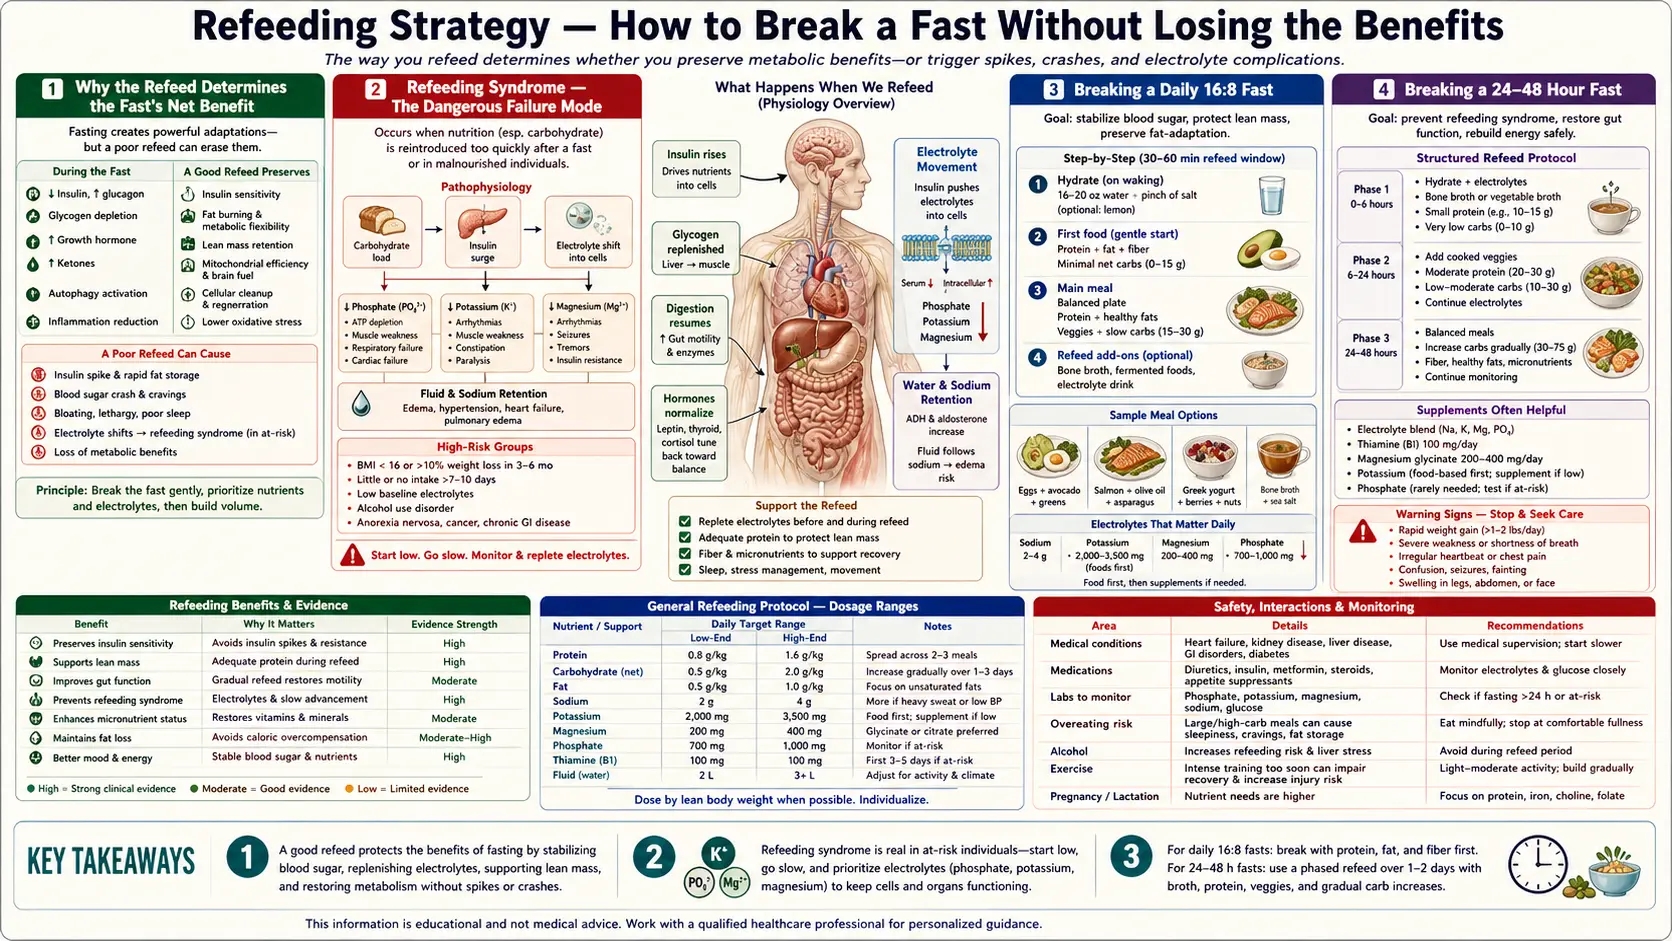
The most-skipped chapter of fasting education is refeeding. Practitioners obsess over fasting protocols, beta-hydroxybutyrate (ketone) strips, and autophagy markers, then break a 72-hour fast with a pizza and wonder why they feel terrible. The refeed itself either preserves or destroys the metabolic benefits of the preceding fast — and in extended fasts of 5+ days, an improperly executed refeed can produce refeeding syndrome, a potentially fatal disorder of phosphorus, potassium, magnesium, and thiamine homeostasis first recognized in liberated World War II concentration-camp survivors who died from cardiac and respiratory failure within days of being given high-carbohydrate meals. This page covers the bone-broth-then-fat-then-protein-then-carbs sequence, the electrolyte and thiamine repletion that prevents refeeding syndrome, the role of L-glutamine and probiotics in gut-mucosa recovery, and the discipline of not overcompensating after a successful fast.
Interactive Visualization Fat Burning & Ketosis — what actually happens Follow a fatty acid out of a fat cell to the mitochondrial gate and find it padlocked by insulin. Drop the carbs, open CPT1, and watch the liver start making ketones. Launch →
Table of Contents
- Why the Refeed Determines the Fast's Net Benefit
- Refeeding Syndrome — The Dangerous Failure Mode
- Breaking a Daily 16:8 Fast
- Breaking a 24-48 Hour Fast
- Breaking a 72-Hour or Longer Fast
- Electrolyte and Thiamine Repletion
- L-Glutamine, Probiotics, and Gut-Mucosa Recovery
- The Post-Fast Binge and What Practitioners Describe Against It
- Warning Signs That Demand Medical Attention
- Key Research Papers
- Connections
- Featured Videos
Why the Refeed Determines the Fast's Net Benefit
The fast itself produces metabolic changes — insulin suppression, ketosis, growth hormone elevation, autophagy induction, immune cell turnover. The refeed is the cellular signal to switch back to growth-and-synthesis mode. Practitioners describe a well-executed refeed as harnessing the elevated growth hormone and the cleared cellular landscape to support a wave of efficient nutrient uptake and tissue rebuilding. Insulin sensitivity is a different matter: in a 2009 study of 14 healthy young adults, a 24-hour fast lowered insulin sensitivity compared with an overnight fast (5.7 to 2.6 units, P < 0.0001) and lowered the immediate insulin response to glucose (Salgin 2009). If executed poorly, the refeed produces dangerous blood-glucose spikes (because the body's glucose-handling machinery has been quiescent for days), violent insulin surges with reactive hypoglycemia, gastrointestinal (GI) distress (because gut digestive enzymes have downregulated), and electrolyte derangement.
The general principle: the longer the fast, the slower and more deliberate the refeed practitioners describe. A 16-hour daily fast is usually broken with a normal meal. For a 24-48 hour fast they describe a few hours of gentle reintroduction, and for a 72-hour fast a structured 24-hour refeed protocol. In a 5-day or longer fast, blood phosphorus, potassium and magnesium can fall quickly once food returns, and practitioners describe 2-3 days of progressive refeeding before normal eating resumes.
The other principle: the refeed is when the gains are consolidated. Practitioners who treat the refeed as a reward and consume large quantities of refined carbohydrates and processed food undo much of the fast's benefit within hours — the insulin surge, mechanistic target of rapamycin (mTOR) reactivation, and inflammatory response of an ultra-processed refeed can overshoot the fasted baseline and produce a net-negative outcome. Practitioners describe the ideal refeed as nourishing food, deliberately paced, and aligned with the post-fast metabolic state.
Refeeding Syndrome — The Dangerous Failure Mode
Refeeding syndrome is the cluster of metabolic disturbances that can follow rapid reintroduction of nutrition in a chronically undernourished patient. It was first systematically described in the 1940s in liberated WWII prisoners of war and concentration-camp survivors who died unexpectedly within days of being fed by well-meaning relief workers. Modern recognition came largely through the parenteral nutrition literature of the 1970s-80s.
The mechanism: during prolonged fasting or starvation, intracellular stores of phosphorus, potassium, magnesium, and water-soluble vitamins (especially thiamine) become depleted, but serum levels often appear normal because of slow renal clearance and intracellular-to-extracellular redistribution. When carbohydrate is reintroduced, the resulting insulin surge drives a sudden intracellular shift of phosphorus, potassium, and magnesium — producing rapid and severe drops in serum levels of all three within hours. Simultaneously, thiamine demand rises sharply because thiamine is the cofactor for pyruvate dehydrogenase and is needed for the resumption of carbohydrate metabolism.
The clinical syndrome:
- Hypophosphatemia — the most dangerous component. Severe hypophosphatemia (< 1.0 mg/dL) produces respiratory muscle weakness (because adenosine triphosphate (ATP) synthesis requires phosphorus), cardiac dysfunction, rhabdomyolysis, hemolysis, and seizures.
- Hypokalemia — cardiac arrhythmias, muscle weakness, ileus.
- Hypomagnesemia — arrhythmias, tetany, seizures.
- Thiamine deficiency — Wernicke encephalopathy (confusion, ataxia, ophthalmoplegia) or wet beriberi (high-output cardiac failure).
- Volume overload — refeeding-induced sodium retention can produce pulmonary edema in patients with marginal cardiac function.
The classic high-risk population is chronically malnourished hospitalized patients receiving aggressive enteral or parenteral nutrition, not healthy intermittent-fasting practitioners. But a 7-day water-only fast in a person who was already lean to begin with can produce a milder version of the same phenomenon. The general rule: fasts beyond 5 days, fasts undertaken by underweight or chronically ill people, and any extended fast where the refeed begins with a large carbohydrate load, all increase refeeding-syndrome risk.
The prevention approach fasting practitioners describe: the refeed starts with bone broth and a small amount of fat-and-protein, not carbohydrate; carbohydrate returns gradually over 24-48 hours; thiamine is taken at 100-300 mg/day for the first several days; and the warning signs (see below) are watched for. For fasts beyond 5 days, they describe checking baseline electrolytes (phosphorus, potassium, magnesium) before refeeding begins and again at 12-24 hour intervals during the refeed. For hospital inpatients, a 2018 expert consensus algorithm describes screening for risk (low body mass index, large unintentional weight loss, little or no nutritional intake, a history of alcohol or drug abuse), a careful start with a stepwise increase in energy and fluids, electrolyte and vitamin supplementation, and close clinical monitoring (Friedli 2018).
The 2020 consensus of the American Society for Parenteral and Enteral Nutrition (ASPEN), written for hospitalized adults and children, defines refeeding syndrome by numbers. It is a fall in any one, two or all three of blood phosphorus, potassium and magnesium, within 5 days of restarting calories: by 10-20% (mild), by 20-30% (moderate), or by more than 30% or with organ dysfunction from these falls or from thiamine deficiency (severe) (da Silva 2020).
Breaking a Daily 16:8 Fast
Daily time-restricted eating (TRE) fasts of 16-18 hours do not produce a refeeding-syndrome risk in healthy adults. The first meal of the eating window can be a normal balanced meal — protein, fat, vegetables, moderate complex carbohydrates — without special precaution.
Practitioners still distinguish between first-meal patterns:
- The first-meal pattern practitioners favor — protein-led, with healthy fat and non-starchy vegetables. Examples: 3-egg omelet with spinach and avocado; grilled salmon with a salad; bone broth followed by a chicken breast and roasted vegetables. The protein-and-fat pattern produces a moderate, sustained insulin response.
- The first-meal pattern practitioners rank lower — carbohydrate-dominant, especially refined carbohydrate. They report that a muffin, a bagel, a sweetened latte, or a bowl of cereal produces a large blood-glucose excursion and reactive hypoglycemia within 2-3 hours.
- Hydration first — many time-restricted eating practitioners report benefit from a glass of water with a pinch of mineral salt 15-30 minutes before the first meal, to rehydrate and pre-replete sodium lost during the overnight fast.
The discipline practitioners credit for sustained time-restricted eating benefit: the eating window contains real food — protein, vegetables, fruits, healthy fats — not a constant grazing pattern of snacks and sweetened beverages. Three meals in an 8-hour window with no snacking is metabolically superior to 5-6 small frequent feedings even at identical total calories, because each snack is its own mechanistic target of rapamycin-activating, insulin-secreting event.
Breaking a 24-48 Hour Fast
By 24 hours of fasting, gastric emptying has slowed, digestive enzyme secretion has downregulated, and the gut mucosa has reduced its turnover. A large meal at this point will sit in the stomach uncomfortably, may produce nausea, and often causes a violent reactive hypoglycemia event 2-3 hours later.
The structured 24-48 hour refeed protocol, as fasting practitioners describe it:
- Hour 0 (breaking the fast) — one cup of warm bone broth, sipped slowly over 15-20 minutes. The protein content is small (3-6 grams), the fat content is moderate, and the gelatin is gentle on the gut mucosa. Most importantly, the electrolytes (sodium, potassium, magnesium) replete the deficit accumulated during the fast.
- Hour 0.5-1 — if the broth is tolerated without nausea, a small portion of healthy fat is added (1/2 avocado, 1 oz nuts, or 1 tbsp olive oil) and a small portion of protein (2-3 oz eggs, fish, or chicken).
- Hour 2-3 — the first "real" meal. Protein (4-6 oz), healthy fat (avocado, olive oil, butter), non-starchy vegetables (leafy greens, broccoli, asparagus). Still no significant carbohydrate.
- Hour 4-6 — if the first meal was well tolerated, a second meal can include modest amounts of starchy vegetables (sweet potato, squash) or fruit (berries). Grains and refined carbohydrates stay out for the first 24 hours of refeeding.
- Hour 8-24 — return to normal balanced eating. The usual goal for the first 24 hours after breaking the fast is approximately 80% of normal caloric intake, with the deficit made up over the following day or two.
The reason for the broth-first protocol: it tests gut tolerance, replenishes electrolytes, and produces a smaller insulin spike than any solid food. The reason given for a first meal without carbohydrate: carbohydrate produces the largest insulin response, the largest blood-glucose excursion, and, practitioners report, the largest risk of reactive hypoglycemia.
Breaking a 72-Hour or Longer Fast
After a 72-hour fast, practitioners describe a more deliberate 24-hour refeed protocol, with explicit electrolyte and thiamine supplementation, and progressive caloric reintroduction.
- Day 1 of refeed — total intake ~25-40% of normal calories. The day begins with bone broth and small portions of fat and protein. These protocols leave out grains, sugar, alcohol and large meals. Their supplements: 100-300 mg thiamine, 400 mg magnesium, 99 mg potassium, plus adequate sodium intake.
- Day 2 of refeed — total intake ~50-70% of normal calories. Introduce starchy vegetables (sweet potato, squash, beets) in modest portions. Thiamine and electrolyte supplementation continue. Grains and refined carbohydrate stay out.
- Day 3 of refeed — total intake ~80-100% of normal calories. Whole grains return in modest portions. Elevated thiamine intake continues for one more day.
- Day 4 onward — return to normal eating pattern. Many extended-fast practitioners maintain a slightly tighter daily eating window (e.g. resuming 16:8 time-restricted eating) for the week following a 72-hour fast, to extend the metabolic flexibility gains.
For fasts of 5 days or longer, practitioners describe baseline serum chemistry (phosphorus, potassium, magnesium, calcium, thiamine if available) before refeeding begins, and repeat chemistry 12-24 hours into refeeding to detect early refeeding syndrome before symptoms emerge. Blood phosphorus, potassium and magnesium can fall quickly once food returns, which is why refeeding syndrome is dated to the first 5 days after calories restart (da Silva 2020).
Electrolyte and Thiamine Repletion
The amounts below are the ones fasting practitioners describe.
- Sodium — 2-3 grams over the first day of refeeding (broth, soup, sea-salted vegetables). The natriuresis of fasting depletes sodium; practitioners describe repleting it deliberately during the refeed.
- Potassium — 3-4 grams from food sources (avocado, spinach, sweet potato, salmon, mushrooms) over the first 24-48 hours. Under US regulation 21 CFR 201.306, coated and uncoated potassium tablets supplying 100 mg or more of potassium carry the prescription statement. The warning that regulation quotes concerns small-bowel lesions that have caused obstruction, hemorrhage and perforation; it calls their incidence low and says a causal relationship in people has not been definitely established. Separately, potassium has a narrow therapeutic window and supraphysiologic dosing can produce dangerous hyperkalemia (high blood potassium). Food-based potassium is safer than supplemental.
- Magnesium — 300-500 mg supplementally (magnesium glycinate or citrate) plus food sources (dark leafy greens, pumpkin seeds, almonds, dark chocolate). Magnesium is the most commonly deficient mineral in fasting practitioners.
- Phosphorus — food sources (dairy, eggs, fish, nuts) are usually adequate; supplemental phosphorus is rarely needed for self-directed extended fasts up to 72 hours. For longer fasts or in people with risk factors for refeeding syndrome, blood phosphorus can fall quickly once food returns, and oral phosphorus supplements are one form of replacement.
- Thiamine (B1) — 100-300 mg/day for 3-5 days after a fast longer than 48 hours. Thiamine is required for the resumption of carbohydrate metabolism (pyruvate dehydrogenase cofactor). The classic refeeding-syndrome complication of Wernicke encephalopathy is prevented by adequate thiamine. Oral thiamine HCl is cheap, well-tolerated, and there is essentially no toxicity risk at these doses.
- B-complex — practitioners also use a general B-complex multivitamin alongside the thiamine as insurance, since the other B vitamins (riboflavin, niacin, B6, folate, B12) are all cofactors for various aspects of carbohydrate, fat, and protein metabolism.
L-Glutamine, Probiotics, and Gut-Mucosa Recovery
The gut mucosa turns over every 3-5 days under fed conditions — one of the fastest-renewing tissues in the body. During a fast longer than 3 days, this turnover slows substantially, and the villus enterocytes that normally absorb nutrients may show measurable atrophy. The refeed is when the mucosa rebuilds.
Practitioners describe three interventions as supporting gut recovery during refeeding:
- L-Glutamine — the primary fuel of enterocytes (gut epithelial cells). 5-10 grams of L-glutamine powder dissolved in water, taken in the first 24-48 hours of refeeding, is described as supporting rapid enterocyte recovery. Glutamine is technically a non-essential amino acid, but during refeeding from extended fasting it becomes "conditionally essential" because the demand outstrips endogenous synthesis. There is a safety finding from a much sicker group: in a trial of 1,223 critically ill adults with multiorgan failure on mechanical ventilation, given glutamine by vein and by feeding tube, 28-day deaths showed a trend toward more with glutamine (32.4% vs. 27.2%, P = 0.05), and in-hospital and 6-month deaths were significantly higher (Heyland 2013). These patients were far sicker than healthy people breaking a fast, and the trial did not study refeeding after a fast.
- Probiotics and fermented foods — practitioners describe the microbiome composition shifting during extended fasting (reduced bacterial diversity, shifts in dominant phyla), and the refeed as the opportunity to deliberately seed beneficial species. In a study of 15 healthy men on a 10-day fast of about 250 kcal a day, bacteria that break down dietary fiber-type carbohydrates (polysaccharides) decreased, other groups increased, and these changes were reversed 3 months later. Blood inflammatory signals (interleukin-6, interleukin-10, interferon gamma and tumor necrosis factor alpha) rose when food was reintroduced, which the authors read as a reactivation of the normal immune response to meals (Mesnage 2019). Fermented foods (sauerkraut, kimchi, kefir, plain yogurt) during the refeed support recolonization. Multi-strain probiotic supplements are also used.
- Bone broth gelatin — the gelatin in well-made bone broth provides glycine and proline, the substrates for collagen synthesis and gut-mucosa repair. This is one of the reasons bone broth is the traditional first food when breaking a fast across many cultures. A laboratory analysis found that broth made to a standardized recipe held significantly less hydroxyproline, glycine, proline and other key amino acids than a 20 g dose of reference collagen supplements, with large variation among non-standardized recipes. Its authors judged broth unlikely to be a consistently reliable source, and noted that whether these building blocks support new collagen in the body is still to be proven (Alcock 2019).
Many practitioners report that their digestive tolerance after a multi-day fast is dramatically improved — foods that previously caused bloating or discomfort suddenly are well-tolerated. They attribute this partly to the gut-mucosa renewal effect and partly to a microbiome reset from the fasting-refeeding cycle. The one study above found the bacterial shifts gone by 3 months (Mesnage 2019).
The Post-Fast Binge and What Practitioners Describe Against It
The psychological challenge of the refeed is often underestimated. After 48-72 hours without food, the ghrelin-driven hunger and the cognitive anticipation of "deserved" food combine to produce an urge to consume large quantities of palatable food immediately upon breaking the fast. This urge undoes the fast's benefits in two distinct ways:
- Physiologically — the large carbohydrate load produces a massive insulin surge, reactivates mechanistic target of rapamycin with full force, suppresses autophagy, and produces inflammatory cytokine elevation. The fast's metabolic benefits are not just lost but actively reversed.
- Behaviorally — the binge reinforces the cognitive pattern of fasting-as-restriction-followed-by-reward, which is the same psychological pattern that drives disordered eating. Practitioners describe healthy fasting practice as a tool, not a deprivation followed by indulgence.
The structural prevention strategies practitioners describe:
- Planning the refeed in advance — the first meal is decided before the fast starts, with the ingredients on hand. The post-fast brain is in a poor state for nutritional decision-making.
- Eating in a calm environment — sitting down, eating slowly, chewing thoroughly. The vagal-tone-driven satiety signal takes 15-20 minutes to develop; rapid eating overshoots before satiety can register.
- The broth-first protocol — even when not strictly required (e.g. for shorter fasts), the broth pre-meal blunts the urge to overeat by providing immediate gastric distension and a small amount of nutrient signal.
- Pre-portioning the first meal — a normal portion served onto a plate, rather than family-style serving dishes where the absence of a defined portion size invites overshoot.
- Leaving out alcohol on refeed day — alcohol after a fast hits much harder than usual (low glycogen, low body water, low blood pressure), produces dramatic insulin and glucose dysregulation, and impairs the post-fast judgment that prevents overeating.
Warning Signs That Demand Medical Attention
Most fasting refeeds proceed uneventfully. The following symptoms during or immediately after refeeding are signs hospitals treat as urgent:
- Confusion, altered mental status, or new neurological symptoms — possible Wernicke encephalopathy from thiamine deficiency, hypoglycemia, hyponatremia, or hypophosphatemia. Hospitals treat this as an emergency.
- Difficulty breathing or sudden weakness — possible respiratory muscle weakness from severe hypophosphatemia. Hospitals treat this as an emergency.
- Palpitations or new arrhythmia — possible electrolyte derangement (potassium, magnesium, or calcium). Hospitals treat this as urgent.
- Severe edema or sudden weight gain within 24-48 hours of refeeding — possible refeeding-induced fluid retention with risk of pulmonary edema. Hospitals treat this as urgent.
- Severe abdominal pain — possible gallstone complication or pancreatitis. Hospitals treat this as urgent.
- Severe headache or visual changes — possible severe electrolyte abnormality or hypertensive event. Hospitals treat this as urgent.
- Persistent vomiting — risk of further electrolyte loss and dehydration, more so if it does not resolve quickly.
The vast majority of fasting practitioners will never encounter any of these. But the prevalence of social-media fasting content has produced a population of self-directed extended fasters who do not recognize the warning signs of refeeding syndrome until they are in the emergency department. Knowing what to watch for is the cheapest form of insurance.
Key Research Papers
- Mehanna HM, Moledina J, Travis J (2008). Refeeding syndrome: what it is, and how to prevent and treat it. BMJ. — PubMed PMID: 18583681
- Crook MA, Hally V, Panteli JV (2001). The importance of the refeeding syndrome. Nutrition. — PubMed PMID: 11448586
- Stanga Z, Brunner A, Leuenberger M et al. (2008). Nutrition in clinical practice-the refeeding syndrome: illustrative cases and guidelines for prevention and treatment. European Journal of Clinical Nutrition 62:687-694. — PubMed PMID: 17700652
- Boateng AA et al. (2010). Refeeding syndrome: treatment considerations based on collective analysis of literature case reports. Nutrition. — PubMed PMID: 20122539
- Solomon SM, Kirby DF (1990). The refeeding syndrome: a review. JPEN. — PubMed PMID: 2109122
- Friedli N, Stanga Z, Culkin A et al. (2018). Management and prevention of refeeding syndrome in medical inpatients: An evidence-based and consensus-supported algorithm. Nutrition 47:13-20. — PubMed PMID: 29429529
- NICE (UK National Institute for Health and Care Excellence) guideline on nutrition support — refeeding syndrome criteria. — PubMed
- Wilhelmi de Toledo F, Buchinger A, Burggrabe H et al. (2013). Fasting therapy - an expert panel update of the 2002 consensus guidelines. Forschende Komplementärmedizin 20:434-43. — PubMed PMID: 24434758
- Wischmeyer PE (2008). Glutamine: role in critical illness and ongoing clinical trials. Current Opinion in Gastroenterology. — PubMed PMID: 18301270
- Wang B, Wu G, Zhou Z et al. (2015). Glutamine and intestinal barrier function. Amino Acids 47:2143-54. — PubMed PMID: 24965526
- Maughan RJ, Shirreffs SM, Watson P (2007). Exercise, heat, hydration and the brain. Journal of the American College of Nutrition 26:604S-612S. — PubMed PMID: 17921473
- Kerndt PR, Naughton JL, Driscoll CE, Loxterkamp DA (1982). Fasting: the history, pathophysiology and complications. Western Journal of Medicine 137:379-99. — PubMed PMID: 6758355
- Maughan RJ, Fallah J, Coyle EF (2010). The effects of fasting on metabolism and performance. British Journal of Sports Medicine 44:490-4. — PubMed PMID: 20484315
- Salgin B, Marcovecchio ML, Humphreys SM et al. (2009). Effects of prolonged fasting and sustained lipolysis on insulin secretion and insulin sensitivity in normal subjects. American Journal of Physiology. Endocrinology and Metabolism 296:E454-61. — PubMed PMID: 19106250
- da Silva JSV, Seres DS, Sabino K et al. (2020). ASPEN Consensus Recommendations for Refeeding Syndrome. Nutrition in Clinical Practice 35:178-195. — PubMed PMID: 32115791
- Heyland D, Muscedere J, Wischmeyer PE et al. (2013). A randomized trial of glutamine and antioxidants in critically ill patients. New England Journal of Medicine 368:1489-97. — PubMed PMID: 23594003
- Mesnage R, Grundler F, Schwiertz A, Le Maho Y, Wilhelmi de Toledo F (2019). Changes in human gut microbiota composition are linked to the energy metabolic switch during 10 d of Buchinger fasting. Journal of Nutritional Science 8:e36. — PubMed PMID: 31798864
- Alcock RD, Shaw GC, Burke LM (2019). Bone Broth Unlikely to Provide Reliable Concentrations of Collagen Precursors Compared With Supplemental Sources of Collagen Used in Collagen Research. International Journal of Sport Nutrition and Exercise Metabolism 29:265-272. — PubMed PMID: 29893587
PubMed Topic Searches
Connections
- All Remedies
- Fat Burning & Ketosis — interactive animation
- Fasting Benefits Hub
- Fasting Overview
- Time-Restricted Eating 16:8
- Extended Fasts (24-72h)
- Autophagy & Mechanistic Target of Rapamycin
- Glutamine (Gut Refeed)
- Bone Broth (Refeed Starter)
- Vitamin B1 (Thiamine)
- Magnesium
- Potassium
- Sodium
- Phosphorus
- Type 2 Diabetes
- Eggs (Refeed Protein)