Low FODMAP — The Monash Protocol for Irritable Bowel Syndrome (IBS)
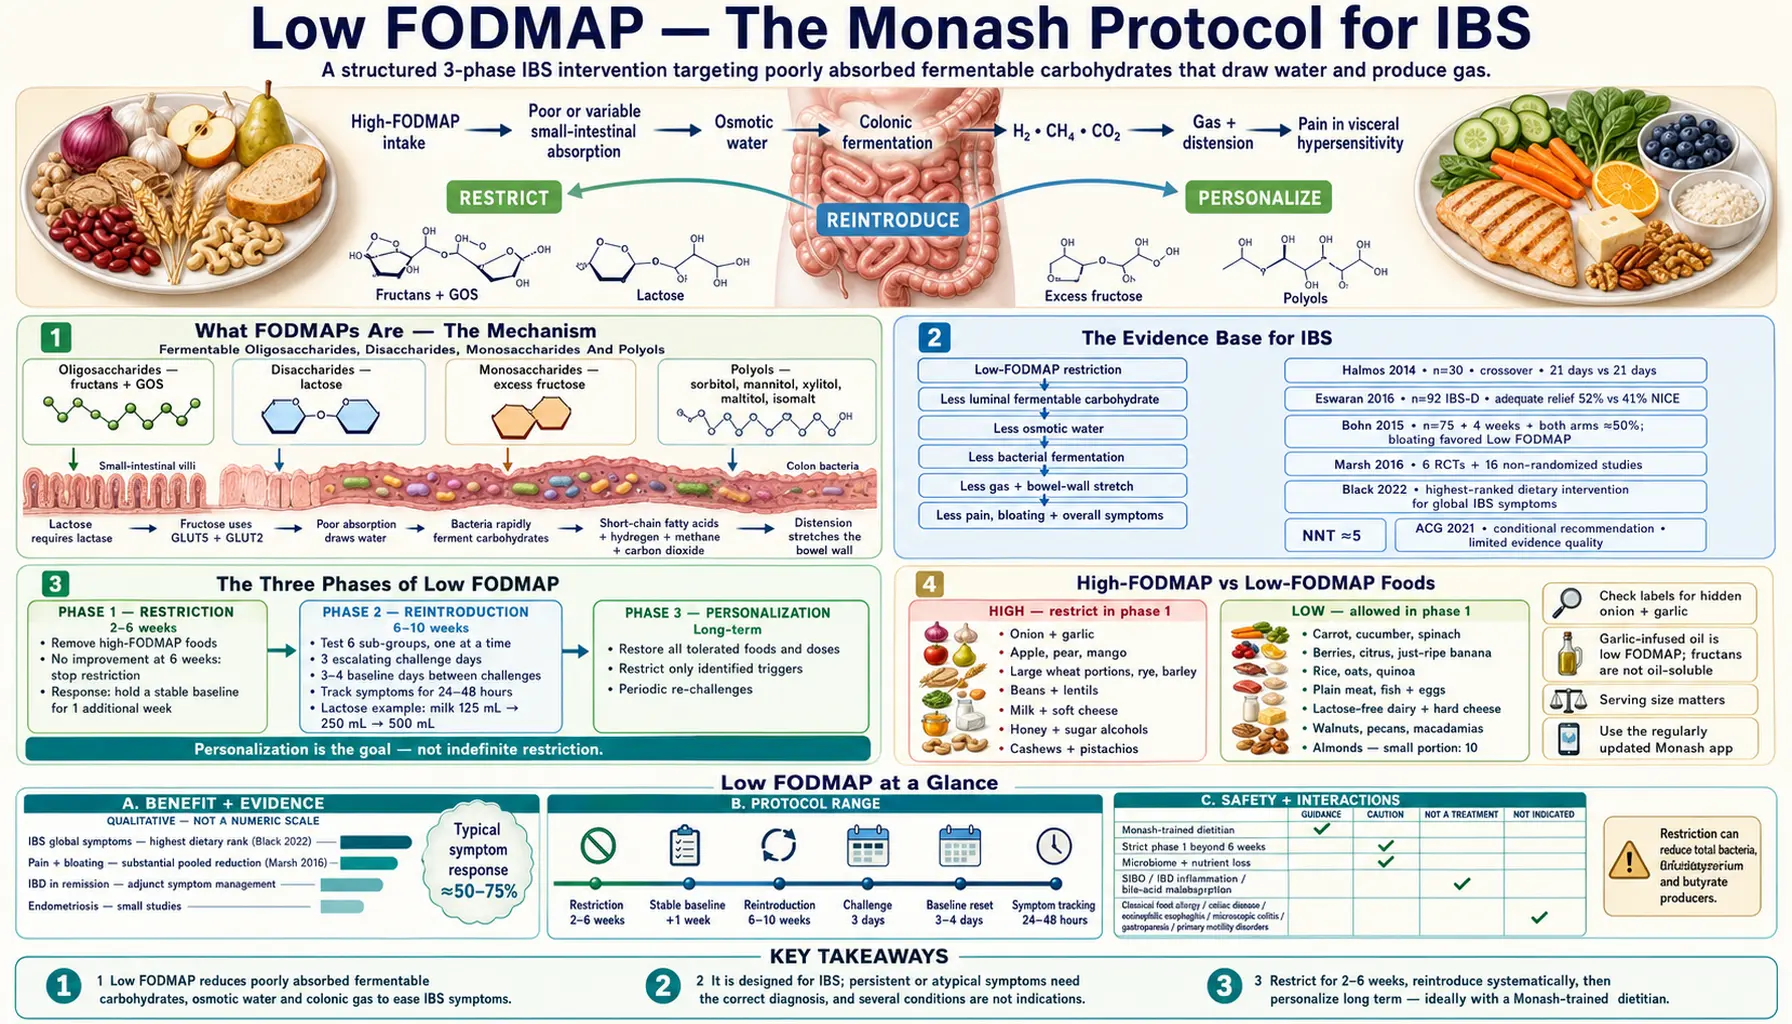
The Low FODMAP diet, developed at Monash University in Melbourne by Peter Gibson, Susan Shepherd, and Jane Muir starting in the early 2000s, is the most evidence-based dietary intervention for irritable bowel syndrome. Multiple randomized controlled trials and meta-analyses (Halmos 2014, Eswaran 2016, Black 2022 network meta-analysis) show approximately 50-75% symptom-response rates — comparable to or exceeding pharmacotherapy. Unlike most "elimination diets" which target speculatively-blamed foods, Low FODMAP targets a specific mechanism: short-chain fermentable carbohydrates that are poorly absorbed in the small intestine, draw water into the small bowel osmotically, then reach the colon where bacterial fermentation produces gas, distension, and pain in patients with visceral hypersensitivity. The protocol is a 3-phase structured intervention — restriction (2-6 weeks), systematic reintroduction by FODMAP sub-group, and long-term personalization — ideally done with a registered dietitian to guard against the over-restriction trap. This page walks through the science, the food list, the structured reintroduction sub-groups, and the personalization phase that turns a temporary intervention into sustainable long-term eating.
Table of Contents
- What FODMAPs Are — The Mechanism
- The Evidence Base for Irritable Bowel Syndrome
- The Three Phases of Low FODMAP
- High-FODMAP vs Low-FODMAP Foods
- The Six Reintroduction Sub-Groups
- The Role of a Registered Dietitian
- Beyond Irritable Bowel Syndrome — Small Intestinal Bacterial Overgrowth, Inflammatory Bowel Disease, Endometriosis
- Microbiome Concerns and the Over-Restriction Trap
- Practical Tools (Smartphone App, Certification Marks)
- Key Research Papers
- Connections
- Featured Videos
What FODMAPs Are — The Mechanism
FODMAP is an acronym for Fermentable Oligosaccharides, Disaccharides, Monosaccharides, And Polyols. These are short-chain carbohydrate molecules that share two clinically relevant properties:
- Poor or variable absorption in the small intestine — either because they require a digestive enzyme that some individuals lack (lactose requires lactase), because they exceed the saturation point of their dedicated transporter (fructose requires GLUT5 and GLUT2 transporters which saturate at modest doses), or because the human small intestine lacks the enzymes to hydrolyze them at all (fructans, galacto-oligosaccharides, and polyols).
- Rapid fermentation by colonic bacteria — once they reach the colon, gut bacteria ferment them into short-chain fatty acids, hydrogen gas, methane, and carbon dioxide. In a healthy gut, this fermentation contributes beneficially to colonocyte energy and microbiome diversity. In patients with visceral hypersensitivity (the core neurobiological feature of irritable bowel syndrome, IBS), the gas distension and the resulting bowel-wall stretching produce disproportionate pain and discomfort.
The specific FODMAP categories and their major dietary sources:
- Oligosaccharides (fructans and galacto-oligosaccharides / GOS): Wheat, rye, barley, onions, garlic, leeks, asparagus, artichokes, chicory root (inulin), legumes (beans, lentils, chickpeas), cashews, pistachios.
- Disaccharides (lactose): Milk, soft cheese (ricotta, cottage cheese), yogurt, ice cream. Hard aged cheese (cheddar, parmesan) is low in lactose. Note: lactose is only a FODMAP for individuals with reduced lactase activity, which is the majority of humans outside Northwest Europe.
- Monosaccharides (excess fructose, defined as fructose in excess of glucose): Apples, pears, mangoes, watermelon, high-fructose corn syrup, honey, agave. Fruits with balanced fructose:glucose ratios (berries, citrus, banana) are low FODMAP.
- Polyols (sugar alcohols): Sorbitol (stone fruits — cherries, peaches, plums; apples), mannitol (mushrooms, cauliflower), xylitol, maltitol, isomalt (in "sugar-free" candies and gum — the major cause of "diet candy diarrhea").
The Monash researchers' insight was that grouping these by mechanism (rather than by chemical class as traditionally taught) and restricting them together produces a single coherent intervention that addresses the multiple food triggers irritable bowel syndrome patients report. Before FODMAP, an irritable bowel syndrome patient might be told "avoid milk" if lactose intolerant, or "avoid apples" if fructose-sensitive, or "avoid wheat" for unclear reasons — without recognition that all three are variations on the same osmotic-and-fermentative theme.
The Evidence Base for Irritable Bowel Syndrome
The Low FODMAP diet has the strongest evidence base of any dietary intervention for irritable bowel syndrome. Key studies:
- Halmos EP et al. 2014 (Search PubMed): The pivotal randomized crossover trial. 30 irritable bowel syndrome patients consumed a low-FODMAP diet for 21 days, then a typical Australian diet for 21 days, with washout periods. Symptom severity scores were substantially lower on the low-FODMAP diet, and the response was reproducible across patients.
- Eswaran SL et al. 2016 (PubMed PMID: 27725652): US-based randomized controlled trial (RCT) comparing low-FODMAP to modified UK National Institute for Health and Care Excellence (NICE) irritable bowel syndrome dietary guidelines in 92 patients with diarrhea-predominant irritable bowel syndrome. 52% on low-FODMAP reported adequate relief vs 41% on the modified National Institute for Health and Care Excellence diet, a difference that was not statistically significant; the low-FODMAP group had significantly more abdominal-pain responders (51% vs 23%).
- Böhn L et al. 2015 (PubMed PMID: 26255043): Swedish randomized controlled trial, 75 irritable bowel syndrome patients randomized to low-FODMAP vs traditional irritable bowel syndrome dietary advice for 4 weeks. Symptom severity fell in both groups with no significant difference between the diets: 50% of the low-FODMAP group and 46% of the traditional-advice group had a drop of at least 50 points on the IBS Symptom Severity Scale.
- Marsh A et al. 2016 (PubMed PMID: 25982757): First major meta-analysis. Six randomized controlled trials (RCTs) and 16 non-randomized intervention studies. Substantial reduction in pain, bloating, and overall symptom scores on low-FODMAP across pooled data.
- Black CJ et al. 2022 (PMID 34376515): Network meta-analysis of 13 randomized controlled trials (944 patients) of the low-FODMAP diet. For global symptom improvement, low-FODMAP ranked first against habitual diet and was superior to all the other comparison diets and dietary advice in the trials, including British Dietetic Association / National Institute for Health and Care Excellence advice; the analysis did not compare the diet with drug treatments.
The number-needed-to-treat (NNT) for meaningful symptom improvement is approximately 5 — that is, treating 5 irritable bowel syndrome patients with the low-FODMAP diet produces 1 additional responder who would not have improved on a control diet. This NNT is competitive with most pharmaceutical irritable bowel syndrome interventions including rifaximin (NNT approximately 10-11 for diarrhea-predominant irritable bowel syndrome, IBS-D), linaclotide, lubiprostone, and tricyclic antidepressants.
The American College of Gastroenterology 2021 irritable bowel syndrome management guideline states: “We recommend a limited trial of a low … (FODMAP) diet in patients with IBS to improve global symptoms.”
The Three Phases of Low FODMAP
The Monash protocol is explicitly three phases, and skipping any phase substantially reduces the intervention's value. The phases are:
Phase 1: Restriction (2-6 weeks)
- All high-FODMAP foods are removed. The developers' smartphone app and certified resources provide the definitive food list. Restriction is binary: high-FODMAP foods are off, low-FODMAP foods are on.
- Duration is the shortest interval needed to assess response — 2 weeks if response is dramatic, up to 6 weeks for slower responders. The protocol does not continue the diet beyond 6 weeks without moving on to reintroduction, because of microbiome and nutritional concerns.
- If there is no improvement at 6 weeks, the protocol treats FODMAPs as not the trigger: the restriction ends and other diagnoses or treatments are looked for.
- If improvement is achieved, the restriction is held for an additional week to establish a stable symptom baseline before beginning reintroductions.
Phase 2: Reintroduction (6-10 weeks)
- Each FODMAP sub-group (fructans, GOS, lactose, fructose, sorbitol, mannitol) is reintroduced systematically and individually: one sub-group at a time across 3 days, then a return to baseline restriction for 3-4 days before the next challenge.
- Each sub-group challenge uses a representative test food at three escalating doses (typically day 1: small, day 2: moderate, day 3: large). For example, the lactose challenge might use milk (125ml whole milk on day 1, 250ml on day 2 if tolerated, 500ml on day 3 if tolerated).
- Symptoms are tracked in a structured journal during and for 24-48 hours after each challenge.
- The output of phase 2 is a personalized list of which sub-groups trigger symptoms and at what threshold doses.
Phase 3: Personalization (long-term)
- The patient reintroduces all tolerated foods at all tolerated doses, restricting only the specific FODMAP sub-groups that triggered symptoms during phase 2 reintroduction.
- Periodic re-challenges are encouraged — FODMAP tolerance can change over time, especially after addressing underlying conditions like small intestinal bacterial overgrowth (SIBO), gastritis, or chronic stress.
- Some patients eventually find they can tolerate small amounts of formerly-trigger FODMAPs but not large amounts — the "dose threshold" model. Personalization respects these individual thresholds.
The personalization phase is the goal — not the restriction phase. A patient on indefinite phase 1 restriction is not "doing FODMAP correctly" — they are missing the entire point of the intervention, which is to identify their personal triggers and eat a maximally varied diet within those constraints.
High-FODMAP vs Low-FODMAP Foods
The definitive food list is maintained by Monash University and updated regularly as new foods are tested in their laboratory. The university's smartphone app carries the full list. A simplified summary of the most consequential categories:
High-FODMAP (restricted in phase 1):
- Vegetables: Onion, garlic (the two biggest offenders, included in nearly all commercial broths, soups, sauces, and seasonings), leek, shallot, asparagus, artichoke, cauliflower, mushroom, sugar snap pea, Brussels sprouts in large portions, beetroot.
- Fruits: Apple, pear, mango, watermelon, peach, plum, cherry, dried fruit (raisins, prunes, dates), apricot, blackberry.
- Grains: Wheat in large amounts (bread, pasta, couscous), rye, barley. Note: small amounts of wheat (less than approximately 25g/day) are tolerated by many.
- Legumes: Chickpeas, kidney beans, black beans, lentils (especially red and large portions of green), baked beans, soy beans.
- Dairy: Milk (cow, goat, sheep), soft cheese (ricotta, cottage cheese, cream cheese), yogurt (most varieties), ice cream.
- Sweeteners: Honey, high-fructose corn syrup, agave, sorbitol, mannitol, xylitol, isomalt, maltitol (the "-itol" sugar alcohols in sugar-free candy and gum).
- Nuts: Cashews, pistachios.
Low-FODMAP (allowed in phase 1):
- Vegetables: Carrots, cucumber, lettuce, spinach, kale (small portions), bell pepper, eggplant, zucchini, tomato, potato, sweet potato (small portions), parsnip, scallion green tops (the white bulb is high FODMAP), bok choy, green beans.
- Fruits: Bananas (just-ripe, not over-ripe), berries (strawberry, blueberry, raspberry), citrus (orange, lemon, lime, mandarin), grapes, kiwi, pineapple, papaya, dragon fruit.
- Grains: Rice (white or brown), oats, quinoa, corn, sourdough wheat bread in small portions (the long fermentation degrades fructans), gluten-free bread and pasta (most are low FODMAP).
- Animal protein: All plain meat, poultry, fish, seafood, eggs. Processed meats may contain garlic and onion — the ingredient label lists them.
- Dairy: Lactose-free milk and yogurt, hard aged cheese (cheddar, parmesan, swiss), butter, ghee.
- Sweeteners: Table sugar (sucrose), maple syrup (small portions), stevia, glucose, dextrose, rice malt syrup.
- Nuts: Almonds (small portions, 10), walnuts, pecans, macadamia, peanuts (small portions).
The single largest practical challenge is garlic and onion. They are nearly ubiquitous in restaurant cooking, prepared foods, and "natural flavors" labels. Garlic-infused oil is low FODMAP (the fructans are not oil-soluble), which provides one workaround — garlic-infused olive oil gives garlic flavor without the FODMAP load.
The Six Reintroduction Sub-Groups
The Monash reintroduction protocol divides FODMAPs into six sub-groups, each tested independently. The standard order and representative test foods:
- Lactose: Test with milk (whole cow's milk, 125ml day 1, 250ml day 2, 500ml day 3). Failure indicates lactose intolerance — the usual responses are limiting dairy or using lactase enzyme supplements with dairy.
- Excess Fructose: Test with honey (1 teaspoon day 1, 2 teaspoons day 2, 1 tablespoon day 3) or mango (small portion escalating). Failure indicates fructose malabsorption.
- Sorbitol: Test with stone fruit (1/2 cup blackberries or 5 dried apricot halves). Failure indicates sorbitol intolerance and predicts trouble with sugar-free candies and gum.
- Mannitol: Test with mushroom (1/2 cup chopped) or cauliflower (1/4 cup). Failure typically co-occurs with sorbitol failure but not always.
- Fructans: Test with wheat (one slice of regular bread day 1, two slices day 2, three slices day 3) or garlic (1/4 clove day 1, 1/2 clove day 2, 1 clove day 3). Often the most consequential single trigger and the hardest to avoid in normal eating. Wheat fructans are often the actual driver of "gluten sensitivity" in non-celiac populations (Biesiekierski 2013 PMID 23648697 found that some self-identified gluten-sensitive patients respond to FODMAP restriction rather than to gluten elimination per se).
- Galacto-Oligosaccharides (GOS): Test with cashews (small handful day 1, larger day 2, larger day 3) or chickpeas. GOS intolerance is the legume trigger — the options commonly described are soaking or sprouting legumes thoroughly, alpha-galactosidase enzyme tablets taken before legume meals, or smaller portions.
Each sub-group challenge takes 3 days of escalating doses followed by 3-4 days of return to baseline restriction. The full reintroduction phase therefore takes approximately 6-10 weeks depending on response patterns.
An important interpretation guideline: a positive reaction means symptoms returned to or exceeded the patient's pre-restriction baseline. Mild fleeting bloating that resolves within a few hours is usually not a true positive. Significant abdominal pain, multiple loose stools, or symptoms that meaningfully impair daily function are true positives.
The Role of a Registered Dietitian
The Monash University position is unambiguous: Low FODMAP is meant to be done with the guidance of a FODMAP-trained dietitian whenever possible. The reasons are practical:
- Pre-restriction nutritional assessment — baseline calcium intake (likely to drop with dairy elimination), fiber intake (likely to drop with the elimination of high-FODMAP fiber sources), iron, B-vitamin status if grains are heavily restricted.
- Phase 1 supervision — avoiding the common error of under-eating from food anxiety, avoiding nutrient deficits, identifying hidden FODMAP sources in commercial products.
- Phase 2 challenge design — selecting appropriate test foods, escalating doses, and especially interpreting equivocal results.
- Phase 3 personalization — producing a personalized food list and re-challenge schedule.
- Recognition of when Low FODMAP is not the right intervention — many gastroenterologists run Low FODMAP as a default "let's try this" intervention even when the symptom pattern suggests small intestinal bacterial overgrowth, microscopic colitis, bile-acid malabsorption, or another condition for which Low FODMAP is not appropriate.
For patients without dietitian access, the developers' smartphone app (regularly updated, with the definitive food list) is the resource most often described. Free patient resources are also published by Monash University, a UK IBS patient charity, and the American College of Gastroenterology. Direct-to-consumer "FODMAP food list" handouts of unknown provenance often contain outdated or incorrect information — Monash periodically re-tests foods and reclassifies them as understanding improves.
Beyond Irritable Bowel Syndrome — Small Intestinal Bacterial Overgrowth, Inflammatory Bowel Disease, Endometriosis
Low FODMAP was developed for irritable bowel syndrome but has been studied in several related conditions:
- small intestinal bacterial overgrowth (SIBO) — symptom overlap with irritable bowel syndrome is substantial, and many small intestinal bacterial overgrowth patients improve symptomatically on Low FODMAP. However, the underlying small intestinal bacterial overgrowth is not treated by dietary restriction — rifaximin or herbal antimicrobials are usually still needed. See our small intestinal bacterial overgrowth page for the broader treatment framework.
- Inflammatory bowel disease (Crohn's, ulcerative colitis) — Low FODMAP can reduce functional symptoms in inflammatory bowel disease (IBD) patients in remission (the irritable bowel syndrome-overlap component), but does not treat the underlying inflammation. A growing body of evidence suggests it may be useful as adjunctive symptom management.
- Endometriosis — small studies have shown symptom benefit, though the mechanism (visceral hypersensitivity overlap, gut-pelvic interaction) is incompletely understood.
- Functional dyspepsia — some symptomatic overlap with irritable bowel syndrome, and Low FODMAP can help when symptoms include lower-abdominal bloating and altered bowel habit.
- Bile-acid malabsorption — not treated by Low FODMAP; the actual treatment is bile acid sequestrants (cholestyramine, colesevelam). This is an important differential because Low FODMAP non-response in diarrhea-predominant irritable bowel syndrome is a common reason clinicians consider bile-acid malabsorption.
Low FODMAP is not indicated for, and may worsen, the following: classical food allergies, celiac disease (the treatment is gluten avoidance, not FODMAP restriction), eosinophilic esophagitis, microscopic colitis, gastroparesis, and primary motility disorders.
Microbiome Concerns and the Over-Restriction Trap
The most legitimate criticism of Low FODMAP is its effect on the gut microbiome during the restriction phase. Several studies have shown:
- Reduction in total bacterial abundance during phase 1 restriction (Halmos 2015)
- Specific reduction in Bifidobacterium species (in Staudacher 2017, PMID 28625832, a multistrain probiotic given alongside the diet increased Bifidobacterium numbers compared with placebo; that trial found no effect of the diet on overall microbiota diversity)
- Reduction in butyrate-producing bacteria, with potential implications for colonocyte health
- Some evidence of partial recovery during the reintroduction and personalization phases
The microbiome concerns are the primary reason the Monash protocol explicitly limits phase 1 to 6 weeks maximum and emphasizes that the personalization phase — not the restriction phase — is the intended long-term state. Patients who remain on strict Low FODMAP for months or years are exposing themselves to potential microbiome and nutritional harm without continued benefit (since by definition they have already responded to the intervention).
The over-restriction trap is real and common. The pattern: patient improves dramatically on phase 1, becomes anxious about reintroducing any high-FODMAP food, never completes phase 2, remains on indefinite restriction. This pattern shares features with orthorexia and warrants attention. A dietitian-supported reintroduction is the usual safeguard described against this trap.
Practical Tools (Smartphone App, Certification Marks)
A widely used practical tool is a smartphone app from the university group that developed the diet, which is regularly updated. The app provides:
- A traffic-light system for every tested food (green = low FODMAP at standard serving, yellow = caution at larger serving, red = high FODMAP)
- Specific serving sizes that move a food from green to red (for example, almonds are green at 10 nuts and red at a handful)
- Sub-group identification (which specific FODMAP category each food contains)
- Recipe collections, food-diary tools, and grocery-list features
For packaged foods, low-FODMAP certification marks exist, including one from an independent Australian certifier and one from the university group that developed the diet. A certification mark on a packaged product means the product has been laboratory-tested and certified to fall under the Low FODMAP threshold at the stated serving size. In US grocery stores the marks matter most on broths, sauces, snack bars, and baking mixes — categories where hidden onion and garlic are pervasive.
Low FODMAP recipe sources include dietitian-written blogs and cookbooks, the recipe collection of the university group that developed the diet, and online low-FODMAP cooking communities.
Key Research Papers
- Halmos EP et al. (2014). A diet low in FODMAPs reduces symptoms of irritable bowel syndrome. Gastroenterology — PubMed PMID: 24076059
- Staudacher HM et al. (2014). Mechanisms and efficacy of dietary FODMAP restriction in IBS. Nature Reviews Gastroenterology & Hepatology — Search PubMed
- Eswaran SL et al. (2016). A Randomized Controlled Trial Comparing the Low FODMAP Diet vs Modified NICE Guidelines in US Adults With IBS-D. American Journal of Gastroenterology — PubMed PMID: 27725652
- Böhn L et al. (2015). Diet low in FODMAPs reduces symptoms of irritable bowel syndrome as well as traditional dietary advice: a randomized controlled trial. Gastroenterology — PubMed PMID: 26255043
- Marsh A, Eslick EM, Eslick GD (2016). Does a diet low in FODMAPs reduce symptoms associated with functional gastrointestinal disorders? A comprehensive systematic review and meta-analysis. European Journal of Nutrition — PubMed PMID: 25982757
- Schumann D et al. (2018). Low fermentable, oligo-, di-, mono-saccharides and polyol diet in the treatment of irritable bowel syndrome: a systematic review and meta-analysis. Nutrition — Search PubMed
- Staudacher HM et al. (2017). A Diet Low in FODMAPs Reduces Symptoms in Patients With Irritable Bowel Syndrome and a Probiotic Restores Bifidobacterium Species. Gastroenterology — PubMed PMID: 28625832
- Hill P, Muir JG, Gibson PR (2017). Controversies and Recent Developments of the Low-FODMAP Diet. Gastroenterology & Hepatology — PubMed PMID: 28420945
- Tuck CJ, Muir JG, Barrett JS, Gibson PR (2014). Fermentable oligosaccharides, disaccharides, monosaccharides and polyols: role in irritable bowel syndrome. Expert Review of Gastroenterology & Hepatology — Search PubMed
- Black CJ et al. (2022). Efficacy of a low FODMAP diet in irritable bowel syndrome: systematic review and network meta-analysis. Gut — PubMed PMID: 34376515
- Whelan K et al. (2018). The low FODMAP diet in the management of irritable bowel syndrome: an evidence-based review of FODMAP restriction, reintroduction and personalisation in clinical practice. Journal of Human Nutrition and Dietetics — PubMed PMID: 29336079
- Biesiekierski JR et al. (2013). No effects of gluten in patients with self-reported non-celiac gluten sensitivity after dietary reduction of fermentable, poorly absorbed, short-chain carbohydrates. Gastroenterology — PubMed PMID: 23648697