Anti-Inflammatory Diet: Omega-3 Rich Foods
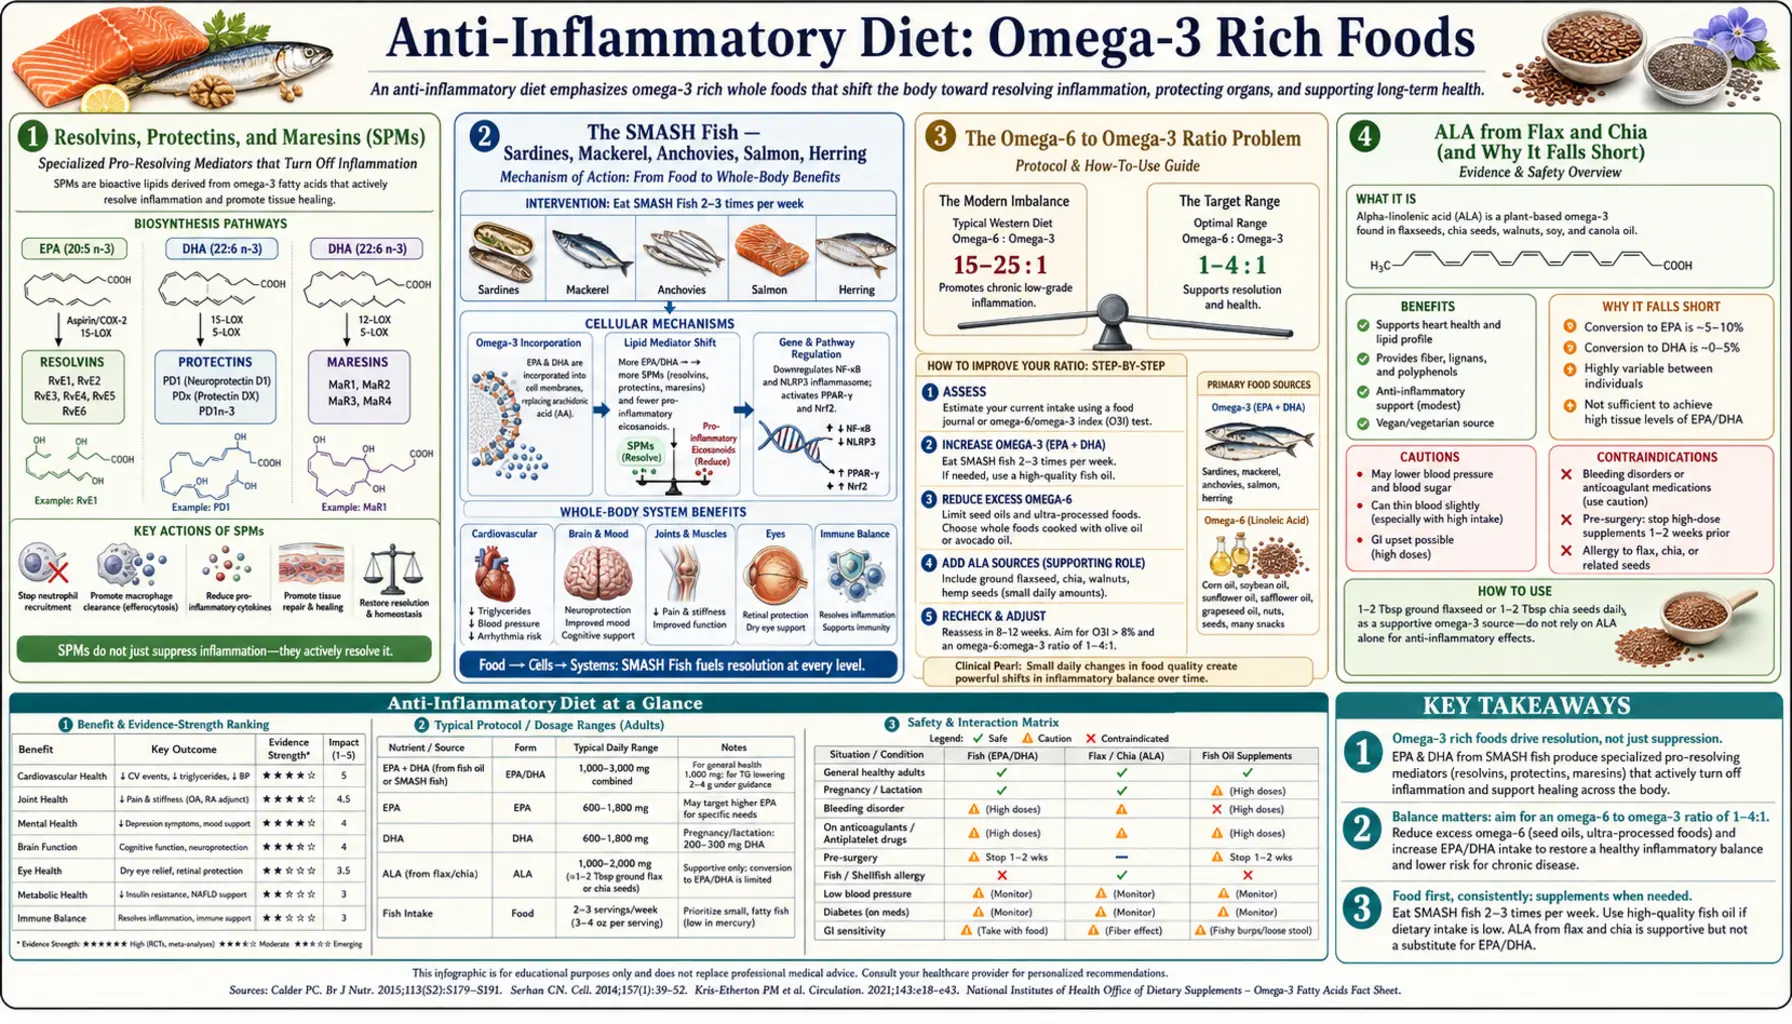
Marine omega-3 fatty acids (eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA)) are not just "heart-healthy fats" they are the substrate the body uses to build resolvins, protectins, and maresins, an entire family of specialized pro-resolving mediators (SPMs) that actively terminate inflammation. Charles Serhan's lab at Harvard discovered these molecules in 2000–2007 and demonstrated they are the missing link between dietary fat composition and the body's ability to switch off an inflammatory episode cleanly. Without sufficient eicosapentaenoic acid and docosahexaenoic acid in cell membranes, inflammation persists in a smoldering, unresolved state — the cellular signature of nearly every chronic disease. This deep-dive covers the SMASH fish, the omega-6 to omega-3 ratio problem, why plant alpha-linolenic acid (ALA) from flax and chia is a poor substitute for marine eicosapentaenoic acid/docosahexaenoic acid, the REDUCE-IT trial of pharmaceutical-grade eicosapentaenoic acid, and a sample weekly plan aimed at 2 g per day of combined eicosapentaenoic acid + docosahexaenoic acid.
Table of Contents
- Resolvins, Protectins, and Maresins (SPMs)
- The SMASH Fish — Sardines, Mackerel, Anchovies, Salmon, Herring
- The Omega-6 to Omega-3 Ratio Problem
- Alpha-Linolenic Acid from Flax and Chia (and Why It Falls Short)
- REDUCE-IT and the Case for Pharmaceutical Eicosapentaenoic Acid
- Fish Oil, Krill Oil, and Algal Docosahexaenoic Acid
- Mercury, Sustainability, and Practical Sourcing
- A Sample Week Aimed at 2 g Eicosapentaenoic Acid+Docosahexaenoic Acid per Day
- Key Research Papers
- Connections
- Featured Videos
Resolvins, Protectins, and Maresins (SPMs)
For most of the 20th century, inflammation was thought to resolve passively — pro-inflammatory mediators simply got diluted, broken down, or cleared, and the tissue returned to baseline. The discovery of specialized pro-resolving mediators (SPMs) by Charles Serhan and colleagues at Harvard, in a series of papers from 2000 to 2007, overturned that view. Resolution of inflammation is an active, enzymatically-driven program. Its substrates are eicosapentaenoic acid and docosahexaenoic acid.
The three SPM families are: (1) Resolvins — E-series resolvins (RvE1, RvE2, RvE3) derived from eicosapentaenoic acid, and D-series resolvins (RvD1 through RvD6) derived from docosahexaenoic acid. They suppress neutrophil infiltration, promote macrophage clearance of apoptotic cells (efferocytosis), and stimulate antimicrobial defense without escalating inflammation. (2) Protectins — protectin D1 (PD1, also called neuroprotectin D1 in the central nervous system, CNS) derived from docosahexaenoic acid. It protects neurons from oxidative stress and is reduced in Alzheimer's brain tissue. (3) Maresins — macrophage-derived from docosahexaenoic acid, MaR1 and MaR2. They drive the macrophage phenotype switch from pro-inflammatory M1 to pro-resolving M2.
The clinical implication: without dietary eicosapentaenoic acid and docosahexaenoic acid, the body cannot synthesize SPMs in adequate amounts, and inflammation does not resolve cleanly. The result is the smoldering, low-grade inflammation that drives atherosclerosis, insulin resistance, neurodegeneration, and the inflammatory tone of autoimmune disease. Restoring eicosapentaenoic acid/docosahexaenoic acid intake within 6–12 weeks measurably increases circulating SPM levels and reduces the persistence of inflammatory episodes.
The SMASH Fish — Sardines, Mackerel, Anchovies, Salmon, Herring
The mnemonic SMASH covers the five categories of fatty cold-water fish with the highest eicosapentaenoic acid + docosahexaenoic acid per serving and the lowest mercury and microplastic contamination (because they are small, short-lived, and feed low on the food chain). Figures below are from USDA FoodData Central, per 100 g unless a serving is named:
- Sardines (Atlantic, canned in oil, drained, with bone): ~980 mg eicosapentaenoic acid + docosahexaenoic acid (USDA: 473 mg eicosapentaenoic acid + 509 mg docosahexaenoic acid). Bone-in, skin-on; also delivers calcium, vitamin D, vitamin K2, selenium, B12. The FDA and EPA list sardines among the "Best Choices" (lowest mercury).
- Mackerel (Atlantic, cooked): ~1,200 mg eicosapentaenoic acid + docosahexaenoic acid (USDA: 504 mg eicosapentaenoic acid + 699 mg docosahexaenoic acid). In the FDA and EPA fish advice, Atlantic and Pacific chub mackerel are "Best Choices," Spanish mackerel is a "Good Choice" (one serving a week), and king mackerel is a "Choice to Avoid" (highest mercury levels).
- Anchovies (canned in oil, drained): ~1,030 mg per 50 g serving (USDA: about 2,050 mg per 100 g). Excellent flavor enhancer for sauces, dressings, and pasta.
- Salmon (wild Pacific or Atlantic farmed): ~860 mg (wild sockeye, cooked) to ~2,150 mg (farmed Atlantic, cooked) per 100 g. Wild Pacific (sockeye, coho, pink) is leaner and has less omega-3 by weight than farmed Atlantic, but with a more favorable omega-6 to omega-3 ratio; salmon is an FDA and EPA "Best Choice" (lowest mercury).
- Herring (pickled or cooked): ~1,390 mg (pickled) to ~2,010 mg (Atlantic, cooked) per 100 g. A Scandinavian and central European staple.
Two servings per week of SMASH fish (~200 g cooked weight) supplies roughly 1.7–4.3 g of eicosapentaenoic acid + docosahexaenoic acid per week by the USDA figures above, or about 250–600 mg per day averaged, around the ~500 mg per day floor recommendation from the American Heart Association for cardiovascular prevention. The 2 g per day this page's plan aims at, and the REDUCE-IT pharmaceutical dose (4 g/day), are more than fish meals alone supply: the sample week below, with four fish meals and a daily supplement, reaches about 1.4–1.6 g per day.
The Omega-6 to Omega-3 Ratio Problem
Ancestral human diets had an omega-6 to omega-3 ratio of roughly 1:1 to 4:1. Modern American and Western European diets typically run 15:1 to 25:1, dominated by linoleic acid from soybean, corn, sunflower, safflower, and cottonseed oils. The Simopoulos hypothesis (Artemis Simopoulos, Center for Genetics, Nutrition and Health) is that this dramatic ratio shift is the single largest dietary change underlying the rise in chronic inflammatory diseases since 1960.
The mechanism is competitive: omega-6 arachidonic acid and omega-3 eicosapentaenoic acid both compete for the same delta-5 and delta-6 desaturase enzymes, the same COX and LOX enzymes, and the same membrane phospholipid incorporation sites. When dietary linoleic acid swamps the system, arachidonic acid wins the competition, producing pro-inflammatory 2-series prostaglandins (PGE2), 4-series leukotrienes (LTB4), and pro-aggregatory thromboxane A2. When eicosapentaenoic acid wins, the system shifts to 3-series prostaglandins, 5-series leukotrienes (10 to 100 times less inflammatory), and the SPM family.
The ratio can be moved from two directions: (1) less omega-6, as when extra-virgin olive oil replaces seed oils for cooking and dressings (see the foods to avoid page); and (2) more omega-3, from SMASH fish 2–4 times per week and fish, krill, or algal oil. Either lever moves the ratio toward 4:1; both levers together can reach 2:1 within 6 months.
Alpha-Linolenic Acid from Flax and Chia (and Why It Falls Short)
Plant omega-3 comes as alpha-linolenic acid (ALA, 18:3 n-3) from flaxseed, chia, walnuts, hemp, and some leafy greens. The body can elongate and desaturate alpha-linolenic acid to eicosapentaenoic acid and then to docosahexaenoic acid — but the conversion is poor and highly variable. A 2002 review by Brenna reported that studies generally agree whole-body conversion of alpha-linolenic acid to docosahexaenoic acid is below 5% in humans and depends on how much omega-6 is in the diet. In a tracer study of young women given labelled alpha-linolenic acid, Burdge and Wootton (2002) estimated net conversion of about 21% to eicosapentaenoic acid, 6% to docosapentaenoic acid and 9% to docosahexaenoic acid, and noted that women may convert more than men. Women generally convert more efficiently than men because estrogen upregulates the delta-6 desaturase, but even at the upper end, dietary alpha-linolenic acid cannot reliably substitute for direct marine eicosapentaenoic acid and docosahexaenoic acid.
The bottleneck is the elongase and desaturase enzymes (FADS1, FADS2, ELOVL5), which are saturable, competitive with omega-6 substrates, and modulated by polymorphisms.
This does not mean flax, chia, hemp, and walnuts are useless — they deliver fiber, lignans, magnesium, and a baseline of alpha-linolenic acid that contributes to overall omega-3 status. But strict vegetarians and vegans cannot rely on alpha-linolenic acid alone for adequate eicosapentaenoic acid and docosahexaenoic acid; algal oil (which provides direct docosahexaenoic acid and a small amount of eicosapentaenoic acid) supplies the marine-type omega-3s without fish. A commonly described plant-based combination is two tablespoons of ground flaxseed daily plus an algal docosahexaenoic acid capsule (typically 300–500 mg docosahexaenoic acid).
REDUCE-IT and the Case for Pharmaceutical Eicosapentaenoic Acid
The Reduction of Cardiovascular Events with Icosapent Ethyl Intervention Trial (REDUCE-IT, Bhatt et al. NEJM 2019) enrolled 8,179 statin-treated patients with elevated triglycerides (135–499 mg/dL) and high cardiovascular risk. They were randomized to 4 g per day of icosapent ethyl (a purified ethyl ester of eicosapentaenoic acid only, no docosahexaenoic acid) or mineral oil placebo, with a median follow-up of 4.9 years. The primary endpoint was a composite of cardiovascular death, nonfatal myocardial infarction (MI), nonfatal stroke, coronary revascularization, or unstable angina.
The result was a 25% relative risk reduction in the primary endpoint (17.2% vs 22.0%, p<0.001) and a 20% reduction in cardiovascular death. The benefit emerged early (visible by 1 year) and persisted throughout follow-up. It was independent of low-density lipoprotein (LDL) lowering and only partly explained by triglyceride reduction — suggesting a direct anti-inflammatory and plaque-stabilizing effect of eicosapentaenoic acid at the 4 g/day dose.
The clinical interpretation has been controversial because the mineral oil placebo may have raised high-sensitivity C-reactive protein (hs-CRP) and low-density lipoprotein in the control arm, exaggerating the apparent benefit. The subsequent STRENGTH trial (Nicholls et al. JAMA 2020), which tested a combined eicosapentaenoic acid + docosahexaenoic acid preparation against a corn oil placebo, did not show benefit: among 13,078 statin-treated patients given the same 4 g/day dose, the primary endpoint occurred in 12.0% vs 12.2% (hazard ratio 0.99), and the trial was stopped early because benefit was unlikely. Its dose matched REDUCE-IT; its formulation (a carboxylic acid form of eicosapentaenoic acid plus docosahexaenoic acid) and patient population (high triglycerides with low HDL cholesterol) differed. Of these two trials, the positive result is REDUCE-IT's, in statin-treated patients with residual triglyceride elevation and high cardiovascular risk taking prescription icosapent ethyl at 4 g/day. Anti-inflammatory diet plans typically aim lower, at 1–2 g/day of combined eicosapentaenoic acid + docosahexaenoic acid from food plus a modest supplement.
REDUCE-IT also reported side effects: more patients on icosapent ethyl were hospitalized for atrial fibrillation or flutter (an irregular heart rhythm) (3.1% vs 2.1%), and serious bleeding was 2.7% vs 2.1% (P=0.06, not statistically significant). Its key secondary endpoint (cardiovascular death, nonfatal heart attack or nonfatal stroke) fell from 14.8% to 11.2%.
The heart-rhythm finding is not limited to one trial. A 2021 pooled analysis of 7 large cardiovascular trials (81,210 people, average follow-up 4.9 years) found 25% more atrial fibrillation with marine omega-3 supplements (hazard ratio 1.25, 95% CI 1.07-1.46), 49% more in trials using more than 1 g/day (hazard ratio 1.49) against 12% more in trials using 1 g/day or less (hazard ratio 1.12), and about 11% more risk for each additional gram per day (Gencer et al., 2021).
Fish Oil, Krill Oil, and Algal Docosahexaenoic Acid
For supplementation beyond dietary fish, the three principal options are:
- Standard fish oil (triglyceride or ethyl ester form): the most studied and lowest-cost option. Third-party certification programs test fish oil for purity (mercury, PCBs, oxidation). Typical concentration is 30% eicosapentaenoic acid + docosahexaenoic acid in a 1000 mg softgel, so a 2 g/day target requires 6–7 softgels; concentrated formulations (60–80%) reduce that to 2–3 softgels.
- Krill oil: phospholipid-bound eicosapentaenoic acid and docosahexaenoic acid from Antarctic krill, plus astaxanthin (a potent carotenoid antioxidant). The phospholipid form may have modestly better absorption per mg of eicosapentaenoic acid/docosahexaenoic acid than triglyceride fish oil, though head-to-head trials are mixed. More expensive and lower total eicosapentaenoic acid+docosahexaenoic acid per capsule.
- Algal docosahexaenoic acid (and eicosapentaenoic acid): derived directly from microalgae (Schizochytrium), the same source from which the fish originally acquired their omega-3s. Provides 300–500 mg docosahexaenoic acid per capsule (some formulations now add eicosapentaenoic acid). Vegan, no fishy taste, no ocean-contaminant exposure. It is the source of preformed docosahexaenoic acid used by plant-based eaters.
Oxidation is a real concern with fish oil — rancid product produces lipid peroxides that are themselves pro-inflammatory. Oxidized fish oil typically smells strongly fishy or tastes burnt, and cold storage after opening slows oxidation. Some third-party certification programs test specifically for oxidation as well as contaminants.
Mercury, Sustainability, and Practical Sourcing
Mercury bioaccumulates up the food chain, so the largest predatory fish carry the highest body burdens. The U.S. Food and Drug Administration (FDA) and Environmental Protection Agency (EPA) advice about eating fish (written for pregnancy, breastfeeding and young children) sorts fish into three lists. "Choices to Avoid" (highest mercury levels): king mackerel, marlin, orange roughy, shark, swordfish, tilefish from the Gulf of Mexico, bigeye tuna. "Good Choices" (1 serving per week) include canned albacore (white) tuna, halibut, snapper, grouper and Spanish mackerel. "Best Choices" (2–3 servings per week) include canned light tuna, salmon, shrimp, sardines, mackerel (Atlantic/Pacific chub), anchovies, herring, trout, tilapia. For pregnancy and breastfeeding, the advice lists 2 to 3 servings a week from the Best Choices, or 1 serving from the Good Choices, with a serving of 4 ounces. For children it lists 2 servings a week from the Best Choices, with a serving of about 1 ounce at age 1–3, 2 ounces at 4–7, 3 ounces at 8–10 and 4 ounces from age 11.
Sustainability matters because overfishing of small forage fish (anchovies, sardines, herring) destabilizes the entire ocean food web. Independent seafood-rating programs provide species-by-species sustainability guidance. For North American consumers, the high-EPA, low-mercury, sustainable fish commonly listed are wild Alaskan sockeye salmon, Atlantic and Pacific sardines, Pacific anchovies, and small Atlantic herring.
A Sample Week Aimed at 2 g Eicosapentaenoic Acid+Docosahexaenoic Acid per Day
The target this sample week aims at is roughly 14 g of eicosapentaenoic acid + docosahexaenoic acid per week, or 2 g per day averaged. Amounts below are calculated from USDA FoodData Central values per 100 g:
- Monday: 1 can sardines (~120 g) on whole-grain toast for lunch — ~1,180 mg eicosapentaenoic acid+docosahexaenoic acid (982 mg per 100 g × 1.2)
- Wednesday: 150 g wild salmon for dinner — ~1,290 mg eicosapentaenoic acid+docosahexaenoic acid for sockeye (859 mg per 100 g cooked × 1.5) to ~2,760 mg for wild Atlantic (1,841 mg per 100 g cooked × 1.5)
- Friday: Anchovy-puttanesca pasta (50 g anchovies in sauce) — ~1,030 mg eicosapentaenoic acid+docosahexaenoic acid (2,053 mg per 100 g canned in oil × 0.5)
- Sunday: Mackerel pate or smoked mackerel salad (100 g) — ~1,200 mg eicosapentaenoic acid+docosahexaenoic acid (Atlantic mackerel, cooked: 1,203 mg per 100 g)
- Daily supplement: 2 softgels of concentrated fish oil (60%) providing ~700 mg eicosapentaenoic acid+docosahexaenoic acid per day, or 4 softgels of standard fish oil (30%) providing similar — ~4,900 mg per week
Total: the four fish meals supply about 4,700–6,200 mg (1,180 + 1,290–2,760 + 1,030 + 1,200), and with the supplement the week comes to roughly 9,600–11,100 mg eicosapentaenoic acid+docosahexaenoic acid, or ~1,370–1,580 mg per day — short of the 2 g per day target. Vegan equivalent: 1 algal docosahexaenoic acid+eicosapentaenoic acid capsule (~500 mg docosahexaenoic acid + 100 mg eicosapentaenoic acid) daily plus 2 tablespoons of ground flaxseed and 30 g walnuts daily. That is about 600 mg of eicosapentaenoic acid + docosahexaenoic acid a day from the capsule (4,200 mg a week), plus about 5.9 g of alpha-linolenic acid a day by USDA values — about 3.2 g from the flaxseed (22.8 g per 100 g; 7 g per tablespoon, ground) and about 2.7 g from the walnuts (9.08 g per 100 g) — most of which is not converted to eicosapentaenoic acid or docosahexaenoic acid (see above).
A blood test used to track omega-3 status is the Omega-3 Index (proposed by Harris and von Schacky in 2004; it measures eicosapentaenoic acid+docosahexaenoic acid as percent of total red blood cell fatty acids). The protective range is ≥8%; the deficient range (associated with sudden cardiac death and cognitive decline) is <4%. Most untreated Americans run at 4–6%; the plan above will typically raise the index to 8–12% within 4–6 months.
Key Research Papers
- Bhatt DL et al., Cardiovascular Risk Reduction with Icosapent Ethyl for Hypertriglyceridemia (REDUCE-IT, NEJM 2019;380:11-22) — PubMed PMID: 30415628
- Serhan CN, Pro-resolving lipid mediators are leads for resolution physiology (Nature 2014;510:92-101) — PubMed PMID: 24899309
- GISSI-Prevenzione Investigators, Dietary supplementation with n-3 polyunsaturated fatty acids after myocardial infarction (Lancet 1999) — PubMed PMID: 10465168
- Calder PC, Omega-3 fatty acids and inflammatory processes: from molecules to man. — PubMed PMID: 28900017
- Brenna JT, Efficiency of conversion of alpha-linolenic acid to long chain n-3 fatty acids in man (Curr Opin Clin Nutr Metab Care 2002;5:127-32) — PubMed PMID: 11844977
- Burdge GC, Wootton SA, Conversion of alpha-linolenic acid to eicosapentaenoic, docosapentaenoic and docosahexaenoic acids in young women (Br J Nutr 2002;88:411-20) — PubMed PMID: 12323090
- Nicholls SJ et al., Effect of High-Dose Omega-3 Fatty Acids vs Corn Oil on Major Adverse Cardiovascular Events (STRENGTH, JAMA 2020) — PubMed PMID: 33190147
- Gencer B, Djousse L, Al-Ramady OT, Cook NR, Manson JE, Albert CM, Effect of Long-Term Marine Omega-3 Fatty Acids Supplementation on the Risk of Atrial Fibrillation in Randomized Controlled Trials of Cardiovascular Outcomes: A Systematic Review and Meta-Analysis (Circulation 2021;144:1981-90) — PubMed PMID: 34612056
- Harris WS, Von Schacky C, The Omega-3 Index: a new risk factor for death from coronary heart disease? — PubMed PMID: 15208005
- Mozaffarian D, Rimm EB, Fish intake, contaminants, and human health: evaluating the risks and the benefits (JAMA 2006) — PubMed PMID: 17047219
- Simopoulos AP, The importance of the ratio of omega-6/omega-3 essential fatty acids. — PubMed PMID: 12442909
- Goldberg RJ, Katz J, A meta-analysis of the analgesic effects of omega-3 polyunsaturated fatty acid supplementation for inflammatory joint pain. — PubMed PMID: 17335973
- Liao Y et al., Efficacy of omega-3 PUFAs in depression: a meta-analysis (Transl Psychiatry 2019) — PubMed PMID: 31383846
- Burdge GC, Calder PC, Conversion of alpha-linolenic acid to longer-chain polyunsaturated fatty acids in human adults. — PubMed PMID: 16188209
PubMed Topic Searches
Connections
- All Remedies
- Diet and Rheumatoid Arthritis — the diet evidence in one autoimmune disease
- Omega-3 and Fish Oil for Rheumatoid Arthritis
- Benefits Hub
- Anti-Inflammatory Diet
- Mediterranean Foundations
- Spices and Herbs
- Foods to Avoid
- Salmon
- Sardines
- Herring
- Cod
- Fish Oil
- Cardiology
- Rheumatology