Anti-Inflammatory Diet: Mediterranean Foundations
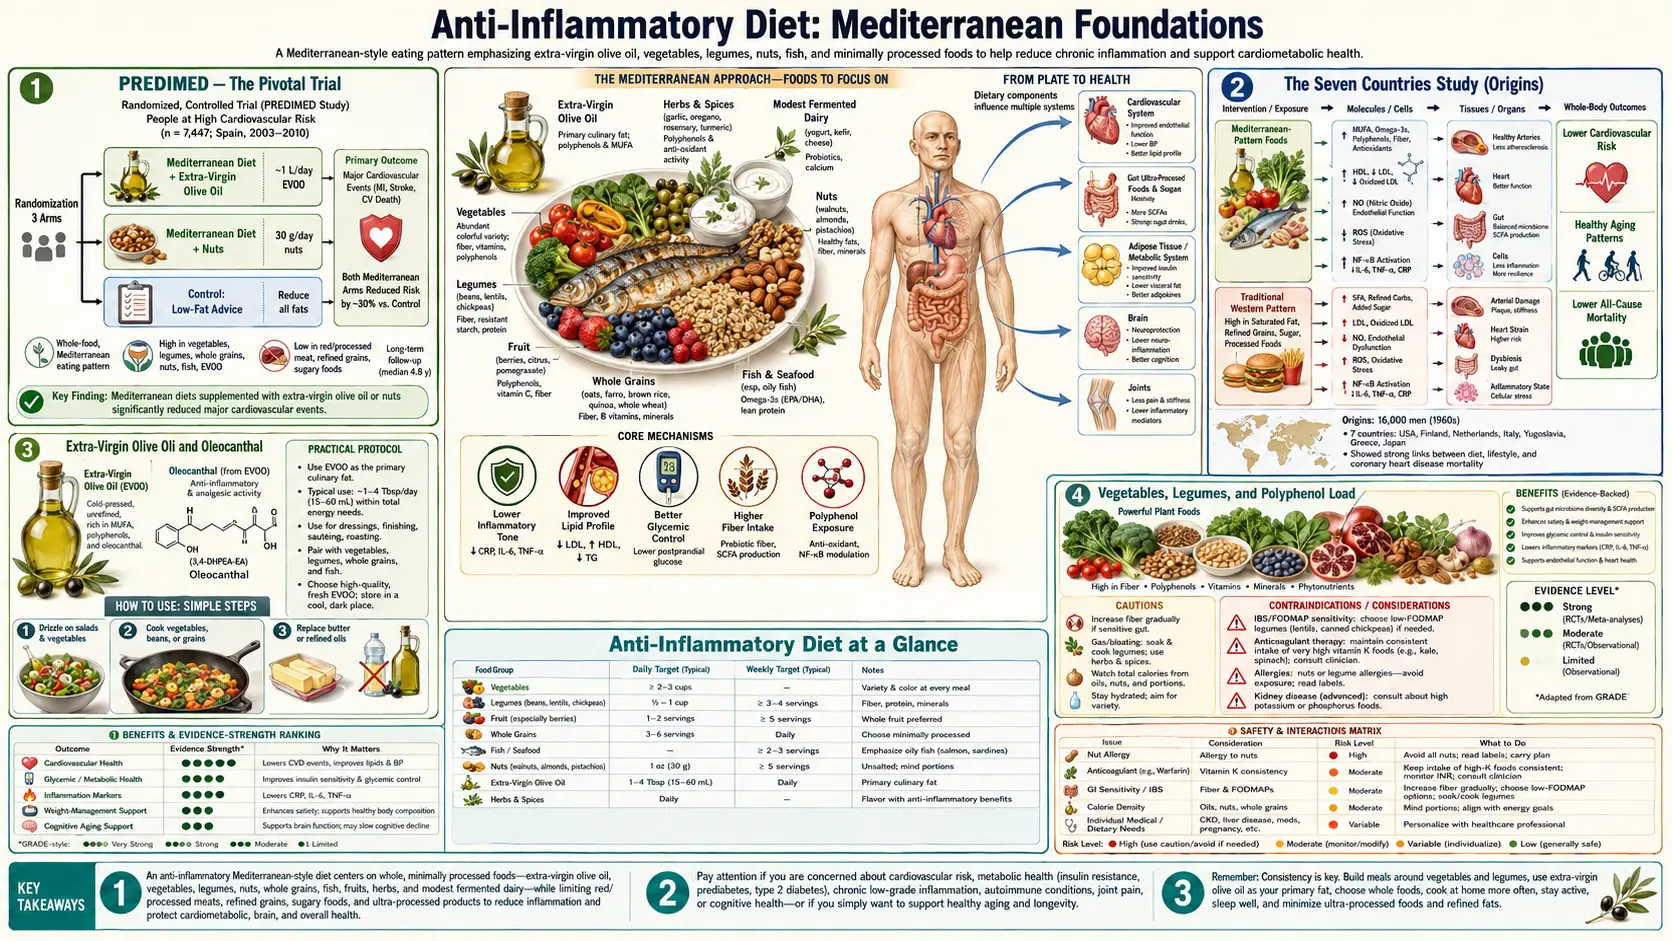
The Mediterranean diet is the most rigorously studied dietary pattern in human nutrition. It is the only eating pattern with a successfully completed, primary-prevention, hard-endpoint randomized controlled trial (PREDIMED) showing a roughly 30% reduction in major cardiovascular events versus a low-fat control diet. Its anti-inflammatory effect is not driven by any single hero ingredient — it is the cumulative result of extra-virgin olive oil as the principal fat source, a daily floor of vegetables and legumes, moderate fish and poultry, very limited red and processed meat, and red wine in moderation with meals. This page maps the seven foundational food categories of the Mediterranean pattern to the specific inflammatory pathways each modulates, then translates the science into a practical pantry and weekly meal blueprint.
Table of Contents
- PREDIMED — The Pivotal Trial
- The Seven Countries Study (Origins)
- Extra-Virgin Olive Oil and Oleocanthal
- Vegetables, Legumes, and Polyphenol Load
- Whole Grains, Nuts, and Seeds
- Fish and the Animal-Protein Hierarchy
- Red Wine in Moderation (and the Caveats)
- The Weekly Mediterranean Pantry and Plate
- Key Research Papers
- Connections
- Featured Videos
PREDIMED — The Pivotal Trial
The Prevención con Dieta Mediterránea (PREDIMED) trial enrolled 7,447 Spanish adults aged 55–80 at high cardiovascular risk (with type 2 diabetes or at least three risk factors) and randomized them to one of three diets: (1) a Mediterranean diet supplemented with about one liter per week of extra-virgin olive oil, (2) a Mediterranean diet supplemented with about 30 grams per day of mixed nuts (walnuts, almonds, hazelnuts), or (3) a low-fat control diet. Participants were followed for a median 4.8 years, and the primary endpoint was a composite of myocardial infarction, stroke, and cardiovascular death.
The trial was stopped on the basis of a prespecified interim analysis. The original 2013 report was withdrawn after the investigators found that some household members had been enrolled without randomization and that some participants at one of the 11 sites had been assigned without randomization. The 2018 reanalysis (Estruch et al. NEJM 2018) confirmed a relative risk reduction of approximately 30% for the primary composite endpoint in both Mediterranean diet arms versus the control diet (advice to reduce dietary fat): hazard ratio 0.69 with olive oil and 0.72 with nuts. In plain numbers, 3.8% of the olive-oil group, 3.4% of the nut group and 4.4% of the control group had a heart attack, stroke or cardiovascular death over a median 4.8 years. Critically, both Mediterranean arms achieved the benefit despite no significant weight loss compared with the control diet — demonstrating that the inflammatory and cardiovascular benefit comes from food composition, not calorie restriction.
A mechanistic substudy of PREDIMED (Casas and colleagues, 164 participants) documented reductions in high-sensitivity C-reactive protein, interleukin-6, soluble intercellular adhesion molecule 1 (sICAM-1) and P-selectin over 12 months compared with the low-fat diet, along with lower blood pressure and low-density lipoprotein (LDL) cholesterol. These markers all sit on the pathway from chronic inflammation to atherosclerotic plaque rupture, and their reduction is the most plausible mechanism for the observed event reduction.
Two later studies extend the picture. The CORDIOPREV trial (Lancet 2022, Córdoba, Spain) randomized 1,002 people who already had coronary heart disease to a Mediterranean diet or a low-fat diet for 7 years: 87 people on the Mediterranean diet and 111 on the low-fat diet had a major cardiovascular event (adjusted hazard ratios 0.72 to 0.75). The difference was clear in the 827 men but not in the 175 women. In the Women's Health Study, 25,315 initially healthy US women were followed for about 25 years; those with the highest Mediterranean-diet adherence had 23% lower all-cause mortality (hazard ratio 0.77). Inflammation markers explained about 13% of that link and small-molecule metabolites about 15%. That finding is observational.
The Seven Countries Study (Origins)
The Mediterranean diet entered scientific consciousness through Ancel Keys' Seven Countries Study, launched in 1958. Keys compared diet and coronary heart disease rates in 12,763 middle-aged men across Finland, the Netherlands, Italy, Greece (Crete and Corfu), Yugoslavia, the United States, and Japan. The Cretan cohort had the lowest 10-year and 25-year coronary mortality — far below Finland and the United States — despite a total fat intake of approximately 37% of calories. The fat composition, however, was dominated by extra-virgin olive oil (monounsaturated) and contained little saturated fat from meat or dairy.
The study also documented that the protective Cretan pattern depended on a complete food environment: daily vegetables and legumes, moderate fish and goat dairy, infrequent meat (often only on Sundays), wine with meals, and high physical activity from walking and farming. Subsequent decades of work (Trichopoulou's 2003 NEJM paper on the Mediterranean adherence score, then PREDIMED in 2013/2018) translated this observation into a quantifiable, reproducible dietary pattern. In Trichopoulou's study of 22,043 Greek adults, each 2-point rise on the 0–9 Mediterranean diet score went with 25% lower total mortality (hazard ratio 0.75) and 33% lower death from coronary heart disease (hazard ratio 0.67), while individual food groups on their own were generally not significantly linked to mortality — the pattern mattered, not any one food.
Extra-Virgin Olive Oil and Oleocanthal
Extra-virgin olive oil (EVOO) is the keystone fat of the Mediterranean pattern. PREDIMED used roughly one liter per week per household, or about 40–50 mL per person per day — far more than most Americans consume. The anti-inflammatory effect comes from three components: (1) approximately 73% oleic acid (monounsaturated 18:1), which is metabolically neutral or slightly anti-inflammatory; (2) approximately 200–500 mg/kg of polyphenols, dominated by hydroxytyrosol, tyrosol, and oleuropein, all potent free-radical scavengers and modulators of NF-kappaB; and (3) oleocanthal, a phenolic compound that produces the characteristic peppery throat-burn of high-quality EVOO.
The 2005 Nature paper by Beauchamp and colleagues demonstrated that oleocanthal is a natural, dose-dependent inhibitor of cyclooxygenase-1 and cyclooxygenase-2 — the same enzymes blocked by ibuprofen and aspirin. A typical 50 mL serving of robust EVOO contains roughly 9 mg of oleocanthal, equivalent in COX inhibition to about 10% of a single 200 mg ibuprofen dose. Cumulative daily exposure produces a small but durable shift in eicosanoid synthesis.
Label points that matter for quality: "extra-virgin" (a defined chemical standard, not a marketing term), a harvest date (polyphenols degrade over 12–18 months), a dark glass bottle (light degrades polyphenols), and the country of origin (single-country Italian, Greek, or Spanish oils are commonly regarded as better than multi-country blends). Cooking does not destroy the oleic acid (EVOO is stable to 405°F / 207°C), and high-polyphenol oils remain protective during typical sauteing.
Vegetables, Legumes, and Polyphenol Load
The Mediterranean pattern targets approximately 5–7 servings of vegetables per day plus 3–4 servings per week of legumes (chickpeas, lentils, white beans, fava beans). Three benefits operate in parallel:
- Soluble and insoluble fiber — legumes deliver 6–8 g of fiber per half-cup serving, half soluble. Soluble fiber is fermented by colonic bacteria into short-chain fatty acids (butyrate, propionate, acetate), which strengthen intestinal epithelial tight junctions, reduce lipopolysaccharide (LPS) translocation, and provide the principal energy source for colonocytes.
- Polyphenol diversity — deeply colored vegetables (red cabbage, beets, eggplant, dark leafy greens, tomatoes) and pulses each contribute distinct polyphenol classes (anthocyanins, flavonols, isoflavones, betalains). The diversity matters because each class modulates a different set of inflammatory targets; cumulative exposure across 20–30 plant species per week is the goal.
- Plant protein substitution — legumes replace some of the red meat protein in the diet without sacrificing satiety, reducing total saturated fat, heme iron load, and advanced glycation end product (AGE) exposure from high-temperature cooking.
The minimum effective dose to produce a measurable high-sensitivity C-reactive protein (hs-CRP) reduction in randomized trials is roughly 400 g (about 5 servings) of vegetables per day. Cooking method matters: steaming, sauteing in EVOO, and raw all preserve polyphenols; high-temperature deep-frying and prolonged boiling (especially of polyphenol-rich vegetables) lose 30–70% of phenolic content to the cooking water.
Whole Grains, Nuts, and Seeds
The PREDIMED nut arm provided 15 g of walnuts, 7.5 g of almonds, and 7.5 g of hazelnuts daily (~30 g total, roughly a handful). The nut arm achieved the same approximately 30% cardiovascular event reduction as the EVOO arm. The contributing components are (1) alpha-linolenic acid (the plant omega-3, particularly concentrated in walnuts at about 2.5 g per ounce), (2) magnesium and potassium, (3) plant sterols, (4) arginine (a nitric oxide precursor that improves endothelial function), and (5) polyphenol load from the skins.
Whole grains contribute fiber, magnesium, B vitamins, and lignans. The traditional Mediterranean staples are bulgur, farro, barley, oats, and stone-ground whole-wheat pasta — not refined white bread or white pasta. The shift from refined to whole grains lowers postprandial glucose excursions, reduces glycation pressure, and feeds the same fiber-fermenting colonic bacteria that legumes do. A 2016 BMJ meta-analysis (Aune and colleagues, 45 studies) found that each 90 g a day more whole grain — about three servings — went with lower risk of coronary heart disease (relative risk 0.81), cardiovascular disease (0.78) and death from all causes (0.83). The PURE study's own grain analysis (BMJ 2021, 137,130 people in 21 countries) found no significant association between whole grains and health outcomes; it was the highest refined-grain intake that went with higher total mortality and more cardiovascular events.
Seeds — flax, chia, hemp, sesame, sunflower — add additional alpha-linolenic acid (ALA), lignans, and minerals. Two tablespoons of ground flaxseed daily delivers about 3 g of alpha-linolenic acid plus the lignan secoisolariciresinol diglucoside (SDG), which is converted by gut bacteria to mammalian lignans with weak estrogenic and anti-inflammatory activity.
Fish and the Animal-Protein Hierarchy
The traditional Mediterranean diet places fish at the top of the animal-protein hierarchy (2–3 times per week), poultry in the middle (1–2 times per week), and red and processed meat at the bottom (no more than a few times per month). The fish recommendation specifically targets fatty cold-water species — sardines, anchovies, herring, mackerel, salmon — because these supply the marine omega-3s (eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA)) that drive the resolvin and protectin pathways covered on the omega-3 deep-dive page.
The case for restricting red and processed meat in an anti-inflammatory pattern rests on three observations: (1) the 2015 International Agency for Research on Cancer (IARC) Monograph 114 classified processed meat as Group 1 (carcinogenic to humans) for colorectal cancer and red meat as Group 2A (probably carcinogenic); (2) heme iron from red meat increases gut lipid peroxidation and circulating N-nitroso compounds; and (3) the Maillard browning that develops on charred, grilled, or pan-seared meat produces AGEs and heterocyclic amines that activate the receptor for advanced glycation end products (RAGE) and drive systemic inflammation.
For people who eat meat, the traditional Mediterranean pattern and the cooking research point the same way: (1) poultry and fish more often than beef and pork; (2) braised, stewed, or low-temperature dishes rather than grilled and charred ones; (3) marinades of acidic herb mixes (rosemary, lemon, vinegar), which reduce heterocyclic amine formation; and (4) a portion roughly the size of the palm of the hand, with the rest of the plate occupied by vegetables and legumes.
Red Wine in Moderation (and the Caveats)
The traditional Cretan diet included red wine with meals (typically 1–2 small glasses per day), and PREDIMED's Mediterranean diet score gave a half-point for moderate wine consumption. Red wine delivers resveratrol, anthocyanins, and proanthocyanidins that show anti-inflammatory and endothelial-protective effects in mechanistic studies.
The clinical caveat is significant. The 2018 Lancet Global Burden of Disease alcohol analysis found that the safest level of alcohol consumption for overall health is zero, once cancer (especially breast, head/neck, esophagus, colorectum), liver disease, and accidents are factored in. The cardiovascular benefit of light drinking does not offset the cancer risk in modern populations, and the J-shaped curve of earlier observational studies has been challenged by Mendelian randomization analyses showing dose-dependent harm at all levels.
Where this leaves wine: for people who already drink wine in moderation (1 glass per day for women, 1–2 for men) and have no personal or family history of breast cancer or alcohol use disorder, the Mediterranean pattern is compatible with that habit. The evidence does not support starting to drink for health. The same polyphenols and resveratrol are found, without the alcohol, in concord grape juice, berries, dark chocolate, and tea.
The Weekly Mediterranean Pantry and Plate
A week of Mediterranean-pattern food for one adult looks roughly like this:
- Olive oil: 250–350 mL of robust extra-virgin olive oil (single-origin, harvest date within 12 months).
- Vegetables: 2 kg total — tomatoes, cucumbers, peppers, onions, garlic, leafy greens, eggplant, zucchini, cruciferous (broccoli, cauliflower), one root vegetable.
- Legumes: 400 g dried (or 3–4 cans) of chickpeas, lentils, white beans, or fava beans.
- Whole grains: 500 g of bulgur, farro, oats, barley, or stone-ground whole-wheat pasta.
- Fruit: 1 kg mixed — citrus, berries, apples, melon, figs, pomegranate when in season.
- Nuts and seeds: 250 g mixed — walnuts, almonds, hazelnuts, pumpkin seeds, ground flaxseed.
- Fish: 400–600 g per week, mostly fatty cold-water species (canned sardines, frozen mackerel, fresh or frozen salmon).
- Poultry, eggs, dairy: 1–2 servings of chicken or turkey, 6–7 eggs, 200–400 g of yogurt or feta.
- Herbs and spices: rotating rosemary, oregano, thyme, basil, parsley, mint, turmeric, ginger, garlic, cinnamon, black pepper — see the spices page.
- Kept small or left out: red and processed meat, refined grains, sugar-sweetened beverages, ultra-processed snack foods, industrial seed oils — see the foods to avoid page.
The plate model: half the plate vegetables (cooked and raw), one quarter whole grains or legumes, one quarter protein (fish more often than poultry; legumes more often than meat), with extra-virgin olive oil drizzled liberally, herbs as the principal flavoring, and a piece of fruit for dessert. This pattern alone — without supplements, without calorie counting — reproduces the PREDIMED intervention.
Key Research Papers
- Estruch R et al., Primary Prevention of Cardiovascular Disease with a Mediterranean Diet Supplemented with Extra-Virgin Olive Oil or Nuts (NEJM 2018;378(25):e34, retracted-and-republished reanalysis of 2013) — PubMed PMID: 29897866
- Beauchamp GK et al., Phytochemistry: ibuprofen-like activity in extra-virgin olive oil (Nature 2005;437:45-46) — PubMed PMID: 16136122
- Trichopoulou A et al., Adherence to a Mediterranean diet and survival in a Greek population (NEJM 2003;348:2599-2608) — PubMed PMID: 12826634
- Salas-Salvadó J et al., Prevention of diabetes with Mediterranean diets: a subgroup analysis of a randomized trial (Ann Intern Med 2014;160(1):1-10) — PubMed PMID: 24573661
- Casas R et al., The effects of the Mediterranean diet on biomarkers of vascular wall inflammation and plaque vulnerability in subjects with high risk for cardiovascular disease. A randomized trial (PLoS One 2014;9(6):e100084) — PubMed PMID: 24925270
- Schwingshackl L, Hoffmann G, Mediterranean dietary pattern, inflammation and endothelial function: a systematic review and meta-analysis of intervention trials (Nutr Metab Cardiovasc Dis 2014;24(9):929-939) — PubMed PMID: 24787907
- Sofi F et al., Adherence to Mediterranean diet and health status: meta-analysis (BMJ 2008) — PubMed PMID: 18786971
- Dinu M et al., Mediterranean diet and multiple health outcomes: an umbrella review of meta-analyses. — PubMed PMID: 28488692
- Keys A et al., The diet and 15-year death rate in the seven countries study. — PubMed PMID: 3776973
- Scarmeas N et al., Mediterranean diet and risk for Alzheimer's disease (Ann Neurol 2006) — PubMed PMID: 16622828
- Toledo E et al., Mediterranean diet and invasive breast cancer risk among women at high cardiovascular risk in PREDIMED. — PubMed PMID: 26365989
- Rajaram S, Damasceno NRT, Braga RAM, et al., Effect of nuts on markers of inflammation and oxidative stress: a narrative review (Nutrients 2023;15(5):1099) — PubMed PMID: 36904099
- Aune D, Keum N, Giovannucci E, et al., Whole grain consumption and risk of cardiovascular disease, cancer, and all cause and cause specific mortality: systematic review and dose-response meta-analysis of prospective studies (BMJ 2016;353:i2716) — PubMed PMID: 27301975
- Swaminathan S, Dehghan M, Raj JM, et al., Associations of cereal grains intake with cardiovascular disease and mortality across 21 countries in Prospective Urban and Rural Epidemiology study: prospective cohort study (BMJ 2021;372:m4948) — PubMed PMID: 33536317
- Delgado-Lista J, Alcala-Diaz JF, Torres-Peña JD, et al., Long-term secondary prevention of cardiovascular disease with a Mediterranean diet and a low-fat diet (CORDIOPREV): a randomised controlled trial (Lancet 2022) — PubMed PMID: 35525255
- Ahmad S, Moorthy MV, Lee IM, et al., Mediterranean diet adherence and risk of all-cause mortality in women (JAMA Netw Open 2024;7(5):e2414322) — PubMed PMID: 38819819