Chiropractic Care
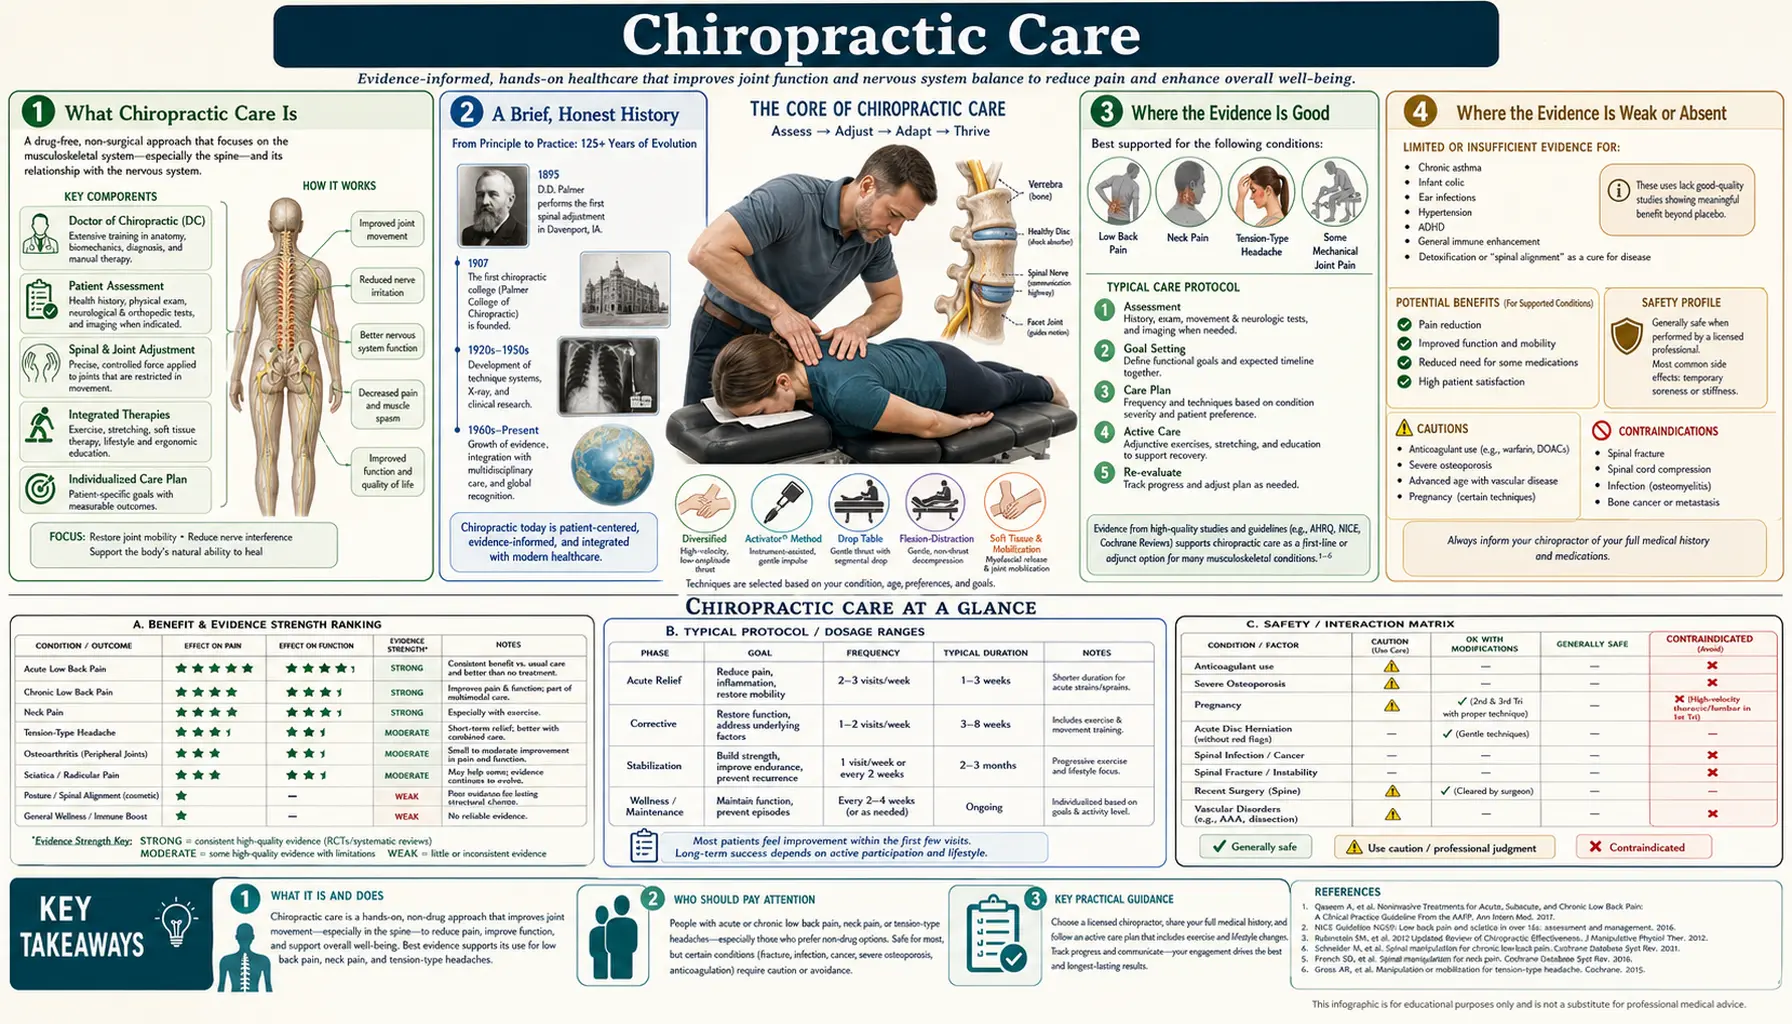
Chiropractic is a licensed health profession that focuses on the muscles, joints, and bones of the body — especially the spine. Its signature treatment is spinal manipulation, also called an adjustment: a quick, controlled push applied to a joint, often producing an audible pop. Many people find real relief from ordinary back and neck pain through chiropractic care, and for those complaints the research is genuinely supportive. But chiropractic also carries a century of controversy, because the idea it was founded on — that misaligned vertebrae cause disease throughout the body — has not held up to scientific testing. This page tries to be scrupulously fair: it separates what chiropractic does well from what it has overpromised, explains what an adjustment actually is and feels like, and is honest about safety, including the rare but serious risk tied to forceful neck manipulation. It also sets out where chiropractic fits and which warning signs point to a medical problem that manipulation does not treat.
Table of Contents
- What Chiropractic Care Is
- A Brief, Honest History
- Where the Evidence Is Good
- Where the Evidence Is Weak or Absent
- What an Adjustment Is & What to Expect
- Safety: Common, Rare, and Serious Risks
- Neck Manipulation and Stroke
- Who Benefits & the Medical Warning Signs
- How It Fits With Evidence-Based Care
- Signs of Evidence-Based Chiropractic Care
- The Honest Bottom Line
- Key Research Papers
- Connections
- Featured Videos
What Chiropractic Care Is
Chiropractic is a regulated healthcare profession centered on the musculoskeletal system — the network of muscles, ligaments, joints, and bones that lets you move — with a particular emphasis on the spine. In most countries a chiropractor must complete a multi-year doctoral program, pass board examinations, and hold a license to practice. The title "Doctor of Chiropractic" (DC) reflects that training, though it is not the same as a medical degree (MD or DO).
The core tool of the profession is spinal manipulative therapy (SMT). In an adjustment, the practitioner uses their hands or a small instrument to move a joint quickly through a short distance, usually to the end of its normal range. Chiropractors also use related techniques — slower joint mobilization, soft-tissue and muscle work, stretching, exercise instruction, and advice on posture and activity. In practice, good chiropractic care for back or neck pain looks a lot like other forms of conservative, hands-on physical care.
It helps to hold two ideas at once. As a set of manual techniques for mechanical back and neck problems, chiropractic is a mainstream, evidence-supported option. As a theory of disease — the historical claim that the spine is the gateway to overall health — it is not supported by evidence. Much of the confusion around chiropractic comes from mixing those two things together.
A Brief, Honest History
Chiropractic began in Davenport, Iowa, in 1895, when a magnetic healer named Daniel David (D.D.) Palmer reported restoring a janitor's hearing by adjusting his spine. From that single anecdote Palmer built an entire system. He proposed that a life force he called "Innate Intelligence" flowed through the nerves, that misaligned vertebrae — which he named vertebral subluxations — pinched those nerves and blocked the flow, and that correcting the subluxations by hand could cure disease throughout the body. His son B.J. Palmer turned the idea into a movement and a thriving school.
It is important to be clear-eyed about this origin. The subluxation theory was not derived from anatomy, physiology, or experiment; it was a metaphysical idea from the era before modern medicine. As the science of the nervous system and the spine advanced, the theory did not gain support — the "subluxations" Palmer described cannot be reliably found on imaging and do not correspond to a demonstrated cause of illness.
The profession has spent more than a century in tension over this legacy. Many modern chiropractors are essentially evidence-based spine and musculoskeletal clinicians who have largely set the old theory aside and practice much like physical therapists. A smaller group still centers care on detecting and correcting subluxations and promotes broad, whole-body health claims. When you evaluate a chiropractor, it is worth knowing which tradition they draw from — it strongly shapes what they will offer you and what they will claim.
Where the Evidence Is Good
Here is the genuinely good news, and it deserves to be stated plainly: for ordinary low-back pain and neck pain, spinal manipulation is a reasonable, evidence-supported treatment.
For acute (recent) low-back pain, a 2017 systematic review and meta-analysis in JAMA identified 26 randomized trials; pooling 15 of them for pain and 12 for function, it found that spinal manipulation was associated with modest improvements in pain and function at up to 6 weeks, although results varied widely between studies, and no trial reported a serious adverse event (Paige 2017). For chronic low-back pain, a large 2019 meta-analysis in The BMJ concluded that SMT gives short-term improvements in pain and function roughly comparable to other recommended therapies such as exercise (Rubinstein 2019). A 2012 Cochrane review of 20 trials in acute low-back pain was more cautious: it concluded that manipulation was no more effective than inert treatments, sham manipulation, or adding it to another treatment, and appeared no better than other recommended therapies (Rubinstein 2012).
For neck pain, a 2015 Cochrane review found support for thoracic (upper-back) manipulation compared with control for neck pain, function and quality of life, while results for manipulation and mobilization of the neck itself compared with control were few and varied (Gross 2015).
Crucially, this evidence has made its way into mainstream clinical guidelines. The American College of Physicians recommends starting with non-drug options for low-back pain — and lists spinal manipulation among the reasonable choices alongside exercise, heat, massage, and acupuncture (Qaseem 2017). A pragmatic trial in active-duty military members found that adding chiropractic care to usual medical care improved pain and disability more than usual care alone (Goertz 2018). In other words, for the right complaint, chiropractic is not fringe — it sits squarely within accepted conservative care.
Two honest caveats keep this in perspective. First, the benefits are typically modest and short-term, similar to other good conservative treatments rather than dramatically better than them. Second, mechanical back and neck pain often improves on its own within weeks, so some of what people credit to an adjustment is natural recovery. That does not make the treatment worthless — feeling better sooner and moving more comfortably is a real benefit — but it argues for realistic expectations.
Where the Evidence Is Weak or Absent
Now the other half of an honest account. Several long-standing chiropractic claims are not supported by evidence, and it is important to name them.
The subluxation theory itself. The founding idea — that tiny spinal misalignments block nerve flow and cause disease — has never been validated. The "subluxations" described by traditional chiropractic cannot be reliably identified, and there is no demonstrated mechanism by which correcting them would cure illness elsewhere in the body.
Treating non-musculoskeletal disease. The claim that spinal adjustments can treat conditions unrelated to the muscles and joints — such as asthma, ear infections, infant colic, allergies, high blood pressure, digestive disorders, bed-wetting, or immune problems — is not supported by good clinical trials. Where these conditions have been studied, manipulation has generally shown no meaningful benefit beyond placebo. This includes chiropractic offered as a treatment for a child's asthma, colic, or recurrent infections: a 2010 evidence report found manipulation no better than sham manipulation for infant colic and asthma in children, and the evidence inconclusive for ear infections and bed-wetting (Bronfort 2010).
"Maintenance" and lifelong adjustment schedules. There is little good evidence that frequent adjustments in people without symptoms prevent future problems or keep you healthy. A recommendation for open-ended, indefinite visits — especially bundled into a large prepaid package — has no such evidence behind it.
Routine full-spine X-rays. Repeated X-rays to hunt for subluxations expose you to radiation without changing the treatment for ordinary back or neck pain. Imaging has a real place — ruling out fracture, tumor, or infection when red-flag symptoms are present — but not as a routine screen on every visit.
None of this means a good chiropractor is a bad clinician. It means the specific promises matter. Care aimed at your aching back or stiff neck rests on solid ground; care sold as a cure for asthma or a lifetime health-maintenance program does not.
What an Adjustment Is & What to Expect
A spinal adjustment — clinicians call it a high-velocity, low-amplitude thrust — is a fast, small, targeted push applied to a joint, usually taking it just past its normal range of motion. The technique is quick and precise rather than forceful over a long distance.
The familiar popping sound is not a bone being "cracked" or a vertebra snapping back into place. It is cavitation: a small gas bubble forms and collapses in the fluid inside the joint as the pressure changes, much like the pop of a knuckle. The sound is harmless and, importantly, is not a measure of whether the treatment worked.
A typical first visit includes a history and physical examination, questions about how the pain started and what makes it better or worse, and screening for warning signs that call for medical work-up. A reasonable treatment course for a mechanical complaint is usually a defined number of visits over a few weeks, with a clear plan to reassess: if you are meaningfully better, care winds down; if you are not improving after a short trial, that is a signal to change course rather than to keep going indefinitely. Alongside adjustments, expect soft-tissue work, stretches, exercise advice, and guidance on posture and daily activity — the parts of care that help you stay better between visits.
Safety: Common, Rare, and Serious Risks
For most people receiving care for the low back, chiropractic is generally safe. A systematic review of chiropractic safety found that serious adverse events are rare and that the most common effects are mild and temporary (Gouveia 2009).
Common and minor. The most frequent side effect is short-lived soreness, stiffness, or a headache in the day or two after an adjustment — usually mild and self-resolving. In a randomized trial of 767 patients with neck or back pain, 51% of those who had at least three treatments reported at least one such event, most often muscle soreness, and the events were transient (Paanalahti 2014); large case series report minor short-lived effects 50% to 67% of the time (Paige 2017). This is expected and not a cause for alarm.
Uncommon but real. Forceful manipulation can occasionally aggravate an existing problem. In people with a herniated disc, severe osteoporosis, spinal instability, inflammatory arthritis affecting the spine, or bones weakened by cancer, aggressive manipulation can do harm and is generally not appropriate. A careful chiropractor screens for these before treating.
Rare and serious. The most serious concern is tied specifically to manipulation of the neck, and it deserves its own honest discussion below.
Reviews of adverse events emphasize two themes: serious harms are uncommon, but they are also under-reported, so the true rate is not known with precision (Ernst 2007). That uncertainty is a reason for careful screening and informed consent — not a reason to either dismiss the risk or to exaggerate it.
Neck Manipulation and Stroke
This is the part of chiropractic that requires the most care to describe accurately, because it is easy to either frighten people or to wave the concern away. Neither is fair. Here is what the evidence actually shows.
The concern is a rare event called cervical artery dissection — a small tear in the inner wall of one of the arteries that run up through the neck to the brain (most often the vertebral artery). A tear can lead to a clot and, in the worst case, a stroke. Warning signs can include a sudden, unusual, severe headache or neck pain, dizziness, double vision, slurred speech, or trouble with balance and coordination.
What is genuinely debated is cause versus coincidence. A large population-based study of 818 such strokes in Ontario found that, in people under 45, those who had the stroke were about three times more likely than people without it to have visited a chiropractor — or a primary-care doctor — beforehand; in older people, only the primary-care visits showed this link. The authors concluded that people with neck pain and headache from an artery that was already tearing were seeking care before the stroke, and found no excess risk with chiropractic care compared with primary care (Cassidy 2008). In that reading, the manipulation did not cause the dissection; the early dissection caused the symptom that led to the visit. A later study of over 1.1 million Medicare patients aged 66 to 99 with neck pain found stroke risk lower after a chiropractic visit than after a primary-care visit at 7 days and slightly higher at 30 days (hazard ratio 1.10); the authors judged these small differences probably not clinically significant (Whedon 2015).
At the same time, the risk cannot be dismissed. Case reviews document dissections and strokes that followed neck manipulation, and biologically it is plausible that a forceful rotational thrust could injure a vulnerable artery (Kranenburg 2017). The honest synthesis is this: a stroke caused by neck manipulation is very rare — estimates are on the order of roughly one per hundreds of thousands to millions of manipulations — its causal role is uncertain and debated, but it is real enough to warrant caution.
Points that follow from both the rarity and the seriousness: informed consent before neck manipulation includes a discussion of this risk; gentler mobilization and non-thrust techniques exist as alternatives to a high-velocity neck thrust; a sudden severe headache, neck pain, dizziness, or other nervous-system symptoms after a neck adjustment are warning signs of artery dissection and stroke that hospitals treat as an emergency; and an unusual new headache or neck pain that is present before care can itself be an early sign of a tearing artery (Cassidy 2008).
Who Benefits & the Medical Warning Signs
Who the evidence covers. The research above concerns uncomplicated mechanical low-back or neck pain — the everyday aches, stiffness, and strains that make up most spine complaints. Chiropractic is a hands-on, drug-free approach, and it fits into a plan built around movement and exercise.
Medical "red flags." These signs can point to a problem that hospitals treat as urgent, and that manipulation does not treat:
- New loss of bladder or bowel control, or numbness in the groin/saddle area (a possible medical emergency).
- Progressive weakness, numbness, or tingling in an arm or leg.
- Back or neck pain following a significant injury, fall, or car accident.
- Fever, unexplained weight loss, or a history of cancer along with new back pain.
- A sudden, severe, "worst-ever" headache or neck pain, or pain with dizziness, slurred speech, or vision changes.
- Known severe osteoporosis, spinal instability, or bones weakened by disease.
For children, and for non-musculoskeletal illnesses — asthma, infections, colic, allergies, digestive complaints — the research does not show that spinal manipulation treats the illness itself (Bronfort 2010). Chiropractic care is not a substitute for evaluating and treating disease.
How It Fits With Evidence-Based Care
The most useful way to think about chiropractic is as one tool within conservative musculoskeletal care — not a rival to medicine and not a complete health system on its own. For back and neck pain, the treatments with the best evidence overlap heavily: staying active, guided exercise, physical therapy, manual therapy (including manipulation and massage), heat, and time. Guidelines increasingly favor this whole toolkit over rushing to imaging, opioids, or surgery for ordinary spine pain (Qaseem 2017).
In that light, chiropractic and physical therapy are more complementary than competing. Both use hands-on techniques and exercise; the biggest predictor of a good outcome is often not which profession you choose but whether the clinician screens carefully, sets realistic goals, and gets you moving rather than keeping you dependent on passive treatment. A chiropractor who coordinates with your physician, welcomes exercise, and refers you onward when needed is practicing exactly the kind of integrated care the evidence supports.
The opposite framing is the one the evidence does not support: a practice that positions adjustments as an alternative to mainstream medicine, discourages standard care, or treats the spine as the master switch for all health. That is the part of chiropractic's history that the science left behind.
Signs of Evidence-Based Chiropractic Care
The research above points to several features that separate evidence-based care from overpromising:
- Claims that match the evidence. Care aimed at back or neck pain is well-founded. Promises to treat asthma, allergies, infections, or "boost immunity" through adjustments are not supported by the research.
- A real exam and a time-limited plan. A good first visit includes history-taking and screening for red flags, and a course of care with a point to reassess — not an open-ended commitment.
- No large prepaid packages. Dozens of prepaid "maintenance" visits for someone without symptoms are not a treatment supported by evidence.
- No routine repeat X-rays. Imaging answers a specific question (like ruling out fracture when red flags exist); it is not a screen for "subluxations" on every visit.
- A discussion before neck manipulation. Informed consent for neck manipulation covers its risks and the alternatives, such as gentler mobilization instead of a forceful thrust.
- Improvement over a short trial. When a short trial of care is not helping, evidence-based practice changes the plan or brings in a medical opinion rather than continuing indefinitely.
The Honest Bottom Line
Chiropractic care earns a genuinely mixed but fair verdict. For mechanical low-back and neck pain, spinal manipulation is a reasonable, evidence-supported part of conservative care — roughly as helpful as other good non-drug options, endorsed in mainstream guidelines, and generally safe. Many people are helped, and there is no need to be dismissive of that.
At the same time, the founding subluxation theory is not supported by evidence, and claims that adjustments treat asthma, infections, colic, allergies, or disease throughout the body are not supported by the research. The rare but serious risk associated with forceful neck manipulation is real enough to warrant caution and informed consent, even though its causal role is debated. And red-flag symptoms point to medical problems that manipulation does not treat.
Used for what it does well — and kept away from what it has overpromised — chiropractic is a legitimate, useful option for common back and neck pain. Its value depends on the specific problem and the specific claims made; for common back and neck pain it sits within a broader, evidence-based plan.
Key Research Papers
- Paige NM, Miake-Lye IM, Booth MS, et al. Association of spinal manipulative therapy with clinical benefit and harm for acute low back pain: systematic review and meta-analysis. JAMA. 2017;317(14):1451–1460. — 26 trials identified, 15 pooled for pain and 12 for function; SMT was associated with modest pain/function improvement for acute low-back pain at up to 6 weeks, with large heterogeneity between studies. — doi:10.1001/jama.2017.3086
- Rubinstein SM, de Zoete A, van Middelkoop M, et al. Benefits and harms of spinal manipulative therapy for the treatment of chronic low back pain: systematic review and meta-analysis of randomised controlled trials. BMJ. 2019;364:l689. — for chronic low-back pain, SMT produced short-term improvement similar to other recommended treatments such as exercise. — doi:10.1136/bmj.l689
- Rubinstein SM, Terwee CB, Assendelft WJJ, et al. Spinal manipulative therapy for acute low-back pain. Cochrane Database Syst Rev. 2012;(9):CD008880. — Cochrane review of 20 trials: for acute low-back pain SMT was no more effective than inert interventions, sham SMT, or when added to another intervention, and appeared no better than other recommended therapies. — doi:10.1002/14651858.CD008880.pub2
- Gross A, Langevin P, Burnie SJ, et al. Manipulation and mobilisation for neck pain contrasted against an inactive control or another active treatment. Cochrane Database Syst Rev. 2015;(9):CD004249. — support for thoracic manipulation versus control for neck pain, function and quality of life; results for cervical manipulation and mobilisation versus control were few and diverse. — doi:10.1002/14651858.CD004249.pub4
- Qaseem A, Wilt TJ, McLean RM, et al. Noninvasive treatments for acute, subacute, and chronic low back pain: a clinical practice guideline from the American College of Physicians. Ann Intern Med. 2017;166(7):514–530. — mainstream guideline listing spinal manipulation among reasonable non-drug options for low-back pain. — doi:10.7326/M16-2367
- Goertz CM, Long CR, Vining RD, et al. Effect of usual medical care plus chiropractic care vs usual medical care alone on pain and disability among US service members with low back pain: a comparative effectiveness clinical trial. JAMA Netw Open. 2018;1(1):e180105. — adding chiropractic care to usual care improved pain and disability more than usual care alone. — doi:10.1001/jamanetworkopen.2018.0105
- Bronfort G, Haas M, Evans R, et al. Effectiveness of manual therapies: the UK evidence report. Chiropr Osteopat. 2010;18:3. — broad review: manipulation helps spine-related pain but evidence is lacking for most non-musculoskeletal conditions. — doi:10.1186/1746-1340-18-3
- Gouveia LO, Castanho P, Ferreira JJ. Safety of chiropractic interventions: a systematic review. Spine (Phila Pa 1976). 2009;34(11):E405–E413. — serious adverse events are rare; most effects are mild and transient, but reporting is incomplete. — doi:10.1097/BRS.0b013e3181a16d63
- Ernst E. Adverse effects of spinal manipulation: a systematic review. J R Soc Med. 2007;100(7):330–338. — catalogs reported serious harms and stresses that under-reporting makes true risk hard to quantify. — doi:10.1177/014107680710000716
- Cassidy JD, Boyle E, Côté P, et al. Risk of vertebrobasilar stroke and chiropractic care: results of a population-based case-control and case-crossover study. Spine (Phila Pa 1976). 2008;33(4 Suppl):S176–S183. — 818 vertebrobasilar strokes; under age 45, cases were about three times more likely than controls to have seen a chiropractor or a primary-care doctor beforehand; the authors attributed this to early dissection prompting the visit and found no excess risk with chiropractic compared with primary care. — doi:10.1097/BRS.0b013e3181644600
- Whedon JM, Song Y, Mackenzie TA, et al. Risk of stroke after chiropractic spinal manipulation in Medicare B beneficiaries aged 66 to 99 years with neck pain. J Manipulative Physiol Ther. 2015;38(2):93–101. — 1,157,475 beneficiaries; stroke risk after chiropractic was lower at 7 days (hazard ratio 0.39) and slightly higher at 30 days (hazard ratio 1.10) than after primary-care visits; the authors judged the small differences probably not clinically significant. — doi:10.1016/j.jmpt.2014.12.001
- Kranenburg HA, Schmitt MA, Puentedura EJ, et al. Adverse events associated with the use of cervical spine manipulation or mobilization and patient characteristics: a systematic review. Musculoskelet Sci Pract. 2017;28:32–38. — reviews reported cervical-manipulation adverse events, including artery dissection, and the difficulty of predicting who is at risk. — doi:10.1016/j.msksp.2017.01.008
- Paanalahti K, Holm LW, Nordin M, Asker M, Lyander J, Skillgate E. Adverse events after manual therapy among patients seeking care for neck and/or back pain: a randomized controlled trial. BMC Musculoskelet Disord. 2014;15:77. — 767 patients; 51% of those receiving at least three treatments had at least one adverse event, most often muscle soreness; adverse events were common and transient. — PubMed PMID: 24618345
Connections
- All Remedies
- Acupuncture
- Massage Therapy
- Exercise
- Low Back Pain
- Sciatica
- Herniated Disc
- Osteoarthritis
- Stroke
- Migraine
- Orthopedics
- Neurology
- Covered in depth on its own page: Neck Pain