Iron and Athletic Performance
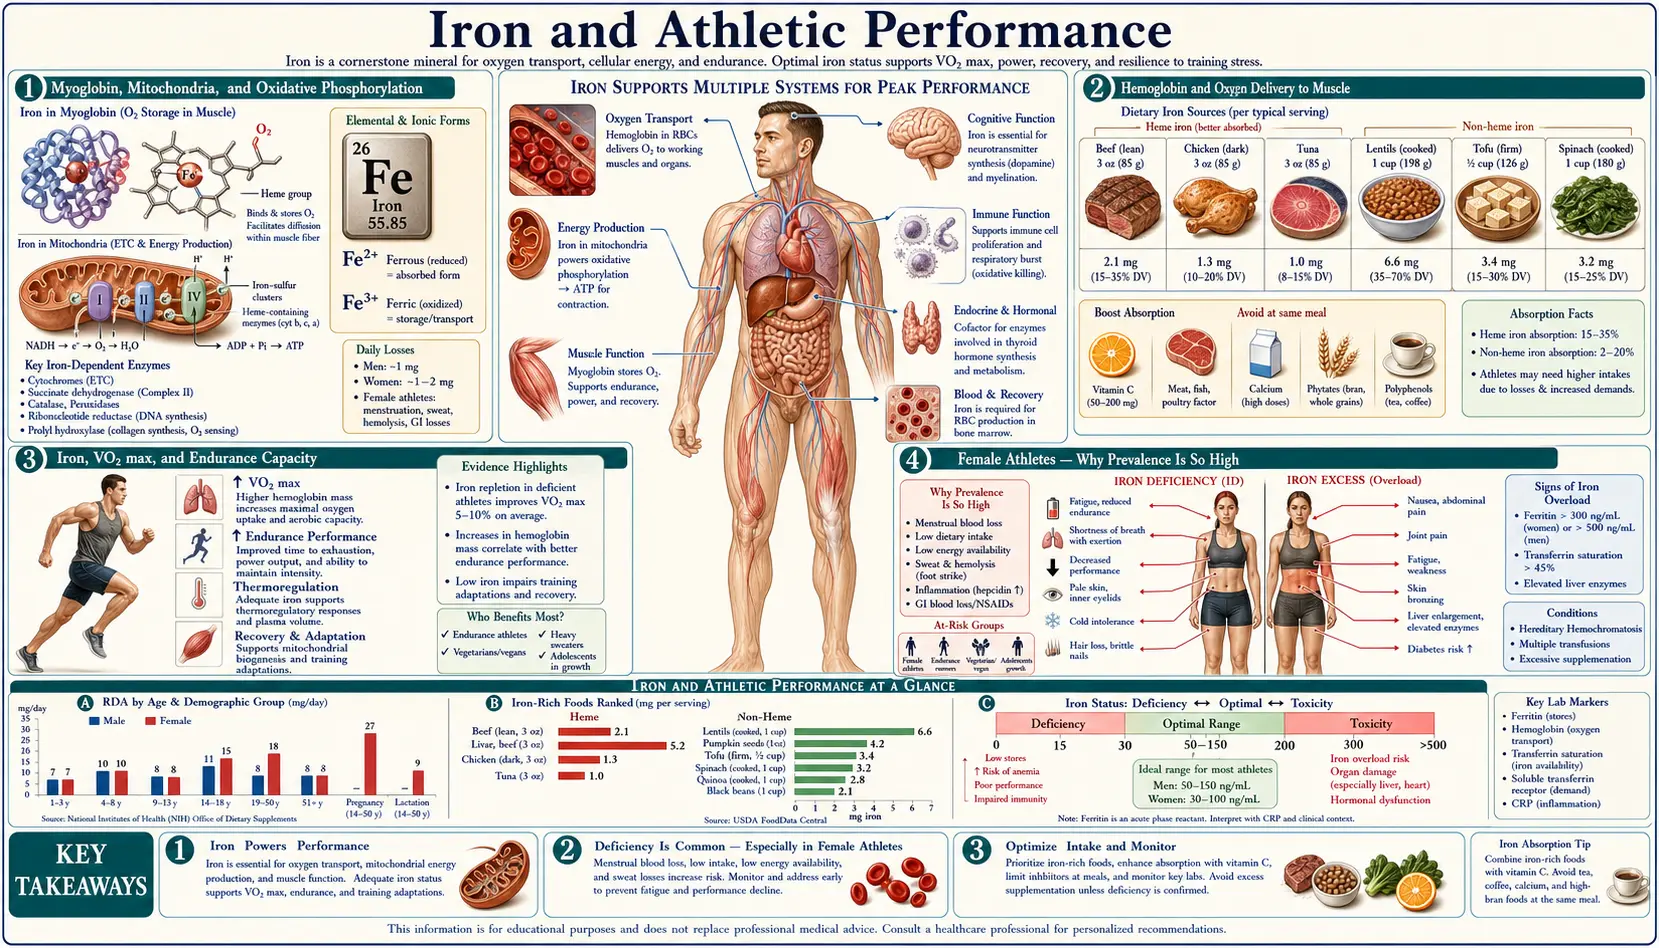
Iron is the single nutrient with the largest documented impact on endurance athletic performance. Hemoglobin carries oxygen from lung to muscle, myoglobin buffers oxygen within the working muscle, and the iron-sulfur clusters and heme cytochromes of the mitochondrial electron transport chain extract energy from that oxygen. Iron deficiency at any of these levels reduces VO2max, time to exhaustion, and submaximal endurance performance — effects that appear at the iron-deficient-erythropoiesis stage, before hemoglobin drops below the WHO anemia cutoff. Female endurance athletes are the highest-risk group, with iron-deficiency prevalence estimates of 20-50% in collegiate distance runners, rowers, and triathletes. Randomized trials from J. D. Haas's group at Cornell University found greater VO2max and time-trial gains with training when non-anemic iron-depleted women took iron, and the work of Peeling, Sim and colleagues on the hepcidin-IL-6 axis describes why endurance exercise itself transiently suppresses iron absorption in the post-exercise window. This deep-dive maps the molecular biology onto what the training and supplementation research describes.
Table of Contents
- Myoglobin, Mitochondria, and Oxidative Phosphorylation
- Hemoglobin and Oxygen Delivery to Muscle
- Iron, VO2max, and Endurance Capacity
- Female Athletes — Why Prevalence Is So High
- Iron-Repletion Trials in Iron-Depleted Women
- The Hepcidin-IL-6 Inflammatory Feedback in Exercise
- "Training-Induced Anemia" vs True Iron Deficiency
- Foot-Strike Hemolysis and Gastrointestinal Losses
- Screening, Targets, and Practical Supplementation
- Cautions (Overload, Doping Rules, Hemochromatosis)
- Key Research Papers
- Connections
- Featured Videos
Myoglobin, Mitochondria, and Oxidative Phosphorylation
Skeletal and cardiac muscle contain approximately 10% of the body's total iron, the majority of which is locked inside myoglobin and the mitochondrial electron transport chain. Myoglobin is the muscle-specific cousin of hemoglobin, a monomeric heme protein with a higher oxygen affinity than hemoglobin, which gives it the role of a local oxygen buffer — it accepts oxygen from hemoglobin in the muscle capillary bed and releases it intracellularly to the mitochondria as oxygen demand spikes during contraction. Muscle fibers with high oxidative capacity (slow-twitch type I, fast-twitch oxidative type IIa) have high myoglobin content, which is why those fibers appear red and dark. The fast-twitch glycolytic type IIb fibers have low myoglobin and appear pale.
The mitochondrial electron transport chain depends on iron at two distinct levels. Heme-containing cytochromes (b, c1, c, a, and a3) shuttle single electrons between Complexes III and IV, with Complex IV (cytochrome c oxidase) catalyzing the final four-electron reduction of O2 to water. Iron-sulfur clusters in Complexes I, II, and III also carry electrons one at a time as the gradient is built up across the inner mitochondrial membrane. Aconitase, the citric acid cycle enzyme that interconverts citrate and isocitrate, requires a [4Fe-4S] cluster for catalysis.
The practical consequence: iron deficiency degrades muscle oxidative capacity at the enzymatic level before hemoglobin drops. Skeletal muscle biopsies in iron-deficient rats show reduced cytochrome c oxidase activity, reduced adenosine triphosphate (ATP) production, and reduced endurance time on treadmill running — all of which can be partially restored within days of starting iron repletion, before hemoglobin or hematocrit normalize. This separation between "central" (hemoglobin-mediated oxygen delivery) and "peripheral" (mitochondrial-mediated oxygen utilization) iron effects is why iron-deficient-but-non-anemic athletes can still see meaningful performance gains from iron repletion.
Hemoglobin and Oxygen Delivery to Muscle
Approximately two-thirds of total body iron resides in circulating hemoglobin, which carries oxygen from the alveolar capillaries to working tissues. The maximum rate of aerobic energy production is directly limited by the rate at which oxygen can be delivered to the mitochondria, and this delivery is the product of cardiac output, hemoglobin concentration, and arterial oxygen saturation (the Fick principle: VO2 = cardiac output × arteriovenous oxygen difference).
Each gram of hemoglobin can carry approximately 1.34 mL of oxygen when fully saturated. An adult male with 15 g/dL hemoglobin and 5 L of blood thus has a total circulating oxygen-carrying capacity of about 1 L; an iron-deficient woman with 11 g/dL hemoglobin and 4 L of blood has about 590 mL. The difference is a roughly 40% reduction in maximal oxygen-carrying capacity — equivalent in performance terms to losing roughly the oxygen advantage that altitude-acclimated elite distance runners spend years to acquire. The system partially compensates with higher cardiac output (resting tachycardia and exercise tachycardia), but this compensation has limits and itself has metabolic costs (the heart is using adenosine triphosphate to push more blood per beat).
Within the working muscle, oxygen extraction from arterial blood is limited by the partial-pressure gradient between capillary and mitochondrion, and by myoglobin's ability to buffer oxygen delivery to the mitochondrion during the muscle contraction phase. Iron deficiency reduces this delivery capacity at the systemic level (less hemoglobin), the local level (less myoglobin), and the consumption level (less cytochrome c oxidase).
Iron, VO2max, and Endurance Capacity
VO2max — the maximum rate of oxygen consumption a person can sustain during incremental exercise — is the single best laboratory predictor of endurance performance and is tightly coupled to hemoglobin concentration. Studies in iron-deficient elite endurance athletes show a linear relationship between hemoglobin and VO2max across the normal physiological range, with each 1 g/dL change in hemoglobin producing approximately a 4 mL/kg/min change in VO2max in trained athletes. The relationship is even more pronounced in submaximal endurance tasks where lactate threshold (the exercise intensity at which blood lactate rises rapidly) is iron-sensitive.
The lactate-threshold sensitivity is particularly notable because lactate threshold (rather than VO2max per se) is what determines time-to-exhaustion in long-duration endurance events. An iron-deficient runner running at 80% of her VO2max may be above her lactate threshold and accumulating fatigue quickly, where an iron-replete runner at the same percentage of VO2max may still be below her lactate threshold and able to sustain the pace much longer. This is why iron-deficient endurance athletes complain of disproportionate fatigue at submaximal training intensities even when they can still hit acceptable VO2max numbers in a laboratory test.
Pre-iron-repletion vs post-iron-repletion comparisons in non-anemic iron-deficient female endurance athletes consistently show 1-3% improvements in time-to-exhaustion at fixed submaximal intensity and 5-15% improvements in time-trial performance over middle-distance events (3-15 km running, 10-40 km cycling). In elite athletes where every fraction of a percent matters, these are large effects.
Female Athletes — Why Prevalence Is So High
Female endurance athletes are the highest-risk demographic for iron deficiency outside of pregnancy. Reported prevalence in published cohorts of collegiate and elite athletes runs 20-50% for non-anemic iron deficiency (ferritin < 30 ng/mL) and 5-15% for iron deficiency anemia. The drivers are additive:
- Menstrual blood loss: Baseline 0.5 mg/day average iron loss, higher with heavy menses. This alone puts the Recommended Dietary Allowance (RDA) at 18 mg/day for premenopausal women, double the male Recommended Dietary Allowance.
- Increased iron loss in sweat, urine, gastrointestinal (GI) mucosa: Endurance training elevates basal iron losses by an additional 0.5-1 mg/day.
- Foot-strike hemolysis: Discussed below; mechanical destruction of red cells in the plantar capillaries during distance running releases hemoglobin into plasma where free hemoglobin is captured by haptoglobin and removed via reticuloendothelial system, with iron loss.
- Exercise-induced gastrointestinal bleeding: Endurance exercise causes splanchnic vasoconstriction and ischemic gastrointestinal mucosal injury, with occult blood loss documented in 16-85% of marathon runners depending on intensity. Even small per-event losses add up over a training year.
- Hepcidin elevation post-exercise: Discussed in detail below; the inflammatory interleukin-6 (IL-6) response to endurance exercise transiently suppresses iron absorption in the 3-6 hour post-exercise window.
- Dietary patterns: Many endurance athletes follow restricted or partly vegetarian diets for body-composition or perceived-health reasons, reducing heme iron intake. Carbohydrate-loaded diets often displace red meat. Energy-deficient (REDS, female athlete triad) athletes have even lower iron intake.
- Frequent blood donation: Some athletes donate plasma or whole blood for income and inadvertently strip 200-250 mg iron per donation.
The cumulative result is that an elite female endurance athlete training 60-100 km per week on a partly-plant-based diet faces a high risk of developing iron deficiency over the course of a season when iron intake and ferritin are not tracked. DellaValle and Haas (2011), who found 30% of non-anemic female collegiate rowers iron-depleted, concluded that screening for low iron stores at the start of a training program in female endurance athletes may be clinically useful.
Iron-Repletion Trials in Iron-Depleted Women
Much of the randomized, placebo-controlled evidence on iron repletion in non-anemic iron-depleted women comes from J. D. Haas's group in the Division of Nutritional Sciences at Cornell University (Hinton 2000, Brownlie 2002, DellaValle 2011); John Beard and Brenda Tobin reviewed iron status and exercise in 2000. The Brownlie 2002 trial randomized 41 untrained, iron-depleted, non-anemic women to 50 mg ferrous sulfate twice daily or placebo for 6 weeks; all of them trained on cycle ergometers 5 days a week for 4 weeks, beginning in week 3. The iron group showed:
- Significantly greater improvement in VO2max with training than the placebo group
- Improved serum ferritin, serum transferrin receptor and transferrin saturation
- No change in hemoglobin or hematocrit
- Effects concentrated among the women with poor baseline iron status (serum transferrin receptor above 8.0 mg/L)
In a related trial, Brutsaert, Haas and colleagues (2003, State University of New York at Albany and Cornell) gave 20 iron-depleted, non-anemic women iron or placebo for 6 weeks (10 per group). In the iron group the loss of quadriceps strength during a knee-extension fatigue test slowed: maximal strength was about 15% higher at the sixth minute and about 27% higher at the end of the protocol after treatment.
The interpretation was that even in subjects not classically anemic, iron deficiency limited the ability to respond to endurance training stimulus — presumably by limiting mitochondrial biogenesis and the cytochrome / iron-sulfur-cluster expansion that normally accompanies endurance adaptation. The implication is that iron deficiency does not just hurt current performance, it hurts the capacity to improve through training.
The Hinton 2000 trial (42 untrained, iron-depleted, non-anemic women given 100 mg ferrous sulfate a day or placebo for 6 weeks, training during the final 4 weeks) found a greater improvement in 15-km cycle-ergometer time with iron (P = 0.04). The DellaValle and Haas (2011) screening study of 165 female collegiate rowers gave no iron: the 30% of non-anemic rowers who were iron-depleted reported 2-km times about 21 seconds slower than rowers with normal iron status. The McClung et al. (2009) trial in 219 female US Army soldiers during 8 weeks of basic combat training (100 mg ferrous sulfate or placebo) found that iron limited the fall in iron status and improved vigor scores, with faster 2-mile run times only in volunteers who began training with iron-deficiency anemia.
The aggregate effect-size picture: iron repletion in iron-deficient (ferritin < 20-25 ng/mL) female athletes typically produces 1-3% improvement in submaximal endurance, 2-5% improvement in VO2max, and 5-15% improvement in time-trial endurance over the 6-16 week timecourse needed to restore ferritin to > 30-40 ng/mL.
The Hepcidin-IL-6 Inflammatory Feedback in Exercise
Peter Peeling, Marc Sim, and colleagues at the University of Western Australia mapped out a counterintuitive but clinically important loop: endurance exercise itself transiently elevates hepcidin, the master regulator of iron absorption and recycling, with the practical consequence that iron taken in the post-exercise window is poorly absorbed.
The mechanism: endurance exercise produces a measurable rise in interleukin-6 (IL-6) from working skeletal muscle, peaking 1-2 hours post-exercise. Interleukin-6 is a potent stimulus for hepatic hepcidin synthesis, with hepcidin levels rising 3-6 hours post-exercise. Hepcidin binds to ferroportin (the only known cellular iron exporter) and induces its internalization and degradation, effectively closing the gate at both intestinal absorption (blocking dietary iron uptake) and macrophage iron recycling (blocking iron release from senescent red cell breakdown).
For an endurance athlete, this means that an iron-rich meal taken right after a hard workout will have substantially reduced iron absorption, while a meal taken before the workout or several hours after — ideally morning, before training — will be absorbed normally. A related finding on dose spacing comes from Nicole Stoffel and colleagues (2017, ETH Zurich), who studied iron-depleted women aged 18-40 without any exercise testing: fractional iron absorption was higher with 60 mg iron on alternate days than on consecutive days (21.8% vs 16.3%), and splitting a dose into 08:00 and 17:00 halves gave no more absorption than a single 08:00 dose while raising serum hepcidin.
The chronic version of this feedback contributes to the "anemia of endurance training" phenomenon: cumulative hepcidin elevation across consecutive training days can keep iron absorption suppressed enough to drive negative iron balance over weeks-to-months even in athletes consuming adequate dietary iron. This is a particular trap for athletes in heavy training blocks, racing seasons, or altitude camps.
Training-camp protocols described in sports practice place oral iron in the morning with vitamin C, separated from training by several hours, and use alternate-day rather than daily dosing (in the Stoffel trials the alternate-day dose let hepcidin fall between doses, improving fractional absorption per dose). For athletes with persistent low ferritin despite oral iron, intravenous ferric carboxymaltose (a single 750-1000 mg infusion) is used in endurance sports medicine. In the page's cited intravenous-iron trial (Burden 2015), a single 500 mg intravenous iron injection in 15 iron-deficient, non-anemic elite runners improved iron status for at least 4 weeks but made no difference to VO2max, total hemoglobin mass or time to exhaustion compared with placebo.
"Training-Induced Anemia" vs True Iron Deficiency
Endurance training produces an obligatory expansion of plasma volume, typically 200-400 mL within the first 1-2 weeks of a heavy training block. Because the red cell mass does not expand at the same rate, the hemoglobin concentration measured in g/dL drops — even though the absolute hemoglobin mass (total grams of hemoglobin in circulation) is unchanged or higher. This dilutional pseudoanemia is the basis of the "athletes have low hemoglobin" observation, and it is sometimes called "sports anemia" or "training-induced anemia."
The diagnostic challenge is that this pseudoanemia and true iron deficiency anemia look similar on a routine complete blood count (CBC) — both show hemoglobin below population norms. They are distinguished by iron studies: a dilutional pseudoanemia has normal ferritin, normal transferrin saturation, and a normal red cell distribution width with normal MCV. A true iron deficiency shows low ferritin, low transferrin saturation, elevated RDW, and microcytosis on the smear.
This matters because the responses differ. Dilutional pseudoanemia is an adaptive sign of effective endurance training and needs no treatment — iron supplementation in a non-deficient athlete does not improve performance. True iron deficiency anemia, even at the same hemoglobin number, is treated promptly in sports medicine because performance gains are large and structural recovery improves.
For this reason the sports-medicine workup of an endurance athlete with a "low hemoglobin" includes serum ferritin and transferrin saturation rather than starting iron empirically. Ferritin > 30 ng/mL with normal saturation = dilutional pseudoanemia, no treatment needed. Ferritin < 30 with low saturation = iron-deficient erythropoiesis, the range that is treated. Ferritin in the 30-50 ng/mL range with symptoms but no anemia = the gray zone where empirical short-term repletion trials are often appropriate based on clinical suspicion.
Foot-Strike Hemolysis and Gastrointestinal Losses
Foot-strike hemolysis is the mechanical destruction of red blood cells in the plantar capillaries during repetitive heel-strike of distance running. With each foot-strike, the capillaries in the heel and forefoot are compressed against the bones of the foot. The shear forces and brief ischemia damage red cell membranes, releasing free hemoglobin into the plasma where it is bound by haptoglobin and cleared by the reticuloendothelial system. A portion of the released iron is lost in urine as hemoglobinuria when haptoglobin is saturated.
The phenomenon is well-documented in marathon runners, with measurable haptoglobin depletion, free hemoglobin elevation, and occasionally visible hemoglobinuria immediately post-race. The same mechanism operates in other repetitive-impact sports including triathlon (run leg), dance, and certain military training contexts. Cycling and swimming, with low or no impact loading on the feet, do not produce foot-strike hemolysis.
Practical mitigation: cushioned shoes, soft surfaces, midfoot rather than heel strike, and lower body mass all reduce per-stride loading and thus per-race iron loss. The accumulated effect across a marathon training year is meaningful but not overwhelming — foot-strike alone does not produce iron deficiency in a runner with adequate iron intake, but it adds to other losses and tips the balance in already-marginal athletes.
Exercise-induced gastrointestinal blood loss is the second mechanical loss mechanism and is often underappreciated. Splanchnic vasoconstriction during heavy endurance exercise produces ischemic mucosal injury in the gastric, small-intestinal, and colonic walls. Occult fecal blood is detectable in 16-85% of marathon runners post-race depending on intensity, hydration status, nonsteroidal anti-inflammatory drug (NSAID) use, and individual susceptibility. Per-event losses are small, but cumulative losses over a competitive season can be significant. Nonsteroidal anti-inflammatory drug use, in particular, both directly damages gastric mucosa and inhibits cyclooxygenase-mediated prostaglandin protection of gastric mucosa — the routine pre-race ibuprofen of many endurance athletes is a meaningful contributor.
Screening, Targets, and Practical Supplementation
The sports-medicine consensus that has emerged over the last decade:
- Annual screening minimum: Ferritin, hemoglobin, hematocrit, MCV, RDW at preseason physical for all endurance athletes, especially female athletes.
- Mid-season recheck: For athletes with marginal baseline ferritin or symptomatic fatigue / performance decrement.
- Iron-deficient threshold (athletes): Ferritin < 35 ng/mL flags repletion candidate. Some sports-medicine programs use < 50.
- Iron-deficient anemia threshold: Hemoglobin < 12 g/dL (women) or < 13 g/dL (men) with iron-deficient iron studies — the range treated most promptly.
- Target after repletion: Ferritin > 50-100 ng/mL for endurance athletes, depending on training load.
Amounts and schedules used in the cited trials and in sports-medicine practice:
- Ferrous sulfate in the trials: the Hinton 2000 and Brownlie 2002 trials gave 100 mg ferrous sulfate a day for 6 weeks, and the McClung 2009 trial 100 mg ferrous sulfate a day for 8 weeks. Stoffel 2017 gave 60 mg iron as ferrous sulfate at 08:00; alternate days gave higher fractional absorption than consecutive days (21.8% vs 16.3%), with lower serum hepcidin over the first 14 days. Vitamin C taken with the dose raises non-heme iron absorption, while coffee, tea, calcium and dairy taken at the same time lower it.
- Ferrous bisglycinate alternative: 25-50 mg elemental iron every day or every other day is the range used for athletes who do not tolerate ferrous sulfate. It is reported as better tolerated, with slightly lower mg-for-mg absorption.
- Timing relative to training: sports-practice protocols place oral iron in the morning, 4-6 hours before a hard workout or 6-8 hours after, outside the post-exercise hepcidin window when absorption is suppressed.
- Intravenous ferric carboxymaltose (FCM): used as a single 750-1000 mg dose for athletes with persistent low ferritin despite oral iron, gastrointestinal intolerance, or a short timeline before competition, usually after oral iron has failed. In Burden 2015 a single 500 mg intravenous iron injection raised iron status but not aerobic capacity.
- Reassessment timeline: ferritin is typically rechecked at 8-12 weeks; a rise of ~25-50 ng/mL per quarter on therapy is the range described.
- Dietary support: heme iron sources (red meat, poultry, fish) at 3-5 meals per week are the dietary pattern described. See Heme vs Non-Heme Iron.
Cautions (Overload, Doping Rules, Hemochromatosis)
- Iron overload risk: Indefinite high-dose iron supplementation in non-deficient athletes is risky. Excess iron drives Fenton-chemistry oxidative stress, accumulates in liver and heart, and in HFE-mutation carriers (1 in 200-400 of Northern European ancestry are C282Y homozygotes) drives hemochromatosis. For this reason sports-medicine protocols limit supplementation to documented deficiency and stop it once ferritin reaches the target range rather than continuing indefinitely.
- Pre-supplementation HFE screening: described as reasonable for athletes of Northern European ancestry being started on chronic iron supplementation. In C282Y/C282Y homozygotes, iron given without documented deficiency adds to the iron loading of hemochromatosis; when deficiency is documented, supplementation is given with caution and follow-up monitoring.
- WADA doping considerations: Oral iron is not on the World Anti-Doping Agency (WADA) Prohibited List. Intravenous iron falls under prohibited method M2.2: intravenous infusions and/or injections of more than a total of 100 mL per 12-hour period are prohibited, except for those legitimately received in the course of hospital treatments, surgical procedures or clinical diagnostic investigations; outside those settings an athlete needs a Therapeutic Use Exemption (TUE). Erythropoietin (EPO) and EPO-mimetic peptides ARE banned. Hemoglobin and reticulocyte tracking in the Athlete Biological Passport program will flag suspicious rapid hemoglobin increases — documented iron-deficiency repletion, recorded in the athlete's medical record, provides a legitimate explanation. Blood transfusion (autologous or homologous) is WADA-banned. Normal therapeutic oral iron use carries no doping issue.
- Athlete iron deficiency and disordered eating: A significant fraction of iron-deficient female endurance athletes have concurrent low energy availability (RED-S, the female athlete triad). Iron is only part of the problem. Repletion of iron without addressing energy availability is incomplete and often ineffective — the underlying restrictive eating prevents iron repletion through both inadequate intake and elevated baseline hepcidin from the relative inflammation/stress state. Sports-medicine workups for this group include a nutrition assessment.
- "Just push iron higher" antipattern: Once ferritin is in the 50-100 ng/mL range and performance is adequate, more iron is not better. Continuing high-dose oral iron pushes ferritin into the iron-overload range without performance benefit and with cumulative oxidative-stress and HFE-unmasking risk.
- Copper-ceruloplasmin counterpoint: See the Morley Robbins discussion on the Cognitive Performance page. Some practitioners argue that iron supplementation without copper repletion drives unbound iron deposition and underlying ceruloplasmin dysfunction. These practitioners describe checking ceruloplasmin in cases that do not respond to iron supplementation.
Key Research Papers
- Brutsaert TD, Hernandez-Cordero S, Rivera J, Viola T, Hughes G, Haas JD (2003). Iron supplementation improves progressive fatigue resistance during dynamic knee extensor exercise in iron-depleted, nonanemic women. American Journal of Clinical Nutrition. — PubMed PMID: 12540406
- Hinton PS, Giordano C, Brownlie T, Haas JD (2000). Iron supplementation improves endurance after training in iron-depleted, nonanemic women. Journal of Applied Physiology 88(3):1103-11. — PubMed PMID: 10710409
- Brownlie T 4th, Utermohlen V, Hinton PS, Giordano C, Haas JD (2002). Marginal iron deficiency without anemia impairs aerobic adaptation among previously untrained women. American Journal of Clinical Nutrition 75(4):734-42. — PubMed PMID: 11916761
- Beard J, Tobin B (2000). Iron status and exercise. American Journal of Clinical Nutrition 72(2 Suppl):594S-7S. — PubMed PMID: 10919965
- Peeling P, Dawson B, Goodman C, Landers G, Trinder D (2008). Athletic induced iron deficiency: new insights into the role of inflammation, cytokines and hormones. European Journal of Applied Physiology. — PubMed PMID: 18365240
- Sim M, Garvican-Lewis LA, Cox GR, Govus A, McKay AKA et al. (2019). Iron considerations for the athlete: a narrative review. European Journal of Applied Physiology. — PubMed PMID: 31055680
- Stoffel NU, Cercamondi CI, Brittenham G, Zeder C, Geurts-Moespot AJ et al. (2017). Iron absorption from oral iron supplements given on consecutive versus alternate days and as single morning doses versus twice-daily split dosing in iron-depleted women. Lancet Haematology. — PubMed PMID: 29032957
- DellaValle DM, Haas JD (2011). Impact of iron depletion without anemia on performance in trained endurance athletes at the beginning of a training season. International Journal of Sport Nutrition and Exercise Metabolism. — PubMed PMID: 22089308
- McClung JP, Karl JP, Cable SJ, Williams KW, Nindl BC, Young AJ, Lieberman HR (2009). Randomized, double-blind, placebo-controlled trial of iron supplementation in female soldiers during military training. American Journal of Clinical Nutrition. — PubMed PMID: 19474138
- Telford RD, Sly GJ, Hahn AG, Cunningham RB, Bryant C, Smith JA (2003). Footstrike is the major cause of hemolysis during running. Journal of Applied Physiology. — PubMed PMID: 12391035
- Nemeth E, Rivera S, Gabayan V, Keller C, Taudorf S, Pedersen BK, Ganz T (2004). IL-6 mediates hypoferremia of inflammation by inducing the synthesis of the iron regulatory hormone hepcidin. Journal of Clinical Investigation 113(9):1271-6. — PubMed PMID: 15124018
- Burden RJ, Pollock N, Whyte GP, Richards T, Moore B, Busbridge M et al. (2015). Effect of intravenous iron on aerobic capacity and iron metabolism in elite athletes. Medicine and Science in Sports and Exercise. — PubMed PMID: 25386711
- Pasricha SR, Low M, Thompson J, Farrell A, De-Regil LM (2014). Iron supplementation benefits physical performance in women of reproductive age: a systematic review and meta-analysis. Journal of Nutrition. — PubMed PMID: 24717371
PubMed Topic Searches
Connections
- All Minerals
- Iron Benefits Hub
- Iron Overview
- Iron Deficiency Anemia
- Heme vs Non-Heme Iron
- Iron and Cognitive Performance
- Copper
- Hemoglobin and Ceruloplasmin
- Zinc
- Magnesium
- Vitamin C
- Vitamin B12
- Vitamin D3
- Iron Panel
- Complete Blood Count
- Fatigue
- Beef
- Salmon
- Organ Meats
- Hemochromatosis
- Deficiency
- Toxicity
- History
- Sources