⚠ Evidence warning: Clinical trials or other evidence do not support the claims that iron repletion improves antidepressant response, that iron deficiency speeds multiple sclerosis disability, that iron gains in women match methylphenidate, and that much iron deficiency is really copper deficiency. This page keeps it as a report of what people, websites or other media say.
Iron and Cognitive Performance
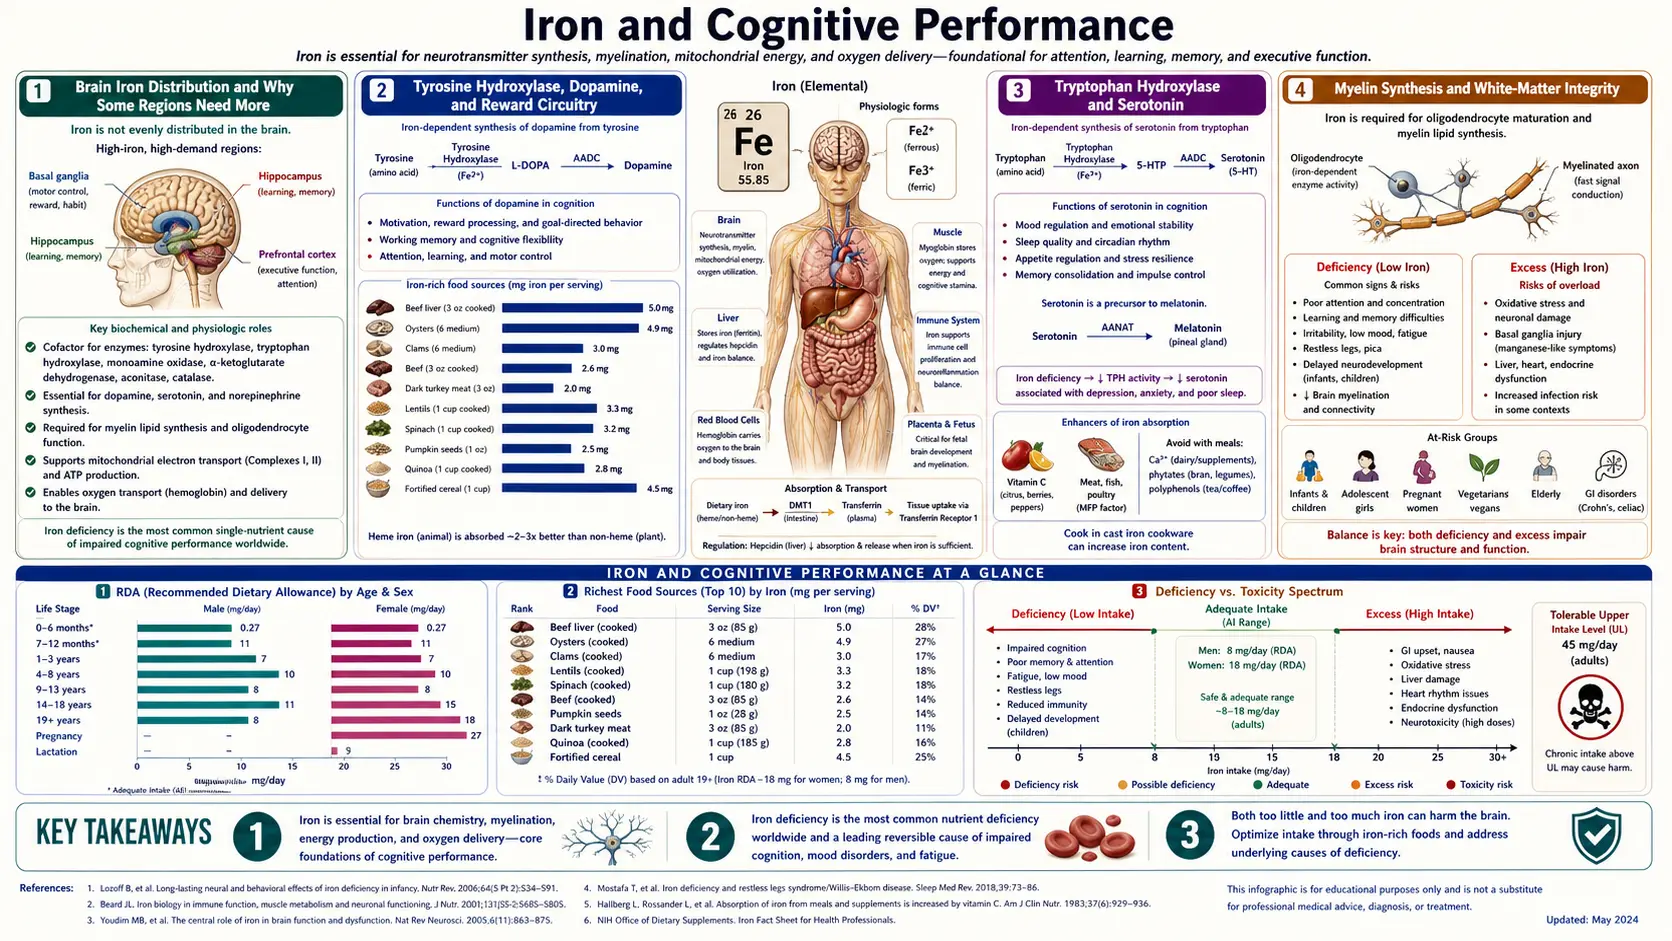
Iron is the rate-limiting cofactor for the brain's monoamine synthesis machinery — tyrosine hydroxylase (dopamine, norepinephrine) and tryptophan hydroxylase (serotonin) both require ferrous iron at their active sites — and it is required for the cholesterol-rich myelin sheath that oligodendrocytes wrap around axons to enable rapid saltatory conduction. The behavioral, attentional, and executive-function consequences of iron deficiency are therefore not secondary to anemia: they appear at the iron-deficient-erythropoiesis stage, before hemoglobin drops, and may not fully reverse in the developing brain even after later repletion. Betsy Lozoff's 25-year follow-up of Costa Rican infants with chronic iron deficiency reported lower school completion and poorer emotional health in early adulthood, the Murray-Kolb trial linked rising ferritin to better cognitive performance in young women, and Earley and Allen demonstrated brain-region-specific iron loss as the central abnormality in restless legs syndrome. This deep-dive walks through the molecular machinery, the developmental windows, the adult ADHD/RLS literature, and the practical clinical thresholds.
Table of Contents
- Brain Iron Distribution and Why Some Regions Need More
- Tyrosine Hydroxylase, Dopamine, and Reward Circuitry
- Tryptophan Hydroxylase and Serotonin
- Myelin Synthesis and White-Matter Integrity
- The Lozoff Studies — Persistent Sequelae of Infant Iron Deficiency
- Murray-Kolb — Executive Function in Iron-Deficient Adult Women
- Ferritin and Attention-Deficit/Hyperactivity Disorder — The Konofal Signal
- Restless Legs Syndrome and the Allen Brain Ferritin Model
- Iron Deficiency in Cognitive Aging and Dementia Risk
- Clinical Thresholds and Practical Protocol
- Cautions (Brain Iron Excess in Neurodegeneration)
- Key Research Papers
- Connections
- Featured Videos
Brain Iron Distribution and Why Some Regions Need More
The adult human brain contains approximately 60 mg of non-heme iron, but it is not distributed evenly. The basal ganglia — specifically the substantia nigra, putamen, globus pallidus, and caudate nucleus — concentrate iron at 5 to 10 times the levels found in cortex. The choroid plexus, the red nucleus, and the dentate nucleus of the cerebellum are similarly iron-dense. These regions all share two features: high oxidative metabolism (making them energy-expensive and dependent on cytochrome-based adenosine triphosphate (ATP) synthesis) and reliance on monoamine neurotransmitter signaling (making them dependent on the iron-requiring rate-limiting enzymes for dopamine and serotonin synthesis).
Iron crosses the blood-brain barrier through transferrin-receptor-mediated endocytosis at the endothelial cells of cerebral capillaries. Once inside the brain parenchyma, iron is shuttled by astrocyte-secreted transferrin to neurons and to oligodendrocytes, the latter being the most iron-rich cell type in the central nervous system. Oligodendrocytes need the iron not for their own dopaminergic signaling but to build the cholesterol- and lipid-rich myelin membranes they wrap around axons — iron is a cofactor for several enzymes in cholesterol biosynthesis and for the sphingolipid synthesis required for myelin assembly.
The brain regulates its own iron homeostasis somewhat independently of the systemic compartment. Hepcidin is expressed locally in the brain in response to inflammation and iron loading, and brain ferritin (predominantly the H-isoform with higher ferroxidase activity, suited to neurons' reactive-oxygen-prone environment) provides local storage. This means that systemic iron deficiency does not produce immediate proportional brain iron depletion — the brain is partially buffered — but sustained deficiency or deficiency during critical developmental windows will eventually deplete brain stores, particularly in the basal ganglia where demand is highest.
Tyrosine Hydroxylase, Dopamine, and Reward Circuitry
The rate-limiting step in dopamine synthesis is the hydroxylation of tyrosine to L-3,4-dihydroxyphenylalanine (L-DOPA), catalyzed by tyrosine hydroxylase (TH). TH belongs to the family of biopterin-dependent aromatic amino acid hydroxylases, and at its active site it carries a single ferrous (Fe2+) iron atom coordinated by two histidines and a glutamate. The iron atom activates molecular oxygen in cooperation with the tetrahydrobiopterin cofactor to produce a high-valent iron-oxo species that hydroxylates tyrosine. Without iron, the enzyme is catalytically dead. With insufficient iron, the enzyme works but does not keep up with dopaminergic firing demand — particularly in the nigrostriatal and mesocorticolimbic pathways that drive reward, motivation, motor initiation, and executive function.
The later steps run on other cofactors. Dopamine beta-hydroxylase, which converts dopamine to norepinephrine in noradrenergic neurons (locus coeruleus, peripheral sympathetic terminals), is a copper enzyme: the 2016 structure paper describes an ascorbate-dependent glycoprotein that needs two bound copper ions, with the electrons supplied by two ascorbate (vitamin C) molecules, and gives iron no role. Monoamine oxidase A and B, which break down dopamine and norepinephrine, are flavoenzymes rather than iron enzymes; the 2002 structure of monoamine oxidase B places it on the outer membrane of mitochondria, and its described chemistry takes place at the flavin.
Behaviorally, iron deficiency therefore produces a phenotype that overlaps strikingly with dopaminergic dysfunction: reduced motivation and reward sensitivity, attention deficits, impaired working memory, fatigue with intact muscle strength (suggesting a central rather than peripheral fatigue), and in extreme cases anhedonia. These are not vague subjective complaints — they map onto specific dopaminergic neural circuits and onto measurable behavioral testing on rotarod, eight-arm maze, and operant conditioning paradigms in iron-deficient animal models, all of which improve with iron repletion.
Tryptophan Hydroxylase and Serotonin
The rate-limiting enzyme in serotonin synthesis, tryptophan hydroxylase (TPH1 in the periphery, TPH2 in the brain), is structurally homologous to tyrosine hydroxylase and shares the same ferrous-iron / tetrahydrobiopterin active-site chemistry. It converts tryptophan to 5-hydroxytryptophan, which is then decarboxylated to serotonin by aromatic L-amino acid decarboxylase. Iron deficiency reduces TPH2 activity in the raphe nuclei, the midbrain origin of nearly all serotonergic projections to the cortex, hippocampus, and limbic system.
The serotonergic consequences of iron deficiency are less dramatic clinically than the dopaminergic ones — presumably because circulating tryptophan levels and TPH2 affinity for tryptophan provide partial buffering — but they contribute to the mood, sleep, and appetite changes documented in iron-deficient adults. Sleep architecture studies in iron-deficient infants show reduced REM sleep proportions, an effect partly attributable to disrupted serotonergic regulation of sleep-stage transitions. Mood symptoms (irritability, low mood, anxiety) in iron-deficient adolescent girls correlate with serum ferritin and improve with iron repletion in randomized trials.
The interaction with selective serotonin reuptake inhibitor (SSRI) therapy deserves more attention than it gets clinically. Selective serotonin reuptake inhibitors work by blocking the serotonin transporter, increasing synaptic serotonin from whatever is being synthesized. If the rate-limiting synthesis step (TPH2) is iron-limited, a selective serotonin reuptake inhibitor can only do so much. There is a small but consistent literature suggesting that iron repletion in iron-deficient patients with treatment-resistant depression improves selective serotonin reuptake inhibitor response, and an open-label literature suggesting that iron status should be checked in any new depression workup before declaring a patient selective serotonin reuptake inhibitor-non-responsive.
Myelin Synthesis and White-Matter Integrity
Oligodendrocytes are the most iron-rich cell type in the central nervous system, concentrating iron at levels several-fold higher than neurons. Their iron need is driven by their role as the brain's myelin factory. Each oligodendrocyte wraps multiple axons (up to 60 in human white matter) with successive lipid-rich membrane sheaths, and these membranes are 70-80% lipid by dry weight — primarily cholesterol, galactosylceramide, sulfatide, and phospholipids. Iron is a cofactor for several enzymes in cholesterol biosynthesis (including lanosterol 14-alpha-demethylase, an iron-dependent oxygenase; squalene monooxygenase, its neighbour on the pathway, is a flavin adenine dinucleotide-dependent epoxidase rather than an iron enzyme) and for the desaturases that introduce double bonds into myelin fatty acids.
Iron deficiency during the first two years of life — the period of most rapid myelination — produces measurable reductions in white-matter volume on magnetic resonance imaging (MRI), reduced myelin water fraction, and slowed brainstem auditory evoked response conduction velocity. These structural abnormalities persist on follow-up magnetic resonance imaging into adolescence even when serum ferritin has been normalized in the interim. This is the structural correlate of the persistent cognitive deficits observed in the Lozoff cohort discussed below.
The adult brain undergoes much less de novo myelination, but myelin turnover continues throughout life, and remyelination is a critical process after demyelinating injury (multiple sclerosis, stroke, traumatic brain injury). Iron deficiency in adults with multiple sclerosis is associated with poorer remyelination capacity and faster disability progression in observational cohorts, though the causal relationship has not been definitively established by intervention trial.
The Lozoff Studies — Persistent Sequelae of Infant Iron Deficiency
Betsy Lozoff's longitudinal cohort study of iron-deficient Costa Rican infants is the most-cited and most-influential body of work on the long-term cognitive consequences of early iron deficiency. The cohort was assembled in the 1980s and followed for over 25 years. At baseline, infants with iron deficiency anemia (hemoglobin < 10.5 g/dL with low serum ferritin and elevated free erythrocyte protoporphyrin) were compared with iron-sufficient controls on the Bayley Scales of Infant Development. Anemic infants scored 10-12 points lower on the mental development index and 7-10 points lower on the psychomotor development index, with greater impairment in those whose deficiency was more severe and longer-standing at diagnosis.
The infants were then enrolled in a randomized trial of iron repletion. After 3 months of treatment, the lower scores were no longer seen in the 36% of anemic infants whose anemia and iron deficiency were both corrected. They persisted in the 64% with more severe or chronic deficiency, who were no longer anemic but still showed biochemical evidence of iron deficiency. The children were then followed prospectively for years. At age 5, the previously-anemic group scored lower on visual-motor integration, fine motor coordination, and standardized cognitive testing. At age 11-14, the 48 children with chronic, severe deficiency in infancy were compared with 114 who had good iron status before and/or after therapy: they scored lower on arithmetic, written expression, and motor function, more had repeated a grade, and parents and teachers reported more concern about anxiety/depression, social problems and attention problems.
At age 25, 58.1% of the 33 adults with chronic iron deficiency in infancy had not completed secondary school, against 19.8% of the 89 who had been iron-sufficient before and/or after therapy (a comparison group that includes treated infants, so not a never-anemic group). The chronic group also reported poorer emotional health. The authors describe a chain running from chronic deficiency through poorer cognitive functioning in early adolescence to leaving school, and they caution that “the observational nature of this study limits our ability to draw causal inference.”
The interpretation is that early iron deficiency during the critical period of brain development (peak myelination and synaptogenesis from approximately 6 months to 24 months postnatal) produces structural and functional changes that are not fully reversible by later iron repletion. The Costa Rica findings have been replicated in Chilean, Honduran, Indian, and Chinese cohorts. The mechanistic best-guess is reduced white-matter myelination at a non-recoverable developmental window, combined with persistent dopaminergic abnormalities in the developing basal ganglia.
More iron is not always better for babies, however. In a Chilean trial, healthy infants were randomly given iron-fortified formula (12 mg/L) or low-iron formula (2.3 mg/L) from 6 to 12 months of age. At 16 years, the 405 participants who were followed up showed lower scores for visual memory, arithmetic and reading comprehension in the fortified-formula group. Visual-motor skill depended on the baby's starting hemoglobin: the fortified group did better when 6-month hemoglobin was low and worse when it was high. The authors state that preventing iron deficiency anemia in infancy is important for brain development, but that the optimal level of iron supplementation in infancy is unclear.
The Lozoff work places the emphasis on preventing iron deficiency during the first two years of life. The American Academy of Pediatrics recommends universal screening for iron deficiency at age 12 months, iron-fortified formula or iron supplementation for breastfed infants from 4 months until complementary foods provide adequate iron, and iron-fortified cereals as an early complementary food. Routine ferrous sulfate drops (1 mg/kg/day from 4 months in exclusively breastfed infants) are inexpensive and effective.
Murray-Kolb — Executive Function in Iron-Deficient Adult Women
Laura Murray-Kolb and colleagues at Penn State conducted a series of randomized, placebo-controlled iron-supplementation trials in iron-deficient (but not necessarily anemic) adult women to test whether the cognitive deficits associated with iron deficiency could be reversed with repletion in adults — a question previously assumed to be answered yes but never rigorously tested in adult cohorts.
In the seminal 2007 trial, women aged 18-35 of varied iron status were randomly assigned to iron or placebo for 16 weeks in a blinded, stratified design. Of 149 tested at baseline, 42 were iron-sufficient, 34 had iron deficiency anemia and 73 were iron-deficient without anemia; 113 women across these groups were tested again at 16 weeks. At baseline, the iron-sufficient women performed better and faster than the women with anemia, and the iron-deficient non-anemic women fell in between. After treatment, a significant improvement in serum ferritin was associated with a 5-7-fold improvement in cognitive performance, and a significant improvement in hemoglobin with faster task completion. The abstract does not state the ferrous sulfate dose of 160 mg iron daily, the ferritin cut-offs of < 16 and > 30 ng/mL, or a separate placebo result, all of which have been quoted for this trial; the full text could not be opened to confirm them.
Cognition was measured with 8 tasks from Detterman's Cognitive Abilities Test. The gains have been described as falling in attention, verbal learning, memory, processing speed, working memory and task-switching, and as comparable in size to methylphenidate in mild adult attention-deficit/hyperactivity disorder (ADHD). The abstract does not split its results by those areas and names no Rey test, and neither the abstract nor Murray-Kolb's 2011 review abstract makes the methylphenidate comparison. Its stated conclusion is that severity of anemia mainly affects processing speed, and severity of iron deficiency affects accuracy across a broad range of tasks.
What is not known extends to children. A 2022 meta-analysis of 9 studies (1,196 children and teens aged 5-19, in low- and middle-income countries) found that iron raised intelligence test scores (standardized mean difference 0.47) but had no significant effect on attention, short-term memory, long-term memory or school performance.
The clinical reading of this work is that the cognitive symptoms attributed to "just being tired" or "stressed" in young adult women, particularly those with heavy menstrual periods, frequent blood donation, or vegetarian/vegan diets, may be substantially due to iron-deficient cognition even in the absence of anemia. In that reading ferritin, not hemoglobin, is the marker that matters, and a premenopausal woman with ferritin in the 10-20 ng/mL range and persistent fatigue, brain fog, or attention complaints is regarded as a candidate for therapeutic iron repletion regardless of whether her hemoglobin meets World Health Organization criteria for anemia.
Ferritin and Attention-Deficit/Hyperactivity Disorder — The Konofal Signal
Eric Konofal and colleagues at Hôpital Robert-Debré in Paris reported in 2004 that 53 children with attention-deficit/hyperactivity disorder had significantly lower serum ferritin levels than 27 age-matched controls (mean 23 ng/mL vs 44 ng/mL; below 30 ng/mL in 84% vs 18%), and that ferritin level inversely correlated with attention-deficit/hyperactivity disorder symptom severity on the Conners Parent Rating Scale. The relationship was independent of hemoglobin — the attention-deficit/hyperactivity disorder children were not anemic, only iron-low — suggesting that brain iron status (which ferritin partially indexes) was the relevant variable, not erythrocyte iron. A 2026 meta-analysis of 46 case-control studies (5,515 cases, 8,166 controls) also found lower ferritin in children and teens with the condition, with high variation between studies. These are associations, which do not show that low iron causes it.
The follow-up trial by the same group randomized 23 non-anemic attention-deficit/hyperactivity disorder children aged 5-8 with ferritin < 30 ng/mL, in a 3:1 ratio, to ferrous sulfate (80 mg/day, 18 children) or placebo (5 children) for 12 weeks. The ADHD Rating Scale fell progressively and significantly on iron (-11.0, P < 0.008), and not on placebo. Improvement on the Conners Parent Rating Scale (P = 0.055) and Conners Teacher Rating Scale (P = 0.076) failed to reach significance. The authors describe effectiveness as comparable to stimulants and call for larger controlled trials. Subsequent placebo-controlled trials by other groups have produced mixed results, with some confirming the Konofal signal and others (notably in non-iron-deficient attention-deficit/hyperactivity disorder populations) finding no benefit.
One interpretation of this work is that attention-deficit/hyperactivity disorder in the context of low brain iron is iron-responsive, but attention-deficit/hyperactivity disorder per se is not an iron-deficiency disease. From it comes the clinical view that a ferritin check belongs in an evaluation for attention-deficit/hyperactivity disorder, that iron repletion comes first or alongside a stimulant trial when ferritin is below 30 ng/mL, and that iron supplementation is not expected to improve attention-deficit/hyperactivity disorder symptoms when ferritin is adequate. The same reasoning is applied to adult attention-deficit/hyperactivity disorder, where ferritin screening is described as a low-cost, high-information addition to the standard workup.
Mechanistically, the attention-deficit/hyperactivity disorder-iron connection runs through the dopaminergic pathways discussed above. Attention-deficit/hyperactivity disorder is increasingly understood as a dopamine-deficit-and-dysregulation syndrome in the prefrontal-striatal circuits, and stimulant medications work by elevating synaptic dopamine. If tyrosine hydroxylase is iron-limited, the dopamine deficit is partly a biosynthetic one, and iron repletion addresses the upstream supply problem rather than just the downstream reuptake problem.
Restless Legs Syndrome and the Allen Brain Ferritin Model
Restless legs syndrome (RLS), now also called Willis-Ekbom disease, is one of the clearest examples of region-specific brain iron deficiency producing a clinically distinct neurological syndrome. Richard Allen and colleagues at Johns Hopkins published the foundational evidence in the early 2000s: cerebrospinal fluid ferritin is reduced and transferrin elevated in RLS patients compared with controls, despite normal serum iron studies. Subsequent post-mortem and magnetic resonance imaging studies confirmed reduced iron content specifically in the substantia nigra of RLS patients.
The pathophysiology is now understood as a regional dopaminergic deficit in nigrostriatal and diencephalic A11 dopamine pathways, driven by reduced tyrosine hydroxylase activity from regional iron deficiency, with downstream consequences for descending modulation of spinal sensorimotor processing. The clinical syndrome — an irresistible urge to move the legs that worsens at rest, in the evening, and in bed, and is partially relieved by movement — reflects this circuit-level dysfunction. RLS is dramatically responsive to dopaminergic medications (pramipexole, ropinirole) for the same reason.
The American Academy of Sleep Medicine's 2025 guideline states that clinicians should regularly test iron studies, including ferritin and transferrin saturation, in all patients with clinically significant RLS. The iron thresholds it quotes come from consensus guidelines that it notes “have not been empirically tested”: oral or intravenous iron in adults if ferritin is at or below 75 ng/mL or transferrin saturation below 20%, and only intravenous iron if ferritin is between 75 and 100 ng/mL. The reasoning given for iron first: iron repletion can dramatically reduce or eliminate RLS symptoms in iron-deficient patients without exposing them to the long-term complications of dopaminergic medications (augmentation, impulse control disorders). The Allen group's 2018 International Restless Legs Syndrome Study Group task force report goes beyond a fallback role for intravenous iron: it states that ferric carboxymaltose 1000 mg is effective for moderate to severe RLS in those with serum ferritin below 300 µg/L and could be used as first-line treatment, and that oral iron (65 mg elemental iron) is possibly effective in those with ferritin at or below 75 µg/L.
The same 2025 guideline strongly recommends gabapentin, gabapentin enacarbil, pregabalin and intravenous ferric carboxymaltose (with suitable iron levels) for adults with RLS. It suggests against the standard use of pramipexole, ropinirole, rotigotine and levodopa, with long-term worsening of symptoms (augmentation) as the stated concern, while noting they may suit people who put more value on short-term relief. It names addressing alcohol, caffeine, certain medicines (antihistaminergic, serotonergic and antidopaminergic) and untreated obstructive sleep apnea as the first step.
RLS in pregnancy, a common and often overlooked entity, is particularly amenable to iron-based management because the pregnancy itself produces iron depletion that worsens through the third trimester. Aggressive iron supplementation in pregnant women with RLS often resolves the syndrome without need for medication.
Iron Deficiency in Cognitive Aging and Dementia Risk
The cognitive role of iron in older adults is more complicated than in young adults or infants, because the aging brain accumulates iron in pathological deposits while sometimes being functionally iron-deficient at the cellular level. Excess iron in the substantia nigra is a feature of Parkinson's disease, and excess iron in the basal ganglia, hippocampus, and cortex has been documented in Alzheimer's disease postmortem and on susceptibility-weighted magnetic resonance imaging.
At the same time, frank iron-deficiency anemia in older adults is associated with accelerated cognitive decline, increased dementia risk in observational cohorts, and worse outcomes after stroke and hip fracture. The reconciliation is that iron in the wrong place (deposited in plaques, in degenerating neurons, in inflammatory microglia) is toxic, while iron in the right place (in healthy neurons supporting normal neurotransmitter synthesis) is essential. Systemic iron-deficiency anemia in the elderly does not improve neurodegeneration but does worsen the global cognitive picture by producing brain hypoxia, reduced adenosine triphosphate supply, and impaired neurotransmitter synthesis on top of any underlying neurodegenerative process.
The clinical view for older adults, which no study on this page tested, treats iron-deficiency anemia like any other treatable contributor to cognitive impairment, gives no iron to non-deficient older adults in the hope of improving brain function, and keeps ferritin and transferrin saturation in the lower-normal range (50-100 ng/mL, <40% saturation) in people with documented Parkinson's or Alzheimer's disease rather than pushing toward repletion targets used in younger adults.
Trials of lowering brain iron have gone the other way from what the deposits might suggest. In 372 people with newly diagnosed Parkinson's disease, the iron-binding drug deferiprone for 36 weeks worsened the total symptom rating score by 15.6 points against 6.3 on placebo, although iron in the affected brain area fell more than on placebo. In 81 people with mild cognitive impairment or early Alzheimer's disease, 12 months of deferiprone lowered hippocampal iron and sped cognitive decline. These trials do not show that high brain iron is something removing iron can fix; the Alzheimer's trial authors conclude that lowering iron with deferiprone is detrimental to those patients.
Clinical Thresholds and Practical Protocol
For brain-focused iron repletion, the relevant biomarker is serum ferritin, not hemoglobin. Hemoglobin is a lagging indicator that does not drop until the deficiency is severe. Ferritin is the body's storage iron and the best proxy for brain iron availability. The bands below are one practice framework, reported as such; no study on this page tested them as targets.
- Ferritin < 30 ng/mL: Iron-deficient in this framework and in the Konofal studies. The World Health Organization's expert-opinion thresholds are lower (below 15 µg/L in women, below 12 µg/L in children; 1 µg/L equals 1 ng/mL), and a 2021 US national survey analysis proposed physiological thresholds of about 25 µg/L in non-pregnant women and about 20 µg/L in children. The framework describes treatment here, with targets for pregnant women, RLS patients, attention-deficit/hyperactivity disorder patients, and patients with cognitive complaints of ferritin > 50 (general adult) or > 75-100 (RLS, treatment-resistant depression, severe attention-deficit/hyperactivity disorder).
- Ferritin 30-50 ng/mL: "Adequate" by population norms but probably suboptimal for brain-iron-dependent functions in symptomatic patients. The framework describes a repletion trial in patients with brain-symptom complaints (cognitive fog, attention deficits, mood, restless legs, fatigue).
- Ferritin 50-150 ng/mL: Described as optimal for most adults, with no supplementation called for.
- Ferritin > 200 ng/mL (women) or > 300 ng/mL (men): Possible iron overload. The usual investigations are HFE gene testing, transferrin saturation and liver enzymes, and the framework has no place for supplements at this level.
The usual first-line iron supplement described in this framework is ferrous sulfate 325 mg (65 mg elemental iron) on alternate days (per the alternate-day-dosing evidence discussed on the Iron Deficiency Anemia page) taken with vitamin C 250 mg, away from coffee/tea/calcium/dairy. A 2020 randomized trial in 440 adults with iron deficiency anemia found iron alone equivalent to iron plus 200 mg vitamin C (hemoglobin up 1.84 vs 2.00 g/dL at 2 weeks; ferritin up 34.48 vs 35.75 ng/mL at 8 weeks), and its authors concluded vitamin C is not essential to take alongside it. Ferrous bisglycinate is described as a well-tolerated alternative for patients with gastrointestinal intolerance to sulfate. The framework rechecks ferritin at 8-12 weeks and expects a rise of 25-50 ng/mL per quarter on therapy if the underlying deficiency is corrected.
Timing has been tested directly. In 150 young Swiss women with ferritin at or below 30 µg/L, 100 mg of iron on alternate days for 6 months gave the same median ferritin as daily iron for 3 months at the same total dose (44.8 vs 43.8 µg/L). Daily dosing had 1.56 times the rate of stomach and gut side effects, and iron deficiency at 6 months was 11.4% on daily dosing against 3.0% on alternate days.
Cautions (Brain Iron Excess in Neurodegeneration)
- Neurodegenerative iron excess: Pantothenate kinase-associated neurodegeneration (PKAN, formerly Hallervorden-Spatz disease), neuroferritinopathy, aceruloplasminemia, and the "neurodegeneration with brain iron accumulation" (NBIA) spectrum all involve pathological iron deposition in basal ganglia. Iron supplementation is contraindicated. So is empirical iron in any patient with established Parkinson's or Alzheimer's without documented systemic iron deficiency.
- Morley Robbins / copper-ceruloplasmin framework: The Robbins critique of iron supplementation argues that much of what is called "iron deficiency" is actually copper deficiency producing functional iron deficiency, because copper-dependent ceruloplasmin is required to load iron onto transferrin and to mobilize iron from ferritin stores. In this view, giving iron without addressing copper insufficiency drives unbound iron deposition into tissues, including brain, while leaving the underlying ceruloplasmin functional deficit untreated. See Hemoglobin and Ceruloplasmin and Whole Food Copper Sources for this counterpoint. In this framework, ceruloplasmin is checked alongside ferritin and transferrin saturation if iron supplementation does not produce the expected ferritin rise.
- Hemochromatosis screening: HFE genotyping (C282Y, H63D) and baseline transferrin saturation are described for people of Northern European ancestry being started on chronic iron supplementation. A heterozygote C282Y carrier supplemented with iron can accelerate iron overload.
- Selective serotonin reuptake inhibitor / dopaminergic interactions: Iron repletion in iron-deficient patients on stimulants or dopaminergic agonists can occasionally unmask dopamine excess (anxiety, agitation, insomnia), which is why lower starting doses with gradual increases are described. The same caution applies to iron repletion in patients on selective serotonin reuptake inhibitors — some develop transient activation or akathisia as serotonin synthesis catches up with reuptake blockade.
- Constipation and gastrointestinal tolerability: The leading cause of iron-supplementation failure is gastrointestinal intolerance. Alternate-day dosing, taking iron with food (at the cost of some absorption), ferrous bisglycinate, or splitting to smaller divided doses all help.
Key Research Papers
- Lozoff B, Jimenez E, Hagen J, Mollen E, Wolf AW (2000). Poorer behavioral and developmental outcome more than 10 years after treatment for iron deficiency in infancy. Pediatrics. — PubMed PMID: 10742372
- Lozoff B, Beard J, Connor J, Felt B, Georgieff M, Schallert T (2006). Long-lasting neural and behavioral effects of iron deficiency in infancy. Nutrition Reviews. — PubMed PMID: 16770951
- Murray-Kolb LE, Beard JL (2007). Iron treatment normalizes cognitive functioning in young women. American Journal of Clinical Nutrition. — PubMed PMID: 17344500
- Konofal E, Lecendreux M, Arnulf I, Mouren MC (2004). Iron deficiency in children with attention-deficit/hyperactivity disorder. Archives of Pediatrics and Adolescent Medicine. — PubMed PMID: 15583094
- Konofal E, Lecendreux M, Deron J, Marchand M, Cortese S et al. (2008). Effects of iron supplementation on attention deficit hyperactivity disorder in children. Pediatric Neurology. — PubMed PMID: 18054688
- Allen RP, Earley CJ (2007). The role of iron in restless legs syndrome. Movement Disorders. — PubMed PMID: 17566122
- Earley CJ, Connor J, Garcia-Borreguero D, Jenner P, Winkelman J et al. (2014). Altered brain iron homeostasis and dopaminergic function in Restless Legs Syndrome. Sleep Medicine. — PubMed PMID: 25201131
- Allen RP, Picchietti DL, Auerbach M et al. (2018). Evidence-based and consensus clinical practice guidelines for the iron treatment of restless legs syndrome/Willis-Ekbom disease in adults and children: an IRLSSG task force report. Sleep Medicine. — PubMed PMID: 29425576
- Beard JL, Connor JR (2003). Iron status and neural functioning. Annual Review of Nutrition. — PubMed PMID: 12704220
- Georgieff MK (2011). Long-term brain and behavioral consequences of early iron deficiency. Nutrition Reviews. — PubMed PMID: 22043882
- Wenger MJ, DellaValle DM, Murray-Kolb LE, Haas JD (2019). Effect of iron deficiency on simultaneous measures of behavior, brain activity, and energy expenditure in the performance of a cognitive task. Nutritional Neuroscience. — PubMed PMID: 28784049
- Beard J (2003). Iron deficiency alters brain development and functioning. Journal of Nutrition. — PubMed PMID: 12730445
- Murray-Kolb LE (2011). Iron status and neuropsychological consequences in women of reproductive age: what do we know and where are we headed? Journal of Nutrition. — PubMed PMID: 21346109
- Lozoff B, Brittenham GM, Wolf AW, McClish DK, Kuhnert PM et al. (1987). Iron deficiency anemia and iron therapy effects on infant developmental test performance. Pediatrics. — PubMed PMID: 2438638
- Lozoff B, Smith JB, Kaciroti N, Clark KM, Guevara S, Jimenez E (2013). Functional significance of early-life iron deficiency: outcomes at 25 years. Journal of Pediatrics. — PubMed PMID: 23827739
- Gahagan S, Delker E, Blanco E, Burrows R, Lozoff B (2019). Randomized Controlled Trial of Iron-Fortified versus Low-Iron Infant Formula: Developmental Outcomes at 16 Years. Journal of Pediatrics. — PubMed PMID: 31253407
- Winkelman JW, Berkowski JA, DelRosso LM, Koo BB, Scharf MT et al. (2025). Treatment of restless legs syndrome and periodic limb movement disorder: an American Academy of Sleep Medicine clinical practice guideline. Journal of Clinical Sleep Medicine. — PubMed PMID: 39324694
- Devos D, Labreuche J, Rascol O, Corvol JC, Duhamel A et al. (2022). Trial of Deferiprone in Parkinson's Disease. New England Journal of Medicine. — PubMed PMID: 36449420
- Ayton S, Barton D, Brew B, Brodtmann A, Clarnette R et al. (2025). Deferiprone in Alzheimer Disease: A Randomized Clinical Trial. JAMA Neurology. — PubMed PMID: 39495531
- Chen Z, Yang H, Wang D, Sudfeld CR, Zhao A et al. (2022). Effect of Oral Iron Supplementation on Cognitive Function among Children and Adolescents in Low- and Middle-Income Countries: A Systematic Review and Meta-Analysis. Nutrients. — PubMed PMID: 36558491
- Wang W, Tian L, Xu H, Zhou J, Geng M (2026). Essential Trace Elements Zinc, Iron, Copper and Attention-Deficit/Hyperactivity Disorder in Children and Adolescents: A Systematic Review and Meta-Analysis of Case-Control Studies. Nutrients. — PubMed PMID: 42280439
- Mei Z, Addo OY, Jefferds ME, Sharma AJ, Flores-Ayala RC, Brittenham GM (2021). Physiologically based serum ferritin thresholds for iron deficiency in children and non-pregnant women: a US National Health and Nutrition Examination Surveys (NHANES) serial cross-sectional study. The Lancet Haematology. — PubMed PMID: 34329578
- Li N, Zhao G, Wu W, Zhang M, Liu W et al. (2020). The Efficacy and Safety of Vitamin C for Iron Supplementation in Adult Patients With Iron Deficiency Anemia: A Randomized Clinical Trial. JAMA Network Open. — PubMed PMID: 33136134
- von Siebenthal HK, Gessler S, Vallelian F, Steinwendner J, Kuenzi UM et al. (2023). Alternate day versus consecutive day oral iron supplementation in iron-depleted women: a randomized double-blind placebo-controlled study. EClinicalMedicine. — PubMed PMID: 38021373
- Binda C, Newton-Vinson P, Hubálek F, Edmondson DE, Mattevi A (2002). Structure of human monoamine oxidase B, a drug target for the treatment of neurological disorders. Nature Structural Biology. — PubMed PMID: 11753429
- Vendelboe TV, Harris P, Zhao Y, Walter TS, Harlos K et al. (2016). The crystal structure of human dopamine β-hydroxylase at 2.9 Å resolution. Science Advances. — PubMed PMID: 27152332
- Padyana AK, Gross S, Jin L, Cianchetta G, Narayanaswamy R et al. (2019). Structure and inhibition mechanism of the catalytic domain of human squalene epoxidase. Nature Communications. — PubMed PMID: 30626872
PubMed Topic Searches
Connections
- All Minerals
- Iron Benefits Hub
- Iron Overview
- Iron Deficiency Anemia
- Heme vs Non-Heme Iron
- Iron and Athletic Performance
- Copper
- Hemoglobin and Ceruloplasmin
- Zinc
- Vitamin C
- Vitamin B12
- Folate (B9)
- L-Tyrosine
- L-Tryptophan
- Fatigue
- Restless Legs Syndrome
- Parkinson's Disease
- Iron Panel
- Whole Food Copper Sources
- Organ Meats
- Deficiency
- Toxicity
- History
- Sources