Comfrey: Topical Use for Sprains and Bruises
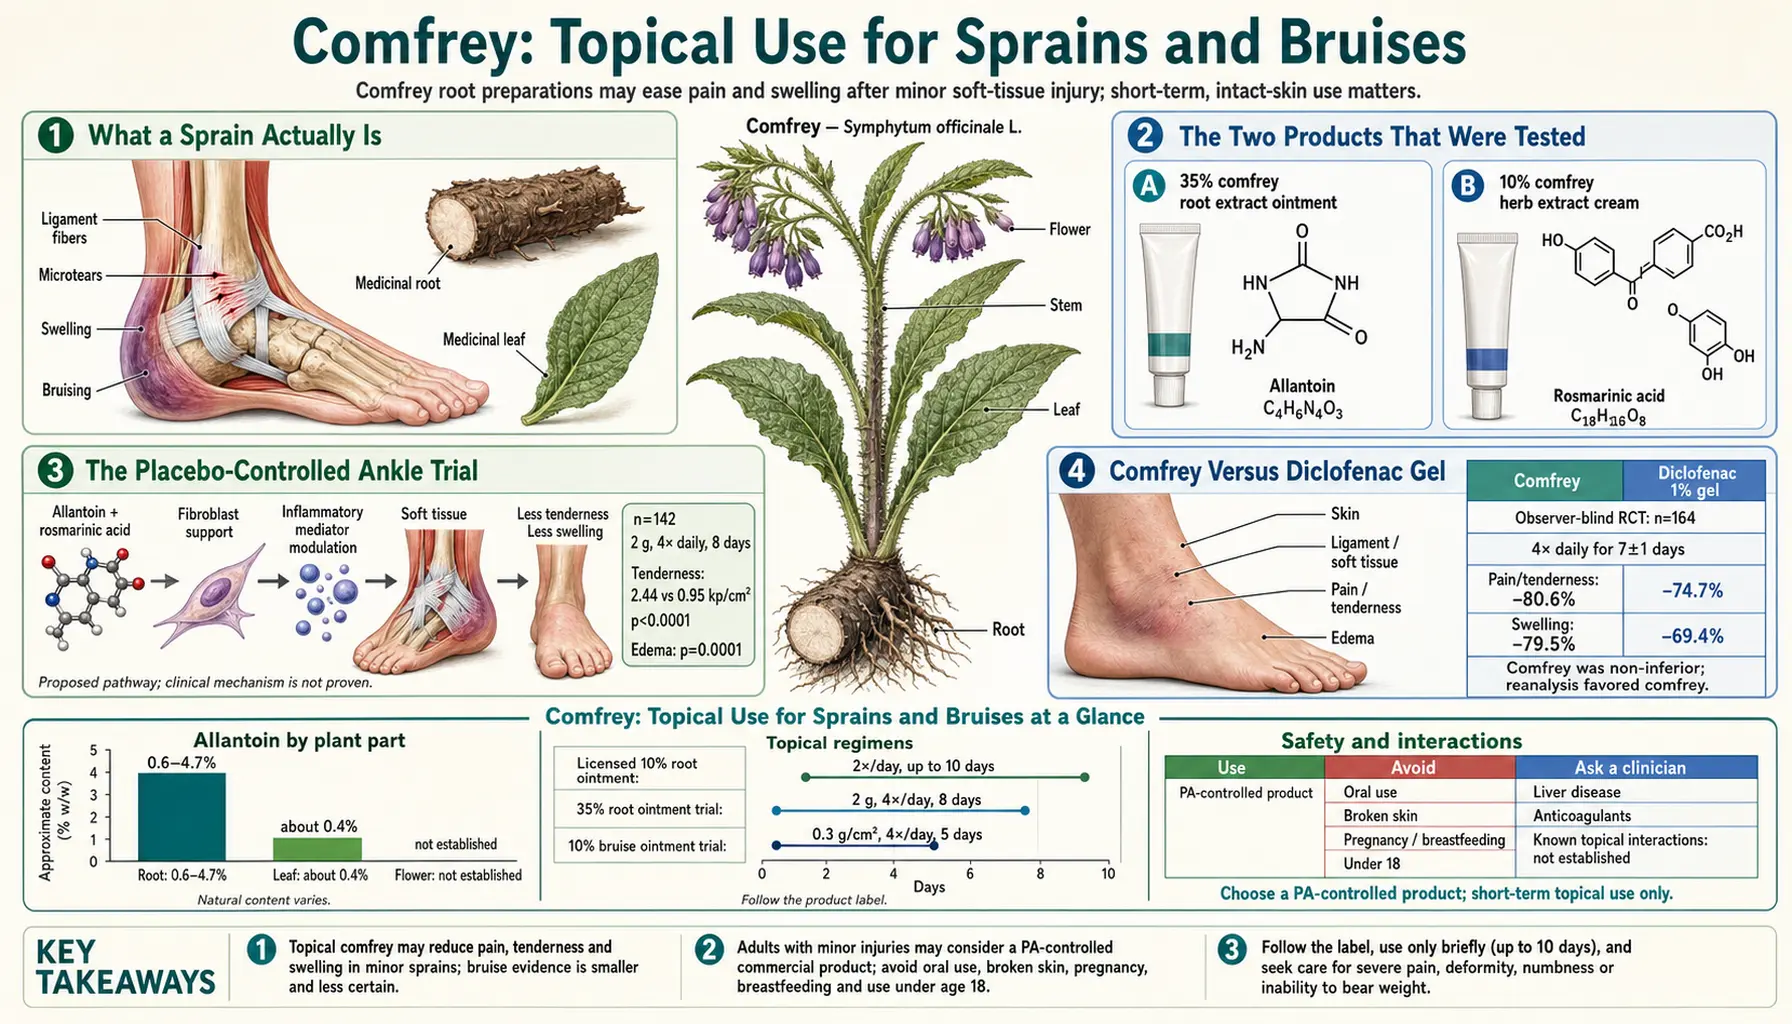
You rolled your ankle. It is swollen, it hurts to put weight on it, and someone has handed you a tube of comfrey cream. The reasonable question is whether that tube does anything a bag of frozen peas would not.
The answer, unusually for a herbal remedy, is yes — and the evidence is specific enough to be worth reading in detail. Standardized comfrey preparations have been tested in three randomised controlled trials of acute ankle sprain, with 142, 164 and 203 patients. One of those trials compared comfrey directly with diclofenac gel, the standard pharmacy anti-inflammatory rub, and comfrey was not beaten (its data were later published a second time as a re-analysis). That is a stronger evidence base than most over-the-counter topical products carry.
⚠ Before any of that matters, the fact that governs this whole herb: comfrey is used on the outside of the body only, because swallowing it is the dangerous use. It contains pyrrolizidine alkaloids, which cause irreversible and sometimes fatal liver injury when swallowed — documented in human deaths, including from comfrey tea. Oral comfrey products have been removed from the market or restricted in the United States, the United Kingdom, Germany, Canada and Australia. Those alkaloids also cross broken skin, so the European herbal monograph limits even a topical product to intact skin and a short course (typically no more than 10 days), and lists it as not recommended in pregnancy, breastfeeding or under 18 years of age.
Table of Contents
- What a Sprain Actually Is
- The Two Products That Were Tested
- The Placebo-Controlled Ankle Trial
- Comfrey Versus Diclofenac Gel
- The Dose-Response Trial
- Bruises and Blunt Injury
- Why It Would Work at All
- How It Was Used in the Trials
- What It Will Not Do: Bones
- The Honest Limits of This Evidence
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
What a Sprain Actually Is
A sprain is a stretched or partly torn ligament — the tough fibrous band that holds two bones together at a joint. Roll your foot inward and you typically injure the anterior talofibular ligament on the outside of the ankle, which is why the swelling and the tender spot sit just in front of and below the bony knob of your outer ankle.
What hurts is not really the torn fibres themselves. Within minutes, damaged cells release inflammatory mediators; small blood vessels leak; fluid and inflammatory cells flood the tissue. The joint swells, the pressure rises, and nerve endings that were quiet become exquisitely sensitive. That is why a sprain often hurts more two hours later than at the moment of injury.
So a topical treatment has two plausible jobs: reduce the inflammatory response, and reduce the pain signal. It does not need to repair the ligament — the body does that over weeks regardless. It needs to make the first week bearable and get the joint moving sooner, because early controlled movement is what actually prevents a stiff, chronically unstable ankle. The trials below measured exactly that: pain, swelling, and range of motion.
The Two Products That Were Tested
Every one of these trials used a defined commercial preparation, and the two differ enough that the difference matters.
- Comfrey root ointment (a German product). A fluid extract of Symphytum officinale root in an ointment base. The root is the alkaloid-rich part of the plant, so the extract is processed to reduce pyrrolizidine alkaloid content.
- Comfrey herb cream (a German product). A cream containing 10 % of a 2.5:1 aqueous-ethanolic pressed concentrate of freshly harvested aerial parts of Symphytum × uplandicum Nyman — equivalent to about 25 g of fresh herb per 100 g of cream. The manufacturer uses a selected cultivar and specifies the alkaloid content as below the limit of detection.
This distinction is not pedantry. A jar of home-made salve simmered from comfrey root you dug out of the garden is a different product from either: unknown extract strength, unknown alkaloid load, and made from the part of the plant with the most alkaloid in it. The trial results do not transfer to it.
The Placebo-Controlled Ankle Trial
The cleanest single piece of evidence is a multicentre, randomised, double-blind, placebo-controlled trial published in Phytomedicine in 2004 by Koll and colleagues.
- Who: 142 patients with unilateral acute ankle sprain, mean age 31.8 years, 78.9 % male — a sports-injury population.
- What: comfrey root ointment or an identical-looking placebo ointment, applied four times a day for 8 days.
- How measured: pain was quantified with a tonometer — a calibrated instrument that presses on the injured area with a known force, so the reading is not just a patient’s impression. Swelling was measured with the figure-of-eight tape method around the ankle. Mobility used the neutral-zero method.
- Result: comfrey beat placebo on pain (p<0.0001, the primary endpoint) and on ankle oedema (p=0.0001), with significant differences in mobility and global efficacy as well. No adverse drug reactions were reported in the active group.
Two things make this trial better than the average herbal study. The primary outcome was an instrument reading rather than a questionnaire, and the design was double-blind against a matched placebo ointment — which matters, because rubbing anything on a sore ankle four times a day produces a real placebo effect through massage, attention and expectation.
Comfrey Versus Diclofenac Gel
The trial people actually want to know about compared comfrey with the thing they would otherwise buy.
Predel and colleagues (Phytomedicine, 2005) ran an observer-blind, randomised, multicentre trial in 164 outpatients with acute unilateral ankle sprain, mean age 29, split evenly: 82 received a 6 cm strip of comfrey root ointment, 82 received diclofenac gel containing 1.16 g of diclofenac diethylamine salt, both four times daily for 7 ± 1 days. The primary outcome was the area under the curve of tonometer-measured pressure pain over the treatment week.
The trial was designed as a non-inferiority study — the question was whether comfrey was not worse than diclofenac, not whether it was better. It passed: the 95 % confidence interval for the difference lay entirely above the non-inferiority margin, and the authors noted the direction of the secondary outcomes favoured comfrey.
A follow-up publication (D’Anchise and colleagues, Arzneimittelforschung, 2007) re-analysed the same 164-patient dataset for superiority rather than non-inferiority, and reported a mean difference of +61.1 h·N/cm² in comfrey’s favour (95 % confidence interval (CI) 19.08 to 103.09), concluding comfrey was superior. The 2005 paper had given the confidence interval as 19.01 to 103.09 — essentially the same interval, which shows plainly that both papers rest on one dataset. This is important to read correctly: it is one trial reported twice, not two independent trials. Re-analysing an existing dataset with a different hypothesis is a weaker form of evidence than pre-specifying superiority from the start, and in any count of “how many studies show comfrey beats diclofenac” it is one, not two.
Even read conservatively, though, the finding is meaningful. Diclofenac gel is a real drug with real efficacy in soft-tissue injury. A plant extract matching it in a head-to-head trial with instrument-based endpoints is a genuine result.
The Dose-Response Trial
The third ankle trial (Kucera and colleagues, Wiener Medizinische Wochenschrift, 2004) took a different and rather clever approach. Instead of comparing comfrey with an inert placebo, it compared a 10 % comfrey herb cream against a 1 % version of the same cream — 203 patients with acute ankle distortion, 104 on the strong version and 99 on the weak one.
The strong cream produced significantly better reductions in pain on movement, pain at rest, and functional impairment at days 3–4 and day 7 (p<0.001), and better reduction of swelling at days 3–4 (p<0.01). Physicians rated efficacy good to excellent in 85.6 % of the high-dose group versus 65.7 % of the low-dose group.
The strength of this design is that it demonstrates a dose-response relationship — more comfrey, more effect — which is one of the classic arguments that a drug is doing something real rather than reflecting expectation. Its weakness is that the “control” still contained comfrey, so the trial cannot tell you how much of the benefit in either arm was placebo. Notice, too, that the 65.7 % rating in the 1 % arm is itself high — sprains improve on their own, and quickly.
Bruises and Blunt Injury
Here honesty requires a step down in confidence. Comfrey is traditionally the bruise herb — the old name bruisewort is as common as knitbone — and comfrey creams are widely marketed for bruising. But there is no independent randomised controlled trial of comfrey for bruises as a standalone condition. A 2012 overview written by an author affiliated with the root ointment’s manufacturer states that randomised trials showed efficacy for “sprains, contusions and strains after sports injuries and accidents”, grouping bruises (contusions) together with sprains and strains. What exists is:
- Ankle sprain trials, which are blunt soft-tissue injuries and do involve bruising and swelling, where comfrey measurably reduced oedema.
- A myalgia trial in 215 patients showing reduced muscle pain, which is closely related to the deep soreness of a contusion.
- An abrasion-healing trial in 278 patients, covered in the wound-healing article.
Applying comfrey to a bruise is therefore a reasonable extrapolation from adjacent evidence, not a demonstrated indication. For bruise-specific trial data, arnica has been studied more directly, and a Cochrane review found arnica gel performed similarly to ibuprofen gel in hand osteoarthritis. Comfrey’s trial evidence is in sprains, back pain and knee osteoarthritis.
Why It Would Work at All
For years the obvious criticism of these trials was that nobody could say how a comfrey ointment could reduce swelling. That gap has now largely closed.
A 2019 study in Frontiers in Pharmacology exposed primary human endothelial cells — the cells lining blood vessels, which orchestrate the leaky, sticky, inflamed state around an injury — to interleukin-1, then treated them with a hydroalcoholic comfrey root extract. The extract dose-dependently suppressed the pro-inflammatory programme: E-selectin, vascular cell adhesion molecule-1 (VCAM-1), intercellular adhesion molecule-1 (ICAM-1) and cyclooxygenase-2 (COX-2) expression all fell. Those are precisely the adhesion molecules that recruit white cells into injured tissue, plus the enzyme that non-steroidal anti-inflammatories inhibit.
The extract achieved this by blocking nuclear factor kappa B (NF-κB), the master transcriptional switch for inflammation, at two separate steps: it dampened activation of the IκB kinases (IKK1/2) and the resulting breakdown of the inhibitor protein IκBα, and it separately interfered with the p65 subunit’s shuttling into the nucleus and its transcriptional activity. Notably, the mucilage-depleted fraction was more active than the whole extract — so the slippery polysaccharides that make comfrey feel soothing are not the anti-inflammatory part.
Alongside that, comfrey root contains rosmarinic acid and other phenolic acids with antioxidant activity, and allantoin, which stimulates cell proliferation. That is a coherent package for a soft-tissue injury: less inflammatory signalling, less oxidative stress, more tissue turnover. It is cell-culture work rather than human pharmacokinetics, and it does not prove the same thing happens under a layer of skin — but it removes the “there is no plausible mechanism” objection.
How It Was Used in the Trials
The trials used defined amounts, frequencies and durations:
| Question | What the trials used |
|---|---|
| How much? | Roughly a 6 cm strip of ointment per application in the diclofenac comparison; about 2 g per application in the knee osteoarthritis work. A layer thick enough to cover the injured area, not rubbed in to invisibility. |
| How often? | Four times a day in the ankle trials; three times a day in the back-pain and knee trials. |
| For how long? | 7 to 8 days in the ankle sprain trials. The European herbal monograph for comfrey root caps self-treatment at about 10 days. |
| Where? | Over the injured area, on intact skin only. Not on grazes, cuts, blisters or broken skin. |
| How soon? | Trials started treatment within a day or two of injury. The back-pain trial detected an effect within an hour of the first application. |
| With what else? | Comfrey is an add-on, not a replacement for rest, ice, compression, elevation and early controlled movement. |
Reading a label. A fully labelled product states the species (Symphytum officinale or S. × uplandicum), the plant part (root or herb), the extract ratio or the percentage of concentrate, and something explicit about pyrrolizidine alkaloid content — “PA-free,” “alkaloid content below the limit of detection,” or a stated maximum in micrograms. A label that says only “comfrey extract” in a proprietary blend gives none of this. Prices are roughly those of a diclofenac gel; what separates products is disclosure, not cost.
Availability. In Germany and much of the EU, comfrey root preparations for external use are registered traditional herbal medicines with defined labelling. In the United States they are sold as cosmetics, which means no equivalent regulatory scrutiny of the extract — and the specific products used in these trials are often not the ones on the shelf. Some manufacturers publish their alkaloid testing; others do not.
What It Will Not Do: Bones
The folk name is knitbone, and the tradition — going back to Dioscorides — held that a comfrey poultice bound over a fracture would help the bone fuse. The Greek genus name Symphytum itself means roughly “to grow together.”
There is no human trial showing that comfrey speeds fracture healing. Not a small one, not a poor one — none. What comfrey has been shown to do is reduce pain, swelling and stiffness in the soft tissue around an injury, which would make a splinted limb more comfortable without touching the bone. Given that a poultice sits on the skin and a fracture line sits centimetres deeper under muscle and periosteum, the folk claim was always mechanically improbable.
This matters practically. A fracture is diagnosed by imaging and treated by immobilisation, and a fracture treated only with a herbal ointment can heal crookedly. Inability to bear weight, deformity, bony point tenderness over the malleolus or the base of the fifth metatarsal, and pain out of proportion are the signs used to decide on an X-ray. The comfrey trials enrolled sprains, not fractures.
The Honest Limits of This Evidence
- Sponsorship. The ankle trials were run or authored by staff at, or investigators working with, the companies that make the two products. Industry-sponsored trials systematically report larger effects, so every number here is best read as an upper estimate.
- Independent replication is thin. No independent research group has repeated these trials with its own funding. An independent scoping review of comfrey’s external uses reached exactly this conclusion — promising, methodologically limited, and in need of research the manufacturers did not pay for. It included 26 studies (13 randomised controlled trials, 5 non-randomised trials and 8 observational studies); most trials had an unclear risk of bias because of poor reporting, and few adverse events were reported.
- One dataset, two papers. The 2005 non-inferiority paper and the 2007 superiority paper describe the same 164 patients.
- Short horizons. Nothing here runs longer than about three weeks. That matches the European monograph’s limit of about 10 days of self-treatment — but it means there is no evidence at all about repeated or long-term use, which is precisely where cumulative alkaloid exposure would matter.
- Product-specific. These results belong to two specific German preparations. A generic “comfrey cream” of unknown strength is untested.
- Sprains get better anyway. Most ankle sprains improve substantially within one to two weeks with no treatment. Comfrey shortens the miserable part; it does not change the destination.
Cautions and Contraindications
⚠ Swallowed comfrey, in any form, is the dangerous use. Tea, capsules, tincture and eaten leaves all deliver the alkaloids. Pyrrolizidine alkaloids cause hepatic veno-occlusive disease (blocked small veins in the liver), which is often irreversible and has killed people. See Comfrey Taken Internally.
- Intact skin only. Percutaneous absorption of comfrey’s alkaloids has been measured directly in animals. Intact skin is a real barrier — oral dosing produced 20 to 50 times more urinary alkaloid excretion than dermal dosing in that study — but broken skin removes it. That rules out open wounds, cuts, grazes, ulcers, weeping eczema and mucous membranes.
- Short course. About 10 days of self-treatment is the standard European limit for comfrey root preparations, and German dosing rules additionally cap external use at roughly four to six weeks total per year.
- Pregnancy and breastfeeding. Pyrrolizidine alkaloids cross the placenta and enter breast milk, and the developing liver is the target organ. This applies to topical use too.
- Children. The European Medicines Agency (EMA) herbal monograph for comfrey root states that use under 18 years of age is not recommended. Children have far more skin surface per kilogram of body weight than adults, so the same smear delivers a proportionally larger dose. An open study of a comfrey herb (not root) cream treated 712 children for bruises and sports injuries for up to 2 weeks — 386 on intact skin and 326 with grazes or shallow wounds: no reactions occurred on intact skin and one burning and reddening reaction on broken skin (0.14 %). The study had no comparison group, was short, and measured skin tolerance only, not alkaloid exposure or the liver.
- Liver disease — hepatitis, cirrhosis, fatty liver disease — or medication that already stresses the liver adds to the burden on the organ the alkaloids damage.
- Occlusive dressings. Covering the area with an airtight dressing increases absorption of anything applied under it.
- Boraginaceae allergy. Contact dermatitis is uncommon but reported; the small American knee trial saw two participants per active group develop temporary rash and itching.
- Drug interactions. There is no meaningful interaction data for topical comfrey, largely because systemic absorption of the active constituents is low. The theoretical concern is additive liver burden with methotrexate, azathioprine, isoniazid, high-dose paracetamol or any drug with known hepatotoxicity — and with any product that combines topical comfrey with an oral herbal blend.
- Eyes and mouth. The EMA monograph states that contact with the eyes or mucous membranes is to be avoided; cream left on the hands is the usual route there.
Key Research Papers
Every identifier below was verified live against NCBI E-utilities — title, first author, journal and year all had to match before a PMID link was written.
- Koll R, Buhr M, Dieter R, et al. Efficacy and tolerance of a comfrey root extract (Extr. Rad. Symphyti) in the treatment of ankle distorsions: results of a multicenter, randomized, placebo-controlled, double-blind study. Phytomedicine. 2004;11(6):470–477 — PubMed PMID: 15500257. — 142 patients; comfrey root ointment four times daily for 8 days beat placebo for pain and oedema, with no adverse drug reactions reported.
- Predel HG, Giannetti B, Koll R, Bulitta M, Staiger C. Efficacy of a comfrey root extract ointment in comparison to a diclofenac gel in the treatment of ankle distortions. Phytomedicine. 2005;12(10):707–714 — PubMed PMID: 16323288. — 164 patients, 82 per arm; comfrey confirmed non-inferior to diclofenac diethylamine gel over 7 days.
- D’Anchise R, Bulitta M, Giannetti B. Comfrey extract ointment in comparison to diclofenac gel in the treatment of acute unilateral ankle sprains (distortions). Arzneimittelforschung. 2007;57(11):712–716 — PubMed PMID: 18193693. — A superiority re-analysis of the same 164-patient dataset. Not an independent second trial.
- Kucera M, Barna M, Horáček O, Kováriková J, Kucera A. Efficacy and safety of topically applied Symphytum herb extract cream in the treatment of ankle distortion: results of a randomized controlled clinical double blind study. Wiener Medizinische Wochenschrift. 2004;154(21–22):498–507 — PubMed PMID: 15638067. — 203 patients; 10 % cream beat a 1 % version of itself, demonstrating dose-response but not placebo control.
- Kucera M, Barna M, Horàcek O, Kàlal J, Kucera A, Hladìkova M. Topical Symphytum herb concentrate cream against myalgia: a randomized controlled double-blind clinical study. Advances in Therapy. 2005;22(6):681–692 — PubMed PMID: 16510384. — 215 patients with back muscle pain; number needed to treat 3.2.
- Kucera M, Kálal J, Polesná Z. Effects of Symphytum ointment on muscular symptoms and functional locomotor disturbances. Advances in Therapy. 2000;17(4):204–210 — PubMed PMID: 11185060. — The earlier, smaller observational precursor to the myalgia work.
- Seigner J, Junker-Samek M, Plaza A, et al. A Symphytum officinale root extract exerts anti-inflammatory properties by affecting two distinct steps of NF-κB signaling. Frontiers in Pharmacology. 2019;10:289 — PubMed PMID: 31105555. — Cell culture. The mechanism study; the mucilage-depleted fraction was the more active one.
- Frost R, MacPherson H, O’Meara S. A critical scoping review of external uses of comfrey (Symphytum spp.) Complementary Therapies in Medicine. 2013;21(6):724–745 — PubMed PMID: 24280482. — The independent appraisal of the whole external-use literature.
- Frost R, O’Meara S, MacPherson H. The external use of comfrey: a practitioner survey. Complementary Therapies in Clinical Practice. 2014;20(4):347–355 — PubMed PMID: 25113427. — What practitioners actually do with comfrey, including on broken skin, which the authors flag as a safety concern.
- Staiger C. Comfrey: a clinical overview. Phytotherapy Research. 2012;26(10):1441–1448 — PubMed PMID: 22359388. — Comprehensive, but written by an author affiliated with the manufacturer of the trial ointment.
- Brauchli J, Lüthy J, Zweifel U, Schlatter C. Pyrrolizidine alkaloids from Symphytum officinale L. and their percutaneous absorption in rats. Experientia. 1982;38(9):1085–1087 — PubMed PMID: 7128756. — Animal study. Skin absorption is measurable; oral dosing gave 20 to 50 times higher urinary excretion.
- Cameron M, Chrubasik S. Topical herbal therapies for treating osteoarthritis. Cochrane Database of Systematic Reviews. 2013;(5):CD010538 — PubMed PMID: 23728701. — Not a sprain review, but the only fully independent systematic appraisal of any topical comfrey trial.
- Kucera A, Barna M, Holcova S, Horacek O, Hladiková M, Ottillinger B. Tolerability and effectiveness of an antitrauma cream with comfrey herb extract in pediatric use with application on intact and on broken skin. International Journal of Pediatrics and Adolescent Medicine. 2018;5(4):135–141 — PubMed PMID: 30805549. — Open study, 712 children, herb cream; one local reaction, on broken skin.
PubMed Topic Searches
- PubMed: Comfrey and ankle sprain
- PubMed: Symphytum officinale ointment
- PubMed: Comfrey versus diclofenac
- PubMed: Topical NSAIDs for soft-tissue injury
- PubMed: Ankle sprain treatment trials
- PubMed: Rosmarinic acid anti-inflammatory activity
- PubMed: Arnica for bruising
- PubMed: Comfrey percutaneous absorption
Connections
- All Herbs
- Comfrey Benefits — hub
- Comfrey — main topic page
- Osteoarthritis and Back Pain
- Wound Healing and Allantoin
- ⚠ Comfrey Taken Internally
- Orthopedics — sprains, strains and joint injury
- Butterbur — the other alkaloid-bearing herb
- Calendula — for skin that is actually broken
- Marshmallow Root — mucilage without the alkaloids