Slippery Elm for Digestive & Gut Health
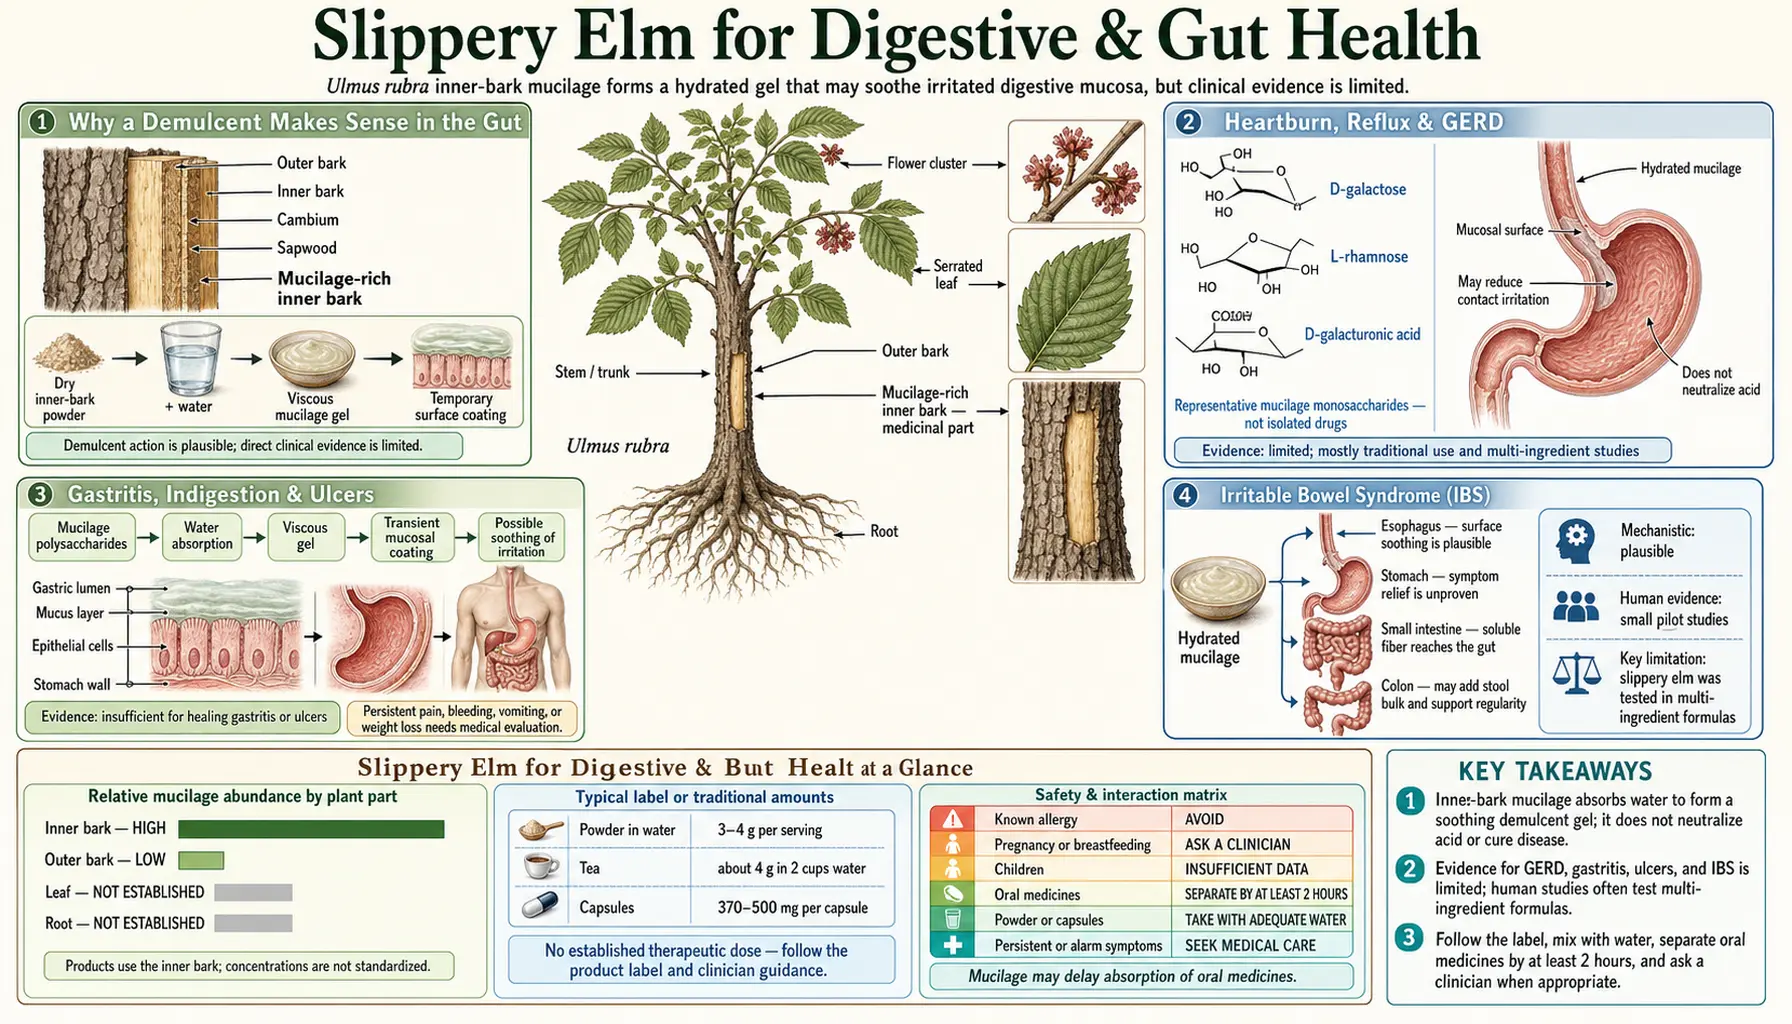
Of all slippery elm's traditional uses, the digestive ones are the most enduring — and the most reasonable. The inner bark's mucilage swells into a soft gel that can coat the lining of the esophagus, stomach, and intestine, which is exactly why generations of herbalists reached for it in heartburn, indigestion, irritable bowel, and inflammatory gut conditions. This page lays out the demulcent rationale honestly: what the coating plausibly does, slippery elm's role in classic gut formulas such as “Robert's Formula,” the handful of small human trials (nearly all of multi-herb blends, not slippery elm alone), and the preclinical antioxidant and anti-inflammatory signals from elm-bark extracts. It also draws a clear line between soothing a symptom and treating its cause — because reflux, irritable bowel syndrome (IBS), and inflammatory bowel disease (IBD) all deserve a real diagnosis, not just a coating.
Table of Contents
- Why a Demulcent Makes Sense in the Gut
- Heartburn, Reflux & Gastroesophageal Reflux Disease
- Gastritis, Indigestion & Ulcers
- Irritable Bowel Syndrome (IBS)
- Inflammatory Bowel Disease (IBD)
- Slippery Elm and Gut Bacteria in a Laboratory Study
- Robert's Formula & Gut-Soothing Blends
- What the Human Evidence Actually Shows
- How People Use It & Practical Cautions
- Key Research Papers
- External Resources
- Connections
- Featured Videos
Why a Demulcent Makes Sense in the Gut
The digestive tract is a long tube lined with delicate mucous membrane. That lining is normally protected by its own mucus layer, but heartburn, infection, medications like nonsteroidal anti-inflammatory drugs (NSAIDs), and chronic inflammation can all leave it raw and irritated. A demulcent works by adding a second, borrowed layer of protection: when slippery elm mucilage meets moisture, it forms a slick gel that clings to the mucosa.
The rationale is intuitive and mechanistically plausible. If a coating physically separates inflamed tissue from acid, rough food, or friction, the surface gets a chance to calm down. Modern gastroenterology uses the very same idea in evidence-based products — alginate rafts (which float on stomach contents and shield the esophagus) and sucralfate (which sticks to ulcer craters). Slippery elm is the traditional, botanical cousin of these agents. The crucial difference is the depth of testing: alginates and sucralfate have been through many controlled trials, while slippery elm has been through very few. So the mechanism is credible; the clinical proof is thin. Both facts are true at once, and this page keeps them both in view.
Heartburn, Reflux & Gastroesophageal Reflux Disease
Gastroesophageal reflux disease (GERD) happens when stomach acid washes back up into the esophagus, whose lining is not built to withstand it. The result is heartburn, regurgitation, and, over time, inflammation of the esophageal wall. Herbalists have long suggested slippery elm before or after meals on the theory that its gel coats and soothes the irritated esophagus and may buffer the sensation of acid.
There is a genuine scientific thread here, even though it does not come from slippery elm trials directly. Researchers have shown that the topical integrity of the esophageal mucosa can be protected by surface agents, and that alginate-based coatings measurably shield esophageal cells from acid-and-pepsin damage in laboratory models. In the 2015 coating study by Woodland and colleagues, esophageal tissue samples (biopsies) from 12 patients were coated either with an alginate solution or with a plain thick (viscous) control solution, then exposed to acid an hour later. The tissue's electrical resistance, a measure of how intact its barrier is, fell by 8.3% under the alginate coating against 25.1% under the plain thick solution. Being thick and slippery alone therefore gave much less protection than the alginate — a point that matters for a mucilage like slippery elm, which was not itself tested. Those studies validate the general principle — a physical coating can protect the esophagus — without proving that slippery elm specifically does the job as well as a purpose-built alginate. Modern gastroesophageal reflux disease management is also clear that persistent reflux needs proper evaluation, because untreated inflammation can progress to ulceration and, rarely, precancerous change.
A 2019 review of popular remedies for heartburn and other esophageal symptoms by Ahuja and Ahuja included slippery elm, licorice and peppermint oil among the herbal products it covered. It found that “a substantial gap persists” between what people report about most of these remedies and what has been tested.
In this picture, slippery elm is a comfort measure for occasional heartburn, used apart from other medicines, alongside the standard tools (weight management, meal timing, not eating late, and, where indicated, acid-suppressing therapy). It does not replace the investigation of frequent reflux or of reflux with alarm symptoms.
Gastritis, Indigestion & Ulcers
The same coating logic extends to the stomach itself. In traditional practice, slippery elm gruel was a classic food-medicine for an inflamed or ulcerated stomach — bland, soothing, and easy to keep down when appetite fails. For gastritis and functional dyspepsia (indigestion with no structural cause), the gruel served double duty as gentle nourishment and a soothing layer.
It is important to be candid about what has changed. Most peptic ulcers are now known to be caused by Helicobacter pylori infection or by nonsteroidal anti-inflammatory drug (NSAID) use, and they are cured by targeting those causes — antibiotics for the bacterium, acid suppression, and stopping the offending drug. Slippery elm does nothing to eradicate H. pylori. So a demulcent may ease the discomfort of an irritated stomach, but it does not treat these causes, which a medical work-up looks for. Preclinical studies of elm-bark extracts show antioxidant and anti-inflammatory activity in cells and animals, which is encouraging background biology but not evidence of ulcer healing in people.
Irritable Bowel Syndrome (IBS)
Irritable bowel syndrome is a functional disorder of gut sensation and motility — abdominal pain with altered bowel habits, and no visible damage on scans or scopes. Because slippery elm both soothes the gut lining and adds soluble, gel-forming fiber, it has a plausible dual role: comfort for a hypersensitive gut and stool-normalizing bulk. In practice, herbalists tend to use it more for the constipation-predominant and mixed subtypes, where its soluble fiber can soften and regulate stools.
The most relevant human data come from a small Australian pilot study by Hawrelak and Myers, which tested two whole formulas — and both contained slippery elm alongside other agents. The study recruited 31 people with irritable bowel syndrome in Australia in 2001 and was open-label and uncontrolled, with no placebo group. The formula for constipation-predominant irritable bowel syndrome (slippery elm bark, lactulose, oat bran and licorice root; 10 patients) was followed by a 20% increase in bowel-movement frequency and by significant improvements in stool consistency, straining, abdominal pain, bloating and overall symptom severity; lactulose in that formula is itself a laxative. The formula for diarrhea-predominant and alternating irritable bowel syndrome (bilberry fruit, slippery elm bark, agrimony and cinnamon; 21 patients) did not improve bowel habit, in the authors' conclusion, though it significantly reduced straining, abdominal pain, bloating, flatulence and overall symptoms. This is a genuine, published signal, but it comes with heavy caveats: it was a small, uncontrolled pilot, and because slippery elm was only one ingredient in a blend, its individual contribution cannot be separated out. A later study by Ried and colleagues (2020) of a different multi-herb digestive powder (which also included slippery elm) reported improvements in upper and lower gastrointestinal (GI) symptoms in adults with digestive complaints — again a formula, not slippery elm alone. The powder combined curcumin, aloe vera, slippery elm, guar gum, pectin, peppermint oil and glutamine. It was a 16-week before-and-after study without a placebo group: after a control phase, participants took 5 g and then 10 g a day of the formula, 43 people completed it, and the frequency and severity of symptoms such as indigestion, heartburn, nausea, constipation or diarrhea and abdominal pain improved by 60%–80%.
Honest bottom line for irritable bowel syndrome: slippery elm is a low-risk, plausibly helpful soluble-fiber demulcent that some people find settling, and it appears in formulas with modest pilot-level evidence — but there is no rigorous trial isolating slippery elm itself for irritable bowel syndrome.
Inflammatory Bowel Disease (IBD)
Unlike irritable bowel syndrome, inflammatory bowel disease — Crohn's disease and ulcerative colitis — involves real, immune-driven tissue damage that can lead to serious complications. In this setting a demulcent is a comfort measure only; no study shows that it changes the course of the disease.
The most cited laboratory work is Langmead and colleagues' in vitro study of herbal remedies used by inflammatory bowel disease patients, which found that several — slippery elm among them — had measurable antioxidant activity and could reduce reactive oxygen species in intestinal tissue models. Separately, extracts of the related East Asian elm Ulmus davidiana have shown anti-inflammatory and immune-modulating effects on macrophages and mouse intestinal immune cells, and a 116-kDa glycoprotein isolated from the stems of the same East Asian elm (Ulmus davidiana, not slippery elm) reduced the inflammatory cytokines tumor necrosis factor-alpha and interleukin-6 in a chemical model of early colon tumorigenesis in mice. These are legitimate preclinical findings that make the “soothing plus mild anti-inflammatory” story biologically coherent.
But preclinical is not clinical. None of this shows that slippery elm induces or maintains remission in human inflammatory bowel disease. For people with Crohn's disease or ulcerative colitis, the evidence places slippery elm in the “may soothe symptoms” category; it has not been tested as a replacement for prescribed treatment.
Slippery Elm and Gut Bacteria in a Laboratory Study
A 2018 laboratory study by Peterson and colleagues added slippery elm bark (Ulmus rubra), licorice and the Ayurvedic blend triphala to cultures of human stool bacteria grown without oxygen. Each herb shifted the mix of bacteria in its own way. Slippery elm and triphala significantly increased the share of bacteria that make butyrate, a short-chain fatty acid that colon cells use as fuel, and the herbs as a group increased Bifidobacterium and Lactobacillus species while reducing some potential disease-causing bacteria. This was a test-tube study, not a human trial; the authors wrote that clinical trials will be needed to test whether the same happens in people.
Robert's Formula & Gut-Soothing Blends
Slippery elm rarely appears alone in traditional gut medicine. Its classic home is Robert's Formula, a naturopathic combination handed down through the Eclectic and naturopathic traditions for inflamed or ulcerated digestive tissue. Recipes vary, but a typical version pairs slippery elm and marshmallow root (both demulcents) with an astringent (such as geranium or bayberry), an anti-inflammatory or antimicrobial (such as goldenseal or Echinacea), a carminative (such as cabbage powder or okra), and sometimes a laxative or bitter. The philosophy is layered: coat and soothe, tone and tighten, and calm inflammation all at once.
Modern digestive blends echo this design — the formulas tested in the pilot studies above combined slippery elm with other soothing and motility-supporting botanicals. The strength of a formula is also its scientific weakness: blends may work better than single herbs in practice, but they make it impossible to know how much credit slippery elm deserves. When you read that “slippery elm helped in a study,” it is almost always a formula that helped.
What the Human Evidence Actually Shows
Pulling the threads together, here is the state of the evidence in plain terms:
- Strong tradition, weak trials. Slippery elm has centuries of documented use for digestive irritation, but only a few small human studies, almost all of multi-herb formulas.
- Plausible mechanism. The demulcent coating idea is supported indirectly by mucosal-protection research on purpose-built agents (alginates, sucralfate), and by antioxidant/anti-inflammatory findings in elm-bark cell and animal models.
- No isolated randomized trial. There is, at the time of writing, no well-powered randomized controlled trial of slippery elm by itself for gastroesophageal reflux disease, irritable bowel syndrome, or inflammatory bowel disease.
- Low risk, modest expectation. Taken sensibly, slippery elm is very well tolerated. The reasonable expectation is symptom comfort, not cure.
That combination — safe, plausible, under-studied — is precisely why slippery elm endures as a folk remedy while remaining absent from formal treatment guidelines. On this evidence, its realistic role is a gentle adjunct with modest expectations.
How People Use It & Practical Cautions
Traditional digestive preparations include a warm gruel (1–2 teaspoons of inner-bark powder whisked into hot water or plant milk), a tea, capsules (often 400–500 mg), and chewable lozenges. Many people take it shortly before meals for reflux, or between meals for general gut soothing. See the companion Sources & Preparation page for full details on forms and dosing.
Two cautions matter most for gut use:
- Overlap with medicines. Because mucilage forms a coating and adds soluble fiber, slippery elm can slow or reduce the absorption of drugs taken at the same time. Taking it 1–2 hours apart from oral medicines avoids this overlap.
- A coating can mask alarm symptoms. Unintended weight loss, difficulty swallowing, vomiting blood, black stools, persistent vomiting, or a marked change in bowel habits are warning signs; vomiting blood and black stools are signs of bleeding that hospitals treat as urgent. A demulcent does not treat the causes of any of them.
Used within those limits, slippery elm is one of the gentler options in the herbal digestive toolkit, sitting comfortably beside other soothing plants such as licorice (as DGL), fenugreek, chamomile, and peppermint.
Key Research Papers
Slippery elm's digestive evidence base is small and mostly preclinical or formula-based. The papers below are real and directly relevant; note carefully which tested a blend rather than slippery elm alone.
- Hawrelak JA, Myers SP (2010). Effects of two natural medicine formulations on irritable bowel syndrome symptoms: a pilot study. Journal of Alternative and Complementary Medicine — PubMed PMID: 20954962
- Ried K, Travica N, Dorairaj R, Sali A (2020). Herbal formula improves upper and lower gastrointestinal symptoms and gut health in Australian adults with digestive disorders. Nutrition Research 76:37–51 — PubMed PMID: 32151878
- Langmead L et al. (2002). Antioxidant effects of herbal therapies used by patients with inflammatory bowel disease: an in vitro study. Alimentary Pharmacology & Therapeutics — PubMed PMID: 11860402
- Lee EH, Park CW, Jung YJ (2013). Anti-inflammatory and immune-modulating effect of Ulmus davidiana var. japonica Nakai extract on a macrophage cell line and immune cells in the mouse small intestine. Journal of Ethnopharmacology — PubMed PMID: 23384785
- Lee SJ et al. (2007). Inhibitory effect of phytoglycoprotein on TNF-alpha and IL-6 at the initiation stage of colon cancer in 1,2-dimethylhydrazine-treated ICR mice. Toxicology and Applied Pharmacology — PubMed PMID: 17868752
- Woodland P, Batista-Lima F, Lee C, Preston SL, Dettmar P, Sifrim D (2015). Topical protection of human esophageal mucosal integrity. American Journal of Physiology – Gastrointestinal and Liver Physiology 308(12):G975–80 — PubMed PMID: 25907692
- In vitro study of topical sodium alginate protection against peptic damage in treatment-resistant GERD (2024). International Journal of Molecular Sciences — PubMed PMID: 39409043
- Pharmacological management of gastro-esophageal reflux disease: state of the art in 2024. Expert Opinion on Pharmacotherapy — PubMed PMID: 39392340
- Gastrointestinal pharmacology: practical tips for the esophagologist (2020). Annals of the New York Academy of Sciences — PubMed PMID: 32822080
- Peterson CT, Sharma V, Uchitel S, Denniston K, Chopra D, Mills PJ, Peterson SN (2018). Prebiotic Potential of Herbal Medicines Used in Digestive Health and Disease. Journal of Alternative and Complementary Medicine 24(7):656–665 — PubMed PMID: 29565634
- Ahuja A, Ahuja NK (2019). Popular Remedies for Esophageal Symptoms: a Critical Appraisal. Current Gastroenterology Reports 21(8):39 — PubMed PMID: 31289950
- Drugs and Lactation Database (LactMed). Slippery Elm monograph. NCBI Bookshelf — Search PubMed
PubMed Topic Searches
External Resources
Connections
- All Herbs
- Slippery Elm Benefits Hub
- Slippery Elm for Throat & Cough
- Slippery Elm Sources & Preparation
- Slippery Elm (Main Page)
- Gastroesophageal Reflux Disease (Acid Reflux)
- Irritable Bowel Syndrome
- Inflammatory Bowel Disease
- Crohn's Disease
- Ulcerative Colitis
- Gastritis
- Peptic Ulcer Disease
- Functional Dyspepsia
- Small Intestinal Bacterial Overgrowth
- Licorice (DGL)
- Fenugreek