⚠ Evidence warning: Clinical trials or other evidence do not support the practitioner claims that particular manuka honey grades and dressing routines give reliable wound results. This page keeps it as a report of what people, websites or other media say.
Manuka Honey for Wound Healing
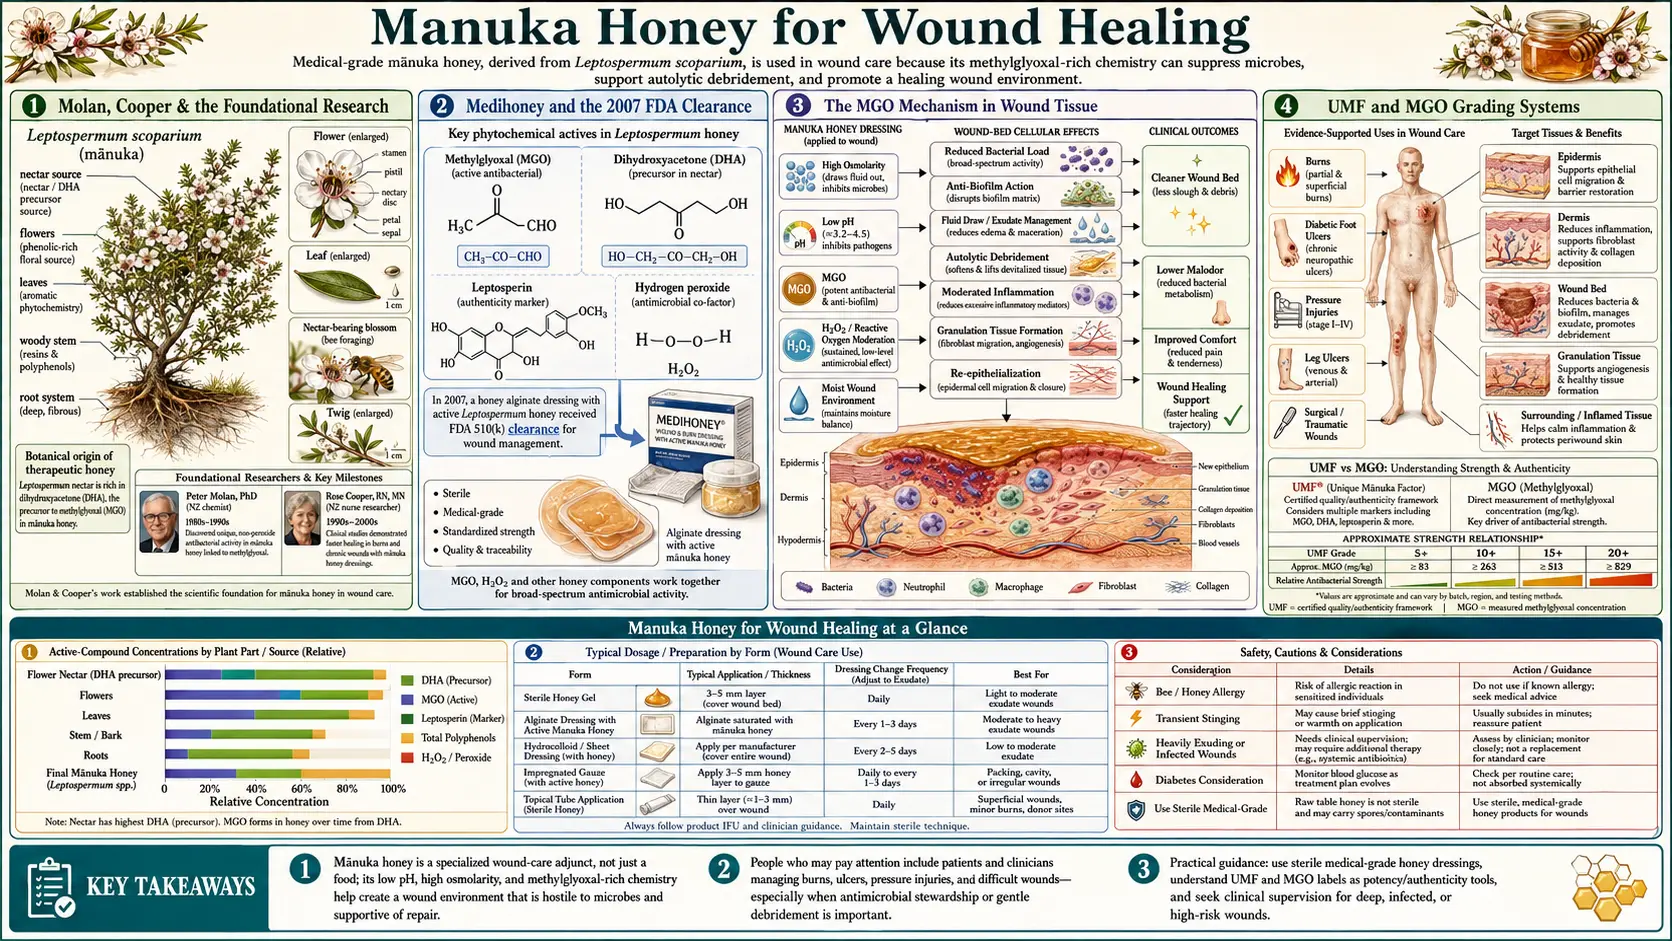
Wound healing is the application that took manuka honey from folk medicine to the U.S. Food and Drug Administration (FDA) medical device listings. In 2007, the U.S. Food and Drug Administration cleared gamma-irradiated Leptospermum scoparium honey dressings for use on diabetic foot ulcers, leg ulcers, pressure ulcers, donor sites, and burns. The path runs from Peter Molan's 1980s laboratory work at the University of Waikato in Hamilton, New Zealand, through Rose Cooper's antibacterial characterization at the University of Wales Institute, Cardiff, to randomized clinical trials in venous leg ulcers, diabetic foot ulcers, and partial-thickness burns, with results that range from high-quality evidence in burns to unclear effects in leg and foot ulcers. This deep-dive walks through the mechanism (osmotic + low pH + MGO + residual hydrogen peroxide + bee defensin), the foundational research, the trials, the UMF and MGO grading systems, and the dressing routines practitioners describe.
Table of Contents
- Molan, Cooper & the Foundational Research
- Medical-Grade Honey Dressings and the 2007 U.S. Food and Drug Administration Clearance
- The MGO Mechanism in Wound Tissue
- UMF and MGO Grading Systems
- Venous Leg Ulcer Trials
- Diabetic Foot Ulcer Trials
- Partial-Thickness Burn Trials
- Autolytic Debridement and Exudate Management
- Clinical Application Protocols
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
Molan, Cooper & the Foundational Research
The modern scientific case for manuka honey in wound care begins with Peter Molan, a biochemist at the University of Waikato in Hamilton, New Zealand. Molan began systematic study of honey's antibacterial activity in 1981 after seeing patients with chronic wounds treated with locally produced manuka honey at a New Zealand hospital. Over the next two decades, his lab characterized the dual-mechanism nature of honey antibacterial activity — the well-known hydrogen-peroxide pathway present in all nectar honeys, and a second, stable, non-peroxide activity unique to manuka. Molan's 1992 Bee World review — "The antibacterial activity of honey. 1. The nature of the antibacterial activity" — remains a foundational reference.
The chemical identity of the non-peroxide component was unknown until 2008, when two independent groups (Mavric et al. at the Technical University of Dresden, and Adams et al. at the University of Waikato) simultaneously identified methylglyoxal (MGO) as the dominant antibacterial molecule. Mavric's paper in Molecular Nutrition & Food Research measured MGO at 38 to 761 mg/kg in six commercial New Zealand manuka samples, up to 100-fold higher than in conventional honeys, and the authors concluded that manuka's pronounced antibacterial activity in their laboratory tests comes directly from MGO. The MGO is formed non-enzymatically over weeks to months from dihydroxyacetone (DHA), which is present at unusually high concentration only in Leptospermum scoparium nectar.
The clinical microbiology was characterized in parallel by Rose Cooper's group at the University of Wales Institute, Cardiff. Cooper's 2002 paper "The sensitivity to honey of Gram-positive cocci of clinical significance isolated from wounds" tested 45 strains in the laboratory: 18 of methicillin-resistant Staphylococcus aureus (MRSA) and 7 of vancomycin-sensitive enterococci from infected wounds, and 20 of vancomycin-resistant enterococci from hospital surfaces. Both manuka and pasture honey inhibited all of them at concentrations below 10% (v/v). A later laboratory study from Cooper's group exposed six bacterial cultures to sub-lethal concentrations of manuka honey. Susceptibility fell during long-term stepwise training, but the changes were not permanent and no honey-resistant mutants were detected. The authors reported that honey-resistant bacteria have not been isolated from wounds and judged the risk of resistance low if high concentrations are maintained clinically.
Medical-Grade Honey Dressings and the 2007 U.S. Food and Drug Administration Clearance
Medical-grade honey dressings are sterilized Leptospermum scoparium honey products, made from selected high-UMF manuka and processed by gamma irradiation to eliminate spore-forming bacteria (including Clostridium botulinum) that could contaminate the raw honey. The gamma irradiation does not destroy MGO, which is heat- and radiation-stable. They are sold as both a viscous gel applied directly to wound beds and as a pre-loaded calcium-alginate or hydrogel dressing.
The U.S. Food and Drug Administration cleared a medical-grade manuka honey dressing through its 510(k) route on November 7, 2007 (K072956), after an earlier honey alginate dressing on July 12, 2007 (K053095), with later clearances for other forms. The agency's 2007 letter lists the device as unclassified, under the wound dressing product code FRO. The 2007 summary lists these uses, for wounds with light to moderate fluid:
- Leg ulcers (venous, arterial and mixed)
- Diabetic foot ulcers
- Pressure ulcers and sores (partial and full thickness)
- Donor sites for skin grafts
- First- and second-degree partial-thickness burns
- Traumatic and surgical wounds
The clearance was based on the substantial-equivalence pathway, with the earlier honey dressing as the predicate device. The 2007 summary cites biocompatibility testing (cytotoxicity, sensitization and irritation), not clinical trials. Licensed honey wound products reached Europe in 2004 and North America in 2007, and similar products are reported in use in the UK National Health Service (NHS) and approved by Australia's Therapeutic Goods Administration.
Other medical-grade honey products used abroad include a blend of medical-grade honey with vitamins C and E and zinc oxide, and an engineered medical honey with controlled hydrogen peroxide release.
The MGO Mechanism in Wound Tissue
Methylglyoxal's antibacterial mechanism is multi-target, which is proposed as the reason it works against a broad spectrum of organisms and why the 2010 laboratory study above detected no honey-resistant mutants. MGO is a small, highly reactive alpha-oxoaldehyde (chemical formula CH3-CO-CHO) that:
- Crosslinks bacterial proteins by reacting with arginine, lysine, and cysteine residues to form irreversible advanced glycation end-products (AGEs). This disables essential enzymes including those required for cell wall biosynthesis, protein synthesis, and DNA replication.
- Modifies bacterial nucleic acids by reacting with guanine and other DNA bases, producing mutagenic and lethal adducts that bacterial DNA repair systems cannot keep up with at high MGO concentrations.
- Disrupts membrane integrity by reacting with phospholipid amine head groups, contributing to membrane leakage and loss of ion gradients.
- Inhibits bacterial cell division by reacting with FtsZ and other cell-division proteins, leading to the formation of elongated non-dividing cells visible by microscopy in MGO-exposed bacterial cultures.
- Disrupts biofilm structure by reacting with extracellular polymeric substance (EPS) components, breaking down established biofilms (a critical clinical advantage because most chronic wound infections are biofilm-based and refractory to systemic antibiotics).
Host tissues are partially protected from MGO toxicity by the glyoxalase system (glyoxalase I and II, requiring glutathione as a cofactor), which converts MGO to D-lactate. Bacteria have less effective glyoxalase systems and are correspondingly more susceptible. This therapeutic-index advantage allows medical-grade manuka honey to kill bacteria at MGO concentrations that human tissue can tolerate.
The osmotic mechanism is additive but distinct. Honey at applied concentration in the wound bed creates a hypertonic environment that draws water out of bacterial cells (loss of turgor, halted growth) and out of edematous host tissue (reduction of wound edema, mechanical debridement of necrotic material). The low pH (3.2-4.5) reduces bacterial growth rates and is hypothesized to improve local tissue oxygenation through the Bohr effect on hemoglobin in the surrounding capillary bed. Residual hydrogen peroxide and bee defensin-1 contribute additional antibacterial activity in the freshly-diluted wound bed.
UMF and MGO Grading Systems
Two parallel grading systems quantify the antibacterial activity of manuka honey. Clinicians and shoppers meet both on labels.
UMF (Unique Manuka Factor) is a trademarked grading owned by the UMF Honey Association of New Zealand. The UMF number is determined by an agar-diffusion bioassay against Staphylococcus aureus — a 25% solution of the honey is added to wells in an agar plate, and the diameter of the bacterial growth-inhibition zone is measured and compared to the inhibition zone produced by serial dilutions of phenol. The UMF number is the equivalent concentration of phenol (% w/v) that would produce the same zone. UMF 10+ means the honey has antibacterial activity equivalent to a 10% phenol solution. Only licensed UMF Honey Association members may use the UMF mark on packaging, and audited annually for compliance.
MGO (Methylglyoxal) is a direct chemical assay (by high-performance liquid chromatography) of methylglyoxal concentration in mg/kg of honey. It is not trademarked and is used by both UMF licensees and non-licensees. MGO is more reproducible than UMF (chemistry versus bioassay) but loses some information about the contributions of other minor antibacterial compounds and the bioavailability of MGO in different honey matrices.
The two systems correlate tightly:
- UMF 5+ ≈ MGO 83 (food grade, minimal therapeutic activity)
- UMF 10+ ≈ MGO 263 (medical-grade threshold)
- UMF 15+ ≈ MGO 514 (active wound dressing range)
- UMF 18+ ≈ MGO 696
- UMF 20+ ≈ MGO 829
- UMF 24+ ≈ MGO 1122
- UMF 26+ ≈ MGO 1282+ (rare premium product)
Practitioners describe UMF 12+ to UMF 18+ (MGO 350 to 700) as the typical practical range for chronic wounds, a figure that comes from practice rather than from a trial. They also report that higher MGO does not necessarily produce proportionally better clinical outcomes, because the limiting factor is often bioavailability and wound contact time rather than peak MGO concentration. They report that below UMF 10+ / MGO 263, antibacterial activity is too low for reliable clinical effect against established wound infection, and that above UMF 25+ / MGO 1200+, cost rises sharply without proportional clinical benefit for routine wound care, though some practitioners reserve UMF 25+ for refractory chronic wounds.
Manuka honey is sold both with and without UMF or MGO certification, and the global market is reported to include counterfeit and adulterated product (estimated to be more manuka honey sold worldwide annually than is physically produced in New Zealand). Certified product carries a batch number traceable to the producer.
Venous Leg Ulcer Trials
Venous leg ulcers (VLUs) are chronic wounds caused by venous insufficiency of the lower extremity. They affect approximately 1% of adults over age 65 and are notoriously slow to heal — mean time to closure with standard compression therapy alone is approximately 24 weeks, with 30% recurrence within one year. The chronic, infected, slough-laden character of VLUs makes them a natural test case for an antibacterial, debridement-supporting topical agent.
The largest honey trial in venous leg ulcers, by Jull and colleagues in the British Journal of Surgery in 2008, gave 368 people either calcium alginate dressings impregnated with manuka honey or usual care, all with compression bandaging. At 12 weeks, 55.6% of the honey group and 49.7% of the usual-care group had healed (P = 0.258), a difference that was not statistically significant. Adverse events were more common with honey (relative risk 1.3), honey was probably more expensive, and the other outcomes did not differ.
A trial earlier presented on this page as pivotal has been retracted. Gethin and Cowman's multicentre randomized controlled trial of 108 people with sloughy venous ulcers, comparing a manuka honey dressing with a hydrogel dressing (Journal of Clinical Nursing, 2009), was retracted in 2015 by agreement between the journal's editor, the authors and the publisher, because of errors in the data analysis that affect its findings. Its results are not repeated here. A separate bacteriology report from the same trial (Journal of Wound Care, 2008) is not itself marked as retracted. Methicillin-resistant Staphylococcus aureus was present in only 16 wounds at the start, and after 4 weeks it was gone from 7 of 10 honey-treated wounds and 1 of 6 hydrogel-treated wounds. Pseudomonas went the other way: it was eliminated in 33% (2 wounds) with honey and 50% (5 wounds) with hydrogel.
The Robson et al. 2009 randomized controlled trial (RCT) in Journal of Advanced Nursing compared a standardized antibacterial medical-grade honey with conventional dressings in 105 patients with a mix of wounds. Median time to healing was 100 days with honey and 140 days with conventional dressings, and 46.2% and 34.0% had healed at 12 weeks, but the difference was not statistically significant (hazard ratio 1.30, 95% confidence interval 0.77 to 2.19, P = 0.321). The authors said further research is needed.
The 2015 Cochrane systematic review by Jull et al. of 26 randomized controlled trials (RCTs) (3,011 patients) of honey for wounds concluded that honey appears to heal partial-thickness burns more quickly than conventional treatment. For venous leg ulcers (2 trials, 476 people, low quality evidence) it called the effects unclear, and outside burns and infected post-operative wounds it said the evidence "does not form a robust basis for decision making". What is not known is whether a honey dressing adds anything to compression bandaging for venous leg ulcers. Some wound-care practitioners still report choosing manuka honey for sloughy or infected VLUs that have failed to progress on standard moisture-retentive dressings, particularly when methicillin-resistant Staphylococcus aureus or Pseudomonas colonization is documented; this is a practice view, and no guideline is cited for it here.
For more on the broader venous insufficiency picture, see our Venous Insufficiency page and the Cellulitis page for the infection-secondary complication.
Diabetic Foot Ulcer Trials
Diabetic foot ulcers (DFUs) are the leading cause of non-traumatic lower-extremity amputation worldwide. The combination of peripheral neuropathy (loss of protective sensation), peripheral vascular disease (impaired tissue perfusion and oxygen delivery), and immune dysfunction (impaired neutrophil function in chronic hyperglycemia) makes DFUs uniquely refractory to conventional wound care. Approximately 20-25% of all DFUs progress to amputation within 5 years, and 5-year mortality after a major DFU-related amputation is approximately 50% — worse than most cancers.
Moghazy et al. (2010) in Diabetes Research and Clinical Practice studied 30 infected diabetic foot wounds treated with commercial clover honey dressings, not manuka, for 3 months. Outcomes:
- Healing rate: 43.3% complete healing
- Decrease in size and healthy granulation in another 43.3%
- Treatment failure in 6.7%
- Bacterial load in all ulcers significantly reduced after the first week
- The authors concluded that clover honey is a clinical and cost-effective dressing for diabetic wounds in developing countries
The Eddy et al. (2008) Wisconsin Medical Journal paper "Practical considerations of using topical honey for neuropathic diabetic foot ulcers: a review" is written to familiarize physicians with practical use. Its authors, who report their own experience with topical honey, conclude that honey is a low-cost therapy that may be considered in diabetic foot ulcers, after discussing risks and benefits and alongside standard wound care.
The Imran et al. 2015 randomized controlled trial in Journal of College of Physicians and Surgeons Pakistan divided 348 DFU patients between dressings impregnated with Beri honey, not manuka, and normal saline dressings. Wounds healed completely in 75.97% (136 of 179) with honey and 57.39% (97 of 169) with saline (p = 0.001), and median healing time was 18 days and 29 days (p < 0.001).
Larger summaries came later. In 2015 the Cochrane review called the effects of honey on diabetic foot ulcers unclear (2 trials, 93 people, low quality evidence). A 2026 meta-analysis pooled 16 randomized trials with 1,423 people comparing honey dressings of various kinds with conventional dressings. Honey raised the odds of complete healing (odds ratio 2.28, moderate-quality evidence) and shortened healing time by a mean of 4.38 (low-quality evidence; the abstract gives no unit for this difference).
Manuka honey itself was tested in a 2026 randomized trial of 60 people, against a silver-containing calcium alginate dressing. After 4 weeks, the total wound score fell 41.3% with medical-grade manuka honey and 2.0% with silver, and every score item except wound depth improved significantly more with honey (p < 0.001).
Practitioners describe these practical advantages of manuka honey for DFUs:
- Activity against polymicrobial flora including methicillin-resistant Staphylococcus aureus, Pseudomonas, and anaerobes — the typical DFU microbiome
- Autolytic debridement of slough and necrotic tissue without surgical sharps
- Maintenance of moist wound environment that supports granulation tissue formation
- Compatibility with offloading devices (total contact casts, removable boots) because the dressing can be left in place for several days
- Cost: medical-grade manuka dressings are expensive per gram but inexpensive per healed wound when they accelerate closure
See our Diabetes page for the broader management of the underlying disease.
Partial-Thickness Burn Trials
The strongest evidence base for honey in wound care is in partial-thickness burns, and the 2015 Cochrane systematic review separated two comparisons. Against conventional dressings (polyurethane film, paraffin gauze, soframycin-impregnated gauze, sterile linen, or leaving the burn exposed), high quality evidence from 2 trials with 992 people showed honey healing about 4.7 days faster (weighted mean difference -4.68 days, 95% confidence interval -5.09 to -4.28). Against silver sulfadiazine cream, very low quality evidence from 4 trials with 332 people suggested faster healing (weighted mean difference -5.12 days), while high quality evidence from 6 trials with 462 people showed no difference in the overall risk of healing within 6 weeks (risk ratio 1.00), with fewer adverse events on honey.
Subrahmanyam (1998) in Burns randomized 50 patients with superficial burns to honey dressing versus 1% silver sulfadiazine. Epithelialization (new skin covering the wound) was satisfactory by day 7 in 84% with honey and 72% with silver sulfadiazine, and by day 21 in 100% and 84%. The author also reported better control of infection with honey.
Multiple subsequent Subrahmanyam trials (in Burns, Annals of Burns and Fire Disasters, and British Journal of Surgery) replicated this finding across several hundred additional patients in different burn etiologies (thermal, chemical, electrical) and depths.
The mechanism for burn benefit overlaps but extends beyond the antibacterial activity: the osmotic effect of honey reduces wound edema (a major contributor to depth-progression of burn injury in the first 48 hours), the low pH may improve tissue oxygenation, and the maintained moist wound environment optimizes re-epithelialization rate. For deeper burns (full-thickness, third-degree), honey is not a primary therapy — these require surgical debridement and grafting — but medical-grade honey dressings are cleared as donor-site dressings for skin-graft harvest sites.
First-aid guidance for thermal burns before professional medical care centers on cooling (20 minutes of cool but not cold running water). Practitioners use manuka honey at the dressing stage, after cooling and initial wound assessment.
Autolytic Debridement and Exudate Management
One of the practical clinical advantages of manuka honey in chronic wound care is its dual action as both an antibacterial agent and an autolytic debridement agent. Slough and fibrinous exudate are barriers to healing — chronic wounds with persistent slough rarely re-epithelialize, regardless of how clean the bacterial culture is. Conventional approaches to debridement include sharp (scalpel), mechanical (wet-to-dry dressings, ultrasonic), enzymatic (collagenase), and autolytic (occlusive dressings that allow endogenous proteases to dissolve necrotic tissue). Each has limitations — sharp debridement is painful and requires skilled practitioners; mechanical debridement can damage healthy tissue; enzymatic debridement is expensive and slow; autolytic debridement requires intact host wound fluid chemistry that is often impaired in chronic wounds.
Manuka honey's osmotic action provides a fifth debridement modality. The hypertonic honey draws water out of necrotic tissue, softening and loosening slough so that it can be wiped away at dressing changes. Combined with the antibacterial activity that reduces the bacterial bioburden in the slough, practitioners report visible slough reduction within days.
Exudate management is the other practical consideration. Heavily exudating wounds will dilute applied honey and reduce both its antibacterial concentration and its osmotic effect. Two approaches manage this:
- Calcium-alginate-impregnated honey dressings — the alginate fiber absorbs exudate and gels in place, maintaining honey contact with the wound bed
- Frequent dressing changes — for heavily exudating wounds, daily dressing changes maintain a therapeutic honey concentration in the wound bed
For low-exudate wounds, dressings can typically be left in place for 3-7 days, balancing antibacterial activity (peak in the first 24-48 hours after application as MGO concentration is highest in undiluted honey) with practical convenience.
Clinical Application Protocols
Wound-care practitioners describe the following routine for medical-grade manuka honey in outpatient or wound-clinic settings. It comes from practice, not from a trial cited here:
- Wound assessment — clinics document wound dimensions (length, width, depth), tissue type (granulation, slough, eschar percentages), exudate volume and character, surrounding skin condition, and signs of infection. A culture is usual with cellulitis, systemic signs, or no progress after 2 weeks.
- Wound cleansing — gentle saline or commercial wound cleanser removes loose debris and surface bacteria, without aggressive scrubbing of healthy granulation tissue.
- Honey application — medical-grade manuka honey (UMF 12+ to 18+, or equivalent MGO 350-700) is applied generously to the entire wound bed, and cavity wounds are filled. Practitioners describe a layer at least 5 mm thick, to maintain therapeutic concentration as exudate dilutes it.
- Secondary dressing — a non-adherent contact layer or absorbent secondary dressing manages exudate and contains honey at the wound site. On dependent body sites (e.g. lower leg), film or foam secondary dressings keep honey from migrating.
- Outer dressing — compression bandage for venous leg ulcers (this is the primary therapy for VLU; manuka is the adjunct). Offloading device for diabetic foot ulcers. Standard absorbent dressing for non-pressure-dependent wounds.
- Dressing change frequency — daily for heavily exudating wounds, every 2-3 days for moderate exudate, up to weekly for low-exudate clean wounds, adjusted to wound response.
- Progress monitoring — weekly wound measurement and photographic documentation. Practitioners report visible slough reduction within 1-2 weeks and bacterial culture clearance within 2-4 weeks. Lack of progress at 4 weeks leads clinics to reassess the underlying diagnosis (vascular insufficiency, osteomyelitis, malignancy, atypical infection).
- Duration — manuka honey is used throughout the healing process from inflammation through proliferation, until the wound is fully re-epithelialized.
Cautions and Contraindications
- Infants under 12 months — absolute contraindication. Raw honey of any kind, including unirradiated manuka, can contain Clostridium botulinum spores. The immature infant gut cannot prevent germination and toxin production, and infant botulism is a life-threatening condition. Medical-grade gamma-irradiated dressings are theoretically safer in this regard, but the public-health warning stands: infant botulism is the reason honey of any type is warned against for any infant under 1 year of age, even the smallest taste.
- Honey allergy / bee allergy — rare but documented. Practitioners describe testing a small area before extensive application in patients with known bee or pollen allergies. Systemic reactions are extremely rare with topical use but theoretically possible.
- Diabetes (systemic) — topical honey application has negligible systemic glucose effect because absorption from intact or wound tissue is minimal. Eaten honey is a different matter: it counts as sugar and carbohydrate in the diet.
- Stinging sensation — common in the first 5-10 minutes after application, particularly in wounds with substantial inflammation. Generally subsides spontaneously. Practitioners report that severe or persistent stinging is a reason some patients stop.
- Wound color change — honey will temporarily stain wound tissue yellow-amber. This is cosmetic and does not indicate infection. Wound clinics describe telling patients in advance to prevent alarm.
- Drug interactions — no clinically significant drug interactions with topical use. Oral ingestion of large amounts (rare) could theoretically affect medications metabolized by the same hepatic pathways, but in practice this is not a concern.
- Counterfeit product — the global manuka market is reported to include substantial counterfeit and adulterated product. UMF or MGO certification is the check available to buyers, and medical-grade dressings are the form cleared by the U.S. Food and Drug Administration.
- Cost — medical-grade manuka dressings are expensive ($30-$60 per dressing depending on size). Insurance coverage varies by jurisdiction and indication.
Key Research Papers
- Molan PC (1992). The antibacterial activity of honey. 1. The nature of the antibacterial activity. Bee World, 73(1): 5-28. — doi:10.1080/0005772X.1992.11099109
- Mavric E, Wittmann S, Barth G, Henle T (2008). Identification and quantification of methylglyoxal as the dominant antibacterial constituent of Manuka (Leptospermum scoparium) honeys from New Zealand. Mol Nutr Food Res, 52(4): 483-9. — PubMed PMID: 18210383
- Adams CJ et al. (2008). Isolation by HPLC and characterisation of the bioactive fraction of New Zealand manuka (Leptospermum scoparium) honey. Carbohydr Res, 343(4): 651-9. — PubMed PMID: 18194804
- Cooper RA, Molan PC, Harding KG (2002). The sensitivity to honey of Gram-positive cocci of clinical significance isolated from wounds. J Appl Microbiol, 93(5): 857-63. — PubMed PMID: 12392533
- Cooper RA et al. (2010). Absence of bacterial resistance to medical-grade manuka honey. Eur J Clin Microbiol Infect Dis, 29(10): 1237-41. — PubMed PMID: 20549529
- Gethin G, Cowman S (2009). Manuka honey vs. hydrogel--a prospective, open label, multicentre, randomised controlled trial to compare desloughing efficacy and healing outcomes in venous ulcers. J Clin Nurs, 18(3): 466-74. RETRACTED in 2015 (see the retraction statement below). — PubMed PMID: 18752540
- Retraction statement: Manuka honey vs. hydrogel - a prospective, open label, multicentre, randomised controlled trial to compare desloughing efficacy and healing outcomes in venous ulcers. J Clin Nurs (2015), 24(17-18): 2686. — PubMed PMID: 26311521
- Gethin G, Cowman S (2008). Bacteriological changes in sloughy venous leg ulcers treated with manuka honey or hydrogel: an RCT. J Wound Care, 17(6): 241-4, 246-7. — PubMed PMID: 18666717
- Jull A, Walker N, Parag V, Molan P, Rodgers A (2008). Randomized clinical trial of honey-impregnated dressings for venous leg ulcers. Br J Surg, 95(2): 175-82. — PubMed PMID: 18161896
- Robson V, Dodd S, Thomas S (2009). Standardized antibacterial honey (Medihoney) with standard therapy in wound care: randomized clinical trial. J Adv Nurs, 65(3): 565-75. — PubMed PMID: 19222654
- Subrahmanyam M (1998). A prospective randomised clinical and histological study of superficial burn wound healing with honey and silver sulfadiazine. Burns, 24(2): 157-61. — PubMed PMID: 9625243
- Jull AB et al. (2015). Honey as a topical treatment for wounds. Cochrane Database Syst Rev, CD005083. — PubMed PMID: 25742878
- Eddy JJ, Gideonsen MD, Mack GP (2008). Practical considerations of using topical honey for neuropathic diabetic foot ulcers: a review. WMJ, 107(4): 187-90. — PubMed PMID: 18702435
- Moghazy AM et al. (2010). The clinical and cost effectiveness of bee honey dressing in the treatment of diabetic foot ulcers. Diabetes Res Clin Pract, 89(3): 276-81. — PubMed PMID: 20646771
- Imran M, Hussain MB, Baig M (2015). A Randomized, Controlled Clinical Trial of Honey-Impregnated Dressing for Treating Diabetic Foot Ulcer. J Coll Physicians Surg Pak, 25(10): 721-5. — PubMed PMID: 26454386
- Yao L, Dai J, Mei S (2026). Honey dressing for diabetic foot ulcers: a systematic review and meta-analysis of randomized controlled trials. Front Endocrinol (Lausanne), 17: 1759703. — PubMed PMID: 41928876
- Rojczyk E, Spyrka K, Sieroń A, Bazaliński D, Kucharzewski M (2026). Manuka honey as a natural remedy for diabetic foot ulcers: efficacy compared with silver-based dressing. Front Pharmacol, 17: 1790277. — PubMed PMID: 41982668
PubMed Topic Searches
Connections
- All Herbs
- Manuka Honey Overview
- Manuka Honey Benefits Hub
- Antimicrobial Spectrum
- Digestive & Sore Throat
- Skin Conditions & Acne
- Diabetes
- Staphylococcus aureus / Methicillin-Resistant Staphylococcus Aureus
- Pseudomonas aeruginosa
- Cellulitis
- Collagen (Wound Healing)
- Silver Nanoparticles
- Tea Tree
- Honey (Conventional)
- History