Nhan Tran (Adenosma caeruleum) for Liver and Bile Flow
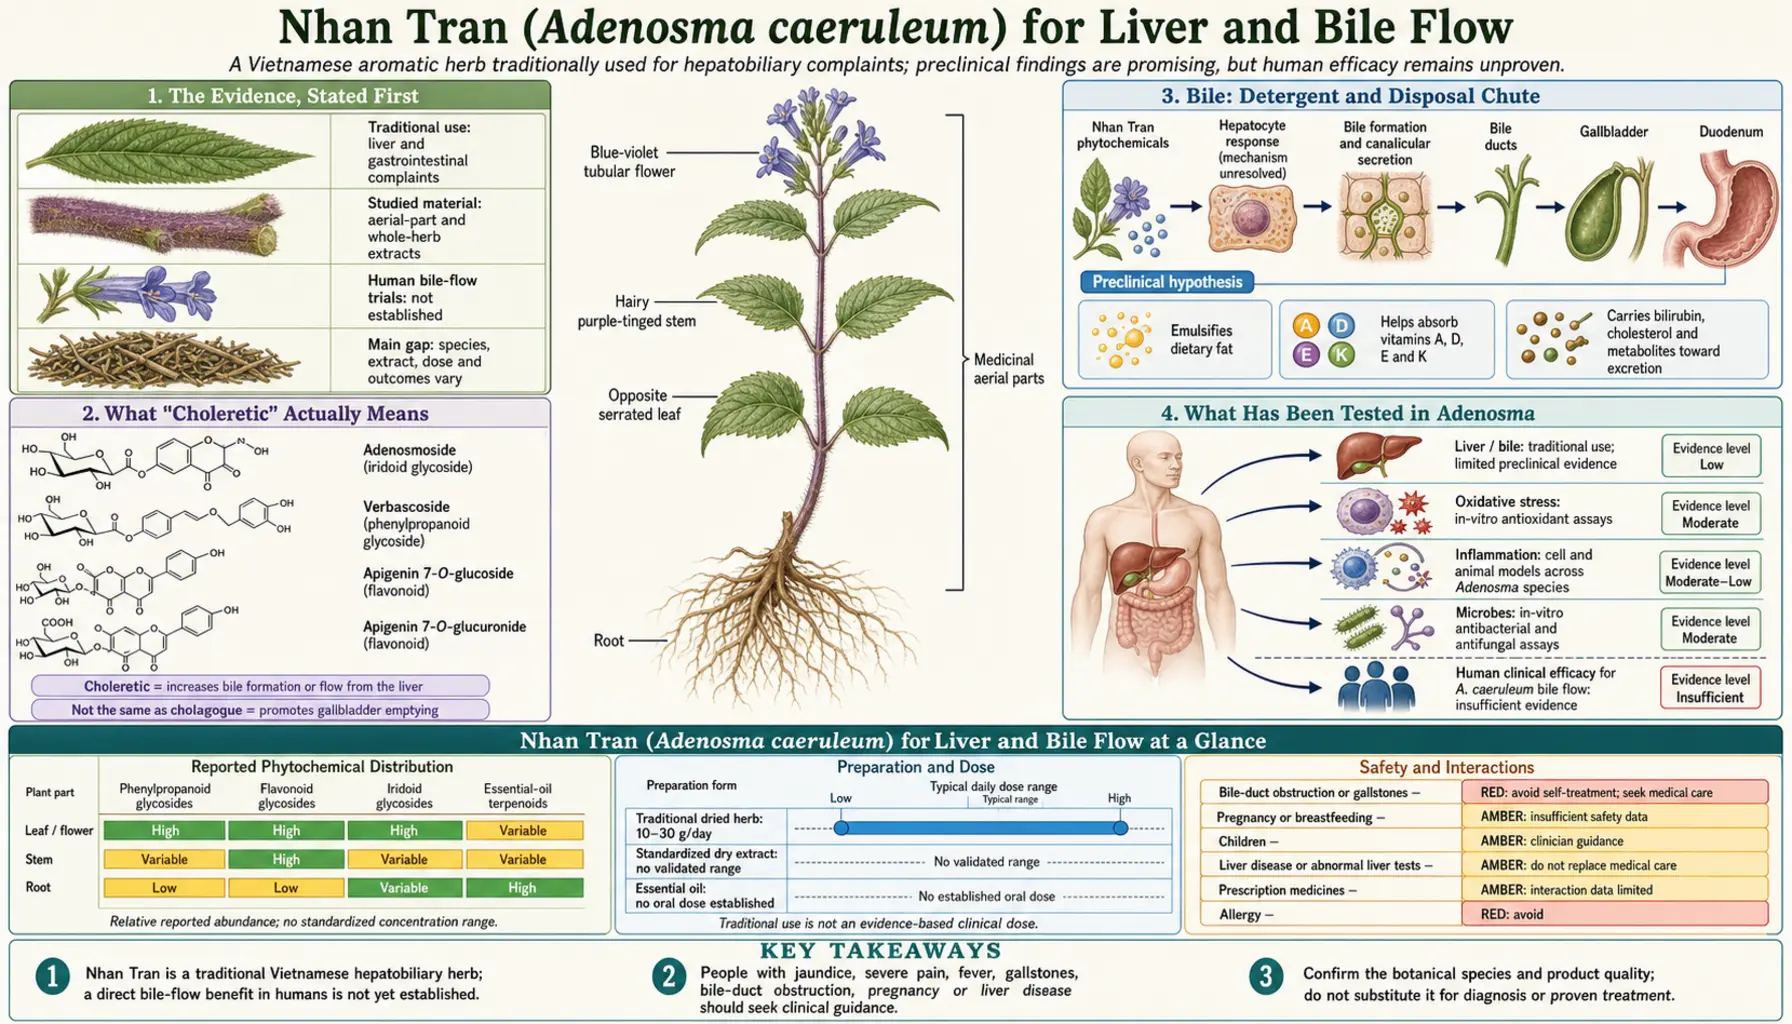
If nhân trần has a reputation, this is it. In Vietnam the tea is drunk for nóng gan — "hot liver" — a folk category that covers yellowish eyes, dark urine, greasy skin, bad breath, poor appetite after rich food, and the general feeling that something in the middle of you is congested. The claimed action is choleretic: it is supposed to make bile move.
Read this before anything else. There are no randomized controlled trials of Adenosma caeruleum in humans — none for liver disease, none for jaundice, none for bile flow. What exists is a modest amount of rodent work, a great deal of traditional use, and a very large research literature on a completely different plant that shares the same Vietnamese name. This page keeps those three things apart on purpose.
Table of Contents
- The Evidence, Stated First
- What "Choleretic" Actually Means
- Bile: Detergent and Disposal Chute
- What Has Been Tested in Adenosma
- The Yin Chen Hao Literature Is a Different Plant
- Jaundice Is a Symptom, Not a Diagnosis
- Where a Bile-Moving Tea Could Plausibly Help
- How It Is Prepared for Liver Complaints
- Cautions and Who the Research Raises Concerns For
- Key Research Papers
- Connections
- Featured Videos
The Evidence, Stated First
Three tiers, in descending order of strength:
- Animal work. Extracts of Adenosma species have been evaluated in rodents using bile-duct cannulation — the standard choleretic assay — and in chemically induced liver-injury models where serum alanine aminotransferase (ALT) and aspartate aminotransferase (AST) are the readout. Reports of increased bile output and reduced enzyme elevation exist, largely in Vietnamese-language pharmacognosy journals. These are hypothesis-generating results in animals, at doses and by routes that do not translate directly to a cup of tea.
- In-vitro work. Antioxidant and cell-protection assays on extracts. Almost every plant extract on earth performs well in these; a positive result is close to uninformative on its own.
- Traditional use. Generations of Vietnamese households. This tells you the tea is broadly tolerated at customary doses by adults who chose to keep drinking it. It does not tell you it works.
What is entirely absent: any human trial with a control group, any measurement of bile flow in people, any before-and-after liver-enzyme study in patients. Anyone who tells you nhân trần is "clinically proven" for the liver is either mistaken or quoting the wrong plant.
What "Choleretic" Actually Means
Two similar-sounding words get muddled constantly, and the difference matters:
- Choleretic — increases the production of bile by liver cells. More bile is made and secreted into the tiny canals between hepatocytes.
- Cholagogue — promotes the emptying of the gallbladder, squeezing stored bile down into the small intestine.
Think of it as a factory and a warehouse. A choleretic raises factory output. A cholagogue opens the warehouse doors. A herb can do one, both, or neither. Traditional descriptions of nhân trần mix the two freely, and the rodent assays used to test it measure the first.
Both effects are, importantly, only useful when the pipe is open. If the bile duct is blocked by a stone or a tumour, stimulating more bile production pushes against a closed door. That is why "increases bile flow" is not automatically a good thing, and why a choleretic tea is not a treatment for obstructive jaundice.
Bile: Detergent and Disposal Chute
Bile does two jobs that have almost nothing to do with each other.
Job one: emulsification. Bile salts are biological detergents. Fat arriving in the small intestine is a blob; lipase can only work on its surface. Bile salts break the blob into a fine suspension of droplets, multiplying the surface area enormously, so fat and the fat-soluble vitamins A, D, E and K can actually be absorbed. People with poor bile flow often report exactly what you would predict — heaviness after fatty meals, pale greasy stools, nausea after fried food.
Job two: excretion. Bile is also the liver's rubbish chute. Bilirubin, excess cholesterol, some hormones, some drug metabolites and various toxins are conjugated in the liver and dumped into bile for removal in the stool. When that chute backs up, those substances accumulate in blood — which is what jaundice is.
Bilirubin deserves its own sentence, because it is the pigment behind every yellow-skin story. Old red blood cells are broken down; haem becomes unconjugated bilirubin, which is fat-soluble and travels bound to albumin. The liver enzyme UGT1A1 attaches glucuronic acid to it, producing water-soluble conjugated bilirubin, which is secreted into bile. Anything that overwhelms production, impairs conjugation, or blocks secretion produces jaundice — by three quite different routes with three quite different treatments.
What Has Been Tested in Adenosma
The Adenosma liver literature is small, old and mostly Vietnamese. Typical study designs you will find:
- Bile-duct cannulation in rats. A cannula is placed in the common bile duct, bile is collected over timed intervals, and volume is compared between treated and control animals. An increase in millilitres per hour is a choleretic signal. This is a real, reproducible assay — but it is an anaesthetised rodent receiving a concentrated extract, often intraduodenally.
- Carbon tetrachloride or paracetamol liver-injury models. Animals are given a hepatotoxin; serum alanine aminotransferase and aspartate aminotransferase rise; a protective agent blunts that rise. Extracts of many aromatic and flavonoid-rich plants blunt it somewhat. It is a screening model, not a disease model, and dozens of substances that pass it have never shown a human benefit.
- Antioxidant assays. DPPH, ABTS, FRAP. These measure whether a solution can donate electrons in a test tube. They do not measure anything that happens in a liver.
Two honest caveats about this body of work. First, much of it does not distinguish clearly between Adenosma caeruleum and Adenosma bracteosum (bồ bồ, "nhân trần Tây Ninh"), which are traded interchangeably. Second, it is largely inaccessible to outside review — not indexed, not translated, rarely replicated. That is a limitation to state, not a scandal; a great deal of useful regional pharmacognosy lives in journals the English-language world never reads. But it means the reader cannot verify it, and neither can this page.
A 2021 review of the whole Adenosma genus, which searched English, Chinese and Vietnamese sources, found that these plants are traditionally used for stomach and gut complaints, hepatitis, colds and skin problems, and that phenolic acids, flavonoids and terpenoids are their main plant compounds. The activities tested so far (against diabetes, against cancer, and against insects) come from laboratory tests, cell lines and animal models, and the authors call for further study of “the toxicity and identity of the bioactive compounds” and how they work.
The Yin Chen Hao Literature Is a Different Plant
Search "nhân trần liver" and you will surface an impressive-looking body of hepatology research. Nearly all of it concerns Artemisia capillaris Thunb. — Chinese 茵陈, yīn chén hāo — a member of the daisy family (Asteraceae) whose Chinese name is also translated "nhân trần" in Vietnamese texts of Chinese medicine.
Artemisia capillaris is not a relative of Adenosma caeruleum. Different family, different growth habit, different chemistry. Its characteristic compounds are coumarins — notably scoparone (6,7-dimethoxycoumarin) — plus the chromone capillarisin and abundant chlorogenic acid. Adenosma's chemistry is essential-oil-dominant: limonene, fenchone, 1,8-cineole, α-humulene. The two plants' signature compounds differ (scoparone and capillarisin in Artemisia capillaris, an essential oil in Adenosma), though both contain common plant phenolic acids and flavonoids — the aerial parts of Adenosma caeruleum have yielded phenylpropanoids such as verbascoside and two apigenin flavonoid glycosides.
The Artemisia capillaris research is genuinely interesting on its own terms. It is the backbone of the classical formula Yin Chen Hao Tang, used for centuries for jaundice, and there is real mechanistic work on a related Artemisia capillaris formula, Yin Zhi Huang (a decoction of the herb with three others, used in Asia for newborn jaundice). In mice, Yin Zhi Huang sped up the clearance of bilirubin by activating the nuclear receptor CAR (constitutive androstane receptor), which switched on the bilirubin-clearance machinery, including the bilirubin-conjugating enzyme (UGT1A1); its compound scoparone (6,7-dimethylesculetin) activated CAR in mouse liver cells and sped up bilirubin clearance in the mice — a coherent molecular story for why an ancient jaundice remedy might do something.
None of that is evidence for Adenosma caeruleum. Borrowing it would be like citing aspirin trials to support willow-scented soap. Whenever this site cites Yin Chen Hao work, the species is named explicitly and labelled as a different plant. If a supplement label, a blog post or a seller quotes "clinical research on nhân trần for jaundice," the Latin binomial on the product shows whether that research applies to what is in the bag.
Jaundice Is a Symptom, Not a Diagnosis
This is the section that matters most: yellow skin or yellow whites of the eyes is a sign that hospitals investigate with blood tests — the cause can be blocked bile ducts, hepatitis or the breakdown of red blood cells, and only tests tell them apart. A tea does not.
Yellowing appears when total bilirubin rises to roughly 2–3 mg/dL (about 34–51 µmol/L), typically visible first in the sclerae. The causes fall into three buckets, and telling them apart requires laboratory work — it cannot be done by how you feel:
- Pre-hepatic — too much bilirubin being made. Haemolysis, from autoimmune disease, glucose-6-phosphate dehydrogenase (G6PD) deficiency, transfusion reactions, some infections, some drugs. Unconjugated bilirubin dominates.
- Hepatic — the liver cannot process it. Viral hepatitis A, B, C or E; alcohol-related liver disease; drug and herb-induced liver injury; autoimmune hepatitis; cirrhosis; Gilbert syndrome (benign, common, harmless).
- Post-hepatic — the drain is blocked. Gallstones in the common bile duct, stricture, pancreatic head tumour, cholangiocarcinoma, primary sclerosing cholangitis. Conjugated bilirubin dominates, often with pale clay-coloured stools and dark urine.
The minimum workup is straightforward and cheap in most places: total and direct bilirubin, alanine aminotransferase, aspartate aminotransferase, alkaline phosphatase, gamma-glutamyl transferase (GGT), albumin, international normalized ratio (INR), a full blood count, viral hepatitis serology, and an abdominal ultrasound. Those tests separate the three buckets in a day.
Hospitals treat jaundice with any of these as an emergency: fever and shaking chills (possible ascending cholangitis — a surgical emergency), severe right-upper-quadrant pain, confusion or unusual drowsiness, vomiting blood or black stools, or bruising and bleeding gums. In Vietnam and elsewhere, chronic hepatitis B is common and often silent until it is not; jaundice in that setting is a reason for urgent assessment.
Drinking a cooling tea and waiting to see whether the yellow fades is the single most dangerous thing anyone does with this herb. It is not that the tea is toxic — it is that the delay is.
Where a Bile-Moving Tea Could Plausibly Help
Setting aside disease, is there a scenario where a mild aromatic choleretic is reasonable? Honestly, yes — a narrow one, and it is about comfort rather than cure.
Warm bitter-aromatic infusions after a heavy, fatty meal are a near-universal human habit: fennel in India, gentian and artichoke digestifs in Europe, chrysanthemum and hawthorn in China, nhân trần in Vietnam. The plausible mechanism is unremarkable — mild bitter and aromatic stimulation of upper-gut secretion and motility, plus the simple physiology of warm fluid and a pause after eating. If a cup of nhân trần after a rich lunch makes you feel less heavy, that experience is real, and it costs almost nothing.
What it cannot do, on any current evidence: lower liver enzymes in hepatitis, dissolve gallstones, "detox" or "cleanse" a liver (the liver is the detox organ — it does not need one), reverse fatty liver, or substitute for antiviral treatment. Metabolic dysfunction-associated steatotic liver disease (MASLD; formerly called non-alcoholic fatty liver disease), the most common liver problem in the world today, responds to sustained weight loss, reduced added sugar and alcohol, and exercise. No tea has ever matched that.
The new name dates from 2023, when a consensus process led by three large international liver associations replaced “non-alcoholic fatty liver disease” with MASLD. MASLD is defined as fat in the liver plus at least 1 of 5 cardiometabolic risk factors. People with MASLD who also drink more alcohol (140–350 g a week for women, 210–420 g a week for men) are placed in a separate category, MetALD (metabolic and alcohol related/associated liver disease).
How It Is Prepared for Liver Complaints
Traditional Vietnamese preparation is simple. Roughly 10–20 g of the dried aerial parts per litre of water, either steeped like tea in just-boiled water for 10–15 minutes, or simmered gently for a similar time, then drunk warm through the day. It is often taken as a daily hot-weather drink rather than as a timed dose.
Commercial forms include loose dried herb, tea bags, and tablets or capsules of dried extract. Extract products are the least transparent: extraction ratio, solvent and species are rarely stated, and an alcohol extract of an oil-rich herb is not the same preparation as a water infusion.
The commonest commercial presentation is nhân trần blended with licorice (cam thảo). That blend has a specific, real safety problem — the two herbs work against each other pharmacologically, and chronic licorice carries a documented risk of pseudoaldosteronism. It is covered in full on the Traditional Tea and Safety page, which covers the risks of drinking it daily.
There is no established therapeutic dose, because there is no trial from which to derive one. Any number quoted anywhere, including here, is customary practice rather than a studied dose.
Cautions and Who the Research Raises Concerns For
- Known or suspected biliary obstruction — gallstones in the duct, strictures, tumours. Stimulating bile against a blockage is at best pointless; a blockage is found by imaging, such as an abdominal ultrasound.
- Any unexplained jaundice — its cause is found only by blood tests and imaging (see above).
- Established liver disease or liver failure — there is no safety data for this herb in a compromised liver, and herb-induced liver injury is a real, under-recognised category. The U.S. National Institutes of Health (NIH) LiverTox database exists because of it.
- Pregnancy and breastfeeding — Vietnamese traditional practice cautions against habitual daily use, and no modern safety data exist.
- Children — no data. Adult folk dosing does not scale down by guesswork.
- Licorice-blended products in hypertension, heart failure, kidney disease, or with diuretics, digoxin or corticosteroids — this is the practical interaction that actually sends people to hospital.
- Species uncertainty — you may be drinking A. caeruleum, A. bracteosum, or Artemisia capillaris. Only a label that names the botanical species shows which plant is in the bag.
One more point, easily missed: no study has tested nhân trần alongside prescription medicines for liver conditions, hepatitis antivirals in particular, so the lack of a known interaction is not evidence that there is none, and the tea has never been tested as a replacement for those medicines.
Key Research Papers
Where a specific paper is cited, its PubMed identifier is given; the other entries are live PubMed queries. Much of the Adenosma literature is Vietnamese-language and not indexed, and a wrong identifier is worse than an honest search link.
- Huang W, Zhang J, Moore DD. A traditional herbal medicine enhances bilirubin clearance by activating the nuclear receptor CAR. Journal of Clinical Investigation. 2004;113(1):137-143. — PubMed PMID: 14702117 — Species: Artemisia capillaris in the Yin Zhi Huang formula, tested in mice — not Adenosma caeruleum.
- Wang C, Zhang H, Liu Q, Qi J, Zhuang H, Gou Y, Wang H, Wang Y. A review of the aromatic genus Adenosma: Geographical distribution, traditional uses, phytochemistry and biological activities. Journal of Ethnopharmacology. 2021;275:114075. — PubMed PMID: 33823165 — Genus review: Adenosma.
- De Abreu MB, Malafronte N, Van Kiem P, Braca A. A new iridoid from Adenosma caeruleum R. Br. Fitoterapia. 2009;80(6):358-360. — PubMed PMID: 19442709 — Species: Adenosma caeruleum.
- Rinella ME, Lazarus JV, Ratziu V, Francque SM, Sanyal AJ, Kanwal F, et al.; NAFLD Nomenclature consensus group. A multisociety Delphi consensus statement on new fatty liver disease nomenclature. Hepatology. 2023;78(6):1966-1986. — PubMed PMID: 37363821
- Reviews of Artemisia capillaris phytochemistry and hepatoprotective pharmacology, covering scoparone and capillarisin. Search. Different plant, labelled.
- Clinical and mechanistic literature on Yin Chen Hao Tang for jaundice and cholestasis. Search. Different plant, labelled.
- Essential-oil composition of Adenosma caeruleum — limonene, fenchone, 1,8-cineole, α-humulene. Search.
- Studies on Adenosma bracteosum, the second Vietnamese species sold under the same market name. Search.
- Methodology of choleretic testing by bile-duct cannulation in rodents. Search.
- UGT1A1, bilirubin conjugation, and the genetics of Gilbert syndrome. Search.
- Diagnostic approach to the jaundiced adult: laboratory pattern and imaging. Search.
- Herb-induced liver injury: incidence, causality assessment and reporting. Search.
PubMed Topic Searches
- PubMed: Adenosma caeruleum
- PubMed: Adenosma hepatoprotective
- PubMed: Choleretic herbal medicine
- PubMed: Artemisia capillaris and CAR
- PubMed: Obstructive jaundice management
- PubMed: Hepatitis B prevalence in Vietnam
- PubMed: NAFLD lifestyle intervention
- PubMed: CCl4 liver-injury model limitations
- PubMed: Enterohepatic circulation of bile acids
- PubMed: Vietnamese traditional liver herbs
Connections
- All Herbs
- Nhan Tran (Adenosma caeruleum) — the full research article.
- Nhan Tran: History and Traditional Use — where the name and the confusion came from.
- Milk Thistle — the liver herb with actual human trials, worth comparing.
- Dandelion — the Western bitter choleretic with the same traditional logic.
- Chanca Piedra — folk "stone breaker," another thin-evidence hepatobiliary herb.
- Licorice — the usual blend partner and the real safety issue.
- Artemisia annua — a different Artemisia; useful for keeping species straight.