Nhan Tran (Adenosma caeruleum): Traditional Tea and Safety
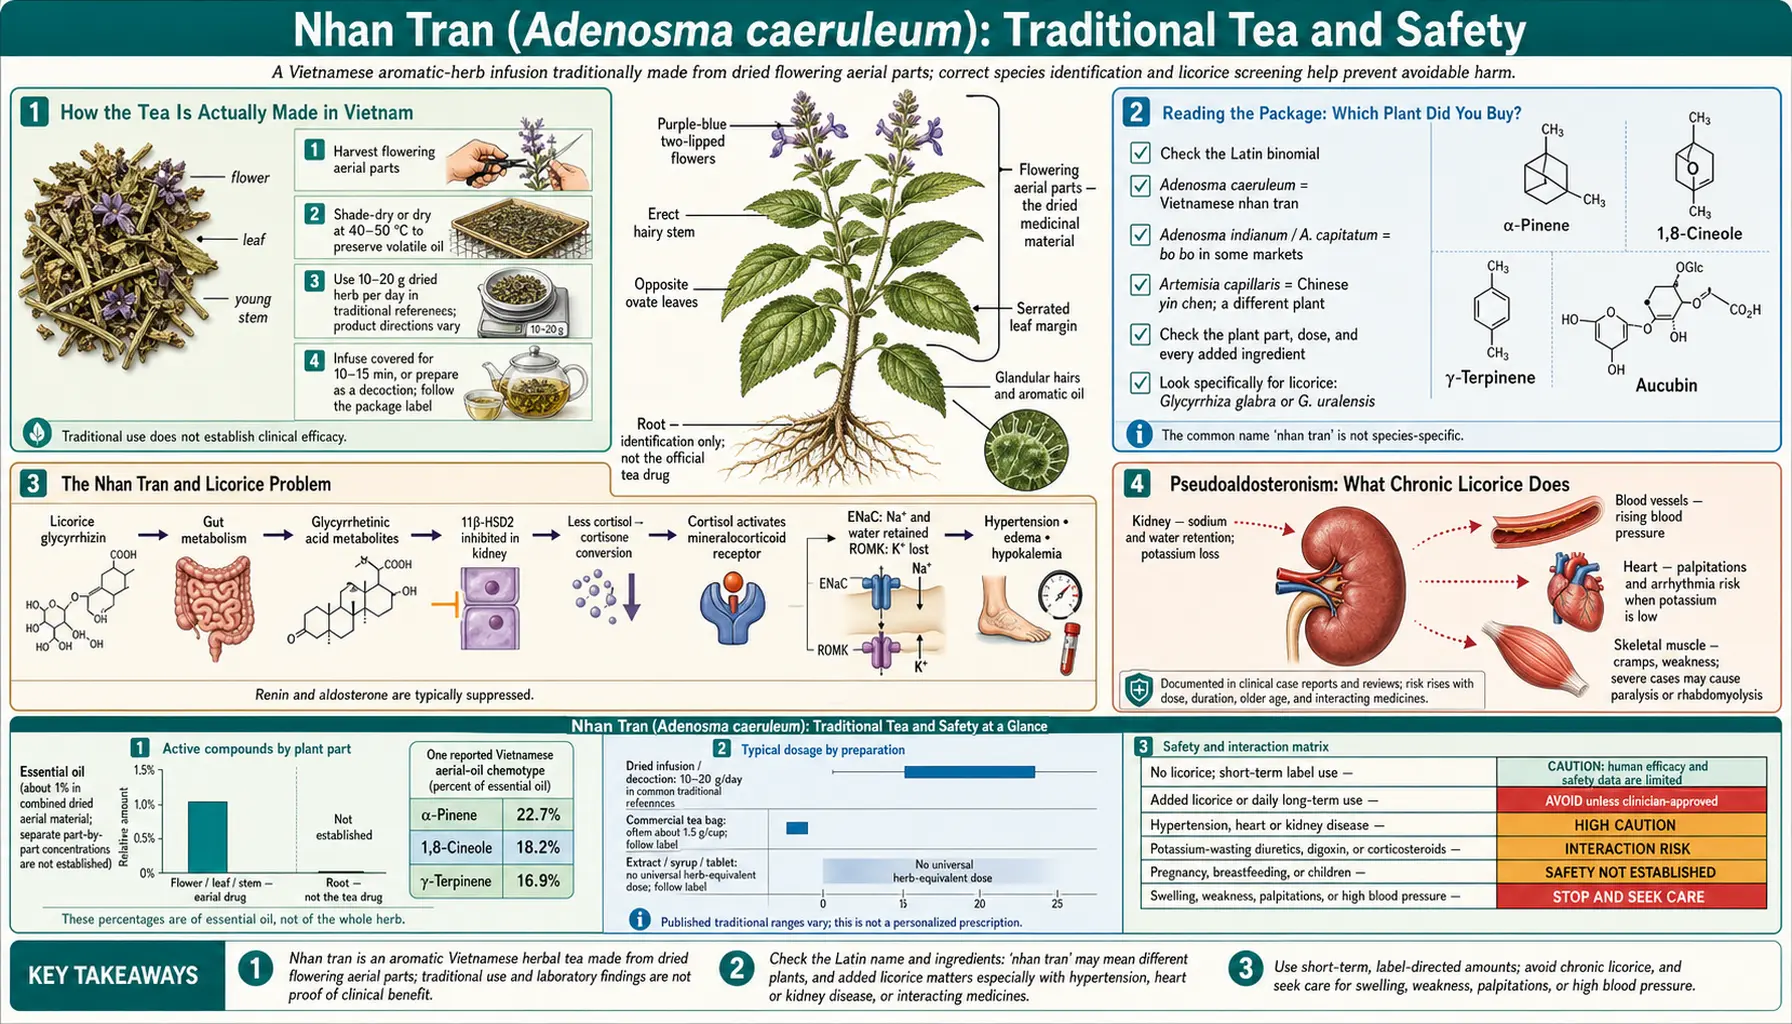
This is the most useful of the four Benefits pages, because the realistic risk from nhân trần is not the herb — it is the way it is packaged, blended and drunk. Millions of people in Vietnam drink this tea daily, most of them from a mixture that also contains licorice, and most of them have never been told that the two ingredients work against each other or that one of them has a documented dose-related toxicity.
The honesty statement first, as on every page in this set: there are essentially no randomized controlled trials of Adenosma caeruleum in humans, and no formal human toxicology either. "No reported harm" from a plant nobody has studied is not a safety record. What follows is built from the pharmacology that is established — most of it about licorice — plus traditional Vietnamese caution and general principles of herbal safety.
Table of Contents
- How the Tea Is Actually Made in Vietnam
- Reading the Package: Which Plant Did You Buy?
- The Nhan Tran and Licorice Problem
- Pseudoaldosteronism: What Chronic Licorice Does
- Pregnancy and Breastfeeding
- Where There Is No Safety Data At All
- Habit Versus Course: Two Different Exposures
- Drug Interactions Worth Thinking About
- Points Worth Knowing
- Key Research Papers
- Connections
- Featured Videos
How the Tea Is Actually Made in Vietnam
Nhân trần is sold as bundles of dried whole aerial plant — stems, leaves and flowering spikes cut at flowering and shade-dried — as loose chopped herb, as tea bags, and as ready-mixed blends. It is cheap, and it is stocked in ordinary markets rather than pharmacies.
The customary preparation is unfussy:
- Amount: a handful, commonly quoted as roughly 10–20 g of dried herb, per litre of water.
- Method: either poured over with just-boiled water and steeped 10–15 minutes like tea, or simmered gently for a similar time. Many households rinse the herb briefly with hot water first and discard that rinse, to wash off dust from open-air drying.
- Serving: drunk warm, or cooled and drunk through the day as an everyday beverage. A litre a day is unremarkable in hot weather.
- Season and context: heaviest use in hot months, after rich or fried food, during convalescence, and in the postpartum month, when Vietnamese custom favours warm herbal drinks over cold water.
Two things about that pattern matter more than any pharmacology. First, the dose is not measured — a "handful" varies severalfold between households. Second, it is consumed as a drink, not as a medicine, which means people rarely think about duration, cumulative dose, or what else is in the packet.
Reading the Package: Which Plant Did You Buy?
"Nhân trần" is a market name covering at least three unrelated plants. This is not a trivia point; it changes the chemistry of what is in your cup.
| Sold as | Actual species | Family | Characteristic chemistry |
|---|---|---|---|
| Nhân trần, nhân trần cái, chè cát | Adenosma caeruleum R.Br. | Plantaginaceae | Essential oil (~1%): limonene, fenchone, 1,8-cineole, α-humulene; flavonoids, saponins |
| Nhân trần Tây Ninh, bồ bồ | Adenosma bracteosum Bonati | Plantaginaceae | Related essential oil, different proportions |
| Nhân trần (in Chinese-medicine texts) | Artemisia capillaris Thunb. | Asteraceae | Coumarins (scoparone), capillarisin, chlorogenic acid — no relation chemically |
The chemistry of Adenosma caeruleum goes beyond its essential oil. A 2009 laboratory analysis of the plant’s aerial parts identified a new iridoid glycoside (named adenosmoside), five phenylpropanoids including verbascoside, and two apigenin flavonoids — so the plant also contains iridoids and phenylpropanoids, not only essential oil, flavonoids and saponins.
Practical consequences:
- Research does not transfer. The large hepatology literature on Yin Chen Hao (茵陈, Artemisia capillaris) is not evidence about Adenosma caeruleum. A seller quoting "clinical studies on nhân trần for jaundice" is almost certainly quoting the wrong plant.
- The botanical name is the check. A supplier who prints Adenosma caeruleum on the label has at least taken a position that can be checked. One who prints only "nhân trần" has not.
- Allergy matters here. Artemisia capillaris is in the daisy family, alongside ragweed, mugwort and chrysanthemum. Anyone with Asteraceae or mugwort allergy could react to it while tolerating Adenosma perfectly well — and would have no way of knowing which they had bought.
The Nhan Tran and Licorice Problem
This is the single most important safety item on the nhân trần pages.
Nhân trần is very commonly sold and drunk pre-blended with cam thảo — licorice root (Glycyrrhiza species). The reason is culinary: licorice is intensely sweet and rounds off a herb that tastes faintly bitter and medicinal. The blend is so normal that many people do not think of it as two herbs at all.
The problem is that the two are asked to do opposite things.
Nhân trần is used for its diuretic and bile-moving action — the whole traditional point is to move fluid and bile, to "clear heat," to make things flow.
Licorice does the reverse. Its principal constituent, glycyrrhizin, is hydrolysed in the gut to glycyrrhetinic acid, which inhibits the enzyme 11β-hydroxysteroid dehydrogenase type 2 (11β-HSD2) in the kidney. That enzyme's job is to convert cortisol into inactive cortisone in the cells lining the distal nephron, protecting the mineralocorticoid receptor from being swamped by cortisol, which circulates at far higher concentrations than aldosterone. Block the enzyme, and cortisol reaches and activates the mineralocorticoid receptor. The kidney behaves as though aldosterone were high: it retains sodium and water and dumps potassium.
So one component is being taken to promote fluid loss while the other actively promotes fluid retention. Pharmacologically they oppose each other. The result is not a balanced middle ground — it is two active agents pulling in opposite directions in a person who believes they are drinking a plain herbal beverage.
And the licorice half is not benign. It is the half with a well-documented, dose-related human toxicity.
Pseudoaldosteronism: What Chronic Licorice Does
The syndrome caused by sustained licorice intake is called apparent mineralocorticoid excess or pseudoaldosteronism. It is thoroughly described in the medical literature, with case reports going back decades and a clear mechanism. Its features:
- Hypokalaemia — low blood potassium, the central abnormality.
- Sodium and water retention — swelling of ankles, face and hands, and weight gain that is fluid, not fat.
- Rising blood pressure — sometimes substantially, sometimes into hypertensive-emergency territory in heavy users.
- Muscle cramps, weakness and fatigue — the classic consequences of low potassium. Severe cases progress to rhabdomyolysis, muscle breakdown that can damage the kidneys.
- Metabolic alkalosis, and suppressed renin and aldosterone on blood testing — which is the diagnostic fingerprint, because true hyperaldosteronism shows high aldosterone while licorice shows it low.
- Cardiac arrhythmias in severe hypokalaemia, which is how the rare fatal cases have occurred.
Two facts make this genuinely relevant to a daily tea rather than an exotic case report.
It happens at ordinary doses. Some regulators have used about 100 mg of glycyrrhizic acid a day as a guide intake, but a 2017 meta-analysis of 18 studies (337 people) in which people took at least 100 mg a day found that blood pressure rose — systolic by 5.45 mm Hg and diastolic by 3.19 mm Hg on average — while blood potassium, renin and aldosterone fell, and higher daily doses went with larger rises in blood pressure. The authors concluded that these effects appear even at modest doses. The guide figure is also a population average with wide individual variation, and susceptible people show changes below it. Effects have been reported from sustained intakes in the range of a few grams of licorice root per day — an amount easily present in a herbal blend drunk by the litre.
Susceptibility varies enormously. Women appear more sensitive than men. Older people, people already on diuretics, people with existing hypertension, heart failure, kidney disease or low potassium for any other reason, and people eating a low-potassium diet are all at higher risk. Some individuals have naturally lower 11β-HSD2 activity and react to modest amounts.
The onset is silent. Nobody notices their potassium falling. The first symptoms — tiredness, cramps, mild ankle swelling, a headache — are exactly the vague complaints people drink herbal tea for in the first place. That feedback loop is the real hazard: feeling unwell can lead someone to drink more of the thing making them unwell.
What this means in practice: for a daily nhân trần drinker, whether the tea contains cam thảo is the key question. Plain nhân trần carries none of the licorice risk, and the licorice risk grows with daily, unbroken use. It weighs most on people who already have high blood pressure, take a diuretic, or have kidney disease or heart failure; the 2017 meta-analysis authors noted that their findings are of particular relevance to people with existing cardiovascular disease. Recovery after stopping is usual but not instant — potassium and blood pressure can take weeks to normalise, because the enzyme inhibition outlasts the last cup.
Pregnancy and Breastfeeding
Vietnamese traditional practice itself cautions against habitual daily use of nhân trần in pregnancy and during breastfeeding. That is worth pausing on. Traditional medicine is generally permissive about its own remedies; when a tradition tells you to be careful with its own everyday tea, the caution deserves weight even without a trial behind it.
The traditional reasoning is that a herb used to promote fluid loss and clear "damp heat" is a drying agent, considered unsuitable for a state that requires expansion of blood volume and, later, milk production. Whether or not one accepts the framework, the conclusion is a cautious one.
Modern findings that point the same way:
- No human pregnancy data exists for Adenosma caeruleum. No developmental toxicity studies, no exposure registries, nothing.
- The licorice half has real pregnancy data, and it is not reassuring. Studies of high glycyrrhizin consumption during pregnancy have associated it with shorter gestation and with differences in cognitive and behavioural outcomes in the children, plausibly because 11β-HSD2 is also the placental enzyme that shields the fetus from maternal cortisol. Inhibiting it increases fetal cortisol exposure. In a Helsinki cohort of 378 children examined at about age 12.5, those whose mothers had eaten 500 mg or more of glycyrrhizin a week in pregnancy scored about 7 points lower on intelligence (IQ) tests, had poorer memory and had 3.3 times the odds of attention-deficit/hyperactivity disorder (ADHD) problems, compared with children whose mothers ate 249 mg a week or less; the exposed girls were also taller, heavier and further along in puberty. This was an observational study, which shows an association rather than proof of cause. It is a genuine, mechanistically coherent concern and it applies to any licorice-blended tea.
- Fluid balance in pregnancy is not something to nudge casually. Sodium retention and rising blood pressure are precisely what antenatal care watches for.
- Breastfeeding: no data on transfer of Adenosma constituents into milk, and no data on infant effects.
What this adds up to: Vietnamese tradition cautions against regular nhân trần use in pregnancy and breastfeeding, and licorice-blended versions carry the additional glycyrrhizin findings above. This is not the same as saying a single cup causes harm — the risk is unquantified and the benefit is unproven.
Where There Is No Safety Data At All
Complete blanks, stated as blanks:
- Liver failure and advanced liver disease. Ironic, given the traditional indication. A failing liver metabolises everything unpredictably, and herb-induced liver injury is a real and under-recognised category — the U.S. National Institutes of Health (NIH) maintains the LiverTox database precisely because of it. Nobody has studied this herb in a damaged liver.
- Biliary obstruction. A choleretic given when the duct is blocked pushes against a closed door. There is no evidence of benefit and a theoretical reason for concern. Obstruction is diagnosed by imaging and usually treated with a procedure.
- Children. No paediatric dosing, no toxicology, no trials. Children are not small adults — they have different body water fractions, different renal handling and different metabolic capacity. Herbal teas are widely given to children in Vietnam; that is custom, not evidence.
- Kidney disease. A herb used as a diuretic in a person with impaired kidneys is exactly where fluid and potassium disturbances become dangerous, and the licorice blend compounds it.
- Long-term use. No cohort has ever been followed. Years of daily consumption is entirely unstudied.
- Contaminants. Open-air-dried market herbs can carry pesticide residues, heavy metals from soil, and mould including aflatoxin-producing fungi if dried or stored damp. Nobody routinely tests bundles sold loose in a market. A musty rather than aromatic smell, visible mould or dust are signs of a damp-stored or contaminated batch.
Habit Versus Course: Two Different Exposures
The most useful distinction on this page, and the one most often missed.
Traditional herbal medicine, in Vietnam as elsewhere, mostly prescribes courses: a specific herb, for a specific complaint, for a limited period, then stop. The complaint resolves and the herb is put away. Under that pattern, cumulative exposure is small and self-limiting.
What happens with nhân trần is different. It has become a beverage — the thing in the flask on the table, drunk by the litre every day for years, in the absence of any complaint at all. That is a completely different exposure profile from the one traditional use implies, and it is the pattern under which slow, dose-dependent effects like pseudoaldosteronism actually appear.
The same shift explains many modern herbal problems: kava as an occasional ceremonial drink versus a daily standardised capsule; licorice as a confection versus a daily infusion; comfrey as a poultice versus a tea. Dose and duration turn a traditional remedy into a chronic exposure, and traditional safety experience does not cover the new pattern.
The exposure from a daily habit is smaller with a licorice-free product, with regular breaks — for instance a few weeks on, a few weeks off — rather than years of unbroken consumption, and with rotation among other unsweetened teas so no single plant becomes a daily lifelong exposure. Drunk as a pleasant infusion rather than as therapy, the tea stays closer to the traditional pattern.
Drug Interactions Worth Thinking About
Almost all of these come from the licorice component or from the diuretic-type action, not from anything demonstrated for Adenosma itself. That distinction is stated honestly rather than blurred.
- Diuretics (furosemide, hydrochlorothiazide, indapamide) — additive potassium loss. This combination is the classic route to symptomatic hypokalaemia.
- Digoxin — low potassium markedly increases digoxin toxicity. This combination has caused hospital admissions.
- Corticosteroids — glycyrrhetinic acid slows cortisol breakdown, effectively potentiating steroid exposure.
- Antihypertensives — licorice raises blood pressure and can undo treatment quietly.
- Antiarrhythmics and QT-prolonging drugs — hypokalaemia increases arrhythmia risk.
- Warfarin and other anticoagulants — no specific data for this herb, but any change in bile flow could in principle affect absorption of fat-soluble vitamin K. Such a change would show up in the international normalized ratio (INR) blood test used to monitor warfarin.
- Anything with a narrow therapeutic index — lithium, for example, is sensitive to fluid and sodium shifts. A daily diuretic tea is not a neutral background.
Most people describe their prescription medicines to their doctor and pharmacist and omit the litre of herbal tea. From a pharmacological standpoint, the tea is a daily dose of something.
Points Worth Knowing
- Cam thảo / licorice / Glycyrrhiza on the ingredient list marks a licorice blend — the part of the tea with documented daily-dose effects.
- The botanical name tells the plants apart. Adenosma caeruleum, Adenosma bracteosum and Artemisia capillaris are three different plants sold under one market name.
- Daily, indefinite use is the pattern under which slow effects such as pseudoaldosteronism appear; traditional courses had breaks.
- Pregnancy and breastfeeding: Vietnamese tradition cautions against regular use, and licorice in pregnancy is linked to the findings in children described above.
- Licorice blends raise blood pressure and lower potassium — systolic pressure rose by 5.45 mm Hg on average in studies of 100 mg or more of glycyrrhizic acid a day. That matters most for people with high blood pressure, heart failure, kidney disease or low potassium, or who take diuretics, digoxin or corticosteroids; low potassium makes digoxin more toxic.
- Jaundice is not a tea problem. Yellow eyes or skin, dark urine, pale stools or right-upper-abdominal pain are signs that hospitals investigate promptly with blood tests and an ultrasound.
- The quiet signs of low potassium are new muscle cramps, unusual weakness, palpitations, ankle swelling and rising blood pressure readings. A blood test shows the potassium level, and licorice-related changes usually reverse over weeks once the tea is stopped.
- Children: no paediatric safety data exist; “herbal” does not mean “safe for anyone.”
- Storage: a good batch smells aromatic, not musty, and keeps best airtight, dry and out of sunlight; mould is a sign of spoilage.
- Medication lists: a litre a day of an active plant is a daily dose that rarely makes it onto one.
Key Research Papers
Most identifiers below are given as live PubMed queries rather than quoted PMIDs; the three papers quoted with figures on this page link their checked PubMed records. Much of the Adenosma literature is Vietnamese-language and unindexed, and a fabricated identifier is worse than an honest search link. The licorice literature, by contrast, is large, English-language and easy to verify — start there.
- Clinical reviews of licorice-induced pseudoaldosteronism: mechanism, hypokalaemia, hypertension and case series. Search.
- Glycyrrhetinic acid inhibition of 11β-hydroxysteroid dehydrogenase type 2 and apparent mineralocorticoid excess. Search.
- Dose-response studies of glycyrrhizic acid on blood pressure and serum potassium in humans, and proposed tolerable intakes. Search.
- Licorice consumption in pregnancy and offspring outcomes, including gestational length and neurocognitive findings. Search.
- Placental 11β-HSD2 as the barrier to maternal cortisol, and consequences of its inhibition. Search.
- Licorice-induced rhabdomyolysis and severe hypokalaemia: reported cases. Search.
- Essential-oil composition of Adenosma caeruleum. Search.
- Herb-induced liver injury: recognition, causality assessment and under-reporting. Search.
- Heavy metals, pesticide residues and mycotoxins in traded medicinal herbs. Search.
- Patient non-disclosure of herbal product use to clinicians. Search.
- Penninkilampi R, Eslick EM, Eslick GD. The association between consistent licorice ingestion, hypertension and hypokalaemia: a systematic review and meta-analysis. Journal of Human Hypertension. 2017;31(11):699–707. — PubMed PMID: 28660884
- Räikkönen K, Martikainen S, Pesonen AK, Lahti J, Heinonen K, Pyhälä R, Lahti M, Tuovinen S, Wehkalampi K, Sammallahti S, Kuula L, Andersson S, Eriksson JG, Ortega-Alonso A, Reynolds RM, Strandberg TE, Seckl JR, Kajantie E. Maternal licorice consumption during pregnancy and pubertal, cognitive, and psychiatric outcomes in children. American Journal of Epidemiology. 2017;185(5):317–328. — PubMed PMID: 28158597
- De Abreu MB, Malafronte N, Van Kiem P, Braca A. A new iridoid from Adenosma caeruleum R. Br. Fitoterapia. 2009;80(6):358–360. — PubMed PMID: 19442709
PubMed Topic Searches
- PubMed: Adenosma caeruleum
- PubMed: Adenosma bracteosum
- PubMed: Glycyrrhizin toxicity
- PubMed: Licorice and hypertension
- PubMed: Hypokalaemia: causes and management
- PubMed: Digoxin toxicity and low potassium
- PubMed: Herbal tea safety in pregnancy
- PubMed: Aflatoxin in dried herbs
- PubMed: Vietnamese postpartum practices
- PubMed: Herbal species substitution
Connections
- All Herbs
- Nhan Tran (Adenosma caeruleum) — the full research article.
- Nhan Tran: History and Traditional Use — the name, the texts and the species muddle.
- Licorice — the half of the blend with the real toxicology.
- Milk Thistle — a liver herb with genuine human trial data.
- Dandelion — another traditional diuretic and bitter, with the same open questions.
- Chanca Piedra — folk hepatobiliary herb, thin evidence.
- Artemisia annua — a different Artemisia, useful for keeping the genus straight.