Nhan Tran (Adenosma caeruleum): Antimicrobial and Skin Uses
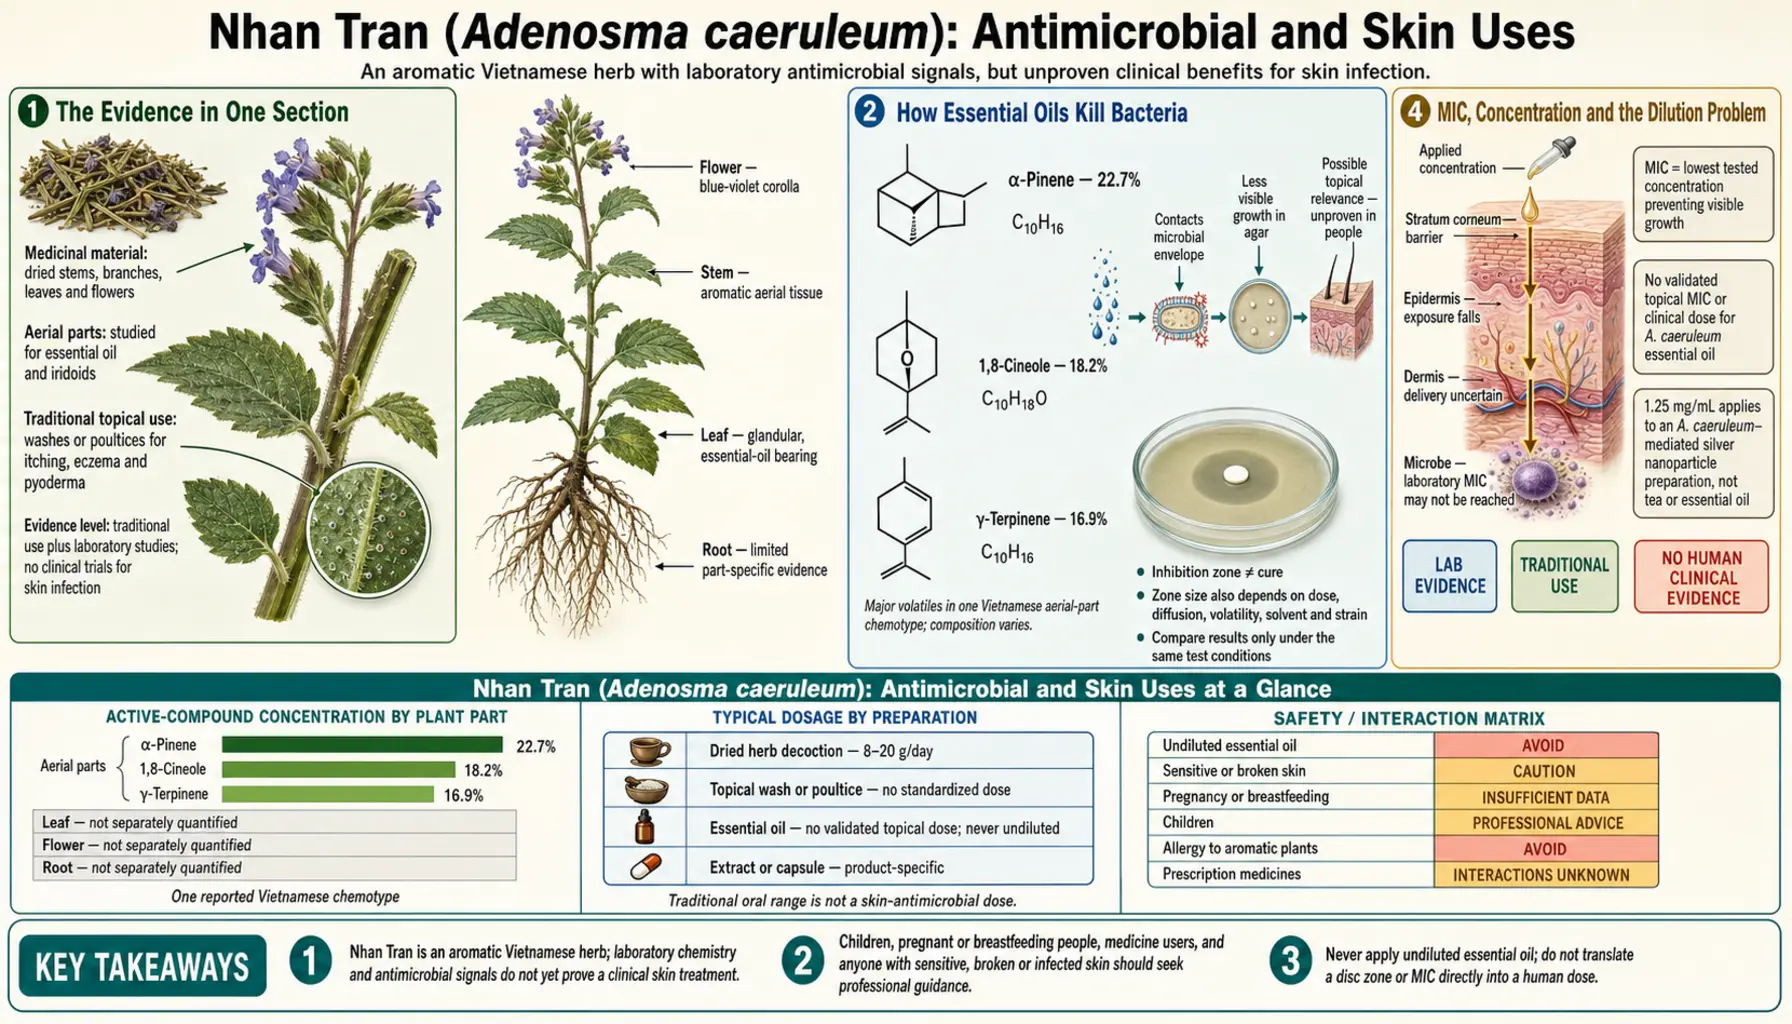
Search any aromatic herb and you will find papers reporting that its essential oil "exhibits significant antibacterial activity." For Adenosma caeruleum, no PubMed-indexed screen of its own essential oil against bacteria or fungi was found; the only indexed germ test on the plant used silver nanoparticles made with its extract (described below). Traditionally, the fresh or dried plant has also been used in Vietnam as a wash or steam for itchy skin, rashes and postpartum bathing.
The honest summary, first: there is no human trial of Adenosma caeruleum for any infection, internal or topical. Zero. The evidence is traditional topical use, one laboratory test of silver nanoparticles made with the plant’s extract, and laboratory work on a related species. This page explains what those screens actually measure, why a large inhibition halo is much less impressive than it looks, and why "kills bacteria in a petri dish" and "treats an infection in a person" are separated by a gap that most essential oils never cross.
Table of Contents
- The Evidence in One Section
- How Essential Oils Kill Bacteria
- Reading a Disc-Diffusion Result Honestly
- Minimum Inhibitory Concentration, Concentration and the Dilution Problem
- What Has Been Screened for Adenosma
- Traditional Washes, Steams and Baths
- Skin: Itch, Rash and the Postpartum Bath
- Why In-Vitro Is Not a Treatment
- What Is Known About Topical Use
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Evidence in One Section
Ranked from strongest to weakest, which for this topic is a short list:
- In-vitro screening against common test organisms — typically Staphylococcus aureus, Escherichia coli, Pseudomonas aeruginosa, Bacillus subtilis and Candida albicans. No indexed study was found that screens A. caeruleum essential oil this way. The indexed laboratory work is a 2026 test of silver nanoparticles made with the plant’s extract and a 2024 test of the oil of a related species, fleagrass (Adenosma buchneroides), against Candida albicans.
- Traditional topical use in Vietnam as a wash, bath or steam for itching, heat rash and postpartum care.
- Animal infection models — essentially absent for this species.
- Human trials, topical or systemic — none.
Note also the recurring species problem: screening papers do not always distinguish Adenosma caeruleum from Adenosma bracteosum (bồ bồ, "nhân trần Tây Ninh"), and material collected in a market as "nhân trần" may be either — or, in a Chinese-medicine context, Artemisia capillaris, a daisy-family plant with completely different chemistry. Antimicrobial results are oil-composition-dependent, so species and even harvest region change the answer.
How Essential Oils Kill Bacteria
Monoterpenes such as limonene, 1,8-cineole and fenchone are small, greasy, lipid-loving molecules. Their antimicrobial action is not a clever lock-and-key like penicillin binding a specific enzyme. It is closer to blunt force chemistry.
These molecules partition into the lipid bilayer of the bacterial cell membrane, wedging between the phospholipid tails. At sufficient concentration the membrane loses its ordered packing. It becomes leaky: potassium ions and protons escape, the proton-motive force that powers adenosine triphosphate (ATP) synthesis collapses, cell contents drain, and the cell dies. Fungal membranes, which contain ergosterol, are disrupted by a broadly similar mechanism.
Two consequences follow, and they explain everything else on this page.
First, it is broadly non-specific. A membrane is a membrane. What disrupts a bacterial membrane also disrupts human cell membranes at not-very-different concentrations. That is why essential oils have a narrow gap between "kills the germ" and "irritates the tissue" — the therapeutic window is thin. Penicillin, by contrast, attacks a structure humans do not have at all, which is why it can be given at doses thousands of times above its minimum inhibitory concentration.
Second, it is strictly concentration-dependent. There is no catalytic amplification. Dilute the oil enough and the membrane simply reorders itself and the bacteria grow. This is why the dose delivered by a cup of tea is essentially irrelevant to a bacterium living in your bladder.
Reading a Disc-Diffusion Result Honestly
The classic screening image — a plate lawn of bacteria with clear circles around little paper discs — is the Kirby-Bauer disc diffusion assay. A disc is loaded with test substance, placed on inoculated agar, incubated overnight; the substance diffuses outward and the diameter of the clear zone is measured in millimetres.
What it tells you: something in the sample inhibited growth of that organism under those conditions.
What it does not tell you, and this is where most popular reporting goes wrong:
- Zone size is not potency. Diameter depends heavily on how fast the compound diffuses through agar. Essential oils are hydrophobic and diffuse badly in a water-based gel, so an oil can be genuinely potent and produce a small halo, or moderately active and produce a big one. Comparing an oil's zone to an antibiotic's zone is close to meaningless.
- The concentration on the disc is usually enormous. Screens routinely load neat oil or 10–100 mg/mL solutions. Nothing remotely like that concentration reaches any tissue after drinking tea.
- It says nothing about killing versus inhibiting. A clear zone may mean the organism was killed or merely stopped from dividing while the compound was present.
- The solvent matters. Oils need dimethyl sulfoxide (DMSO), ethanol or a surfactant to disperse. Inadequate solvent controls are a common flaw in low-quality screening papers, and the solvent can produce its own halo.
- Laboratory strains are not clinical isolates. Standard collection strains are chosen for reproducibility, not for resembling the organism causing anyone's actual infection.
Thousands of plants have published disc-diffusion activity. The number that became antibacterial drugs is approximately zero. That is not because the assays were fraudulent — it is because the assay is the very first step of a very long road, and most candidates fail at the next one.
Minimum Inhibitory Concentration, Concentration and the Dilution Problem
A more informative measurement is the minimum inhibitory concentration (MIC): the lowest concentration that prevents visible growth, measured by serial dilution in broth. It gives a real number in µg/mL or mg/mL, and it can be compared across studies.
Typical MICs for monoterpene-rich essential oils against common bacteria fall in the range of roughly 0.5 to 10 mg/mL — that is, hundreds to thousands of micrograms per millilitre. For comparison, clinically useful antibiotics commonly have MICs measured in single-digit µg/mL or lower, a thousandfold difference.
Now run the arithmetic for a cup of tea. Dried nhân trần is about 1% essential oil. A generous 20 g of herb therefore contains at most about 200 mg of oil — and hot water extracts only a small, poorly-quantified fraction of that, because monoterpenes are barely water-soluble. Suppose, very generously, that 20 mg reaches the infusion and is fully absorbed. Distributed through roughly 40 litres of body water, that is about 0.0005 mg/mL — three to four orders of magnitude below the minimum inhibitory concentration, before accounting for first-pass liver metabolism, which is rapid for terpenes.
This is not a quibble. It is the reason no aromatic herbal tea has ever been shown to treat a systemic bacterial infection. The chemistry cannot reach the required concentration in a living body, and increasing the dose to close that gap would poison the person before it sterilised the bacterium.
Topical application is different in one respect: on skin, you can apply the actual concentration, without dilution into 40 litres of body water. That is why topical antiseptic uses of essential oils are at least mechanistically coherent, while oral antimicrobial claims usually are not.
What Has Been Screened for Adenosma
No indexed study was found that screens the essential oil of Adenosma caeruleum against bacteria or fungi (PubMed and Europe PMC searches). Much of the Adenosma literature is Vietnamese-language and unindexed, so such screens may exist, but this page cannot confirm what they report. What is indexed:
- Silver nanoparticles made with the plant’s extract (2026). Vietnamese chemists used an A. caeruleum extract to make silver nanoparticles and tested them in the lab. At a 30 µL dose the clear zones were 21.0 mm (Escherichia coli), 22.0 mm (Salmonella typhimurium), 14.0 mm (Bacillus cereus), 14.0 mm (Staphylococcus aureus) and 12.0 mm (Candida albicans), with Gram-negative bacteria generally more susceptible; the minimum inhibitory concentration was 1.25 mg/mL for all tested organisms. This tested the nanoparticles, not the herb as people use it in a wash or tea, and the abstract does not report the extract on its own.
- A related species, fleagrass (Adenosma buchneroides), 2024. Its essential oil showed high fungicidal activity against Candida albicans at 0.5% v/v in the lab, damaging the yeast’s cell wall and membrane. Fleagrass is a different species from nhân trần.
Essential oils in general show a Gram-positive/Gram-negative gradient: moderate activity against Gram-positive bacteria such as Staphylococcus aureus and Bacillus subtilis, weaker activity against Gram-negative organisms such as Escherichia coli and especially Pseudomonas aeruginosa. (The silver-nanoparticle study above found the reverse.) The gradient has a structural explanation. Gram-negative bacteria carry an additional outer membrane rich in lipopolysaccharide, which acts as a permeability barrier to hydrophobic molecules. Terpenes struggle to get through it. Gram-positives have a thick but comparatively porous peptidoglycan wall and no such outer membrane, so the oil reaches the cell membrane more easily.
The practical reading: nothing indexed distinguishes Adenosma oil from ordinary monoterpene-rich essential oils such as oregano, thyme, tea tree or clove oil, none of which are systemic antibiotics either.
Traditional Washes, Steams and Baths
Vietnamese folk practice uses aromatic herbs — nhân trần among many others including lemongrass, perilla and various mints — in three topical or semi-topical ways:
- Nước tắm / herbal bath water. A strong decoction added to bath water, used for heat rash, prickly heat and general itching in hot weather, and for infants in some households.
- Xông / steam inhalation. A pot of hot herbal decoction under a blanket. Aromatic and warming, traditionally used for colds and "wind" complaints. Whatever the herbal contribution, warm humid air itself loosens nasal secretions and feels good.
- Washes for skin complaints. Cooled decoction used to bathe rashes or minor irritations.
These uses are old, widespread and — at the dilutions actually used — generally well tolerated in adults. What they have never been is tested. There is no controlled trial of a nhân trần bath for anything.
Skin: Itch, Rash and the Postpartum Bath
Most of what a warm aromatic herbal wash does to itchy skin is probably not antimicrobial at all:
- Temperature. Cool or tepid water reduces itch directly; cooling terpenes such as 1,8-cineole and menthol-type compounds activate TRPM8 receptors, producing a cooling sensation that competes with itch signalling in the spinal cord.
- Cleaning. Washing removes sweat, salt, irritants and allergens. In a hot climate, that alone resolves a lot of "rashes."
- Ritual and relief. Twenty minutes of warm water and attention has genuine, non-mystical value, particularly postpartum.
A wash also carries different chemistry from the oil. Chemists who analysed the aerial parts of Adenosma caeruleum isolated a new iridoid glycoside named adenosmoside, five known phenylpropanoids including verbascoside, and two apigenin glycosides. These are glycosides (compounds bound to a sugar), a different class from the volatile oil; the study identified them but did not test them on germs or on skin.
The postpartum bath deserves a specific caution. Traditional Vietnamese postpartum practice includes hot herbal baths and steams. Modern obstetric advice is more careful here: it keeps perineal wounds and caesarean incisions clean and dry, not soaked in unsterile plant decoctions, and very hot steam near a fresh wound is a burn risk. Warm plain-water washing of the perineum is the standard recommendation. This is a case where the traditional practice and modern wound care genuinely disagree, and the modern advice is better supported.
Why In-Vitro Is Not a Treatment
Between a clear zone on an agar plate and a cure for an infection lie a series of hurdles, each of which eliminates most candidates:
- Concentration. Can the active concentration be achieved at the site of infection without poisoning the patient? For terpenes taken orally, almost never.
- Absorption and metabolism. Terpenes are rapidly oxidised and conjugated by the liver and excreted. Blood levels after oral dosing are low and short-lived.
- Selectivity. Does it harm the bacterium substantially more than the host cell? Membrane-active compounds score poorly here.
- Environment. Plates have no serum proteins, no pus, no biofilm, no immune cells and one organism at a fixed density. Real infections have all of those, and each blunts a hydrophobic compound.
- Proof. Even a compound clearing all of the above must show benefit in a controlled trial. None exists for this plant.
The stakes here are not abstract. Untreated bacterial infections — cellulitis, abscess, pyelonephritis, pneumonia, sepsis — progress. A person who chooses a herbal wash over antibiotics for spreading cellulitis is not making a gentle choice; they are losing time. Nhân trần is not a substitute for an antibiotic in a diagnosed bacterial infection, and nothing on this page suggests otherwise.
What Is Known About Topical Use
For an ordinary itchy heat rash on intact skin, a traditional herbal wash is a low-stakes practice. The relevant facts:
- Patch testing. A patch test applies the cooled decoction to a small area of forearm and checks it after 24 hours. Contact dermatitis to plant material is common, and an aromatic oil-bearing plant is a plausible sensitiser.
- Decoction versus essential oil. The traditional preparation is the decoction, not the essential oil. Undiluted essential oil of any species is a skin hazard; dilutions described for skin are about 1% in a carrier — roughly 6 drops per 30 mL.
- Broken skin, wounds, burns and surgical incisions. An unsterile plant decoction on an open wound is an infection risk.
- Infants. Infant skin is thinner, absorbs more, and 1,8-cineole and camphor-type compounds have caused respiratory problems in young children when applied near the face.
- Stinging, redness or spreading. Worsening after application points to irritation or allergy, not healing.
- Signs of a spreading skin infection: spreading redness, warmth, fever, pus, red streaking, a rash that blisters or peels. These, and any rash in someone immunosuppressed or diabetic, are signs that clinics treat as urgent.
Cautions
- Not an antibiotic. No systemic antimicrobial use is supported for this herb. A real bacterial infection left without antibiotics progresses (see above).
- Contact allergy. Aromatic plants are a recognised source of allergic contact dermatitis; limonene in particular oxidises on air exposure into known skin sensitisers.
- Swallowing concentrated essential oil. Terpene ketones such as fenchone are considerably more toxic than the infusion, and no safe oral dose has been established.
- Pregnancy and breastfeeding. Vietnamese tradition cautions against habitual internal use, and no modern safety data exist for internal or topical use.
- Children. No safety data. Essential oil near the face of an infant or young child is the specific concern (see above).
- Licorice blends. For people drinking the tea rather than washing with it, the Traditional Tea and Safety page covers the cam thảo blend — the real practical hazard of this herb.
Key Research Papers
Identifiers are given as live PubMed queries rather than quoted PMIDs. Much of the Adenosma literature is Vietnamese-language and unindexed, and a fabricated identifier is worse than an honest search link. The three indexed Adenosma studies are cited by PMID.
- De Abreu MB, Malafronte N, Van Kiem P, Braca A. A new iridoid from Adenosma caeruleum R. Br. Fitoterapia. 2009;80(6):358–360. PubMed PMID: 19442709
- Nguyen VS, Vo TC, Van TK, Vo TK. Green synthesis of silver nanoparticles using the extract of Adenosma caeruleum R.Br.: evaluation of antibacterial, antifungal and antioxidant activity. Applied Biochemistry and Biotechnology. 2026;198(10):8038–8059. PubMed PMID: 42406010
- Wu Y, Zhang H, Chen H, Du Z, Li Q, Wang R. Fleagrass (Adenosma buchneroides Bonati) acts as a fungicide against Candida albicans by damaging its cell wall. Journal of Microbiology. 2024;62(8):661–670. PubMed PMID: 38958871
- Antibacterial and antifungal screening of Vietnamese medicinal plant essential oils. Search.
- Reviews of essential-oil antibacterial mechanism: membrane partitioning, proton-motive force collapse and ion leakage. Search.
- Why Gram-negative bacteria resist hydrophobic agents: the lipopolysaccharide outer-membrane barrier. Search.
- Methodological critiques of disc-diffusion testing for essential oils and the case for MIC-based reporting. Search.
- Tea tree oil (Melaleuca alternifolia) — the best-studied topical essential-oil antiseptic, useful as a benchmark for what a positive human topical result looks like. Search.
- Oxidised limonene as a contact allergen. Search.
- Safety of 1,8-cineole and camphor-type compounds applied near the face in young children. Search.
- Perineal and caesarean wound care after childbirth: evidence-based practice. Search.
PubMed Topic Searches
- PubMed: Adenosma antimicrobial
- PubMed: Adenosma bracteosum essential oil
- PubMed: Essential oil MIC vs S. aureus
- PubMed: Limonene antibacterial activity
- PubMed: 1,8-Cineole antimicrobial
- PubMed: Herbal baths and dermatitis
- PubMed: Delayed antibiotics in cellulitis
- PubMed: Contact dermatitis from plant oils
- PubMed: Essential oils and biofilms
- PubMed: TRPM8 cooling and itch
Connections
- All Herbs
- Nhan Tran (Adenosma caeruleum) — the full research article.
- Nhan Tran: History and Traditional Use — the name and the species confusion.
- Artemisia annua — the rare case where a traditional herb did yield a real drug.
- Licorice — the usual blend partner in nhân trần tea.
- Dandelion — another everyday folk herb with modest evidence.
- Milk Thistle — for comparison, a herb with real human trial data.
- Chanca Piedra — folk remedy, thin evidence, similar reasoning applies.