Hibiscus: Brewing, Dosing and Cautions
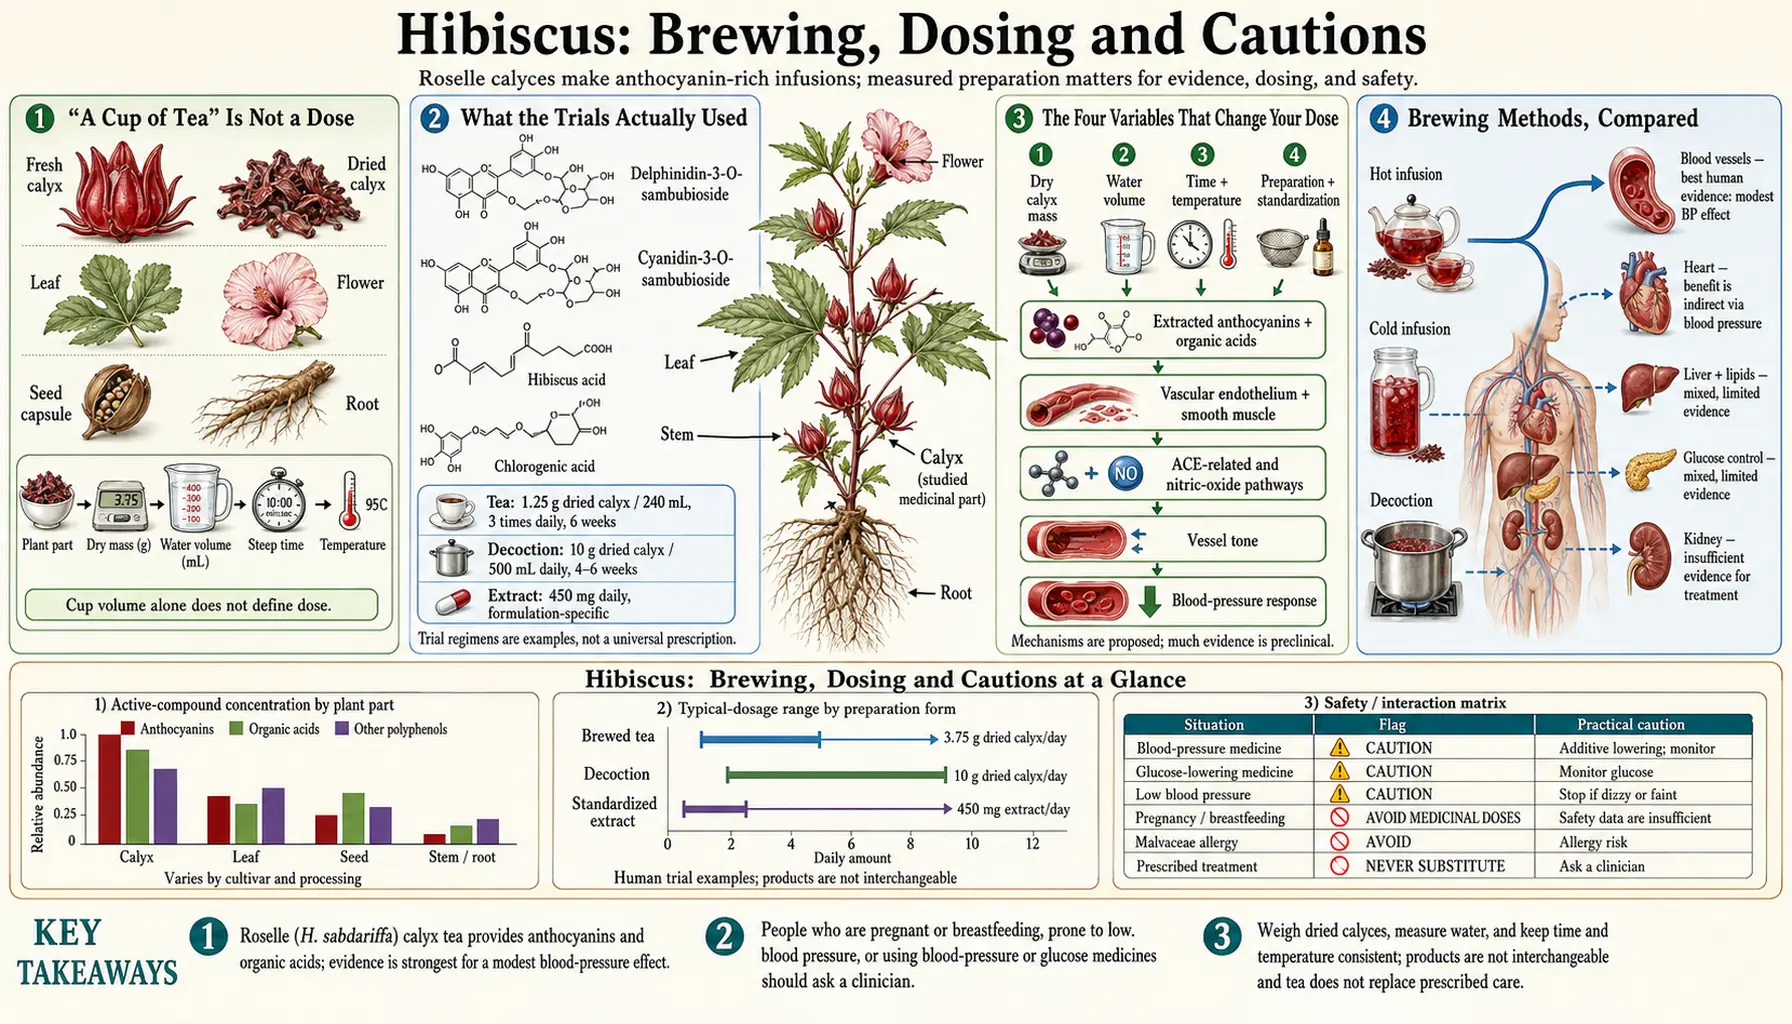
Every article about hibiscus eventually says something like “two to three cups a day.” It is a comforting sentence and it is close to meaningless, because a cup of hibiscus tea is not a defined quantity of anything. Two people can follow that advice to the letter and one of them can be drinking three or four times as much active material as the other.
This article is about closing that gap: what the trials actually gave people, which brewing variables move the dose and by how much, and how to make your cup repeatable enough that you could actually tell whether it is doing anything. Then it deals properly with the cautions — not a token paragraph, but the documented interactions with real numbers attached, and the honest gaps where nobody has done the study.
Table of Contents
- “A Cup of Tea” Is Not a Dose
- What the Trials Actually Used
- The Four Variables That Change Your Dose
- Brewing Methods, Compared
- Making It Repeatable
- Forms: Calyces, Bags, Powders, Extracts
- Sweetening Without Undoing It
- Drug Interactions: What Is Documented
- Pregnancy and Breastfeeding
- Other Cautions
- Warning Signs Worth Knowing
- Key Research Papers
- Connections
- Featured Videos
“A Cup of Tea” Is Not a Dose
Think about what varies between two people who both say they drink hibiscus tea daily.
One uses a supermarket tea bag — typically around 2 g of blended material, of which hibiscus may be a minority ingredient behind rosehip and apple — steeped three minutes in 200 mL. The other packs a level tablespoon of whole dried calyces, roughly 5 g of pure roselle, into a 400 mL mug, steeps it fifteen minutes and presses the calyces against the strainer on the way out.
Both had “a cup of hibiscus tea.” The second person consumed something in the region of five to ten times as much extracted plant material as the first. If hibiscus has a dose–response relationship — and every pharmacologically active substance does — those are not the same intervention.
This vagueness is not just a personal problem. It is a substantial part of why the clinical literature is so heterogeneous. A 2022 meta-analysis of 17 trials (Ellis and colleagues) found that hibiscus lowered systolic blood pressure by 7.10 mmHg more than placebo, with an I² of 95 percent — a measure meaning the individual trials’ results differed widely — and its authors called for more studies to establish an effective dose and treatment duration. A larger 2025 pooled analysis of 26 randomised trials with 1,797 people found that the fall in systolic and diastolic blood pressure grew with the dose. Trials that describe their intervention as “hibiscus tea” without a weight, a volume and a steep time are not describing a reproducible treatment.
What the Trials Actually Used
Here is what can be said precisely, and where the record is vaguer.
| Trial | Preparation | Schedule |
|---|---|---|
| McKay 2010 (Tufts) | Brewed hibiscus tea from a standardised sachet, against a matched placebo beverage | Three 240 mL servings daily for six weeks — the clearest dosing statement in the literature |
| Herrera-Arellano 2004 (vs captopril) | An infusion of 10 g of dried calyx in about 0.5 L of water, carrying 9.6 mg of total anthocyanins | Once daily before breakfast, four weeks; compared with captopril 25 mg twice a day (50 mg/day), with no significant difference in blood-pressure effect |
| Herrera-Arellano 2007 (vs lisinopril) | A standardised herbal medicinal product, dosed on total anthocyanin content rather than plant weight: 250 mg of total anthocyanins per dose | Once daily, four weeks; blood pressure fell by 17/12 mmHg (from 146/98 to 130/86), less than with lisinopril 10 mg |
| Mozaffari-Khosravi 2009 | Sour-tea infusion, compared against black tea, in 60 people with type 2 diabetes and mild high blood pressure | Twice daily for one month; systolic pressure fell from 134.4 to 112.7 mmHg |
| Chang 2014 (obesity) | Concentrated hibiscus extract in capsules | Daily, twelve weeks |
Two patterns are worth extracting from that table. First, the tea trials cluster around one to three servings a day for four to six weeks (one strong infusion a day in the 2004 trial) — that is the schedule with evidence behind it, and it is a habit rather than a dose taken when you remember. Second, the more rigorous trials moved away from plant weight entirely and dosed on total anthocyanins in milligrams, because plant weight is not a reliable proxy for content. Figures on the order of a couple of hundred milligrams of total anthocyanins per day are commonly quoted for the standardised-extract trials; the 2007 trial used 250 mg per dose, once a day, while the 2004 infusion of 10 g of calyx carried 9.6 mg.
What nobody can give you is a conversion factor. There is no defensible arithmetic that turns “250 mg total anthocyanins” into “X grams of the dried calyces in your cupboard,” because the anthocyanin content of dried calyx varies severalfold with cultivar, growing conditions, harvest timing, drying method and age, and your extraction efficiency is unknown. Anyone who gives you a precise conversion has made it up.
The Four Variables That Change Your Dose
1. How much calyx
The largest single variable and the easiest to fix. Volume measures are terrible for a bulky, irregular, springy material: a “teaspoon” of whole dried calyces and a “teaspoon” of cut-and-sifted hibiscus differ enormously in mass, and heaped versus level is another factor of two. A cheap digital kitchen scale eliminates the problem permanently.
A range of 1.5 to 2.5 g of dried calyx per 240 mL cup is a common everyday strength. That sits in the region of what tea trials have used and produces a drink most people find strong but tolerable.
2. Water temperature
Extraction of both the pigments and the organic acids is strongly temperature-dependent. Freshly boiled water (around 95–100 °C) extracts fast and hard. Water at 80 °C extracts noticeably less in the same time. Cold water extracts slowly — but given enough hours it gets there, and it pulls fewer of the harsh astringent compounds, giving a rounder drink.
There is a trade-off: prolonged high heat also degrades anthocyanins. A hard rolling boil for twenty minutes extracts a great deal and destroys some of what it extracted. A steep in freshly boiled water off the heat balances the two.
3. Steep time
The most under-appreciated variable, because colour saturates long before extraction finishes. Within two minutes the water is already vividly red and looks done. It is not. Acids and phenolics keep coming out for another ten to fifteen minutes with essentially no further visual change. Judging strength by eye systematically under-doses a short steep and gives you no warning.
A timer measures the steep; the colour does not.
4. Whether you press the calyces
Rehydrated calyces swell and hold a surprising amount of concentrated liquor. Pressing them against the strainer with the back of a spoon recovers it and meaningfully raises the yield. Whether the calyces are pressed is a real dose variable, so a cup made the same way each time keeps it constant.
Brewing Methods, Compared
| Method | How | Relative strength | Character |
|---|---|---|---|
| Hot steep (default) | 2 g calyx per 240 mL freshly boiled water, covered, 8–10 minutes, strain | Reference point | Bright, sharp, clean. Covering the cup keeps aromatics in |
| Long hot steep | Same, 15–20 minutes | Noticeably stronger | More astringent and tannic; some people find it harsh |
| Decoction / simmer | Simmer calyx in water 10–15 minutes | Strongest per gram | Traditional for agua de Jamaica and sorrel; deepest colour, some pigment loss to heat |
| Cold brew | Same weight in cold water, refrigerated 8–12 hours | Comparable to a hot steep if given the full time; weaker if rushed | Smoothest and least astringent, so the easiest to drink unsweetened |
| Concentrate | Brew at 4× strength, dilute at serving | Whatever you dilute to | Practical for iced drinking; makes daily consistency easy |
| Tea bag | Per packet | Usually weakest — often a blend | Convenient, consistent, but hibiscus is not always even the first ingredient |
| Capsule / extract | Per label | Whatever the label states | The only form with a stated milligram dose — if the label states anthocyanin content |
A note on the concentrate method: it answers the consistency problem directly. A litre brewed at four times strength keeps in the fridge for up to about five days, and a measured amount is poured into a glass with water and ice. Every serving is then identical, which is exactly what the tea-bag drinkers get automatically and the loose-calyx drinkers usually do not.
Making It Repeatable
Telling whether hibiscus does anything for one person needs the drink to stop being a variable. The steps that make it repeatable:
- One bag of one product, finished before switching. Different calyces are different material.
- Weighing rather than scooping, with the number written on the jar.
- A fixed water volume — a marked mug or the same vessel every time.
- A timer. Same steep, every time.
- One decision about pressing, kept.
- A fixed schedule. One to three servings daily is the trial pattern; the same times each day make it a habit rather than a decision.
- Six weeks. Effects in the literature appear over two to eight weeks of daily use. A single cup measures nothing.
- Something tracked. For blood pressure, that means home readings taken properly — a week of morning and evening readings before starting, and another week at the end, compared as weekly averages.
None of this is glamorous. It is the entire difference between “I drink hibiscus, I think it helps” and actually knowing.
Forms: Calyces, Bags, Powders, Extracts
- Whole dried calyces — the best default. Cheapest per gram, keeps longest, easiest to assess by eye. Good calyces are deep crimson, not brown. Sold as flor de Jamaica, karkade, bissap, sorrel or roselle.
- Cut and sifted — more surface area, faster extraction, faster degradation in storage. It suits quick use.
- Tea bags — convenient and consistent, but the ingredient list matters. Many “hibiscus” blends lead with rosehip and apple and use hibiscus mainly for colour. If hibiscus is not first on the list, the drink is mostly something else.
- Powder — convenient for smoothies, degrades fastest, and the fine grind makes adulteration easy to hide, so the supplier matters more than for whole calyces.
- Capsules and standardised extracts — the only form that can give a real dose figure, but only if the label states total anthocyanin content in milligrams per capsule. A “10:1 extract” claim without a marker compound is a ratio, not a dose, and says nothing that can be compared to a trial.
What a label can show
| Element | What a good product says | Red flag |
|---|---|---|
| Species | Hibiscus sabdariffa L. (roselle) | “Hibiscus flower” with no species |
| Plant part | Calyx / calyces | “Flower,” “petals,” or unspecified |
| Position in a blend | First ingredient, or sole ingredient | Third, after rosehip and apple |
| Marker content (extracts) | Total anthocyanins in mg per capsule | “10:1” or “standardised” with no marker named |
| Colour | Deep crimson to burgundy | Brown, dull, faded orange |
| Testing | Named third-party lab, certificate available | A GMP logo and nothing else |
Sweetening Without Undoing It
Hibiscus is genuinely, aggressively sour — a brewed infusion sits at pH 2.5 to 3 — and almost nowhere in the world is it drunk unsweetened. Agua de Jamaica, bissap, karkade and Jamaican sorrel are all sweetened, frequently heavily. A large sweetened glass can carry as much added sugar as a soft drink, which is enough to erase any metabolic benefit several times over (the arithmetic is laid out in the Cholesterol and Metabolic article).
Ways people cut the sugar:
- Brewing it weaker. Most people over-extract and then need sugar to survive the result.
- Cold-brewing it. Far less astringent, which removes much of the reason to sweeten.
- Serving it very cold. Cold substantially blunts perceived sourness.
- Aromatics instead of sugar. Mint, fresh ginger, cinnamon stick, cloves, allspice, star anise, lemongrass, a strip of orange zest. Ginger and cinnamon in particular read as sweetness without being sweet.
- Tapering. Cutting the sugar by a quarter every fortnight. Sour tolerance is trainable and the change is barely noticeable step by step.
- Blending. Half hibiscus, half unsweetened rooibos or mint tea makes a gentler drink that still carries plenty of hibiscus.
Drug Interactions: What Is Documented
Hibiscus is a food, and it is also demonstrably pharmacologically active. That combination is exactly the profile that produces herb–drug interactions. What follows is what has actually been published, with the study species named — not a list of theoretical concerns.
Antihypertensive medicines — additive effect
This one is straightforward pharmacology rather than a specific study finding: hibiscus lowers blood pressure, blood-pressure tablets lower blood pressure, and the effects add. That is usually harmless and occasionally not, particularly in older people, in people whose pressure already runs low or who take several agents, and in people who start drinking hibiscus in quantity all at once.
The trials show the size of the drop, measured with hibiscus given on its own: three 240 mL cups a day lowered systolic pressure by 7.2 mmHg against 1.3 mmHg with placebo over six weeks (McKay 2010); a strong daily infusion took it from 139 to 124 mmHg in four weeks (Herrera-Arellano 2004); and a standardised extract lowered it by 17/12 mmHg (Herrera-Arellano 2007). A drop of that size arriving on top of a tablet is what makes the effect additive. New dizziness or light-headedness on standing is the usual sign that pressure has fallen too far, and a home blood-pressure reading shows it.
Chloroquine — substantially reduced absorption (human)
The most striking interaction in the hibiscus literature, and it is a human study. Mahmoud and colleagues in Khartoum gave healthy male volunteers 600 mg of oral chloroquine on an empty stomach, washed down either with water or with one of three common Sudanese beverages, and measured plasma chloroquine by HPLC.
With water, mean total exposure (AUC) was 7.52 mg·h/L. With karkadi — hibiscus — it was 2.16. That is roughly a 71 percent reduction in the amount of drug that reached the circulation. Peak concentration fell by a similar proportion. The authors’ own conclusion was that a parallel reduction in the drug’s antimalarial efficacy might be expected.
Two honest qualifications. Tamarind and lemon produced very similar reductions, so this may be a property of acidic beverages generally rather than something specific to hibiscus. And it was a single dose on an empty stomach, which maximises any absorption effect. But the size of the signal is large, the consequence of under-dosing an antimalarial is serious. The comparison in the study was plain water, with which chloroquine reached its full exposure.
Hydrochlorothiazide — altered handling (animal)
Ndu and colleagues at the University of Nigeria examined hibiscus extract alongside hydrochlorothiazide in rats and rabbits, and the result runs opposite to intuition.
Co-administration increased and prolonged the plasma concentration of hydrochlorothiazide, raised its area under the curve and its volume of distribution over a 24-hour sampling period, and reduced its plasma clearance and elimination rate constant — with the effect growing as the hibiscus dose rose. In other words the animals were retaining more drug for longer, not less. On the pharmacodynamic side, the combination increased urine volume and lowered urinary pH and the concentrations of sodium, bicarbonate and chloride.
This is an animal study, and animal pharmacokinetics translate imperfectly to humans. But hydrochlorothiazide is one of the most widely prescribed antihypertensives in exactly the populations where hibiscus is a daily beverage, and the finding points in the direction of more drug effect, not less — more diuresis, potentially lower pressure, and electrolyte shifts on top. Shifts in sodium, potassium and chloride are what periodic blood tests for electrolytes detect.
The Nigerian clinical group has looked at the human side of this: Nwachukwu and colleagues compared hibiscus against hydrochlorothiazide directly in hypertensive volunteers and measured the electrolyte profile, and in separate studies examined renin–angiotensin–aldosterone activity and renal function.
Simvastatin — reduced exposure (human)
Showande and colleagues gave six healthy volunteers a single 40 mg dose of simvastatin with and without a hibiscus beverage, in a randomised crossover design. The beverage increased simvastatin clearance by about 45 percent and reduced peak concentration by 18 percent. The geometric mean ratio for total exposure was 0.646 (90% confidence interval (CI) 0.564–0.758) — outside the accepted bioequivalence range, meaning roughly a third less drug.
Six people and a single dose is a signal, not a settled fact, and other statins have not been tested. But the authors concluded that “co-administration of the beverage with simvastatin should be discouraged until more clinical data are available.” Their study gave the drug with and without the beverage; it did not test a time gap between the two.
Acetaminophen (paracetamol) — a modest elimination effect (human)
This one is frequently overstated, so here it is precisely. Kolawole and Maduenyi gave six healthy male volunteers 1 g of acetaminophen, once alone and once after a zobo drink (hibiscus water extract).
The absorption parameters did not change significantly — not the absorption half-life, not the absorption rate constant, not the time to peak, not the peak concentration, not total exposure. What did change significantly were the elimination parameters, with total clearance increasing by about 11.7 percent.
An 11.7 percent change in clearance of a drug with a wide therapeutic window, in six people, is worth knowing about and is not a reason for alarm. It does illustrate the general point: hibiscus is not pharmacologically inert.
Diclofenac (human)
Fakeye and colleagues studied a water extract of Hibiscus sabdariffa and its effect on the excretion of a diclofenac formulation in human volunteers — another indication that hibiscus interacts with the handling of common drugs. (Note for anyone chasing citations: this Fakeye paper is about diclofenac, and is frequently miscited elsewhere as a paracetamol study. The paracetamol work is the separate Kolawole paper above.)
The general rule
Across chloroquine, simvastatin, hydrochlorothiazide, acetaminophen and diclofenac, the pattern is that hibiscus alters how drugs are absorbed and cleared — sometimes up, sometimes down.
In the human studies the comparison was the drug taken with plain water or without the hibiscus drink; none of them tested how many hours apart the two need to be. Drugs with a narrow therapeutic window — warfarin, lithium, digoxin, thyroid hormone, anti-epileptics, transplant immunosuppressants — are the ones where small changes in blood level matter most, and none of them has been studied with hibiscus. Where an interaction is possible but unmeasured, a steady daily amount keeps any effect on blood levels steady too, while an amount that varies widely week to week makes the effect vary with it.
Pregnancy and Breastfeeding
This deserves its own section because the honest answer is uncomfortable and often glossed over.
Roselle carries a long-standing traditional reputation as an emmenagogue — a substance believed to stimulate menstrual flow — across several of the cultures that use it most heavily. Traditional reputation is not evidence of effect, and plenty of emmenagogue claims do not survive testing. But in this case there is also a body of animal reproductive and developmental work, and it is not reassuring at higher doses: rodent studies have reported effects relevant to pregnancy and offspring at substantial extract doses.
- Puberty and weight in the offspring (rats, 2008). Pregnant rats given hibiscus extract as their drinking water throughout pregnancy had offspring with greater weight gain after birth, later onset of puberty and a higher body mass index at puberty, linked to higher sodium and corticosterone (a stress hormone) in the mothers’ blood during pregnancy.
- Male reproductive development (rats, 2016). Pregnant rats given 250 or 500 mg/kg of hibiscus extract from mid-pregnancy to the end of nursing had male offspring with fewer sperm in the epididymis at puberty; in adulthood the higher dose reduced sperm production. The authors concluded that exposure in the womb can adversely influence the male reproductive system in rats.
These are animal studies only, using extract given every day across pregnancy, not occasional cups of tea.
There is no adequate human safety data on medicinal hibiscus use in pregnancy. No trial has enrolled pregnant women, for the obvious ethical reason.
What this adds up to:
- Medicinal or large daily amounts during pregnancy are where the concern lies. A daily litre of strong hibiscus is a therapeutic habit, not a beverage choice.
- Occasional culinary amounts are a different question — a glass of agua de Jamaica at a family meal is not the same exposure — but nobody has tested where the line is, and “probably fine” is the most anyone can honestly offer.
- Breastfeeding has the same gap: absence of data rather than evidence of harm.
- For someone who has already been drinking it while pregnant, this is not cause for alarm: the animal findings come from extract given every day across pregnancy.
It is worth being clear about what kind of statement this is. It is not “hibiscus is dangerous in pregnancy.” It is “hibiscus is pharmacologically active, has a traditional reputation specifically involving the uterus, has animal data that raise questions, and has no human safety data in pregnancy.”
Other Cautions
Low blood pressure and fainting on standing
The mechanism that helps hypertension is unhelpful for people who already run low or get light-headed on standing: for them, hibiscus in quantity adds to the problem.
Surgery
Pre-surgery instructions for pharmacologically active botanicals commonly ask for them to be stopped about two weeks before elective surgery and reported to the anaesthetist. Blood pressure under anaesthesia is managed tightly and an unreported daily antihypertensive habit is an unnecessary variable.
Diuretic effect and electrolytes
Hibiscus has a demonstrated diuretic effect in animals, characterised pharmacologically by Alarcón-Alonso and colleagues and examined alongside toxicity by Njinga and colleagues. In people at drinking amounts it is mild. It becomes relevant for people who already take a diuretic, have kidney disease, or have a history of electrolyte problems — periodic blood tests are how electrolyte shifts show up in them.
Kidney function
Nwachukwu and colleagues specifically asked whether an aqueous hibiscus extract affected renal function in people with mild to moderate hypertension — the right question to ask of anything with a diuretic action. That such studies exist is reassuring; that they are small is the usual caveat.
Liver
Very high extract doses in animals have raised questions about liver effects, and Njinga and colleagues assessed sub-acute and sub-chronic oral toxicity directly. Nothing here indicates a problem with ordinary tea drinking. It is a reason not to assume that a very concentrated extract is simply “more of a nice tea”: concentrated extracts of anything deliver far more per dose than the whole plant. In people, a 2025 pooled analysis of 26 randomised trials (1,797 participants) found a small rise in the liver enzyme aspartate aminotransferase (AST) that the authors judged clinically insignificant, with no increase in adverse events.
Tooth enamel
An underrated practical issue. At pH 2.5 to 3 hibiscus is in the range that erodes enamel over time, comparable to cola or citrus juice. Dental guidance for acidic drinks in general lists drinking through a straw, rinsing with plain water afterwards, not sipping continuously across a whole afternoon, and waiting at least half an hour before brushing — brushing acid-softened enamel does more damage than the acid alone.
Stomach
The same acidity can provoke reflux or discomfort on an empty stomach. Taken with or after food, it usually causes less trouble.
Iron absorption
Like all polyphenol-rich beverages, hibiscus can reduce the absorption of non-haem (plant) iron when drunk with a meal. For people treating iron deficiency, the effect is smallest when the tea is drunk between meals rather than with them, and apart from an iron supplement.
Children
Hibiscus is a traditional family drink in many countries and is not considered hazardous for children as a beverage. Concentrated extracts and capsules are a different matter and have not been studied in children.
Allergy
Uncommon but real. Mallow-family sensitivity exists, and hibiscus pollen is a recognised allergen in some settings.
Warning Signs Worth Knowing
Straightforward triggers, worth keeping in mind precisely because hibiscus feels like just a nice drink:
- Dizziness, light-headedness on standing, or unusual fatigue after starting hibiscus alongside blood-pressure medication — signs that pressure may have dropped too far, which a home reading shows. This is the most likely adverse event, and a medicine dose can be adjusted for it.
- Home blood-pressure readings running consistently below target. With a drink and a tablet both lowering pressure, the combined effect can go beyond what the tablet dose was set for.
- Any new symptom after starting a concentrated extract — particularly nausea, right-upper-abdominal discomfort, dark urine or yellowing of the eyes or skin. Rare, but concentrated botanical extracts are where liver signals appear; these are signs of liver injury that hospitals treat as urgent.
- Pregnancy, confirmed or suspected — the point at which the animal findings above apply to a daily therapeutic habit.
- Starting an antimalarial, a statin, or any new medication — chloroquine and simvastatin are drugs whose blood levels a hibiscus drink lowered in the human studies above.
And the underlying principle: hibiscus is a pleasant, low-risk, mildly active drink with a genuine but modest blood-pressure effect. In the head-to-head trials it matched captopril and fell short of lisinopril.
Key Research Papers
Every identifier was verified live against NCBI E-utilities before printing. Study species is stated for each interaction finding.
Dosing and the clinical trials
- McKay DL, Chen CY, Saltzman E, Blumberg JB. Hibiscus sabdariffa L. tea (tisane) lowers blood pressure in prehypertensive and mildly hypertensive adults. The Journal of Nutrition. 2010;140(2):298–303 — PubMed PMID: 20018807 — Human; three 240 mL servings daily for six weeks.
- Herrera-Arellano A, Flores-Romero S, Chávez-Soto MA, Tortoriello J. Effectiveness and tolerability of a standardized extract from Hibiscus sabdariffa in patients with mild to moderate hypertension: a controlled and randomized clinical trial. Phytomedicine. 2004;11(5):375–382 — PubMed PMID: 15330492 — Human.
- Herrera-Arellano A, Miranda-Sánchez J, Avila-Castro P, et al. Clinical effects produced by a standardized herbal medicinal product of Hibiscus sabdariffa on patients with hypertension: a randomized, double-blind, lisinopril-controlled clinical trial. Planta Medica. 2007;73(1):6–12 — PubMed PMID: 17315307 — Human; dosed on total anthocyanin content.
- Chang HC, Peng CH, Yeh DM, Kao ES, Wang CJ. Hibiscus sabdariffa extract inhibits obesity and fat accumulation, and improves liver steatosis in humans. Food & Function. 2014;5(4):734–739 — PubMed PMID: 24549255 — Human; capsule extract, 12 weeks.
- Mozaffari-Khosravi H, Jalali-Khanabadi BA, Afkhami-Ardekani M, Fatehi F, Noori-Shadkam M. The effects of sour tea (Hibiscus sabdariffa) on hypertension in patients with type II diabetes. Journal of Human Hypertension. 2009;23(1):48–54 — PubMed PMID: 18685605 — Human; twice daily for one month.
- Ellis LR, Zulfiqar S, Holmes M, Marshall L, Dye L, Boesch C. A systematic review and meta-analysis of the effects of Hibiscus sabdariffa on blood pressure and cardiometabolic markers. Nutrition Reviews. 2022;80(6):1723–1737 — PubMed PMID: 34927694 — 17 trials; systolic −7.10 mmHg versus placebo, I² 95%.
- Norouzzadeh M, Hasan Rashedi M, Azizi MH, Teymoori F, Maghsoomi Z, Shidfar F. Efficacy and safety of Hibiscus sabdariffa in cardiometabolic health: an overview of reviews and updated dose-response meta-analysis. Complementary Therapies in Medicine. 2025;89:103135 — PubMed PMID: 39870328 — 26 trials, 1,797 people; dose-dependent fall in blood pressure; small, clinically insignificant rise in AST.
Documented drug interactions
- Mahmoud BM, Ali HM, Homeida MM, Bennett JL. Significant reduction in chloroquine bioavailability following coadministration with the Sudanese beverages Aradaib, Karkadi and Lemon. Journal of Antimicrobial Chemotherapy. 1994;33(5):1005–1009 — PubMed PMID: 8089046 — Human. Chloroquine AUC fell from 7.52 to 2.16 mg·h/L with karkadi — about a 71 percent reduction.
- Ndu OO, Nworu CS, Ehiemere CO, Ndukwe NC, Ochiogu IS. Herb-drug interaction between the extract of Hibiscus sabdariffa L. and hydrochlorothiazide in experimental animals. Journal of Medicinal Food. 2011;14(6):640–644 — PubMed PMID: 21480802 — Rat and rabbit. Increased and prolonged hydrochlorothiazide plasma levels and AUC; reduced clearance; added to diuresis and shifted urinary electrolytes.
- Showande SJ, Adegbolagun OM, Igbinoba SI, Fakeye TO. In vivo pharmacodynamic and pharmacokinetic interactions of Hibiscus sabdariffa calyces extracts with simvastatin. Journal of Clinical Pharmacy and Therapeutics. 2017;42(6):695–703 — PubMed PMID: 28925046 — Rat plus six-volunteer human crossover. Exposure ratio 0.646 (90% CI 0.564–0.758), outside bioequivalence.
- Kolawole JA, Maduenyi A. Effect of zobo drink (Hibiscus sabdariffa water extract) on the pharmacokinetics of acetaminophen in human volunteers. European Journal of Drug Metabolism and Pharmacokinetics. 2004;29(1):25–29 — PubMed PMID: 15151167 — Human. Absorption unchanged; elimination parameters changed, total clearance up about 11.7 percent.
- Fakeye TO, Adegoke AO, Omoyeni OC, Famakinde AA. Effects of water extract of Hibiscus sabdariffa, Linn (Malvaceae) ‘Roselle’ on excretion of a diclofenac formulation. Phytotherapy Research. 2007;21(1):96–98 — PubMed PMID: 17094172 — Human. Note this paper concerns diclofenac, not paracetamol.
Diuresis, renal effects and toxicity
- Alarcón-Alonso J, Zamilpa A, Aguilar FA, Herrera-Ruiz M, Tortoriello J, Jimenez-Ferrer E. Pharmacological characterization of the diuretic effect of Hibiscus sabdariffa Linn (Malvaceae) extract. Journal of Ethnopharmacology. 2012;139(3):751–756 — PubMed PMID: 22178178 — Rodent.
- Njinga NS, Kola-Mustapha AT, Quadri AL, et al. Toxicity assessment of sub-acute and sub-chronic oral administration and diuretic potential of aqueous extract of Hibiscus sabdariffa calyces. Heliyon. 2020;6(9):e04853 — PubMed PMID: 33005778 — Animal.
- Nwachukwu DC, Aneke EI, Nwachukwu NZ, Azubike N, Obika LF. Does consumption of an aqueous extract of Hibiscus sabdariffa affect renal function in subjects with mild to moderate hypertension? The Journal of Physiological Sciences. 2017;67(1):227–234 — PubMed PMID: 27221151 — Human.
- Nwachukwu DC, Aneke E, Nwachukwu NZ, Obika LF, Nwagha UI, Eze AA. Effect of Hibiscus sabdariffa on blood pressure and electrolyte profile of mild to moderate hypertensive Nigerians: a comparative study with hydrochlorothiazide. Nigerian Journal of Clinical Practice. 2015;18(6):762–770 — PubMed PMID: 26289514 — Human.
- Nwachukwu DC, Aneke EI, Obika LF, Nwachukwu NZ. Effects of aqueous extract of Hibiscus sabdariffa on the renin-angiotensin-aldosterone system of Nigerians with mild to moderate essential hypertension: a comparative study with lisinopril. Indian Journal of Pharmacology. 2015;47(5):540–545 — PubMed PMID: 26600645 — Human.
- Da-Costa-Rocha I, Bonnlaender B, Sievers H, Pischel I, Heinrich M. Hibiscus sabdariffa L. – a phytochemical and pharmacological review. Food Chemistry. 2014;165:424–443 — PubMed PMID: 25038696 — Review, including the safety and toxicology literature.
Pregnancy and offspring (animal studies)
- Iyare EE, Adegoke OA. Mechanism of the delayed puberty onset in offspring of rats that consumed aqueous extract of Hibiscus sabdariffa during pregnancy. Nigerian Journal of Physiological Sciences. 2008;23(1–2):71–77 — PubMed PMID: 19434218 — Rat.
- de Arruda A, Cardoso CA, Vieira Mdo C, Arena AC. Safety assessment of Hibiscus sabdariffa after maternal exposure on male reproductive parameters in rats. Drug and Chemical Toxicology. 2016;39(1):22–27 — PubMed PMID: 25682722 — Rat.
PubMed Topic Searches
- PubMed: Hibiscus herb–drug interactions
- PubMed: Hibiscus in pregnancy
- PubMed: Hibiscus reproductive toxicity, animal studies
- PubMed: Hibiscus and liver toxicity
- PubMed: Hibiscus, diuresis and electrolytes
- PubMed: Hibiscus extraction conditions and anthocyanin yield
- PubMed: Acidic beverages and dental erosion
- PubMed: Polyphenols and non-haem iron absorption
Connections
- All Herbs
- Hibiscus Benefits — hub
- Hibiscus — the main article
- Blood Pressure
- Cholesterol and Metabolic
- Anthocyanins and Antioxidant Chemistry
- Anthocyanins
- Butterfly Pea
- Hypertension
- Cardiology
- Potassium