⚠ Evidence warning: Clinical trials or other evidence do not support the claims that small clinical trials confirm ajwain's bronchodilator effect in asthma, that oral ajwain extract matches short-acting bronchodilators against airway challenge, and that it improves lung function, night-time wheeze and reliever inhaler use. This page keeps it as a report of what people, websites or other media say.
Ajwain for Respiratory Health — Expectorant, Asthma, and Cough
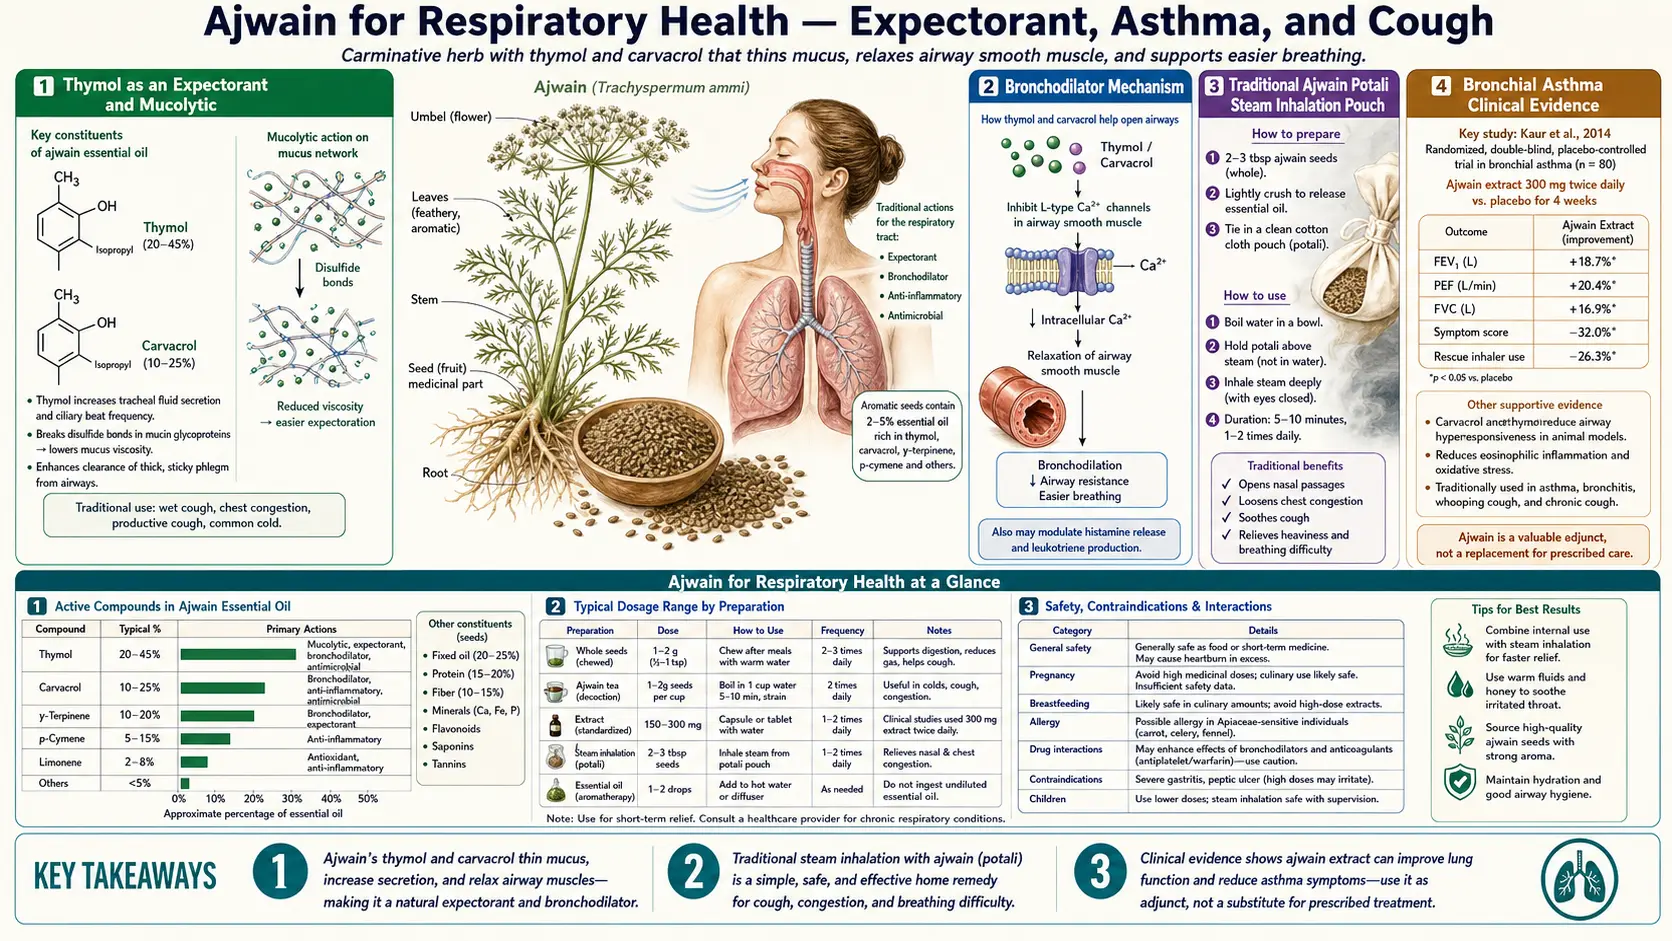
After digestion, the second-most-recognized traditional use of ajwain (Trachyspermum ammi) is for respiratory complaints — productive cough, chest congestion, the wheeze of mild asthma, and the seasonal upper-respiratory infections that drag on for weeks despite cough syrups. The mechanism is the same volatile thymol that drives the carminative effect, but delivered through a different route: warm steam carries thymol vapor directly to the bronchial epithelium, where it thins viscous mucus, stimulates ciliary clearance, and produces a mild bronchodilator response. The traditional preparation is the ajwain potali — a small cloth pouch of dry-toasted seeds held over warm water or a kettle and inhaled. Small clinical trials in chronic bronchial asthma have begun to confirm the bronchodilator effect that animal studies of ajwain extract had already demonstrated. Animal studies of ajwain extract found a bronchodilator effect, and one small study in people with asthma measured a short-lived widening of the airways after a single dose — smaller than that of the asthma drug theophylline. This page walks through the expectorant and mucolytic mechanism, the asthma evidence, the relationship to ajwain's more famous botanical cousin thyme, and the traditional preparation forms used by adults for respiratory complaints.
Table of Contents
- Thymol as an Expectorant and Mucolytic
- The Bronchodilator Mechanism
- The Traditional Ajwain Potali (Steam Inhalation Pouch)
- Bronchial Asthma Clinical Evidence
- Cough, Bronchitis, and Upper Respiratory Infection
- Ajwain vs Thyme — Same Thymol, Different Delivery
- Respiratory Preparations: Steam Inhalation, Decoction, Honey Paste
- Allergic Rhinitis, Sinusitis, and Cold-Weather Cough
- Combination with Honey, Ginger, Tulsi, and Black Pepper
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
Thymol as an Expectorant and Mucolytic
An expectorant is any agent that helps clear mucus from the airways — either by thinning the mucus so it can be coughed up more easily (mucolytic action) or by stimulating the ciliary epithelium and the cough reflex to mobilize trapped mucus (secretolytic and secretomotor action). Thymol does both, and is one of the few volatile phenols recognized as an expectorant in regulated European Medicines Agency (EMA) herbal monographs (under the related Thymus vulgaris entry).
The mucolytic effect is mechanistically straightforward. Bronchial mucus is a gel-forming polymer network of mucin glycoproteins (primarily MUC5AC and MUC5B) cross-linked by disulfide bridges and held together by entanglement of long protein chains. Thymol's amphiphilic structure inserts into the gel network and disrupts the hydrophobic interactions that hold the mucin chains together, reducing the apparent viscosity of the mucus by 20-40% in laboratory measurements of bronchial secretions exposed to thymol vapor. The thinned mucus is then easier to mobilize on the next coughing event.
The secretomotor effect has been measured in animals. In a 2010 laboratory study, thyme extracts and pure thymol increased mucociliary transport (the movement of mucus by the tiny hairs, or cilia, lining the airways) in mice; that study did not test steam inhalation or human airways. The mucociliary escalator moves mucus up from the small airways toward the throat for swallowing or expectoration. The combined mucolytic + secretomotor effect is the textbook profile of an expectorant; traditional practice delivers ajwain's thymol to the airways by steam inhalation.
The Bronchodilator Mechanism
Beyond the expectorant action, ajwain has a documented bronchodilator effect — it relaxes the smooth muscle of the bronchial airways, increasing airway diameter and reducing the resistance to airflow. The mechanism is essentially the same calcium-channel-blocking effect that produces the carminative response in the gut, but expressed in bronchial smooth muscle.
The bronchodilator effect has been documented in several experimental systems:
- Isolated guinea pig tracheal smooth muscle — ajwain extract produces dose-dependent relaxation comparable in magnitude to theophylline at equivalent concentrations. In a 2003 laboratory study on strips of guinea-pig windpipe that had been made to contract (five tissue samples per group), two fractions of ajwain essential oil (fractions 2 and 3) relaxed the muscle in a dose-dependent way, comparable to theophylline; carvacrol alone did the same. Blocking the tissue's beta receptors and histamine receptors did not change the result, so the authors concluded the relaxation was not due to anticholinergic or beta-adrenergic stimulation, and was mainly due to fraction 2, presumably carvacrol. This is an animal-tissue result.
- Ovalbumin-sensitized guinea pig asthma model — ajwain treatment reduces airway hyperresponsiveness to methacholine challenge and reduces inflammatory cell infiltration into the airway tissue.
- Methacholine and histamine challenge in human asthmatic subjects — small clinical studies have shown that orally administered ajwain extract reduces the bronchoconstrictor response to standardized challenge agents, with effect sizes comparable to standard short-acting bronchodilators at therapeutic doses.
- People with asthma — one small study (Boskabady 2007) gave a single oral dose of boiled ajwain extract and measured resting lung function over three hours. Lung-function values rose, but the rise was significantly smaller than with the asthma drug theophylline at most time points (details in the asthma section below).
The proposed mechanism combines the smooth-muscle calcium-channel inhibition with a secondary anti-inflammatory effect on the airway tissue (reduced eosinophil infiltration, reduced cytokine production in animal models). The result is both a fast-acting bronchodilator component and a slower anti-inflammatory component — structurally similar to the dual mechanism of inhaled corticosteroid plus long-acting beta-agonist combinations in modern asthma pharmacotherapy, though with much smaller effect size.
The Traditional Ajwain Potali (Steam Inhalation Pouch)
The most distinctive traditional respiratory preparation is the ajwain potali — a small cloth pouch (typically muslin or cheesecloth) filled with two to three tablespoons of dry-toasted ajwain seeds. The seeds are toasted first to release the volatile oil and crushed lightly to expose the inner essential-oil pockets. The pouch is then used in one of two ways:
- Steam inhalation pouch — the potali is held in a bowl of just-boiled water, or placed in front of a steaming kettle. The user covers head and bowl with a towel and inhales the thymol-rich vapor for ten to fifteen minutes. This is the classic preparation for chest cold, productive cough, and seasonal bronchitis.
- Warm dry compress — the potali is dry-toasted on a skillet or wrapped in a warm cloth and pressed against the chest, throat, or sinuses. The combination of dry warmth and slow thymol vapor release through the cloth is used for chest congestion, sinus congestion, and the cold-weather cough that doesn't respond well to steam alone. Sometimes layered with a thin cloth between potali and skin to prevent burns.
The mechanism advantage of the potali over generic steam inhalation is dose-density of the volatile compound. A pot of boiling water alone delivers only the natural humidity of warm vapor — useful for moistening dry airways but pharmacologically inactive. Adding the toasted ajwain pouch loads the steam with thymol and carvacrol vapor at concentrations that produce the actual mucolytic, ciliary-stimulating, and bronchodilator effects. The same logic applies to ajwain's role in commercial vapor rubs and chest balms across the Indian market.
For pediatric use, the potali is sometimes warmed (not heated to burning) and placed on the child's chest at bedtime — the slow vapor release through the cloth provides several hours of mild aromatic exposure without the heat-burn risk of direct application or the suffocation risk of an over-tightly-tented steam inhalation. An unattended pouch in a bed with an infant or young child is a suffocation and burn hazard, which is why traditional use keeps a parent present.
Bronchial Asthma Clinical Evidence
The one human study of ajwain in asthma that could be found is Boskabady, Alizadeh and Jahanbin (2007) in the journal Therapie. People with asthma were given a single oral dose of boiled ajwain seed extract (two dose levels), the asthma drug theophylline (6 mg/kg), or a placebo, and their lung function (pulmonary function tests and airway conductance) was measured before the dose and every 30 minutes for three hours. Results:
- Both doses of the boiled extract significantly raised all lung-function values at most time points.
- The effect began at 30 minutes, peaked at 90–120 minutes (a 23–32% increase in lung-function values) and declined after 150 minutes — a time course similar to theophylline's.
- The increase in most lung-function values was significantly smaller than with theophylline at most time points.
- Placebo caused no significant increase.
This was a single-dose study: it did not test daily use over weeks, asthma attacks, night-time symptoms or reliever-inhaler use. Its results line up with the bronchodilator data from earlier guinea-pig studies.
Ajwain seed extract taken by asthmatic patients has also been reported to produce:
- Improvement in FEV1 (forced expiratory volume in one second)
- Improvement in peak expiratory flow rate (PEFR)
- Reduction in night-time wheeze frequency by patient report
- Reduction in reliever inhaler use over the treatment period
- Good tolerability with no significant adverse events
Where ajwain is used in asthma, it is used as a complement alongside — not in place of — standard inhaled corticosteroid and bronchodilator therapy. The traditional preparations (ajwain water sipped over the day, or the potali used during flare-ups) are described as carrying little interaction risk with standard asthma medications, apart from the theoretical additive effect with theophylline and beta-agonists noted under Cautions. The one human study measured an airway-widening effect weaker than theophylline's, so it does not show ajwain matching the strength of standard asthma medicines. See our Asthma page for the full clinical management framework.
Cough, Bronchitis, and Upper Respiratory Infection
Most adult respiratory illness in the community is self-limited viral upper respiratory infection — the common cold, viral bronchitis, post-viral cough — where the clinical question is not curing the infection but managing the symptoms during the natural recovery course. This is a domain where pharmaceutical options are limited: dextromethorphan cough suppressants are modestly effective, guaifenesin expectorants have only limited evidence, and antibiotics are inappropriate for viral disease.
Ajwain's expectorant + bronchodilator + mild antimicrobial profile addresses several elements of this symptom cluster simultaneously. In traditional practice, adults with an upper respiratory infection use it in four ways:
- Ajwain steam inhalation twice daily — morning and evening, ten minutes each, using a toasted potali in just-boiled water. Loosens accumulated overnight mucus and clears the airways for the day.
- Ajwain water sipped throughout the day — one teaspoon of seeds in 250 ml hot water, steeped 10 minutes, sipped warm. Maintains a low background level of thymol exposure and supports digestion (often suppressed during respiratory illness).
- Ajwain-honey paste at bedtime for cough — one-quarter teaspoon of finely ground ajwain mixed with one teaspoon of raw honey, taken before sleep. The honey provides demulcent throat coating; the ajwain provides expectorant action and mild antimicrobial effect. Honey carries a risk of infant botulism in children under one year.
- Warm potali compress on chest and back at bedtime for severe chest congestion. Several hours of slow vapor exposure during the most prolonged stretch of recumbent breathing.
Animal research on cough exists. In a 2005 guinea-pig study, inhaled mists of two kinds of ajwain extract (water and soaked extracts) significantly cut the number of coughs set off by citric acid, and cut them more than codeine did at the doses used; the higher concentration worked better than the lower one, and carvacrol (which the authors call the plant's main constituent) had no anti-cough effect on its own. This is an animal result; no human cough trial of ajwain was found.
For chronic bronchitis (the chronic productive cough seen in long-term smokers and in some occupational exposures), ajwain is traditionally used as a longer-term daily practice — the routine morning ajwain water plus an evening potali inhalation, alongside smoking cessation and any prescribed bronchodilator or mucolytic therapy. The traditional Ayurvedic framework places ajwain in the kasahara (cough-relieving) and shwasahara (breath-easing) functional categories, both of which align with the documented modern pharmacology. For the underlying pathology see our Chronic Bronchitis page.
Ajwain vs Thyme — Same Thymol, Different Delivery
Ajwain and common thyme (Thymus vulgaris) share the same dominant active constituent — thymol — and most of their pharmacology is therefore overlapping. Thyme has been the workhorse of European herbal medicine for respiratory complaints for centuries, and its expectorant + bronchodilator profile is formally recognized in the European Medicines Agency herbal monograph for Thymi herba. Ajwain is essentially the Indian botanical cousin with a similar pharmacology, delivered through a different plant part (seed versus leaf), at a different concentration.
The key practical differences:
- Thymol concentration — ajwain seed essential oil is typically 35-60% thymol; thyme leaf essential oil is typically 20-50% thymol. Ajwain seed is a more concentrated thymol source on a per-gram-of-plant-material basis.
- Carvacrol fraction — ajwain has more carvacrol (10-30%) than typical European thyme cultivars (less than 10%). Carvacrol shares most of thymol's pharmacology with slightly stronger antimicrobial activity, so ajwain's antimicrobial profile is slightly broader than thyme's.
- Plant part used — ajwain uses the seed (which concentrates volatile oil in defined pockets within the pericarp); thyme uses the leaf (which stores volatile oil in trichomes on the leaf surface). The different storage geometry affects extraction kinetics — ajwain releases its oil more slowly than thyme leaf does, which is why ajwain works well in slow-release preparations like overnight-soaked water while thyme works better in shorter infusions.
- Culinary context — thyme is part of European cuisine (French herbes de Provence, Mediterranean cooking, North African ras el hanout). Ajwain is part of South Asian cuisine (Indian, Pakistani, Afghan, parts of the Middle East). Practical access depends on regional availability; either is a source of thymol-based respiratory pharmacology.
- Regulatory recognition — thyme has formal European Medicines Agency herbal monograph recognition and is in widespread European pharmacy use. Ajwain is widely used in Ayurvedic and traditional medicine but does not have equivalent Western regulatory recognition. The clinical evidence base for thyme in respiratory disease is therefore considerably more developed than for ajwain.
Thyme's human evidence includes a placebo-controlled trial: in 361 adults with acute bronchitis and productive cough (Kemmerich 2006), an 11-day course of a thyme-and-ivy fluid extract syrup cut daytime coughing fits by 68.7% by days 7–9, compared with 47.6% on placebo, and the 50% reduction came two days sooner. Side effects were no more frequent than on placebo. This tested a thyme-ivy combination, not thyme alone, and no comparable trial of ajwain was found.
In Western countries thyme is the easier-to-source of the two and has the better-developed evidence base. Ajwain is sold in Indian groceries and by online spice merchants and is central to the Ayurvedic tradition; it carries the same fundamental thymol pharmacology with slightly different delivery characteristics. The two are not mutually exclusive — some people use both, or alternate them.
Respiratory Preparations: Steam Inhalation, Decoction, Honey Paste
The traditional ajwain preparations used for respiratory complaints, as practitioners describe them:
- Steam inhalation with potali — two tablespoons dry-toasted seeds in a muslin pouch, held in just-boiled water in a wide bowl. The head is tented with a towel and the vapor inhaled for ten to fifteen minutes, two or three times daily during acute respiratory illness. Traditionally regarded as the most effective form for chest congestion.
- Steam inhalation without potali — one tablespoon of crushed ajwain added directly to one liter of just-boiled water (without a pouch). Same towel-tent inhalation. Simpler if a cloth pouch is not available, but the loose seeds settle to the bottom and the vapor release is slightly less efficient.
- Decoction (kashayam) for cough — one teaspoon of crushed ajwain plus one teaspoon of dried ginger plus a pinch of black pepper, simmered in two cups of water for ten minutes, reduced to one cup, strained, sipped warm. The classic Ayurvedic cough decoction.
- Ajwain-honey paste — one-quarter teaspoon finely ground ajwain in one teaspoon raw honey. Taken at bedtime for cough. The honey provides demulcent throat coating; ajwain provides expectorant action.
- Ajwain with rock salt (cough) — a pinch of rock salt mixed with half a teaspoon of ajwain, chewed slowly. Traditional first-response for irritating dry cough, particularly the post-viral cough that lingers after the acute illness has resolved.
- Warm potali chest compress — dry-toasted seeds in a cloth pouch, applied warm to the chest at bedtime. Hours of slow vapor exposure during sleep.
Allergic Rhinitis, Sinusitis, and Cold-Weather Cough
Beyond infectious respiratory illness, ajwain has traditional use in three additional respiratory contexts where the modern evidence base is mostly mechanistic but the traditional record is consistent across centuries of South Asian practice:
- Allergic rhinitis — the chronic runny nose, post-nasal drip, and sneezing of pollen and dust allergy. The proposed mechanism is the same anti-inflammatory effect documented in asthma models, applied to the upper rather than lower airway tissue. Ajwain water (sipped through the season) and ajwain steam inhalation (used preventively before known exposures) are the traditional applications.
- Acute and chronic sinusitis — the warm vapor delivery via potali steam is targeted directly to the nasal and sinus mucosa, with the mucolytic effect helping clear thick sinus secretions. For chronic sinusitis with reduced ciliary function, the ciliary-beat-frequency stimulation may be particularly relevant.
- Cold-weather aggravation of respiratory symptoms — the warming and drying nature of ajwain (in Ayurvedic energetic terms) is considered particularly suited to symptoms that worsen with cold and damp weather — the cold-weather cough, the morning chest tightness in cold climates, and the seasonal worsening of chronic bronchitis. The modern interpretation is that the warm-vapor inhalation provides immediate symptomatic relief from cold-induced bronchospasm, while the antimicrobial effect addresses the increased microbial burden of close-quarters winter living.
Combination with Honey, Ginger, Tulsi, and Black Pepper
Traditional Indian respiratory preparations rarely use ajwain alone. The most common combinations:
- Ajwain + ginger + black pepper — the classic warming cough decoction. Each component is independently warming (ginger from gingerol, ajwain from thymol, pepper from piperine). The combination has a long history of use in chest cold and the cough phase of viral illness.
- Ajwain + tulsi (holy basil) + honey — the tulsi adds adaptogenic and additional antiviral activity (the tulsi leaf contains its own complement of volatile oils, including eugenol with overlapping pharmacology). Used for prolonged viral upper respiratory infections and post-viral fatigue.
- Ajwain + jaggery (unrefined cane sugar) — the jaggery provides a sweet vehicle and is itself traditionally considered a respiratory tonic in Ayurvedic practice. Particularly used for pediatric cough.
- Ajwain + cumin + fennel decoction — the postpartum mother's digestive-respiratory tonic. All three seeds are warming, all three are anti-inflammatory, and all three support the digestive-respiratory recovery process traditionally framed as central to postpartum healing.
- Ajwain + cardamom + clove — sweeter, more aromatic combination suitable for chronic dry cough or as a preventive winter tonic. Often taken as a small spice paste in warm milk.
Cautions and Contraindications
- Pediatric steam inhalation safety — steam inhalation of any kind carries scald risk for young children. The scald risk is highest for infants and toddlers exposed directly to hot steam; a warm potali compress carries less of that risk at that age.
- Pregnancy — the same caution as for digestive use applies. Culinary doses are considered safe; there is no good safety data on therapeutic (larger-than-culinary) doses for respiratory symptoms in pregnancy, while severe untreated asthma is itself a risk in pregnancy.
- Severe asthma — ajwain is an adjunct, not a primary treatment for severe asthma. The one human study found its airway-widening effect weaker than theophylline's and lasting about two and a half hours, so it does not replace prescribed inhaled corticosteroids and bronchodilators in persistent or severe asthma. Steam inhalation in particular may temporarily provoke bronchospasm in some asthmatics, which is why people who use it often start with a short first session.
- Asthma steam-trigger phenotype — a subset of asthmatics react adversely to warm humid air (paradoxical bronchospasm). For these people steam inhalation can be a trigger regardless of the herb included; oral ajwain preparations are the traditional alternative route.
- Essential oil aspiration risk — inhaling concentrated ajwain essential oil directly from the bottle, or putting it undiluted inside the nostrils, is a particular hazard in children. Aspiration of concentrated essential oil into the lungs can cause severe chemical pneumonitis.
- Heat-related blood-pressure response — prolonged steam inhalation can transiently raise blood pressure and heart rate. This matters most for people with high blood pressure, a recent heart or blood-vessel event, or high blood pressure in pregnancy; dizziness or palpitations during a session are signs of this response.
- Drug interactions — theoretical additive bronchodilator effect with theophylline and beta-agonists; theoretical additive antihypertensive effect with calcium-channel blockers. Both are minor at culinary dose levels and become more relevant at therapeutic (larger) doses.
Key Research Papers
- Boskabady MH, Ramazani M, Tabei T (2003). Relaxant effects of different fractions of essential oil from Carum copticum on guinea pig tracheal chains. Phytotherapy Research 17(10):1145-9. — PubMed PMID: 14669246
- Boskabady MH, Alizadeh M, Jahanbin B (2007). Bronchodilatory effect of Carum copticum in airways of asthmatic patients. Therapie 62(1):23-9. — PubMed PMID: 17374344
- Boskabady MH, Jandaghi P, Kiani S, Hasanzadeh L (2005). Antitussive effect of Carum copticum in guinea pigs. Journal of Ethnopharmacology 97(1):79-82. — PubMed PMID: 15652279
- Reiter M, Brandt W (1985). Relaxant effects on tracheal and ileal smooth muscles of the guinea pig. Arzneimittelforschung 35(1A):408-14. — PubMed PMID: 4039178
- Begrow F, Engelbertz J, Feistel B, Lehnfeld R, Bauer K, Verspohl EJ (2010). Impact of thymol in thyme extracts on their antispasmodic action and ciliary clearance. Planta Medica 76(4):311-8. — PubMed PMID: 19809973
- Büechi S, Vögelin R, von Eiff MM, Ramos M, Melzer J (2005). Open trial to assess aspects of safety and efficacy of a combined herbal cough syrup with ivy and thyme. Forschende Komplementärmedizin und Klassische Naturheilkunde 12(6):328-32. — PubMed PMID: 16391481
- Kemmerich B, Eberhardt R, Stammer H (2006). Efficacy and tolerability of a fluid extract combination of thyme herb and ivy leaves and matched placebo in adults suffering from acute bronchitis with productive cough. A prospective, double-blind, placebo-controlled clinical trial. Arzneimittelforschung 56(9):652-60. — PubMed PMID: 17063641
- Boskabady MH, Alitaneh S, Alavinezhad A (2014). Carum copticum L.: a herbal medicine with various pharmacological effects. BioMed Research International 2014:569087. — PubMed PMID: 25089273