Tea Tree Oil for Antimicrobial Use & Methicillin-Resistant Staphylococcus Aureus (MRSA)
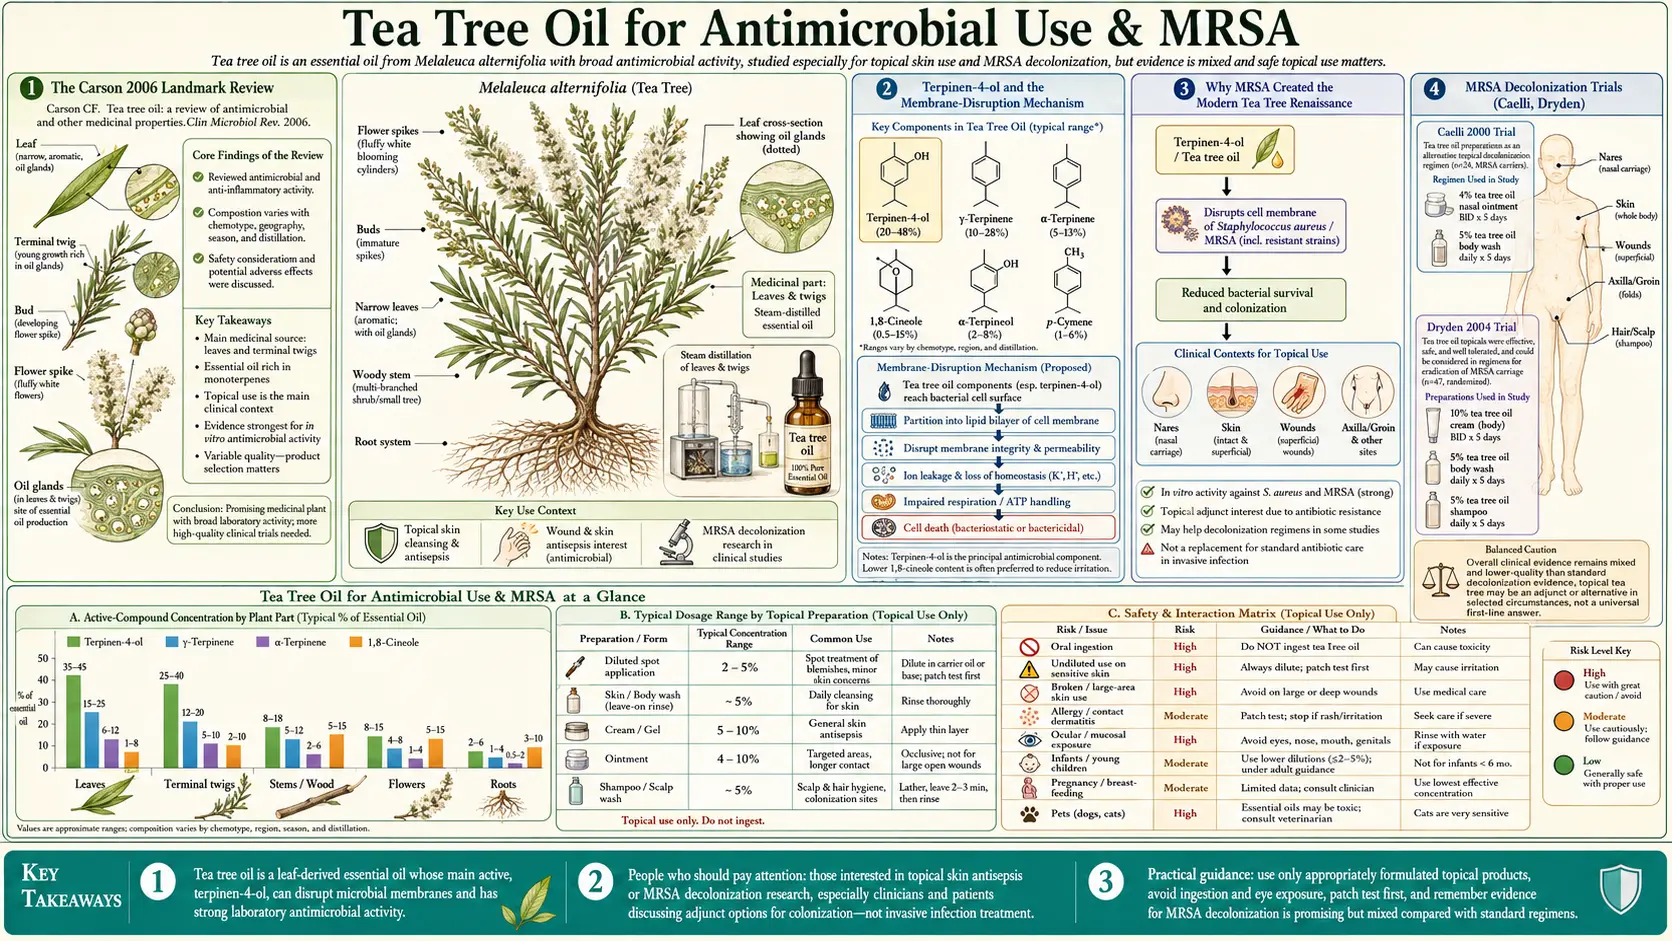
Tea tree oil is one of the most extensively-studied botanical antimicrobials in the peer-reviewed literature. The Carson, Hammer & Riley 2006 Clinical Microbiology Reviews paper — a 13-page review (pages 50–62) — documented in vitro activity against more than 60 distinct bacterial and fungal species, including methicillin-resistant Staphylococcus aureus (MRSA), vancomycin-resistant Enterococcus, multi-drug-resistant Pseudomonas aeruginosa, and clinical strains of Candida albicans that had developed azole resistance. The principal antimicrobial constituent is terpinen-4-ol (30–48% of the oil), which disrupts microbial cell membranes through a biophysical mechanism that is exceptionally difficult for resistant strains to evade. The standardized topical concentration is 5%, embedded in a gel, cream, or carrier oil, applied to intact skin or to the anterior nares for methicillin-resistant Staphylococcus aureus decolonization. Two controlled hospital trials have compared tea tree regimens (a 4% or 10% tea tree nasal product plus a 5% tea tree body wash) with standard mupirocin-based regimens for methicillin-resistant Staphylococcus aureus decolonization: neither found a statistically significant overall difference, and in the larger trial mupirocin cleared nasal carriage better (78% vs 47%).
Table of Contents
- The Carson 2006 Landmark Review
- Terpinen-4-ol and the Membrane-Disruption Mechanism
- Why Methicillin-Resistant Staphylococcus Aureus Created the Modern Tea Tree Renaissance
- Methicillin-Resistant Staphylococcus Aureus Decolonization Trials (Caelli, Dryden)
- Hospital Infection Control Applications
- The 5% Topical Concentration Standard
- Biofilm Activity and Wound Care
- Why Resistance Is Rare
- Practical Topical Use
- Cautions (Swallowing, Oxidation, Contact Dermatitis)
- Key Research Papers
- Connections
- Featured Videos
The Carson 2006 Landmark Review
The single most-cited paper on tea tree oil is the 2006 Clinical Microbiology Reviews review by Christine Carson, Katherine Hammer, and Thomas Riley — three microbiologists at the University of Western Australia who have spent careers studying the oil's pharmacology and microbiology. The review compiled essentially every published study on tea tree oil through 2005 into one comprehensive document, with a particular focus on antimicrobial spectrum, mechanism of action, clinical efficacy, and toxicity.
The headline findings:
- Documented in vitro inhibitory activity against more than 60 distinct bacterial species, including all clinically important gram-positive cocci (Staphylococcus, Streptococcus, Enterococcus), most gram-negative rods (E. coli, Klebsiella, Pseudomonas), anaerobes (Bacteroides), and acid-fast organisms (Mycobacterium smegmatis)
- Documented antifungal activity against dermatophytes (Trichophyton, Microsporum, Epidermophyton), yeasts (Candida, Malassezia), and filamentous fungi (Aspergillus)
- Documented antiviral activity against enveloped viruses including HSV-1, HSV-2, and influenza A
- Minimum inhibitory concentrations (MIC) typically in the 0.25–2% range for susceptible bacteria, well below the 5% concentration used in commercial topical products
- Possible synergy of tea tree oil with other essential oils (such as lavender) and essential-oil components (such as β-triketones from manuka oil) investigated in vitro, with much more work described as needed
- An anti-inflammatory effect separate from the antimicrobial activity, mediated by suppression of histamine release and reduction of tumor necrosis factor-alpha and interleukin-1 (IL-1) production by activated monocytes
The review remains the standard reference. Subsequent research has filled in mechanistic details (membrane fluidity disruption confirmed by NMR, biofilm activity confirmed in flow cell models) but has not overturned any of the major findings. The original Carson 2006 paper remains the fullest single summary of this work.
Terpinen-4-ol and the Membrane-Disruption Mechanism
The principal antimicrobial constituent of tea tree oil is terpinen-4-ol, a small lipophilic alcohol that accounts for 30–48% of the oil by ISO 4730 standard. Mechanistic studies by Carson and colleagues, and independently by groups in Italy and Germany, have established the membrane-disruption mechanism through several converging lines of evidence:
- Loss of intracellular potassium — treated bacteria release potassium ions, indicating direct membrane permeabilization. This happens within minutes of tea tree exposure and is dose-dependent
- Collapse of the proton-motive force — the electrochemical gradient across the bacterial inner membrane is required for adenosine triphosphate (ATP) synthesis. Tea tree oil treatment dissipates this gradient, halting energy production
- Increased membrane fluidity — NMR studies show that terpinen-4-ol intercalates between membrane phospholipids and increases the rotational mobility of the lipid acyl chains, exactly as expected for a small lipophilic disruptor
- Inhibition of respiration — oxygen consumption by treated bacteria drops sharply, consistent with electron transport chain dysfunction secondary to membrane integrity loss
- Cell lysis at higher concentrations — at concentrations above the minimum bactericidal concentration, bacteria release cytoplasmic contents and become non-viable
The clinical significance of this mechanism is that it is fundamentally different from how conventional antibiotics work. Beta-lactams inhibit cell wall synthesis. Aminoglycosides inhibit ribosomes. Fluoroquinolones inhibit DNA gyrase. Each of these is a single-target inhibitor that bacteria can evade through a single mutation (PBP changes for beta-lactams, ribosomal modifications for aminoglycosides, gyrase mutations for fluoroquinolones). Tea tree oil's membrane disruption mechanism has no single target to mutate around — the bacterium would have to reinvent its membrane chemistry, which is essentially impossible without catastrophic loss of viability. This is why methicillin-resistant Staphylococcus aureus, which is resistant to nearly every beta-lactam antibiotic available, remains fully susceptible to tea tree oil.
Why Methicillin-Resistant Staphylococcus Aureus Created the Modern Tea Tree Renaissance
Tea tree oil had a long history of folk and commercial use in Australia (legend has it that Australian soldiers were supplied the oil in their military kits during World War II, though the Carson 2006 review found no evidence to corroborate these accounts), but it largely fell out of mainstream medical use after the introduction of antibiotics in the late 1940s. The renaissance of clinical interest in tea tree oil dates to the late 1990s and is directly attributable to the emergence of methicillin-resistant Staphylococcus aureus as a major nosocomial pathogen.
By the mid-1990s, methicillin-resistant Staphylococcus aureus was the dominant cause of hospital-acquired skin and soft-tissue infection in most developed countries. Mupirocin nasal ointment was the standard agent for methicillin-resistant Staphylococcus aureus decolonization — eradication of nasal carriage in patients colonized but not infected, a step that demonstrably reduces subsequent surgical site infection and bloodstream infection in carriers. However, mupirocin resistance emerged within years of widespread use. By the early 2000s, hospitals were seeing mupirocin failure rates of 10–30% in methicillin-resistant Staphylococcus aureus decolonization protocols, and the resistance was spreading.
Australian researchers, with the long-established commercial tea tree industry providing standardized oil for study, began investigating tea tree as an alternative to mupirocin. The minimum inhibitory concentration data looked promising — tea tree oil was bactericidal against all tested methicillin-resistant Staphylococcus aureus isolates at concentrations far below its tolerable topical concentration. The mechanism argued for low resistance potential. And the cost was a fraction of mupirocin. A series of controlled trials followed.
Methicillin-Resistant Staphylococcus Aureus Decolonization Trials (Caelli, Dryden)
The two pivotal early decolonization trials were Caelli et al. 2000 and Dryden et al. 2004:
Caelli 2000, a small pilot study, compared a standard regimen (2% mupirocin nasal ointment plus triclosan body wash) with a tea tree regimen (4% tea tree nasal ointment plus 5% tea tree body wash) in 30 methicillin-resistant Staphylococcus aureus-colonized hospitalized patients, 15 per group. As summarized in the Carson 2006 review, 2 of the 15 patients on the conventional regimen were cleared (8 remained colonized), while 5 of the 15 on tea tree were cleared (3 remained colonized); the rest did not complete therapy. The tea tree combination appeared to perform better, but the difference was not statistically significant, most likely because of the small number of patients.
Dryden 2004 was a larger and better-powered trial: 224 methicillin-resistant Staphylococcus aureus-colonized hospitalized patients randomized to mupirocin nasal ointment plus chlorhexidine body wash vs 10% tea tree nasal cream plus 5% tea tree body wash. The primary outcome was clearance of methicillin-resistant Staphylococcus aureus at all body sites at 48 hours after completion of the 5-day regimen. Results: 49% clearance with the conventional regimen vs 41% clearance with tea tree. The difference was not statistically significant. Mupirocin was significantly more effective at clearing nasal carriage (78% vs 47% with the tea tree cream), while the tea tree treatment was more effective than chlorhexidine or silver sulfadiazine at clearing superficial skin sites and skin lesions.
The Dryden trial did not run a non-inferiority analysis; it reported no significant overall difference between the regimens and concluded that the tea tree preparations were effective, safe and well tolerated and could be considered in regimens for eradication of methicillin-resistant Staphylococcus aureus carriage. The Edmondson 2011 follow-up was an uncontrolled pilot series of methicillin-resistant Staphylococcus aureus-positive wounds: 11 people were treated with a 3.3% tea tree oil solution during wound cleansing, no participant was methicillin-resistant Staphylococcus aureus-negative after treatment, and the study did not achieve its primary aim; 8 of the 11 wounds had begun to heal and got smaller.
Hospital Infection Control Applications
Beyond methicillin-resistant Staphylococcus aureus decolonization, tea tree oil has been studied in several hospital infection control contexts:
- Hand hygiene — Messager 2005 tested tea tree hand-cleansing formulations against E. coli on volunteers' hands (the European EN 1499 handwashing method) and on freshly excised human skin, compared with a non-medicated soft soap. 5% tea tree oil in Tween 80 and an alcoholic tea tree skin wash were significantly more active than the soft soap after 1 minute, and the tea tree formulations met the European in-vivo method requirements
- Pre-operative skin preparation — smaller studies have used tea tree-containing washes as preoperative skin preparation, with documented reduction in skin flora counts comparable to standard chlorhexidine. Tea tree is not yet incorporated into mainstream surgical-site-infection prevention guidelines but remains an active area of investigation
- Vascular catheter site care — small studies have used tea tree-containing dressings around central venous catheter exit sites, with reduction in colonization rates. Larger trials would be needed before this enters guidelines
- Wound care — tea tree-containing dressings have been studied for chronic ulcers, particularly diabetic foot ulcers and venous stasis ulcers, with documented improvement in bioburden and healing rates. The biofilm activity discussed below is particularly relevant in this setting
- Hospital cleaning — tea tree-containing surface disinfectants have shown bactericidal activity against hospital surface contamination at concentrations of 5–10%, though typical hospital cleaning protocols still rely on bleach or quaternary ammonium compounds for cost and standardization reasons
For broader context on methicillin-resistant Staphylococcus aureus and Staphylococcus management, see our Staphylococcus aureus page. For other natural antimicrobials with similar applications, see Manuka Honey (which has its own substantial methicillin-resistant Staphylococcus aureus literature) and Silver Nanoparticles.
The 5% Topical Concentration Standard
The most-studied topical concentration of tea tree oil is 5% in a gel, cream, or carrier oil base. This concentration emerged from the antimicrobial efficacy and tolerability data:
- Antimicrobial efficacy — the minimum inhibitory concentration against methicillin-resistant Staphylococcus aureus and most clinically important bacteria is 0.25–2% tea tree oil. The bactericidal concentration (MBC) is typically 2× the minimum inhibitory concentration. A 5% preparation therefore provides 2.5× to 20× the killing concentration at the application site, with adequate margin for dilution by skin moisture and inter-individual variation in skin chemistry
- Skin tolerability — controlled tolerability studies have shown that 5% preparations produce minimal irritation in the majority of users. Concentrations of 10% and above show progressively higher rates of stinging, redness, and contact dermatitis. Concentrations of 25% and above produce substantial discomfort in most users (the high-concentration studies in nail fungus, discussed on the antifungal page, accept this tradeoff because the nail itself is keratinized and not innervated)
- Cost — tea tree oil is comparatively inexpensive (approximately $0.50–$2 per mL for pharmaceutical-grade oil at retail), so a 5% preparation in a carrier base remains affordable. There is no economic pressure to use lower concentrations
Commercial 5% tea tree gels and creams are sold in pharmacies and health-food shops, including store-brand versions, and compounding pharmacies can prepare custom-concentration tea tree creams.
Biofilm Activity and Wound Care
One particularly clinically important property of tea tree oil is activity against bacterial biofilms. Biofilms are sessile, matrix-encased bacterial communities that form on surfaces (medical devices, chronic wound beds, the airways of cystic fibrosis patients) and exhibit 100–1000-fold reduced susceptibility to conventional antibiotics compared to planktonic bacteria of the same species. The biofilm matrix physically excludes antibiotics, the slow-growing biofilm bacteria are metabolically less vulnerable to most antibiotic mechanisms, and persister cells within biofilms survive even prolonged antibiotic exposure.
Brady et al. 2006 examined tea tree activity against established methicillin-resistant Staphylococcus aureus biofilms in vitro and showed concentration-dependent biofilm disruption at 5% tea tree concentrations — concentrations achievable in topical wound preparations. The mechanism is twofold: terpinen-4-ol penetrates the biofilm matrix more effectively than larger antibiotic molecules, and the membrane-disruption mechanism does not require active bacterial metabolism (so the slow-growing biofilm bacteria remain susceptible).
The clinical translation is the use of tea tree-containing wound dressings for chronic wounds, particularly diabetic foot ulcers, venous stasis ulcers, and pressure injuries with biofilm involvement. Small clinical trials have shown improved healing trajectories. Tea tree is not yet incorporated into mainstream wound care guidelines but is increasingly used in specialty wound centers, often in combination with conventional antimicrobial dressings.
Why Resistance Is Rare
One of the most reassuring features of tea tree oil from an antimicrobial stewardship perspective is the extreme rarity of clinically meaningful resistance. Hammer et al. 2008 measured how often single-step mutants resistant to tea tree oil arise in Staphylococcus aureus (including a clinical methicillin-resistant isolate), Staphylococcus epidermidis and Enterococcus faecalis, and found very low frequencies (below 1 in a billion, <10−9). In their later multistep work (Hammer 2012), bacteria cultured daily for 6 days with subinhibitory tea tree oil alone showed median minimum inhibitory concentration rises of 4-fold for S. aureus and 2-fold for E. coli, and S. aureus and S. epidermidis subcultured 14 to 22 times with terpinen-4-ol showed few significant changes in susceptibility.
The mechanistic explanation: bacterial cell membranes have been evolutionarily optimized over billions of years for stability and barrier function. Any mutation that would resist terpinen-4-ol intercalation also tends to compromise normal membrane function. There is no "free lunch" mutation that confers tea tree resistance without fitness penalty. This is fundamentally different from antibiotic resistance, where bypass mutations (efflux pumps, modifying enzymes, target alterations) can be acquired with relatively small fitness cost.
The practical implication: tea tree oil can be used repeatedly in the same patient (chronic acne, recurrent nail fungus, methicillin-resistant Staphylococcus aureus decolonization in carriers) without the resistance accumulation that limits long-term mupirocin or antibiotic use. This is particularly valuable for patients who are chronic methicillin-resistant Staphylococcus aureus carriers and require repeat decolonization courses over years.
Practical Topical Use
How tea tree oil is commonly used on the skin for antimicrobial purposes, and what the studies used:
- A 5% preparation is the usual strength for routine topical antimicrobial use on intact or minimally compromised skin. It is sold ready-made as a gel or cream, or made by mixing 5 mL of 100% tea tree oil into 95 mL of a carrier oil (jojoba, sweet almond, fractionated coconut)
- Patch testing — a small amount on the inner forearm, checked after 24 hours, is the usual way people test for a skin reaction before wider use; redness, itching, or stinging that lasts beyond the first few minutes is the sign of a reaction
- Fresh, properly stored oil — oxidized tea tree oil is substantially more sensitizing than fresh oil. The Hammer 2006 toxicity review links allergic reactions to oxidation products formed when the oil is exposed to light and/or air; small amber glass bottles kept in a cool dark place and replaced within 12–18 months of opening limit that exposure
- Mucous membranes — the eyes, mouth and genitals are more sensitive than ordinary skin to concentrated tea tree oil. The Hammer 2006 toxicity review states that tea tree oil can cause skin irritation at higher concentrations and is toxic if swallowed in higher doses
- For methicillin-resistant Staphylococcus aureus decolonization — the best-studied tea tree regimen is the Dryden 2004 protocol, as described in the Carson 2006 review: 10% tea tree nasal cream applied three times a day, 5% tea tree body wash at least once a day, and 10% tea tree cream on skin lesions and wounds once a day, all for 5 days. In that trial, mupirocin cleared nasal carriage better (78% vs 47%)
- Hand hygiene — tea tree is not a substitute for soap-and-water hand hygiene. It is used as an adjunct, particularly by healthcare workers and household contacts of methicillin-resistant Staphylococcus aureus carriers
Cautions (Swallowing, Oxidation, Contact Dermatitis)
- Swallowed tea tree oil is poisonous — this is the single most important caution (the Hammer 2006 toxicity review: toxic if ingested in higher doses). Oral ingestion of tea tree oil produces dose-dependent central nervous system depression, ataxia, vomiting, hallucination, coma, and in severe cases respiratory failure. Two published child cases show how fast it acts: a 23-month-old boy became confused and unable to walk 30 minutes after swallowing less than 10 mL of 100% oil, was free of symptoms within 5 hours and went home the next day (Jacobs 1994); a 4-year-old boy who swallowed a small amount became unsteady (ataxic) within 30 minutes and then unresponsive, paramedics placed a breathing tube, and he recovered gradually over 10 hours (Morris 2003). There is no oral therapeutic use for tea tree oil; it is a topical-only agent. Both published cases involved young children swallowing the oil
- Pre-pubertal boys — controversial gynecomastia association — Henley et al. 2007 NEJM reported three pre-pubertal boys whose gynecomastia (breast tissue growth) coincided with topical use of products containing lavender and tea tree oils and resolved shortly after the products were stopped. In the same paper, studies in human cell lines showed estrogenic and antiandrogenic activity of the two oils, and the authors concluded that repeated topical exposure probably caused the gynecomastia. The conclusion was challenged in a 2014 letter, “Lack of evidence that essential oils affect puberty” (Carson, Tisserand and Larkman, Reproductive Toxicology). The question remains open, and the published cases involved products containing both lavender and tea tree oils
- Allergic contact dermatitis — tea tree oil is the most common essential oil cause of allergic contact dermatitis in patch test referrals. The principal sensitizers are oxidation products (ascaridole, 1,2,4-trihydroxymenthane, peroxides) rather than the parent monoterpenes. Fresh oil sensitization rates are low (under 2% in patch test populations); oxidized oil sensitization rates are substantially higher. For a person with confirmed tea tree oil contact dermatitis, the allergy is to the oil itself, so any product containing it can bring the rash back
- Drug interactions — topical tea tree oil has minimal systemic absorption and few documented drug interactions. Severely compromised skin (extensive burn, ulceration) may absorb enough oil to produce mild systemic effects; the Hammer 2006 toxicity review describes adverse reactions as minimized by applying only diluted oil topically
- Pregnancy and breastfeeding — topical use at standard 5% concentrations on intact skin is generally considered acceptable, but data are limited. Oil applied to the nipple area during breastfeeding can be swallowed by the infant
- Pet safety — tea tree oil is significantly more toxic to cats and dogs than to humans. Even dilute topical application to pets has produced ataxia, hypothermia, depression, and death in cats. The Carson 2006 review describes about 120 mL of undiluted oil applied to the shaved but intact skin of three cats, which caused hypothermia, uncoordination, dehydration and trembling; one of the cats died
Key Research Papers
- Carson CF, Hammer KA, Riley TV (2006). Melaleuca alternifolia (Tea Tree) oil: a review of antimicrobial and other medicinal properties. Clinical Microbiology Reviews. — PubMed PMID: 16418522
- Carson CF, Mee BJ, Riley TV (2002). Mechanism of action of Melaleuca alternifolia (tea tree) oil on Staphylococcus aureus. Antimicrobial Agents and Chemotherapy. — PubMed PMID: 12019108
- Caelli M, Porteous J, Carson CF, Heller R, Riley TV (2000). Tea tree oil as an alternative topical decolonization agent for methicillin-resistant Staphylococcus aureus. Journal of Hospital Infection. — PubMed PMID: 11073734
- Dryden MS, Dailly S, Crouch M (2004). A randomized, controlled trial of tea tree topical preparations versus a standard topical regimen for the clearance of MRSA colonization. Journal of Hospital Infection. — PubMed PMID: 15066738
- Edmondson M, Newall N, Carville K, Smith J, Riley TV, Carson CF (2011). Uncontrolled, open-label, pilot study of tea tree (Melaleuca alternifolia) oil solution in the decolonisation of methicillin-resistant Staphylococcus aureus positive wounds and its influence on wound healing. International Wound Journal. — PubMed PMID: 21564552
- Brady A, Loughlin R, Gilpin D, Kearney P, Tunney M (2006). In vitro activity of tea-tree oil against clinical skin isolates of methicillin-resistant and -sensitive Staphylococcus aureus and coagulase-negative staphylococci. Journal of Medical Microbiology. — PubMed PMID: 17005786
- Hammer KA, Carson CF, Riley TV (2012). Effects of Melaleuca alternifolia (tea tree) essential oil and the major monoterpene component terpinen-4-ol on the development of single- and multistep antibiotic resistance and antimicrobial susceptibility. Antimicrobial Agents and Chemotherapy. — PubMed PMID: 22083482
- Loughlin R, Gilmore BF, McCarron PA, Tunney MM (2008). Comparison of the cidal activity of tea tree oil and terpinen-4-ol against clinical bacterial skin isolates and human fibroblast cells. Letters in Applied Microbiology. — PubMed PMID: 18298453
- Messager S, Hammer KA, Carson CF, Riley TV (2005). Effectiveness of hand-cleansing formulations containing tea tree oil assessed ex vivo on human skin and in vivo with volunteers using European standard EN 1499. Journal of Hospital Infection. — PubMed PMID: 15694979
- LaPlante KL (2007). In vitro activity of lysostaphin, mupirocin, and tea tree oil against clinical methicillin-resistant Staphylococcus aureus. Diagnostic Microbiology and Infectious Disease. — PubMed
- Hammer KA, Carson CF, Riley TV, Nielsen JB (2006). A review of the toxicity of Melaleuca alternifolia (tea tree) oil. Food and Chemical Toxicology. — PubMed PMID: 16243420
- Henley DV, Lipson N, Korach KS, Bloch CA (2007). Prepubertal gynecomastia linked to lavender and tea tree oils. New England Journal of Medicine. — PubMed PMID: 17267908
- Hammer KA, Carson CF, Riley TV (2008). Frequencies of resistance to Melaleuca alternifolia (tea tree) oil and rifampicin in Staphylococcus aureus, Staphylococcus epidermidis and Enterococcus faecalis. International Journal of Antimicrobial Agents. — PubMed PMID: 18571379
- Carson CF, Tisserand R, Larkman T (2014). Lack of evidence that essential oils affect puberty. Reproductive Toxicology. — PubMed PMID: 24556344
- Jacobs MR, Hornfeldt CS (1994). Melaleuca oil poisoning. Journal of Toxicology. Clinical Toxicology. — PubMed PMID: 8057407
- Morris MC, Donoghue A, Markowitz JA, Osterhoudt KC (2003). Ingestion of tea tree oil (Melaleuca oil) by a 4-year-old boy. Pediatric Emergency Care. — PubMed PMID: 12813303
PubMed Topic Searches
Connections
- All Herbs
- Tea Tree Overview
- Tea Tree Benefits Hub
- Tea Tree for Acne
- Tea Tree for Nail Fungus
- Tea Tree for Head Lice
- Antibacterial Herbs
- Manuka Honey (Methicillin-Resistant Staphylococcus Aureus)
- Oregano (Carvacrol)
- Thyme (Thymol)
- Garlic (Allicin)
- Olive Leaf (Oleuropein)
- Silver Nanoparticles
- Staphylococcus aureus (Methicillin-Resistant Staphylococcus Aureus)
- Pseudomonas aeruginosa
- Cellulitis
- History