Atractylodes (Bai Zhu) for Immune Function and Inflammation
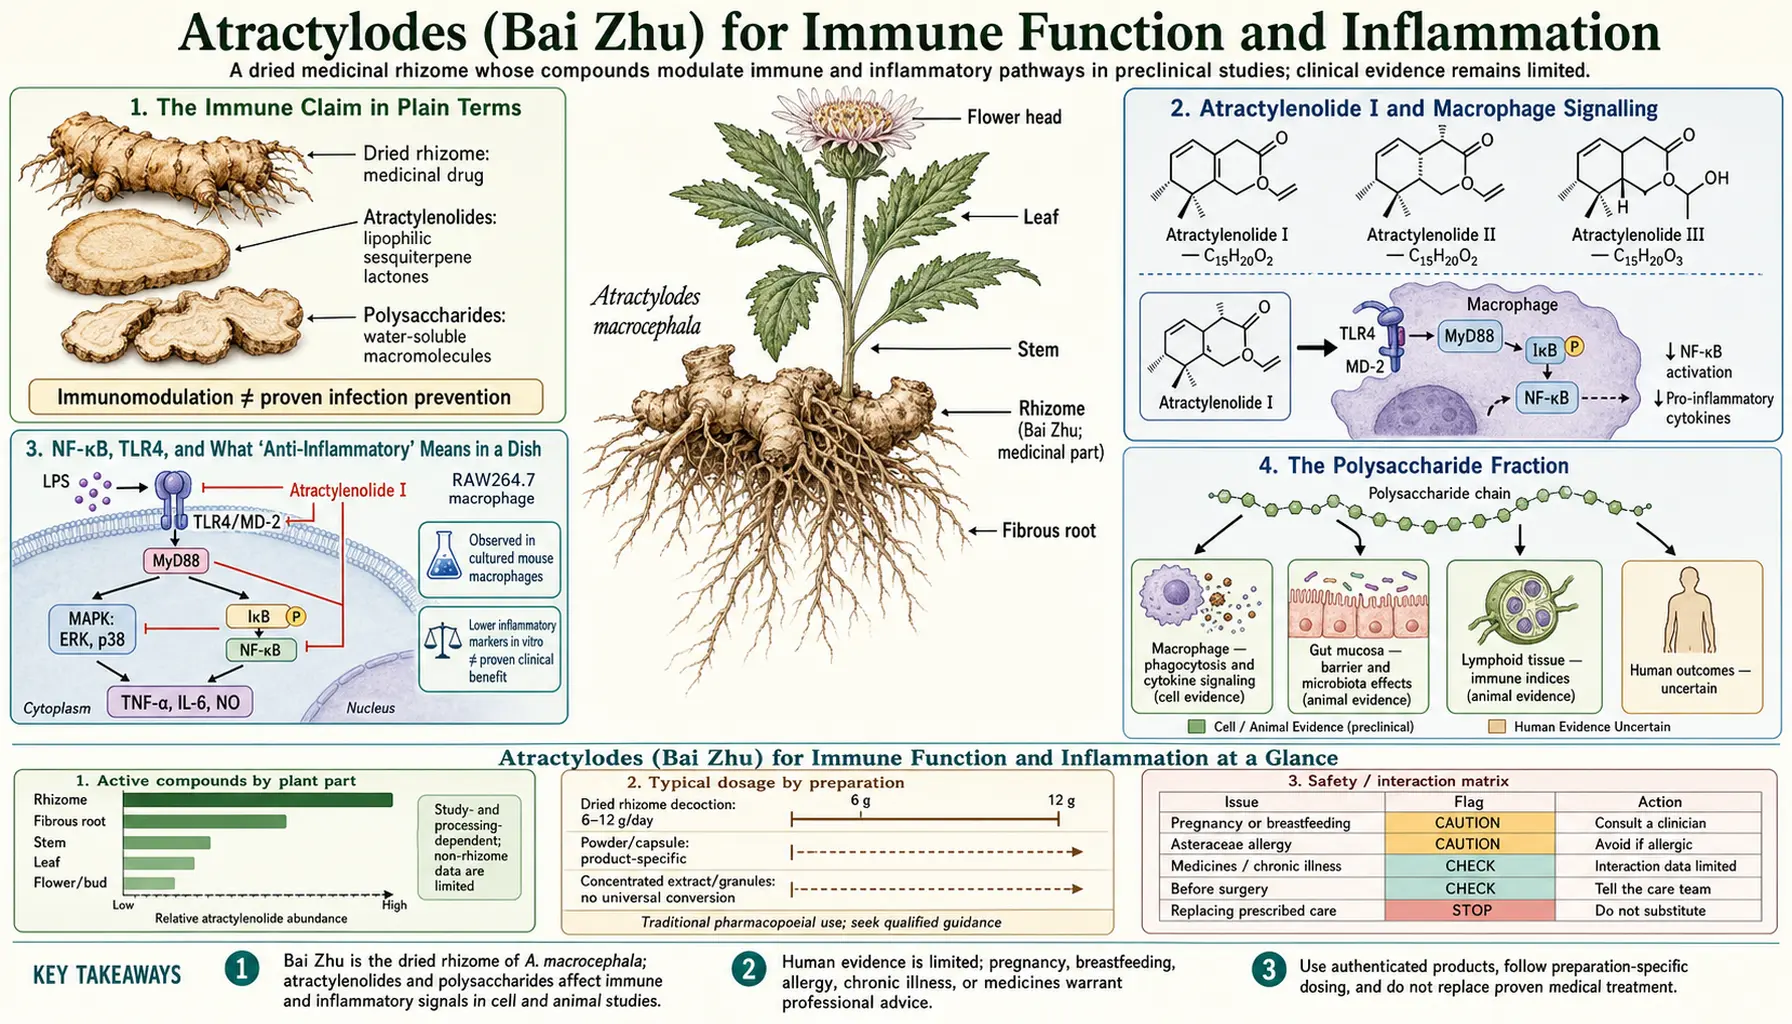
Of everything published on bai zhu — Atractylodes macrocephala Koidz., the dried rhizome Rhizoma Atractylodis Macrocephalae, Vietnamese bạch truật — the immune and inflammation literature is the largest and the most easily misread. It contains real, careful signalling biology. It also contains a large body of cancer cell-line work that is routinely quoted out of context in supplement marketing.
Set expectations honestly up front. Human clinical evidence for bai zhu as a single herb is very limited. The immune literature is overwhelmingly cell culture and rodent work, plus small trials of the multi-herb formula Yu Ping Feng San in which this herb’s individual contribution cannot be isolated. And the oncology-adjacent findings discussed below are preclinical — they are not evidence that this herb treats cancer.
Table of Contents
- The Immune Claim in Plain Terms
- Atractylenolide I and Macrophage Signalling
- NF-κB, TLR4, and What “Anti-Inflammatory” Means in a Dish
- The Polysaccharide Fraction
- Yu Ping Feng San: Stabilising the Exterior
- The Recurrent Respiratory Infection Trials
- The Cancer Literature Is Preclinical
- Autoimmunity and Immunosuppressant Drugs
- Practical Use
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
The Immune Claim in Plain Terms
Traditional texts credit bai zhu with the ability to “stabilise the exterior and stop sweating” (固表止汗). Stripped of the metaphor, that describes a person who catches every virus circulating, sweats easily and inappropriately, feels draughts more than other people do, and takes longer than others to recover. In the traditional model this is a defensive-qi (wei qi) problem, and the remedy is to strengthen the digestion that is supposed to be generating that defensive capacity in the first place — which is why the immune formula, Jade Windscreen Powder, is built on a digestive tonic.
The modern reframing is “immunomodulation.” That word does a lot of concealing work. It is used to mean any measurable change in any immune parameter, in any direction, in any model system — a rise in a cytokine in a cell line, a change in a lymphocyte subset count in a mouse, an antibody titre in a chicken. None of those is the same as fewer infections in a person, and the distance between them is where most supplement marketing lives.
Atractylenolide I and Macrophage Signalling
The volatile-oil fraction of bai zhu contains the sesquiterpene lactones — atractylenolide I, II and III, plus atractylon and β-eudesmol. Atractylenolide I is the main modern research target, and macrophages are the cell type where most of the work has been done.
Macrophages are the immune system’s first responders and general contractors: they engulf debris and pathogens, present antigen, and release the cytokines that either escalate or resolve an inflammatory response. Because they are easy to culture — the mouse RAW 264.7 line is a laboratory staple — they are the default system for testing whether a plant compound does anything immunological.
What the atractylenolide I literature reports, broadly, is a context-dependent effect. Applied to resting macrophages, it has been reported to increase activation markers and cytokine output — the “immune-stimulating” reading. Applied to macrophages already stimulated with bacterial lipopolysaccharide (LPS), it has been reported to reduce the output of tumor necrosis factor-α, interleukin-1 beta (IL-1β), interleukin-6 (IL-6), nitric oxide and prostaglandin E₂ the “anti-inflammatory” reading.
That dual behaviour is often presented as elegant proof that the herb “balances” immunity. The evidence calls for more caution than that. Bidirectional results in cell culture frequently reflect dose, timing and cytotoxicity rather than a genuine regulatory intelligence: at high concentrations many plant lactones stress or kill cells, and a dying macrophage releases fewer cytokines. Studies that report cytokine suppression without concurrent viability data cannot distinguish the two. The better papers do measure viability; not all of them do.
NF-κB, TLR4, and What “Anti-Inflammatory” Means in a Dish
The mechanism most often proposed runs through toll-like receptor 4 (TLR4) and NF-κB. In plain terms: toll-like receptor 4 is a receptor on the macrophage surface that recognises bacterial lipopolysaccharide. When it fires, a signalling cascade frees the transcription factor NF-κB from its inhibitor, NF-κB moves into the nucleus, and it switches on the genes for the inflammatory cytokines. It is the master switch for the innate inflammatory response — a fire alarm wired to the sprinklers.
Atractylenolide I has been reported to dampen that cascade, with proposed points of action including toll-like receptor 4 engagement itself, the phosphorylation and degradation of IκB (the protein that holds NF-κB in the cytoplasm), and downstream mitogen-activated protein kinase (MAPK) pathways. Related work touches on the NLR family pyrin domain containing 3 (NLRP3) inflammasome, a protein complex inside immune cells which controls interleukin-1β maturation.
Three caveats apply:
- NF-κB is not a bad thing. It is how you clear infections. A compound that blunts it is not automatically beneficial; corticosteroids do the same and carry known costs.
- Concentrations used in vitro often exceed anything achievable in vivo. Studies applying tens of micromoles per litre directly to cells are not modelling a person drinking a decoction of a herb whose lactone content is a small percentage of dry weight and whose oral bioavailability is poorly characterised.
- Nothing in this literature is a clinical outcome. It describes what a purified compound does to cultured cells, not what a herb does to a human being.
The Polysaccharide Fraction
The second active fraction is entirely different chemistry: the water-soluble polysaccharides, abbreviated AMP (Atractylodes macrocephala polysaccharide) or PAMK (polysaccharide of Atractylodes macrocephala Koidz.) in the agricultural literature, where they are studied as feed additives for poultry.
Polysaccharides are large sugar polymers. They are not absorbed intact and do not circulate as drug-like molecules. Whatever immune effect they have must be initiated at the gut, where the largest concentration of immune tissue in the body sits — Peyer’s patches, the mesenteric lymph nodes, and the dendritic cells that sample the lumen. Proposed routes include direct engagement of pattern-recognition receptors on gut immune cells and indirect effects through the microbiota and its fermentation products.
Reported findings in rodents and poultry include changes in spleen and thymus weight, altered lymphocyte proliferation, shifted CD4/CD8 ratios, higher secretory immunoglobulin A (IgA), and increased antibody responses to vaccination. Much of this comes from animals deliberately immunosuppressed with cyclophosphamide first — a model that shows a compound can restore a drug-flattened immune system, which is not the same as improving a normal one. The gut barrier page goes into this fraction in more detail.
Yu Ping Feng San: Stabilising the Exterior
Yu Ping Feng San — Jade Windscreen Powder — is the traditional prescription for someone who catches everything. It has three ingredients:
- Astragalus (huang qi) — the chief herb, the one with the largest independent immune literature of the three;
- Bai zhu — the deputy, strengthening digestion so that defensive capacity has something to be built from;
- Siler (fang feng, Saposhnikovia divaricata) — the assistant, dispersing external pathogenic influence.
The name is the clinical concept: a screen at the window that keeps the wind out without shutting you in. It is used prophylactically, over weeks to months, for people with frequent colds — not as an acute treatment once you are already ill.
For the honest reader, the important structural point is that bai zhu is the second herb in a three-herb formula whose lead ingredient has its own well-developed immune pharmacology. Any clinical benefit of Jade Windscreen is a benefit of the combination. Attributing it to atractylodes is not supported by the trial designs.
The Recurrent Respiratory Infection Trials
Yu Ping Feng San has been trialled, mostly in China and mostly in children, for recurrent respiratory tract infection — and in adults for allergic rhinitis, asthma and chronic obstructive pulmonary disease as an add-on. Systematic reviews of this body of work exist and are worth reading for what they say about quality.
The recurring findings of those reviews:
- Individual trials are small — often several dozen to a couple of hundred participants.
- Reported results are almost uniformly positive, which in a literature of this size is itself a red flag for publication bias rather than a reassurance.
- Methodology is frequently weak: randomisation and allocation concealment inadequately described, blinding absent, comparators heterogeneous (sometimes placebo, often an antiviral, an immunostimulant, or nothing), and outcome definitions inconsistent — “number of infections” is defined differently across studies.
- Formula composition and dose vary between trials, so they are not really testing the same intervention.
- Reviewers’ conclusions land consistently on: possible benefit, evidence too low in quality to be confident, rigorous trials needed.
Three examples show the pattern:
- A 2016 meta-analysis in children. Across 12 trials with 1,236 children with recurrent respiratory tract infections, adding the Yupingfeng formula to treatment reduced the frequency of infections (by 3.80 episodes, as a weighted mean difference) and raised blood levels of the antibodies immunoglobulin A, G and M (IgA, IgG and IgM). The authors write that more well-designed trials with larger sample sizes are needed to evaluate its efficacy and safety.
- A 2022 meta-analysis of granules. Across 17 randomised trials of Yupingfeng granules added to usual treatment in children with recurrent respiratory tract infections, the overall clinical response rate was higher (risk ratio 1.18) and immunoglobulin levels were higher than in the comparison groups — but the authors conclude that the granules’ effectiveness and safety “remain to be further verified”.
- A placebo-controlled trial in allergic rhinitis. In a randomised, double-blind trial of a modified Yu Ping Feng formula, 58 people with allergic rhinitis (recruited between April 2022 and June 2023) took the formula or a placebo for 8 weeks. Quality-of-life scores improved at weeks 4, 8, 12 and 16 compared with placebo, but the nasal symptom score at week 8, one of the trial’s main outcomes, did not improve; no overt side effects were seen in either group.
So: a plausible and traditionally coherent use, a signal in low-quality trials, no high-quality confirmation, and no way to attribute any of it to bai zhu specifically. For Jade Windscreen in winter colds, the reviews describe a possible benefit resting on thin evidence, not a proven one.
The Cancer Literature Is Preclinical
A large share of atractylenolide papers indexed in PubMed involve cancer cell lines. Search the compound and you will find titles reporting that atractylenolide I or III inhibits proliferation, induces apoptosis, arrests the cell cycle, or suppresses migration in gastric, colorectal, ovarian, lung, breast, bladder or melanoma cell lines, often with mouse xenograft follow-up. Related work examines atractylenolides in cancer-associated cachexia models.
None of that is evidence that atractylodes treats cancer in a human being.
Why not:
- Killing cancer cells in a dish is easy. Bleach does it. Distilled water does it. Thousands of plant compounds do it. The entire difficulty of oncology is selectivity and delivery — harming the tumour and not the patient, at a concentration reachable in the tumour after oral dosing. Cell-line work addresses none of that.
- Concentrations are usually unreachable. The micromolar levels applied to cultured cells generally cannot be produced in human tissue by swallowing a decoction.
- Xenograft models flatter compounds. Human tumour cells injected under the skin of an immunodeficient mouse behave very differently from a tumour in an intact human immune environment. The attrition rate from positive xenograft data to positive human trial is brutal.
- There is a concrete harm. People with cancer read these abstracts and delay or decline effective treatment. That is not hypothetical, and choosing alternative medicine instead of treatment has a measured cost: a study of 281 patients with non-metastatic breast, prostate, lung or colorectal cancer who chose alternative medicine as their only anticancer treatment found that their risk of death was 2.5 times that of matched patients given conventional cancer treatment (hazard ratio 2.50).
There is also a specific safety concern that cuts against the marketing: some of the same signalling this herb touches — immune activation, NF-κB modulation — could in principle interact with immunotherapy or chemotherapy in unpredictable directions. The concern is theoretical, based on the direction of the preclinical pharmacology rather than on a documented clinical event.
Autoimmunity and Immunosuppressant Drugs
The polysaccharide fraction is studied specifically for immune stimulation. That creates a coherent theoretical concern for two groups:
- People with autoimmune disease — rheumatoid arthritis, lupus, multiple sclerosis, psoriasis, inflammatory bowel disease, autoimmune thyroid disease. If a herb genuinely pushes immune activity up, that direction is not obviously desirable when the problem is an immune system already attacking the wrong target. In practice, no flare signal has been documented for atractylodes specifically — but nobody has looked, and “no reports” is not “no risk.”
- People on immunosuppressants — tacrolimus, ciclosporin, azathioprine, mycophenolate, methotrexate, or a biologic; and transplant recipients above all, where graft survival depends on maintaining suppression. In theory an immune stimulant works against drugs given to suppress immunity; the interaction has not been documented in people.
This is a theoretical interaction based on the direction of the preclinical pharmacology, not a documented clinical event. It is flagged here because it is exactly the kind of thing that gets omitted from product labelling.
Practical Use
In traditional practice, the immune indication is a formula indication, not a single-herb one. Yu Ping Feng San is taken as a decoction, granule or patent pill over weeks to months during the season when infections are frequent, and stopped during an acute infection — the classical logic being that you do not “close the windows” while a pathogen is already inside. Bai zhu’s share within it is the usual 6–12 g/day of dried rhizome.
On labels: the binomial matters — Atractylodes macrocephala is bai zhu; A. lancea or A. chinensis is cang zhu, a more aromatic and more strongly drying herb used to dry dampness rather than to tonify, and not the herb in Jade Windscreen. The medicinal part is the rhizome. Both the single herb and the three-herb formula are sold, and the labels often do not make clear which a product is.
For comparison, seasonal influenza and COVID vaccination, hand hygiene, sleep, correcting a documented vitamin D deficiency, and not smoking all have far better support for reducing respiratory infection than any herb in this article.
Cautions and Contraindications
- Immunosuppressants and transplant. Theoretical opposition to the intended drug effect; the interaction has not been documented in people.
- Autoimmune disease. Theoretical concern from the direction of the preclinical pharmacology; undocumented either way.
- Active cancer treatment. The cell-line literature is not clinical evidence, and alternative medicine used in place of conventional treatment for curable cancer was associated with a higher risk of death (see above).
- Asteraceae allergy. Atractylodes is in the daisy family. People who react to ragweed, chrysanthemum, chamomile or marigold may plausibly cross-react to it.
- Diuretics. Bai zhu is traditionally fluid-moving; combined with furosemide, a thiazide or spironolactone the theoretical effect on fluid and electrolytes is additive.
- Pregnancy. Classical texts describe bai zhu as calming the fetus, and it appears in traditional pregnancy formulas. There is no reliable human safety data supporting that use, and no adequate study exists. Tradition does not fill that gap.
- Acute febrile illness. Traditional practice suspends “exterior-stabilising” formulas during an active infection; different herbs are used then.
- Traditional contraindication. Avoided in yin deficiency with heat — dryness, thirst, night sweats.
Key Research Papers
Each link resolves to the PubMed record of the paper named, or to a live PubMed record set for the topic named. Author, title and journal are plain text so you can verify each independently.
- Zhu B, Zhang QL, Hua JW, Cheng WL, Qin LP. The traditional uses, phytochemistry, and pharmacology of Atractylodes macrocephala Koidz.: a review. Journal of Ethnopharmacology. 2018;226:143–167. PubMed PMID: 30130541
- Atractylenolide I and macrophage activation, TLR4 engagement and NF-κB signalling. PubMed record set.
- Atractylenolides and LPS-induced cytokine release in RAW 264.7 macrophages. PubMed record set.
- Immunomodulatory activity of Atractylodes macrocephala polysaccharide (AMP/PAMK) in animal models. PubMed record set.
- PAMK in cyclophosphamide-immunosuppressed animal models. PubMed record set.
- Systematic reviews of Yu Ping Feng San for recurrent respiratory tract infection. PubMed record set.
- Yu Ping Feng San as add-on therapy in allergic rhinitis, asthma and COPD. PubMed record set.
- Preclinical (cell line and xenograft) studies of atractylenolides in cancer models — hypothesis-generating only. PubMed record set.
- Translation failure rates from preclinical oncology models to human trials. PubMed record set.
- Song T, Hou X, Yu X, et al. Adjuvant treatment with Yupingfeng formula for recurrent respiratory tract infections in children: a meta-analysis of randomized controlled trials. Phytotherapy Research. 2016;30(7):1095–1103. PubMed PMID: 27145435
- Zhang L, Wang X, Wang D, Guo Y, Zhou X, Yu H. Adjuvant treatment with yupingfeng granules for recurrent respiratory tract infections in children: a systematic review and meta-analysis. Frontiers in Pediatrics. 2022;10:1005745. PubMed PMID: 36619520
- Lin ZX, Ho TM, Xian YF, et al. Exploring the efficacy and safety of Yu-Ping-Feng powder with variation against allergic rhinitis: a randomized, double-blind, placebo-controlled trial. Chinese Medicine. 2025;20(1):70. PubMed PMID: 40420199
- Johnson SB, Park HS, Gross CP, Yu JB. Use of alternative medicine for cancer and its impact on survival. Journal of the National Cancer Institute. 2018;110(1). PubMed PMID: 28922780
- Methodological quality and publication bias in Chinese herbal medicine randomised trials. PubMed record set.
PubMed Topic Searches
- PubMed: Atractylenolide
- PubMed: Atractylodes macrocephala immune
- PubMed: Yupingfeng San
- PubMed: PAMK polysaccharide Atractylodes
- PubMed: Astragalus polysaccharide immune function
- PubMed: NF-kB innate immunity review
- PubMed: Saposhnikovia divaricata (fang feng) pharmacology
- PubMed: Herbal supplements and immunosuppressant interaction
Connections
- All Herbs
- Atractylodes (Bai Zhu) — the main research article
- Atractylodes Benefits hub
- Atractylodes: History and Traditional Use
- Digestion and Spleen Qi
- Fluid Balance and Edema
- Gut Barrier and Microbiome
- Astragalus — chief herb in Jade Windscreen
- Codonopsis
- Poria Mushroom
- Licorice
- Ginger
- Small Intestinal Bacterial Overgrowth