Atractylodes (Bai Zhu) for Gut Barrier and Microbiome
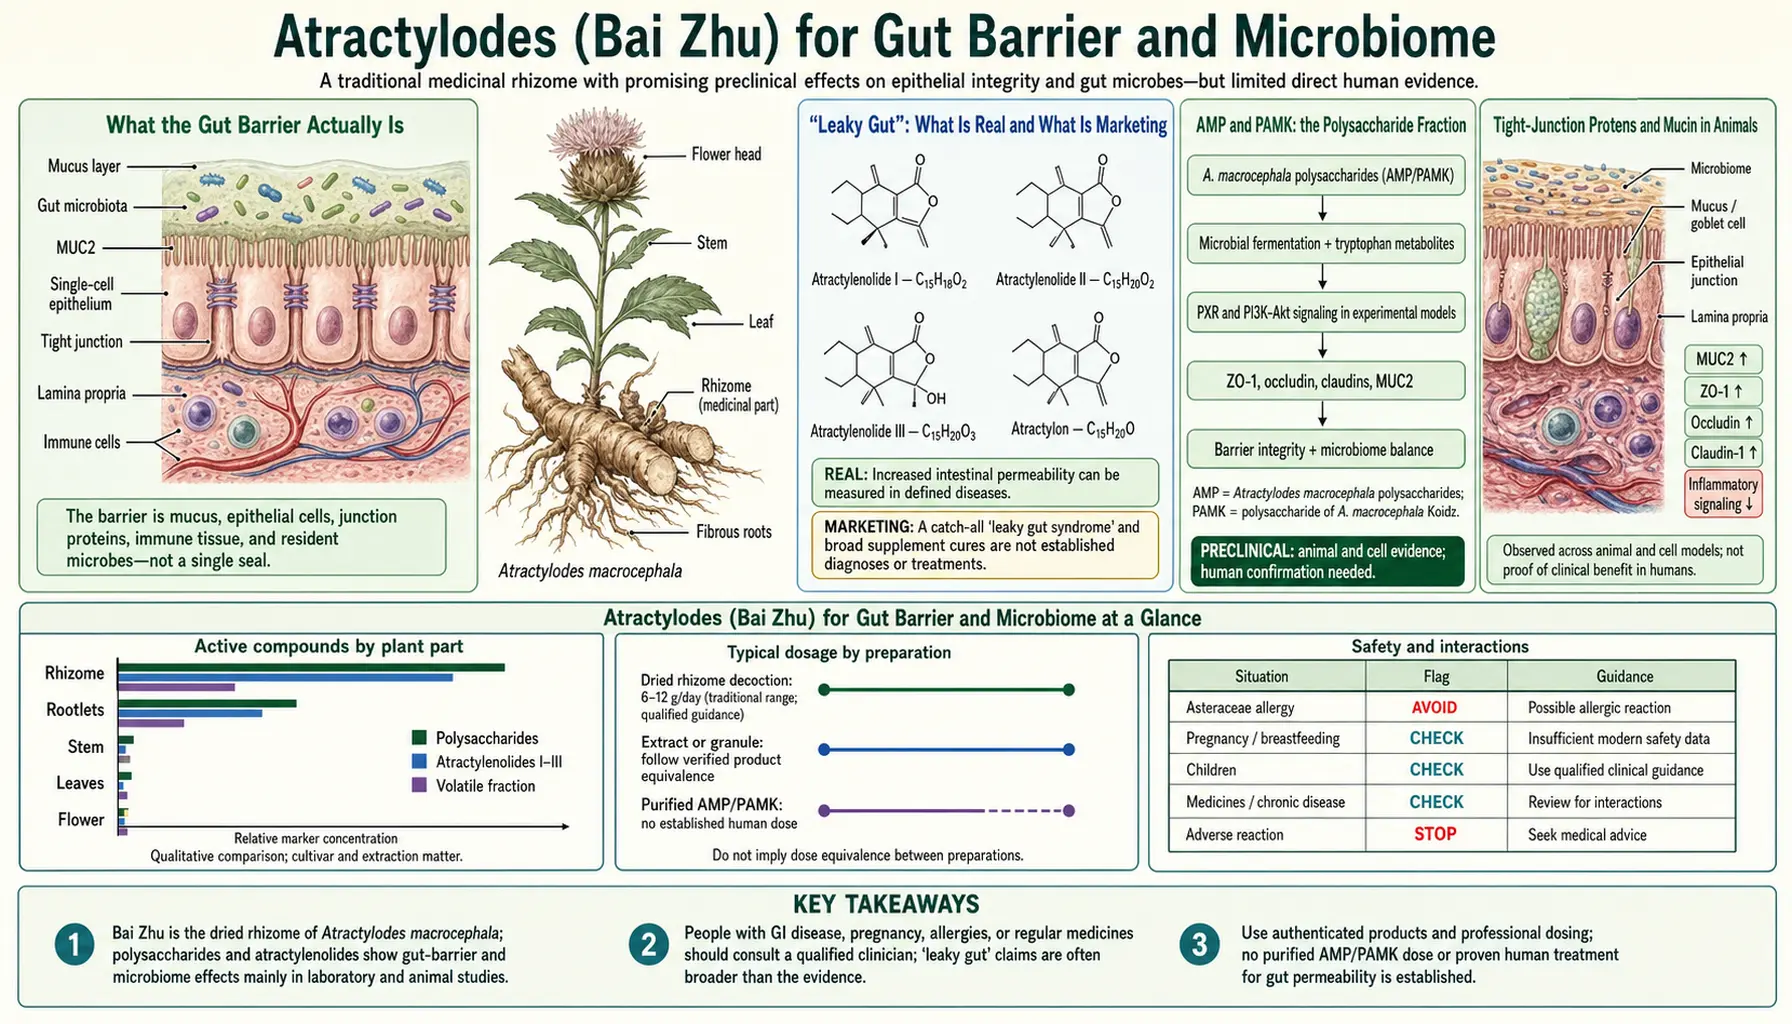
This is the newest claim attached to bai zhu — Atractylodes macrocephala Koidz., the dried rhizome Rhizoma Atractylodis Macrocephalae, Vietnamese bạch truật — and the one with the shortest history. Classical texts say nothing about intestinal barriers or microbiota; those concepts did not exist. What has happened is that modern researchers took a herb with a two-thousand-year reputation for fixing loose stools and asked whether the mechanism might be barrier function and gut bacteria. The answer, so far, comes almost entirely from mice, rats, geese and broiler chickens.
The honesty note, which matters more here than anywhere else in this family of pages. Human clinical evidence for bai zhu as a single herb is very limited; the gut-barrier work is preclinical without exception. And rodent gut-barrier findings have a particularly poor record of translating to humans — a long list of compounds that raised tight-junction proteins in mice have gone on to do nothing measurable in people. Nothing on this page says atractylodes treats “leaky gut” or cures irritable bowel syndrome, because nothing in the literature supports either claim.
Table of Contents
- What the Gut Barrier Actually Is
- “Leaky Gut”: What Is Real and What Is Marketing
- AMP and PAMK: the Polysaccharide Fraction
- Tight-Junction Proteins and Mucin in Animals
- Prebiotic Framing and Short-Chain Fatty Acids
- Why Rodent Barrier Findings Translate Badly
- The Formulas Used for Diarrhoea and Irritable Bowel Syndrome-Type Symptoms
- Zonulin, Lipopolysaccharide Panels and What Testing Can Tell You
- Practical Use — and What Has Better Evidence
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
What the Gut Barrier Actually Is
Your gut lining is a single layer of cells — one cell thick — separating roughly forty trillion bacteria from your bloodstream. It has to be selectively permeable: nutrients through, bacteria and endotoxin out. It manages this with several overlapping layers:
- The mucus layer. Secreted by goblet cells, built from large glycoproteins called mucins — MUC2 is the dominant one in the intestine. In the colon this forms two layers: an outer one where bacteria live, and an inner one that is normally kept nearly sterile. It is the first line of defence, and it is physical, not immunological.
- The epithelium. The enterocytes themselves, replaced every three to five days — among the fastest-turning tissues in the body.
- Tight junctions. Protein complexes that seal the gaps between adjacent cells. The main players are occludin, the claudins, and the scaffolding protein ZO-1 (zonula occludens-1). They are not static seals but dynamic gates that open and close under regulation.
- Gut-associated lymphoid tissue. Peyer’s patches, plasma cells producing secretory immunoglobulin A (IgA), and dendritic cells sampling the lumen — the largest concentration of immune tissue in the body.
Barrier failure is real and well documented in specific diseases: coeliac disease, Crohn’s disease, severe burns, critical illness, alcoholic liver disease, and chemotherapy-induced mucositis. In those settings, measurable increased permeability is an established finding.
“Leaky Gut”: What Is Real and What Is Marketing
Two distinct things share this name, and separating them is essential.
The real phenomenon is increased intestinal permeability, measurable in a laboratory with dual-sugar absorption tests, and demonstrated in the conditions listed above. It is a genuine area of research and nobody serious disputes it exists.
The marketing construct is “leaky gut syndrome” the claim that a permeable intestine is the hidden root cause of fatigue, brain fog, joint pain, eczema, mood disorders, autoimmune disease and food intolerance in the general population, diagnosable by mail-order test and treatable with a supplement stack. That claim goes far beyond the evidence in at least three ways: the causal direction is usually unestablished (in most conditions where permeability is increased, it may well be a consequence rather than a cause); the diagnostic tests marketed direct-to-consumer are not validated for that purpose; and no supplement has been shown in adequate human trials to normalise permeability and thereby improve any of those symptoms.
Atractylodes has not been shown to treat “leaky gut,” and it has not been shown to cure irritable bowel syndrome. Anyone selling it for either is ahead of the data by a wide margin.
AMP and PAMK: the Polysaccharide Fraction
The gut-barrier research does not use the whole herb or the aromatic volatile oil. It uses the water-soluble polysaccharide fraction, abbreviated AMP (Atractylodes macrocephala polysaccharide) or PAMK, which is the standard abbreviation in the animal-science literature where these compounds are studied as feed additives.
Some properties worth knowing:
- They are large sugar polymers, typically glucose- and fructose-rich, with molecular weights in the tens to hundreds of kilodaltons. Reported composition varies considerably between papers because extraction and purification protocols differ — which makes cross-study comparison harder than it looks.
- They are not absorbed intact. Human digestive enzymes cannot break most of these linkages, so they reach the colon largely unchanged. Any effect is a luminal and mucosal effect, not a systemic drug effect.
- They are extracted efficiently by water, which means traditional decoction delivers them and an alcohol tincture largely does not. A traditional decoction and a modern tincture are, on this axis, different products.
- Much of the research funding is agricultural. PAMK is studied in geese and broilers because gut health drives feed conversion. That is legitimate science, and it also means the dosing, endpoints and animal models were chosen for farming, not for human medicine.
Tight-Junction Proteins and Mucin in Animals
The core body of work runs like this. Animals — mice, rats, geese, chickens — are given a barrier insult: dextran sodium sulphate (DSS) to induce colitis, lipopolysaccharide (LPS) to induce systemic inflammation, heat stress, a mycotoxin, or a chemotherapy agent. Some receive PAMK in feed or by gavage; controls do not. Afterwards, investigators measure intestinal tissue for tight-junction protein expression (occludin, ZO-1, claudin-1), goblet-cell numbers and MUC2, villus height and crypt depth, inflammatory cytokines in the mucosa, and sometimes serum markers of translocation such as endotoxin, D-lactate or diamine oxidase.
The consistently reported pattern is that PAMK-treated animals show higher occludin, ZO-1 and claudin expression, more goblet cells and mucin, better-preserved villus architecture, and lower mucosal inflammatory cytokines than untreated damaged controls. Some studies also report reduced markers of bacterial translocation.
How to read that fairly:
- It is a real and reasonably reproducible preclinical finding, reported by several independent groups across several species. That is more than can be said for many herbal claims.
- It is a protection-against-injury result, not an improvement-of-normal result. Nearly all of it comes from animals given a deliberate insult. It does not show that a healthy gut gets better.
- Doses in feeding trials are often high relative to body weight compared with a human decoction, and the polysaccharide is usually purified rather than delivered as whole herb.
- Protein expression on a Western blot is a surrogate. It is not the same as measured permeability, and it is a long way from a symptom.
Prebiotic Framing and Short-Chain Fatty Acids
A second line of work asks whether these polysaccharides act as a prebiotic — a substrate that colonic bacteria ferment, in the same general category as inulin and resistant starch.
The mechanistic story is straightforward and biologically sound: undigested polysaccharide reaches the colon; resident bacteria ferment it; fermentation produces short-chain fatty acids — acetate, propionate and above all butyrate. Butyrate is the preferred fuel of colonocytes, and there is good independent evidence that it supports barrier integrity and has anti-inflammatory effects in the colonic mucosa. So a fermentable fibre that raises butyrate is a plausible barrier-support agent.
Studies of atractylodes polysaccharide in rodents have reported shifts in microbiota composition — commonly framed as increases in Lactobacillus and Bifidobacterium and changes in the ratio of the major phyla — along with higher caecal short-chain fatty acids.
Two honest qualifications. First, the interpretive framework here is shaky: labelling taxa “good” or “bad” is a simplification the microbiome field has largely moved past, and the Firmicutes-to-Bacteroidetes ratio in particular has not held up as a meaningful health marker. Second, and more deflating: if the mechanism really is prebiotic fermentation, then bai zhu is doing something that ordinary dietary fibre does — at a fraction of the quantity. A 9 g dose of dried rhizome contributes a very small amount of fermentable substrate compared with a serving of oats, beans or vegetables.
Why Rodent Barrier Findings Translate Badly
This deserves its own section, because it is the reason to be cautious about everything above.
- Rodent and human guts differ substantially. Caecum size and function, colonic transit, mucus architecture, bile-acid pools, and baseline microbiota composition are all different. Laboratory mice are also genetically near-identical, raised in a clean environment, and eating a fixed diet — none of which resembles a human population.
- The insult models are artificial. DSS colitis is a chemically induced injury used because it is convenient and reproducible, not because it is Crohn’s disease. Protecting against DSS predicts very little about protecting against human inflammatory bowel disease.
- Surrogate endpoints inflate apparent success. Tight-junction protein expression is a snapshot of one variable. Human trials have to measure permeability, symptoms or disease activity — and the effect that looked robust on a blot routinely disappears there.
- There is a track record, and it is not encouraging. Glutamine, zinc carnosine, colostrum, various probiotic strains and multiple plant polysaccharides have all produced impressive rodent barrier data; human trials have ranged from modest and setting-specific to flatly negative. Atractylodes polysaccharide has not yet even had that test.
- Publication bias. Negative preclinical results in this field are rarely published, so the visible literature is systematically more favourable than the underlying reality.
The correct posture is interest, not confidence. This is a reasonable hypothesis waiting for a human trial that nobody has run.
The Formulas Used for Diarrhoea and Irritable Bowel Syndrome-Type Symptoms
What tradition actually offers here is formulas for chronic loose stools, which is where a modern researcher would look for a barrier effect:
- Shen Ling Bai Zhu San — the classical prescription for chronic diarrhoea with poor appetite. Built on Four Gentlemen (codonopsis or ginseng, bai zhu, poria, licorice) plus lotus seed, coix, Chinese yam and cardamom — several of which are themselves starchy, fermentable foods, which is worth noticing if you find the prebiotic hypothesis persuasive.
- Tong Xie Yao Fang — bai zhu, white peony, tangerine peel and siler. The classical formula for pain-with-urgency diarrhoea, often triggered by stress, which is about as close as classical Chinese medicine gets to describing diarrhoea-predominant irritable bowel syndrome (IBS).
- Charred bai zhu (jiao bai zhu) — the processing form traditionally reserved for diarrhoea, on the principle that charring makes a herb astringent. Note the direct conflict with the polysaccharide hypothesis: charring drives off volatile oil and degrades organic material, so the traditional anti-diarrhoeal form is not the form best preserved for polysaccharide content. Tradition and modern mechanism do not always point the same way, and pretending they do is a form of dishonesty.
Trials of Shen Ling Bai Zhu San for chronic diarrhoea exist, mainly from China, and share the limitations described across these pages: small, unblinded, inconsistently reported, and testing a formula rather than a herb. A 2022 meta-analysis pooled 14 randomised trials with 1,158 adults with chronic diarrhoea: Shen Ling Bai Zhu San, with or without conventional medicine, was linked to greater patient-reported satisfaction than conventional medicine alone, with no increase in side effects. The authors called for rigorous, adequately powered trials with objective outcome measures to confirm the effect.
Tong Xie Yao Fang, which contains bai zhu, has been tested against placebo in two double-blind trials in diarrhoea-predominant irritable bowel syndrome. In a 2018 trial of 160 people treated for 4 weeks, 57.5% of those taking the formula granules reported adequate relief of their overall symptoms, compared with 37.5% on placebo. In a 2025 trial of 96 people treated for 8 weeks, 79.2% on the formula and 70.8% on placebo responded; the difference was not statistically significant, and both groups improved substantially.
Zonulin, Lipopolysaccharide Panels and What Testing Can Tell You
A “leaky gut” result is only as meaningful as the test that produced it.
Serum zonulin is the most heavily marketed test. Zonulin is a protein that regulates tight junctions, and its biology is genuine — but the commercial ELISA kits have been shown to cross-react with other proteins, so what they measure is not reliably zonulin, and reference ranges are not standardised between kits. In a 2018 German study that measured serum zonulin in 376 people, a widely used commercial zonulin ELISA kit did not detect pre-haptoglobin-2 — the protein identified as zonulin — even when the purified protein was added; it picked up related proteins instead, with properdin the most likely candidate. A number is produced; its meaning is unclear.
Anti-LPS and anti-endotoxin antibody panels sold direct to consumers are likewise not validated as diagnostics for intestinal permeability in an otherwise healthy person.
Dual-sugar absorption tests (lactulose/mannitol or lactulose/rhamnose) are the closest thing to a research standard: you drink two sugars of different sizes and their ratio in urine reflects paracellular leak. Even these are affected by kidney function, gastric emptying, collection timing and transit, and they are used mainly in research rather than clinical practice.
The practical consequence: an abnormal result on a consumer permeability panel is not a diagnosis and does not by itself justify treatment. If you have persistent gut symptoms, the tests that actually change management are coeliac serology, faecal calprotectin, inflammatory markers, thyroid function, and where indicated endoscopy — not a zonulin number.
Practical Use — and What Has Better Evidence
Traditionally bai zhu is taken as part of a formula, as a decoction, at the usual 6–12 g/day of dried rhizome, over weeks rather than days; a concrete outcome such as stool form on the Bristol scale is one way any change can be judged. Decoction matters here more than usual, since water extraction is what delivers the polysaccharide fraction that all the barrier research is about; a tincture largely does not.
The binomial on the label matters. Atractylodes macrocephala is bai zhu. A. lancea or A. chinensis is cang zhu — more aromatic, more strongly drying, used to dry dampness rather than to tonify, and not the herb in these formulas. Western labels that say only “Atractylodes” do not show the species; a supplier who will not specify the species is telling you something about their supply chain.
For gut-barrier and microbiome health in humans, the factors with actual evidence are unglamorous: dietary fibre diversity (30 g/day of fibre from many plant sources), fermented foods, less alcohol, fewer unnecessary nonsteroidal anti-inflammatory drugs (NSAIDs) and antibiotics (both are known to disturb the gut lining and the gut bacteria), adequate sleep, and treatment of the underlying disease where one exists. Any herb is a rounding error next to those.
Cautions and Contraindications
- Chronic diarrhoea has many causes. Coeliac disease, inflammatory bowel disease, microscopic colitis, bile-acid diarrhoea, pancreatic exocrine insufficiency, thyroid disease and colorectal cancer all cause chronic diarrhoea. Blood in the stool, unintentional weight loss, night-time diarrhoea, anaemia or new symptoms after age 50 are warning signs that doctors investigate for these diseases.
- Fermentable substrate can worsen bloating. If your symptoms fit small intestinal bacterial overgrowth (SIBO) or you react badly to FODMAPs, a fermentable polysaccharide may increase gas and distension rather than relieve it. Starchy formula ingredients such as Chinese yam and lotus seed can do the same.
- Asteraceae allergy. Atractylodes is in the daisy family; cross-reaction is plausible if you react to ragweed, chrysanthemum, chamomile or marigold.
- Diuretics. Bai zhu is traditionally fluid-moving; the theoretical effect alongside furosemide, a thiazide or spironolactone is additive on fluid and electrolyte loss — and matters more if you are also losing fluid to diarrhoea.
- Pregnancy. Classical texts describe bai zhu as calming the fetus and it appears in traditional pregnancy formulas, but there is no reliable human safety data supporting that use and no adequate study exists.
- Immunosuppressants. The same polysaccharide fraction discussed here is studied for immune stimulation in animal and laboratory studies — an effect that runs opposite to the purpose of tacrolimus, ciclosporin, azathioprine, methotrexate and biologics, which are taken to damp the immune system down. No study has tested bai zhu together with these drugs in people.
- Traditional contraindication. Avoided in yin deficiency with heat — dryness, thirst, night sweats.
Key Research Papers
Entries ending in a PubMed PMID link point to a single paper; the others link to a live PubMed record set for the topic named. Author, title and journal are plain text so each can be verified independently.
- Zhu B, Zhang QL, Hua JW, Cheng WL, Qin LP. The traditional uses, phytochemistry, and pharmacology of Atractylodes macrocephala Koidz.: a review. Journal of Ethnopharmacology. 2018;226:143–167. PubMed PMID: 30130541
- PAMK and intestinal tight-junction proteins (occludin, ZO-1, claudin) in rodent and poultry models. PubMed record set.
- Atractylodes macrocephala polysaccharide and mucin/goblet-cell responses in the intestine. PubMed record set.
- Atractylodes polysaccharide in DSS-induced colitis models. PubMed PMID: 41317806.
- Effects of Atractylodes macrocephala polysaccharide on gut microbiota composition and short-chain fatty acids. PubMed record set.
- Butyrate, colonocyte metabolism and intestinal barrier function. PubMed record set.
- Intestinal permeability measurement: dual-sugar tests and their limitations. PubMed record set.
- Scheffler L, Crane A, Heyne H, Tönjes A, Schleinitz D, Ihling CH, et al. Widely used commercial ELISA does not detect precursor of haptoglobin2, but recognizes properdin as a potential second member of the zonulin family. Frontiers in Endocrinology. 2018;9:22. PubMed PMID: 29459849
- Wang H, Hou YN, Yang M, Feng Y, Zhang YL, Smith CM, et al. Herbal formula Shenling Baizhu San for chronic diarrhea in adults: a systematic review and meta-analysis. Integrative Cancer Therapies. 2022;21:15347354221081214. PubMed PMID: 35635135
- Chen M, Tang TC, Wang Y, Shui J, Xiao XH, Lan X, et al. Randomised clinical trial: Tong-Xie-Yao-Fang granules versus placebo for patients with diarrhoea-predominant irritable bowel syndrome. Alimentary Pharmacology & Therapeutics. 2018;48(2):160–168. PubMed PMID: 29856472
- Liang SB, Cheng HJ, Zhang QY, Han M, Li YF, Cao HJ, et al. Chinese herbal formula Tongxie Yaofang granules for diarrhoea-predominant irritable bowel syndrome: a randomised, double-blind, placebo-controlled, phase II trial. BMJ Open. 2025;15(1):e088410. PubMed PMID: 39870499
- Translation of preclinical intestinal-barrier findings to human trials. PubMed record set.
PubMed Topic Searches
- PubMed: Atractylodes macrocephala polysaccharide
- PubMed: PAMK intestinal
- PubMed: Intestinal barrier tight junction ZO-1 occludin
- PubMed: MUC2 mucus layer colon barrier
- PubMed: Prebiotic polysaccharide short-chain fatty acids
- PubMed: Leaky gut syndrome evidence critique
- PubMed: Shenling Baizhu San
- PubMed: Dietary fibre diversity and the human microbiome
Connections
- All Herbs
- Atractylodes (Bai Zhu) — the main research article
- Atractylodes Benefits hub
- Atractylodes: History and Traditional Use
- Digestion and Spleen Qi
- Fluid Balance and Edema
- Immune and Inflammation
- Small Intestinal Bacterial Overgrowth — when fermentable substrate makes things worse
- Codonopsis
- Poria Mushroom
- Licorice
- Astragalus
- Ginger
- White Peony Root (Bai Shao) — bai zhu's antispasmodic partner in Tong Xie Yao Fang, the pain-with-urgency diarrhoea formula above