Cod Liver Oil — Vitamin D and the Original Multivitamin
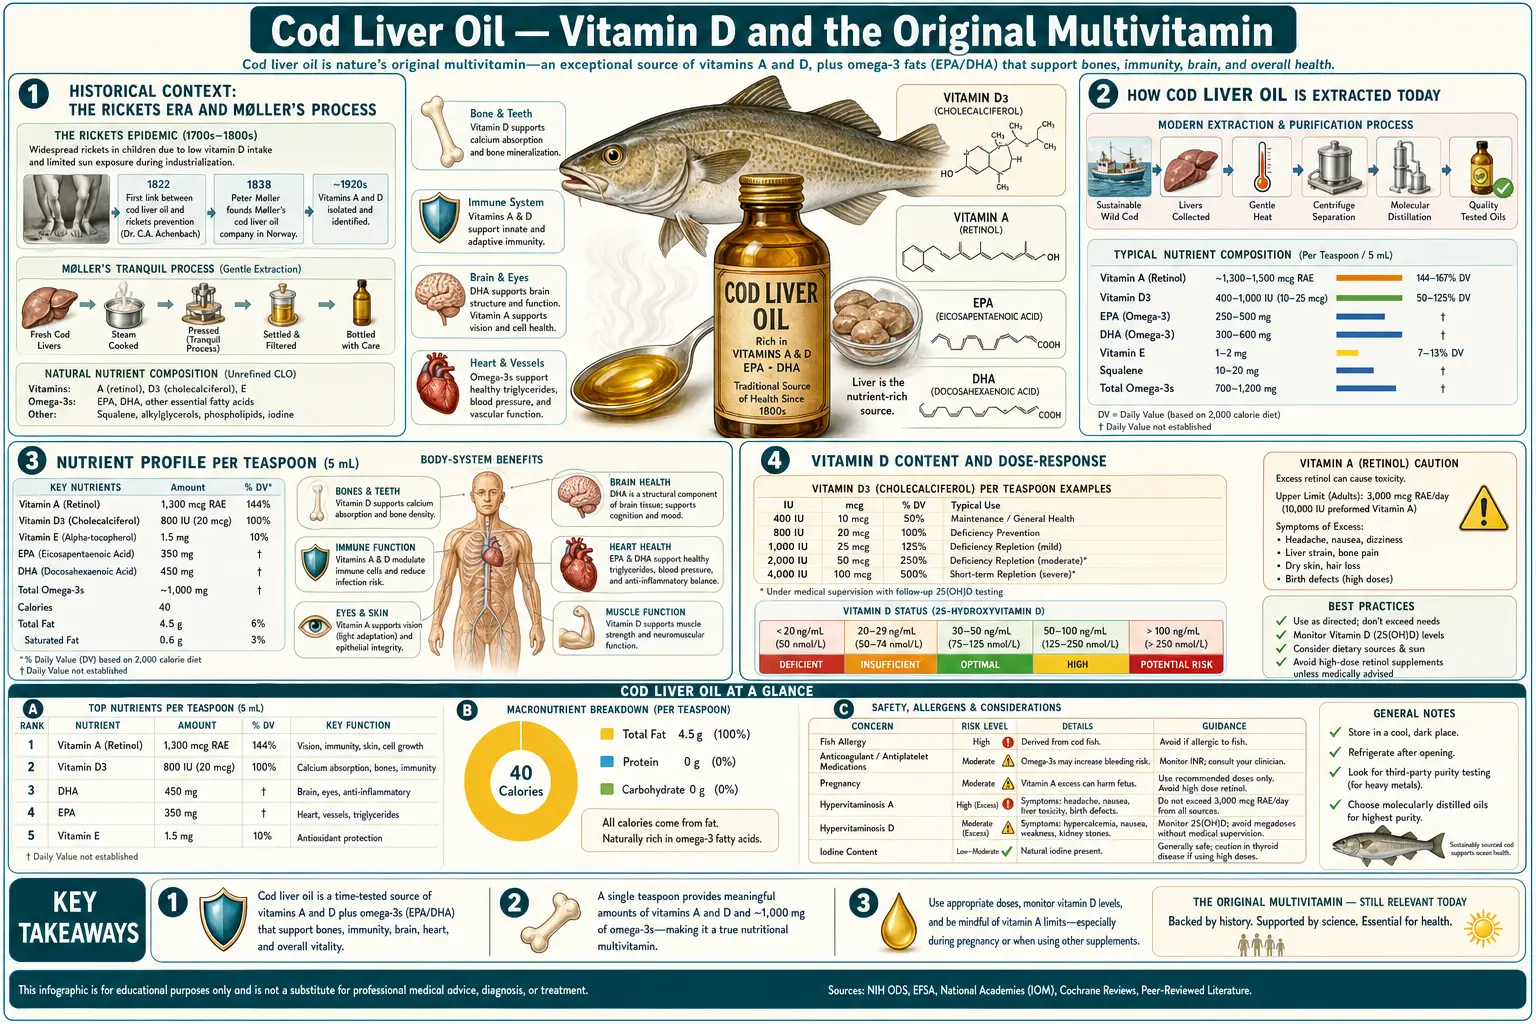
Cod liver oil was the original commercially produced vitamin supplement in human history. Norwegian pharmacist Peter Møller's 1854 industrial steam-extraction process gave the world a reproducible, palatable, and shelf-stable preparation that within a generation became the primary public-health response to childhood rickets across Northern Europe and the eastern United States. A century before the term "vitamin" existed, cod liver oil was empirically known to prevent and reverse a wasting bone disease that affected a third of urban children. The active ingredients turned out to be Vitamin D (which Adolf Windaus characterized in the 1920s, winning the 1928 Nobel Prize) and Vitamin A (which Elmer McCollum and Marguerite Davis identified at the University of Wisconsin in 1913). One teaspoon of standardized cod liver oil today delivers approximately 4,500 international units (IU) Vitamin A, 400-500 international units Vitamin D, and 800-1,000 mg combined eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA) — a remarkable nutrient profile from a single tablespoon-sized dose, and one that requires understanding the Vitamin A teratogenicity ceiling to use safely in pregnancy.
Table of Contents
- Historical Context: The Rickets Era and Møller's Process
- How Cod Liver Oil Is Extracted Today
- Nutrient Profile per Teaspoon
- Vitamin D Content and Dose-Response
- Vitamin A Content and Safety Ceiling
- Eicosapentaenoic Acid and Docosahexaenoic Acid Omega-3 Content
- Cod Liver Oil in Norway
- Stene and the Type 1 Diabetes Studies
- Respiratory Infection Prevention
- Pregnancy Considerations (the Hard Vitamin A Ceiling)
- Cod Liver Oil vs Fractionated Fish Oil
- Doses Used and Label Features
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Historical Context: The Rickets Era and Møller's Process
Rickets — the softening and bowing of children's growing bones due to inadequate mineralization — was the signature childhood disease of the Industrial Revolution. In the dense, sooty, sun-deprived urban centers of London, Glasgow, New York, and Boston, working-class children spent most of their childhoods indoors or in narrow alleys where direct sunlight rarely reached. Cutaneous Vitamin D synthesis, which depends on ultraviolet B (UVB) exposure on bare skin, fell catastrophically. By the late 19th century, autopsy series in Boston and Glasgow found rachitic skeletal changes in approximately one-third of children examined.
The empirical observation that cod liver oil could prevent and even reverse rickets predates any understanding of why it worked. Fishermen along the Norwegian and Scottish coasts had used cod liver oil as a folk remedy for centuries — partly as a general tonic, partly specifically for joint pain and what we now recognize as Vitamin D-deficient osteomalacia. In 1789, the English physician Darby Dale published the first English-language medical recommendation of cod liver oil for chronic rheumatism. By the 1820s, German clinicians were testing cod liver oil for tuberculosis (with mixed results), and by 1841 the British physician John Hughes Bennett had published a monograph documenting cod liver oil's benefit in rickets, scrofula, and chronic skin conditions.
The breakthrough that allowed cod liver oil to become a public-health intervention rather than a folk remedy was Peter Møller's 1854 industrial process in Christiania (modern Oslo). Møller, a Norwegian pharmacist, recognized that traditional cod liver oil — produced by letting livers rot in barrels and decanting the released oil — was variable, foul-tasting, and often rancid. He developed a steam-extraction process that produced a pale, less odorous oil from fresh livers. Møller's sons commercialized the process and built a global distribution network. By 1900, Møller's Tran was sold in pharmacies from Norway to North America, and "a daily spoonful of cod liver oil" had entered the public consciousness as a near-universal pediatric prescription.
The biochemistry was only worked out decades later. Vitamin A was identified by McCollum and Davis at the University of Wisconsin in 1913 (initially as "fat-soluble factor A"). Vitamin D was distinguished from Vitamin A by McCollum's laboratory in 1922 and characterized chemically by Windaus in Germany (Nobel Prize 1928). By the time the cause of cod liver oil's effectiveness was understood, the supplement had already prevented millions of cases of rickets worldwide.
How Cod Liver Oil Is Extracted Today
Modern cod liver oil production follows a more refined version of Møller's process. Fresh cod livers from commercial fishing operations are transferred under refrigeration to a processing facility within 24-48 hours of catch. The livers are gently steam-heated to render the oil, which is then separated by centrifugation. The crude oil undergoes:
- Degumming — removal of phospholipids and water-soluble impurities
- Alkali refining — neutralization of free fatty acids
- Bleaching — adsorption of pigments and oxidation products onto bleaching earth (clay)
- Winterization — removal of saturated fatty acids that would crystallize at refrigerator temperature
- Molecular distillation (some producers only) — removal of dioxins, PCBs, mercury, and other contaminants under high vacuum at low temperature
- Deodorization — steam stripping under vacuum to remove residual odors
- Standardization — addition or reduction of natural Vitamin A and D to hit label specifications
Two important consequences follow from this processing. First, modern refined cod liver oil is essentially odorless and palatable — a long way from the rancid, fishy preparations of Møller's era. Second, the heavy processing removes naturally occurring antioxidants (Vitamin E, mixed tocopherols), so commercial products typically add Vitamin E back to prevent rancidity during shelf storage. Some artisanal "fermented" cod liver oil products are sold as an alternative, but these have come under scrutiny for inconsistent Vitamin A and D content and for high levels of oxidation products.
The major commercial producers today are Norwegian and Icelandic. Cod liver oil from these northern producers typically uses Atlantic cod (Gadus morhua) caught in the Norwegian Sea and Barents Sea. Pacific cod liver oil (using Gadus macrocephalus from Alaskan waters) is also commercially available but represents a smaller market share.
Nutrient Profile per Teaspoon
A 5 mL (1 US teaspoon, approximately 4.5 g) serving of standardized cod liver oil typically provides:
- Vitamin A (as retinol): 4,000-4,500 international units (1,200-1,350 mcg RAE)
- Vitamin D (as cholecalciferol, D3): 400-500 international units (10-12.5 mcg)
- eicosapentaenoic acid (EPA): 350-500 mg
- docosahexaenoic acid (DHA): 400-600 mg
- Total long-chain omega-3: 800-1,100 mg
- Vitamin E (added): 5-15 international units
- Energy: 41 kcal (essentially all from fat)
The exact values vary by brand and batch. Norwegian and Icelandic standardized products generally hit the higher end of the ranges above. Some brands sell "high-potency" cod liver oil with elevated Vitamin D (1,000 international units per teaspoon) achieved by partial fortification with added cholecalciferol.
The 4:1 to 9:1 ratio of Vitamin A to Vitamin D in natural cod liver oil is a historical accident of cod biology — cod livers concentrate both vitamins from the cod's diet of zooplankton and small fish that produce or accumulate provitamin sterols. This ratio is biologically reasonable (Vitamin A and D synergize at the RXR-containing retinoid X receptor heterodimer and at the bone mineralization site), but it limits the practical Vitamin D dose that can be achieved without exceeding Vitamin A safety thresholds. A 1-tablespoon daily dose (3 teaspoons) of standard cod liver oil delivers 1,200-1,500 international units Vitamin D — useful for general health support — but also 12,000-13,500 international units Vitamin A, which exceeds the adult upper limit for preformed vitamin A (10,000 international units, or 3,000 mcg RAE, per day) — the same limit applies in pregnancy.
Vitamin D Content and Dose-Response
The Vitamin D content of cod liver oil is what made the supplement historically transformative. In sun-deprived populations — northern latitudes, urban industrial workers, women in modest dress, dark-skinned individuals in northern climates — cutaneous synthesis cannot keep up with demand. Dietary Vitamin D from oily fish, egg yolks, and fortified dairy is insufficient to compensate. Cod liver oil at 1 teaspoon daily provides 400-500 international units, which historically pushed children from severe deficiency (rickets-causing) into the marginally adequate range that prevented skeletal disease.
Modern Vitamin D research has expanded the relevant outcomes well beyond bone health. Adequate Vitamin D status (serum 25-hydroxyvitamin D above 30 ng/mL) is associated with reduced risk of:
- Respiratory tract infections (upper and lower)
- Type 1 diabetes in childhood (the Stene studies discussed below)
- Multiple sclerosis (gradient-of-latitude epidemiology, supplementation prevention trials underway)
- Several autoimmune conditions (rheumatoid arthritis, Hashimoto's thyroiditis, systemic lupus)
- Falls and fractures in older adults
- All-cause mortality (meta-analyses of observational studies and supplementation trials)
For most adults aiming for serum 25(OH)D above 30 ng/mL, the supplemental dose required is 1,000-2,000 international units per day — well above what a single teaspoon of cod liver oil provides. A single teaspoon of cod liver oil on its own therefore falls short of the modern target ranges. It contributes meaningfully — 400-500 international units per teaspoon is a real dose — but Vitamin D3 as a stand-alone product (1,000-5,000 international units softgels) reaches target serum levels more efficiently and does not bring Vitamin A along.
The exception is patients who actually need both Vitamin A and Vitamin D — for example, individuals with documented fat malabsorption (cystic fibrosis, post-bariatric surgery, advanced Crohn's), who are typically deficient in both fat-soluble vitamins simultaneously. For them, cod liver oil at 1-2 teaspoons daily supplies both vitamins at once.
For Vitamin D fundamentals and target serum levels, see the dedicated Vitamin D3 page.
Vitamin A Content and Safety Ceiling
The Vitamin A content of cod liver oil is the single most important consideration for safe dosing. Preformed retinol — the form found in animal products, including cod liver oil — is potently bioactive and accumulates in liver storage with sustained intake above the homeostatic capacity for regulation. The Tolerable Upper Intake Level (UL) for adults is 3,000 mcg RAE/day (10,000 international units), set by the Institute of Medicine based on hepatotoxicity, bone loss, and teratogenicity data.
A typical 1-teaspoon cod liver oil dose delivers approximately 1,200-1,350 mcg RAE Vitamin A. A 1-tablespoon dose delivers 3,600-4,000 mcg RAE, which exceeds the adult Tolerable Upper Intake Level. For someone consuming a standard cod liver oil product:
- 1 teaspoon/day = 40-45% of the adult Tolerable Upper Intake Level — safe long-term
- 2 teaspoons/day = 80-90% of the adult Tolerable Upper Intake Level — safe but close to ceiling
- 1 tablespoon/day = 120-135% of the adult Tolerable Upper Intake Level — above the limit for long-term intake
The clinical concern at chronic intake above the Tolerable Upper Intake Level is gradual hepatotoxicity (elevated liver enzymes, fibrosis in extreme cases) and skeletal effects (reduced bone mineral density, increased fracture risk in older adults). Acute hypervitaminosis A from a single megadose (typically >500,000 international units at once) produces a different syndrome: headache, increased intracranial pressure, nausea, vomiting, peeling skin. Polar bear liver, which contains approximately 1,000,000 international units Vitamin A per 100 grams, has historically caused acute hypervitaminosis A in Arctic explorers who consumed it — a single ounce can exceed the lethal dose.
For pregnant women aged 19 and over, the Tolerable Upper Intake Level is the same 3,000 mcg RAE (10,000 international units) of preformed Vitamin A per day set for all adults, and Vitamin A is a known teratogen at sustained intakes above approximately that level. The mechanism is retinoic acid signaling disruption during embryonic development, producing characteristic malformations of the craniofacial region, heart, and central nervous system (the so-called "retinoic acid embryopathy" pattern). Norwegian public-health guidance specifically warns against cod liver oil during pregnancy at doses above 1 teaspoon per day. UK and US guidance is more conservative: many prenatal vitamins deliberately use beta-carotene instead of preformed retinol to avoid the teratogenicity risk.
For the underlying mechanism, see the Beta-Carotene vs Preformed Retinol deep-dive on the Vitamin A Benefits hub.
Eicosapentaenoic Acid and Docosahexaenoic Acid Omega-3 Content
Cod liver oil delivers long-chain omega-3 fatty acids (eicosapentaenoic acid and docosahexaenoic acid) at approximately 800-1,100 mg per teaspoon — a meaningful dose that approaches the 1,000 mg per day target recommended by the American Heart Association for individuals with established coronary heart disease.
The omega-3 content is what differentiates cod liver oil from the historical 19th-century product (which was used primarily for its fat-soluble vitamins) and from straight Vitamin A and D supplements today (which lack the omega-3s entirely). Eicosapentaenoic acid and docosahexaenoic acid have well-established effects on:
- Triglyceride reduction — consistent 15-25% reduction in serum triglycerides at 2-4 g daily eicosapentaenoic acid+docosahexaenoic acid. Mechanism involves reduced hepatic very-low-density lipoprotein (VLDL) secretion.
- Inflammation — eicosapentaenoic acid and docosahexaenoic acid are precursors to specialized pro-resolving mediators (resolvins, protectins, maresins) that actively resolve inflammation. Cellular incorporation displaces arachidonic acid from membrane phospholipids, reducing pro-inflammatory eicosanoid synthesis.
- Cardiovascular outcomes — the REDUCE-IT trial (icosapent ethyl, pure eicosapentaenoic acid, 2 g twice daily) showed a 25% reduction in major adverse cardiovascular events in high-risk patients with persistent hypertriglyceridemia despite statin therapy. The STRENGTH trial (mixed eicosapentaenoic acid/docosahexaenoic acid) did not replicate this, suggesting eicosapentaenoic acid specifically may be the active component.
- Brain function — docosahexaenoic acid is the dominant fatty acid in neuronal membrane phospholipids; adequate docosahexaenoic acid supports membrane fluidity and synaptic function. Maternal docosahexaenoic acid intake during pregnancy correlates with offspring cognitive development.
- Eye function — docosahexaenoic acid is concentrated in retinal photoreceptor outer segments. Adequate docosahexaenoic acid status is associated with reduced age-related macular degeneration risk.
For a deeper treatment of omega-3 biology, dosing, and clinical applications, see the Omega-3 Fatty Acids page. The practical implication for cod liver oil users is that the omega-3 content delivered — 800-1,100 mg per teaspoon — provides meaningful cardiovascular and anti-inflammatory benefit at a single teaspoon daily, and the marginal added benefit of higher doses comes at the cost of approaching the Vitamin A ceiling.
Cod Liver Oil in Norway
Norway has a long history of cod liver oil use. The country lies at high latitude with limited winter sunlight (Bergen is at 60°N), the cod fishery is an economic foundation of its coast, and the population has historically high cod liver oil consumption that gradually declined over the 20th century as other supplements became available.
Norwegian research on cod liver oil includes Brustad and colleagues' work on vitamin D status in relation to diet and sunlight in women living at 65-71°N, and the type 1 diabetes case-control studies of Lars Stene and the Norwegian Childhood Diabetes Study Group, which found lower risk in children who took cod liver oil during their first year of life (next section).
Stene and the Type 1 Diabetes Studies
One of the more striking observational findings in cod liver oil research came from Lars Stene and the Norwegian Childhood Diabetes Study Group, published in the American Journal of Clinical Nutrition in 2003 — a nationwide case-control study of 545 children with childhood-onset type 1 diabetes and 1,668 population controls. The study examined cod liver oil use during the first year of life and during pregnancy in relation to subsequent type 1 diabetes diagnosis in the child.
The key findings:
- First year of life: children who themselves took cod liver oil during their first year had a significantly lower risk of type 1 diabetes (adjusted odds ratio 0.74; 95% confidence interval 0.56-0.99).
- Pregnancy: mothers' use of cod liver oil or other vitamin D supplements during pregnancy was not associated with type 1 diabetes in the child in the 2003 study. An earlier, smaller case-control study by Stene and colleagues in Vest-Agder county (Diabetologia, 2000; 85 children with diabetes, 1,071 controls) had found lower risk in children whose mothers took cod liver oil during pregnancy (unadjusted odds ratio 0.30).
- The effect was specific to cod liver oil — other vitamin D supplements taken during the first year of life were not associated with type 1 diabetes in the 2003 study.
The 2003 authors suggested cod liver oil may act through the anti-inflammatory effects of its long-chain omega-3 fatty acids; the 2000 authors suggested vitamin D, the omega-3 fatty acids, or both. Type 1 diabetes is an autoimmune destruction of pancreatic beta cells, and Vitamin D modulates T-cell function and regulatory T-cell expansion in ways that could plausibly prevent or delay the autoimmune cascade. The omega-3 contribution likely also matters — eicosapentaenoic acid and docosahexaenoic acid influence beta-cell membrane composition and reduce islet inflammation.
The findings have not been tested in a randomized controlled trial — the long lead time (15+ years to type 1 diabetes onset) and the rarity of the outcome make such a trial logistically extremely difficult. The observational findings remain the strongest evidence on the topic. Norwegian pediatric guidance now recommends cod liver oil supplementation in pregnancy and early childhood at least in part on the basis of this finding.
Respiratory Infection Prevention
Cod liver oil's effect on respiratory tract infections in children has been studied for over a century, with consistently positive but modest findings. The most cited modern trial is Linday et al. (2004): two pediatric offices in upper Manhattan were randomized, one to supplementation and one to a medical-records control, with 94 inner-city Latino children aged 6 months to 5 years. Children at the supplementation site took 1 teaspoon of lemon-flavored cod liver oil plus half a tablet of a children's multivitamin-mineral with selenium each day; their number of upper respiratory tract pediatric visits decreased over time (p = .042), while the control site showed no change. The authors concluded the approach deserves further research.
The mechanism plausibly involves all three active components:
- Vitamin A maintains mucosal epithelial integrity of the respiratory tract, supports mucus production and ciliary function, and stimulates secretory immunoglobulin A (IgA) production — see the Vitamin A Immune Function deep-dive for the full mechanism.
- Vitamin D stimulates cathelicidin antimicrobial peptide production by respiratory epithelium and modulates adaptive immunity (T-cell function, regulatory T-cell expansion).
- Eicosapentaenoic acid and docosahexaenoic acid reduce excessive pro-inflammatory cytokine release during acute viral infection, potentially reducing the severity (though not the incidence) of infection-associated symptoms.
Winter is when both Vitamin D status and respiratory infection burden are at their seasonal extremes, which is when cod liver oil has traditionally been given to children. The supplement is not a replacement for standard hygiene measures, vaccinations, and management of underlying conditions (allergic rhinitis, asthma, immunodeficiency).
For adults with frequent winter respiratory infections, the evidence is less strong but suggestive. Cod liver oil at 1 teaspoon daily, particularly during October through March in northern latitudes, is the traditional pattern. A serum 25(OH)D test shows whether Vitamin D status is adequate; levels persistently below 30 ng/mL despite cod liver oil mean the teaspoon is not supplying enough Vitamin D, and additional Vitamin D3 is the usual addition.
Pregnancy Considerations (the Hard Vitamin A Ceiling)
Cod liver oil in pregnancy is a topic with genuinely conflicting clinical guidance across countries:
- Norwegian guidance actively recommends 1 teaspoon daily cod liver oil during pregnancy for combined Vitamin D, docosahexaenoic acid, and Vitamin A support. This is informed by the favorable Helland trial showing improved offspring cognitive outcomes at age 4 in children whose mothers took 10 mL daily cod liver oil from 18 weeks gestation through 3 months postpartum.
- UK guidance (NHS) explicitly recommends against cod liver oil in pregnancy due to Vitamin A teratogenicity concerns. Pregnant women in the UK are advised to take a pregnancy-specific multivitamin with no Vitamin A and to supplement with separate Vitamin D and omega-3 products.
- US guidance (ACOG, AAP) is silent on cod liver oil specifically but recommends limiting preformed Vitamin A intake to under 3,000 mcg RAE (10,000 international units) per day during pregnancy. A standard 1-teaspoon cod liver oil dose at 4,500 international units Vitamin A is within this limit; a 1-tablespoon dose is not.
The empirical risk data shows clear teratogenicity above approximately 10,000 international units/day preformed Vitamin A in pregnancy. Below that threshold, the risk is unclear — observational studies have not found increased malformation risk at intakes of 5,000-8,000 international units/day, but the absence of randomized evidence below the documented teratogenicity threshold leaves uncertainty. The precautions described for pregnancy are:
- A cod liver oil product with clearly labeled Vitamin A content per serving
- No more than 1 teaspoon per day during pregnancy (Norwegian practice; typically delivering 4,000-4,500 international units Vitamin A — well under the 10,000 international units threshold)
- Not combining cod liver oil with a prenatal multivitamin that contains Vitamin A — the cumulative dose can approach the ceiling
- No additional high-Vitamin-A foods (beef liver, polar bear liver, fortified foods) on days when cod liver oil is taken
A fractionated fish oil (eicosapentaenoic acid + docosahexaenoic acid, no Vitamin A) plus a separate Vitamin D3 supplement supplies the docosahexaenoic acid and Vitamin D without the Vitamin A — the separate-products approach UK guidance describes for pregnancy.
Cod Liver Oil vs Fractionated Fish Oil
Modern fractionated fish oil products (eicosapentaenoic acid + docosahexaenoic acid, no fat-soluble vitamins) have largely displaced cod liver oil in the supplement marketplace because they allow higher omega-3 doses without Vitamin A loading. Key differences:
- Cod liver oil (per teaspoon, 5 mL): 4,000-4,500 international units Vitamin A, 400-500 international units Vitamin D, 800-1,100 mg eicosapentaenoic acid+docosahexaenoic acid, 41 kcal
- Fractionated fish oil (per 1 g softgel): 0 international units Vitamin A, 0 international units Vitamin D, 300-1,000 mg eicosapentaenoic acid+docosahexaenoic acid depending on concentration, 9 kcal
- High-concentration fish oil concentrates: some products deliver 800+ mg eicosapentaenoic acid + 600+ mg docosahexaenoic acid per 1 g softgel, allowing therapeutic doses (2-4 g/day) without bulk
- Prescription icosapent ethyl (purified eicosapentaenoic acid): 1 g per softgel, pure eicosapentaenoic acid, prescription product with cardiovascular outcomes data (REDUCE-IT trial)
How the two are usually matched to situations:
- Cod liver oil fits: wanting combined Vitamin A and D and omega-3 in one product; documented fat malabsorption, where both fat-soluble vitamins are needed; low intake of high-Vitamin-A foods (no liver, no organ meats); high-latitude populations with cultural use of cod liver oil; children with recurrent respiratory infections.
- Fractionated fish oil fits: higher omega-3 doses (2+ g daily); pregnancy, where Vitamin A loading is the concern; people who already eat organ meats or take a multivitamin with Vitamin A; hypertriglyceridemia needing a therapeutic eicosapentaenoic acid+docosahexaenoic acid dose; allergy or sensitivity to cod specifically.
Doses Used and Label Features
Adult cod liver oil amounts described for different goals:
- General nutritional support: 1 teaspoon (5 mL) daily, usually taken with a meal containing fat for absorption
- Vitamin D repletion in deficient adults: 1-2 teaspoons daily for 8-12 weeks, with serum 25(OH)D checked; a higher-dose Vitamin D3-only supplement is the usual next step when 1-2 teaspoons of cod liver oil is insufficient
- Cardiovascular omega-3 support: 1 teaspoon daily provides approximately 1,000 mg eicosapentaenoic acid+docosahexaenoic acid; therapeutic doses (2-4 g daily) are usually given as fractionated fish oil to avoid Vitamin A overload
- Pregnancy: 1 teaspoon daily maximum (Norwegian practice); UK guidance recommends avoiding cod liver oil entirely in pregnancy
- Pediatric general use: Norwegian guidance is 5 mL daily for children over 6 months
Label and product features:
- Source transparency — whether the label identifies the source (Atlantic vs Pacific cod) and the fishery
- Molecular distillation — molecularly distilled products have mercury, dioxins, and PCBs removed to non-detectable levels. Independent third-party testing programmes check purity claims
- Specified Vitamin A and D content — precise international units values per serving on the label, rather than just "naturally occurring vitamins"
- Vitamin E added — many producers add mixed tocopherols (5-15 international units per serving) to prevent oxidation; a product with no antioxidant listed may be prone to rancidity
- Liquid vs softgel — liquid allows flexible dosing and is often less expensive per serving; softgels are more convenient and have a longer shelf life once opened
- Flavored vs unflavored — lemon, orange, and mint flavors mask the residual fish taste; some users find unflavored more palatable in the long term
- Storage — once opened, cod liver oil keeps best refrigerated and used within 3-4 months; oxidized cod liver oil (rancid smell, discolored) has spoiled
Molecularly distilled products typically cost $0.15-0.30 per teaspoon dose and generic store-brand cod liver oil $0.05-0.10 per dose. Contaminant load matters most in pregnancy and for children.
Cautions and Drug Interactions
- Pregnancy Vitamin A ceiling — the most consequential caution, repeated above. Norwegian practice sets 1 teaspoon daily as the maximum in pregnancy, and UK guidance recommends against cod liver oil entirely during pregnancy.
- Anticoagulant interaction — the eicosapentaenoic acid and docosahexaenoic acid content of cod liver oil has mild antiplatelet effects. In people taking warfarin, apixaban, rivaroxaban, dabigatran, or daily aspirin, this effect adds to the bleeding risk the medicine already carries. The risk is modest at 1 teaspoon daily but increases at higher doses.
- Vitamin K antagonism — high doses of Vitamin A and D can theoretically interfere with Vitamin K-dependent processes, including warfarin metabolism. More frequent international normalized ratio (INR) checks are the usual practice when warfarin patients start cod liver oil.
- Chronic high-dose Vitamin A toxicity — sustained intake above 3,000 mcg RAE/day produces gradual hepatotoxicity (elevated aspartate aminotransferase (AST)/alanine aminotransferase (ALT), fibrosis), alopecia, dry skin, increased intracranial pressure, and bone loss. A 1-tablespoon-daily cod liver oil regimen exceeds this threshold.
- Surgery — because of the antiplatelet effect of omega-3s, cod liver oil is typically stopped 1-2 weeks before elective surgery to reduce bleeding risk.
- Allergy — rare cases of fish allergy can extend to cod liver oil. Algal oil is a non-fish source of docosahexaenoic acid.
- Persistent organic pollutants — unrefined or poorly produced cod liver oil can contain dioxins, PCBs, and mercury. Molecular distillation removes these, and third-party purity certification documents it; this matters most in pregnancy and for children.
- Vitamin D toxicity — the Vitamin D content of cod liver oil is moderate, but a person already taking high-dose Vitamin D3 supplementation adds the cod liver oil amount to that total, which counts toward the Vitamin D Tolerable Upper Intake Level of 4,000 international units/day for adults.
Key Research Papers
- Stene LC, Joner G, Norwegian Childhood Diabetes Study Group (2003). Use of cod liver oil during the first year of life is associated with lower risk of childhood-onset type 1 diabetes: a large, population-based, case-control study. American Journal of Clinical Nutrition. — PubMed PMID: 14668274
- Stene LC, Ulriksen J, Magnus P, Joner G (2000). Use of cod liver oil during pregnancy associated with lower risk of Type I diabetes in the offspring. Diabetologia. — PubMed PMID: 11043854
- Helland IB, Smith L, Saarem K, Saugstad OD, Drevon CA (2003). Maternal supplementation with very-long-chain n-3 fatty acids during pregnancy and lactation augments children's IQ at 4 years of age. Pediatrics. — PubMed PMID: 12509593
- Linday LA, Shindledecker RD, Tapia-Mendoza J, Dolitsky JN (2004). Effect of daily cod liver oil and a multivitamin-mineral supplement with selenium on upper respiratory tract pediatric visits by young, inner-city, Latino children: randomized pediatric sites. Annals of Otology, Rhinology, and Laryngology. — PubMed PMID: 15562899
- Rajakumar K (2003). Vitamin D, cod-liver oil, sunlight, and rickets: a historical perspective. Pediatrics. — PubMed PMID: 12897318
- Brustad M, Alsaker E, Engelsen O, Aksnes L, Lund E (2004). Vitamin D status of middle-aged women at 65-71 degrees N in relation to dietary intake and exposure to ultraviolet radiation. Public Health Nutrition. — PubMed PMID: 15003141
- Bhatt DL et al. (2019). Cardiovascular Risk Reduction with Icosapent Ethyl for Hypertriglyceridemia (REDUCE-IT). NEJM. — PubMed PMID: 30415628
- Nicholls SJ et al. (2020). Effect of high-dose omega-3 fatty acids vs corn oil on major adverse cardiovascular events in patients at high cardiovascular risk (STRENGTH trial). JAMA. — PubMed PMID: 33190147
- Holick MF (2007). Vitamin D deficiency. NEJM. — PubMed PMID: 17634462
- Martineau AR et al. (2017). Vitamin D supplementation to prevent acute respiratory tract infections: systematic review and meta-analysis of individual participant data. BMJ. — PubMed PMID: 28202713
- Lammer EJ et al. (1985). Retinoic acid embryopathy. NEJM. — PubMed PMID: 3162101
- Brustad M, Edvardsen K, Wilsgaard T, Engelsen O, Aksnes L, Lund E (2007). Seasonality of UV-radiation and vitamin D status at 69 degrees north. Photochemical & Photobiological Sciences. — PubMed PMID: 17668121
PubMed Topic Searches
Connections
- All Food
- Cod Hub
- Cod Benefits Deep Dive
- Cod Lean Protein Profile
- Cod for Iodine & Thyroid
- Mercury vs Other Fish
- Vitamin D3
- Vitamin A
- Vitamin A Benefits Deep Dive
- Beta-Carotene vs Preformed
- Vitamin A for Immune Function
- Vitamin K2
- Omega-3 Fatty Acids
- Salmon
- Herring
- Sardines
- Organ Meats (Liver as Vitamin A Source)
- Cardiovascular Disease
- Type 1 Diabetes
- Pneumonia
- Anti-Inflammatory Diet
- Cod Liver — the organ this oil is pressed from, and its full nutrient profile.
- Fat-Soluble Activators: Vitamins A, D and K2
- History
- Nutrients