⚠ Evidence warning: Clinical trials or other evidence do not support the claim that kimchi suits people with food allergies and atopic conditions. This page keeps it as a report of what people, websites or other media say.
Kimchi Sodium and Vegetable Trade-off
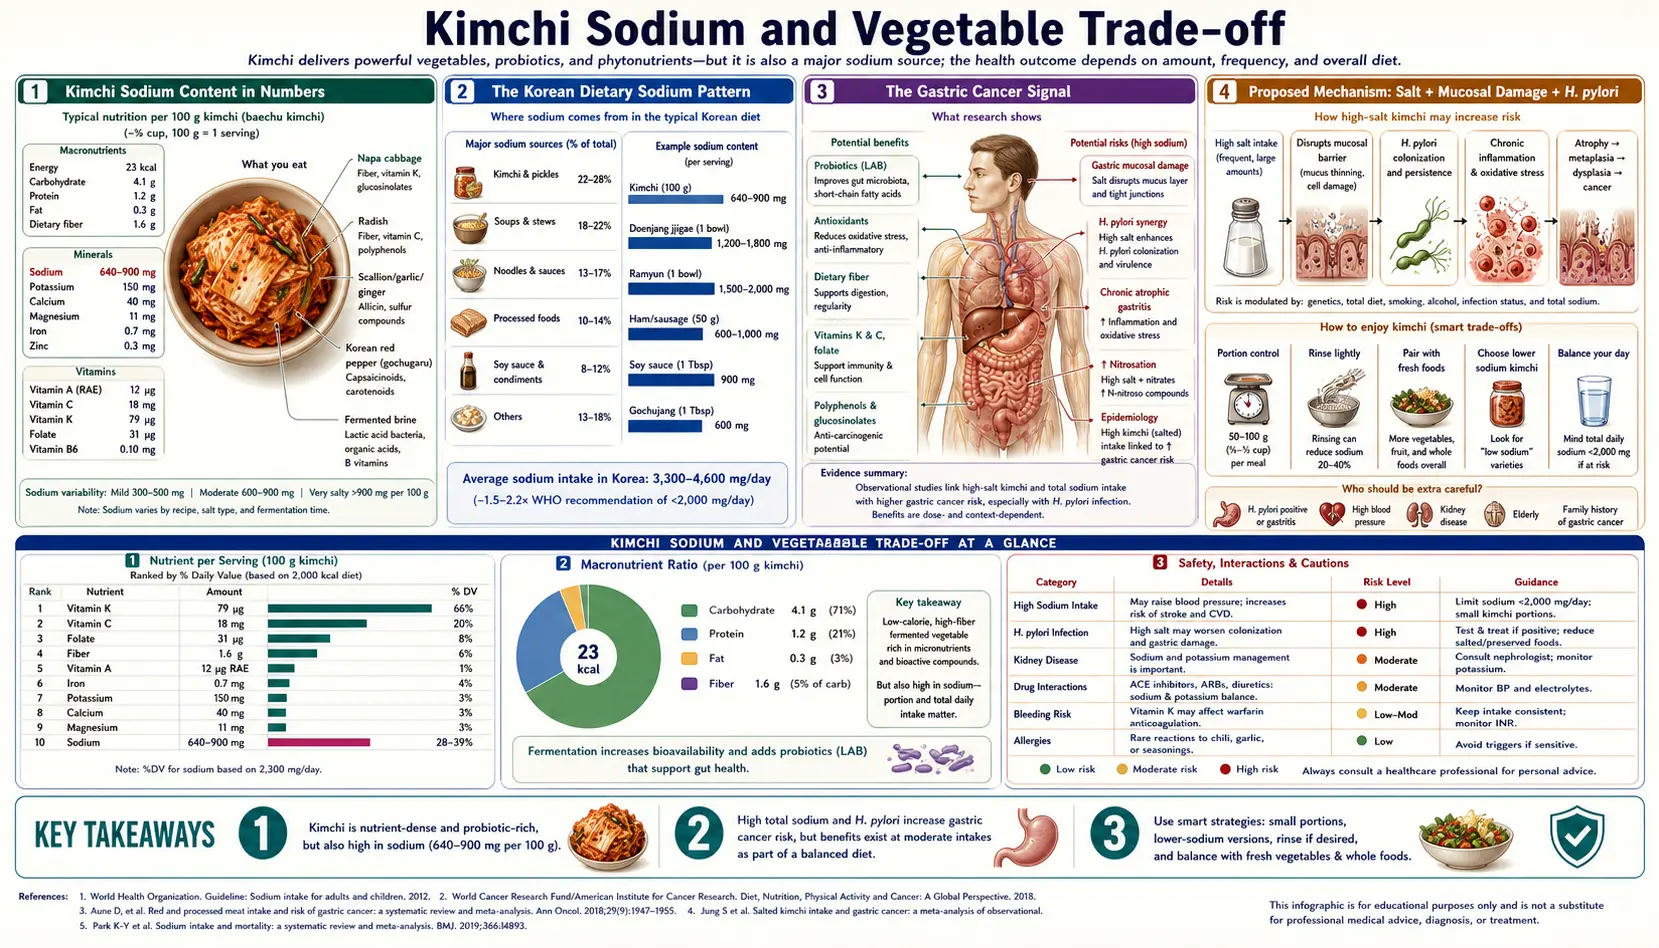
The honest scientific summary of kimchi is that it is a high-sodium fermented vegetable with documented probiotic and chemopreventive benefits, eaten in a country with one of the highest gastric cancer incidence rates in the developed world and one of the highest national sodium intakes. None of these statements contradict each other — they coexist, and the practical answer to "is kimchi good for me" depends on which framework you weight and what the rest of your diet looks like. This page walks through the Korean cohort epidemiology, the proposed sodium-and-gastric-cancer mechanism, the cardiovascular trade-offs, the lower-sodium home and commercial variants, and how to think about kimchi in a Western dietary context that already has its own sodium pressures from processed food.
Table of Contents
- Kimchi Sodium Content in Numbers
- The Korean Dietary Sodium Pattern
- The Gastric Cancer Signal
- Proposed Mechanism: Salt + Mucosal Damage + H. pylori
- Cardiovascular Trade-offs
- Confounding and the Whole-Diet Question
- Low-Sodium Kimchi Variants
- Home-Fermentation Guidance
- Who the Research Raises Concerns For
- Bottom Line
- Key Research Papers
- Connections
- Featured Videos
Kimchi Sodium Content in Numbers
The sodium content of kimchi is much higher than most consumers realize. Reference values from U.S. Department of Agriculture (USDA), Korean Food Composition Database, and published analyses:
- Commercial baechu kimchi (napa cabbage) — 600-1,200 mg sodium per 100 g (1.5-3% salt by weight)
- Traditional kimjang home kimchi — often higher, 800-1,500 mg sodium per 100 g, reflecting the historical preservation requirement of higher salt for winter-long storage
- Kkakdugi (radish cube kimchi) — similar range, 600-1,000 mg per 100 g
- Dongchimi (water kimchi) — lower in the cabbage portion (300-500 mg per 100 g), but the brine is consumed and contains the bulk of the sodium
- Modern "low-sodium" commercial kimchi — reported at 300-500 mg per 100 g. By the same arithmetic as the first line above, that is under about 1.25% salt, which is below the roughly 1.5% that fermenters treat as the practical limit for fermentation safety (below ~1.5% salt the fermentation outcome becomes less predictable and food-safety risk rises)
The USDA FoodData Central record for kimchi ("Cabbage, kimchi", FDC 170392) lists 498 mg sodium and 151 mg potassium per 100 g, below the commercial range above, so products and data sources differ widely.
For context, the American Heart Association recommended limit for total daily sodium intake is 1,500-2,300 mg per day. A single 100 g serving of commercial kimchi delivers 30-80% of that entire daily limit. A traditional Korean meal pattern of 100 g kimchi per meal, three meals per day, exceeds the entire American Heart Association (AHA) daily sodium recommendation from kimchi alone, before any other food.
This is not a small effect. Kimchi is genuinely a high-sodium food. The question is how that sodium intake interacts with the rest of the diet and with individual health risk factors.
The Korean Dietary Sodium Pattern
Korea has one of the highest national average sodium intakes in the developed world. KNHANES (Korean National Health and Nutrition Examination Survey) data over the past two decades have documented average sodium intake around 4,000-5,000 mg per day — roughly double the World Health Organization (WHO) recommendation and well above even the American Heart Association upper-bound. The Korean government has run sustained national campaigns to reduce sodium intake, with measurable success: from 2010 to 2019, mean intake fell by 32.9%, from 4,831 to 3,243 mg/day. The decline has plateaued since 2017, and intake remains above the World Health Organization recommendation.
The major dietary contributors to Korean sodium intake, in approximate descending order. In the 2013-2017 survey, mean intake was 3,477-3,890 mg/day, and the top three dish groups were noodles and dumplings, kimchi, and soups. Counted as ingredients rather than dishes, seasonings were the largest food group (1,598-1,871 mg/day).
- Noodles and dumplings — 537-573 mg/day in the 2013-2017 survey, with instant ramyeon the main source in teenagers and people in their twenties
- Kimchi — 487-540 mg/day in the same survey; described as contributing roughly 15-25% of total daily sodium in traditional patterns
- Soups and stews (jjigae, guk) — salted broths and stews are eaten at most meals; 368-429 mg/day for soups in the same survey
- Salt-fermented seafood (jeotgal) — concentrated salty condiments
- Fermented soybean pastes (doenjang, gochujang) — used in soups, marinades, sauces
- Soy sauce (ganjang) — primary salt-delivery condiment in many dishes
- Salted side dishes (banchan) — the array of small dishes accompanying rice; many are salted vegetables, dried fish, or pickled items
Critically, the Korean sodium signal is not from one food. Reducing only kimchi while leaving the other contributors unchanged would have a modest effect on total intake. The successful Korean public-health response has been broader — reformulating instant noodles, reducing soup and stew sodium, reformulating commercial kimchi, and educating consumers about hidden sodium in convenience foods.
Koreans also eat less kimchi than they did. National survey data show intake fell in both men and women from 2010 to 2024, and the share of adults eating none on the survey day rose from 11.7% to 22.7%.
The Gastric Cancer Signal
Korea has historically had one of the highest gastric (stomach) cancer incidence rates in the world, peaking at approximately 80 cases per 100,000 population per year in the 1990s. In 1999-2010, age-standardized incidence fell only slightly and not significantly (0.2% a year in men, 0.4% in women), while deaths fell much faster (4.3% and 5.9% a year). Korea remains in the top group globally. The Korean government launched a national gastric cancer screening program in 1999, offering biennial upper endoscopy or upper gastrointestinal X-ray series from age 40. Compared with people never screened, the odds of dying from gastric cancer were 0.79 overall, 0.53 with endoscopy and 0.98 (no association) with the X-ray series.
Findings on kimchi itself are not consistent; a 2026 commentary says epidemiologic findings on kimchi and gastric cancer "remain inconsistent", likely because of differences in sodium content, fermentation practices and overall diet. Salt as a whole is clearer: a pooled analysis of 7 prospective studies found high salt intake linked to a 1.68 times higher risk than low intake (95% confidence interval 1.17-2.41). The signal includes:
- High kimchi intake — no pooled figure for kimchi alone was found. Korean case-control studies point in both directions: one of 421 patients and 632 controls linked kimchi to higher risk, a smaller one linked high kimchi intake to early gastric cancer, and a third found lower risk with cabbage kimchi and higher risk with radish and water kimchi
- High salt-fermented seafood (jeotgal) intake — similar pattern; pooled risk for salted fish was 1.17 times higher, highest against lowest intake, just short of statistical significance (95% confidence interval 0.99-1.38)
- High soup / stew intake — sodium delivery vehicle
- Pickled vegetables generally — same pattern in Japan with takuan, umeboshi, salt-fermented Chinese vegetables in China. A 2020 pooled analysis that included two large Korean cohorts linked each extra 40 g/day of pickled vegetables with a 15% higher risk (relative risk 1.15, 95% confidence interval 1.07-1.23)
For scale, one estimate attributes 16.0% of Korean gastric cancer cases in 2018 to high intake of salted vegetables and 2.4% to salted fish.
The signal is not unique to Korean kimchi — it appears in similar form for traditional high-salt fermented foods across northeast Asia, central Asia, and parts of Europe (including the historical association between salt-pickled foods and gastric cancer in pre-refrigeration northern European populations). The pattern strongly implicates dietary sodium as the relevant exposure rather than any specific Korean ingredient.
Proposed Mechanism: Salt + Mucosal Damage + H. pylori
The mechanistic story behind sodium and gastric cancer involves an interaction with Helicobacter pylori infection — a bacterium that colonizes the stomach lining. In a large Korean health-examination series, the share of adults testing positive on antibody tests fell from 66.9% in 1998 to 59.6% in 2005, 54.4% in 2011 and 43.9% in 2016-17, while the share reporting eradication therapy rose to 23.5%. The proposed pathway:
- High dietary sodium damages the gastric mucosal barrier — the gastric mucus-bicarbonate layer is normally a physical and chemical barrier protecting epithelial cells from the acidic luminal environment. Hyperosmolar salt exposure damages this barrier, exposing epithelial cells to acid and to luminal bacteria.
- Mucosal damage facilitates H. pylori colonization and effects — H. pylori already established in the gastric niche can more easily damage epithelial cells when the mucosal barrier is compromised. The CagA virulence factor (in CagA-positive H. pylori strains) is injected into gastric epithelial cells and disrupts cell signaling in ways that promote malignant transformation.
- Chronic atrophic gastritis develops — the combined insult of salt damage and H. pylori inflammation, sustained over decades, produces atrophic gastritis (loss of normal gastric glandular tissue), intestinal metaplasia (replacement with intestinal-type epithelium), dysplasia, and eventually adenocarcinoma
- N-nitroso compounds amplify the signal — nitrites and nitrates from various dietary sources (including fermented foods) can be reduced to bacterial-derived N-nitroso compounds in the achlorhydric stomach, which are direct carcinogens
The key insight is that the gastric cancer risk is concentrated in H. pylori-positive high-salt consumers. H. pylori-negative individuals with the same sodium intake have a much smaller incremental risk.
For more on H. pylori specifically, see our Helicobacter pylori page.
Cardiovascular Trade-offs
Beyond gastric cancer, high sodium intake has well-established cardiovascular effects: it raises blood pressure (with substantial individual variation in salt-sensitivity), increases left ventricular hypertrophy, accelerates renal damage in patients with pre-existing kidney disease, and is associated with cerebrovascular events. A 2021 worldwide analysis placed South Korean women among the lowest for age-standardized hypertension prevalence in 2019, and South Korea among the highest for hypertension treatment and control.
The cardiovascular calculation for kimchi is more straightforward than the gastric cancer calculation:
- Normotensive individuals with normal kidney function — modest kimchi consumption (50-100 g/day) probably does not produce meaningful cardiovascular harm in the context of an otherwise sensible diet. The potassium in cabbage partially offsets the sodium effect on blood pressure.
- Salt-sensitive hypertensives, especially African-American, elderly, and pre-existing chronic kidney disease (CKD) — even modest kimchi consumption is described as able to produce measurable blood pressure (BP) rises within hours; no study of this was found. The concern is the sodium, and low-sodium variants are the option used.
- Heart failure (especially on diuretics) — sodium restriction is a cornerstone of management. Regular kimchi consumption sits badly with that restriction; small occasional servings are the usual limit described.
- Advanced chronic kidney disease on sodium restriction — same consideration; the typical chronic kidney disease diet allows ~2,000 mg/day total sodium, which a single 200 g kimchi serving could exceed
The one long follow-up found for this page points away from a kimchi-specific effect on blood pressure. Among 5,932 Korean adults followed for 12 years, 1,798 developed hypertension, with no significant difference across levels of total kimchi intake. A trend appeared only for watery kimchi in obese men.
The probiotic and chemopreventive benefits of kimchi do not offset the cardiovascular effects of sodium in patients with established sodium-sensitive disease. The risk-benefit calculus is individual, not universal.
Confounding and the Whole-Diet Question
The Korean epidemiology of kimchi-and-gastric-cancer is complicated by serious confounding. High-kimchi consumers are typically also high consumers of:
- Salt-fermented seafood (jeotgal) — possibly the larger gastric carcinogen signal
- Salted soups and stews
- Smoked and grilled meats (charred surface contains polycyclic aromatic hydrocarbons, also gastric carcinogens)
- Lower fresh-fruit-and-vegetable intake (the calories displaced by the heavy starch + side dish + kimchi pattern)
- Higher H. pylori carriage rates (older birth cohorts)
Disentangling the kimchi-specific effect from these covariates is methodologically difficult. Some studies, after adjustment, find that the kimchi-specific gastric cancer signal narrows substantially — the residual effect being driven mainly by the salt content rather than any kimchi-specific carcinogen. Other studies find a persistent kimchi signal even after adjustment. The honest reading is that kimchi is part of a broader high-salt dietary pattern that elevates gastric cancer risk, and the kimchi-specific marginal contribution depends on the other dietary choices made alongside it.
Two Korean case-control studies show why this is hard. In one, cabbage kimchi went with lower risk while radish and water kimchi went with higher risk. In another, people with both H. pylori and a strong preference for salty taste had a 10-fold higher risk of early gastric cancer than people with neither.
Kimchi may also carry benefits that a sodium count misses. A 2024 cross-sectional study of 115,726 Korean adults linked 1-3 servings of kimchi a day to lower odds of obesity in men (odds ratios about 0.88-0.89). The pattern was J-shaped, meaning the odds rose again at higher intake, and a study of this kind cannot show cause.
This is fundamentally a different question from "does kimchi cause gastric cancer in a low-salt Western dietary context?" The answer to that question is essentially unstudied because nobody eats 200 g/day kimchi in isolation while maintaining an otherwise low-sodium diet. Plausibly, the Westernized pattern of 50-100 g/day kimchi as part of a diet with modest total sodium (2,500-3,500 mg/day) does not carry the gastric cancer risk seen in the Korean cohorts. But this is extrapolation, not direct evidence.
Low-Sodium Kimchi Variants
Several practical approaches reduce kimchi sodium while preserving most of the probiotic and Brassica chemistry benefits:
- Commercial reduced-sodium kimchi — many Korean and Korean-American brands now offer 30-50% reduced-sodium versions. The fermentation is generally fine at 1.5-2% salt (the practical lower limit for reproducible fermentation dominated by lactic acid bacteria, or LAB), and the flavor is identifiable as kimchi though slightly less pungent than the traditional version.
- Dongchimi (water kimchi) — the cabbage and radish are eaten without the brine, substantially reducing sodium intake per serving
- Rinsing kimchi briefly before serving — a quick water rinse reduces surface salt by 20-30%, with minor flavor impact. Useful for elderly or hypertensive consumers who want some kimchi without the full sodium load.
- Home fermentation at 1.5-1.8% salt — controllable, the fermentation outcome is usually fine, and by the same arithmetic the sodium content is about 600-720 mg per 100 g, the low end of the commercial range above
- Potassium chloride salt substitution — partial replacement of sodium chloride with potassium chloride (typical ratios up to 30% KCl) is used in some commercial reduced-sodium products. KCl has a slightly bitter aftertaste but is generally acceptable at moderate substitution ratios. The added potassium has its own modest cardiovascular benefit (further offsets the sodium effect on blood pressure). Note that KCl is contraindicated in advanced chronic kidney disease and in patients on potassium-sparing diuretics or angiotensin-converting enzyme inhibitors (ACE inhibitors).
- Smaller serving sizes — 30-50 g per meal instead of 100 g per meal reduces the sodium exposure proportionally while still providing the live LAB, sulforaphane, and bioactive load
Whether lowering salt in this way lowers stomach cancer is not settled. In the large Salt Substitute and Stroke Study in 600 Chinese villages (20,996 people), a later analysis found that a potassium-enriched salt substitute did not significantly lower stomach cancer (rate ratio 0.77, 95% confidence interval 0.54-1.08), though the trend pointed that way. It tested table salt, not kimchi.
Home-Fermentation Guidance
Home fermentation gives the consumer direct control over the salt content, the seasonings, the fermentation timing, and the absence of preservatives and additives sometimes added to commercial products. Basic outline for reduced-sodium home kimchi (adapt to taste):
- Salt and brine the cabbage at 1.5-2% salt — for 2 kg napa cabbage, use 30-40 g coarse sea salt (no iodine, which can inhibit fermentation). Toss the quartered cabbage with salt, then submerge in light brine (3% brine, made with the same coarse salt) for 2-3 hours, weighting if needed to keep submerged. Rinse briefly and drain.
- Prepare the seasoning paste — grated Korean radish, scallion, garlic, ginger, gochugaru (Korean chili powder — use 2-4 tablespoons per kg cabbage depending on heat tolerance), and optional fermented seafood (saeujeot or anchovy sauce; use small amounts — these are concentrated sodium sources). Vegan: omit seafood, add 1-2 tablespoons of soaked dried shiitake plus 1 tablespoon of miso for umami.
- Mix and pack — rub the paste into the cabbage layers, pack tightly into a glass or onggi jar leaving 1-2 inches headspace, weight or use a fermentation airlock to maintain anaerobic conditions
- Ferment at room temperature 1-3 days — until you see active bubbling and a clearly sour taste develops. Then refrigerate.
- Refrigerator-ferment 1-3 weeks — the slow cold fermentation produces the mat-i-deulda flavor and the maximum LAB density. The kimchi continues to evolve in flavor for several weeks before passing peak quality.
By the same arithmetic as the commercial figures above (1.5% salt is about 600 mg sodium per 100 g), a finished kimchi at 1.5-2% salt holds roughly 600-800 mg sodium per 100 g, the low end of the commercial range. The fermentation will still proceed reliably because the 1.5-2% salt is above the threshold for selecting LAB over spoilage organisms.
Who the Research Raises Concerns For
Groups for whom the research raises little concern about moderate kimchi intake:
- Healthy adults without hypertension, kidney disease, or heart failure, eating a generally low-to-moderate sodium baseline diet
- People with constipation or irritable bowel syndrome (IBS) who tolerate fiber and capsaicin
- People with food allergies and atopic conditions, on the reported idea that LAB strains have favorable effects on regulatory T cells
- Adults interested in fermented food diversity and Brassica vegetable intake
Groups the research raises concerns for:
- Salt-sensitive hypertension — low-sodium variants and small portions are the options described
- Advanced chronic kidney disease — both sodium and potassium content are concerns
- Heart failure on sodium restriction — small occasional servings are the usual limit described
- History of gastric cancer or significant atrophic gastritis — high-salt foods are the concern
- Active H. pylori infection without eradication therapy — the salt + bacteria interaction is the relevant mechanism
- Histamine intolerance or mast cell activation — fermented food histamine content can be problematic
- Severe immunocompromise (post-transplant, neutropenia, advanced human immunodeficiency virus (HIV) without antiretroviral therapy) — live-bacteria food safety concern, though kimchi LAB are generally regarded as safe
- Children under 1 year — salt content and choking hazard from the cabbage texture
Bottom Line
Kimchi is a high-sodium fermented vegetable with real probiotic and Brassica-chemoprevention benefits. In the context of the broader high-sodium Korean dietary pattern, heavy lifelong kimchi consumption has been linked in some Korean studies, though not all, to elevated gastric cancer risk, with the salt-and-mucosal-damage mechanism in H. pylori-positive individuals as the proposed explanation. In the context of a moderate-sodium Western dietary pattern with modest kimchi consumption (50-100 g/day, perhaps a few times per week rather than three times daily), the risk-benefit balance is much more favorable.
What the research and food data point to:
- Properly fermented kimchi (not pasteurized, not "fresh" geotjeori) is the kind that carries live LAB
- Moderate servings (50-100 g) with meals, not every meal, keep the sodium load lower
- Reduced-sodium variants and home fermentation at 1.5-2% salt are the lower-salt options
- Total daily sodium from all sources matters more than kimchi alone; in Korea, noodles and seasonings carry more than kimchi, and soups nearly as much
- The salt and H. pylori interaction is the main concern raised for people who carry the bacterium, for whom eradication therapy exists
- For people with hypertension, heart failure, or advanced chronic kidney disease, the concern is the sodium, and an occasional small portion is the pattern described rather than a daily side dish
Key Research Papers
- Lee SA et al. (2003). Effect of diet and Helicobacter pylori infection to the risk of early gastric cancer. Journal of Epidemiology. — PubMed PMID: 12749604
- Kim HJ et al. (2002). Dietary factors and gastric cancer in Korea: a case-control study. International Journal of Cancer. — PubMed PMID: 11802218
- Tsugane S, Sasazuki S (2007). Diet and the risk of gastric cancer: review of epidemiological evidence. Gastric Cancer. — PubMed PMID: 17577615
- D'Elia L et al. (2012). Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clinical Nutrition. — PubMed PMID: 22296873
- Wang XQ et al. (2009). Review of salt consumption and stomach cancer risk: epidemiological and biological evidence. World Journal of Gastroenterology. — PubMed PMID: 19437559
- Ha SK (2014). Dietary salt intake and hypertension. Electrolyte & Blood Pressure. — PubMed PMID: 25061468
- Lee Y et al. (2026). From Children to the Entire Population: Policy Lessons From a Decade of Successful Sodium Intake Reduction in South Korea. Korean Circulation Journal. — PubMed PMID: 42324222
- Jeong Y et al. (2021). Trends in sodium intake and major contributing food groups and dishes in Korea: the Korea National Health and Nutrition Examination Survey 2013-2017. Nutrition Research and Practice. — PubMed PMID: 34093978
- Zhao HY et al. (2026). Changing patterns and related factors of kimchi consumption among Korean adults: a nationwide cross-sectional analysis of the Korea National Health and Nutrition Examination Survey, 2010-2024. Korean Journal of Community Nutrition. — PubMed PMID: 42425751
- Yang JY et al. (2026). Kimchi friend or foe: preserving cultural foods developed pre-refrigeration. Preventive Medicine Reports. — PubMed PMID: 41560871
- Nan HM et al. (2005). Kimchi and soybean pastes are risk factors of gastric cancer. World Journal of Gastroenterology. — PubMed PMID: 15929164
- Yoo JY et al. (2020). Pickled Vegetable and Salted Fish Intake and the Risk of Gastric Cancer: Two Prospective Cohort Studies and a Meta-Analysis. Cancers. — PubMed PMID: 32316595
- Cho HJ et al. (2024). Gastric and colorectal cancer incidence attributable to dietary factors in Korea. Journal of Gastrointestinal Oncology. — PubMed PMID: 38989404
- Lim SH et al. (2018). Trends in the seroprevalence of Helicobacter pylori infection and its putative eradication rate over 18 years in Korea: A cross-sectional nationwide multicenter study. PLoS One. — PubMed PMID: 30332428
- Song M et al. (2015). Age and sex interactions in gastric cancer incidence and mortality trends in Korea. Gastric Cancer. — PubMed PMID: 25091081
- Jun JK et al. (2017). Effectiveness of the Korean National Cancer Screening Program in Reducing Gastric Cancer Mortality. Gastroenterology. — PubMed PMID: 28147224
- NCD Risk Factor Collaboration (2021). Worldwide trends in hypertension prevalence and progress in treatment and control from 1990 to 2019: a pooled analysis of 1201 population-representative studies with 104 million participants. Lancet. — PubMed PMID: 34450083
- Song HJ et al. (2017). High consumption of salt-fermented vegetables and hypertension risk in adults: a 12-year follow-up study. Asia Pacific Journal of Clinical Nutrition. — PubMed PMID: 28582822
- Jung H et al. (2024). Association between kimchi consumption and obesity based on BMI and abdominal obesity in Korean adults: a cross-sectional analysis of the Health Examinees study. BMJ Open. — PubMed PMID: 38290970
- Zhang X et al. (2025). Effect of sodium-reduced potassium-enriched salt substitutes on stomach cancer: the Salt Substitute and Stroke Study (SSaSS). BMC Medicine. — PubMed PMID: 40264179