Carbon Monoxide Poisoning
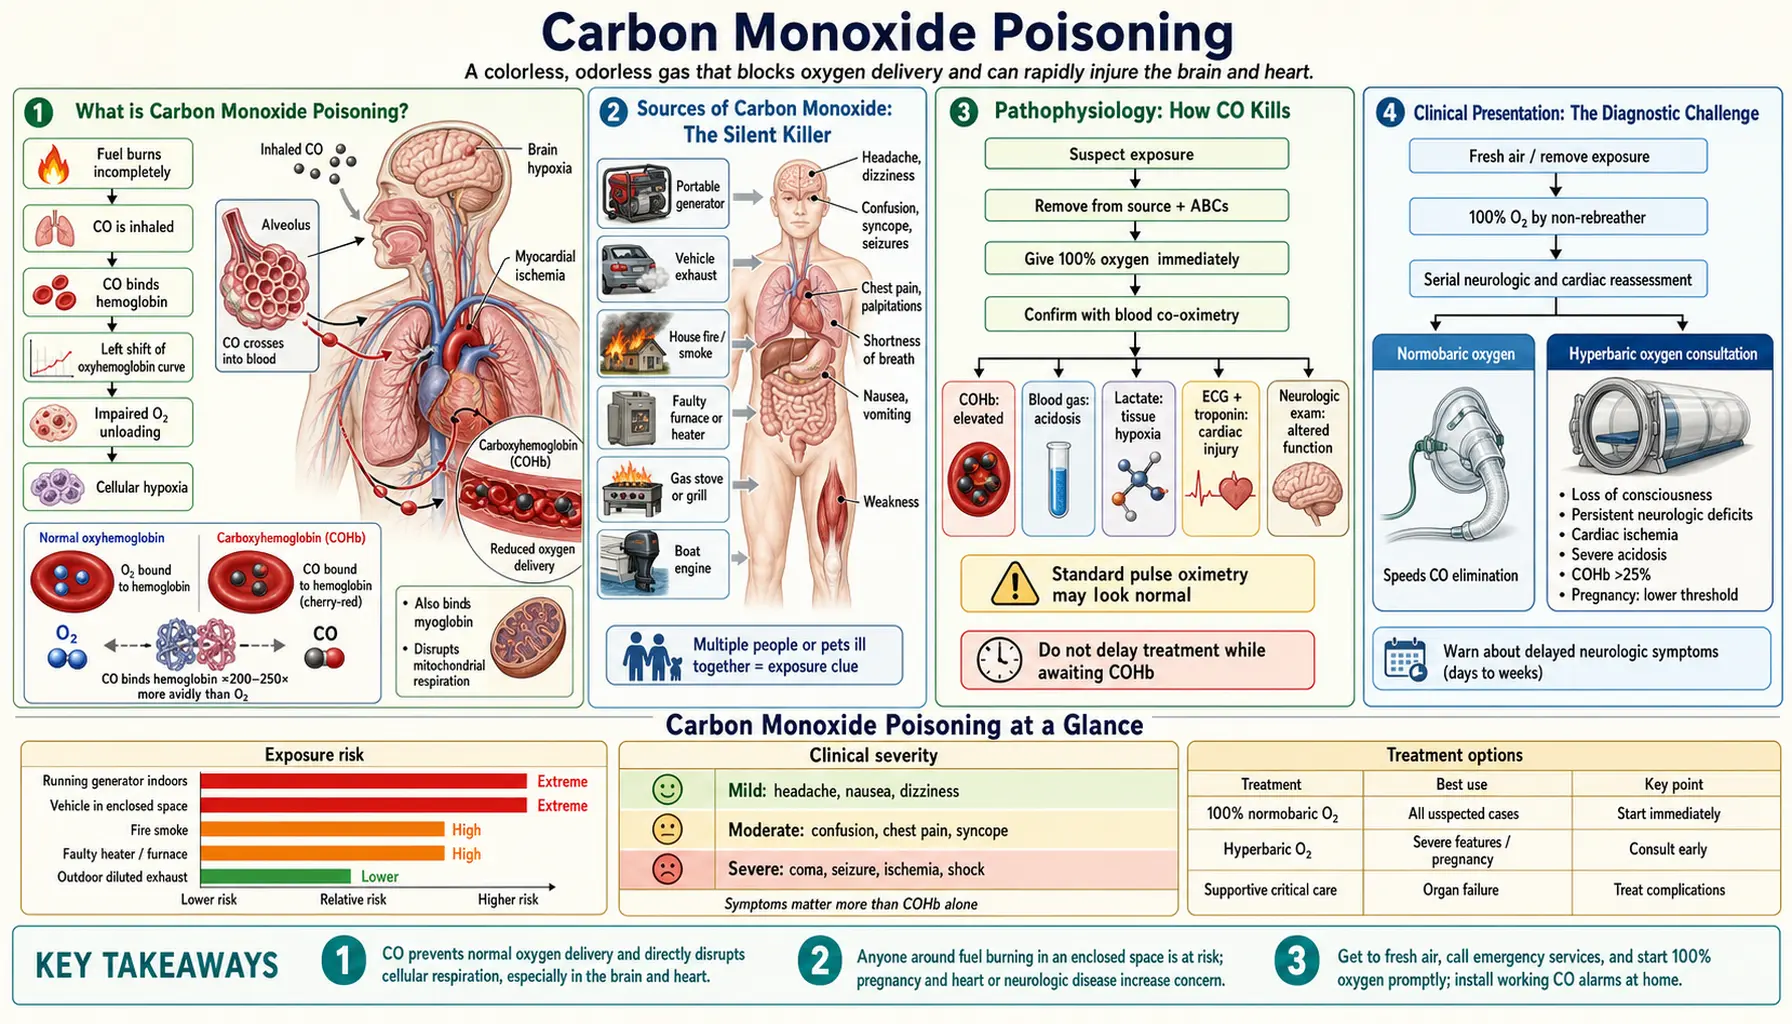
Carbon monoxide (CO) poisoning is among the leading causes of poisoning in the United States — and among the most treatable, when recognized in time. Its danger lies precisely in the fact that CO is colorless, odorless, and tasteless: it provokes no warning sensation. People exposed to building up CO levels feel progressively unwell and often have no idea why. This page explains how CO kills, why routine pulse oximetry misses it entirely, how it is treated, and how it is prevented.
- What Carbon Monoxide Poisoning Is
- Sources of Carbon Monoxide: The Silent Killer
- Pathophysiology: How CO Kills
- Clinical Presentation: The Diagnostic Challenge
- Diagnosis: CO-Oximetry and Why Pulse Oximetry Fails
- Severity Assessment and COHb Levels
- Treatment: Oxygen Therapy and Hyperbaric Oxygen
- Delayed Neurological Sequelae
- Prevention: Detectors and Safety Rules
- Key Research Papers
- Connections
What Carbon Monoxide Poisoning Is
Carbon monoxide poisoning occurs when a person inhales sufficient quantities of CO gas to impair oxygen delivery to the body's tissues. Because CO is completely invisible and produces no smell or taste, there is no natural sensory warning — the gas accumulates silently while the victim's symptoms escalate from mild fatigue and headache to coma and death.
CO poisoning accounts for approximately 50,000 emergency department visits per year in the United States and causes roughly 400–500 unintentional, non-fire-related deaths annually. Many more deaths occur in the context of residential fires, where CO is a major contributor to mortality before the flames themselves cause injury. Globally, CO poisoning follows similar patterns, with a striking winter peak that mirrors the increased use of fuel-burning heating appliances as temperatures drop.
A national surveillance report for 2005 to 2018 gives these yearly rates of unintentional poisoning: 56.5 emergency visits per million people (17 states), 7.3 hospital stays per million (26 states) and 3.3 deaths per million nationally. Rates of hospital stays and deaths not related to fire fell over those years (Shin 2023). A US cost study found that the benefit of home detectors can be as high as 7.2 times their cost (Ran 2018).
Poisoning can be unintentional — caused by a malfunctioning heating system, a portable generator running indoors, or a vehicle idling in an attached garage — or intentional, as CO inhalation is a common method in suicidal exposures. In both contexts, the physiology and treatment are identical.
One of the most clinically dangerous aspects of CO poisoning is its propensity to be misdiagnosed. The combination of headache, nausea, fatigue, and dizziness is indistinguishable from influenza, food poisoning, or migraine without a specific index of suspicion. Patients are sent home, return to the same environment, and worsen. Maintaining a high clinical suspicion — particularly when multiple household members are ill simultaneously — is the most important diagnostic step.
Sources of Carbon Monoxide: The Silent Killer
Carbon monoxide is a product of incomplete combustion — any time a carbon-based fuel (natural gas, propane, gasoline, wood, charcoal, kerosene) burns without sufficient oxygen, CO is produced alongside carbon dioxide. The most common and most dangerous sources are:
Gas Furnaces and Water Heaters
Cracked heat exchangers, blocked or disconnected flues, improper installation, and inadequate combustion air are the most common causes of CO accumulation in homes during winter months. A furnace may function normally for years before a developing crack in the heat exchanger begins leaking combustion gases into circulating household air. The US Consumer Product Safety Commission urges an annual professional inspection of all fuel-burning appliances, and that inspection is the primary prevention strategy.
Portable Generators
Portable gasoline-powered generators are responsible for the largest number of CO deaths in the United States after natural disasters — power outages from hurricanes, ice storms, and blizzards prompt people to run generators indoors or in garages. A single generator can produce CO at concentrations 100 times higher than a car exhaust; CO can reach lethal levels in a closed garage within minutes. Safety guidance places generators outdoors only, at least 20 feet from any window, door, or vent. The published counts read for this page do not reach a combined figure of over 400 generator deaths after Hurricanes Katrina, Sandy, and Irma/Maria: a review of US disasters from 1991 to 2009, which covers Katrina but not the later storms, counted 1,888 poisoning cases and 75 deaths from all sources (Iqbal 2012), and one county's investigation after Hurricane Irma counted 91 cases and 3 deaths (Falise 2019).
In that review, generators were the main source in 83% of deaths, and 67% of those deaths came from a generator placed indoors. Most deaths (94%) happened at home, and nearly 89% happened within 3 days of the disaster starting. Charcoal grills were a major source during winter storms.
Charcoal Grills and Hibachis
Charcoal combustion produces extremely high concentrations of CO. A charcoal grill used indoors, in a garage, in a screened porch, or in a tent — even in rain — can fill that space with dangerous CO. The same hazard applies to camping stoves burning propane or white gas in enclosed spaces.
Gasoline-Powered Tools and Equipment
Chainsaws, pressure washers, lawn mowers, snow blowers, and other gas-powered tools generate large volumes of CO, which builds up in any enclosed space where they run. Using a pressure washer inside a warehouse, barn, or parking garage — even with the door open — has caused fatal poisonings.
Vehicle Exhaust in Attached Garages
Even briefly warming up a car in an attached garage, with the garage door open, can allow CO to accumulate inside the adjoining home at dangerous concentrations. The CO diffuses through gaps around the door connecting the garage to the living space. A fully open garage door and backing the car out immediately shorten the time exhaust stays in the garage.
Gas Ranges and Ovens
Prolonged use, malfunction, or intentional misuse (running an oven as a space heater) can produce dangerous CO. Burner malfunctions that produce yellow-orange rather than blue flames signal incomplete combustion.
Boats and Marine Engines
Carbon monoxide from generator or engine exhaust can accumulate near swim platforms, in cockpits, and under bimini tops — a hazard called "generator backdraft" or "station wagon effect." Multiple deaths have occurred when swimmers rested on swim platforms near operating generators. The US Coast Guard's boating safety program tells boaters to "install and maintain CO alarms inside your boat"; a search of the federal regulations (Titles 33 and 46 of the Code of Federal Regulations) found no detector requirement for recreational boats.
House Fires and Industrial Exposure
CO is a major cause of death in structural fires — often killing occupants before flames reach them. Industrial workers in foundries, steel mills, and chemical plants face occupational CO exposure. Firefighters are at particular risk when entering burning structures without self-contained breathing apparatus (SCBA).
Pathophysiology: How CO Kills
Carbon monoxide's toxicity operates through three simultaneous mechanisms, each capable of causing profound cellular injury independently. Together, they create a state of oxygen deprivation that standard oxygen measurements — including pulse oximetry — completely miss.
Carboxyhemoglobin Formation: Functional Anemia
Carbon monoxide binds to hemoglobin with approximately 240 times greater affinity than oxygen. When CO occupies a hemoglobin binding site, it forms carboxyhemoglobin (COHb) — a molecule that cannot carry oxygen. A patient with 40% COHb has effectively lost 40% of their oxygen-carrying capacity, producing the equivalent of severe anemia, but with a total hemoglobin level that appears entirely normal on routine blood tests.
The Haldane Effect: Impaired Oxygen Unloading
CO poisoning has a second, subtler effect on the remaining oxygenated hemoglobin. The presence of CO on some hemoglobin subunits shifts the oxyhemoglobin dissociation curve leftward — meaning the unaffected, oxygen-carrying hemoglobin molecules now hold onto their oxygen more tightly and release less of it to tissues. This is the Haldane effect. The combination of reduced oxygen loading (because CO occupies binding sites) and reduced oxygen unloading (because the remaining oxygenated Hb grips O2 more tightly) produces profound tissue hypoxia that is worse than either effect alone would predict.
Cytochrome c Oxidase Inhibition: Cellular Respiratory Arrest
Even if sufficient oxygen could somehow be delivered to a cell, CO would still be toxic at the cellular level. CO directly inhibits cytochrome c oxidase (Complex IV), the final enzyme in the mitochondrial electron transport chain responsible for cellular adenosine triphosphate (ATP) production. By blocking this enzyme, CO arrests cellular respiration at the tissue level — cells cannot use oxygen even when it is present. This mechanism explains why CO poisoning produces a lactic acidosis (anaerobic metabolism) and why symptoms can persist even after COHb levels normalize with treatment.
Myocardial and Muscle Injury
Cardiac myocytes have among the highest oxygen demands of any tissue and are particularly vulnerable to CO-mediated hypoxia and cytochrome inhibition. Electrocardiogram (ECG) changes, ST-segment elevation mimicking myocardial infarction, troponin elevation, and arrhythmias are common at moderate-to-severe exposures. CO also binds myoglobin in skeletal and cardiac muscle, adding direct muscle toxicity and contributing to rhabdomyolysis at high exposures.
Heart damage has long-term consequences. In a study that followed 230 adults treated with hyperbaric oxygen for moderate to severe poisoning, 37% had measurable heart injury. Over a median of 7.6 years, 38% of those with heart injury died, against 15% of those without it (Henry 2006). This was an observational cohort, not a trial.
Clinical Presentation: The Diagnostic Challenge
The central clinical challenge in CO poisoning is that its symptoms are completely nonspecific. There is no pathognomonic sign that — by itself — confirms the diagnosis. The presentation perfectly mimics dozens of common conditions, and the most dangerous aspect of CO poisoning is not the physiology but the diagnostic delay it causes.
The Classic Presentation: Flu Without Fever
The most common initial symptom is headache — typically described as dull, frontal, and progressively worsening. Nausea and vomiting, fatigue, malaise, and dizziness accompany the headache in most cases. The key distinguishing feature is the absence of fever: CO poisoning does not cause elevated body temperature, while genuine influenza almost always does. Despite this, CO poisoning is among the most commonly misdiagnosed conditions seen in emergency departments during winter months.
The Household Clue: Multiple Victims Including Pets
A critically important clinical observation: if multiple people in the same enclosed space are ill simultaneously, CO poisoning is an immediate suspect. Dogs and other pets, with their higher respiratory rates and smaller body mass, often show symptoms — lethargy, ataxia, collapse — before humans reach dangerous COHb levels. Pets acting abnormally alongside a sick household are a warning sign that emergency services treat as urgent: everyone leaves the building and help is called.
The Hallmark History: Symptoms That Improve on Leaving the Building
Perhaps the single most diagnostically useful question is: "Did your symptoms improve when you left home or work — and then return when you went back?" This pattern of location-linked symptom fluctuation is highly characteristic of CO poisoning and is the history emergency clinicians look for in patients presenting with nonspecific headache and nausea during winter months.
The Myth of Cherry-Red Skin
Medical textbooks traditionally describe cherry-red lips and skin as a hallmark of CO poisoning. In clinical practice, this finding is rare and unreliable — it is seen only at very high COHb concentrations and is most commonly observed post-mortem. Its absence absolutely does not exclude CO poisoning. Clinicians who wait for cherry-red skin before testing for COHb will miss the majority of cases.
Neurological and Cardiac Symptoms at Higher Exposures
As COHb levels rise, symptoms escalate from the nonspecific flu-like presentation toward frank neurological and cardiovascular impairment: confusion, slowed mentation, syncope, ataxia, and seizures. Chest pain, palpitations, and dyspnea reflect myocardial ischemia. At the highest exposures: coma, respiratory failure, and cardiac arrest.
Diagnosis: CO-Oximetry and Why Pulse Oximetry Fails
Understanding the diagnostic limitations of routine monitoring equipment is essential — a failure to grasp this point leads directly to missed diagnoses and patient deaths.
Standard Pulse Oximetry Falsely Reads Normal in CO Poisoning
The standard bedside pulse oximeter used in virtually every clinical setting measures oxygen saturation using two wavelengths of light (660 nm red and 940 nm infrared). It detects the optical difference between oxyhemoglobin and deoxyhemoglobin — but it cannot distinguish between oxyhemoglobin and carboxyhemoglobin. Carboxyhemoglobin absorbs light at wavelengths very similar to oxyhemoglobin and is read by the pulse oximeter as oxygenated hemoglobin. A patient with 50% COHb will display a pulse oximetry reading of 98–99% — appearing completely normal — while in reality half of their hemoglobin is nonfunctional. This is one of the most clinically important limitations of routine pulse oximetry.
CO-Oximetry: The Required Test
The correct diagnostic test is CO-oximetry, performed on an arterial blood gas (ABG) sample analyzed on a laboratory co-oximeter. Unlike a standard blood gas analyzer, a co-oximeter uses four or more wavelengths of light and can directly and accurately measure COHb%, methemoglobin (MetHb%), and other dyshemoglobins. This is the definitive test. Venous blood can also be used. In a study of 61 adults, venous and arterial COHb were nearly the same: the average difference was 0.15% COHb, with 95% of differences between 2.4% and -2.1%, and the authors concluded that patients can be screened with venous blood without an arterial puncture (Touger 1995). Both are used for diagnosis and management decisions.
Point-of-Care Non-Invasive CO-Oximetry
A pulse CO-oximeter is a non-invasive device that measures COHb transcutaneously using eight wavelengths of light. It is increasingly used for rapid screening in emergency department triage, enabling identification of CO-poisoned patients without waiting for an ABG. Its accuracy is lower than laboratory co-oximetry (particularly at low-to-moderate COHb levels). Unlike the standard two-wavelength pulse oximeter it does attempt to read COHb, but a normal reading does not clear someone: in one emergency department study the device caught only 11 of 23 people with a laboratory level above 15% (sensitivity 48%, specificity 99%). Its readings differed from the laboratory by -11.6% to 14.4% COHb, and the authors concluded it may not be used interchangeably with the laboratory test (Touger 2010).
Supporting Laboratory and Electrocardiographic Studies
An electrocardiogram is part of the hospital work-up — ST-segment changes (including ST elevation that can mimic a major heart attack, called ST-elevation myocardial infarction or STEMI), sinus tachycardia, and ventricular arrhythmias are common at moderate-severe exposures and guide both risk stratification and disposition decisions. Troponin elevation is found in a substantial proportion of significant CO exposures and carries prognostic weight: troponin I above 0.4 ng/mL has been associated with adverse neurological outcomes. Serum lactate is elevated due to impaired mitochondrial respiration, correlating roughly with severity, though it is not CO-specific. Head computed tomography (CT) or magnetic resonance imaging (MRI) is indicated for patients with altered mental status or neurological signs — characteristic basal ganglia lesions (particularly in the globus pallidus) are visible on magnetic resonance imaging and may appear on initial imaging or develop over the subsequent weeks as part of delayed neurological syndrome.
Severity Assessment and COHb Levels
Carboxyhemoglobin levels provide a useful but imperfect guide to clinical severity. An important caveat: COHb levels correlate poorly with clinical severity on an individual basis. Individuals with chronic exposure (such as heavy smokers, who may run baseline COHb of 5–10%) or those with significant comorbidities may be more or less symptomatic than their COHb level predicts. Duration of exposure matters as much as peak level. Clinical symptoms, cardiac findings, and neurological status are read alongside the COHb measurement.
COHb Level Reference Ranges
- Less than 10%: Minimal or no symptoms. Note that heavy smokers can have baseline COHb of 5–10% from cigarette combustion alone.
- 10–20%: Throbbing headache, dizziness, nausea, mild cognitive impairment. Most patients are symptomatic.
- 20–40%: Severe headache, nausea and vomiting, confusion, weakness, palpitations, visual changes. Neurological function begins to deteriorate.
- 40–60%: Syncope, seizures, tachycardia, hypotension, chest pain, ST changes. Potentially fatal without treatment.
- Greater than 60%: Coma, respiratory failure, cardiovascular collapse, death.
Severity Classification for Treatment Decisions
The determination of whether to pursue hyperbaric oxygen (HBO) therapy is based on a severity classification that integrates COHb level with clinical features:
- Mild: No loss of consciousness; COHb less than 25%; no cardiac involvement; no significant neurological symptoms.
- Moderate to Severe (HBO indicated): Any loss of consciousness or syncope; COHb 25% or greater; cardiac involvement (troponin elevation, electrocardiogram changes); focal neurological deficits; seizures; pregnancy (any symptomatic exposure — the threshold for HBO is much lower due to increased fetal susceptibility).
Treatment: Oxygen Therapy and Hyperbaric Oxygen
Treatment of CO poisoning follows a clear stepwise approach, with urgency calibrated to severity. The fundamental principle is removing CO from the body and reversing the tissue hypoxia it has caused — and doing so as rapidly as possible to prevent irreversible neurological injury.
Step 1: Immediate Removal from Exposure
Treatment begins with getting the person out of the CO-containing environment immediately. Entering an enclosed CO-contaminated space without self-contained breathing apparatus (SCBA) is itself deadly — multiple rescuers have been incapacitated or killed attempting to rescue CO victims without proper respiratory protection. Emergency services are called and everyone in the building is evacuated.
Step 2: 100% Normobaric Oxygen
100% oxygen via a tight-fitting non-rebreather mask is the first and most universally available treatment. Supplemental oxygen works by mass action: at very high inspired oxygen concentrations, the partial pressure of O2 dramatically exceeds that of CO, accelerating displacement of CO from hemoglobin binding sites. The COHb half-life on room air is approximately 4–5 hours. On 100% normobaric oxygen (NBO), this falls to approximately 60–90 minutes. Oxygen at 100% is continued until COHb is below 5% and the patient is clinically asymptomatic. Nasal cannula alone is inadequate — a properly fitted non-rebreather mask is required to bring the fraction of inspired oxygen (FiO2) near 100%.
Step 3: Hyperbaric Oxygen Therapy (HBO)
Hyperbaric oxygen involves breathing 100% oxygen inside a pressurized chamber at 2–3 atmospheres absolute (ATA). This treatment offers mechanistic advantages beyond simple acceleration of CO elimination:
- Faster CO elimination: The COHb half-life falls to approximately 20–30 minutes in the hyperbaric chamber — three to four times faster than NBO.
- Plasma-dissolved oxygen: At 3 ATA breathing 100% O2, enough oxygen dissolves directly in plasma to meet resting tissue oxygen requirements without any hemoglobin contribution — effectively bypassing the carboxyhemoglobin problem entirely.
- Cytochrome c oxidase recovery: HBO has been shown to displace CO from cytochrome c oxidase and restore mitochondrial respiratory function — addressing the cellular level of toxicity that NBO does not directly reverse.
- Reduction of lipid peroxidation and neuroinflammation: HBO inhibits neutrophil-mediated oxidative damage in the brain — the mechanism believed to underlie delayed neurological syndrome.
The landmark randomized controlled trial by Weaver et al. (2002, PMID 12362006) compared three sessions of HBO versus NBO in moderate-to-severe CO poisoning and demonstrated a significantly lower rate of cognitive sequelae at 6 weeks in the HBO group — providing the strongest prospective evidence for HBO's benefit beyond simple CO elimination.
Indications for HBO (Weaver criteria) include: any loss of consciousness or syncope; neurological signs or symptoms; COHb 25% or greater; cardiac involvement; and any symptomatic pregnant patient. Practical limitations — HBO chambers are not universally available, and transport time is weighed against the clinical urgency and the time-sensitivity of the HBO benefit — require individualized judgment.
Whether Hyperbaric Oxygen Prevents Lasting Brain Problems Is Still Disputed
A 2011 Cochrane review of 6 randomized trials (1,361 people) found 2 trials positive and 4 not, with design or analysis flaws in all of them. The pooled result showed no significant benefit (odds ratio for neurological deficits 0.78, 95% confidence interval 0.54 to 1.12), and the authors wrote that existing trials do not establish whether hyperbaric oxygen reduces adverse neurologic outcomes (Buckley 2011). A 2026 meta-analysis of 6 trials also found no significant benefit on deaths or neurological outcomes, even at 2.5 atmospheres or higher, rated the evidence low to very low, and called for larger trials (Fujita 2026).
Two of the trials on this page's reading list did not find a benefit. In Scheinkestel 1999, where both groups received high doses of oxygen, the authors concluded that hyperbaric oxygen did not benefit and may have worsened the outcome. In Annane 2011 (385 patients), full recovery at 1 month was 58% with and 61% without hyperbaric oxygen in people who had briefly lost consciousness, and 47% with two sessions against 68% with one in people who had been in a coma.
Supportive Care
Cardiac monitoring for arrhythmias and ischemia is continuous in moderate-to-severe cases. Vasopressors are indicated for persistent hypotension after volume resuscitation. Benzodiazepines are first-line for seizures. Intravenous fluids are generally needed. A normal COHb level after apparent recovery does not mean a person is safe from further neurological injury, because delayed neurological syndrome can still appear; significant exposures are observed and counseled about it for that reason.
Delayed Neurological Sequelae
Delayed neurological sequelae (DNS) is one of the most distinctive and feared complications of CO poisoning — a neuropsychiatric syndrome that appears days to weeks after the patient has apparently recovered from the acute poisoning and been discharged home.
Definition and Incidence
DNS is defined as the emergence or re-emergence of neuropsychiatric symptoms after an apparent clinical recovery from acute CO poisoning. A 2000 review gives the window as 2 to 28 days (Raub 2000); in Choi's 1983 series of 2,360 victims the symptom-free interval ran from 2 to 40 days, with a mean of 22.4 days. Its incidence varies with exposure severity and with how it is counted: it is rare after mild poisoning. Choi found it in 2.75% of all victims and 11.8% of those admitted, and a 2026 cohort of people treated with hyperbaric oxygen found 19% to 37% depending on the protocol (Gur 2026). A range of 30–50% of patients with moderate-to-severe exposures who do not receive hyperbaric oxygen therapy sits close to the 46% in the Weaver trial, but that trial measured cognitive sequelae at 6 weeks, a different outcome. This makes it one of the most common serious late complications in emergency medicine.
Mechanism: Oxidative White Matter Injury
The pathophysiology involves a delayed inflammatory and oxidative cascade that injures cerebral white matter. CO exposure triggers lipid peroxidation in myelin-rich white matter, platelet activation, and neutrophil adhesion to brain microvascular endothelium — processes that continue after CO has been eliminated from the body. The result is a delayed demyelination of white matter tracts, with the globus pallidus being particularly vulnerable due to its high metabolic demand and vascular anatomy.
Clinical Features
DNS presents as a deterioration in neurological and cognitive function days to weeks after the patient appeared to have recovered. Common manifestations include: cognitive impairment (memory loss, confusion, difficulty concentrating, impaired executive function); personality changes (apathy, irritability, emotional lability); parkinsonian features (masked facies, shuffling gait, rigidity, tremor); urinary or fecal incontinence; and psychosis or frank dementia in severe cases. These deficits range from subtle and transient to severe and permanent.
Neuroimaging
Magnetic resonance imaging is the imaging modality of choice. Characteristic findings include bilateral symmetric bright areas in the white matter on T2 and fluid-attenuated inversion recovery (FLAIR) scans (periventricular and deep white matter) and basal ganglia lesions, particularly in the globus pallidus. These changes may be absent on magnetic resonance imaging performed during acute poisoning and develop or become more pronounced in the weeks that follow — serial neuroimaging is often required for diagnosis.
The Role of Hyperbaric Oxygen in Prevention
The primary clinical argument for HBO therapy — beyond simply speeding CO elimination — is that it may lower DNS incidence, and the trials disagree on this (see Treatment). The Weaver 2002 trial showed that HBO treatment reduced the rate of cognitive sequelae at 6 weeks from 46% (NBO group) to 25% (HBO group); it measured cognitive sequelae, not DNS as such. The proposed explanation is HBO's effect on interrupting the oxidative and inflammatory cascade responsible for delayed white matter injury, rather than simply removing CO faster. This is the reasoning behind recommending HBO even for patients whose acute neurological symptoms have resolved with NBO, if their exposure qualifies by severity criteria.
In a 2026 review of records from 312 patients treated with hyperbaric oxygen, delayed neuropsychiatric problems were less common at higher pressure: 36.2% at 2.0 atmospheres against 19.3% at 2.8. Three sessions added no significant benefit over one. This was a look back at past patients, not a randomized comparison (Gur 2026).
Prognosis and Follow-Up
Most patients with DNS show partial improvement over months. In Choi's series, 27 of 36 patients followed for two years (75%) recovered within one year. Some patients make a full recovery; others are left with permanent cognitive deficits, personality changes, or movement disorder. Serial neuropsychological testing is important for documentation and management. New neurological or psychiatric symptoms in the weeks after poisoning are signs of this syndrome that hospitals treat as urgent, which is why warning patients and families at discharge is part of follow-up.
Prevention: Detectors and Safety Rules
Carbon monoxide poisoning is almost entirely preventable. The interventions are straightforward, inexpensive, and highly effective — but they require education and consistent practice.
Carbon Monoxide Detectors
CO detectors are the most important single prevention tool for residential poisoning. They are now legally required in most US states for residential buildings, and their installation has measurably reduced CO mortality in jurisdictions that enforce detector laws. Common guidance:
- The US Consumer Product Safety Commission recommends alarms on each level of the home, outside each sleeping area; common guidance includes the basement.
- Detectors near sleeping areas matter because CO poisoning most often kills people in their sleep.
- Common maintenance guidance is a new battery every year and a test every month.
- Common guidance is a new detector unit every 5–7 years (electrochemical sensors degrade with age).
- When the detector alarm sounds, the safety steps are: everyone evacuates immediately, leaving the door open; no one looks for the source or goes back in; 911 is called from outside; and no one returns until emergency responders confirm it is safe.
Generator Safety
Portable generator misuse is the single most preventable cause of CO death in the United States. The US Consumer Product Safety Commission states: "Never use a generator inside a home or garage, even if doors and windows are open. Only use generators outside and far away from windows, doors and vents." The same danger applies in a carport, on a porch, or near any window, door, or vent opening, even with the space ventilated, and the US Environmental Protection Agency warns that deadly levels can linger for hours after the generator has shut off. The minimum safe distance from any building opening is 20 feet. Prevention depends on every household member knowing this before an emergency. The label "portable" does not mean "indoor-safe" — it means nothing about where it can be operated safely.
Annual Heating System Maintenance
The US Consumer Product Safety Commission urges an annual professional inspection of all fuel-burning appliances. For heating, that means gas furnaces, boilers, oil furnaces, wood stoves and fireplaces inspected annually by a licensed professional. Heat exchangers in gas furnaces crack with age and can leak combustion gases into circulating air. Chimney flues can become blocked by bird nests, debris, or ice, preventing combustion gases from venting. An annual service call before heating season begins is inexpensive insurance.
Garage Safety
Idling a car in an attached garage, even briefly and even with the garage door fully open, lets CO diffuse through door frames and shared walls into the living space. Backing the car out immediately after starting it keeps that time short. If the garage is directly connected to the home, installing a CO detector inside the home adjacent to the connecting door provides early warning of CO entry.
Grill Safety
Charcoal and propane grills are outdoor-only appliances: in a garage, carport, screened porch, or tent, including during rain, they expose the people inside to CO. Charcoal grills are particularly dangerous because they continue producing CO long after visible flames subside and charcoal appears spent.
Boat Safety
The US Coast Guard's boating safety program tells boaters to install and maintain CO alarms inside the boat. Exhaust ports positioned and directed away from swim platforms, cockpits, and any area where people congregate reduce exposure. The program also warns: "Never sit, teak surf, or hang on the back deck or swim platform while the engines are running," and describes keeping everyone away from engine and generator exhaust outlets.
Occupational Safety
Firefighters use SCBA when entering any potentially CO-containing atmosphere. In foundries, parking structures, metal-working facilities, and other high-exposure workplaces, the safeguard is continuous ambient CO monitoring with audible alarms. Post-exposure COHb testing is a part of occupational health protocols for symptomatic workers.
After Any Significant Exposure
After any CO poisoning event, the danger remains until the building has been professionally inspected and the CO source identified and corrected. Fire departments and utilities typically provide free CO source investigation following a poisoning incident. A falling CO detector level alone does not show the building is safe, because the underlying cause is still there until it is found and fixed.
Key Research Papers
The following peer-reviewed studies underpin current understanding of CO poisoning pathophysiology, diagnosis, and treatment.
- Weaver LK, Hopkins RO, Chan KJ, et al. Hyperbaric oxygen for acute carbon monoxide poisoning. N Engl J Med. 2002;347(14):1057–1067. — PubMed PMID: 12362006
- Raub JA, Mathieu-Nolf M, Hampson NB, Thom SR. Carbon monoxide poisoning — a public health perspective. Toxicology. 2000;145(1):1–14. — PubMed PMID: 10771127
- Thom SR. Hyperbaric oxygen: its mechanisms and efficacy. Plast Reconstr Surg. 2011;127 Suppl 1:131S–141S. — PubMed PMID: 21200283
- Hampson NB, Piantadosi CA, Thom SR, Weaver LK. Practice recommendations in the diagnosis, management, and prevention of carbon monoxide poisoning. Am J Respir Crit Care Med. 2012;186(11):1095–1101. — PubMed PMID: 23087025
- Miro O, Casademont J, Barrientos A, Urbano-Márquez A, Cardellach F. Mitochondrial cytochrome c oxidase inhibition during acute carbon monoxide poisoning. Pharmacol Toxicol. 1998;82(4):199–202. — PubMed PMID: 9584335
- Kao LW, Nañagas KA. Carbon monoxide poisoning. Emerg Med Clin North Am. 2004;22(4):985–1018. — PubMed PMID: 15474779
- Scheinkestel CD, Bailey M, Myles PS, et al. Hyperbaric or normobaric oxygen for acute carbon monoxide poisoning: a randomised controlled clinical trial. Med J Aust. 1999;170(5):203–210. — PubMed PMID: 10092916
- Hampson NB, Hauff NM. Carboxyhemoglobin levels in carbon monoxide poisoning: do they correlate with the clinical picture? Am J Emerg Med. 2008;26(6):665–669. — PubMed PMID: 18606318
- Rose JJ, Wang L, Xu Q, et al. Carbon monoxide poisoning: pathogenesis, management, and future directions of therapy. Am J Respir Crit Care Med. 2017;195(5):596–606. — PubMed PMID: 27753502
- Annane D, Chadda K, Gajdos P, Jars-Guincestre MC, Chevret S, Raphael JC. Hyperbaric oxygen therapy for acute domestic carbon monoxide poisoning: two randomized controlled trials. Intensive Care Med. 2011;37(3):486–492. — PubMed PMID: 21125215
- Wolf SJ, Lavonas EJ, Sloan EP, Jagoda AS; American College of Emergency Physicians. Critical issues in the management of adult patients presenting to the emergency department with acute carbon monoxide poisoning. Ann Emerg Med. 2008;51(2):138–152. — PubMed PMID: 18206551
- Hampson NB, Weaver LK. Carbon monoxide poisoning: a new incidence for an old disease. Undersea Hyperb Med. 2007;34(3):163–168. — PubMed PMID: 17672172
- Touger M, Gallagher EJ, Tyrell J. Relationship between venous and arterial carboxyhemoglobin levels in patients with suspected carbon monoxide poisoning. Ann Emerg Med. 1995;25(4):481–483. — PubMed PMID: 7710152
- Touger M, Birnbaum A, Wang J, Chou K, Pearson D, Bijur P. Performance of the RAD-57 pulse CO-oximeter compared with standard laboratory carboxyhemoglobin measurement. Ann Emerg Med. 2010;56(4):382–388. — PubMed PMID: 20605259
- Choi IS. Delayed neurologic sequelae in carbon monoxide intoxication. Arch Neurol. 1983;40(7):433–435. — PubMed PMID: 6860181
- Gur I, Safrai A, Nov Y. The effects of hyperbaric oxygen dosing on the delayed neuropsychiatric sequalae of carbon monoxide poisoning. Clin Toxicol (Phila). 2026;64(10):888–896. — PubMed PMID: 42148903
- Iqbal S, Clower JH, Hernandez SA, Damon SA, Yip FY. A review of disaster-related carbon monoxide poisoning: surveillance, epidemiology, and opportunities for prevention. Am J Public Health. 2012;102(10):1957–1963. — PubMed PMID: 22897556
- Falise AM, Griffin I, Fernandez D, Rodriguez X, Moore E, Barrera A, Suarez J, Cutie L, Zhang G. Carbon Monoxide Poisoning in Miami-Dade County Following Hurricane Irma in 2017. Disaster Med Public Health Prep. 2019;13(1):94–96. — PubMed PMID: 30012229
- Buckley NA, Juurlink DN, Isbister G, Bennett MH, Lavonas EJ. Hyperbaric oxygen for carbon monoxide poisoning. Cochrane Database Syst Rev. 2011;2011(4):CD002041. — PubMed PMID: 21491385
- Fujita M, Todani M, Ajimi Y, Yatabe T, Yokobori S, Araki M, Chihara N, Nagayama M, Sakamoto T, Tsuruta R; Japan Resuscitation Council (JRC) Neuroresuscitation Task Force and the Guidelines Editorial Committee. Evaluating the Efficacy of Hyperbaric Oxygen Therapy for Acute Carbon Monoxide Poisoning: A Systematic Review and Meta-Analysis. Acute Med Surg. 2026;13(1):e70114. — PubMed PMID: 41624627
- Ran T, Nurmagambetov T, Sircar K. Economic implications of unintentional carbon monoxide poisoning in the United States and the cost and benefit of CO detectors. Am J Emerg Med. 2018;36(3):414–419. — PubMed PMID: 28888530
- Shin M, Bronstein AC, Glidden E, Malone M, Chang A, Law R, Boehmer TK, Strosnider H, Yip F. Morbidity and Mortality of Unintentional Carbon Monoxide Poisoning: United States 2005 to 2018. Ann Emerg Med. 2023;81(3):309–317. — PubMed PMID: 36585319
- Henry CR, Satran D, Lindgren B, Adkinson C, Nicholson CI, Henry TD. Myocardial injury and long-term mortality following moderate to severe carbon monoxide poisoning. JAMA. 2006;295(4):398–402. — PubMed PMID: 16434630
For additional literature, search PubMed: carbon monoxide poisoning hyperbaric oxygen carboxyhemoglobin delayed neurological sequelae carbon monoxide pulse oximetry diagnosis
Connections
- Pulmonology
- Acute Respiratory Distress Syndrome (ARDS)
- Cardiology: Cardiac Complications
- Neurology: Brain Injury and Neurological Disease
- Addiction and Overdose
- Carbon Monoxide — the toxin page: sources, detectors, exposure limits.
- Chemical and Environmental Toxins
- Air Pollution and Lung Disease
- Rhabdomyolysis (CO can trigger muscle breakdown)
- Laboratory Tests and Diagnostics