⚠ Evidence warning: Clinical trials or other evidence do not support the claim that oral atropine works as well as surgery for pyloric stenosis. This page keeps it as a report of what people, websites or other media say.
Pyloric Stenosis (Hypertrophic Pyloric Stenosis)
- Overview and Epidemiology
- Pathophysiology
- Clinical Presentation
- The Classic Electrolyte Derangement
- Diagnosis — Ultrasound and Beyond
- Differential Diagnosis of Infant Vomiting
- Pre-operative Resuscitation
- Ramstedt Pyloromyotomy
- Post-operative Care and Outcomes
- Key Research Papers
- Connections
Overview and Epidemiology
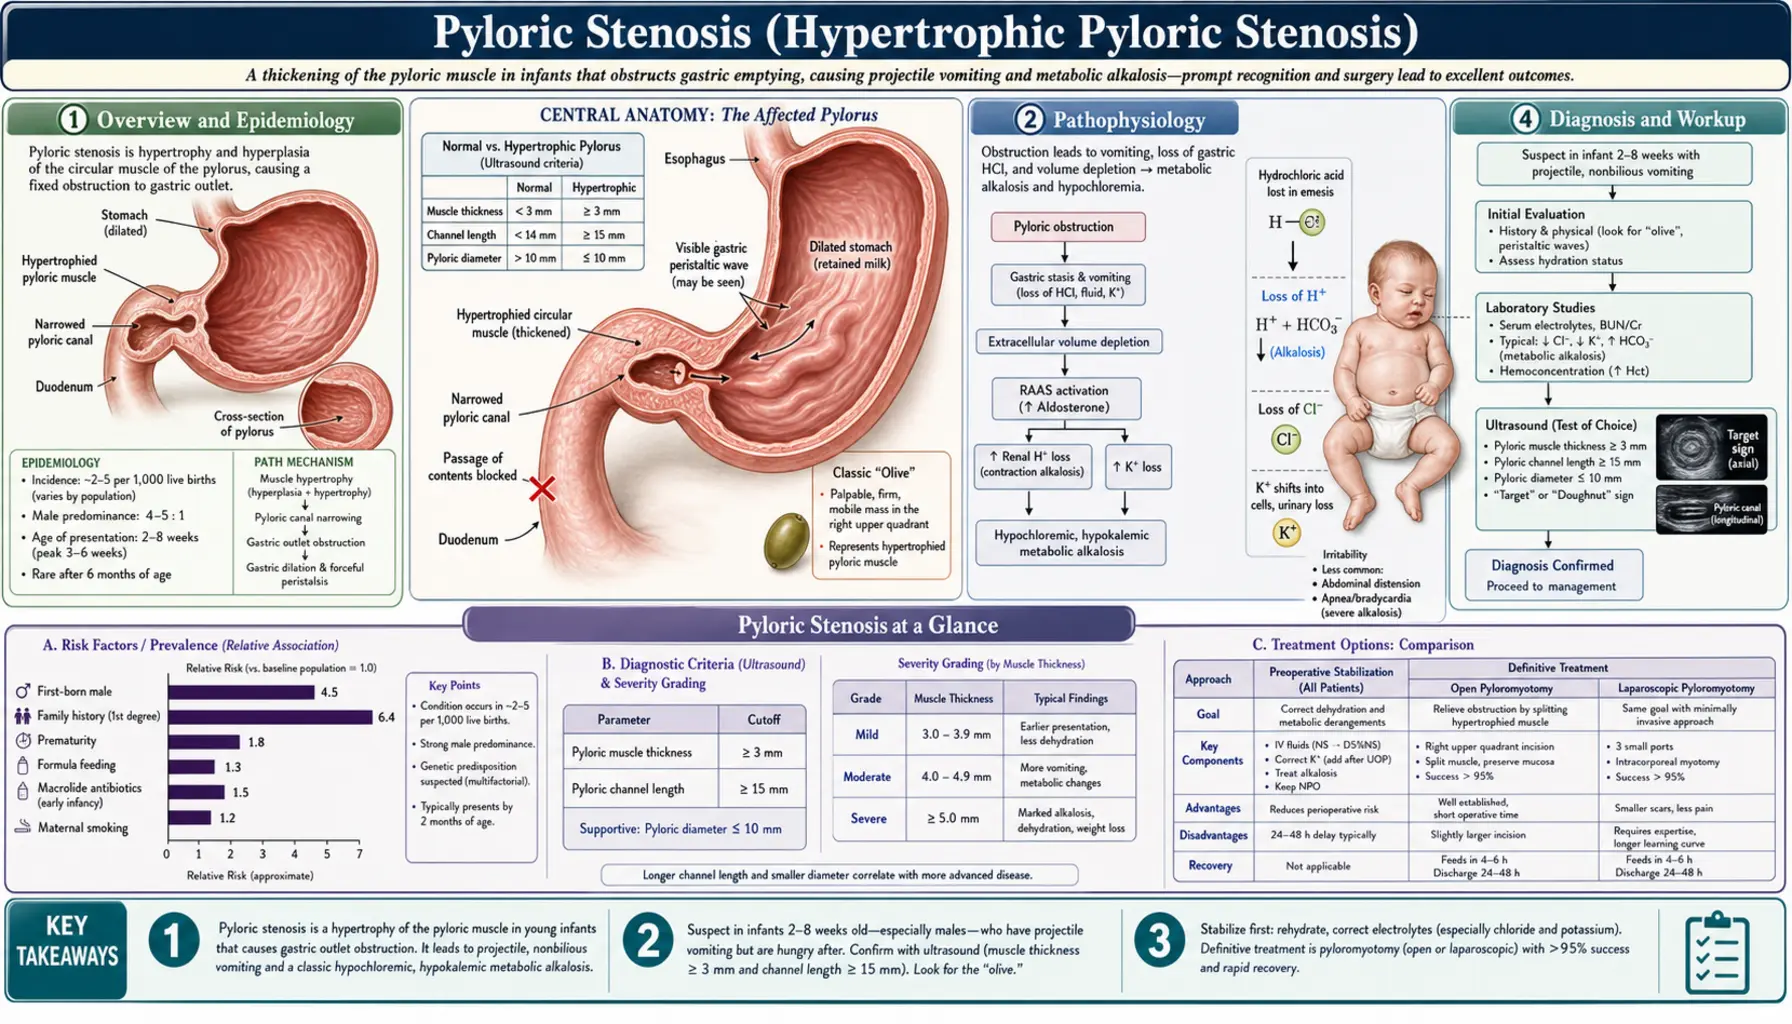
Hypertrophic pyloric stenosis (HPS) is the most common surgical cause of vomiting in infancy and one of the most common conditions requiring surgery in the first few months of life. It occurs when the muscular wall of the pylorus — the short canal connecting the stomach to the duodenum — undergoes progressive hypertrophy, narrowing the outlet until the stomach cannot empty effectively.
Incidence in Western populations is approximately 2–4 per 1,000 live births, though this varies substantially by ethnicity: rates are higher in White Northern European populations and lower in Black and Asian populations. There is a striking 4:1 male predominance, with boys affected far more often than girls. The reasons for this sex bias are incompletely understood but likely involve androgen-dependent effects on pyloric smooth muscle.
The condition presents between 2 and 8 weeks of age (onset before 2 weeks or after 12 weeks is rare). First-born males are at highest risk — first-born males have approximately twice the risk of later-born males. The reason for birth-order effect is unclear; altered gut microbiome from first-time breastfeeding, different feeding practices with first children, and subtle genetic interactions have all been proposed.
Other established risk factors include:
- Family history: figures often quoted in reference texts say that if the mother had HPS, her son has a ~20% risk and her daughter ~7%; if the father had HPS, risk is ~5% for a son and ~2.5% for a daughter, read as a sign of multifactorial genetic inheritance. A 2010 Danish cohort of 1,999,738 children found no difference in rate ratios between maternal and paternal relatives, or by sex. Its rate ratios were 182 for identical twins, 29.4 for fraternal twins and 18.5 for siblings
- Macrolide antibiotic exposure: erythromycin by mouth in the first 2 weeks of life (given to prevent whooping cough, or pertussis, or to treat chlamydial conjunctivitis) raises HPS risk: a relative risk of 10.51 in a 2001 cohort, 6.8 in a 1999 hospital cluster, and an adjusted odds ratio of 13.3 in a 2015 military health cohort. Azithromycin carries a lower but still elevated risk in that 2015 cohort (adjusted odds ratio 8.26 in the first 14 days). At 15–42 days of life the figures were 4.10 for erythromycin and 2.98 for azithromycin, with no link at 43–90 days. Erythromycin eye ointment was not linked to HPS in the 2001 cohort. The mechanism involves the motilin-receptor agonist properties of macrolides, which cause intense pyloric contractions
- Bottle-feeding: in the Danish National Birth Cohort of 70,148 infants, bottle-fed infants had a 4.6-fold higher risk than infants not bottle-fed (hazard ratio 4.62, 95% confidence interval 2.78–7.65), though many exclusively breastfed infants develop HPS
Since its first description by Harald Hirschsprung in 1888 and the development of Ramstedt's curative pyloromyotomy in 1912, pyloric stenosis has gone from a frequently fatal condition to one with essentially zero mortality in high-resource settings with prompt diagnosis and appropriate surgical care.
Pathophysiology
The pyloric channel normally measures 2–3 mm in muscle wall thickness and approximately 12–14 mm in length in a newborn. In HPS, the circular and longitudinal muscle layers of the pylorus undergo progressive hypertrophy and hyperplasia, thickening the muscle wall and elongating the canal until it resembles a firm, white, olive-shaped mass. The lumen narrows to a pinhole that cannot pass food.
The trigger for this aberrant muscle growth remains unclear despite decades of research. Current evidence points to an interstitial cell of Cajal (ICC) deficiency. ICCs are the pacemaker cells of the gut that coordinate smooth muscle contractions; they are markedly reduced in the hypertrophied pylorus of HPS. Without normal ICC-mediated relaxation signals, the pyloric muscle remains in a state of persistent partial contraction, and the mechanical stress of peristaltic contractions against this non-relaxing outlet drives further hypertrophy in a self-reinforcing cycle.
Neuronal nitric oxide synthase (nNOS) is another key player. nNOS-expressing neurons in the myenteric plexus normally release nitric oxide to relax smooth muscle. HPS pylori show marked reduction in nNOS neurons. Without nitric oxide-mediated relaxation, pyloric smooth muscle tone is exaggerated. This finding also explains why pharmacological approaches (atropine, which blocks acetylcholine-mediated contraction) have had limited success — the fundamental problem is not excessive excitation but loss of inhibitory relaxation.
Genetic studies have identified several susceptibility loci including regions on chromosomes 11q14-22, MBNL1, and EML4. The condition likely results from the interaction of multiple genes and environmental triggers rather than a single-gene defect. The concordance rate in monozygotic twins is 25–40%, confirming that environmental factors modify genetic risk. Heritability is high: 87% in the 2010 study of nearly two million Danish children. A genome-wide study of 1,001 Danish cases and 2,401 controls, with a second replication set, linked the condition to common gene variants near MBNL1 and NKX2-5, a gene involved in embryonic gut development.
Because the obstruction is at the pylorus (distal to the stomach, before the duodenum), the vomited material is entirely gastric — no bile, no duodenal contents. This is the defining clinical feature: non-bilious vomiting. Any vomiting with bile (green) in an infant suggests a more distal obstruction (malrotation, duodenal atresia) and is a surgical emergency.
Clinical Presentation
The presentation of pyloric stenosis has a classic trajectory that becomes more recognizable once understood. Parents typically describe a baby who was feeding normally for the first few weeks of life, then began vomiting, with the vomiting progressively worsening over 1–2 weeks until it is occurring with every feed.
The cardinal feature is projectile non-bilious vomiting:
- Non-bilious — clear, white, or curdled — never green. The obstruction is proximal to the ampulla of Vater where bile enters the bowel.
- Projectile — forceful, often shooting several feet across the room; this reflects the powerful peristaltic contractions of a hypertrophied stomach attempting to force milk through the narrowed pyloric channel. Not all cases are dramatically projectile early in the course, and parents may initially describe "spit-up" that progressively worsens.
- Post-vomiting hunger — the infant typically feeds eagerly immediately after vomiting ("hungry vomiter"). This distinguishes HPS from other causes of vomiting in infants; a baby who vomits and then does not want to feed suggests a different pathology.
Physical examination findings:
- Visible gastric peristalsis — waves of peristalsis visible through the thin abdominal wall moving from left to right across the upper abdomen. This occurs because the stomach is vigorously contracting against the obstructed pylorus. Elicited by feeding the infant during examination.
- Palpable pyloric mass ("olive") — a firm, smooth, 1.5–2 cm oval mass in the right epigastrium or right upper quadrant, palpated most easily after vomiting when the stomach is empty and the infant is relaxed. This is the hypertrophied pylorus. Requires an experienced examiner; best palpated after a test feed that empties by vomiting. In the ultrasound era, the olive is sought less aggressively but remains a useful finding when present.
- Signs of dehydration: sunken fontanelle, dry mucous membranes, decreased skin turgor, decreased wet diapers
- Weight loss or failure to gain weight appropriate to age
- Jaundice — some infants with HPS develop jaundice from raised unconjugated bilirubin ("icteropyloric syndrome"). Older accounts give approximately 5%; a 2005 series found 14.3%. It is attributed to caloric deprivation reducing hepatic glucuronosyltransferase activity, the liver enzyme that processes bilirubin. In the 2005 series a gene change behind Gilbert syndrome (UGT1A1*28) was 4-fold more common in the jaundiced infants (43.8% vs 10.7%), and a 1999 report of three patients also linked the jaundice to this gene. It resolves promptly after successful surgery.
The Classic Electrolyte Derangement
The metabolic consequence of repeated vomiting in HPS is one of the most elegant examples of physiology in clinical medicine: hypochloremic hypokalemic metabolic alkalosis. Understanding it mechanistically (not by rote memorization) allows confident prediction and management.
Step 1 — Losing gastric contents. Every vomit ejects gastric juice, which is rich in hydrochloric acid (HCl). Each molecule of HCl lost removes one H⁺ and one Cl⁻ from the body. Serum chloride falls. The loss of H⁺ means less acid in the blood — bicarbonate accumulates and pH rises: metabolic alkalosis.
Step 2 — The kidney's initial response. As metabolic alkalosis develops, the kidney attempts to correct the pH by excreting bicarbonate. Bicarbonate exits in the urine as NaHCO₃, pulling sodium with it. Urine is alkaline at this stage.
Step 3 — Volume depletion takes priority. As vomiting continues, the infant becomes volume-depleted. The kidney now has a competing priority: preserve sodium and water (via the renin-angiotensin-aldosterone system, RAAS). Aldosterone secretion rises, directing the kidney to retain sodium. But aldosterone drives a Na⁺/K⁺ exchange in the collecting duct — to retain one Na⁺, the kidney excretes one K⁺. Hypokalemia develops.
Step 4 — Paradoxical aciduria. As potassium becomes depleted, the Na⁺/K⁺ exchange in the collecting duct cannot be sustained. The kidney shifts to a Na⁺/H⁺ exchange instead — excreting H⁺ to preserve Na⁺, even though the body is alkalotic. The urine becomes acidic despite systemic alkalosis: paradoxical aciduria. This is a late finding indicating severe depletion and immediate need for fluid resuscitation.
Summary of the typical blood gas and electrolyte pattern in HPS:
| Parameter | Direction | Typical value (moderate depletion) |
|---|---|---|
| pH | High | 7.50–7.60 |
| Bicarbonate (HCO₃) | High | 28–40 mEq/L |
| Chloride (Cl⁻) | Low | 85–95 mEq/L (normal 98–106) |
| Potassium (K⁺) | Low | 3.0–3.5 mEq/L |
| Sodium (Na⁺) | Low-normal | 130–140 mEq/L |
| Urine pH | Paradoxically low | <6.0 in severe depletion |
The key clinical principle: the urgent part is correcting the fluids and salts; the operation is not an emergency and waits until the metabolic derangement is corrected. Anesthesia in the setting of severe alkalosis carries serious risks (cardiac arrhythmias, impaired ventilator weaning, laryngospasm at extubation). Safe anesthesia requires a bicarbonate below approximately 26–30 mEq/L, normochloremia, and normokalemia.
Diagnosis — Ultrasound and Beyond
Ultrasound has replaced clinical examination as the primary diagnostic tool since the 1980s and is now considered the gold-standard investigation for suspected HPS.
Ultrasound criteria for HPS (Teele and Share, validated across multiple studies):
- Pyloric muscle thickness >4 mm — the most sensitive individual criterion; measures the echogenic circular muscle layer on transverse view
- Pyloric channel length >17 mm — measured in longitudinal section from gastric antrum to duodenum
- Pyloric transverse diameter >13–14 mm
When both muscle thickness >4 mm and channel length >17 mm are met, ultrasound has sensitivity >97% and specificity approaching 100% for HPS. Findings are confirmed by observing absence of flow through the pyloric channel during real-time scanning: the stomach fills, contracts vigorously, but gastric contents cannot pass into the duodenum.
What ultrasound cannot always tell: In the first 2–3 weeks of the clinical course, the pylorus may not yet meet full criteria even if HPS is the underlying diagnosis. A borderline ultrasound in a child with classic symptoms is commonly followed by a repeat study in 24–48 hours or discussion with a pediatric surgeon.
Upper gastrointestinal (GI) contrast series (barium/water-soluble contrast): Largely replaced by ultrasound but still used in some centers or when ultrasound is equivocal. Classic findings include the "string sign" (thin line of contrast squeezed through the elongated pyloric channel), the "double-track sign" (parallel tracks of contrast separated by the hypertrophied pyloric ridges), and the "shoulder sign" (pyloric muscle bulging into the gastric antrum).
Investigations at presentation usually also include: electrolytes (sodium, potassium, chloride, bicarbonate), blood gas (venous acceptable), serum glucose, full blood count (assess for anemia), and urinalysis.
Differential Diagnosis of Infant Vomiting
Non-bilious vomiting in a young infant has a broad differential. The combination of age, vomiting character, clinical findings, and ultrasound differentiates HPS from alternatives.
| Condition | Age | Vomit character | Key differentiating features |
|---|---|---|---|
| Pyloric stenosis (HPS) | 2–8 weeks | Non-bilious, projectile | Hungry after vomiting; palpable olive; ultrasound confirms |
| Gastro-oesophageal reflux (GOR) | Any infant age | Non-bilious, effortless ("happy spitter") | Not projectile; not hungry after; no weight loss; resolves with positioning/feeds |
| Overfeeding | Any infant age | Non-bilious | Excessive feed volumes; no distress; thriving; resolve with volume reduction |
| Malrotation with midgut volvulus | Any age (often <1 month) | Bilious | SURGICAL EMERGENCY; bile = red flag; abdominal distension; shock |
| Duodenal atresia / web | Newborn period | Bilious (post-ampullary) or non-bilious (pre-ampullary) | Often diagnosed antenatally; "double bubble" on X-ray |
| Pyloric atresia | Newborn | Non-bilious | Rare; gasless abdomen; complete obstruction from birth |
| Congenital adrenal hyperplasia (salt-wasting) | 2–4 weeks | Non-bilious | Hyponatremia + hyperkalemia (opposite of HPS); ambiguous genitalia in girls; adrenal crisis |
| Pyloric spasm | 2–8 weeks | Non-bilious | Ultrasound shows normal pyloric dimensions but functional spasm; may respond to atropine |
| Sepsis / meningitis | Any neonatal age | Non-bilious | Ill-appearing; temperature instability; bulging fontanelle; cerebrospinal fluid (CSF) abnormal |
Critical rule: bilious vomiting in any infant is a surgical emergency until proven otherwise. Malrotation with midgut volvulus can infarct the entire midgut in hours. Hospitals treat bilious (green) vomiting in an infant as urgent for surgeons, regardless of how well the infant appears.
Pre-operative Resuscitation
Pyloric stenosis is not an emergency operation. There is no benefit to rushing to theater before the metabolic derangement is corrected; significant harm can result from anesthetizing a severely alkalotic, hypokalemic infant. The sequence surgical reviews describe is: stabilize, correct, then operate.
Fluid resuscitation protocol:
- Oral feeds stop — a nasogastric tube is passed and any residual gastric contents are drawn off to prevent aspiration. The tube is left on free drainage to decompress the stomach.
- Initial bolus — for signs of haemodynamic compromise (poor perfusion, tachycardia): 10–20 mL/kg isotonic saline (0.9% NaCl) over 30–60 minutes. This expands circulating volume. Most infants with HPS are volume-depleted but not in shock.
- Maintenance and replacement fluids — after initial resuscitation, the usual fluid is 0.45% NaCl + 5% dextrose + 20–40 mEq/L KCl at 1.5 times maintenance. The chloride load corrects the hypochloremia and allows the kidney to excrete bicarbonate (once chloride is available, the kidney can finally reabsorb chloride instead of bicarbonate). Potassium supplementation corrects hypokalemia.
- Monitoring — electrolytes are measured every 4–6 hours and the blood gas is repeated. The biochemical targets before anesthesia are:
- Serum bicarbonate <30 mEq/L (ideally <26)
- Chloride >95 mEq/L
- Potassium >3.5 mEq/L
- Adequate urine output (>1 mL/kg/hr)
Most infants reach these targets within 24–48 hours of appropriate resuscitation. Severe derangements may require 72 hours. There is no value in operating sooner.
Ramstedt Pyloromyotomy
The Ramstedt pyloromyotomy, first performed by Conrad Ramstedt in 1912, remains the definitive curative treatment for HPS more than 110 years after its introduction. The operation is elegant in its simplicity: divide the hypertrophied pyloric muscle longitudinally without entering the mucosa, allowing the pyloric channel to spring open.
Surgical technique: Under general anesthesia, the pylorus is delivered through a right upper quadrant transverse incision (open approach) or through 3 laparoscopic ports (laparoscopic approach). The hypertrophied pyloric muscle is incised longitudinally with a knife or diathermy from the gastric antrum to the duodenum. The incision is deepened through the full thickness of the muscle, and the fibers are bluntly separated to allow the pyloric mucosa to bulge upward through the gap. A successful myotomy shows the mucosa clearly visible in the base of the divided muscle, with no resistance to spreading, and inflation of the stomach with air via nasogastric tube confirms no mucosal perforation.
Laparoscopic vs open pyloromyotomy: Multiple randomized controlled trials and meta-analyses have compared the two approaches. Laparoscopic pyloromyotomy offers:
- Smaller incisions and improved cosmesis
- Faster return to full feeds (by approximately 4–8 hours) and shorter hospital stay (by approximately half a day) in some studies
- Equivalent safety profile
A double-blind multicentre randomized trial of 180 infants reported a median time to full feeds of 23.9 hours after open surgery and 18.5 hours after laparoscopic (keyhole) surgery, and a median stay after surgery of 43.8 versus 33.6 hours, with similar vomiting and complications. A 2012 meta-analysis of 4 randomized trials (502 infants) found major complications in 4.9% of the laparoscopic group, not significantly more than with open surgery, and a time to full feeds about 2 hours shorter (mean difference 2.27 hours).
In experienced hands, both approaches have essentially identical outcomes and complication rates. The choice depends on surgeon expertise — a laparoscopic pyloromyotomy in inexperienced hands has a higher mucosal perforation rate than an open procedure by a skilled surgeon. The 2012 meta-analysis authors write that the laparoscopic procedure "should preferably be performed in centers with pediatric surgeons with expertise in this procedure."
Complications of pyloromyotomy (overall complication rate <5% in experienced centers):
- Mucosal perforation (0.5–2%) — most common serious complication; recognized and repaired immediately; requires a second myotomy site on the anterior wall of the pylorus
- Incomplete myotomy (<1%) — insufficient muscle division leaving residual obstruction; requires repeat operation if vomiting persists beyond 48–72 hours post-operatively
- Wound infection — more common with open approach
Medical (non-surgical) alternative: Oral atropine sulfate has been used in Japan and some European centers as an alternative to surgery, particularly in infants with cardiac contraindications to anesthesia. Atropine relaxes pyloric smooth muscle by blocking muscarinic acetylcholine receptors. Some accounts describe oral atropine as non-inferior to surgery in achieving symptom resolution, with 87% of atropine-treated infants symptom-free at 3 months vs 96% for surgery; no published study with those figures could be traced. A 2018 meta-analysis found no prospective or randomized studies. Across 12 reports (508 infants), atropine resolved HPS in 402 infants (79.1%), and side effects were documented in 38 of 251 infants (15.1%): fast heartbeat, raised liver enzymes and flushed skin. In five comparative studies, pyloromyotomy succeeded in 100% and atropine in 80.8%, with hospital stays of 5.6 and 10.3 days. Those authors found "no evidence-based literature to support atropine treatment" and write that it is for infants unfit for general anesthesia or surgery. A 2016 meta-analysis reported benefit in 77 of 110 infants (70%) on oral atropine and 288 of 345 (83.5%) on intravenous then oral atropine, and called it a possible alternative, particularly in infants with major concurrent disease. However, atropine requires 3 weeks of treatment, prolonged hospitalization in some protocols, and a significantly longer time to cure. It is not standard of care in North American or UK practice but is described as an option for selected patients.
Post-operative Care and Outcomes
Recovery from Ramstedt pyloromyotomy is rapid. The pyloric muscle heals over 2–4 weeks, but after successful surgery the pyloric channel is permanently widened and the condition does not recur.
Post-operative feeding: Most protocols allow small feeds of breast milk or formula to begin 4–6 hours after surgery, with volumes progressively increased over 24 hours to full feeds. Some centers use an ad lib demand-feeding approach from 3–4 hours post-op. Post-operative vomiting is common in the first 24–48 hours and is not by itself a sign of a problem — the stomach has adapted to persistent obstruction and takes time to normalize its motility and size. Surgical teams tell parents that some vomiting in the first few days after surgery is normal and does not indicate a complication.
Hospital stay: Most infants are discharged 24–48 hours after surgery, once tolerating full feeds. Some centers achieve same-day or next-day discharge in uncomplicated cases.
Breastfeeding: Hospitals commonly support mothers to continue breastfeeding and to pump during the nil-by-mouth period and the initial restricted-feed phase to maintain milk supply. Breastfeeding success rates are high after HPS surgery when proactively supported.
Long-term outcomes are excellent. There is no increased risk of pyloric pathology in adulthood. Gastrointestinal function is normal. Growth and development proceed normally after recovery from the episode of acute illness. Multiple long-term follow-up studies (up to 45 years) have found no increased rates of peptic ulcer disease, gastro-oesophageal reflux, or functional gastrointestinal disorders compared to the general population.
The mortality rate for HPS in high-resource settings is effectively zero when diagnosed and managed appropriately. Deaths, when they occur, result from delayed diagnosis leading to severe malnutrition and electrolyte derangement or from aspiration during anesthesia — both preventable with timely recognition and adequate pre-operative resuscitation.
Key Research Papers
- Pandya S, Heiss K. Pyloric stenosis in pediatric surgery: an evidence-based review. Surg Clin North Am. 2012;92(3):527–539. Comprehensive surgical review covering incidence, pathophysiology, diagnosis, operative technique, and outcomes including comparative data for open vs laparoscopic approaches. — PubMed PMID: 22595707
- Teele RL, Share JC. Ultrasonography of Infants and Children. Philadelphia: W.B. Saunders; 1991. Textbook cited for the ultrasound criteria for HPS (muscle thickness >4mm, channel length >17mm). — doi:10.1056/NEJM199208273270927 (book review)
- Oomen MW, Hoekstra LT, Bakx R, Ubbink DT, Heij HA. Open versus laparoscopic pyloromyotomy for hypertrophic pyloric stenosis: a systematic review and meta-analysis focusing on major complications. Surg Endosc. 2012;26(8):2104–2110. Meta-analysis of 4 randomized trials (502 infants); major complications not significantly more common with the laparoscopic approach, time to full feeds about 2 hours shorter, hospital stay tended to be shorter. — PubMed PMID: 22350232
- Hernanz-Schulman M. Pyloric stenosis: role of imaging. Pediatr Radiol. 2009;39 Suppl 2:S134–S139. Review of imaging strategies including ultrasound and upper GI contrast series; discusses diagnostic accuracy and practical approach to equivocal ultrasounds. — PubMed PMID: 19308372
- Krogh C, Fischer TK, Skotte L, et al. Familial aggregation and heritability of pyloric stenosis. JAMA. 2010;303(23):2393–2399. Population-based Danish cohort of 1,999,738 children quantifying familial aggregation; heritability 87%, no difference by maternal or paternal relatives or by sex. — PubMed PMID: 20551410
- Mahon BE, Rosenman MB, Kleiman MB. Maternal and infant use of erythromycin and other macrolide antibiotics as risk factors for infantile hypertrophic pyloric stenosis. J Pediatr. 2001;139(3):380–384. Retrospective cohort of 14,876 infants linking systemic erythromycin to HPS, highest in the first 2 weeks of age (relative risk 10.51); no link with erythromycin eye ointment. — PubMed PMID: 11562617
- Hall NJ, Pacilli M, Eaton S, et al. Recovery after open versus laparoscopic pyloromyotomy for pyloric stenosis: a double-blind multicentre randomised controlled trial. Lancet. 2009;373(9661):390–398. Trial of 180 infants at six centres; quicker full feeds and shorter stay after laparoscopic surgery, with similar vomiting and complications. — PubMed PMID: 19155060
- Lauriti G, Cascini V, Chiesa PL, Pierro A, Zani A. Atropine treatment for hypertrophic pyloric stenosis: a systematic review and meta-analysis. Eur J Pediatr Surg. 2018;28(5):393–399. Systematic review of atropine medical treatment evidence and comparison with pyloromyotomy; no prospective or randomized studies found. — PubMed PMID: 28701002
- Jobson M, Hall NJ. Contemporary management of pyloric stenosis. Semin Pediatr Surg. 2016;25(4):219–224. Narrative review covering all aspects of HPS management including non-surgical treatment options and post-operative feeding regimens. — PubMed PMID: 27521712
- Perger L, Fuchs JR, Komidar L, Mooney DP. Impact of surgical approach on outcome in 622 consecutive pyloromyotomies at a pediatric teaching institution. J Pediatr Surg. 2009;44(11):2119–2125. Single-institution comparison of right upper quadrant, umbilical and laparoscopic approaches; length of stay did not differ, with fewer episodes of vomiting in the laparoscopic group. — PubMed PMID: 19944219
- Wu SF, Lin HY, Huang FK, et al. Efficacy of medical treatment for infantile hypertrophic pyloric stenosis: a meta-analysis. Pediatr Neonatol. 2016;57(6):515–521. Meta-analysis of 11 reports on oral and intravenous atropine, including side effects and ultrasound changes in the pyloric canal. — PubMed PMID: 27215474
- Hernanz-Schulman M, Sells LL, Ambrosino MM, Heller RM, Stein SM, Neblett WW. Hypertrophic pyloric stenosis in the infant without a palpable olive: accuracy of sonographic diagnosis. Radiology. 1994;193(3):771–776. Sonograms of 152 infants with suspected HPS: sensitivity, specificity and accuracy for surgical referral were 100%, validating ultrasound as first-line investigation. An earlier summary here gave 59% of confirmed cases with a palpable olive; that figure is not in the abstract. — PubMed PMID: 7972822
- Honein MA, Paulozzi LJ, Himelright IM, et al. Infantile hypertrophic pyloric stenosis after pertussis prophylaxis with erythromcyin: a case review and cohort study. Lancet. 1999;354(9196):2101–2105. Cluster of seven cases after neonatal erythromycin for whooping cough prevention; relative risk 6.8. — PubMed PMID: 10609814
- Eberly MD, Eide MB, Thompson JL, Nylund CM. Azithromycin in early infancy and pyloric stenosis. Pediatrics. 2015;135(3):483–488. Military health cohort of 1,074,236 children; risk with both macrolides strongest in the first 2 weeks of life. — PubMed PMID: 25687145
- Krogh C, Biggar RJ, Fischer TK, Lindholm M, Wohlfahrt J, Melbye M. Bottle-feeding and the risk of pyloric stenosis. Pediatrics. 2012;130(4):e943–e949. Danish National Birth Cohort, 70,148 singleton infants. — PubMed PMID: 22945411
- Hua L, Shi D, Bishop PR, Gosche J, May WL, Nowicki MJ. The role of UGT1A1*28 mutation in jaundiced infants with hypertrophic pyloric stenosis. Pediatr Res. 2005;58(5):881–884. Prevalence of jaundice 14.3%; Gilbert syndrome mutations in 43.8% of jaundiced infants vs 10.7%. — PubMed PMID: 16257926
- Trioche P, Chalas J, Francoual J, et al. Jaundice with hypertrophic pyloric stenosis as an early manifestation of Gilbert syndrome. Arch Dis Child. 1999;81(4):301–303. Three patients with the gene promoter polymorphism. — PubMed PMID: 10490432
- Etzioni A, Shoshani G, Diamond E, Zinder O, Bar-Maor JA. Unconjugated hyperbilirubinaemia in hypertrophic pyloric stenosis, an enigma. Z Kinderchir. 1986;41(5):272–274. Unconjugated bilirubin above 2.5 mg/dl in 4 of 11 infants. — PubMed PMID: 3788294
- Feenstra B, Geller F, Krogh C, et al. Common variants near MBNL1 and NKX2-5 are associated with infantile hypertrophic pyloric stenosis. Nat Genet. 2012;44(3):334–337. Genome-wide association study of 1,001 cases and 2,401 controls. — PubMed PMID: 22306654