Alpha-Gal Anaphylaxis Emergency Plan
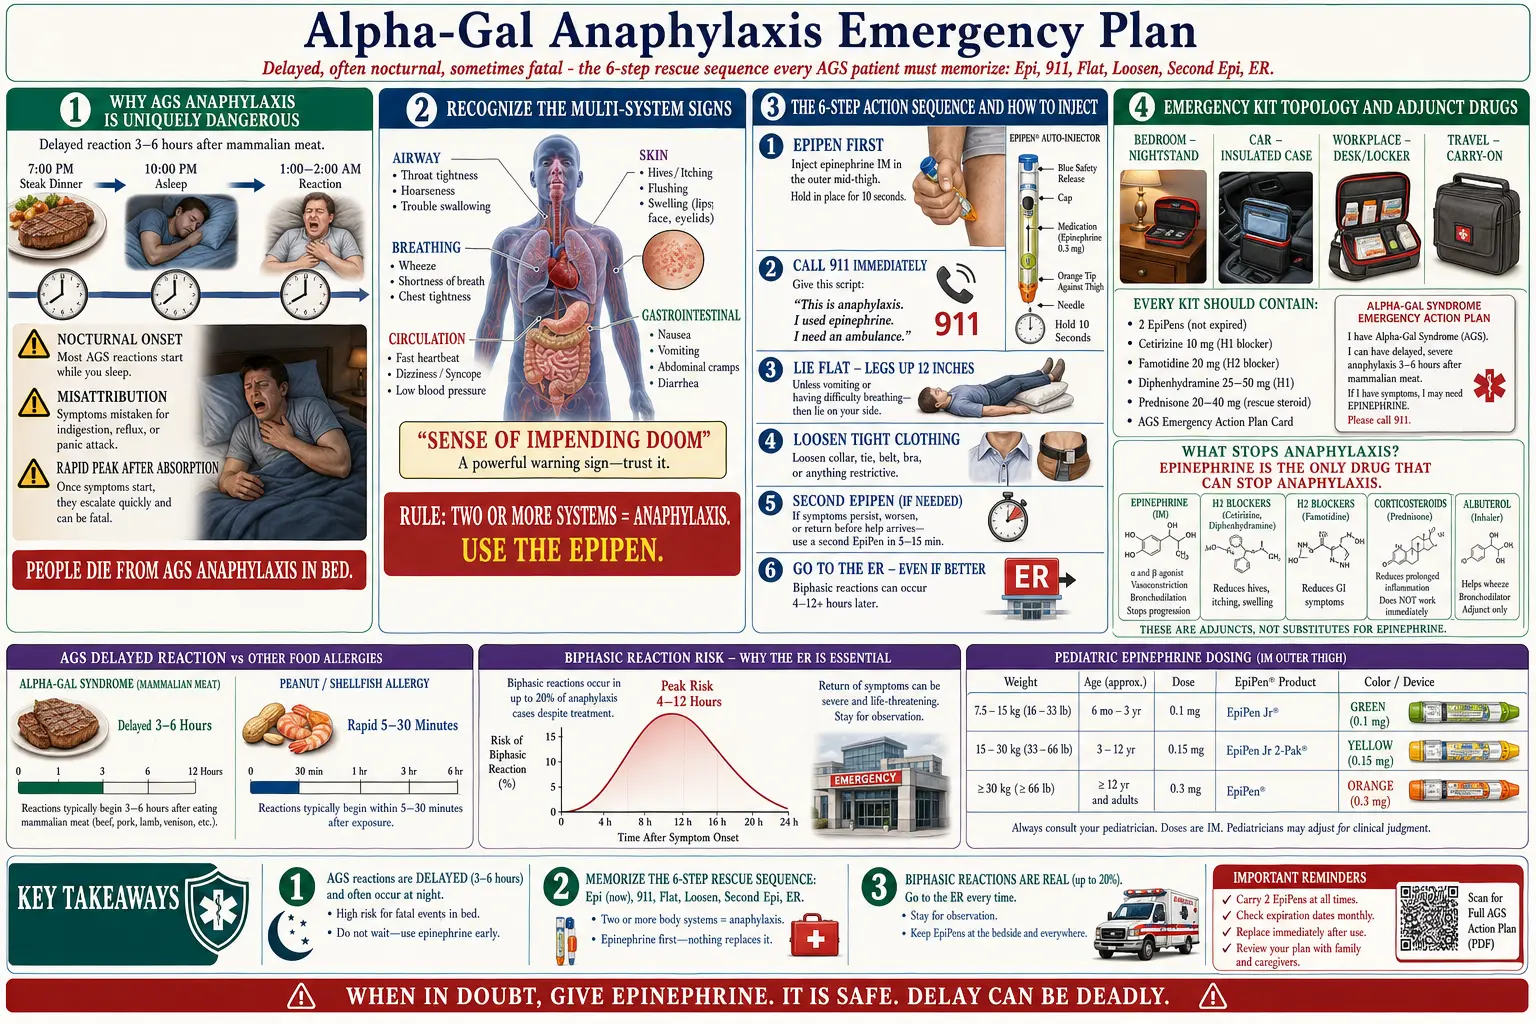
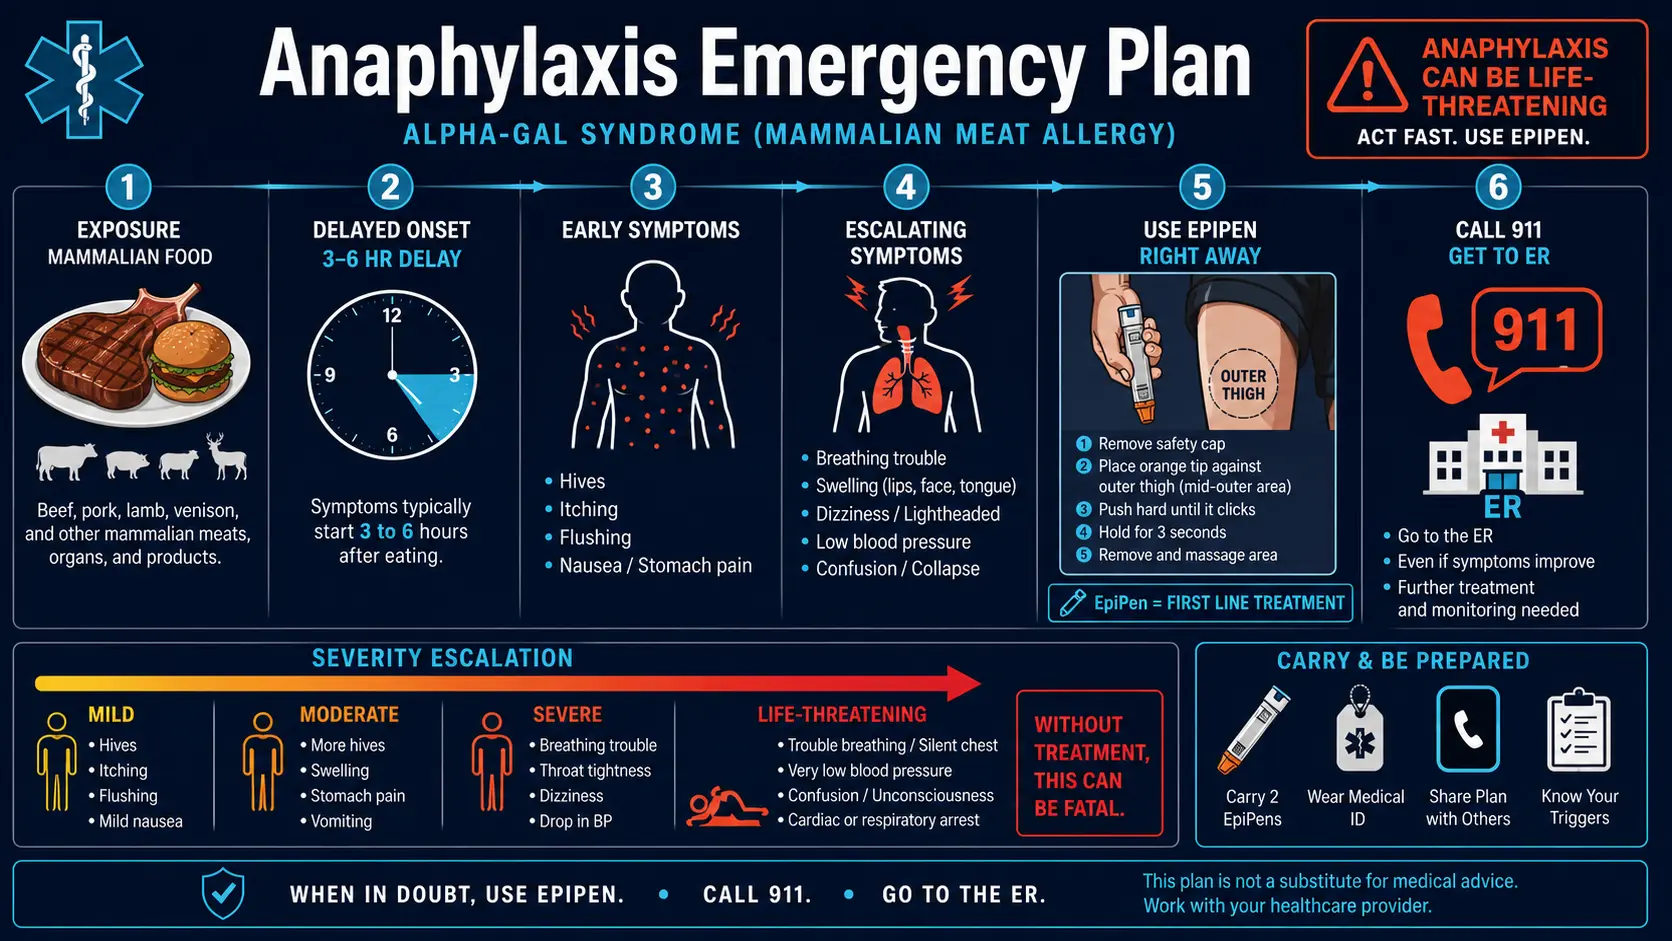
Table of Contents
- Why Alpha-Gal Syndrome (AGS) Anaphylaxis Is Uniquely Dangerous
- Recognize the Signs of Anaphylaxis
- The Emergency Action Sequence in Anaphylaxis Plans
- How an Epinephrine Auto-Injector Is Used
- The Other Tools Besides Epinephrine
- The Emergency Kit — What to Carry Where
- Auto-Injector Storage & Expiration
- Briefing Family Members, Partners, Kids
- ER Communication
- Medication Card / Wallet Template
- Biphasic Reactions — The Hidden Risk
- Triggers to Watch For Beyond Food
- After the Reaction — The Follow-Up Steps
- Contraindications to Epinephrine in Anaphylaxis
- Key Research Papers
- Connections
- Featured Videos
1. Why Alpha-Gal Syndrome (AGS) Anaphylaxis Is Uniquely Dangerous
Standard food anaphylaxis — peanut, shellfish, tree nut — hits within 5 to 30 minutes of exposure. You eat, you react, you know. The allergen and the reaction are tethered in time, and that tether is what saves lives.
Alpha-Gal Syndrome breaks that tether. Because alpha-gal is a carbohydrate bound to mammalian lipids, it has to be digested, absorbed into the lymphatic system, and transported on chylomicrons before it reaches mast cells. That process takes three to six hours, sometimes longer. You eat dinner at 7 p.m. and wake at 2 a.m. covered in hives, throat tight, heart pounding, with no obvious connection to the meal.
This delay creates three specific dangers:
- Nocturnal reactions. Many alpha-gal syndrome reactions are reported in the middle of the night. People wake up already in trouble, alone in a dark room, confused and sleep-drunk. Some never wake up. People die from alpha-gal syndrome anaphylaxis in bed.
- Misattribution. The delay makes it tempting to blame "something that didn’t agree with me." Some people take an antihistamine (diphenhydramine) and go back to sleep as airway swelling progresses.
- Rapid peak. Once symptoms start, the allergen is already fully absorbed. There is no slow build. The reaction can go from hives to airway compromise in minutes.
In a person with alpha-gal syndrome, waking in the night with hives, swelling, a racing heart, or an odd sense that something is wrong can be the start of anaphylaxis.
2. Recognize the Signs of Anaphylaxis
Anaphylaxis is not a single symptom. It is a multi-system reaction. The formal definition: two or more organ systems involved = anaphylaxis. The definition does not require a "worse" symptom; two systems are enough.
Airway
Throat tightness, voice change (hoarse, muffled, "hot potato voice"), wheezing, stridor (high-pitched inhale), difficulty swallowing, the feeling of a lump you can’t clear.
Breathing
Shortness of breath, chest tightness, persistent cough, wheezing, inability to finish a sentence in one breath.
Circulation
Rapid heart rate, dizziness on standing, lightheadedness, fainting, pale or clammy skin, cold sweats, sudden urge to defecate or vomit (vagal response to plummeting blood pressure).
Skin
Widespread hives, severe itching (especially palms, soles, scalp, groin), lip/tongue/face swelling, generalized flushing, a feeling that your skin is "on fire."
Gastrointestinal
Severe cramping, vomiting, explosive diarrhea. In alpha-gal syndrome, GI symptoms are often the first signal because the exposure happens through the gut.
Other — a sign taken seriously
A sense of impending doom. Patients describe it as "something is very wrong" or "I feel like I’m about to die." This is not anxiety. It is a documented clinical sign of anaphylaxis, mediated by catecholamine release and failing circulation. Hospitals treat it as an urgent warning sign.
Two or more systems involved = anaphylaxis, and epinephrine is its first-line treatment.
3. The Emergency Action Sequence in Anaphylaxis Plans
Written anaphylaxis action plans set out a short sequence like the one below. A printed copy can sit inside the medication kit; adrenaline makes reading hard in the moment, which is why the steps are short and practised in advance.
Step 1. Epinephrine auto-injector first.
Into the outer thigh, through clothing if needed. Current U.S. auto-injector labels say to hold it in place for at least 3 seconds (the voice-guided device’s label says 2 seconds). The 2020 practice parameter names epinephrine the first-line treatment for anaphylaxis; an antihistamine is not a substitute and comes after it, not before. Epinephrine goes in first.
Step 2. Calling 911.
Someone else can make the call. A short script gives the dispatcher what matters: "Anaphylaxis. Alpha-Gal Syndrome. Epinephrine given at [time]." The address comes first, symptoms second. For a person who is alone and whose voice is failing, a text to 911 (available in most US counties) or a speakerphone call works.
What the 2023 guideline changed. The 2023 U.S. anaphylaxis practice parameter states that if epinephrine is used promptly, immediate activation of emergency medical services "may not be required" when the person has a prompt, complete and lasting response. It also states that people prescribed auto-injectors need specific counselling and training on when and how to use them, and on whether and when to call 911 — a decision the written plan sets out in advance.
Step 3. Lying flat.
With the legs raised about 12 inches. This keeps blood in the core and protects blood flow to the brain while blood pressure drops. Exception: a person who is vomiting lies on their side (recovery position); if breathing is worse flat, sitting upright is easier.
Step 4. Loosened tight clothing.
Collar, belt, bra. Warm but not hot — a blanket, not a heating pad. Heat widens blood vessels and worsens low blood pressure.
Step 5. A second dose if symptoms persist or return after 5–15 minutes.
The second dose goes into the other thigh. A 2021 review of 86 studies (36,557 anaphylaxis events) found that about one in ten anaphylaxis reactions were treated with more than one dose of epinephrine (7.7% overall; 11.1% of food-induced reactions when the later doses were given by a health professional). Current auto-injector labels recommend that patients have immediate access to two devices at all times.
A 2024 review of the newer guidance reports that the body’s response to injected epinephrine peaks closer to 15 minutes than to 5 minutes, that few patients need a second dose because most stabilise within 15 minutes, and that the rule that everyone carry two auto-injectors at all times has lacked evidence of better outcomes.
Step 6. The emergency room (ER), even after feeling better.
Before 2023, anaphylaxis guidance sent everyone to emergency care after any epinephrine use. The 2023 practice parameter states this may not be required after a prompt, complete and lasting response, and a 2024 review reports that 60 minutes of observation after a person stabilises may be adequate. The watch is for biphasic reactions (rebound anaphylaxis): a 2015 pooled analysis of 27 studies found 192 biphasic reactions among 4,114 people with anaphylaxis, starting a median of 11 hours after the first reaction (range 0.2 to 72 hours). Alpha-gal reactions are delayed and are often reported at night, when nobody may be awake to watch.
Epi. 911. Flat. Loosen. Second Epi. ER. Six steps.
4. How an Epinephrine Auto-Injector Is Used
Most people who own auto-injectors have never used one, and when the day comes many fumble. The labels tell patients and caregivers to practise with the trainer device, which can be used many times, so the hands know the motion before it is needed.
The steps (blue-and-orange auto-injectors)
- The blue safety cap comes off first, pulled straight off. The label warns that twisting, bending or flipping it sideways can set the device off by accident. (Blue to the sky, orange to the thigh.)
- The orange end is pressed firmly into the outer thigh, mid-thigh, not hip, not groin. The labels state the device works through clothing — jeans, leggings, pajamas. It is pushed until it clicks.
- It is held in place for at least 3 seconds (count slowly 1, 2, 3), as the current labels of these auto-injectors state; the voice-guided device’s label says 2 seconds. The label warns that pulling away too early may not deliver the correct dose.
- After removal, the injection site is massaged for about 10 seconds, a step in one generic auto-injector’s instructions.
- The time is noted, even written on a hand. The ER and paramedics ask for it.
- The used pen goes along to the ER. The labels tell patients to give used auto-injectors to their healthcare provider for inspection.
Pediatric dosing
- 0.15 mg auto-injector — children 15–30 kg (roughly 33–66 lbs).
- 0.3 mg auto-injector — anyone 30 kg (about 66 lbs) or more.
- A newer 0.1 mg auto-injector is labeled for infants 7.5–15 kg.
Two-packs of the blue-and-orange auto-injectors come with a trainer device; the voice-guided device’s trainer is available on request. Running the drill with a spouse, a teenager or parents means more than one person in the house knows the motion, even when woken at night.
5. The Other Tools Besides Epinephrine
Every other medication in your emergency kit is an adjunct. None of them replaces epinephrine. None of them stops anaphylaxis. They buy time and smooth symptoms — that is all.
- H1 antihistamine — cetirizine 10 mg or diphenhydramine 50 mg. Slows hives and itching. Does not treat anaphylaxis alone. Not a substitute for epi.
- H2 antihistamine — famotidine 40 mg. Helps gastrointestinal (GI) symptoms and contributes to cardiovascular stabilization. H1 + H2 together work better than either alone.
- Oral prednisone 40–60 mg, or intravenous (IV) hydrocortisone / methylprednisolone in the ER. Onset takes hours, so it does not rescue the current episode. Steroids have been given in the hope of preventing a rebound (biphasic) reaction, but the 2020 practice parameter concluded that antihistamines and/or glucocorticoids are not reliable interventions to prevent biphasic anaphylaxis.
- Inhaled albuterol — for bronchospasm on top of epi, not instead of it.
Epinephrine is the ONLY drug that stops anaphylaxis. Everything else buys time.
6. The Emergency Kit — What to Carry Where
One kit covers one place. The lists below describe several kits, placed where reactions actually happen.
Bag (the one that goes everywhere)
- 2 epinephrine auto-injectors (the labels recommend immediate access to two at all times)
- Epinephrine trainer pen
- Medication card (see template below)
- 4 x cetirizine 10 mg
- 4 x famotidine 20 mg
- Diphenhydramine 50 mg
- Prednisone 60 mg (when prescribed by the allergist)
- Your written action plan, signed by your doctor
Bedside nightstand — critical for alpha-gal syndrome
Because many alpha-gal syndrome reactions are reported at night, the bedside kit is arguably the most important one in the house.
- Auto-injector within arm’s reach — not in a drawer, not in a closet
- Phone on the nightstand, charged
- Glass of water
- Card with "who to call" (spouse in another room, neighbor, 911)
- Medication card
Car
- Auto-injectors in an insulated medical case — the patient labels say not to store them in a vehicle’s glove box or trunk
- Spare set for long trips
- Heat damages epinephrine. The labels allow only brief excursions up to 30°C (86°F), and state that a device that has been in extreme cold or heat should be replaced.
Office / workplace
- Spare auto-injector in a labeled lockbox in the break room, where the employer allows
- Written manager briefing: what alpha-gal syndrome is, what to do, where the pen is
- At least one coworker trained on the trainer pen
7. Auto-Injector Storage & Expiration
- Room temperature. The labels state 20–25°C (68–77°F), with excursions permitted to 15–30°C (59–86°F).
- Not in a hot car. The patient labels name the glove box and the trunk as places not to store them; the dashboard in summer is hotter still. A small insulated case helps when the car is unavoidable.
- No refrigerator. The labels say not to refrigerate. Cold degrades the solution and can cause crystallization.
- No freezer. The labels say not to freeze, and that a device exposed to extreme cold is replaced.
- Protected from light. The labels state epinephrine is light sensitive and is kept in the carrier tube or case it comes in.
- Replaced before expiration. Most pens are good for 12–18 months from dispense. A calendar alarm 30 days ahead leaves time for the refill; insurance sometimes denies an early refill, and pharmacy discount cards and manufacturer coupon programs are a common backup.
- Cloudy or discolored solution = replace. The labels state the solution should be clear and colorless; pinkish or brown, cloudy, or containing particles means the device is replaced.
Generic and alternative auto-injectors
- Voice-guided auto-injector — a device that talks the user through the steps with spoken instructions, beeps and lights. It comes in 0.3 mg, 0.15 mg and 0.1 mg strengths.
- Generic epinephrine auto-injectors — U.S. Food and Drug Administration-approved equivalents, often significantly cheaper.
- The original brand-name auto-injector — the device most people picture.
- Epinephrine nasal spray — on August 9, 2024 the U.S. Food and Drug Administration approved the first epinephrine product for anaphylaxis that is not an injection: one spray into one nostril, with a second spray (from a new device) in the same nostril if symptoms do not improve or get worse. The 2024 approval covered adults and children weighing at least 30 kg (about 66 lb); in four studies in 175 healthy adults it gave blood epinephrine levels comparable to approved injections. The current label also lists a 1 mg spray for children 15 to 30 kg, and warns that nasal conditions such as nasal polyps or past nasal surgery may affect absorption. See FDA Approves the First Needle-Free Epinephrine for Anaphylaxis (2024).
The auto-injectors deliver the same fixed doses into the thigh muscle and are interchangeable clinically; the choice often comes down to which one insurance covers and which one the user has practised with.
Prefilled epinephrine syringes (non-auto-injector) are a different device. One prefilled syringe carries an FDA label for use by patients and caregivers after a healthcare provider reviews the instructions with them; other syringes and vials are hospital supplies, sometimes used as a workaround during shortages. Swapping devices without training means unfamiliar steps in an emergency.
8. Briefing Family Members, Partners, Kids
The person most likely to save your life is often the one sleeping next to you.
Spouse / partner
What a partner needs to know: where the auto-injector is, how to use it, when to call 911, the six-step sequence. Practice with the trainer pen and a spoken walk-through of a night reaction work best when calm — not during a flare, and not for the first time at 2 a.m. in the dark.
Kids
Children old enough (generally 8+) can learn:
- Where mom or dad’s auto-injector is kept
- How to dial 911 and what to say
- "If the grown-up can’t talk, push the orange end into their outer thigh and count to ten."
It works as a conversation, not a lecture, repeated every few months.
Babysitters, grandparents, visitors
A laminated one-page instruction sheet with pictures, and a practice run with the trainer pen before leaving the house, cover the basics. "A nurse in the family" may not know how to use a particular auto-injector — different device, different muscle memory.
Schools
Children with alpha-gal syndrome can qualify for a Section 504 plan, which can cover the school nurse, trained authorized staff and a spare auto-injector in the health office.
Workplace
A written note to human resources or a manager, one or two coworkers trained on the trainer pen and, where policy allows, a spare pen in a labeled break-room lockbox are the workplace measures described in the kit list above.
9. ER Communication
The ER sees hundreds of allergic reactions a year, but most staff have never managed an alpha-gal syndrome reaction specifically, so patients often have to explain the condition themselves.
At triage
A short statement gives triage what matters: "I have Alpha-Gal Syndrome. This is anaphylaxis. I received [X] dose(s) of epinephrine at [time(s)]." The medication card goes with it. Triage nurses move faster when the diagnosis is pre-packaged.
What hospital care can include
- Observation — patients have often been observed for 4–6 hours afterwards, even with no symptoms. A 2024 review of the 2023 practice parameter reports that this step has lacked evidence of better outcomes and that 60 minutes of observation after a person stabilises may be adequate. The 2020 practice parameter names a severe reaction and the need for repeated doses of epinephrine as the risk factors for a biphasic reaction, and states that patients are kept under observation until symptoms have fully resolved.
- Intravenous access, continuous cardiac monitoring, pulse oximetry.
- Intravenous corticosteroids (methylprednisolone or hydrocortisone).
- Intravenous diphenhydramine and intravenous famotidine.
- Repeat epinephrine if symptoms recur.
Cross-reactive medications the ER needs to know about
This is the part where alpha-gal syndrome patients die of preventable exposures during treatment.
- No gelatin-containing intravenous fluids or volume expanders (e.g., succinylated gelatin solution).
- No heparin (bovine or porcine-sourced). Saline flushes are the alternative and, if anticoagulation is needed, fondaparinux or a direct oral anticoagulant.
- No pancreatic enzyme products of porcine origin.
- No cetuximab — panitumumab is the alternative if oncologic therapy is relevant.
- No bovine/porcine heart valves, catgut sutures, or mammalian collagen products if a procedure is needed.
Cross-Reactive Medications has the complete list to show the ER team.
At discharge
A typed discharge summary lists what was given, when, at what dose, and the response. The allergist uses it, and so do future ER visits.
10. Medication Card / Wallet Template
A printable card: one copy for the wallet, one inside the emergency kit, one on the fridge.
ALPHA-GAL SYNDROME — EMERGENCY MEDICAL INFORMATION
I have Alpha-Gal Syndrome, an immunoglobulin E-mediated allergy to galactose-alpha-1,3-galactose, a carbohydrate present in all non-primate mammalian tissue. Reactions are delayed 3–6 hours after exposure. I may present in anaphylaxis with no obvious recent food trigger.
Avoid (do not administer): beef, pork, lamb, venison, gelatin, mammalian glycerin, heparin, porcine pancreatic enzymes, gelatin-containing intravenous fluids, cetuximab, bovine/porcine heart valves, catgut sutures, mammalian collagen products. Dairy tolerance varies — I [do / do not] react to dairy.
Safe alternatives: fondaparinux or direct oral anticoagulants (DOACs) (anticoagulation), panitumumab (in place of cetuximab), synthetic or rooster-comb hyaluronic acid, hydroxypropyl methylcellulose (HPMC, vegetable) capsules, polyester or synthetic sutures.
My allergist: ____________________, phone ______________
My pre-medication protocol for unavoidable exposures: cetirizine 10 mg + famotidine 40 mg 1 hour prior; prednisone 40 mg the night before and morning of, per my allergist.
In case of reaction: epinephrine auto-injector (outer thigh, held at least 3 seconds; a second dose if needed), 911, lie flat, ER observation until symptoms have fully resolved.
11. Biphasic Reactions — The Hidden Risk
The epinephrine works. Symptoms fade. The ER watches you for two hours. You go home, shaken but fine. Four hours later, the airway tightens again — sometimes worse than the first time.
This is a biphasic reaction: anaphylaxis symptoms that resolve with initial treatment, then return hours later without new exposure. A 2015 pooled analysis of 27 observational studies found 192 biphasic reactions among 4,114 patients with anaphylaxis. The rebound began a median of 11 hours after the first reaction, with a range from 0.2 to 72 hours. Food as the trigger carried a lower risk (pooled odds ratio 0.62); low blood pressure at the first presentation (odds ratio 2.18) and an unknown trigger (odds ratio 1.72) carried a higher one. The 2020 practice parameter names a severe reaction and the need for repeated doses of epinephrine as risk factors.
This risk is why emergency rooms have often held patients 4–6 hours, although a 2024 review reports that 60 minutes of observation after a person stabilises may be adequate. Oral steroids are often prescribed at discharge, but the 2020 practice parameter found that glucocorticoids and antihistamines are not reliable for preventing a biphasic reaction; it names epinephrine as the first-line treatment for a biphasic reaction too, which is why a fresh pair of auto-injectors goes home with the patient. The precautions described for the first day or two after discharge:
- Auto-injectors on the nightstand overnight
- Someone in the room, or at least within earshot, for the first 24 hours
- A low threshold for another dose of epinephrine at the first sign of recurrence
- Alcohol, exercise, hot showers, nonsteroidal anti-inflammatory drugs (NSAIDs) and stress kept out of the next 24–48 hours (all lower the anaphylaxis threshold)
12. Triggers to Watch For Beyond Food
Alpha-gal does not act alone. Cofactors — physiological states that raise histamine release and drop the anaphylaxis threshold — routinely turn tolerable exposures into ER visits. The phenomenon is called cofactor-induced anaphylaxis or food-dependent exercise-induced anaphylaxis.
- Exercise within 4 hours before or after a meal with mammalian content.
- Alcohol with or after the meal — vasodilation accelerates reaction kinetics.
- Nonsteroidal anti-inflammatory drugs (aspirin, ibuprofen, naproxen) increase gut permeability and lower the threshold.
- Hot showers, hot tubs, saunas — vasodilation again.
- Stress and sleep deprivation — well-documented threshold reducers.
- Menstruation in some women — hormonal fluctuation affects mast cell stability.
- Concurrent viral illness — the immune system is already primed.
When a meal is uncertain, each cofactor stacked onto the same day adds to the risk.
13. After the Reaction — The Follow-Up Steps
- An allergist follow-up within one week, sooner if the reaction was severe or required two doses.
- A written record of everything. What was eaten in the 8 hours before? Any dairy? Any hidden gelatin (gummy vitamins, marshmallows, medications)? Medications taken? Exercise? Alcohol? Sleep? Menstrual cycle? Stress? The cofactor is often the missing piece.
- Auto-injectors refilled right away, so the kit is not left with a single pen (the labels recommend immediate access to two).
- The written action plan reviewed with the doctor and updated if anything went wrong.
- Alpha-gal immunoglobulin E (IgE) retested 4–6 weeks out. Titers are reported to rise after a reaction; the result informs how strict avoidance needs to be going forward.
- Recent tick exposure counts. A new bite can re-sensitize. See Tick Bite Prevention.
14. Contraindications to Epinephrine in Anaphylaxis
Almost never.
The absolute contraindications to epinephrine are essentially none in the setting of anaphylaxis. Even patients with coronary disease, uncontrolled hypertension, or advanced age are given epinephrine when anaphylaxis is suspected — because untreated anaphylaxis is more lethal than the worst-case epinephrine side effects.
Epinephrine is the first-line treatment for anaphylaxis (2020 practice parameter).
The worst that happens with an unnecessary dose: elevated heart rate for 20–30 minutes, a tremor in the hands, a feeling of anxiety or racing thoughts, maybe a headache. All temporary. All survivable.
The worst that happens when epinephrine is delayed in real anaphylaxis: airway closure, cardiovascular collapse, death.
Withholding epinephrine in real anaphylaxis carries far more danger than giving it unnecessarily.
Key Research Papers
Foundational and recent peer-reviewed publications on anaphylaxis recognition, biphasic reactions, epinephrine auto-injector use, and the unique features of alpha-gal anaphylaxis. Author names, titles, and journals are plain text; the year/volume/issue/pages link opens the DOI.
- Lieberman P, Nicklas RA, Randolph C, Oppenheimer J, Bernstein D, Bernstein J, Ellis A, Golden DBK, Greenberger P, Kemp S, Khan D, Ledford D, Lieberman J, Metcalfe D, Nowak-Wegrzyn A, Sicherer S, Wallace D, Blessing-Moore J, Lang D, Portnoy JM, Schuller D, Spector S, Tilles SA. Anaphylaxis — A Practice Parameter Update 2015. Annals of Allergy, Asthma & Immunology. 2015;115(5):341–384. — doi:10.1016/j.anai.2015.07.019
- Sampson HA, Muñoz-Furlong A, Campbell RL, Adkinson NF Jr, Bock SA, Branum A, Brown SGA, Camargo CA Jr, Cydulka R, Galli SJ, Gidudu J, Gruchalla RS, Harlor AD Jr, Hepner DL, Lewis LM, Lieberman PL, Metcalfe DD, O'Connor R, Muraro A, Rudman A, Schmitt C, Scherrer D, Simons FER, Thomas S, Wood JP, Decker WW. Second Symposium on the Definition and Management of Anaphylaxis: Summary Report — Second National Institute of Allergy and Infectious Disease/Food Allergy and Anaphylaxis Network Symposium. Journal of Allergy and Clinical Immunology. 2006;117(2):391–397. — PubMed PMID: 16461139
- Cardona V, Ansotegui IJ, Ebisawa M, El-Gamal Y, Fernandez Rivas M, Fineman S, Geller M, Gonzalez-Estrada A, Greenberger PA, Sanchez Borges M, Senna G, Sheikh A, Tanno LK, Thong BY, Turner PJ, Worm M. World Allergy Organization Anaphylaxis Guidance 2020. World Allergy Organization Journal. 2020;13(10):100472. — doi:10.1016/j.waojou.2020.100472
- Commins SP, Satinover SM, Hosen J, Mozena J, Borish L, Lewis BD, Woodfolk JA, Platts-Mills TAE. Delayed Anaphylaxis, Angioedema, or Urticaria after Consumption of Red Meat in Patients with IgE Antibodies Specific for Galactose-α-1,3-Galactose. Journal of Allergy and Clinical Immunology. 2009;123(2):426–433. — doi:10.1016/j.jaci.2008.10.052
- Pattanaik D, Lieberman P, Lieberman J, Pongdee T, Keene AT. The Changing Face of Anaphylaxis in Adults and Adolescents. Annals of Allergy, Asthma & Immunology. 2018;121(5):594–597. — doi:10.1016/j.anai.2018.07.017
- Stone CA Jr, Commins SP, Choudhary S, Vethody C, Heavrin JL, Wingerter J, Hemler JA, Babe K, Phillips EJ, Norton AE. Anaphylaxis after Vaccination in a Pediatric Patient: Further Implicating Alpha-Gal Allergy. Journal of Allergy and Clinical Immunology: In Practice. 2019;7(1):322–324.e2. — doi:10.1016/j.jaip.2018.06.005
- Lee S, Bellolio MF, Hess EP, Erwin P, Murad MH, Campbell RL. Time of Onset and Predictors of Biphasic Anaphylactic Reactions: A Systematic Review and Meta-Analysis. Journal of Allergy and Clinical Immunology: In Practice. 2015;3(3):408–416.e1–2. — doi:10.1016/j.jaip.2014.12.010
- Simons FER, Ardusso LRF, Bilò MB, El-Gamal YM, Ledford DK, Ring J, Sánchez-Borges M, Senna GE, Sheikh A, Thong BY. World Allergy Organization Anaphylaxis Guidelines: Summary. Journal of Allergy and Clinical Immunology. 2011;127(3):587–593.e22. — doi:10.1016/j.jaci.2011.01.038
- Platts-Mills TAE, Li RC, Keshavarz B, Smith AR, Wilson JM. Diagnosis and Management of Patients with the α-Gal Syndrome. Journal of Allergy and Clinical Immunology: In Practice. 2020;8(1):15–23.e1. — doi:10.1016/j.jaip.2019.09.017
- Wilson JM, Schuyler AJ, Workman L, Gupta M, James HR, Posthumus J, McGowan EC, Commins SP, Platts-Mills TAE. Investigation Into the α-Gal Syndrome: Characteristics of 261 Children and Adults Reporting Red Meat Allergy. Journal of Allergy and Clinical Immunology: In Practice. 2019;7(7):2348–2358.e4. — doi:10.1016/j.jaip.2019.03.031
- Hilger C, Fischer J, Wölbing F, Biedermann T. Role and Mechanism of Galactose-Alpha-1,3-Galactose in the Elicitation of Delayed Anaphylactic Reactions to Red Meat. Current Allergy and Asthma Reports. 2019;19(1):3. — doi:10.1007/s11882-019-0835-9
- Wilson JM, Erickson L, Levin M, Ailsworth SM, Commins SP, Platts-Mills TAE. Tick Bites, IgE to Galactose-α-1,3-Galactose, and Urticarial or Anaphylactic Reactions to Mammalian Meat: The Alpha-Gal Syndrome. Allergy. 2024;79(6):1440–1454. — doi:10.1111/all.16003
- Patel N, Chong KW, Yip AYG, Ierodiakonou D, Bartra J, Boyle RJ, Turner PJ. Use of Multiple Epinephrine Doses in Anaphylaxis: A Systematic Review and Meta-Analysis. Journal of Allergy and Clinical Immunology. 2021;148(5):1307–1315. — PubMed PMID: 33862009
- Shaker MS, Wallace DV, Golden DBK, Oppenheimer J, Bernstein JA, Campbell RL, Dinakar C, Ellis A, Greenhawt M, Khan DA, Lang DM, Lang ES, Lieberman JA, Portnoy J, Rank MA, Stukus DR, Wang J. Anaphylaxis — A 2020 Practice Parameter Update, Systematic Review, and Grading of Recommendations, Assessment, Development and Evaluation (GRADE) Analysis. Journal of Allergy and Clinical Immunology. 2020;145(4):1082–1123. — PubMed PMID: 32001253
- Golden DBK, Wang J, Waserman S, Akin C, Campbell RL, Ellis AK, Greenhawt M, Lang DM, Ledford DK, Lieberman J, Oppenheimer J, Shaker MS, Wallace DV, Abrams EM, Bernstein JA, Chu DK, Horner CC, Rank MA, Stukus DR. Anaphylaxis: A 2023 Practice Parameter Update. Annals of Allergy, Asthma & Immunology. 2024;132(2):124–176. — PubMed PMID: 38108678
- Shaker MS, Anagnostou A, Greenhawt M. To the ER? Can Patients Treat Their Anaphylaxis at Home? Current Allergy and Asthma Reports. 2024;24(11):623–629. — PubMed PMID: 39222197
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: Alpha-gal delayed anaphylaxis
- PubMed: Biphasic anaphylaxis
- PubMed: Epinephrine auto-injector use
- PubMed: Food-dependent exercise-induced anaphylaxis
- PubMed: Alpha-gal cofactor reactions
- PubMed: Alpha-gal nocturnal reactions
- PubMed: Alpha-gal emergency management
- PubMed: Anaphylaxis observation time in ER
Connections
- Pain & Allergy
- Tick Bite Prevention
- Cross-Reactive Medications
- Natural History and Tolerance
- Alpha-Gal Syndrome Overview
- Allergies
- Mammalian Foods List
- Tick-Origin Science
- Restaurant and Travel Survival
- Testing and Diagnosis
- Mast Cell Activation Syndrome
- Postural Orthostatic Tachycardia Syndrome
- Food Intolerance
- Asthma
- Alpha-Gal and Cardiovascular Risk
- Lyme Disease
- Hives and Flushing
- Anaphylaxis — the general condition, its diagnostic criteria, and standard emergency treatment.