Anaphylaxis
- How Anaphylaxis Works
- Most Common Triggers
- How It Feels: Recognizing an Attack
- The Biphasic Reaction
- Diagnostic Criteria
- First Response: Epinephrine
- Hospital Treatment
- Living with Anaphylaxis Risk
- Special Populations
- Complications and Prognosis
- Key Research Papers
- Connections
How Anaphylaxis Works
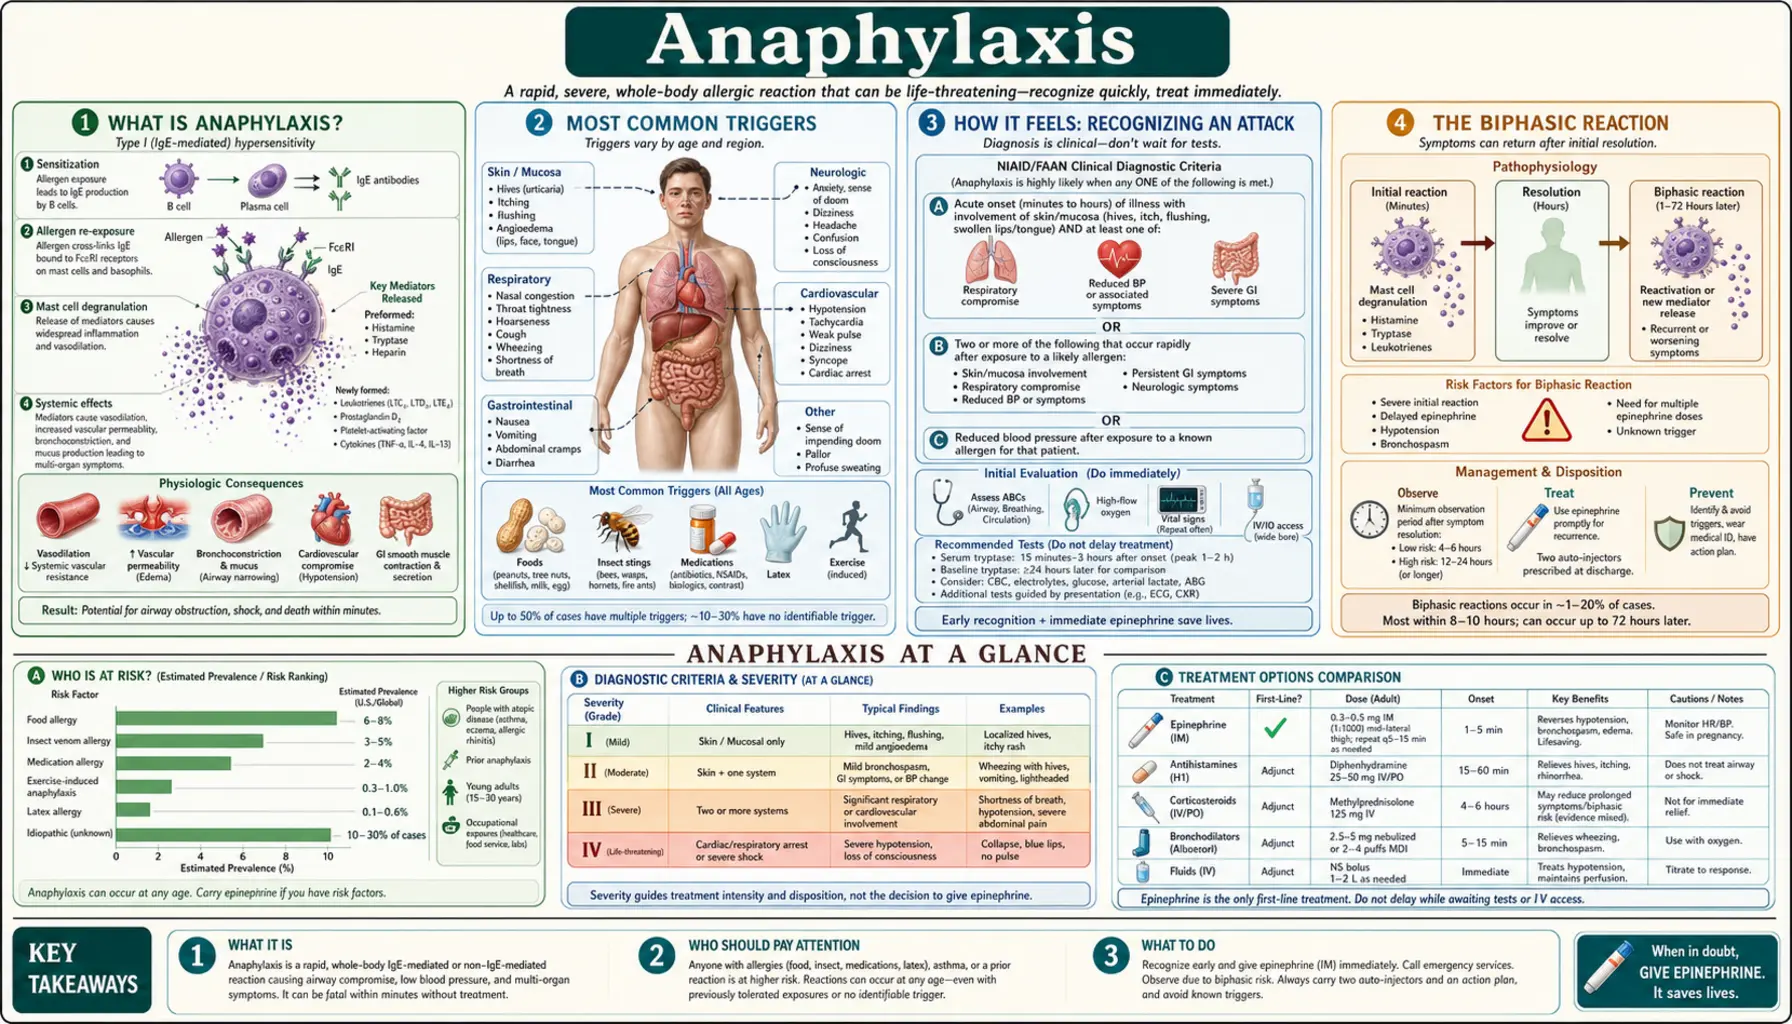
Anaphylaxis is a severe, life-threatening allergic reaction that occurs rapidly and involves multiple body systems simultaneously. It is the most extreme end of the allergic spectrum. The immune system — usually via immunoglobulin E antibodies — responds to a trigger (allergen) by releasing massive amounts of chemical mediators from mast cells and basophils: histamine, tryptase, leukotrienes, prostaglandins, platelet-activating factor. This triggers vasodilation, increased vascular permeability (fluid leaks from blood vessels), bronchoconstriction, and mucus overproduction — all at once.
Without prompt treatment, anaphylaxis can cause distributive shock, respiratory arrest, and death within minutes. A study of US death certificates counted 2,458 anaphylaxis-related deaths in the United States over the 12 years from 1999 to 2010. Medicines were the most common cause (58.8%), followed by "unspecified" triggers (19.3%), insect venom (15.2%) and food (6.7%). Deaths from drug-induced anaphylaxis rose over those years, from 0.27 to 0.51 per million people; the authors link the rise to more use of medicines and X-ray contrast dye, better diagnosis and changes in coding (Jerschow 2014). Incidence is rising, particularly food-triggered anaphylaxis in children.
Most Common Triggers
- Food (most common in children): Milk, eggs, fish, crustacean shellfish, tree nuts, peanuts, wheat, soybeans and sesame are the nine major food allergens named by US law. Sesame was added as the ninth by the FASTER Act, signed on April 23, 2021 and effective January 1, 2023 (US Food and Drug Administration); the original "Big Eight" were the ones long said to account for more than 90% of food-allergic reactions. Peanuts and tree nuts are leading causes of fatal anaphylaxis.
- Medications (most common in adults): Penicillin and related beta-lactam antibiotics; nonsteroidal anti-inflammatory drugs (NSAIDs); aspirin; angiotensin-converting enzyme inhibitors (ACE inhibitors); monoclonal antibodies; contrast dye; anesthetics; opioids.
- Insect stings: Hymenoptera venom (bees, wasps, hornets, yellow jackets, fire ants) — caused 15.2% of the 2,458 US anaphylaxis deaths recorded from 1999 to 2010; fatal venom anaphylaxis was linked to older age, male sex and white race (Jerschow 2014).
- Latex: Particularly in healthcare workers and children with spina bifida.
- Exercise-induced anaphylaxis: Rare but real; can occur with or without a food cofactor (eating wheat then exercising is a classic pattern).
- Idiopathic anaphylaxis: No identifiable trigger despite thorough evaluation; accounts for approximately 30–40% of anaphylaxis in adults.
- Alpha-gal syndrome: Delayed immunoglobulin E-mediated reaction to mammalian meat 3–6 hours after ingestion.
- Mast cell disorders: mast cell activation syndrome (MCAS) or mastocytosis amplifies severity and lowers the reaction threshold.
How It Feels: Recognizing an Attack
Anaphylaxis typically develops within seconds to minutes of allergen exposure (or up to 30 minutes for food). Early warning signs — which patients learn to recognize — include: tingling or itching in the mouth, lips, tongue, or throat; a warm flushing sensation over the skin; hives appearing suddenly; and a feeling of dread or that "something is very wrong."
As the reaction progresses, symptoms escalate: throat tightening, hoarseness, stridor (a high-pitched breathing sound); difficulty swallowing or speaking; chest tightness, wheezing; stomach cramps, nausea, vomiting; lightheadedness or feeling faint; a rapid, weak pulse; and loss of consciousness. The most dangerous signs are throat and airway swelling and cardiovascular collapse (shock). Even patients who have had prior mild reactions can experience a severe or fatal reaction on the next exposure.
The Biphasic Reaction
In 4–23% of cases (estimates vary widely), patients experience a biphasic reaction — a second wave of anaphylaxis occurring 1–72 hours after the initial reaction resolves, even without additional allergen exposure. This is why emergency department observation is recommended for 4–8 hours after apparent recovery, and why epinephrine auto-injectors come in two-packs.
Protracted anaphylaxis (lasting more than 6 hours) is a distinct and more dangerous variant requiring intensive monitoring. Risk factors for a biphasic reaction include: a severe initial reaction; delayed administration of epinephrine; and needing multiple doses of epinephrine during the initial event. Corticosteroids are commonly given to reduce biphasic risk, though the evidence for this practice is weaker than historically believed. The 2020 US anaphylaxis practice parameter states that severe anaphylaxis and the need for repeated doses of epinephrine are risk factors for a biphasic reaction, and that "Antihistamines and/or glucocorticoids are not reliable interventions to prevent biphasic anaphylaxis" (Shaker 2020).
Diagnostic Criteria
The World Allergy Organization (WAO) and NIAID/FAAN diagnostic criteria define anaphylaxis as highly likely when any one of these three criteria is met:
- Acute onset of illness (minutes to hours) with involvement of skin or mucosal tissue plus respiratory compromise or cardiovascular symptoms.
- Two or more of the following after allergen exposure: skin or mucosal symptoms; respiratory compromise; cardiovascular collapse; persistent gastrointestinal (GI) symptoms.
- Reduced blood pressure after exposure to a known allergen for that patient.
Serum tryptase level (drawn 15–180 minutes after onset) can confirm mast cell activation but is not required for clinical diagnosis. A normal tryptase does not rule out anaphylaxis — food-triggered anaphylaxis in particular often shows normal or minimally elevated tryptase.
First Response: Epinephrine
Epinephrine (adrenaline) is the only first-line treatment for anaphylaxis — all other medications are second-line adjuncts. It works by reversing vasodilation (causing vasoconstriction), reducing airway swelling (bronchodilation and decreased mucus production), and supporting cardiac function. There is no absolute contraindication to epinephrine in anaphylaxis.
Dose: 0.3–0.5 mg (adult) or 0.01 mg/kg (child, max 0.5 mg) of 1:1000 solution injected intramuscularly into the outer thigh. Epinephrine auto-injectors and prefilled syringes are pressed firmly into the outer thigh and held in place for the time given in the device instructions; they can be given through clothing. Emergency guidance describes laying the person flat with the legs raised (unless breathing is worse lying flat), calling emergency services (911 in the US) at once, and giving a second dose if there is no improvement in 5–15 minutes.
Needle-free option: In August 2024 the US Food and Drug Administration approved an epinephrine nasal spray, the first epinephrine product for anaphylaxis that is not injected, for adults and children who weigh at least 30 kg (about 66 pounds); it is also approved in Europe. In pooled studies in healthy adults, a 13.2 mg dose of the spray raised blood epinephrine levels faster and higher overall than a 0.3 mg intramuscular auto-injector, with similar effects on heart rate and blood pressure (Greenhawt 2024). Approval was based on studies in healthy adults, not in people having anaphylaxis (FDA; Pouessel 2025).
Delay in epinephrine administration is the leading cause of preventable anaphylaxis death. Antihistamines and steroids do not work fast enough to treat anaphylaxis — they are secondary measures only. The 2020 US practice parameter names epinephrine as the first-line drug for anaphylaxis, and antihistamines and steroids do not replace it.
Hospital Treatment
Emergency department care focuses on supporting the airway, breathing, and circulation while reversing the allergic cascade:
- Intravenous (IV) epinephrine infusion for refractory or cardiovascular-dominant cases
- Intravenous fluid resuscitation (1–2 liters normal saline) for anaphylactic shock
- Supplemental oxygen; nebulized albuterol for bronchospasm
- H1 antihistamines (diphenhydramine) and H2 antihistamines (famotidine) — adjuncts to reduce skin symptoms, not primary treatment
- Systemic corticosteroids (methylprednisolone or prednisone) to reduce late-phase reactions — though evidence for preventing biphasic reactions is weaker than historically believed
- Intubation or emergency cricothyrotomy for complete airway obstruction
- Glucagon (1–5 mg intravenous) for patients on beta-blockers, who have a blunted epinephrine response and may require higher doses or alternative agents
Discharge planning: The 2020 US practice parameter states that patients are kept under observation until symptoms have fully resolved, and that all patients with anaphylaxis receive education on the risk of recurrence, avoiding the trigger, using self-injectable epinephrine and when to seek further care, plus referral to an allergist. Discharge plans commonly include a prescription for two epinephrine auto-injectors and a written anaphylaxis action plan.
Living with Anaphylaxis Risk
Allergy guidance commonly advises people at risk to carry two epinephrine auto-injectors at all times — at school, work, travel, the gym. Epinephrine is stored at room temperature because heat and freezing degrade it, and devices are replaced before their expiry date. Many people wear medical alert identification (bracelet, wallet card, or digital app).
A written anaphylaxis action plan, drawn up with an allergist, is part of standard allergy care. Food-allergic people describe reading ingredient labels on every purchase, because recipes can change without obvious notice. "May contain" labeling is voluntary in the US, and cross-contact during manufacturing is a real risk that varies by facility. When dining out, many people speak directly with kitchen staff about how severe their allergy is.
Allergen immunotherapy for insect venom allergy (allergy shots) can dramatically reduce reaction severity and is curative in many patients — 97% maintain protection long-term. Peanut oral immunotherapy with a peanut allergen powder (approved by the U.S. Food and Drug Administration in 2020) was tested in the PALISADE trial in people aged 4 to 55 who reacted to 100 mg or less of peanut protein, about one third of a peanut kernel. After about 24 weeks on the 300 mg daily maintenance dose, 67.2% of children and teenagers aged 4 to 17 on the active powder could eat 600 mg or more of peanut protein without dose-limiting symptoms, compared with 4.0% on placebo. No benefit was shown in participants aged 18 or older, and more than 95% of the children had side effects during treatment, mostly mild or moderate (Vickery 2018). It does not eliminate risk and requires continued maintenance dosing.
Omalizumab for several food allergies: In a 2024 trial in 177 children and teenagers allergic to peanut plus at least two other foods, omalizumab (an anti-IgE injection given every 2 to 4 weeks) for 16 weeks let 67% eat 600 mg or more of peanut protein without a dose-limiting reaction, compared with 7% on placebo. Results were similar for cashew (41% vs 3%), milk (66% vs 10%) and egg (67% vs 0%). Apart from more injection-site reactions, safety did not differ between the groups (Wood 2024).
Special Populations
Children: Food is the dominant trigger; children are at heightened risk during school meals, birthday parties, and social events. Many schools keep epinephrine available and train staff — 47 US states now mandate school epinephrine policies. Teens are a particularly high-risk group due to risk-taking behavior and delayed epinephrine use.
Pregnant women: Anaphylaxis during pregnancy is rare but dangerous. Epinephrine remains the recommended treatment — the fetal risk from untreated maternal anaphylaxis (hypoxia, shock) far exceeds any medication risk. Maternal cardiovascular collapse reduces uteroplacental blood flow acutely.
Older adults: More likely to have underlying cardiac disease and to be taking beta-blockers (which blunt the epinephrine response and require glucagon rescue); higher latex allergy risk from repeated medical procedures; greater risk of fatal outcomes from cardiovascular compromise.
Mastocytosis and mast cell activation syndrome: Patients with systemic mastocytosis or mast cell activation syndrome have amplified anaphylaxis, lower reaction thresholds, and may require pre-medication protocols before medical procedures or surgeries. They often benefit from standing daily antihistamines and in some cases daily omalizumab.
Complications and Prognosis
With prompt epinephrine, the vast majority of anaphylaxis cases resolve fully within hours. Fatal anaphylaxis risk factors include: underlying asthma (the single most important risk factor); delayed epinephrine administration; peanut or tree nut allergy; lack of an anaphylaxis action plan; exercise as a cofactor; advanced age with cardiac comorbidity; and use of beta-blockers or angiotensin-converting enzyme inhibitors.
Psychological sequelae are common and underrecognized: anxiety, post-traumatic stress, hypervigilance about food, and fear-driven dietary restriction can significantly impair quality of life. Patients — particularly children — benefit from psychological support as part of comprehensive allergy care. Some patients develop agoraphobia or social withdrawal out of fear of exposure.
With allergen avoidance, a solid emergency action plan, and appropriate immunotherapy where indicated, most people at risk for anaphylaxis lead full, active lives. The goal is not a life lived in fear, but a life lived prepared.
Key Research Papers
- Sampson HA, Muñoz-Furlong A, Campbell RL, et al. Second symposium on the definition and management of anaphylaxis: summary report--Second National Institute of Allergy and Infectious Disease/Food Allergy and Anaphylaxis Network symposium. J Allergy Clin Immunol. 2006;117(2):391–397. — PubMed PMID: 16461139 · doi:10.1016/j.jaci.2005.12.1303
- Simons FE, Ardusso LR, Dimov V, et al. World Allergy Organization Anaphylaxis Guidelines: 2013 update of the evidence base. Int Arch Allergy Immunol. 2013;162(3):193–204. — PubMed PMID: 24008815 · doi:10.1159/000354543
- Lieberman P, et al. The diagnosis and management of anaphylaxis practice parameter: 2010 update. J Allergy Clin Immunol. 2010. — PubMed PMID: 20692689
- Shaker MS, Wallace DV, Golden DBK, et al. Anaphylaxis-a 2020 practice parameter update, systematic review, and Grading of Recommendations, Assessment, Development and Evaluation (GRADE) analysis. J Allergy Clin Immunol. 2020;145(4):1082–1123. — PubMed PMID: 32001253 · doi:10.1016/j.jaci.2020.01.017
- Ring J, Grosber M, Möhrenschlager M, Brockow K. Anaphylaxis: acute treatment and management. Chem Immunol Allergy. 2010;95:201–210. — PubMed PMID: 20519892 · doi:10.1159/000315953
- Ellis AK, Day JH. Incidence and characteristics of biphasic anaphylaxis: a prospective evaluation of 103 patients. Ann Allergy Asthma Immunol. 2007;98(1):64–69. — PubMed PMID: 17225722 · doi:10.1016/S1081-1206(10)60861-7
- Rudders SA, Banerji A, Corel B, Clark S, Camargo CA Jr. Multicenter study of repeat epinephrine treatments for food-related anaphylaxis. Pediatrics. 2010;125(4):e711–e718. — PubMed PMID: 20308215 · doi:10.1542/peds.2009-2832
- Pumphrey RS. Fatal posture in anaphylactic shock. J Allergy Clin Immunol. 2003;112(2):451–452. — PubMed PMID: 12897756 · doi:10.1067/mai.2003.1614
- Soar J, Pumphrey R, Cant A, et al. Emergency treatment of anaphylactic reactions--guidelines for healthcare providers. Resuscitation. 2008;77(2):157–169. — PubMed PMID: 18358585 · doi:10.1016/j.resuscitation.2008.02.001
- Golden DB, Kwiterovich KA, Kagey-Sobotka A, Lichtenstein LM. Discontinuing venom immunotherapy: extended observations. J Allergy Clin Immunol. 1998;101(3):298–305. — PubMed PMID: 9525443 · doi:10.1016/S0091-6749(98)70239-8
- PALISADE Group of Clinical Investigators; Vickery BP, Vereda A, Casale TB, et al. AR101 Oral Immunotherapy for Peanut Allergy. N Engl J Med. 2018;379(21):1991–2001. — PubMed PMID: 30449234 · doi:10.1056/NEJMoa1812856
- Commins SP, Satinover SM, Hosen J, et al. Delayed anaphylaxis, angioedema, or urticaria after consumption of red meat in patients with IgE antibodies specific for galactose-alpha-1,3-galactose. J Allergy Clin Immunol. 2009;123(2):426–433. — PubMed PMID: 19070355 · doi:10.1016/j.jaci.2008.10.052
- Jerschow E, Lin RY, Scaperotti MM, McGinn AP. Fatal anaphylaxis in the United States, 1999-2010: temporal patterns and demographic associations. J Allergy Clin Immunol. 2014;134(6):1318–1328.e7. — PubMed PMID: 25280385 · doi:10.1016/j.jaci.2014.08.018
- Wood RA, Togias A, Sicherer SH, et al. Omalizumab for the Treatment of Multiple Food Allergies. N Engl J Med. 2024;390(10):889–899. — PubMed PMID: 38407394 · doi:10.1056/NEJMoa2312382
- Greenhawt M, Lieberman J, Blaiss M, et al. Pharmacokinetic and Pharmacodynamic Profile of Epinephrine Nasal Spray Versus Intramuscular Epinephrine Autoinjector in Healthy Adults. J Allergy Clin Immunol Pract. 2024;12(12):3274–3282.e2. — PubMed PMID: 39395775 · doi:10.1016/j.jaip.2024.10.006
- Pouessel G, Neukirch C. Alternatives to Injectable Adrenaline for Treating Anaphylaxis. Clin Exp Allergy. 2025;55(1):36–51. — PubMed PMID: 39581195 · doi:10.1111/cea.14598
- US Food and Drug Administration. FDA Approves First Nasal Spray for Treatment of Anaphylaxis. Press announcement, August 9, 2024. — fda.gov
- US Food and Drug Administration. Food Allergies (sesame named the 9th major food allergen by the FASTER Act, effective January 1, 2023). — fda.gov
PubMed Topic Searches
Connections
- Pain & Allergy
- Anaphylaxis & the EpiPen: An Allergy Emergency — interactive animation
- Histamine, Mast Cells & Allergy — interactive animation
- Allergies
- Mast Cell Activation Syndrome
- Alpha-Gal Syndrome
- Food Intolerance
- Eosinophilic Esophagitis
- Irritable Bowel Syndrome
- Total Immunoglobulin E Testing
- Tryptase Test
- Alpha-Gal Anaphylaxis Emergency Plan — step-by-step EpiPen, 911, and ER protocol for delayed alpha-gal reactions.