⚠ Evidence warning: Clinical trials or other evidence do not support the claim that no medication reduces delirium incidence, shortens its duration or improves mortality in unselected patients. This page keeps it as a report of what people, websites or other media say.
Delirium
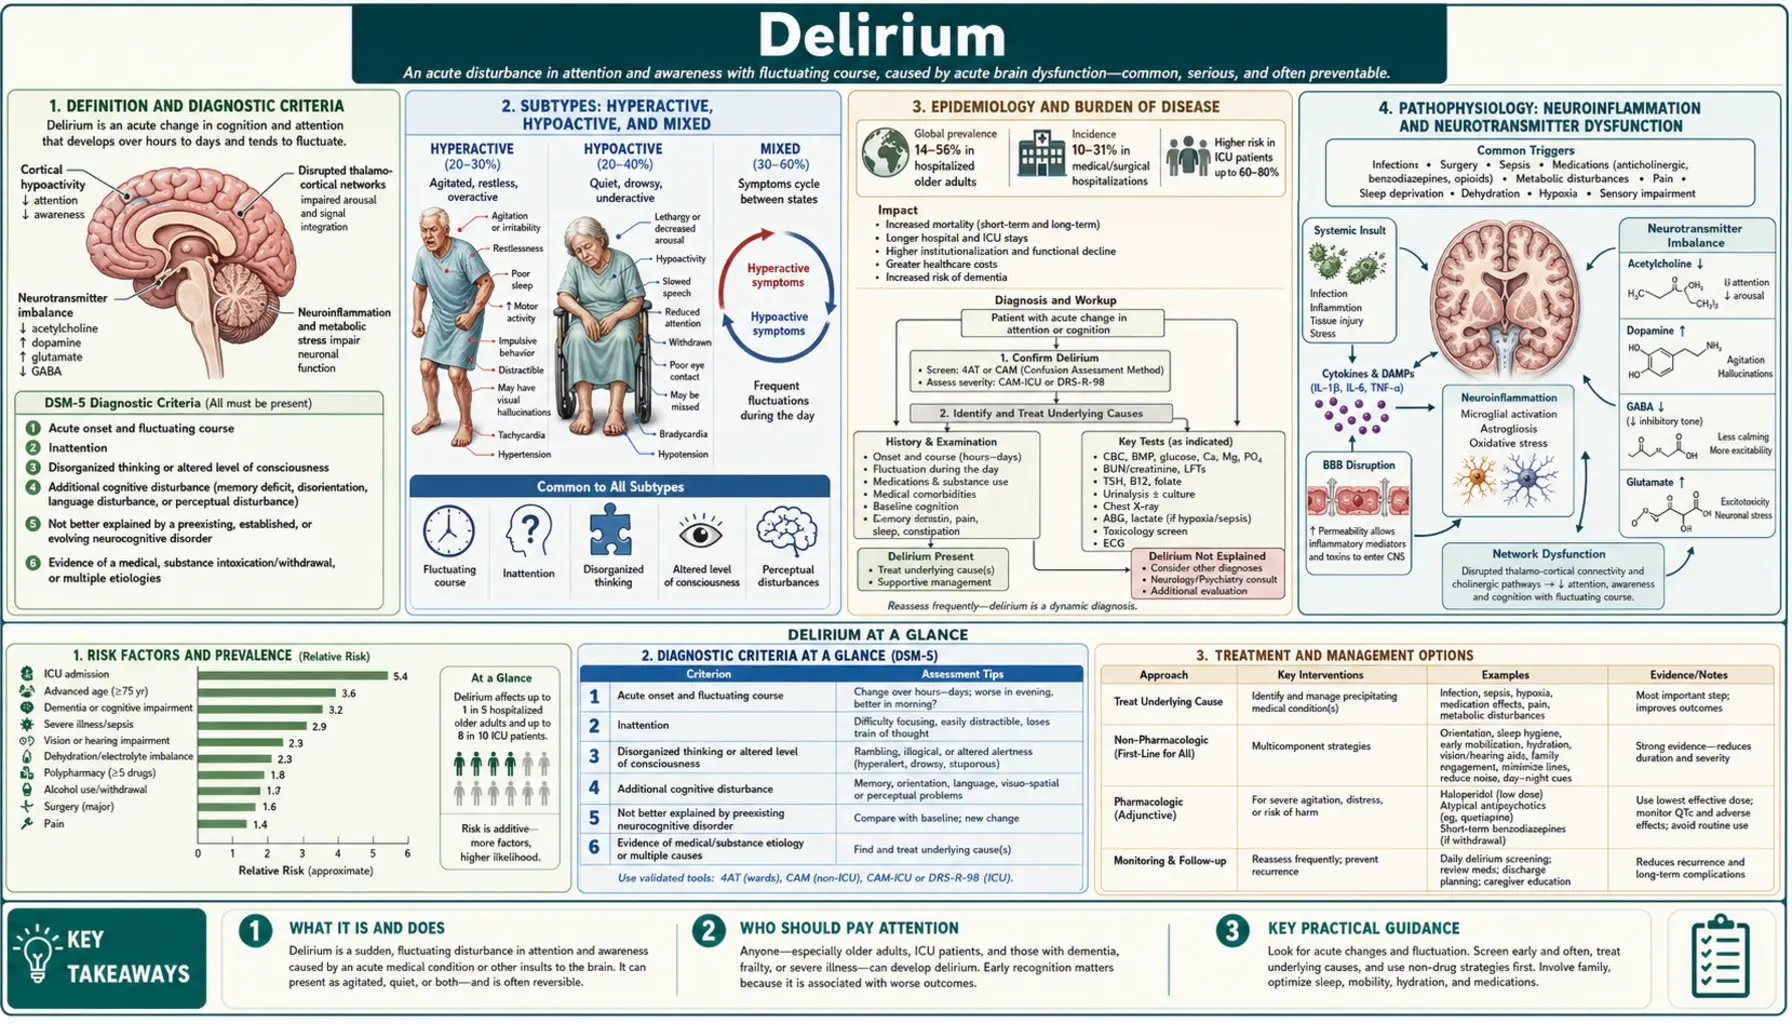
Delirium is an acute neurocognitive emergency defined by sudden-onset, fluctuating disturbances in attention, awareness, and cognition that cannot be explained by a pre-existing or evolving neurodegenerative disorder. It is one of the most common and consequential complications of hospitalization, affecting 10–30% of all admitted adults, 14–56% of intensive care unit (ICU) patients, and up to 80% of those receiving mechanical ventilation. Despite its frequency and severity — delirium independently prolongs hospital stays, accelerates cognitive decline, and increases both short- and long-term mortality — it remains dramatically underrecognized, particularly the hypoactive subtype, which is routinely mistaken for depression or simple fatigue. Understanding delirium as a brain emergency rather than an expected inconvenience of illness is the single most important shift in modern hospital medicine.
- Definition and Diagnostic Criteria
- Subtypes: Hyperactive, Hypoactive, and Mixed
- Epidemiology and Burden of Disease
- Pathophysiology: Neuroinflammation and Neurotransmitter Dysfunction
- Precipitants and Predisposing Risk Factors
- Diagnosis and Assessment Tools
- Investigations and Key Differentials
- Non-Pharmacological Management: The HELP Protocol
- Pharmacological Treatment and Special Scenarios
- Outcomes: Mortality, Cognitive Decline, and Long-Term Consequences
- Key Research Papers
- Connections
Definition and Diagnostic Criteria
The DSM-5 defines delirium by five core criteria: (1) a disturbance in attention — reduced ability to direct, focus, sustain, and shift attention — and in awareness; (2) the disturbance develops over a short period (hours to days) and tends to fluctuate during the course of a day; (3) an additional disturbance in cognition — memory deficit, disorientation, language disturbance, visuospatial ability, or perception; (4) the disturbances are not better explained by a pre-existing or evolving neurodegenerative disorder; and (5) there is evidence from the history, physical exam, or laboratory findings that the disturbance is a direct physiological consequence of a medical condition, substance intoxication or withdrawal, or medication exposure.
The defining features can be remembered with the mnemonic AIOU: Acute onset and Attention deficit, Inattention (core), Over a fluctuating course, and Underlying organic cause. The fluctuating course — characteristically worse at night ("sundowning") and transiently better with stimulation — distinguishes delirium from dementia, which is progressive and non-fluctuating. Inattention is the cardinal feature: a delirious patient cannot recite the months of the year backward, cannot track an interview topic, and will lose the thread of conversation mid-sentence.
It is essential to distinguish delirium from dementia (chronic, stable attention, no acute onset), depression (preserved attention, no disorientation, no fluctuation), and primary psychotic disorders (chronic, no fluctuating course, generally in younger patients without acute medical illness). Critically, delirium and dementia coexist in the majority of elderly patients — pre-existing dementia is the single strongest risk factor for delirium, and delirium itself accelerates underlying dementia.
Back to Table of ContentsSubtypes: Hyperactive, Hypoactive, and Mixed
Delirium is classified into three motor subtypes based on the level of psychomotor activity. Recognition of subtype is critical because only one is easy to detect at the bedside, and the others carry worse prognoses despite — or because of — going undetected.
Hyperactive delirium is the most recognizable but least common subtype, accounting for approximately 25% of cases. Patients are agitated, combative, restless, and may attempt to remove intravenous lines, catheters, or endotracheal tubes. Hallucinations — most commonly visual — are prominent. Patients may be verbally aggressive or attempt to climb out of bed. Because this subtype is impossible to ignore, it is promptly diagnosed, but it represents only a minority of the delirium burden.
Hypoactive delirium is the most common subtype (approximately 50% of cases) and the most dangerous precisely because it is most frequently missed. Patients are quiet, withdrawn, somnolent, and minimally responsive. They appear "comfortable" or "sleeping off their illness," and nurses and physicians may interpret this as appropriate rest. This subtype is most common in the elderly and in patients with pre-existing dementia. Studies show hypoactive delirium carries a worse prognosis than hyperactive delirium, likely because the underlying cause goes unaddressed for longer. It is routinely misdiagnosed as depression or fatigue. In intensive care the quiet form can dominate even more: in the MIND-USA trial's 566 intensive care patients with delirium, 89% had the hypoactive form and only 11% the hyperactive form (Girard et al., 2018).
Mixed delirium accounts for approximately 25% of cases and fluctuates between hyperactive and hypoactive features over the course of a day. A patient may be combative at 2 a.m. and minimally responsive by morning rounds. Because a single snapshot evaluation may completely mischaracterize the clinical picture, mixed delirium is reassessed at multiple time points.
Back to Table of ContentsEpidemiology and Burden of Disease
Delirium affects an estimated 7 million hospitalized Americans annually. Prevalence on general medical wards ranges from 10–30%; in surgical patients following major operations (particularly cardiac and orthopedic surgery), rates climb to 15–53%. In the intensive care unit, delirium affects 14–56% of patients overall and up to 60–80% of those receiving mechanical ventilation. Postoperative delirium is one of the most common surgical complications in patients over 65, with hip fracture repair carrying among the highest rates of any procedure.
The economic burden is enormous. Each episode of delirium is associated with increased intensive care unit and hospital length of stay, higher rates of in-hospital complications (falls, aspiration, pressure ulcers, self-extubation), increased discharge to skilled nursing or long-term care facilities rather than home, and direct mortality. A 2008 analysis of hospitalized adults aged 70 and older (Leslie et al.) put the one-year health care cost attributable to delirium at $16,303–$64,421 per patient, implying a United States national burden of $38–$152 billion each year, rivaling the health care costs of falls and diabetes.
Long-term consequences extend far beyond the hospital stay. Patients who experience delirium — even a single episode — have a significantly increased risk of subsequent dementia and accelerated cognitive decline, even after adjusting for baseline cognitive function. The relationship between delirium and dementia is bidirectional: dementia predisposes to delirium, and delirium accelerates and may directly cause dementia through neuroinflammatory injury. Hospital-acquired delirium is now recognized as a major driver of the post-intensive care syndrome (PICS), which includes persistent cognitive impairment, psychiatric morbidity, and physical debilitation lasting months to years after intensive care unit discharge.
Back to Table of ContentsPathophysiology: Neuroinflammation and Neurotransmitter Dysfunction
The pathophysiology of delirium is genuinely multifactorial, and no single unifying mechanism explains all cases. Several complementary hypotheses have substantial supporting evidence, and they converge on a common endpoint: acute widespread cortical and subcortical dysfunction impairing the neural networks that sustain attention and arousal.
The neuroinflammatory hypothesis is currently the most influential framework. Peripheral inflammatory triggers — infection, surgery, trauma, or critical illness — cause systemic release of pro-inflammatory cytokines including interleukin-1β, interleukin-6, and tumor necrosis factor-alpha. These cytokines cross or circumvent the blood-brain barrier through active transport, circumventricular organs, or barrier disruption, activating microglia and astrocytes. Neuroinflammation then disrupts the cholinergic, dopaminergic, and glutamatergic systems. A core feature of the resulting neurotransmitter imbalance is cholinergic deficiency combined with dopaminergic excess — the same pharmacological imbalance deliberately created by anticholinergic drugs, which are a major precipitant of delirium. Acetylcholine plays a central role in maintaining cortical arousal and attentional networks; its deficiency impairs these systems acutely.
The oxidative stress and mitochondrial dysfunction hypothesis proposes that acute illness, hypoxia, and metabolic derangements impair neuronal aerobic metabolism, increasing reactive oxygen species, disrupting neurotransmitter synthesis, and triggering synaptic failure. This hypothesis explains why metabolic derangements (hypoxia, uremia, hyponatremia, hypoglycemia) are such powerful delirium precipitants. Genetic factors also play a role: polymorphisms in genes involved in inflammatory signaling, cholinergic neurotransmission, and apolipoprotein E (APOE-ε4 genotype) confer increased susceptibility to delirium.
Back to Table of ContentsPrecipitants and Predisposing Risk Factors
Delirium is best understood as a two-hit phenomenon: predisposing vulnerabilities lower the threshold for delirium, while precipitating insults trigger it. Both components matter for prevention and treatment.
Predisposing (baseline) risk factors include: advanced age (the single most important predisposing factor); pre-existing dementia or cognitive impairment (increases delirium risk 2–5 fold); functional impairment and dependence in activities of daily living; vision or hearing impairment; dehydration at baseline; and prior episodes of delirium. These factors reduce the brain's reserve, so that even minor precipitants can trigger delirium in vulnerable patients.
Precipitating factors include the common mnemonic triggers — infection (most common: urinary tract infection, pneumonia, sepsis), medications, metabolic derangements, and environmental factors:
- Infection and sepsis: The most common precipitant. Any infection can cause delirium in vulnerable patients, and delirium may be the only presenting sign of sepsis in the elderly.
- Medications (Beers Criteria drugs): Anticholinergics (diphenhydramine, promethazine, tricyclic antidepressants, bladder antimuscarinics, scopolamine), benzodiazepines, opioids, corticosteroids, and polypharmacy (≥5 medications) are major precipitants. Because medicines are such common triggers, the standard delirium workup includes a review of every medication the person takes.
- Metabolic derangements: Hyponatremia or hypernatremia, uremia, hepatic encephalopathy, hypoglycemia or hyperglycemia, hypothyroidism or hyperthyroidism, hypercalcemia, and hypoxia or hypercapnia.
- Pain and urinary retention: Uncontrolled pain and the discomfort of urinary retention are underrecognized precipitants that respond to simple interventions.
- Constipation and fecal impaction: Particularly in elderly patients, severe constipation can precipitate delirium.
- Sensory deprivation: Absence of glasses, hearing aids, or familiar stimuli in an unfamiliar hospital environment profoundly impairs the brain's ability to orient.
- Sleep deprivation and disruption: intensive care unit environments with continuous lighting, noise, and frequent nighttime interventions are powerful precipitants.
- Immobility: Prolonged bed rest and restraint use (physical or chemical) independently worsen and prolong delirium.
Diagnosis and Assessment Tools
Delirium is a clinical diagnosis. No laboratory test or imaging finding is pathognomonic; the diagnosis rests on recognizing the characteristic clinical features — acute onset, fluctuating course, inattention, and altered cognition — and applying validated assessment tools.
The Confusion Assessment Method (CAM), developed by Inouye and colleagues in 1990, is the gold standard bedside delirium screening tool with sensitivity of 94–100% and specificity of 90–95%. The CAM algorithm requires: (1) acute onset and fluctuating course (and) (2) inattention (and either) (3) disorganized thinking (or) (4) altered level of consciousness. All four features are assessed; delirium is diagnosed if features 1 and 2 are present, plus either feature 3 or 4. A common error is diagnosing delirium based only on altered consciousness without confirming inattention and fluctuation.
The CAM-ICU is a validated adaptation for use in intubated patients who cannot speak. It assesses the same four features using nonverbal tasks — for example, inattention is assessed by squeezing the examiner's hand only when the letter "A" is said in a sequence of letters recited aloud. The CAM-ICU has sensitivity of 76–96% and specificity of 72–96% across validation studies and is the standard tool recommended by the Society of Critical Care Medicine's PADIS guidelines.
The 3-Minute Diagnostic Interview for CAM-Defined Delirium (3D-CAM) and the brief CAM (bCAM) are validated short-form instruments suitable for non-ICU settings where formal delirium screening by nursing or medical staff takes only a few minutes. The Glasgow Coma Scale (GCS) alone is insufficient for diagnosing delirium because it captures level of consciousness but not inattention or cognitive quality.
Back to Table of ContentsInvestigations and Key Differentials
Investigation in delirium serves two purposes: identifying the underlying cause(s) and excluding critical mimics. The investigation is broad because delirium is a syndrome, not a diagnosis, and the underlying cause is frequently multifactorial.
Standard workup includes: complete blood count (CBC) for infection, anemia; basic metabolic panel (BMP) for sodium, potassium, glucose, renal function, bicarbonate; liver function tests (LFTs) for hepatic encephalopathy; thyroid-stimulating hormone (TSH) for thyroid dysfunction; urinalysis and urine culture; blood cultures if infection is suspected; oxygen saturation and arterial blood gas if hypoxia or hypercapnia is possible; and a thorough medication review. Chest imaging, urine toxicology, and blood alcohol level are added based on clinical context. A brain computed tomography (CT) scan is indicated if there is new focal neurological deficit, history of head trauma, fever and nuchal rigidity suggesting meningitis, or first-episode delirium in a young patient without a clear cause.
Critical differentials that hospitals work to rule out include: non-convulsive status epilepticus (NCSE) — an electroencephalogram (EEG) is used when delirium is unexplained or unusually prolonged, because NCSE can mimic delirium and is treatable; Wernicke's encephalopathy — in malnourished or alcohol-dependent patients, standard hospital practice is to give intravenous thiamine (vitamin B1) before glucose; autoimmune encephalitis (anti-NMDAR, anti-LGI1, anti-CASPR2) — considered in subacute delirium with psychiatric features, new-onset seizures, or autonomic instability, especially in younger patients; and meningitis or encephalitis — lumbar puncture (spinal tap) is used when fever plus delirium plus any meningeal sign is present.
Back to Table of ContentsNon-Pharmacological Management: The HELP Protocol
Non-pharmacological interventions are first-line for both prevention and treatment of delirium. Multiple randomized controlled trials demonstrate that multicomponent non-pharmacological protocols reduce delirium incidence by 30–40% in high-risk hospitalized patients. The most rigorously studied program is the Hospital Elder Life Program (HELP), developed by Inouye and colleagues at Yale.
HELP targets six primary delirium risk factors with the following interventions:
- Cognitive impairment: Reorientation (orientation board with date, location, care team names), cognitive activities (word games, reminiscing), provision of familiar stimuli (family photos, favorite music, personal items from home).
- Sleep deprivation: Non-pharmacological sleep protocol — warm milk or herbal tea at bedtime, relaxation music, back massage, noise-reduction strategies (earplugs, staff education about nighttime noise), clustering of nighttime care to minimize disruptions.
- Immobility: Early mobilization — walking three times daily, or active range-of-motion exercises for patients unable to walk; less time in bed and no restraints, which worsen agitation and immobility.
- Visual impairment: Glasses kept at the bedside and worn; magnifying lenses when needed; adequate lighting.
- Hearing impairment: Portable amplifying devices; hearing aids in place and working; less background noise.
- Dehydration: Early recognition and treatment; encouragement to drink; removal of unnecessary fluid restrictions.
The ABCDEF bundle (Assess, prevent and manage pain; Both spontaneous awakening trials (SAT) and spontaneous breathing trials (SBT); Choice of analgesia and sedation; Delirium monitoring and management; Early mobility; Family engagement and empowerment) is the intensive care unit equivalent and is recommended by the Society of Critical Care Medicine. Family presence and engagement, in particular, has a strong effect on delirium prevention and treatment in the intensive care unit by providing familiar stimuli and reorientation.
Back to Table of ContentsPharmacological Treatment and Special Scenarios
In hospital practice, medicines for delirium are generally kept for agitation that poses an immediate safety risk to the patient or staff, after non-drug measures have been tried. No medication reduces delirium incidence, shortens duration, or improves mortality outcomes in unselected patients. Large placebo-controlled trials in intensive care found that antipsychotic drugs did not shorten delirium. In the MIND-USA trial (Girard et al., 2018, NEJM), 566 intensive care patients with delirium received intravenous haloperidol, ziprasidone or placebo: the median days alive without delirium or coma were 8.5 with placebo, 7.9 with haloperidol and 8.7 with ziprasidone, with no difference in 30-day or 90-day survival. The earlier, smaller MIND pilot trial (Girard et al., 2010; 101 ventilated patients) had also found no improvement in days alive without delirium or coma.
The 2022 AID-ICU trial (Andersen-Ranberg et al., NEJM) gave intravenous haloperidol (2.5 mg three times daily plus 2.5 mg as needed, up to 20 mg a day) or placebo to 1,000 intensive care patients with delirium. Days alive and out of hospital at 90 days did not differ significantly (35.8 with haloperidol vs 32.9 with placebo, P = 0.22). Deaths at 90 days were 36.3% with haloperidol and 43.3% with placebo; this was a secondary result, not the trial's main outcome.
The Society of Critical Care Medicine's 2025 focused guideline update (Lewis et al.) made conditional recommendations, for adults in intensive care, to use dexmedetomidine rather than propofol for sedation, to provide enhanced mobilization and rehabilitation rather than usual mobilization, and to give melatonin. The panel was unable to issue a recommendation for or against antipsychotics to treat delirium.
Antipsychotics are the most commonly used agents for agitation management. Haloperidol is the most studied agent; low doses (0.5–1 mg into a vein or by intramuscular injection, repeated every 4 hours as needed) are commonly used in hospital practice. Quetiapine (25–50 mg orally twice daily) and olanzapine are alternatives with sedating properties useful in specific contexts. All antipsychotics carry risks of QTc prolongation (a heart-rhythm change seen on the electrocardiogram), extrapyramidal side effects (stiffness, tremor, restlessness), and — in patients with dementia — increased stroke and mortality risk (black box warning). Prescribing guidance describes the lowest effective dose for the shortest time, tapered and stopped once agitation resolves.
Dexmedetomidine, a selective alpha-2 agonist, is commonly chosen for managing hyperactive delirium in mechanically ventilated intensive care unit patients because it provides sedation without worsening delirium by the mechanism of benzodiazepines. Multiple trials demonstrate lower delirium incidence and shorter time to extubation with dexmedetomidine versus benzodiazepine-based sedation.
Benzodiazepines worsen most delirium — they do so by enhancing GABAergic inhibition (the brain's main calming signal) and impairing cholinergic neurotransmission. The critical exception is alcohol withdrawal delirium (delirium tremens), where benzodiazepines are the first-line and potentially life-saving treatment. Delirium tremens typically begins 24–72 hours after the last drink, features autonomic hyperactivity (tachycardia, hypertension, diaphoresis, fever) and seizures, and carries up to 5% mortality if untreated. The CIWA-Ar (Clinical Institute Withdrawal Assessment for Alcohol) protocol guides benzodiazepine dosing in this specific scenario.
Back to Table of ContentsOutcomes: Mortality, Cognitive Decline, and Long-Term Consequences
Delirium is an independent predictor of adverse outcomes even after controlling for severity of illness, pre-existing dementia, and comorbidities. In-hospital delirium is associated with a 2–5 fold increase in mortality during hospitalization, an approximately 2-fold increase in 1-year mortality, and significantly increased rates of discharge to nursing home rather than home. In the intensive care unit, more days of delirium go with a higher risk of death. In 354 lightly sedated, ventilated intensive care patients (Shehabi et al., 2010), 30.3% of those with delirium died within 30 days, against 11.9% of those without. Compared with no delirium, the risk of death within 30 days was 1.70 times higher after 1 day of delirium, 2.69 times after 2 days and 3.37 times after 3 or more days, even after adjusting for other factors; the rise was steepest in the first days of delirium.
Perhaps the most clinically important but underappreciated long-term consequence is accelerated cognitive decline. The BRAIN-ICU study (Pandharipande et al., NEJM 2013) demonstrated that 3-month and 12-month cognitive impairment in intensive care unit survivors — measured by standard neuropsychological testing — was linearly associated with the number of days spent delirious during the intensive care unit stay, even in patients with no prior cognitive impairment. The severity of cognitive impairment in many survivors resembled that of mild-to-moderate Alzheimer's disease.
Delirium prevention through multicomponent non-pharmacological programs, early mobility, optimization of sedation, and treatment of precipitants remains the most impactful intervention. When delirium does occur, prompt identification of the underlying cause and early non-pharmacological management reduce its duration and mitigate long-term consequences. Systematic delirium screening using validated tools (CAM, CAM-ICU) at least once per shift in high-risk patients transforms delirium from a hidden complication to a recognized, addressable medical problem.
Back to Table of ContentsKey Research Papers
- Inouye SK, van Dyck CH, Alessi CA, et al. Clarifying confusion: The Confusion Assessment Method. A new method for detection of delirium. Ann Intern Med. 1990;113(12):941–948. — PubMed PMID: 2240918 — Development and validation of the CAM instrument (sensitivity 94–100%, specificity 90–95%); the foundational diagnostic tool for delirium.
- Inouye SK, Bogardus ST Jr, Charpentier PA, et al. A multicomponent intervention to prevent delirium in hospitalized older patients. N Engl J Med. 1999;340(9):669–676. — PubMed PMID: 10053175 — Landmark RCT of the HELP protocol; 40% relative risk reduction in incident delirium.
- Ely EW, Inouye SK, Bernard GR, et al. Delirium in mechanically ventilated patients: Validity and reliability of the Confusion Assessment Method for the Intensive Care Unit (CAM-ICU). JAMA. 2001;286(21):2703–2710. — PubMed PMID: 11730446 — Validated the CAM-ICU for nonverbal ICU patients; the two study nurses had sensitivities of 100% and 93% and specificities of 98% and 100%.
- Pandharipande PP, Girard TD, Jackson JC, et al. Long-term cognitive impairment after critical illness. N Engl J Med. 2013;369(14):1306–1316. — PubMed PMID: 24088092 — BRAIN-ICU study: delirium duration linearly predicted 3- and 12-month cognitive impairment resembling dementia in ICU survivors.
- Girard TD, Exline MC, Carson SS, et al.; MIND-USA Investigators. Haloperidol and Ziprasidone for Treatment of Delirium in Critical Illness. N Engl J Med. 2018;379(26):2506–2516. — PubMed PMID: 30346242 — MIND-USA trial: in 566 ICU patients, neither haloperidol nor ziprasidone changed days alive without delirium or coma, or 30- and 90-day survival, versus placebo.
- Girard TD, Pandharipande PP, Carson SS, et al.; MIND Trial Investigators. Feasibility, efficacy, and safety of antipsychotics for intensive care unit delirium: the MIND randomized, placebo-controlled trial. Crit Care Med. 2010;38(2):428–437. — PubMed PMID: 20095068
- Andersen-Ranberg NC, Poulsen LM, Perner A, et al.; AID-ICU Trial Group. Haloperidol for the Treatment of Delirium in ICU Patients. N Engl J Med. 2022;387(26):2425–2435. — PubMed PMID: 36286254
- Devlin JW, Skrobik Y, Gélinas C, et al. Clinical Practice Guidelines for the Prevention and Management of Pain, Agitation/Sedation, Delirium, Immobility, and Sleep Disruption in Adult Patients in the ICU. Crit Care Med. 2018;46(9):e825–e873. — PubMed PMID: 30113379 — Society of Critical Care Medicine PADIS guidelines; comprehensive evidence-based framework for ICU delirium prevention.
- Lewis K, Balas MC, Stollings JL, et al. A Focused Update to the Clinical Practice Guidelines for the Prevention and Management of Pain, Anxiety, Agitation/Sedation, Delirium, Immobility, and Sleep Disruption in Adult Patients in the ICU. Crit Care Med. 2025;53(3):e711–e727. — PubMed PMID: 39982143
- Shehabi Y, Riker RR, Bokesch PM, et al. Delirium duration and mortality in lightly sedated, mechanically ventilated intensive care patients. Crit Care Med. 2010;38(12):2311–2318. — PubMed PMID: 20838332 — Compared with no delirium, 30-day death risk rose with 1 day (hazard ratio 1.70), 2 days (2.69) and 3 or more days (3.37) of delirium.
- van den Boogaard M, Schoonhoven L, Evers AW, et al. Delirium in critically ill patients: Impact on long-term health-related quality of life and cognitive functioning. Crit Care Med. 2012;40(1):112–118. — PubMed PMID: 21926597 — About 18 months after ICU discharge, survivors who had been delirious reported similar health-related quality of life after adjustment, but significantly more cognitive problems.
- Riker RR, Shehabi Y, Bokesch PM, et al. Dexmedetomidine vs Midazolam for Sedation of Critically Ill Patients: A Randomized Trial. JAMA. 2009;301(5):489–499. — PubMed PMID: 19188334 — SEDCOM trial: dexmedetomidine reduced delirium prevalence and time to extubation vs. midazolam in ICU patients.
- Fong TG, Davis D, Growdon ME, Albuquerque A, Inouye SK. The interface between delirium and dementia in elderly adults. Lancet Neurol. 2015;14(8):823–832. — PubMed PMID: 26139023 — Comprehensive review of bidirectional delirium-dementia relationship; shared pathophysiology and long-term cognitive consequences.
- Marcantonio ER, Flacker JM, Wright RJ, Resnick NM. Reducing delirium after hip fracture: A randomized trial. J Am Geriatr Soc. 2001;49(5):516–522. — PubMed PMID: 11380742 — Geriatric consultation lowered delirium from 50% to 32% (relative risk 0.64) and severe delirium from 29% to 12% (relative risk 0.40, a cut of about 60%) after hip fracture repair.
- Inouye SK, Westendorp RG, Saczynski JS. Delirium in elderly people. Lancet. 2014;383(9920):911–922. — PubMed PMID: 23992774 — Landmark comprehensive review of delirium epidemiology, pathophysiology, prevention, and treatment; essential reference.
- Leslie DL, Marcantonio ER, Zhang Y, Leo-Summers L, Inouye SK. One-year health care costs associated with delirium in the elderly population. Arch Intern Med. 2008;168(1):27–32. — PubMed PMID: 18195192