Soft Plaque and Coronary Artery Calcium (CAC) Zero: When a Calcium Score of Zero Isn't a Free Pass
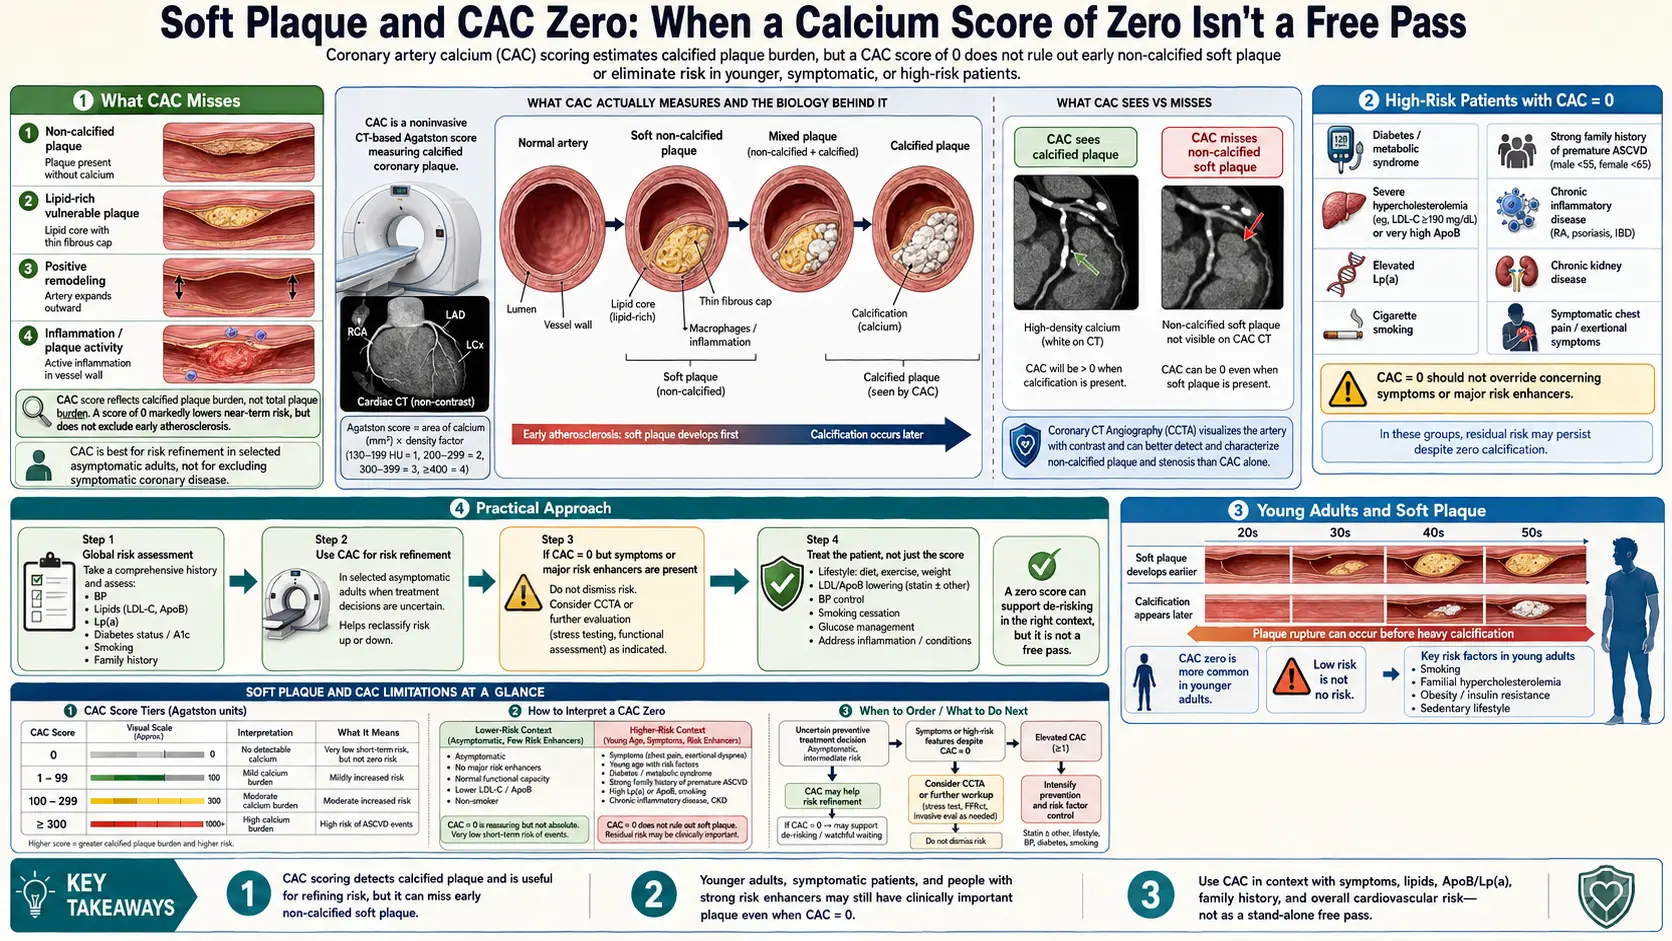
The coronary calcium score has a real blind spot: non-calcified plaque. By design, the coronary artery calcium (CAC) scan only detects calcified material above 130 Hounsfield Units. Mature, stable atherosclerotic plaques are calcified and show up. But early atherosclerotic lesions, the lipid-rich "vulnerable" plaques most prone to rupture, and the soft components within mixed plaques are invisible on a non-contrast coronary artery calcium scan. For most middle-aged and older adults this blind spot is small — calcified plaque correlates well enough with total plaque burden to make coronary artery calcium clinically useful. But there are specific populations where the blind spot matters and a calcium score of zero can mislead.
Table of Contents
- What Coronary Artery Calcium Misses
- Vulnerable Plaque
- "Coronary Artery Calcium-Zero Myocardial Infarction"
- High-Risk Patients with Coronary Artery Calcium = 0
- CCTA as a Complement to Coronary Artery Calcium
- Young Adults and Soft Plaque
- Elevated Lp(a) and Soft Plaque
- Familial Hypercholesterolemia
- Practical Approach
- Key Research Papers
- Connections
- Featured Videos
What Coronary Artery Calcium Misses
Atherosclerosis progresses through stages, and coronary artery calcium is sensitive to the late stages but not the early ones:
- Endothelial dysfunction — the earliest stage; not visible on any imaging modality
- Lipid accumulation in the artery wall — foam cells, fatty streaks; invisible on coronary artery calcium
- Soft plaque formation — lipid-rich core with thin fibrous cap; invisible on coronary artery calcium, visible on CCTA
- Mixed plaque — partial calcification of soft plaque; partly visible on coronary artery calcium
- Mature calcified plaque — stable, dense calcification; clearly visible on coronary artery calcium
Coronary artery calcium catches stages 4 and 5 reliably. Stages 1–3 are the soft-plaque blind spot. The good news: stages 4 and 5 are when most clinical events occur in the population, which is why coronary artery calcium is such a powerful risk-stratification tool. The bad news: stages 1–3 are when the lipid-rich, vulnerable plaque most prone to acute rupture exists in greatest concentration.
Vulnerable Plaque
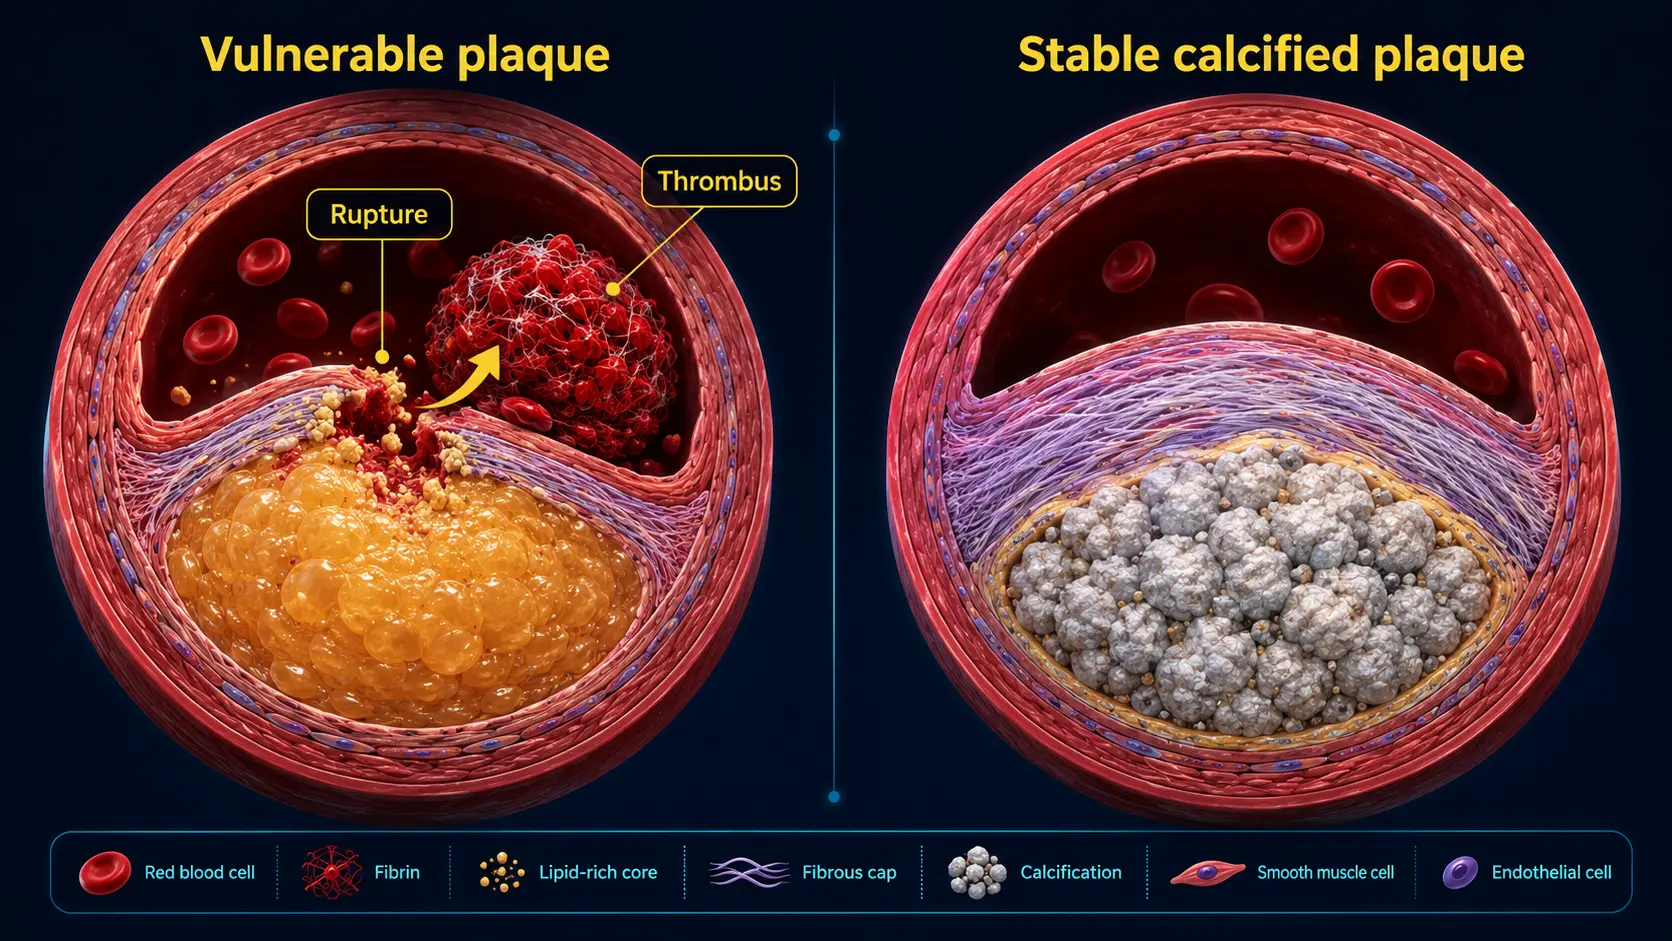
The acute coronary syndromes — STEMI, NSTEMI, unstable angina — are caused predominantly by plaque rupture, not by progressive narrowing. The plaque most likely to rupture has these features:
- Large lipid-rich core
- Thin fibrous cap (<65 µm)
- Macrophage-rich infiltrate
- Sparse smooth muscle cells
- Minimal calcification — calcification is a stabilization process
This is why high-density calcified plaque on a follow-up coronary artery calcium after years of statin therapy is reassuring, while soft plaque on CCTA is worrying: density tracks stability. The Agatston score's density factor weights stable plaque higher, by design.
"Coronary Artery Calcium-Zero Myocardial Infarction"
The "coronary artery calcium-zero myocardial infarction (MI)" is the rare but real phenomenon of a patient suffering an acute coronary event with a normal calcium score. Studies suggest 1–3% of MIs occur in patients with coronary artery calcium = 0. Common patterns:
- Younger patients (under 50) — not enough time for calcification, but soft plaque present
- Heavy smokers — pro-thrombotic and pro-rupture independent of plaque burden
- Cocaine users — vasospasm and pro-thrombotic
- Spontaneous coronary artery dissection (SCAD) — particularly in women, peripartum
- Coronary spasm — vasospastic angina (Prinzmetal)
- Microvascular disease — especially in diabetic patients
- Familial hypercholesterolemia — soft plaque develops early
- Markedly elevated Lp(a) — pro-thrombotic, pro-inflammatory effects independent of total plaque burden
- Connective tissue or autoimmune disease — systemic lupus erythematosus (SLE), RA accelerate plaque rupture
The clinical history matters more than the test result in identifying these patients. Symptoms always override imaging.
High-Risk Patients with Coronary Artery Calcium = 0
Specific scenarios where a coronary artery calcium = 0 result should not provide complete reassurance:
- Symptomatic patient with chest pain — coronary artery calcium = 0 does not exclude soft-plaque-mediated ischemia or non-atherosclerotic causes; further workup (CCTA or stress test) needed
- Family history of premature coronary artery disease (CAD) with FH or markedly elevated Lp(a) — consider CCTA
- Active smoker, especially with other risk factors — coronary artery calcium = 0 does not negate smoking-driven event risk
- Connective tissue disease, especially systemic lupus erythematosus — consider CCTA in younger patients
- Newly diagnosed type 2 diabetes — coronary artery calcium = 0 reassuring but follow-up sooner than usual
CCTA as a Complement to Coronary Artery Calcium
Computed tomography (CT) coronary angiography (CCTA) addresses the soft-plaque blind spot directly. With intravenous (IV) iodinated contrast and gated cardiac CT, CCTA visualizes both calcified and non-calcified plaque, vessel lumen geometry, and (with FFR-CT) the functional impact of stenoses.
When CCTA adds meaningful information beyond coronary artery calcium:
- Symptomatic patients regardless of coronary artery calcium result
- Asymptomatic patients with strong family history of premature coronary artery disease and coronary artery calcium = 0 (rule out soft plaque)
- Asymptomatic patients with markedly elevated Lp(a) or FH with coronary artery calcium = 0
- Following up an unexpectedly low coronary artery calcium score that conflicts with clinical risk picture
- One-time anatomic snapshot in patients with rapid risk-factor evolution (new diabetes, sustained dyslipidemia)
Trade-offs: higher cost ($500–$2,000 vs $99–$200), higher radiation (3–10 mSv vs 1 mSv), need for intravenous contrast and beta-blockade, and longer scan time. CCTA is generally not appropriate as a first-line screening test in low-to-intermediate risk asymptomatic adults — coronary artery calcium remains the right starting point in that population.
Young Adults and Soft Plaque
In adults under 40, atherosclerosis is often soft plaque only — calcification has not had time to develop. A coronary artery calcium = 0 in a 30-year-old with strong family history may be falsely reassuring. The case for additional evaluation in young adults:
- Family history of premature coronary artery disease (male first-degree relative < 55, female < 65)
- Markedly elevated Lp(a) (> 100 nmol/L or > 50 mg/dL)
- Familial hypercholesterolemia (low-density lipoprotein cholesterol (LDL-C) > 190 mg/dL or genetically confirmed)
- Symptoms suggestive of cardiac etiology
For these patients, a complete picture often requires lipid markers (ApoB, Lp(a)), genetic testing where appropriate, and consideration of CCTA. CAC alone is not sufficient.
Elevated Lp(a) and Soft Plaque
Lipoprotein(a) is a genetically determined low-density lipoprotein-like particle linked to apolipoprotein(a). Elevated Lp(a) is associated with:
- Increased pro-thrombotic activity (apolipoprotein(a) shares structural homology with plasminogen)
- Inflammatory and oxidative effects on the arterial wall
- Accelerated atherosclerosis even at "normal" low-density lipoprotein cholesterol
- Calcific aortic valve stenosis in older age
- An event-rate increase even at low coronary artery calcium scores
Patients with markedly elevated Lp(a) (above 100 nmol/L or 50 mg/dL) may have normal or low coronary artery calcium scores yet substantial soft-plaque burden. CCTA may be warranted, and lipid management should be aggressive (low-density lipoprotein cholesterol targets below standard population goals).
Familial Hypercholesterolemia
Familial hypercholesterolemia is a genetic disorder (typically LDLR, APOB, or PCSK9 mutations) causing severely elevated low-density lipoprotein cholesterol from birth. FH patients develop atherosclerosis decades earlier than the general population, often with substantial soft-plaque burden by their 30s. Coronary artery calcium scoring in FH:
- Detects calcified plaque progression earlier than non-FH controls
- Underestimates total burden because soft plaque dominates in younger FH patients
- Should be combined with CCTA evaluation in young or symptomatic FH patients
- Should not be used to defer therapy — FH patients need lifelong intensive lipid-lowering regardless of imaging
Practical Approach
For the typical asymptomatic middle-aged adult:
- Lipid panel, ApoB, Lp(a) once
- ASCVD risk calculation
- Coronary artery calcium if intermediate risk or family history
- Manage based on integrated picture
For the high-risk asymptomatic patient (FH, markedly elevated Lp(a), strong premature coronary artery disease family history):
- Lipid panel, ApoB, Lp(a) once
- Comprehensive risk assessment
- Coronary artery calcium scoring
- If coronary artery calcium > 0, manage as appropriate
- If coronary artery calcium = 0 but high baseline genetic/lipid risk: consider CCTA to rule out soft plaque
- Manage aggressively regardless of imaging if FH or high Lp(a)
For the symptomatic patient at any age: coronary artery calcium alone is not the right test — CCTA, stress test, or invasive evaluation as clinically indicated. See the coronary artery calcium vs Other Tests page.
Key Research Papers
Connections
- All Lab Tests
- Coronary Calcium Score
- Coronary Artery Calcium vs Other Cardiac Tests
- Agatston Score Calculation and Interpretation
- ApoB
- Coronary Artery Calcium Zero and the Power of Negative Result
- Coronary Artery Calcium in Women and Younger Adults
- Statin Threshold and Coronary Artery Calcium
- MESA Risk Calculator and Age Percentiles
- Reversal Plaque Stabilization and Lifestyle
- Lipoprotein(a)
- Lipid Panel
- Atherosclerosis
- Chest Pain
- Full Body Magnetic Resonance Imaging
- Insurance Cost and Access